
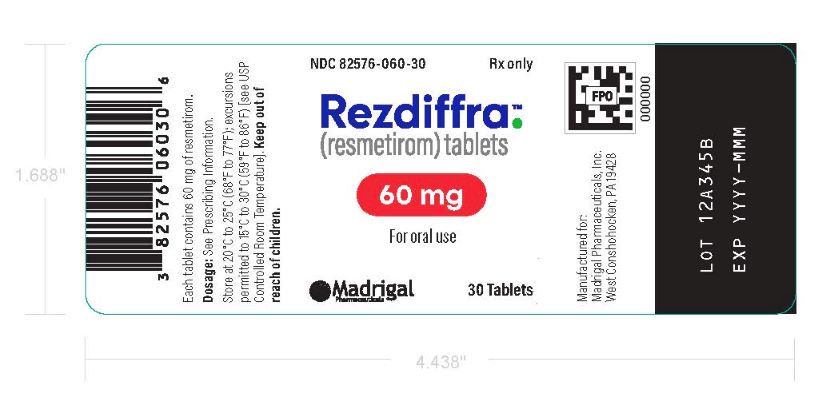
REZDIFFRA Resmetirom 60 mg Tablet, Coated, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Thyroid Hormone Receptor beta Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Resmetirom is used for treatment of patients with nonalcoholic steatohepatitis (NASH; liver inflammation and damage caused by buildup of fat in the liver). Resmetirom is in a class of medications called thyroid hormone receptor (THR)-beta agonists. It works by keeping the liver from forming fat.
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Resmetirom — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $137.31 | $4,119.29 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $141.80 | $4,253.93 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Rezdiffra 60 mgthis 82576-0060-30 | Madrigal | 30 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 11986481 ↗ | Method of use | U-3861 | Sep 17, 2033 |
| US 11986481 ↗ | Method of use | U-3861 | Sep 17, 2033 |
| US 11986481 ↗ | Method of use | U-3861 | Sep 17, 2033 |
| US 11564926 ↗ | Drug substance | U-3861 | Sep 17, 2033 |
| US 11564926 ↗ | Drug substance | U-3861 | Sep 17, 2033 |
| US 11564926 ↗ | Drug substance | U-3861 | Sep 17, 2033 |
| US 10376517 ↗ | Method of use | U-3861 | Sep 17, 2033 |
| US 10376517 ↗ | Method of use | U-3861 | Sep 17, 2033 |
| US 10376517 ↗ | Method of use | U-3861 | Sep 17, 2033 |
| US 12377104 ↗ | Method of use | U-3861 | Feb 4, 2045 |
| US 12377104 ↗ | Method of use | U-3861 | Feb 4, 2045 |
| US 12667575 ↗ | Method of use | U-4567 | Feb 4, 2045 |
| US 12667575 ↗ | Method of use | U-4567 | Feb 4, 2045 |
| US 12661359 ↗ | Method of use | U-4568 | Jan 28, 2042 |
| US 12661359 ↗ | Method of use | U-4568 | Jan 28, 2042 |
| US 12661359 ↗ | Method of use | U-4568 | Jan 28, 2042 |
| US 9266861 ↗ | Drug substance | — | Sep 17, 2033 |
| US 7452882 ↗ | Drug substance | — | Sep 12, 2027 |
| US 7452882 ↗ | Drug substance | — | Sep 12, 2027 |
| US 7452882 ↗ | Drug substance | — | Sep 12, 2027 |
| US 9266861 ↗ | Drug substance | — | Sep 17, 2033 |
| US 9266861 ↗ | Drug substance | — | Sep 17, 2033 |
| Code | What it grants | Expires |
|---|---|---|
| NCE | New Chemical Entity (5-year) | Mar 14, 2029 |
| NCE | New Chemical Entity (5-year) | Mar 14, 2029 |
| NCE | New Chemical Entity (5-year) | Mar 14, 2029 |
Is there a generic version of REZDIFFRA 60 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 82576-0060-30 You're viewing this | 30 TABLET, COATED in 1 BOTTLE (82576-060-30) | 2024-03-14 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE REZDIFFRA ® is indicated in conjunction with diet and exercise for the treatment of adults with noncirrhotic metabolic dysfunction-associated steatohepatitis (MASH), formerly known as nonalcoholic steatohepatitis (NASH), with moderate to advanced liver fibrosis (consistent with stages F2 to F3 fibrosis). This indication is approved under accelerated approval based on improvement of MASH and fibrosis [see Clinical Studies (14) ] . Continued approval for this indication may be contingent upon verification and description of clinical benefit in confirmatory trials.
Limitations of Use Avoid use of REZDIFFRA in patients with decompensated cirrhosis [see Use in Specific Populations (8.7) , Clinical Pharmacology (12.3) ] . REZDIFFRA ® is a thyroid hormone receptor-beta (THR-beta) agonist indicated in conjunction with diet and exercise for the treatment of adults with noncirrhotic metabolic dysfunction-associated steatohepatitis (MASH), formerly known as nonalcoholic steatohepatitis (NASH), with moderate to advanced liver fibrosis (consistent with stages F2 to F3 fibrosis). This indication is approved under accelerated approval based on improvement of MASH and fibrosis.
Continued approval for this indication may be contingent upon verification and description of clinical benefit in confirmatory trials. (1) Limitations of Use Avoid use of REZDIFFRA in patients with decompensated cirrhosis. (1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The recommended dosage of REZDIFFRA is based on actual body weight. For patients weighing: o <100 kg, the recommended dosage is 80 mg orally once daily. o ≥100 kg, the recommended dosage is 100 mg orally once daily. Administer REZDIFFRA with or without food.
Swallow REZDIFFRA tablets whole; do not split, crush, or chew tablets ( 2.1 ) See full prescribing information for REZDIFFRA dosage modifications with concomitant use of moderate CYP2C8 inhibitors. ( 2.2 )
2.1Recommended Dosage and Administration The recommended dosage of REZDIFFRA is based on actual body weight. For patients weighing: <100 kg, the recommended dosage is 80 mg orally once daily. ≥100 kg, the recommended dosage is 100 mg orally once daily. Administer REZDIFFRA with or without food [see Clinical Pharmacology (12.3) ] .
Swallow REZDIFFRA tablets whole; do not split, crush, or chew tablets. Advise patients that if a dose is missed, do not take the missed dose and resume with the next scheduled dose.
2.2Dosage Modifications for CYP2C8 Inhibitors Concomitant use of REZDIFFRA with strong CYP2C8 inhibitors (e.g., gemfibrozil) is not recommended [see Drug Interactions (7.1) ] . If REZDIFFRA is used concomitantly with a moderate CYP2C8 inhibitor (e.g., clopidogrel) [see Drug Interactions (7.1) ] , reduce the dosage of REZDIFFRA: <100 kg, reduce the dosage of REZDIFFRA to 60 mg once daily. ≥100 kg, reduce the dosage of REZDIFFRA to 80 mg once daily.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS REZDIFFRA Tablets: 60 mg: white oval-shaped film-coated tablets debossed with “P60” on one side and plain on the other side. 80 mg: yellow, oval-shaped, film-coated tablets debossed with “P80” on one side and plain on the other side. 100 mg: beige to pink, oval-shaped, film-coated tablets debossed with “P100” on one side and plain on the other side. Tablets: 60 mg, 80 mg, and 100 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hepatotoxicity : Monitor patients during treatment with REZDIFFRA for elevations in liver tests and for the development of liver-related adverse reactions. Discontinue REZDIFFRA and continue to monitor the patient if hepatotoxicity is suspected. (5.1) Gallbladder-Related Adverse Reactions : Cholelithiasis and cholecystitis were observed more often in REZDIFFRA-treated patients.
If cholelithiasis is suspected, gallbladder diagnostic studies and appropriate clinical follow-up are indicated. If an acute gallbladder event such as acute cholecystitis is suspected, interrupt REZDIFFRA treatment until the event is resolved. (5.2)
5.1Hepatotoxicity Hepatotoxicity has been observed with use of REZDIFFRA. One patient had normal alanine aminotransferase (ALT), aspartate aminotransferase (AST), and total bilirubin (TB) levels at baseline, who received REZDIFFRA 80 mg daily, developed substantial elevations of liver biochemistries that resolved when treatment was interrupted. After reinitiating REZDIFFRA, the patient had elevations of ALT, AST, and TB.
Peak values observed were 58 x upper limit of normal (ULN) for ALT, 66 x ULN for AST, 15 x ULN for TB, with no elevation of alkaline phosphatase (ALP). Elevations in liver enzymes were accompanied by elevations in immunoglobulin G levels, suggesting drug-induced autoimmune-like hepatitis (DI-ALH). The liver tests returned to baseline following hospitalization and discontinuation of REZDIFFRA without any therapeutic intervention.
Monitor patients during treatment with REZDIFFRA for elevations in liver tests and for the development of liver-related adverse reactions. Monitor for symptoms and signs of hepatotoxicity (e.g., fatigue, nausea, vomiting, right upper quadrant pain or tenderness, jaundice, fever, rash, and/or eosinophilia [>5%]). If hepatotoxicity is suspected, discontinue REZDIFFRA and continue to monitor the patient.
If laboratory values return to baseline, weigh the potential risks against the benefits of restarting REZDIFFRA. If laboratory values do not return to baseline, consider DI-ALH or autoimmune liver disease in the evaluation of elevations in liver tests.
5.2Gallbladder-Related Adverse Reactions In clinical trials, cholelithiasis, acute cholecystitis, and obstructive pancreatitis (gallstone) were observed more often in REZDIFFRA-treated patients than in placebo-treated patients. If cholelithiasis is suspected, gallbladder diagnostic studies and appropriate clinical follow-up are indicated. If an acute gallbladder event is suspected, interrupt REZDIFFRA treatment until the event is resolved [see Adverse Reactions (6.1) ] .
5.3Drug Interaction with Certain Statins An increase in exposure of atorvastatin, pravastatin, rosuvastatin and simvastatin was observed when concomitantly administered with REZDIFFRA [see Clinical Pharmacology (12.3) ], which may increase the risk of adverse reactions related to these drugs. Dosage adjustment for certain statins is recommended [see Drug Interactions (7.2) ] . Monitor for statin-related adverse reactions including but not limited to elevation of liver tests, myopathy, and rhabdomyolysis .
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in labeling: Hepatotoxicity [see Warnings and Precautions (5.1) ] Gallbladder-Related Adverse Reactions [see Warnings and Precautions (5.2) ] The most common adverse reactions with REZDIFFRA (reported in at least 5% of patients and higher compared to placebo) are: diarrhea, nausea, pruritus, vomiting, constipation, abdominal pain, and dizziness. (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Madrigal Pharmaceuticals, Inc. at 1-800-905-0324 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in clinical trials of another drug and may not reflect the rates observed in clinical practice. The safety of REZDIFFRA was evaluated in two randomized, double-blind, placebo-controlled trials that enrolled a total of 2019 patients. Trial 1 Trial 1 included patients who had noncirrhotic MASH with stages F2 and F3 fibrosis at eligibility (n=888) [see Clinical Studies (14) ] .
Adverse Reactions Leading to Discontinuations The exposure-adjusted incidence rates (EAIRs) per 100 person-years (PY) for treatment discontinuation due to any adverse reaction were higher in the REZDIFFRA dosage arms: 4 per 100 PY, 5 per 100 PY, and 8 per 100 PY in placebo, REZDIFFRA 80 mg once daily, and REZDIFFRA 100 mg once daily arms, respectively. Diarrhea and nausea were the most common causes of treatment discontinuation. Common Adverse Reactions Table 1 displays EAIRs per 100 PY for the common adverse reactions that occurred in at least 5% of patients with F2 or F3 fibrosis treated in either drug arm with REZDIFFRA and were greater than that reported for placebo.
Table 1: Exposure-Adjusted Incidence Rates (EAIR) of Common Adverse Reactions Reported with REZDIFFRA in Adult Patients with Noncirrhotic MASH (Trial 1) a, b, c a Population includes adult patients with noncirrhotic MASH with liver fibrosis (stages F2 and F3 at eligibility). b Median exposure duration was 68 weeks for placebo, 74 weeks for REZDIFFRA 80 mg once daily, and 66 weeks for REZDIFFRA 100 mg once daily. c EAIRs are per 100 person-years (PY) where total PYs were 435, 435, and 407 for placebo, 80 mg once daily, and 100 mg once daily arms, respectively. d The EAIR per 100 PY can be interpreted as an estimated number of first occurrences of the adverse reaction of interest if 100 patients are treated for one year.
Abbreviations: EAIR, exposure-adjusted incidence rate; PY, person-years; MASH, metabolic dysfunction-associated steatohepatitis Adverse Reaction Placebo N=294 n (EAIR d ) REZDIFFRA 80 mg Once Daily N=298 n (EAIR d ) REZDIFFRA 100 mg Once Daily N=296 n (EAIR d ) Diarrhea 52 (14) 78 (23) 98 (33) Nausea 36 (9) 65 (18) 51 (15) Pruritus 18 (4) 24 (6) 36 (10) Vomiting 15 (4) 27 (7) 30 (8) Constipation 18 (4) 20 (5) 28 (8) Abdominal pain 18 (4) 22 (5) 27 (7) Dizziness 6 (1) 17 (4) 17 (4) Gastrointestinal Adverse Reactions The incidence of gastrointestinal adverse reactions was higher for the REZDIFFRA drug arms compared to placebo.
The EAIRs for gastrointestinal adverse reactions were 57 per 100 PY, 73 per 100 PY, and 89 per 100 PY in the placebo, REZDIFFRA 80 mg once daily, REZDIFFRA 100 mg once daily arms, respectively. Diarrhea typically began early in treatment initiation and was mild to moderate in severity. The median time (Q1 to Q3) to a diarrheal event was 39 (2 to 195) days, 17 (3 to 70) days, and 6 (2 to 54) days in the placebo, REZDIFFRA 80 mg once daily, and REZDIFFRA 100 mg once daily arms, respectively.
Median duration of diarrhea was 9 days for placebo compared to 20 days for both REZDIFFRA 80 mg once daily and REZDIFFRA 100 mg once daily dosage arms. Nausea also began early in treatment and was mild to moderate in severity. Among patients with nausea, the median time (Q1 to Q…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Strong or Moderate CYP2C8 Inhibitors: Concomitant use not recommended (strong inhibitor [e.g., gemfibrozil]); or reduce REZDIFFRA dosage (moderate inhibitor [e.g., clopidogrel]). (2.2 , 7.1) Atorvastatin, Pravastatin, Rosuvastatin and Simvastatin : Limit the daily dosage of the statin as recommended. (5.3 , 7.2) CYP2C8 Substrates: Monitor patients more frequently for substrate-related adverse reactions. (7.2)
7.1Effects of Strong or Moderate CYP2C8 Inhibitors on REZDIFFRA Table 3 includes clinically significant drug interaction effects of strong or moderate CYP2C8 inhibitors on REZDIFFRA. Table 3: Clinically Significant Interaction Effects of Strong or Moderate CYP2C8 Inhibitors on REZDIFFRA Clinical Impact Resmetirom is a CYP2C8 substrate. Concomitant use with a strong or moderate CYP2C8 inhibitor can increase resmetirom Cmax and AUC [ see Clinical Pharmacology (12.3) ], which may increase the risk of REZDIFFRA adverse reactions.
Intervention Concomitant use of REZDIFFRA with strong CYP2C8 inhibitors (e.g., gemfibrozil) is not recommended. Reduce REZDIFFRA dosage if used concomitantly with a moderate CYP2C8 inhibitor (e.g., clopidogrel) [ see Dosage and Administration (2.2) ].
7.2Effects of REZDIFFRA on Other Drugs Table 4 includes clinically significant drug interactions affecting other drugs. Table 4: Clinically Significant Interactions Affecting Other Drugs Statins (Atorvastatin, Pravastatin, Rosuvastatin, or Simvastatin) Clinical Impact REZDIFFRA increased plasma concentrations of some statins (atorvastatin, pravastatin, rosuvastatin and simvastatin) [see Clinical Pharmacology (12.3) ] , which may increase the risk of adverse reactions related to these drugs. Intervention Rosuvastatin and simvastatin: Limit daily statin dosage to 20 mg.
Pravastatin and atorvastatin: Limit daily statin dosage to 40 mg. CYP2C8 Substrates Clinical Impact Resmetirom is a weak CYP2C8 inhibitor. Resmetirom increases exposure of CYP2C8 substrates [see Clinical Pharmacology (12.3) ] , which may increase the risk of adverse reactions related to these substrates.
Intervention Monitor patients more frequently for substrate-related adverse reactions if REZDIFFRA is co-administered with CYP2C8 substrates where minimal concentration changes may lead to serious adverse reactions.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Hepatic Impairment: Avoid use of REZDIFFRA in patients with moderate to severe hepatic impairment (Child-Pugh Class B or C). (8.7)
8.1Pregnancy Risk Summary There are no available data on REZDIFFRA use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes. There are risks to the mother and fetus related to underlying MASH with liver fibrosis (see Clinical Considerations ). In animal reproduction studies, adverse effects on embryo-fetal development occurred in pregnant rabbits treated with resmetirom at 3.5 times the maximum recommended dose during organogenesis.
These effects were associated with maternal toxicity, whereas no embryo-fetal effects were observed at lower dose levels with better tolerance in pregnant rabbits. No embryo-fetal developmental effects occurred in pregnant rats treated with resmetirom or the metabolite MGL-3623. A pre- and postnatal development study in rats with maternal dosing of resmetirom during organogenesis through lactation showed a decrease in birthweight and increased incidence of stillbirths and mortality (postnatal days 1-4) at 37 times the maximum recommended dose (see Data ) .
These effects were associated with marked suppression of maternal T4, T3, and TSH levels. The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, and other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Report pregnancies to Madrigal Pharmaceuticals, Inc. Adverse Event reporting line at 1-800-905-0324 or https://pregnancyregistry.madrigalpharma.com .
Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk There are risks to the mother and fetus related to underlying maternal MASH with liver fibrosis, such as increased risks of gestational diabetes, hypertensive complications, preterm birth, and postpartum hemorrhage. Data Animal Data No effects on embryo-fetal development were observed in pregnant rats treated orally with up to 100 mg/kg/day (21 times the maximum recommended dose based on AUC [area under the plasma concentration-time curve]) or in pregnant rabbits treated orally with up to 30 mg/kg/day (2.8 times the maximum recommended dose based on AUC) during the period of organogenesis.
Oral administration of 75 mg/kg/day in pregnant rabbits (3.5 times the maximum recommended dose based on AUC) produced an increase in post-implantation loss and decreases in viable fetuses and fetal weight. These effects were likely due to maternal toxicity (i.e., marked reductions in weight gain and food consumption). A pre- and postnatal development study was performed using oral administration of 3, 30, or 100 mg/kg/day in female rats during organogenesis through lactation.
Treatment with 100 mg/kg/day (37 times the maximum recommended dose based on AUC) produced increases in number of stillborn, pup deaths during postnatal days 1-4, and pups with absence of milk in stomach. Birthweight was decreased by 10% in this dose group, with recovery to normal body weight thereafter. The effects in offspring were associated with marked reductions in maternal plasma levels of T4 (88% decrease), T3 (79% decrease), and TSH (44% decrease).
No effects on postnatal development were observed at doses up to 30 mg/kg/day (7.2 times the maximum recommended dose based on AUC). This study lacked a complete evaluation of physical and neurobehavioral development in offspring; however, no effects of resmetirom were noted in tests of learning and memory. The metabolite MGL-3623 was tested for its effects on embryo-fetal development.
No effects were observed in pregnant rats treated orally with up to 100 mg/kg/day MGL-3623 (4.7 times the maximum recommended dose based on…
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Resmetirom is a partial agonist of the thyroid hormone receptor-beta (THR-β). Resmetirom produced 83.8% of the maximum response compared to triiodothyronine (T3), with an EC 50 of 0.21 µM in an in vitro functional assay for THR-β activation. The same functional assay for thyroid hormone receptor-alpha (THR-α) agonism showed 48.6% efficacy for resmetirom relative to T3, with an EC 50 of 3.74 µM.
THR-β is the major form of THR in the liver, and stimulation of THR-β in the liver reduces intrahepatic triglycerides, whereas actions of thyroid hormone outside the liver, including in heart and bone, are largely mediated through THR-α.
12.2Pharmacodynamics Noninvasive Liver Disease Markers Resmetirom decreases liver fat content measured by magnetic resonance imaging-proton density fat fraction (MRI-PDFF) or ultrasound attenuation (e.g. controlled attenuation parameter (CAP)). Resmetirom also decreases liver stiffness, as measured by transient elastography (TE) and Enhanced Liver Fibrosis (ELF) score. The clinical relevance of these changes is yet to be confirmed.
Prohormone FT4 Resmetirom decreased concentrations of prohormone FT4 were observed at the first assessment at 4 weeks of treatment. Similar decreases in FT4 were observed during the treatment [see Adverse Reactions (6.1) ]. Sex Hormone Binding Globulin (SHBG) Resmetirom increased concentrations of sex hormone binding globulin (SHBG) were observed at the first assessment at 4 weeks of treatment, and at longer durations of treatment.
The clinical significance of this change is unknown. Cardiac Electrophysiology At a dose two times the maximum recommended dose, resmetirom does not prolong the QT interval to any clinically relevant extent.
12.3Pharmacokinetics Following once daily doses, steady state is typically reached within 3 to 6 days of dosing. Resmetirom steady state exposure increases in a dose proportional manner between doses of 40 mg (0.5 times the lowest approved recommended dose) and 100 mg. Resmetirom exposure increases in a greater than dose proportional manner between doses of 100 mg and 200 mg (2 times the highest approved recommended dose) by about 5.6-fold.
Resmetirom exposure increased 1.5- to 3-fold following once daily dosing; however, the MGL-3623 metabolite does not accumulate. The estimated resmetirom systemic exposure at steady state in MASH patients is summarized in Table 5 . Resmetirom exposure is similar between MASH patients with F2 stage fibrosis and F3 stage fibrosis.
Table 5: Resmetirom Estimated Systemic Exposure at Steady State in Patients with MASH with Fibrosis (F2 and F3) Abbreviations: AUC t au,ss = area under the concentration-versus-time curve over one dosing interval at steady state; C max,ss = maximum concentration at steady state; CV = arithmetic coefficient of variation Parameter Resmetirom 80 mg Once Daily Mean (CV%) Resmetirom 100 mg Once Daily Mean (CV%) C max,ss (ng/mL) a 778 (41.5) 971 (40.9) AUC tau,ss (ng*h/mL) a 5850 (60.5) 7780 (65.5) Absorption The resmetirom median time to maximum plasma concentration (T max ) is approximately 4 hours following multiple daily doses of resmetirom 80 mg or 100 mg.
Effect of Food No clinically significant differences in resmetirom pharmacokinetics were observed following administration with a high-fat meal (approximately 150, 250, and 500-600 calories from protein, carbohydrate, and fat, respectively). Concomitant food administration resulted in a 33% decrease in C max , an 11% decrease in AUC, and a delay in median T max by about 2 hours compared to under fasted condition. Distribution Resmetirom apparent volume of distribution (Vd/F) at steady-state is 68 (227%) L.
Resmetirom is greater than 99% protein-bound. Elimination Resmetirom median terminal plasma half-life (t½) is 4.5 hours and the steady state apparent clearance (CL/F) is 17.5 (56.3%) L/h. Metabolism Resmetirom is metabolized by CYP2C8 and is not metabolized by other CYP enzymes in…
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied REZDIFFRA (resmetirom) tablets are packaged in white high-density polyethylene bottles closed with a child-resistant closure containing an induction seal. 60 mg Tablets : white oval-shaped film-coated tablets, debossed “P60” on one side and plain on the other side. Bottle of 30 count (NDC 82576-060-30) 80 mg Tablets : yellow, oval-shaped, film-coated tablets, debossed with “P80” on one side and plain on the other side.
Bottle of 30 count (NDC 82576-080-30) Bottle of 90 count (NDC 82576-080-90) 100 mg Tablets: beige to pink, oval-shaped, film-coated tablets, debossed with “P100” on one side and plain on the other side. Bottle of 30 count (NDC 82576-100-30) Bottle of 90 count (NDC 82576-100-90) Storage and Handling Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [ see USP Controlled Room Temperature ].
📋 Description ▾
11 DESCRIPTION REZDIFFRA (resmetirom) tablets contain resmetirom, a thyroid hormone receptor-beta agonist. The chemical name for REZDIFFRA is 2-[3,5-Dichloro-4-((6-oxo-5-(propan-2-yl)-1,6-dihydropyridazin-3-yl)oxy)phenyl]-3,5-dioxo-2,3,4,5-tetrahydro-1,2,4-triazine-6-carbonitrile. The molecular formula is C 17 H 12 Cl 2 N 6 O 4 and the molecular weight is 435.22.
The chemical structure is: Resmetirom has low aqueous solubility below pH 6 and higher solubility above pH 7 (0.44 mg/mL at pH 7.04). REZDIFFRA tablets are supplied in 60 mg, 80 mg, and 100 mg strengths for oral administration. Each tablet contains the active ingredient, resmetirom, and the following USP/NF excipients: colloidal silicon dioxide, croscarmellose sodium, magnesium stearate, mannitol, and microcrystalline cellulose.
REZDIFFRA tablets are film-coated with an Opadry coating comprised of polyethylene glycol, polyvinyl alcohol, talc, titanium dioxide, red iron oxide (100 mg tablets), yellow iron oxide (80 mg and 100 mg tablets). image description
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Administration Instructions Instruct patients to swallow REZDIFFRA tablets whole and not split, crush, or chew tablets [ see Dosage and Administration (2.1) ]. Hepatotoxicity Inform patients of the risk of hepatotoxicity.
Instruct patients to immediately report any signs or symptoms of severe liver injury (e.g., fatigue, nausea, vomiting, right upper quadrant pain or tenderness, jaundice, fever, rash) to their healthcare provider [see Warnings and Precautions (5.1) ]. Gallbladder-Related Adverse Reactions Inform patients of the potential risk for cholelithiasis, cholecystitis, and obstructive pancreatitis (gallstones) during treatment with REZDIFFRA. Instruct patients to contact their healthcare provider if they develop signs or symptoms of these conditions [see Warnings and Precautions (5.2) ].
Drug Interaction with Statins Inform patients that concomitant use of REZDIFFRA with some statins may increase the risk of statin-related adverse reactions (e.g., elevation of liver tests, myopathy, rhabdomyolysis) [see Warnings and Precautions (5.3) , Drug Interactions (7.2) ] . Pregnancy Inform patients that there is a pregnancy safety study that monitors pregnancy outcomes in women exposed to REZDIFFRA during pregnancy. Encourage patients to report their pregnancy by visiting https://pregnancyregistry.madrigalpharma.com or calling 1-800-905-0324 [ see Use in Specific Populations (8.1) ].
Manufactured for and Distributed by: Madrigal Pharmaceuticals, Inc. West Conshohocken, PA REZDIFFRA ® is a registered trademark owned by Madrigal Pharmaceuticals, Inc. © 2026 Madrigal Pharmaceuticals, Inc.