
Advanced Lipid Control Ingredients & Drug Interactions
What is this page for?
First and foremost: checking Advanced Lipid Control against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Advanced Lipid Control is a dietary supplement by Life Extension with 2 active ingredients. Its ingredients are commonly taken for mental alertness and energy, heart health support, blood pressure and cholesterol.Based on those ingredients, 694 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Black Tea Leaf Extract, Capros. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Advanced Lipid Control by Life Extension
Ask about any prescription or over-the-counter medication and we check it for interactions with Advanced Lipid Control by Life Extension — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Advanced Lipid Control by Life Extension
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
Advanced Lipid Control contains two active ingredients: Black Tea Leaf Extract, which is rich in caffeine and polyphenols, and Capros, a standardized extract of Indian gooseberry (also called amla). The product also includes inactive ingredients—cellulose, stearic acid, vegetable stearate, and silica—that serve as binders, thickeners, and capsule material.
Does it work?
Moderate evidence
Black Tea Leaf Extract is likely effective for mental alertness and possibly effective for heart attack prevention, bone health, blood pressure support, and ovarian cancer risk reduction, though the strength of evidence varies. Capros is possibly effective for reflux disease and cholesterol management, but evidence is insufficient to rate its use for hair loss.
The product is marketed for lipid (cholesterol) control, but the effectiveness data on file doesn't establish how well the combination works for that specific purpose.
How safe is it?
Well-documented data
Black Tea Leaf Extract is generally well tolerated in moderate amounts by healthy adults, but caffeine can cause problems at higher doses—including jitteriness, stomach upset, insomnia, nausea, tremors, and in rare cases arrhythmia or chest pain. Anaphylaxis is possible in people sensitive to caffeine, though true caffeine allergy is uncommon.
Caffeine can also lower potassium levels and in infants may cause a type of anemia. During pregnancy, the safety data advises keeping caffeine intake moderate and checking with your provider, since high amounts may be harmful.
Caffeine passes into breast milk, so moderate intake is recommended to avoid affecting the baby. Capros is generally well tolerated as a food but is less studied at supplement doses.
The safety data advises against using Capros at supplement levels during pregnancy, and there is too little reliable safety information during breastfeeding.
Meds to double-check
Major interaction found
Before taking Advanced Lipid Control, check the following medication types with your pharmacist: stimulants like ephedrine (Major severity risk); anticonvulsants like valproate; blood thinners and antiplatelet drugs including warfarin and clopidogrel; diabetes medications; certain antidepressants; clozapine; cimetidine; fluvoxamine; and dipyridamole. These represent the documented interactions we could check.
The bottom line
Scorecard at a glanceFully disclosed formula with some supporting evidence for its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
If you're managing cholesterol and want to explore herbal options, talk to your pharmacist first—especially if you take any heart, blood pressure, diabetes, anticonvulsant, psychiatric, or blood-thinning medications. The caffeine in Black Tea Leaf Extract and the bleeding risk from Capros mean this product isn't right for everyone.
Use the medication checker below before you start.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 2 of 2 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Mar 25, 2025.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Advanced Lipid Control, straight from the product label.
| Brand | Life Extension |
|---|---|
| Barcode (UPC) | 737870182863 |
| Net contents | 60 Vegetarian Capsule(s) |
| Market status | On market |
| Date entered into DSLD | Mar 25, 2025 |
| DSLD ID | 328277 |
| Product type | Botanical |
| Supplement form | Capsule |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years), Gluten Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
Supplement Facts
The label details for Advanced Lipid Control by Life Extension, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Black Tea Leaf Extract | 350 mg | -- |
| Capros | 500 mg | -- |
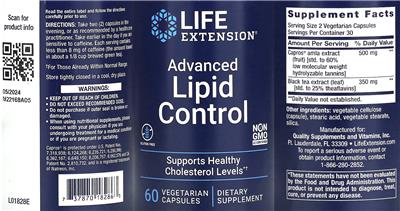
Other ingredients: Cellulose, Stearic Acid, Vegetable Stearate, Silica
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
General Statements
Scan for product info
Suggested/Recommended/Usage/Directions
Read the entire label and follow the directions carefully prior to use. Directions: Take two (2) capsules in the evening or as recommended by a healthcare practitioner. Take earlier in the day if you are sensitive to caffeine.
Formula
Each serving contains less than 8 mg of caffeine (the amount found in about a 1/8 cup brewed green tea).
Formulation
Supports healthy cholesterol levels For those already within normal range.
Gluten Free Non GMO LE Certified
Precautions
Warnings: Keep out of reach of children.
Do not exceed recommended dose. Do not purchase if outer seal is broken or damaged.
When using nutritional supplements, please consult with your physician if you are undergoing treatment for a medical condition or if you are pregnant or lactating.
To report a serious adverse event or obtain product information, contact 1-866-280-2852.
Brand IP Statement(s)
Capros is protected under U.S. Patent Nos. 7,318,938; 6,124,268; 6,235,721; 6,290,996; 6,362,167; 6,649,150; 8,206,757; 8,962,576 and CA Patent No. 2,810,732, and is a registered trademark of Natreon, Inc.
Seals/Symbols
Non GMO LE Certified
FDA Statement of Identity
Dietary Supplement
FDA Disclaimer Statement
These statements have not been evaluated by the Food and Drug Administration. This product is not intended to diagnose, treat, cure, or prevent any disease.
Storage
Store tightly closed in a cool, dry place.
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Advanced Lipid Control by Life Extension label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Advanced Lipid Control by Life Extension
These are the 2 active ingredients this product is made of. Select any to open its full monograph.
Serving size2 Vegetarian Capsule(s) Dosage formCapsule Servings per container30 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Black Tea Leaf Extract
Interacts with694 drugs
Black tea is a popular caffeinated drink made from the fully oxidized leaves of the Camellia sinensis plant, and it contains caffeine and antioxidant...
Black Tea Leaf Extract monograph & interactionsCapros
Interacts with208 drugs
Indian gooseberry (amla) is a vitamin C-rich fruit used in Ayurvedic medicine for many purposes, from antioxidant support to cholesterol and digestion...
Capros monograph & interactionsOther (inactive) ingredients: Cellulose, Stearic Acid, Vegetable Stearate, Silica. These complete the product’s ingredient list but are not active constituents.
Advanced Lipid Control by Life Extension Drug Interactions
HelloPharmacist Interaction Report
Advanced Lipid Control by Life Extension contains two active ingredients, and together they interact with a substantial number of medications.
Black Tea Leaf Extract is the source of the most serious concern: it contains caffeine, which combined with ephedrine (a stimulant) carries a Major severity risk for life-threatening effects including high blood pressure, heart attack, stroke, seizures, and death.
Read the full breakdown — every affected drug type, severity by severity
Black Tea Leaf Extract also has Moderate severity interactions with several other drug types. It may increase the effects and side effects of drugs that slow stomach acid (cimetidine), certain antidepressants (fluvoxamine), and a psychiatric medication (clozapine).
It can reduce how well anticonvulsants (valproate) work and increase seizure risk. It may interfere with stress-test medications (dipyridamole) and slow how your body clears caffeine if you take a medication to quit drinking (disulfiram).
Large amounts of black tea may also reduce the effectiveness of blood thinners (warfarin).
Capros (Indian Gooseberry) carries Moderate severity interactions with blood thinners and antiplatelet drugs—including aspirin and clopidogrel—which may raise bleeding risk. It may also lower blood sugar too much if combined with diabetes medications, requiring dose adjustments.
Altogether, these interactions span 693 individual medications. Use the medication checker on this page to look up any drugs you take before starting this product.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Advanced Lipid Control?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Advanced Lipid Control interact with 694 drugs. Click any drug to see the details.
2 of the 2 ingredients in Advanced Lipid Control interact with drugs. Each result below shows which ingredient is responsible. Black Tea Leaf Extract Capros
Acetaminophen, Chlorpheniramine, Phenylephrine, SalicylamideRhinogesic, Rhinogesic JR
How Acetaminophen, Chlorpheniramine, Phenylephrine, Salicylamide interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acetaminophen, Chlorpheniramine, Phenylephrine, Salicylamide interactionAcetaminophen, Chlorpheniramine, PhenylpropanolamineAlumadrine, Conex, Sinadrin Max Strength, Sinulin
How Acetaminophen, Chlorpheniramine, Phenylpropanolamine interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs, Phenylpropanolamine Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acetaminophen, Chlorpheniramine, Phenylpropanolamine interactionAcetaminophen, Chlorpheniramine, Phenylpropanolamine, OpiumHista-Derfule
How Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractPhenylpropanolamine, Stimulant Drugs Moderate
Interaction Summary
Theoretically, phenylpropanolamine might increase the risk of hypertension, as well as the levels and adverse effects of caffeine.
Read the full Black Tea Leaf Extract + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionAcetaminophen, Chlorpheniramine, Phenylpropanolamine, PhenyltoloxamineNorel Plus
How Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Phenyltoloxamine interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs, Phenylpropanolamine Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Phenyltoloxamine interactionAcetaminophen, Chlorpheniramine, PseudoephedrineAlka-Seltzer PLUS Liquid Gels, Children's Tylenol Cold, Codimal, Comtrex, Extra Strength Tylenol Allergy Sinus, Lorsin +3 more
How Acetaminophen, Chlorpheniramine, Pseudoephedrine interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acetaminophen, Chlorpheniramine, Pseudoephedrine interactionAcetaminophen, Dexbrompheniramine, PseudoephedrineSinadrin Plus
How Acetaminophen, Dexbrompheniramine, Pseudoephedrine interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acetaminophen, Dexbrompheniramine, Pseudoephedrine interactionAcetaminophen, Dextromethorphan, Doxylamine, PseudoephedrineVicks NyQuil
How Acetaminophen, Dextromethorphan, Doxylamine, Pseudoephedrine interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acetaminophen, Dextromethorphan, Doxylamine, Pseudoephedrine interactionAcetaminophen, Dextromethorphan, Guaifenesin, PhenylephrineConar-A
How Acetaminophen, Dextromethorphan, Guaifenesin, Phenylephrine interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acetaminophen, Dextromethorphan, Guaifenesin, Phenylephrine interactionAcetaminophen, Dextromethorphan, Guaifenesin, PhenylpropanolamineAnatuss
How Acetaminophen, Dextromethorphan, Guaifenesin, Phenylpropanolamine interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs, Phenylpropanolamine Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acetaminophen, Dextromethorphan, Guaifenesin, Phenylpropanolamine interactionAcetaminophen, Dextromethorphan, Guaifenesin, PseudoephedrineRobitussin Cold, Severe Cold, Suphedrine Cold/Cough
How Acetaminophen, Dextromethorphan, Guaifenesin, Pseudoephedrine interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acetaminophen, Dextromethorphan, Guaifenesin, Pseudoephedrine interactionAcetaminophen, Dextromethorphan, Phenylpropanolamine, PyrilamineTheracaps
How Acetaminophen, Dextromethorphan, Phenylpropanolamine, Pyrilamine interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs, Phenylpropanolamine Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acetaminophen, Dextromethorphan, Phenylpropanolamine, Pyrilamine interactionAcetaminophen, Dextromethorphan, PseudoephedrineAlka-Seltzer PLUS Flu Liquid Gels, Non Aspirin Cold Caps, Tylenol Cold, Tylenol Flu Daytime Ex Strength, Tylenol Flu Ex Strength
How Acetaminophen, Dextromethorphan, Pseudoephedrine interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acetaminophen, Dextromethorphan, Pseudoephedrine interactionAcetaminophen, Dichloralantipyrine, IsomethepteneAmidrine, Midchlor, Migquin, Migratine
How Acetaminophen, Dichloralantipyrine, Isometheptene interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acetaminophen, Dichloralantipyrine, Isometheptene interactionAcetaminophen, Dichloralphenazone, IsomethepteneMidrin
How Acetaminophen, Dichloralphenazone, Isometheptene interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acetaminophen, Dichloralphenazone, Isometheptene interactionAcetaminophen, Dichlorophenazone, IsometheptaneIsocom
How Acetaminophen, Dichlorophenazone, Isometheptane interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acetaminophen, Dichlorophenazone, Isometheptane interactionAcetaminophen, Diphenhydramine, PseudoephedrineChildren's Tylenol Allergy, Cold Control, Contac Night Allergy Relief
How Acetaminophen, Diphenhydramine, Pseudoephedrine interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acetaminophen, Diphenhydramine, Pseudoephedrine interactionAcetaminophen, Doxylamine, PseudoephedrineEx Strength Tylenol Sinus Nighttime
How Acetaminophen, Doxylamine, Pseudoephedrine interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acetaminophen, Doxylamine, Pseudoephedrine interactionAcetaminophen, IbuprofenCombogesic
How Acetaminophen, Ibuprofen interacts with Advanced Lipid Control — through 2 ingredients. Tap an ingredient for the detail:
CaprosAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, Indian gooseberry may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs; however, research is conflicting.
Read the full Capros + Acetaminophen, Ibuprofen interactionBlack Tea Leaf ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Black Tea Leaf Extract + Acetaminophen, Ibuprofen interactionAcetaminophen, Pamabrom, PyrilamineMidol Max Strength PMS, Pamprin, Pamprin ES
How Acetaminophen, Pamabrom, Pyrilamine interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractDiuretic Drugs, Stimulant Drugs Moderate
Interaction Summary
Theoretically, using black tea with diuretic drugs might increase the risk of hypokalemia.
Read the full Black Tea Leaf Extract + Acetaminophen, Pamabrom, Pyrilamine interactionAcetaminophen, Phenylephrine, ChlorpheniramineSuper Cold Tabs
How Acetaminophen, Phenylephrine, Chlorpheniramine interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acetaminophen, Phenylephrine, Chlorpheniramine interactionAcetaminophen, PhenylpropanolamineTetra Caps
How Acetaminophen, Phenylpropanolamine interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs, Phenylpropanolamine Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acetaminophen, Phenylpropanolamine interactionAcetaminophen, Phenylpropanolamine, PhenyltoloxamineSinubid
How Acetaminophen, Phenylpropanolamine, Phenyltoloxamine interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractPhenylpropanolamine, Stimulant Drugs Moderate
Interaction Summary
Theoretically, phenylpropanolamine might increase the risk of hypertension, as well as the levels and adverse effects of caffeine.
Read the full Black Tea Leaf Extract + Acetaminophen, Phenylpropanolamine, Phenyltoloxamine interactionAcetaminophen, PseudoephedrineChildren's Tylenol Sinus, Dristan N.D., Non-Aspirin Sinus, Ornex, Ornex-Max, Sinutab +5 more
How Acetaminophen, Pseudoephedrine interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acetaminophen, Pseudoephedrine interactionAcetaminophen, Pseudoephedrine, TriprolidineActifed Plus ES
How Acetaminophen, Pseudoephedrine, Triprolidine interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acetaminophen, Pseudoephedrine, Triprolidine interactionAcetazolamideAk-Zol, Diamox
How Acetazolamide interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractDiuretic Drugs Moderate
Interaction Summary
Theoretically, using black tea with diuretic drugs might increase the risk of hypokalemia.
Read the full Black Tea Leaf Extract + Acetazolamide interactionAcetohexamideDymelor
How Acetohexamide interacts with Advanced Lipid Control — through 2 ingredients. Tap an ingredient for the detail:
CaprosAntidiabetes Drugs Moderate
Interaction Summary
Taking Indian gooseberry with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Capros + Acetohexamide interactionBlack Tea Leaf ExtractAntidiabetes Drugs Minor
Interaction Summary
Theoretically, taking black tea with antidiabetes drugs might interfere with blood glucose control.
Read the full Black Tea Leaf Extract + Acetohexamide interactionAcetylsalicylic AcidEntrophen
How Acetylsalicylic Acid interacts with Advanced Lipid Control — through 2 ingredients. Tap an ingredient for the detail:
CaprosAnticoagulant/antiplatelet Drugs, Aspirin Moderate
Interaction Summary
Theoretically, Indian gooseberry may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs; however, research is conflicting.
Read the full Capros + Acetylsalicylic Acid interactionBlack Tea Leaf ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Black Tea Leaf Extract + Acetylsalicylic Acid interactionAcrivastine, PseudoephedrineSemprex D
How Acrivastine, Pseudoephedrine interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Black Tea Leaf Extract + Acrivastine, Pseudoephedrine interactionAdenosineATP Tablets
How Adenosine interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractAdenosine (adenocard) Moderate
Interaction Summary
Theoretically, black tea might decrease the vasodilatory effects of adenosine and interfere with its use prior to stress testing.
Read the full Black Tea Leaf Extract + Adenosine interactionAdenosine (prescription Drug)Adenocard, Adenocor, Adenoscan
How Adenosine (prescription Drug) interacts with Advanced Lipid Control — through 1 ingredient. Tap an ingredient for the detail:
Black Tea Leaf ExtractAdenosine (adenocard) Moderate
Interaction Summary
Theoretically, black tea might decrease the vasodilatory effects of adenosine and interfere with its use prior to stress testing.
Read the full Black Tea Leaf Extract + Adenosine (prescription Drug) interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Advanced Lipid Control with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Black Tea Leaf Extract
Ephedrine
Theoretically, concomitant use might increase the risk for simulant adverse effects.
Black tea contains caffeine. There is evidence that using ephedrine with caffeine might increase the risk of serious life-threatening or debilitating adverse effects such as hypertension, myocardial infarction, stroke, seizures, and death. Tell patients to avoid taking caffeine with ephedrine and other stimulants.
Adenosine (Adenocard)
Theoretically, black tea might decrease the vasodilatory effects of adenosine and interfere with its use prior to stress testing.
Black tea contains caffeine. Caffeine is a competitive inhibitor of adenosine at the cellular level. However, caffeine does not seem to affect supplemental adenosine because high interstitial levels of adenosine overcome the antagonistic effects of caffeine. It is recommended that methylxanthines such as caffeine, as well as methylxanthine-containing products, be stopped 24 hours prior to pharmacological stress tests. However, methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Anticoagulant/Antiplatelet Drugs
Theoretically, black tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Black tea contains caffeine. Caffeine is reported to have antiplatelet activity. Theoretically, the caffeine in black tea might increase the risk of bleeding when used concomitantly with antiplatelet drugs. However, this interaction has not been reported in humans.
Beta-Adrenergic Agonists
Theoretically, concomitant use of large amounts of black tea might increase cardiac inotropic effects of beta-agonists.
Black tea contains caffeine. Caffeine can increase cardiac inotropic effects of beta-agonists.
Carbamazepine (Tegretol)
Theoretically, black tea might reduce the effects of carbamazepine and increase the risk for convulsion.
Black tea contains caffeine. Animal research suggests that caffeine can lower the anticonvulsant effects of carbamazepine and can induce seizures when taken in doses above 400 mg/kg. Human research has shown that taking caffeine 300 mg in three divided doses along with carbamazepine 200 mg reduces the bioavailability of carbamazepine by 32% and prolongs the plasma half-life of carbamazepine 2-fold in healthy individuals.
Cimetidine (Tagamet)
Theoretically, concomitant use might increase the effects and adverse effects of caffeine in black tea.
Black tea contains caffeine. Cimetidine can reduces caffeine clearance by 31% to 42%.
Clozapine (Clozaril)
Theoretically, black tea might increase the levels and adverse effects of clozapine and acutely exacerbate psychotic symptoms.
Concomitant administration of black tea and clozapine might theoretically cause acute exacerbation of psychotic symptoms due to the caffeine in black tea. Caffeine can increase the effects and toxicity of clozapine. Caffeine doses of 400-1000 mg daily inhibit clozapine metabolism. Clozapine is metabolized by cytochrome P450 1A2 (CYP1A2). Researchers speculate that caffeine might inhibit CYP1A2. However, there is no reliable evidence that caffeine affects CYP1A2. There is also speculation that genetic factors might make some patients be more sensitive to the interaction between clozapine and caffeine.
Contraceptive Drugs
Theoretically, concomitant use might increase the effects and adverse effects of caffeine found in black tea.
Black tea contains caffeine. Oral contraceptive drugs can decrease caffeine clearance by 40% to 65%.
Cytochrome P450 1A2 (Cyp1A2) Inhibitors
Theoretically, concomitant use might increase the levels and adverse effects of caffeine.
Black tea contains caffeine. Caffeine is metabolized by CYP1A2,. Theoretically, drugs that inhibit CYP1A2 may decrease the clearance rate of caffeine from black tea and increase caffeine levels.
Dipyridamole (Persantine)
Theoretically, black tea might decrease the vasodilatory effects of dipyridamole and interfere with its use prior to stress testing.
Black tea contains caffeine. Caffeine is a methylxanthine that may inhibit dipyridamole-induced vasodilation. It is recommended that methylxanthines such as caffeine, as well as methylxanthine-containing products such as black tea, be stopped 24 hours prior to pharmacological stress tests. Methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Disulfiram (Antabuse)
Theoretically, disulfiram might increase the risk of adverse effects from caffeine.
Black tea contains caffeine. In human research, disulfiram decreases the clearance and increases the half-life of caffeine.
Diuretic Drugs
Theoretically, using black tea with diuretic drugs might increase the risk of hypokalemia.
Black tea contains caffeine. Caffeine, especially in excessive amounts, can reduce potassium levels due to stimulation of the sodium-potassium pump. Diuretics can also cause lower potassium levels.
Estrogens
Theoretically, estrogens might increase the levels and adverse effects of caffeine.
Black tea contains caffeine. Estrogen inhibits caffeine metabolism.
Ethosuximide (Zarontin)
Theoretically, black tea might reduce the effects of ethosuximide and increase the risk for convulsions.
Black tea contains caffeine. Animal research suggests that caffeine 92.4 mg/kg can decrease the anticonvulsant activity of ethosuximide. However, this effect has not been observed in humans.
Felbamate (Felbatol)
Theoretically, black tea might reduce the effects of felbamate and increase the risk for convulsions.
Black tea contains caffeine. Animal research suggests that a high dose of caffeine 161.7 mg/kg can decrease the anticonvulsant activity of felbamate. However, this effect has not been observed in humans.
Flutamide (Eulexin)
Theoretically, black tea might increase the levels and adverse effects of flutamide.
Black tea contains caffeine. In vitro evidence suggests that caffeine can inhibit the metabolism of flutamide. Theoretically, concomitant use of caffeine and flutamide might increase serum concentrations of flutamide and increase the risk of adverse effects.
Fluvoxamine (Luvox)
Theoretically, fluvoxamine might increase the levels and adverse effects of caffeine.
Black tea contains caffeine. Fluvoxamine reduces caffeine metabolism.
Lithium
Theoretically, abrupt black tea withdrawal might increase the levels and adverse effects of lithium.
Black tea contains caffeine. Abrupt caffeine withdrawal can increase serum lithium levels. Two cases of lithium tremor that worsened with abrupt coffee withdrawal have been reported.
Monoamine Oxidase Inhibitors (Maois)
Theoretically, concomitant use might increase the risk of a hypertensive crisis.
Black tea contains caffeine. Caffeine has been shown to inhibit monoamine oxidase (MAO) A and B in laboratory studies. Concomitant intake of large amounts of caffeine with MAOIs might precipitate a hypertensive crisis. In a case report, a patient that consumed 10-12 cups of caffeinate coffee and took the MAOI tranylcypromine presented with severe hypertension. Hypertension was resolved after the patients switched to drinking decaffeinated coffee.
Nicotine
Theoretically, concomitant use might increase the risk of hypertension.
Black tea contains caffeine. Concomitant use of caffeine and nicotine has been shown to have additive cardiovascular effects, including increased heart rate and blood pressure. Blood pressure was increased by 10.8/12.4 mmHg when the agents were used concomitantly.
Organic Anion-Transporting Polypeptide Substrates (Oatp)
Theoretically, black tea might reduce the absorption of organic anion-transporting polypeptide (OATP) substrates.
In vitro, black tea extract inhibits organic anion-transporting polypeptide (OATP)2B1. OATP2B1 is expressed in the small intestine and liver and is responsible for the uptake of drugs and other compounds. In an animal model, black tea extract was found to inhibit the absorption of rosuvastatin, a substrate of OATP2B1. However, this effect has not been reported in humans.
Pentobarbital (Nembutal)
Theoretically, black tea might decrease the effects of pentobarbital.
Black tea contains caffeine. Theoretically, caffeine might negate the hypnotic effects of pentobarbital.
Phenobarbital (Luminal)
Theoretically, black tea might reduce the effects of phenobarbital and increase the risk for convulsions.
Black tea contains caffeine. Animal research suggests that caffeine can decrease the anticonvulsant activity of phenobarbital. The exact mechanism of this interaction is unclear.
Phenylpropanolamine
Theoretically, phenylpropanolamine might increase the risk of hypertension, as well as the levels and adverse effects of caffeine.
Black tea contains caffeine. Concomitant use of phenylpropanolamine and caffeine might cause an additive increase in blood pressure. Phenylpropanolamine also seems to increase caffeine serum levels.
Phenytoin (Dilantin)
Theoretically, black tea might reduce the effects of phenytoin and increase the risk for convulsions.
Black tea contains caffeine. Animal research suggests that caffeine can decrease the anticonvulsant activity of phenytoin. The effect does not seem to be related to the seizure threshold-lowering effects of caffeine. However, the exact mechanism of this interaction is unclear.
Capros
Anticoagulant/Antiplatelet Drugs
Theoretically, Indian gooseberry may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs; however, research is conflicting.
Clinical research shows that taking Indian gooseberry 500 mg as a single dose or twice daily for 10 days reduces platelet aggregation by about 24% to 36%, increases bleeding time by about 3.8-5.9 seconds, and increases clotting time by about 9.8-12.7 seconds when compared to baseline. However, taking Indian gooseberry 500 mg along with clopidogrel 75 mg or ecosprin 75 mg, as a single dose or for 10 days, does not significantly reduce platelet aggregation or increase bleeding time or clotting time when compared with clopidogrel 75 mg or ecosprin 75 mg alone. Until more is known, use caution when taking Indian gooseberry in combination with anticoagulant/antiplatelet drugs.
Antidiabetes Drugs
Taking Indian gooseberry with antidiabetes drugs might increase the risk of hypoglycemia.
Clinical research shows that taking Indian gooseberry fruit or fruit extract alone or in conjunction with antidiabetes medications can lower blood glucose levels. Dose adjustments to diabetes medications might be necessary.
Aspirin
Theoretically, Indian gooseberry may increase the risk of bleeding if used with aspirin; however, research is conflicting.
Clinical research shows that taking Indian gooseberry 500 mg as a single dose or twice daily for 10 days reduces platelet aggregation by about 24% to 36%, increases bleeding time by about 3.8-5.9 seconds, and increases clotting time by about 9.8-12.7 seconds when compared to baseline. However, taking a single dose of Indian gooseberry 500 mg along with ecosprin 75 mg, or taking a combination of Indian gooseberry 500 mg twice daily plus ecosprin 75 mg once daily for 10 days, does not significantly reduce platelet aggregation or increase bleeding time or clotting time when compared with ecosprin 75 mg alone.
Clopidogrel (Plavix)
Theoretically, Indian gooseberry may increase the risk of bleeding if used with clopidogrel; however, research is conflicting.
Clinical research shows that taking Indian gooseberry 500 mg as a single dose or twice daily for 10 days reduces platelet aggregation by about 24% to 36%, increases bleeding time by about 3.8-5.9 seconds, and increases clotting time by about 9.8-12.7 seconds when compared to baseline. However, taking a single dose of Indian gooseberry 500 mg along with clopidogrel 75 mg, or taking a combination of Indian gooseberry 500 mg twice daily plus clopidogrel 75 mg once daily for 10 days, does not significantly reduce platelet aggregation or increase bleeding time or clotting time when compared with clopidogrel 75 mg alone.
Brand information
Manufacturer and brand details for Advanced Lipid Control, from the product label.
Life Extension
See all Life Extension products- Name
- Quality Supplements and Vitamins, Inc.
- City
- Ft. Lauderdale
- State
- FL
- ZipCode
- 33309
- Phone Number
- 1-866-280-2852
- Web Address
- LifeExtension.com
Advanced Lipid Control by Life Extension: Common Questions
Does Advanced Lipid Control by Life Extension interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
What does Black Tea Leaf Extract do in this product?
What is Capros, and what is it supposed to do?
Can I take this if I'm pregnant?
Can I take this while breastfeeding?
What side effects might I notice from the caffeine?
Did you find any adverse effects reported with Capros in the clinical data?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Advanced Lipid Control is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Advanced Lipid Control’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Black Tea
Interacts with 694 drugsBlack tea is a popular caffeinated drink made from the fully oxidized leaves of the Camellia sinensis plant, and it contains caffeine and antioxidant plant compounds. Moderate tea drinking i...
Read the full Black Tea monograph → Herb & supplement monographIndian Gooseberry
Interacts with 208 drugsIndian gooseberry (amla) is a vitamin C-rich fruit used in Ayurvedic medicine for many purposes, from antioxidant support to cholesterol and digestion. Early research is promising for some u...
Read the full Indian Gooseberry monograph →Sources & How We Checked
Advanced Lipid Control's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 156 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Black Tea 150 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Hertog MGL, Sweetnam PM, Fehily AM, et al. Antioxidant flavonols and ischemic heart disease in a Welsh population of men: the Caerphilly Study. Am J Clin Nutr 1997;65:1489-94. PubMed
- Harder S, Fuhr U, Staib AH, Wolff T. Ciprofloxacin-caffeine: a drug interaction established using in vivo and in vitro investigations. Am J Med 1989;87:89S-91S. PubMed
- Carbo M, Segura J, De la Torre R, et al. Effect of quinolones on caffeine disposition. Clin Pharmacol Ther 1989;45:234-40. PubMed
- Healy DP, Polk RE, Kanawati L, et al. Interaction between oral ciprofloxacin and caffeine in normal volunteers. Antimicrob Agents Chemother 1989;33:474-8. PubMed
- Mester R, Toren P, Mizrachi I, et al. Caffeine withdrawal increases lithium blood levels. Biol Psychiatry 1995;37:348-50. PubMed
- Jefferson JW. Lithium tremor and caffeine intake: two cases of drinking less and shaking more. J Clin Psychiatry 1988;49:72-3.
- Lasswell WL Jr, Weber SS, Wilkins JM. In vitro interaction of neuroleptics and tricylic antidepressants with coffee, tea, and gallotannic acid. J Pharm Sci 1984;73:1056-8. PubMed
- Kulhanek F, Linde OK, Meisenberg G. Precipitation of antipsychotic drugs in interaction with coffee or tea. Lancet 1979;2:1130.
- Merhav H, Amitai Y, Palti H, Godfrey S. Tea drinking and microcytic anemia in infants. Am J Clin Nutr 1985;41:1210-3.
- Joeres R, Klinker H, Heusler H, et al. Influence of mexiletine on caffeine elimination. Pharmacol Ther 1987;33:163-9. PubMed
- Vahedi K, Domingo V, Amarenco P, Bousser MG. Ischemic stroke in a sportsman who consumed MaHuang extract and creatine monohydrate for bodybuilding. J Neurol Neurosurg Psychiatr 2000;68:112-3.
- Wakabayashi K, Kono S, Shinchi K, et al. Habitual coffee consumption and blood pressure: A study of self-defense officials in Japan. Eur J Epidemiol 1998;14:669-73. PubMed
- Hodgson JM, Puddey IB, Burke V, et al. Effects on blood pressure of drinking green and black tea. J Hypertens 1999;17:457-63. PubMed
- Rapuri PB, Gallagher JC, Kinyamu HK, Ryschon KL. Caffeine intake increases the rate of bone loss in elderly women and interacts with vitamin D receptor genotypes. Am J Clin Nutr 2001;74:694-700. PubMed
- The National Toxicology Program (NTP). Caffeine. Center for the Evaluation of Risks to Human Reproduction (CERHR). Available at: http://cerhr.niehs.nih.gov/common/caffeine.html.
- Klebanoff MA, Levine RJ, DerSimonian R, et al. Maternal serum paraxanthine, a caffeine metabolite, and the risk of spontaneous abortion. N Engl J Med 1999;341:1639-44. PubMed
- Eskenazi B. Caffeine—filtering the facts. N Engl J Med 1999;341:1688-9. PubMed
- Fernandes O, Sabharwal M, Smiley T, et al. Moderate to heavy caffeine consumption during pregnancy and relationship to spontaneous abortion and abnormal fetal growth: a meta-analysis. Reprod Toxicol 1998;12:435-44. PubMed
- Pollock BG, Wylie M, Stack JA, et al. Inhibition of caffeine metabolism by estrogen replacement therapy in postmenopausal women. J Clin Pharmacol 1999;39:936-40. PubMed
- Nurminen ML, Niittynen L, Korpela R, Vapaatalo H. Coffee, caffeine and blood pressure: a critical review. Eur J Clin Nutr 1999;53:831-9. PubMed
- Dews PB, Curtis GL, Hanford KJ, O'Brien CP. The frequency of caffeine withdrawal in a population-based survey and in a controlled, blinded pilot experiment. J Clin Pharmacol 1999;39:1221-32. PubMed
- FDA. Proposed rule: dietary supplements containing ephedrine alkaloids. Available at: www.verity.fda.gov (Accessed 25 January 2000).
- Weisburger JH. Tea and health: the underlying mechanisms. Proc Soc Exp Biol Med 1999;220:271-5. PubMed
- Briggs GB, Freeman RK, Yaffe SJ. Drugs in Pregnancy and Lactation. 5th ed. Philadelphia, PA: Lippincott Williams & Wilkins; 1998.
- Hagg S, Spigset O, Mjorndal T, Dahlqvist R. Effect of caffeine on clozapine pharmacokinetics in healthy volunteers. Br J Clin Pharmacol 2000;49:59-63. PubMed
- Watson JM, Jenkins EJ, Hamilton P, et al. Influence of caffeine on the frequency and perception of hypoglycemia in free-living patients with type 1 diabetes. Diabetes Care 2000;23:455-9. PubMed
- Lloyd T, Johnson-Rollings N, Eggli DF, et al. Bone status among postmenopausal women with different habitual caffeine intakes: a longitudinal investigation. J Am Coll Nutr 2000;19:256-61. PubMed
- American Academy of Pediatrics. The transfer of drugs and other chemicals into human milk. Pediatrics 2001;108:776-89. PubMed
- Sinclair CJ, Geiger JD. Caffeine use in sports. A pharmacological review. J Sports Med Phys Fitness 2000;40:71-9.
- Haller CA, Benowitz NL. Adverse cardiovascular and central nervous system events associated with dietary supplements containing ephedra alkaloids. N Engl J Med 2000;343:1833-8. PubMed
- Ali M, Afzal M. A potent inhibitor of thrombin stimulated platelet thromboxane formation from unprocessed tea. Prostaglandins Leukot Med 1987;27:9-13. PubMed
- Ardlie NG, Glew G, Schultz BG, Schwartz CJ. Inhibition and reversal of platelet aggregation by methyl xanthines. Thromb Diath Haemorrh 1967;18:670-3. DOI
- Olthof MR, Hollman PC, Zock PL, Katan MB. Consumption of high doses of chlorogenic acid, present in coffee, or of black tea increases plasma total homocysteine concentrations in humans. Am J Clin Nutr 2001;73:532-8. PubMed
- Hartman TJ, Tangrea JA, Pietinen P, et al. Tea and coffee consumption and risk of colon and rectal cancer in middle-aged Finnish men. Nutr Cancer 1998;31:41-8. PubMed
- Ferrini RL, Barrett-Connor E. Caffeine intake and endogenous sex steroid levels in postmenopausal women. The Rancho Bernardo Study. Am J Epidemiol 1996:144:642-4. PubMed
- Bell DG, Jacobs I, Ellerington K. Effect of caffeine and ephedrine ingestion on anaerobic exercise performance. Med Sci Sports Exerc 2001;33:1399-403. PubMed
- Horner NK, Lampe JW. Potential mechanisms of diet therapy for fibrocystic breast conditions show inadequate evidence of effectiveness. J Am Diet Assoc 2000;100:1368-80. PubMed
- Bracken MB, Triche EW, Belanger K, et al. Association of maternal caffeine consumption with decrements in fetal growth. Am J Epidemiol 2003;157:456-66.. PubMed
- Shekelle PG, Hardy ML, Morton SC, et al. Efficacy and safety of ephedra and ephedrine for weight loss and athletic performance: a meta-analysis. JAMA 2003;289:1537-45.. PubMed
- McGowan JD, Altman RE, Kanto WP Jr. Neonatal withdrawal symptoms after chronic maternal ingestion of caffeine. South Med J 1988;81:1092-4.. PubMed
- Nehlig A, Debry G. Consequences on the newborn of chronic maternal consumption of coffee during gestation and lactation: a review. J Am Coll Nutr 1994;13:6-21.. PubMed
- Massey LK. Is caffeine a risk factor for bone loss in the elderly? Am J Clin Nutr 2001;74:569-70. PubMed
- Dreher HM. The effect of caffeine reduction on sleep quality and well-being in persons with HIV. J Psychosom Res 2003;54:191-8.. PubMed
- Kockler DR, McCarthy MW, Lawson CL. Seizure activity and unresponsiveness after hydroxycut ingestion. Pharmacotherapy 2001;21:647-51.. PubMed
- Nix D, Zelenitsky S, Symonds W, et al. The effect of fluconazole on the pharmacokinetics of caffeine in young and elderly subjects. Clin Pharmacol Ther 1992;51:183. DOI
- Greenblatt DJ, von Moltke LL, Perloff ES, et al. Interaction of flurbiprofen with cranberry juice, grape juice, tea, and fluconazole: in vitro and clinical studies. Clin Pharmacol Ther 2006;79:125-33. PubMed
- Infante S, Baeza ML, Calvo M, et al. Anaphylaxis due to caffeine. Allergy 2003;58:681-2. PubMed
- Massey LK, Whiting SJ. Caffeine, urinary calcium, calcium metabolism and bone. J Nutr 1993;123:1611-4. PubMed
- Nawrot P, Jordan S, Eastwood J, et al. Effects of caffeine on human health. Food Addit Contam 2003;20:1-30. PubMed
- May DC, Jarboe CH, VanBakel AB, Williams WM. Effects of cimetidine on caffeine disposition in smokers and nonsmokers. Clin Pharmacol Ther 1982;31:656-61. PubMed
- Abernethy DR, Todd EL. Impairment of caffeine clearance by chronic use of low-dose oestrogen-containing oral contraceptives. Eur J Clin Pharmacol 1985;28:425-8. PubMed
- Brown NJ, Ryder D, Branch RA. A pharmacodynamic interaction between caffeine and phenylpropanolamine. Clin Pharmacol Ther 1991;50:363-71. PubMed
- Sanderink GJ, Bournique B, Stevens J, et al. Involvement of human CYP1A isoenzymes in the metabolism and drug interactions of riluzole in vitro. Pharmacol Exp Ther 1997;282:1465-72. DOI
- Wahllander A, Paumgartner G. Effect of ketoconazole and terbinafine on the pharmacokinetics of caffeine in healthy volunteers. Eur J Clin Pharmacol 1989;37:279-83. PubMed
- Carrillo JA, Benitez J. Clinically significant pharmacokinetic interactions between dietary caffeine and medications. Clin Pharmacokinet 2000;39:127-53. PubMed
- Underwood DA. Which medications should be held before a pharmacologic or exercise stress test? Cleve Clin J Med 2002;69:449-50. PubMed
- Aqel RA, Zoghbi GJ, Trimm JR, et al. Effect of caffeine administered intravenously on intracoronary-administered adenosine-induced coronary hemodynamics in patients with coronary artery disease. Am J Cardiol 2004;93:343-6. PubMed
- Zheng XM, Williams RC. Serum caffeine levels after 24-hour abstention: clinical implications on dipyridamole (201)Tl myocardial perfusion imaging. J Nucl Med Technol 2002;30:123-7.
- Institute of Medicine. Caffeine for the Sustainment of Mental Task Performance: Formulations for Military Operations. Washington, DC: National Academy Press, 2001. Available at: http://books.nap.edu/books/0309082587/html/index.html. DOI
- Holmgren P, Norden-Pettersson L, Ahlner J. Caffeine fatalities--four case reports. Forensic Sci Int 2004;139:71-3. PubMed
- Dews PB, O'Brien CP, Bergman J. Caffeine: behavioral effects of withdrawal and related issues. Food Chem Toxicol 2002;40:1257-61. PubMed
- Beach CA, Mays DC, Guiler RC, et al. Inhibition of elimination of caffeine by disulfiram in normal subjects and recovering alcoholics. Clin Pharmacol Ther 1986;39:265-70. PubMed
- Sato J, Nakata H, Owada E, et al. Influence of usual intake of dietary caffeine on single-dose kinetics of theophylline in healthy human subjects. Eur J Clin Pharmacol 1993;44:295-8. PubMed
- Benowitz NL, Osterloh J, Goldschlager N, et al. Massive catecholamine release from caffeine poisoning. JAMA 1982;248:1097-8. DOI
- Leson CL, McGuigan MA, Bryson SM. Caffeine overdose in an adolescent male. J Toxicol Clin Toxicol 1988;26:407-15. PubMed
- Juliano LM, Griffiths RR. A critical review of caffeine withdrawal: empirical validation of symptoms and signs, incidence, severity, and associated features. Psychopharmacology (Berl) 2004;176:1-29. PubMed
- Winkelmayer WC, Stampfer MJ, Willett WC, Curhan GC. Habitual caffeine intake and the risk of hypertension in women. JAMA 2005;294:2330-5. PubMed
- Raaska K, Raitasuo V, Laitila J, Neuvonen PJ. Effect of caffeine-containing versus decaffeinated coffee on serum clozapine concentrations in hospitalised patients. Basic Clin Pharmacol Toxicol 2004;94:13-8. DOI
- Forrest WH Jr, Bellville JW, Brown BW Jr. The interaction of caffeine with pentobarbital as a nighttime hypnotic. Anesthesiology 1972;36:37-41. PubMed
- Lake CR, Rosenberg DB, Gallant S, et al. Phenylpropanolamine increases plasma caffeine levels. Clin Pharmacol Ther 1990;47:675-85. PubMed
- Correa A, Stolley A, Liu Y. Prenatal tea consumption and risks of anencephaly and spina bifida. Ann Epidemiol 2000;10:476-7. PubMed
- Weng X, Odouli R, Li DK. Maternal caffeine consumption during pregnancy and the risk of miscarriage: a prospective cohort study. Am J Obstet Gynecol 2008;198:279.e1-8. PubMed
- Savitz DA, Chan RL, Herring AH, et al. Caffeine and miscarriage risk. Epidemiology 2008;19:55-62. PubMed
- Parker DL, Hoffmann TK, Tucker MA, et al. Interaction between warfarin and black tea. Ann Pharmacother 2009;43:150-1. PubMed
- Shet, M. S., McPhaul, M., Fisher, C. W., Stallings, N. R., and Estabrook, R. W. Metabolism of the antiandrogenic drug (Flutamide) by human CYP1A2. Drug Metab Dispos. 1997;25(11):1298-1303.
- Stille, W., Harder, S., Mieke, S., Beer, C., Shah, P. M., Frech, K., and Staib, A. H. Decrease of caffeine elimination in man during co-administration of 4-quinolones. J.Antimicrob.Chemother. 1987;20(5):729-734. PubMed
- Kot, M. and Daniel, W. A. Effect of diethyldithiocarbamate (DDC) and ticlopidine on CYP1A2 activity and caffeine metabolism: an in vitro comparative study with human cDNA-expressed CYP1A2 and liver microsomes. Pharmacol Rep. 2009;61(6):1216-1220. PubMed
- Gasior, M., Borowicz, K., Buszewicz, G., Kleinrok, Z., and Czuczwar, S. J. Anticonvulsant activity of phenobarbital and valproate against maximal electroshock in mice during chronic treatment with caffeine and caffeine discontinuation. Epilepsia 1996;37(3 PubMed
- Jankiewicz, K., Chroscinska-Krawczyk, M., Blaszczyk, B., and Czuczwar, S. J. [Caffeine and antiepileptic drugs: experimental and clinical data]. Przegl.Lek. 2007;64(11):965-967.
- Luszczki, J. J., Zuchora, M., Sawicka, K. M., Kozinska, J., and Czuczwar, S. J. Acute exposure to caffeine decreases the anticonvulsant action of ethosuximide, but not that of clonazepam, phenobarbital and valproate against pentetrazole-induced seizures i
- Chroscinska-Krawczyk, M., Jargiello-Baszak, M., Walek, M., Tylus, B., and Czuczwar, S. J. Caffeine and the anticonvulsant potency of antiepileptic drugs: experimental and clinical data. Pharmacol.Rep. 2011;63(1):12-18. PubMed
- Vaz, J., Kulkarni, C., David, J., and Joseph, T. Influence of caffeine on pharmacokinetic profile of sodium valproate and carbamazepine in normal human volunteers. Indian J.Exp.Biol. 1998;36(1):112-114.
- Gasior, M., Swiader, M., Przybylko, M., Borowicz, K., Turski, W. A., Kleinrok, Z., and Czuczwar, S. J. Felbamate demonstrates low propensity for interaction with methylxanthines and Ca2+ channel modulators against experimental seizures in mice. Eur.J Phar PubMed
- Mohiuddin, M., Azam, A. T., Amran, M. S., and Hossain, M. A. In vive effects of gliclazide and metformin on the plasma concentration of caffeine in healthy rats. Pak.J Biol Sci 5-1-2009;12(9):734-737.
- Mays, D. C., Camisa, C., Cheney, P., Pacula, C. M., Nawoot, S., and Gerber, N. Methoxsalen is a potent inhibitor of the metabolism of caffeine in humans. Clin.Pharmacol.Ther. 1987;42(6):621-626. PubMed
- Wojcikowski, J. and Daniel, W. A. Perazine at therapeutic drug concentrations inhibits human cytochrome P450 isoenzyme 1A2 (CYP1A2) and caffeine metabolism--an in vitro study. Pharmacol Rep. 2009;61(5):851-858. PubMed
- Daniel, W. A., Syrek, M., Rylko, Z., and Kot, M. Effects of phenothiazine neuroleptics on the rate of caffeine demethylation and hydroxylation in the rat liver. Pol.J Pharmacol 2001;53(6):615-621.
- Norager, C. B., Jensen, M. B., Weimann, A., and Madsen, M. R. Metabolic effects of caffeine ingestion and physical work in 75-year old citizens. A randomized, double-blind, placebo-controlled, cross-over study. Clin Endocrinol (Oxf) 2006;65(2):223-228. PubMed
- Wang, X. and Yeung, J. H. Effects of the aqueous extract from Salvia miltiorrhiza Bunge on caffeine pharmacokinetics and liver microsomal CYP1A2 activity in humans and rats. J Pharm Pharmacol 2010;62(8):1077-1083.
- Azcona O, Barbanoi MJ, Torrent J, Jane F. Evaluation of the central effects of alcohol and caffeine interaction. Br J Clin Pharmacol 1995;40:393-400. PubMed
- Harder S, Staib AH, Beer C, et al. 4-quinolones inhibit biotransformation of caffeine. Eur J Clin Pharmacol 1988;35:651-6. PubMed
- Zhang LL, Zhang JR, Guo K, et al. Effects of fluoroquinolones on CYP4501A and 3A in male broilers. Res Vet Sci 2011;90:99-105. PubMed
- Cesana M, Broccali G, Imbimbo BP, Crema A. Effect of single doses of rufloxacin on the disposition of theophylline and caffeine after single administration. Int J Clin Pharmacol Ther Toxicol 1991:29:133-8.
- Broughton LJ, Rogers HJ. Decreased systemic clearance of caffeine due to cimetidine. Br J Clin Pharmacol 1981;12:155-9. PubMed
- Kot M, Daniel WA. Caffeine as a marker substrate for testing cytochrome P450 activity in human and rat. Pharmacol Rep 2008;60:789-97.
- Kjaerstad MB, Nielsen F, Nohr-Jensen L, et al. Systemic uptake of miconazole during vaginal suppository use and effect on CYP1A2 and CYP3A4 associated enzyme activities in women. Eur J Clin Pharmacol 2010;66:1189-97. PubMed
- Goh BC, Reddy NJ, Dandamudi UB, et al. An evaluation of the drug interaction potential of pazopanib, an oral vascular endothelial growth factor receptor tyrosine kinase inhibitor, using a modified Cooperstown 5+1 cocktail in patients with advanced solid t
- Chen Y, Kang Z, Yan J, et al. Liu wei di huang wan, a well-known traditional Chinese medicine induces CYP1A2 while suppressing CYP2A6 and N-acetyltransferase 2 acivities in man. J Ethnopharmacol 2010;132:213-8.
- Suzuki S, Murayama Y, Sugiyama E, et al. Estimating pediatric doses of drugs metabolized by cytochrome P450 (CYP) isozymes, based on physiological liver development and serum protein levels. Yakugaku Zasshi 2010;130:613-20. PubMed
- Chien CF, Wu YT, Lee WC, et al. Herb-drug interaction of Andrographis paniculata extract and andrographolide on the pharmacokinetics of theophylline in rats. Chem Biol Interact 2010;184:458-65. PubMed
- Mills BM, Zaya MJ, Walters RR, et al. Current cytochrome P450 phenotyping methods applied to metabolic drug -drug interaction prediction in dogs. Drug Metab Dispos 2010;38:396-404. PubMed
- Turpault S, Brian W, Van Horn R, et al. Pharmacokinetic assessment of a five-probe cocktail for CYPs 1A2, 2C9, 2C19, 2D6, and 3A. Br J Clin Pharmacol 2009;68:928-35. PubMed
- Filimonova AA, Ziganshina LE, Ziganshin AU, Chichirov AA. On the possibility of patient phenotyping on the basis of cytochrome p-450 1A2 isoenzyme activity using caffeine as the test substrate. Eksp Klin Farmakol 2009;72:61-5.
- Jenkins J, Williams D, Deng Y, et al. Eltrombopag, an oral thrombopoietin receptor agonist, has no impact on the pharmacokinetic profile of probe drugs for cytochrome P450 isoenzymes CYP3A4, CYP1A2, CYP2C9 and CYP2C19 in healthy men: a cocktail analysis.
- Smits P, Straatman C, Pijpers E, Thien T. Dose-dependent inhibition of the hemodynamic response to dipyridamole by caffeine. Clin Pharmacol Ther 1991;50:529-37. PubMed
- Zelenitsky SA, Norman A, Nix DE. The effects of fluconazole on the pharmacokinetics of caffeine in young and elderly subjects. J Infect Dis Pharmacother 1995;1:1-11.
- Joeres R, Richter E. Mexiletine and caffeine elimination. N Engl J Med 1987;317:117. PubMed
- Jonkman JH, Sollie FA, Sauter R, Steinijans VW. The influence of caffeine on the steady-state pharmacokinetics of theophylline. Clin Pharmacol Ther 1991;49:248-55. PubMed
- Weathersbee PS, Olsen LK, Lodge JR. Caffeine and pregnancy. A retrospective survey. Postgrad Med 1977;62:64-9. PubMed
- Fortier I, Marcoux S, Beaulac-Baillargeon L. Relation of caffeine intake during pregnancy to intrauterine growth retardation and preterm birth. Am J Epidemiol 1993;137:931-40. PubMed
- Woodward, M. and Tunstall-Pedoe, H. Coffee and tea consumption in the Scottish Heart Health Study follow up: conflicting relations with coronary risk factors, coronary disease, and all cause mortality. J.Epidemiol.Community Health 1999;53(8):481-487. PubMed
- Steptoe, A., Gibson, E. L., Vuononvirta, R., Hamer, M., Wardle, J., Rycroft, J. A., Martin, J. F., and Erusalimsky, J. D. The effects of chronic tea intake on platelet activation and inflammation: a double-blind placebo controlled trial. Atherosclerosis PubMed
- Heilbrun, L. K., Nomura, A., and Stemmermann, G. N. Black tea consumption and cancer risk: a prospective study. Br.J.Cancer 1986;54(4):677-683. PubMed
- Kinlen, L. J. and McPherson, K. Pancreas cancer and coffee and tea consumption: a case-control study. Br.J.Cancer 1984;49(1):93-96. PubMed
- Smits, P., Temme, L., and Thien, T. The cardiovascular interaction between caffeine and nicotine in humans. Clin Pharmacol Ther 1993;54(2):194-204. PubMed
- Cnattingius, S., Signorello, L. B., Anneren, G., Clausson, B., Ekbom, A., Ljunger, E., Blot, W. J., McLaughlin, J. K., Petersson, G., Rane, A., and Granath, F. Caffeine intake and the risk of first-trimester spontaneous abortion. N.Engl.J.Med. 12-21-2000 PubMed
- Clausson, B., Granath, F., Ekbom, A., Lundgren, S., Nordmark, A., Signorello, L. B., and Cnattingius, S. Effect of caffeine exposure during pregnancy on birth weight and gestational age. Am.J.Epidemiol. 3-1-2002;155(5):429-436. DOI
- MacKenzie, T., Comi, R., Sluss, P., Keisari, R., Manwar, S., Kim, J., Larson, R., and Baron, J. A. Metabolic and hormonal effects of caffeine: randomized, double-blind, placebo-controlled crossover trial. Metabolism 2007;56(12):1694-1698. PubMed
- Barr, H. M. and Streissguth, A. P. Caffeine use during pregnancy and child outcome: a 7-year prospective study. Neurotoxicol.Teratol. 1991;13(4):441-448. PubMed
- Moisey, L. L., Robinson, L. E., and Graham, T. E. Consumption of caffeinated coffee and a high carbohydrate meal affects postprandial metabolism of a subsequent oral glucose tolerance test in young, healthy males. Br.J Nutr. 2010;103(6):833-841. PubMed
- Fenster, L., Eskenazi, B., Windham, G. C., and Swan, S. H. Caffeine consumption during pregnancy and fetal growth. Am.J.Public Health 1991;81(4):458-461. PubMed
- Simmonds, M. J., Minahan, C. L., and Sabapathy, S. Caffeine improves supramaximal cycling but not the rate of anaerobic energy release. Eur.J Appl Physiol 2010;109(2):287-295. PubMed
- Buscemi, S., Verga, S., Batsis, J. A., Donatelli, M., Tranchina, M. R., Belmonte, S., Mattina, A., Re, A., and Cerasola, G. Acute effects of coffee on endothelial function in healthy subjects. Eur.J Clin Nutr. 2010;64(5):483-489. PubMed
- Rigato, I., Blarasin, L., and Kette, F. Severe hypokalemia in 2 young bicycle riders due to massive caffeine intake. Clin J Sport Med. 2010;20(2):128-130. PubMed
- Banko, L. T., Haq, S. A., Rainaldi, D. A., Klem, I., Siegler, J., Fogel, J., Sacchi, T. J., and Heitner, J. F. Incidence of caffeine in serum of patients undergoing dipyridamole myocardial perfusion stress test by an intensive versus routine caffeine his
- Ernest, D., Chia, M., and Corallo, C. E. Profound hypokalaemia due to Nurofen Plus and Red Bull misuse. Crit Care Resusc. 2010;12(2):109-110. DOI
- Fenster, L., Eskenazi, B., Windham, G. C., and Swan, S. H. Caffeine consumption during pregnancy and spontaneous abortion. Epidemiology 1991;2(3):168-174. PubMed
- Clausen, T. Hormonal and pharmacological modification of plasma potassium homeostasis. Fundam.Clin Pharmacol 2010;24(5):595-605. PubMed
- Perera, V., Gross, A. S., and McLachlan, A. J. Caffeine and paraxanthine HPLC assay for CYP1A2 phenotype assessment using saliva and plasma. Biomed.Chromatogr. 2010;24(10):1136-1144. PubMed
- Orozco-Gregorio, H., Mota-Rojas, D., Bonilla-Jaime, H., Trujillo-Ortega, M. E., Becerril-Herrera, M., Hernandez-Gonzalez, R., and Villanueva-Garcia, D. Effects of administration of caffeine on metabolic variables in neonatal pigs with peripartum asphyxia PubMed
- Smits, P., Lenders, J. W., and Thien, T. Caffeine and theophylline attenuate adenosine-induced vasodilation in humans. Clin.Pharmacol.Ther. 1990;48(4):410-418. PubMed
- Caan, B. J. and Goldhaber, M. K. Caffeinated beverages and low birthweight: a case-control study. Am.J.Public Health 1989;79(9):1299-1300. PubMed
- Martin, T. R. and Bracken, M. B. The association between low birth weight and caffeine consumption during pregnancy. Am.J.Epidemiol. 1987;126(5):813-821. PubMed
- Srisuphan, W. and Bracken, M. B. Caffeine consumption during pregnancy and association with late spontaneous abortion. Am.J Obstet.Gynecol. 1986;154(1):14-20. PubMed
- Dlugosz, L., Belanger, K., Hellenbrand, K., Holford, T. R., Leaderer, B., and Bracken, M. B. Maternal caffeine consumption and spontaneous abortion: a prospective cohort study. Epidemiology 1996;7(3):250-255. PubMed
- Jeppesen, U., Loft, S., Poulsen, H. E., and Brsen, K. A fluvoxamine-caffeine interaction study. Pharmacogenetics 1996;6(3):213-222. PubMed
- Cook, D. G., Peacock, J. L., Feyerabend, C., Carey, I. M., Jarvis, M. J., Anderson, H. R., and Bland, J. M. Relation of caffeine intake and blood caffeine concentrations during pregnancy to fetal growth: prospective population based study. BMJ 11-30-1996 PubMed
- Izzo, A. A. and Ernst, E. Interactions between herbal medicines and prescribed drugs: an updated systematic review. Drugs 2009;69(13):1777-1798. PubMed
- Alemdaroglu, N. C., Dietz, U., Wolffram, S., Spahn-Langguth, H., and Langguth, P. Influence of green and black tea on folic acid pharmacokinetics in healthy volunteers: potential risk of diminished folic acid bioavailability. Biopharm.Drug Dispos. 2008;2 PubMed
- Smits, P., Corstens, F. H., Aengevaeren, W. R., Wackers, F. J., and Thien, T. False-negative dipyridamole-thallium-201 myocardial imaging after caffeine infusion. J Nucl.Med. 1991;32(8):1538-1541. DOI
- van der Hoeven N, Visser I, Schene A, van den Born BJ. Severe hypertension related to caffeinated coffee and tranylcypromine: a case report. Ann Intern Med. 2014 May 6;160(9):657-8. doi: 10.7326/L14-5009-8. No abstract available. PubMed
- Bahorun T, Luximon-Ramma A, Neergheen-Bhujun VS, Gunness TK, Googoolye K, Auger C, Crozier A, Aruoma OI. The effect of black tea on risk factors of cardiovascular disease in a normal population. Prev Med. 2012 ;54 Suppl:S98-102. PubMed
- Wikoff D, Welsh BT, Henderson R, et al. Systematic review of the potential adverse effects of caffeine consumption in healthy adults, pregnant women, adolescents, and children. Food Chem Toxicol 2017;109:585-648. PubMed
- Lin S, Xu G, Chen Z, Liu X, Li J, Ma L, Wang X. Tea drinking and the risk of esophageal cancer: focus on tea type and drinking temperature. Eur J Cancer Prev. 2020. doi: 10.1097/CEJ.0000000000000568. PubMed
- Kondo A, Narumi K, Okuhara K, et al. Black tea extract and theaflavin derivatives affect the pharmacokinetics of rosuvastatin by modulating organic anion transporting polypeptide (OATP) 2B1 activity. Biopharm Drug Dispos. 2019;40(8):302-306. PubMed
- Zheng KH, Zhu K, Wactawski-Wende J, et al. Caffeine intake from coffee and tea and invasive breast cancer incidence among postmenopausal women in the Women's Health Initiative. Int J Cancer 2021;149(12):2032-2044. PubMed
- Wang S, Li X, Yang Y, et al. Does coffee, tea and caffeine consumption reduce the risk of incident breast cancer? A systematic review and network meta-analysis. Public Health Nutr 2021;24(18):6377-6389. PubMed
- Alshabi AM, Alkahtani SA, Shaikh IA, Habeeb MS. Caffeine modulates pharmacokinetic and pharmacodynamic profiles of pioglitazone in diabetic rats: Impact on therapeutics. Saudi Med J 2021;42(2):151-160. PubMed
- Gleason JL, Sundaram R, Mitro SD, et al. Association of maternal caffeine consumption during pregnancy with child growth. JAMA Netw Open. 2022;5(10):e2239609. PubMed
Indian Gooseberry 6 references
- Sabu, M. C. and Kuttan, R. Anti-diabetic activity of medicinal plants and its relationship with their antioxidant property. J Ethnopharmacol. 2002;81(2):155-160. PubMed
- Fatima N, Pingali U, Muralidhar N. Study of pharmacodynamic interaction of Phyllanthus emblica extract with clopidogrel and ecosprin in patients with type II diabetes mellitus. Phytomedicine. 2014;21(5):579-85. PubMed
- Shanmugarajan D, Girish C, Harivenkatesh N, Chanaveerappa B, Prasanna Lakshmi NC. Antihypertensive and pleiotropic effects of Phyllanthus emblica extract as an add-on therapy in patients with essential hypertension-A randomized double-blind placebo-contro
- Akhtar MS, Ramzan A, Ali A, Ahmad M. Effect of amla fruit (Emblica officinalis Gaertn.) on blood glucose and lipid profile of normal subjects and type 2 diabetic patients. Int J Food Sci Nutr. 2011;62(6):609-16.
- Usharani P, Fatima N, Muralidhar N. Effects of Phyllanthus emblica extract on endothelial dysfunction and biomarkers of oxidative stress in patients with type 2 diabetes mellitus: a randomized, double-blind, controlled study. Diabetes Metab Syndr Obes. 20 PubMed
- Majeed M, Mundkur L, Paulose S, Nagabhushanam K. Novel Emblica officinalis extract containing ß-glucogallin vs. metformin: a randomized, open-label, comparative efficacy study in newly diagnosed type 2 diabetes mellitus patients with dyslipidemia. Food Fu
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC