
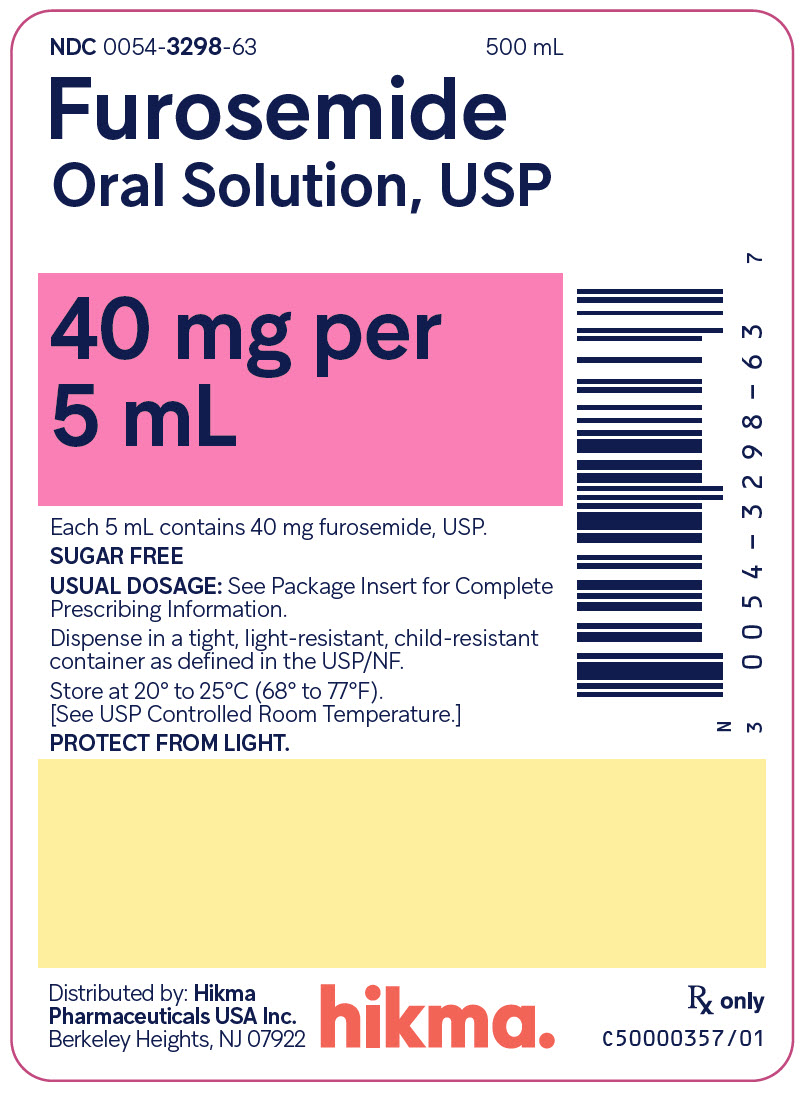
Furosemide 40 mg/5mL Solution, 500 mL — NDC 0054-3298-63 (Billing 00054-3298-63)
This is a package of 500 mL of Furosemide 40 mg/5mL Solution from Hikma Pharmaceuticals USA Inc., marketed since Apr 1987 and currently FDA-listed. It is this product's only package size.
Other active recalls for Furosemide (different manufacturers) — 2 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 008207
- GCN: 34951
- GPI-14 (Medi-Span): 37200030002045
- HICL (First Databank): 003660
- AHFS class code: 24:36.08.00
- RxCUI (RxNorm): 197730
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Loop Diuretic class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Furosemide is used alone or with other medications to treat high blood pressure. Furosemide is used to treat edema excess fluid held in body tissues caused by various medical problems. Furosemide is in a class of medications called diuretics ('water pills'). It works by causing the kidneys to get rid of unneeded water and salt from the body. High blood pressure is a common condition. When not treated, it can cause damage to the brain, heart, blood vessels, kidneys and other parts of the body. This damage may cause heart disease, a heart attack, heart failure, stroke, kidney failure, loss of vi...
Read the full MedlinePlus article ↗- It helps your body get rid of extra fluid. It is used for swelling from heart failure, liver cirrhosis and kidney disease. In adults, oral forms can also treat high blood pressure.
- Tablets and oral solution are swallowed, usually once or twice a day, or on certain days of the week if your doctor says so. Injected forms are for short-term use and are switched...
- Dizziness, stomach upset, headache and more frequent urination can happen. Call your doctor right away for ringing in the ears, hearing loss, fainting, severe weakness, little urin...
- What side effects are normal, and what should I call about?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Furosemide — tap one for details:
Furosemide may be associated with lower levels of 9 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $0.1361 | $68.05 / 500 ml |
| Medicare drug plans payPart D · Q2 2026 | $0.0727 | $36.35 / 500 ml |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00054-3298-63 You're viewing this Main listing | 500 mL in 1 BOTTLE, PLASTIC | 1987-04-22 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Furosemide 40 mg/5mLthis 00054-3298-63 | Hikma | 500 ml | — | — | FDA listed | — |
| Furosemide 40 mg/5mL 17856-3298-01 | Atlantic | 5 ml | — | — | FDA listed | — |
| Furosemide 40 mg/5mL 68094-0867-62 | Precision | 10 cups | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII BQN1B9B9HA
Potassium carbonate is a white crystalline salt made from potassium and carbonate compounds. It functions as a pH buffer and alkalizing agent in medicines, helping maintain proper acidity levels in liquid formulations.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 506T60A25R
Sorbitol is a natural sugar alcohol derived from glucose. It serves as a sweetener, humectant, and bulking agent in medications to improve taste and help maintain moisture in the product.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Edema Furosemide is indicated in adults and pediatric patients for the treatment of edema associated with congestive heart failure, cirrhosis of the liver and renal disease, including the nephrotic syndrome. Furosemide is particularly useful when an agent with greater diuretic potential is desired. Hypertension Oral furosemide may be used in adults for the treatment of hypertension alone or in combination with other antihypertensive agents.
Hypertensive patients who cannot be adequately controlled with thiazides will probably also not be adequately controlled with furosemide alone.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Edema Therapy should be individualized according to patient response to gain maximal therapeutic response and to determine the minimal dose needed to maintain that response. Adults: The usual initial dose of furosemide is 20 mg to 80 mg given as a single dose. Ordinarily a prompt diuresis ensues.
If needed, the same dose can be administered 6 to 8 hours later or the dose may be increased. The dose may be raised by 20 mg or 40 mg and given not sooner than 6 to 8 hours after the previous dose until the desired diuretic effect has been obtained. The individually determined single dose should then be given once or twice daily (e.g., at 8 am and 2 pm).
The dose of furosemide may be carefully titrated up to 600 mg/day in patients with clinically severe edematous states. Edema may be most efficiently and safely mobilized by giving furosemide on 2 to 4 consecutive days each week. When doses exceeding 80 mg/day are given for prolonged periods, careful clinical observation and laboratory monitoring are particularly advisable (See PRECAUTIONS : Laboratory Tests ).
Geriatric Patients: In general, dose selection for the elderly patient should be cautious, usually starting at the low end of the dosing range (See PRECAUTIONS : Geriatric Use ). Pediatric Patients: The usual initial dose of oral furosemide in pediatric patients is 2 mg/kg body weight, given as a single dose. If the diuretic response is not satisfactory after the initial dose, dosage may be increased by 1 or 2 mg/kg no sooner than 6 to 8 hours after the previous dose.
Doses greater than 6 mg/kg body weight are not recommended. For maintenance therapy in pediatric patients, the dose should be adjusted to the minimum effective level. Hypertension Therapy should be individualized according to the patient’s response to gain maximal therapeutic response and to determine the minimal dose needed to maintain the therapeutic response.
Adults: The usual initial dose of furosemide for hypertension is 80 mg, usually divided into 40 mg twice a day. Dosage should then be adjusted according to response. If response is not satisfactory, add other antihypertensive agents.
Changes in blood pressure must be carefully monitored when furosemide is used with other antihypertensive drugs, especially during initial therapy. To prevent excessive drop in blood pressure, the dosage of other agents should be reduced by at least 50% when furosemide is added to the regimen. As the blood pressure falls under the potentiating effect of furosemide, a further reduction in dosage or even discontinuation of other antihypertensive drugs may be necessary.
Geriatric Patients: In general, dose selection and dose adjustment for the elderly patient should be cautious, usually starting at the low end of the dosing range (See PRECAUTIONS : Geriatric Use ).
⛔ Contraindications ▾
CONTRAINDICATIONS Furosemide is contraindicated in patients with anuria and in patients with a history of hypersensitivity to furosemide.
⚠️ Warnings ▾
WARNING Furosemide is a potent diuretic which, if given in excessive amounts, can lead to a profound diuresis with water and electrolyte depletion. Therefore, careful medical supervision is required and dose and dose schedule must be adjusted to the individual patient’s needs (See DOSAGE AND ADMINISTRATION ).
WARNINGS In patients with hepatic cirrhosis and ascites, furosemide therapy is best initiated in the hospital. In hepatic coma and in states of electrolyte depletion, therapy should not be instituted until the basic condition is improved. Sudden alterations of fluid and electrolyte balance in patients with cirrhosis may precipitate hepatic coma; therefore, strict observation is necessary during the period of diuresis.
Supplemental potassium chloride and, if required, an aldosterone antagonist are helpful in preventing hypokalemia and metabolic alkalosis. If increasing azotemia and oliguria occur during treatment of severe progressive renal disease, furosemide should be discontinued. Cases of tinnitus and reversible or irreversible hearing impairment and deafness have been reported.
Reports usually indicate that furosemide ototoxicity is associated with rapid injection, severe renal impairment, the use of higher than recommended doses, hypoproteinemia or concomitant therapy with aminoglycoside antibiotics, ethacrynic acid, or other ototoxic drugs. If the physician elects to use high dose parenteral therapy, controlled intravenous infusion is advisable (for adults, an infusion rate not exceeding 4 mg furosemide per minute has been used) (See PRECAUTIONS: Drug Interactions ).
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Adverse reactions are categorized below by organ system and listed by decreasing severity. Gastrointestinal System Reactions: 1. hepatic encephalopathy in patients with hepatocellular insufficiency 2. pancreatitis 3. jaundice (intrahepatic cholestatic jaundice) 4. increased liver enzymes 5. anorexia 6. oral and gastric irritation 7. cramping 8. diarrhea 9. constipation 10. nausea 11. vomiting Systemic Hypersensitivity Reactions: 1. severe anaphylactic or anaphylactoid reactions (e.g. with shock) 2. systemic vasculitis 3. interstitial nephritis 4. necrotizing angiitis Central Nervous System Reactions: 1. tinnitus and hearing loss 2. paresthesias 3. vertigo 4. dizziness 5. headache 6. blurred vision 7. xanthopsia Hematologic Reactions: 1. aplastic anemia 2. thrombocytopenia 3. agranulocytosis 4. hemolytic anemia 5. leukopenia 6. anemia 7. eosinophilia Dermatologic-Hypersensitivity Reactions: 1. toxic epidermal necrolysis 2.
Stevens-Johnson Syndrome 3. erythema multiforme 4. drug rash with eosinophilia and systemic symptoms 5. acute generalized exanthematous pustulosis 6. exfoliative dermatitis 7. bullous pemphigoid 8. purpura 9. photosensitivity 10. rash 11. pruritus 12. urticaria Cardiovascular Reaction: 1. Orthostatic hypotension may occur and be aggravated by alcohol, barbiturates, or narcotics. 2.
Increase in cholesterol and triglyceride serum levels Other Reactions: 1. hyperglycemia 2. glycosuria 3. hyperuricemia 4. muscle spasm 5. weakness 6. restlessness 7. urinary bladder spasm 8. thrombophlebitis 9. fever Whenever adverse reactions are moderate or severe, furosemide dosage should be reduced or therapy withdrawn. To report SUSPECTED ADVERSE REACTIONS, contact Hikma Pharmaceuticals USA Inc. at 1-800-962-8364 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
Drug Interactions Furosemide may increase the ototoxic potential of aminoglycoside antibiotics, especially in the presence of impaired renal function. Except in life-threatening situations, avoid this combination. Furosemide should not be used concomitantly with ethacrynic acid because of the possibility of ototoxicity.
Patients receiving high doses of salicylates concomitantly with furosemide, as in rheumatic disease, may experience salicylate toxicity at lower doses because of competitive renal excretory sites. There is a risk of ototoxic effects if cisplatin and furosemide are given concomitantly. In addition, nephrotoxicity of nephrotoxic drugs such as cisplatin may be enhanced if furosemide is not given in lower doses and with positive fluid balance when used to achieve forced diuresis during cisplatin treatment.
Furosemide has a tendency to antagonize the skeletal muscle-relaxing effect of tubocurarine and may potentiate the action of succinylcholine. Lithium generally should not be given with diuretics because they reduce lithium’s renal clearance and add a high risk of lithium toxicity. Furosemide combined with angiotensin-converting enzyme inhibitors or angiotensin II receptor blockers may lead to severe hypotension and deterioration in renal function, including renal failure.
An interruption or reduction in the dosage of furosemide, angiotensin-converting enzyme inhibitors, or angiotensin receptor blockers may be necessary. Potentiation occurs with ganglionic or peripheral adrenergic blocking drugs. Furosemide may decrease arterial responsiveness to norepinephrine.
However, norepinephrine may still be used effectively. Simultaneous administration of sucralfate and furosemide tablets may reduce the natriuretic and antihypertensive effects of furosemide. Patients receiving both drugs should be observed closely to determine if the desired diuretic and/or antihypertensive effect of furosemide is achieved.
The intake of furosemide and sucralfate should be separated by at least two hours. In isolated cases, intravenous administration of furosemide within 24 hours of taking chloral hydrate may lead to flushing, sweating attacks, restlessness, nausea, increase in blood pressure, and tachycardia. Use of furosemide concomitantly with chloral hydrate is therefore not recommended.
Phenytoin interferes directly with renal action of furosemide. There is evidence that treatment with phenytoin leads to decreased intestinal absorption of furosemide, and consequently to lower peak serum furosemide concentrations. Methotrexate and other drugs that, like furosemide, undergo significant renal tubular secretion may reduce the effect of furosemide.
Conversely, furosemide may decrease renal elimination of other drugs that undergo tubular secretion. High-dose treatment of both furosemide and these other drugs may result in elevated serum levels of these drugs and may potentiate their toxicity as well as the toxicity of furosemide. Furosemide can increase the risk of cephalosporin-induced nephrotoxicity even in the setting of minor or transient renal impairment.
Concomitant use of cyclosporine and furosemide is associated with increased risk of gouty arthritis secondary to furosemide-induced hyperurecemia and cyclosporine impairment of renal urate excretion. High doses (>80 mg) of furosemide may inhibit the binding of thyroid hormones to carrier proteins and result in transient increase in free thyroid hormones, followed by an overall decrease in total thyroid hormone levels. One study in six subjects demonstrated that the combination of furosemide and acetylsalicylic acid temporarily reduced creatinine clearance in patients with chronic renal insufficiency.
There are case reports of patients who developed increased BUN, serum creatinine and serum potassium levels, and weight gain when furosemide was used in conjunction with NSAIDs. Literature reports indicate that coadministration of indomethacin may reduce the natriuretic and antihypertensi… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
Pregnancy Furosemide has been shown to cause unexplained maternal deaths and abortions in rabbits at 2, 4, and 8 times the maximal recommended human dose. There are no adequate and well-controlled studies in pregnant women. Furosemide should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
Treatment during pregnancy requires monitoring of fetal growth because of the potential for higher birth weights. The effects of furosemide on embryonic and fetal development and on pregnant dams were studied in mice, rats and rabbits. Furosemide caused unexplained maternal deaths and abortions in the rabbit at the lowest dose of 25 mg/kg (two times the maximal recommended human dose of 600 mg/day).
In another study, a dose of 50 mg/kg (four times the maximal recommended human dose of 600 mg/day) also caused maternal deaths and abortions when administered to rabbits between Days 12 and 17 of gestation. In a third study, none of the pregnant rabbits survived a dose of 100 mg/kg. Data from the above studies indicate fetal lethality that can precede maternal deaths.
The results of the mouse study and one of the three rabbit studies also showed an increased incidence and severity of hydronephrosis (distention of the renal pelvis and in some cases of the ureters) in fetuses derived from the treated dams as compared with the incidence in fetuses from the control group.
🧒 Pediatric Use ▾
Pediatric Use In premature infants furosemide may precipitate nephrocalcinosis/nephrolithiasis. Nephrocalcinosis/nephrolithiasis has also been observed in children under 4 years of age with no history of prematurity who have been treated chronically with furosemide. Monitor renal function, and renal ultrasonography should be considered, in pediatric patients receiving furosemide.
If furosemide is administered to premature infants during the first weeks of life, it may increase the risk of persistence of patent ductus arteriosus.
🧓 Geriatric Use ▾
Geriatric Use Controlled clinical studies of furosemide did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for the elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
This drug is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection and it may be useful to monitor renal function (See PRECAUTIONS : General and DOSAGE AND ADMINISTRATION ).
🆘 Overdosage ▾
OVERDOSAGE The principal signs and symptoms of overdose with furosemide are dehydration, blood volume reduction, hypotension, electrolyte imbalance, hypokalemia and hypochloremic alkalosis, and are extensions of its diuretic action. The acute toxicity of furosemide has been determined in mice, rats and dogs. In all three, the oral LD 50 exceeded 1000 mg/kg body weight, while the intravenous LD 50 ranged from 300 to 680 mg/kg.
The acute intragastric toxicity in neonatal rats is 7 to 10 times that of adult rats. The concentration of furosemide in biological fluids associated with toxicity or death is not known. Treatment of overdosage is supportive and consists of replacement of excessive fluid and electrolyte losses.
Serum electrolytes, carbon dioxide level and blood pressure should be determined frequently. Adequate drainage must be assured in patients with urinary bladder outlet obstruction (such as prostatic hypertrophy). Hemodialysis does not accelerate furosemide elimination.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Investigations into the mode of action of furosemide have utilized micropuncture studies in rats, stop flow experiments in dogs and various clearance studies in both humans and experimental animals. It has been demonstrated that furosemide inhibits primarily the absorption of sodium and chloride not only in the proximal and distal tubules but also in the loop of Henle. The high degree of efficacy is largely due to the unique site of action.
The action on the distal tubule is independent of any inhibitory effect on carbonic anhydrase and aldosterone. Recent evidence suggests that furosemide glucuronide is the only or at least the major biotransformation product of furosemide in man. Furosemide is extensively bound to plasma proteins, mainly to albumin.
Plasma concentrations ranging from 1 mcg/mL to 400 mcg/mL are 91% to 99% bound in healthy individuals. The unbound fraction averages 2.3% to 4.1% at therapeutic concentrations. The onset of diuresis following oral administration is within 1 hour.
The peak effect occurs within the first or second hour. The duration of diuretic effect is 6 to 8 hours. In fasted normal men, the mean bioavailability of furosemide from Furosemide Tablets and Furosemide Oral Solution is 64% and 60%, respectively, of that from an intravenous injection of the drug.
Although furosemide is more rapidly absorbed from the oral solution (50 minutes) than from the tablet (87 minutes), peak plasma levels and area under the plasma concentration-time curves do not differ significantly. Peak plasma concentrations increase with increasing dose but times-to-peak do not differ among doses. The terminal half-life of furosemide is approximately 2 hours.
Significantly more furosemide is excreted in urine following the IV injection than after the tablet or oral solution. There are no significant differences between the two oral formulations in the amount of unchanged drug excreted in urine. Geriatric Population Furosemide binding to albumin may be reduced in elderly patients.
Furosemide is predominantly excreted unchanged in the urine. The renal clearance of furosemide after intravenous administration in older healthy male subjects (60 to 70 years of age) is statistically significantly smaller than in younger healthy male subjects (20 to 35 years of age). The initial diuretic effect of furosemide in older subjects is decreased relative to younger subjects (See PRECAUTIONS : Geriatric Use ).
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Furosemide Tablets, USP 20 mg tablets are supplied as white, flat tablets with beveled edges, product identification “54 840” debossed on one side. NDC 0054-8297-25: Unit-Dose (10 x 10) NDC 0054-4297-25: Bottle of 100 Tablets NDC 0054-4297-31: Bottle of 1000 Tablets 40 mg tablets are supplied as white, flat tablets with beveled edges, scored on one side and product identification “54 583” debossed on one side. NDC 0054-8299-25: Unit-Dose (10 x 10) NDC 0054-4299-25: Bottle of 100 Tablets NDC 0054-4299-31: Bottle of 1000 Tablets 80 mg tablets are supplied as white, flat tablets with beveled edges, scored on one side and product identification “54 533” debossed on one side.
NDC 0054-8301-25: Unit-Dose (10 x 10) NDC 0054-4301-25: Bottle of 100 Tablets NDC 0054-4301-29: Bottle of 500 Tablets Store and Dispense Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Note: Dispense in a tight, light-resistant, child-resistant container as defined in the USP/NF. Exposure to light may cause slight discoloration. Discolored tablets should not be dispensed.
Protect From Moisture. PROTECT FROM LIGHT. Furosemide Oral Solution, USP 10 mg per mL oral solution is supplied as a (orange-flavored) clear, orange-colored solution.
NDC 0054-3294-46: Bottle of 60 mL Dispense only in this bottle and only with the calibrated oral syringe provided. NDC 0054-3294-50: Bottle of 120 mL Dispense only in this bottle. PROTECT FROM LIGHT.
NOTE: DISCARD OPENED BOTTLE AFTER 90 DAYS. 40 mg per 5 mL oral solution is supplied as a (pineapple-peach flavored) clear, orange-colored solution. NDC 0054-3298-63: Bottle of 500 mL Dispense in a tight, light-resistant, child-resistant container as defined in the USP/NF PROTECT FROM LIGHT.
Store and Dispense Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Distributed by: Hikma Pharmaceuticals USA Inc. Berkeley Heights, NJ 07922 C50000360/04 Revised November 2025
📋 Description ▾
DESCRIPTION Each tablet for oral administration contains: Furosemide, USP . . . . . . . . . . . . . . . . 20 mg, 40 mg and 80 mg Each mL of Oral Solution for oral administration contains: Furosemide, USP . . . . . . . . . . . . . . . . 10 mg per mL or 8 mg (40 mg per 5 mL) Furosemide is a diuretic which is an anthranilic acid derivative.
Chemically, it is 4-chloro- N -furfuryl-5-sulfamoylanthranilic acid. Furosemide is a white to slightly yellow, crystalline powder. It is practically insoluble in water; freely soluble in acetone, dimethylformamide and in solutions of alkali hydroxides; soluble in methanol; sparingly soluble in alcohol; slightly soluble in ether; very slightly soluble in chloroform.
The CAS Registry Number is 54-31-9. The structural formula is as follows: C 12 H 11 ClN 2 O 5 S M.W. 330.74 Furosemide Tablets, USP are available for oral administration containing 20 mg, 40 mg or 80 mg of Furosemide, USP.
The tablets meet Dissolution Test 1. Each tablet contains the following inactive ingredients: colloidal silicon dioxide, corn starch, lactose monohydrate, microcrystalline cellulose, pregelatinized starch, purified water, sodium lauryl sulfate, sodium starch glycolate and stearic acid. Furosemide Oral Solution, USP is also available for oral administration containing either 10 mg per mL or 40 mg per 5 mL.
The oral solution contains the following inactive ingredients: D and C Yellow No. 10, FD and C Yellow No. 6, flavors, potassium carbonate anhydrous, propylene glycol, purified water and sorbitol solution.
The 10 mg/mL solution is orange flavored and contains prosweet liquid and saccharin sodium. The 40 mg/5 mL solution is pineapple-peach flavored and contains sweet tone. furosemide structural formula image
💬 Information for Patients ▾
Information for Patients Patients receiving furosemide should be advised that they may experience symptoms from excessive fluid and/or electrolyte losses. The postural hypotension that sometimes occurs can usually be managed by getting up slowly. Potassium supplements and/or dietary measures may be needed to control or avoid hypokalemia.
Patients with diabetes mellitus should be told that furosemide may increase blood glucose levels and thereby affect urine glucose tests. The skin of some patients may be more sensitive to the effects of sunlight while taking furosemide. Hypertensive patients should avoid medications that may increase blood pressure, including over-the-counter products for appetite suppression and cold symptoms.
⚠️ Precautions ▾
PRECAUTIONS General Excessive diuresis may cause dehydration and blood volume reduction with circulatory collapse and possibly vascular thrombosis and embolism, particularly in elderly patients. As with any effective diuretic, electrolyte depletion may occur during furosemide therapy, especially in patients receiving higher doses and a restricted salt intake. Hypokalemia may develop with furosemide, especially with brisk diuresis, inadequate oral electrolyte intake, when cirrhosis is present, or during concomitant use of corticosteroids, ACTH, licorice in large amounts, or prolonged use of laxatives.
Digitalis therapy may exaggerate metabolic effects of hypokalemia, especially myocardial effects. All patients receiving furosemide therapy should be observed for these signs or symptoms of fluid or electrolyte imbalance (hyponatremia, hypochloremic alkalosis, hypokalemia, hypomagnesemia or hypocalcemia): dryness of mouth, thirst, weakness, lethargy, drowsiness, restlessness, muscle pains or cramps, muscular fatigue, hypotension, oliguria, tachycardia, arrhythmia, or gastrointestinal disturbances such as nausea and vomiting.
Increases in blood glucose and alterations in glucose tolerance tests (with abnormalities of the fasting and 2-hour postprandial sugar) have been observed, and rarely, precipitation of diabetes mellitus has been reported. In patients with severe symptoms of urinary retention (because of bladder emptying disorders, prostatic hyperplasia, urethral narrowing), the administration of furosemide can cause acute urinary retention related to increased production and retention of urine. Thus, these patients require careful monitoring, especially during the initial stages of treatment.
In patients at high risk for radiocontrast nephropathy, furosemide can lead to a higher incidence of deterioration in renal function after receiving radiocontrast compared to high-risk patients who received only intravenous hydration prior to receiving radiocontrast. In patients with hypoproteinemia (e.g., associated with nephrotic syndrome), the effect of furosemide may be weakened and its ototoxicity potentiated. Asymptomatic hyperuricemia can occur and gout may rarely be precipitated.
Patients allergic to sulfonamides may also be allergic to furosemide. The possibility exists of exacerbation or activation of systemic lupus erythematosus. As with many other drugs, patients should be observed regularly for the possible occurrence of blood dyscrasias, liver or kidney damage, or other idiosyncratic reactions.
Information for Patients Patients receiving furosemide should be advised that they may experience symptoms from excessive fluid and/or electrolyte losses. The postural hypotension that sometimes occurs can usually be managed by getting up slowly. Potassium supplements and/or dietary measures may be needed to control or avoid hypokalemia.
Patients with diabetes mellitus should be told that furosemide may increase blood glucose levels and thereby affect urine glucose tests. The skin of some patients may be more sensitive to the effects of sunlight while taking furosemide. Hypertensive patients should avoid medications that may increase blood pressure, including over-the-counter products for appetite suppression and cold symptoms.
Laboratory Tests Serum electrolytes (particularly potassium), CO 2 , creatinine and BUN should be determined frequently during the first few months of furosemide therapy and periodically thereafter. Serum and urine electrolyte determinations are particularly important when the patient is vomiting profusely or receiving parenteral fluids. Abnormalities should be corrected or the drug temporarily withdrawn.
Other medications may also influence serum electrolytes. Reversible elevations of BUN may occur and are associated with dehydration, which should be avoided, particularly in patients with renal insufficiency. Urine and blood glucose should be checked periodically in diabetics receiving furosemide, even in thos… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Because it appears in breast milk, caution should be exercised when furosemide is administered to a nursing mother. Furosemide may inhibit lactation.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility Furosemide was tested for carcinogenicity by oral administration in one strain of mice and one strain of rats. A small but significantly increased incidence of mammary gland carcinomas occurred in female mice at a dose 17.5 times the maximum human dose of 600 mg. There were marginal increases in uncommon tumors in male rats at a dose of 15 mg/kg (slightly greater than the maximum human dose) but not at 30 mg/kg.
Furosemide was devoid of mutagenic activity in various strains of Salmonella typhimurium when tested in the presence or absence of an in vitro metabolic activation system, and questionably positive for gene mutation in mouse lymphoma cells in the presence of rat liver S9 at the highest dose tested. Furosemide did not induce sister chromatid exchange in human cells in vitro , but other studies on chromosomal aberrations in human cells in vitro gave conflicting results. In Chinese hamster cells it induced chromosomal damage but was questionably positive for sister chromatid exchange.
Studies on the induction by furosemide of chromosomal aberrations in mice were inconclusive. The urine of rats treated with this drug did not induce gene conversion in Saccharomyces cerevisiae . Furosemide produced no impairment of fertility in male or female rats, at 100 mg/kg/day (the maximum effective diuretic dose in the rat and 8 times the maximal human dose of 600 mg/day).
📄 Package Label / Principal Display Panel ▾
PACKAGE/LABEL PRINCIPAL DISPLAY PANEL NDC 0054- 4297 -25 100 Tablets Furosemide Tablets, USP 20 mg Rx only Furosemide Tabs USP, 20 mg (100s) bottle label image
Package/Label Display Panel NDC 0054- 8297 -25 10x10 Unit-Dose Tablets Furosemide Tablets, USP 20 mg Rx only Furosemide Tablets USP, 20 mg (10x10 Unit-Dose Tablets) folding carton image
Package/Label Display Panel NDC 0054- 4299 -25 100 Tablets Furosemide Tablets USP 40 mg Rx only Furosemide Tablets USP, 40 mg (100s) bottle label image
Package/Label Display Panel NDC 0054- 8299 -25 10x10 Unit-Dose Tablets Furosemide Tablets, USP 40 mg Rx only Furosemide Tablets USP, 40 mg (10x10 Unit-Dose Tablets) folding carton image
Package/Label Display Panel NDC 0054- 4301 -25 100 Tablets Furosemide Tablets, USP 80 mg Rx only Furosemide Tablets USP, 80 mg (100s) bottle label image
Package/Label Display Panel NDC 0054- 8301 -25 10x10 Unit-Dose Tablets Furosemide Tablets, USP 80 mg Rx only Furosemide Tablets USP, 80 mg (10x10 Unit-Dose Tablets) folding carton image
Package/Label Display Panel NDC 0054- 3294 -46 60 mL Furosemide Oral Solution, USP 10 mg per mL SUGAR FREE USUAL DOSAGE: See Package Insert For Complete Prescribing Information. Rx only Furosemide Oral Solution USP, 10 mg per mL (60 mL) Sugar Free bottle label image
Package/Label Display Panel NDC 0054- 3294 -46 60 mL BOTTLE and SYRINGE Furosemide Oral Solution, USP 10 mg per mL Rx only Furosemide Oral Solution USP, 10 mg per mL (60 mL Bottle and Syringe) folding carton image
Package/Label Display Panel NDC 0054- 3298 -63 500 mL Furosemide Oral Solution, USP 40 mg per 5 mL Rx only Furosemide Oral Solution USP, 40 mg per 5 mL (500 mL) bottle label image
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |