
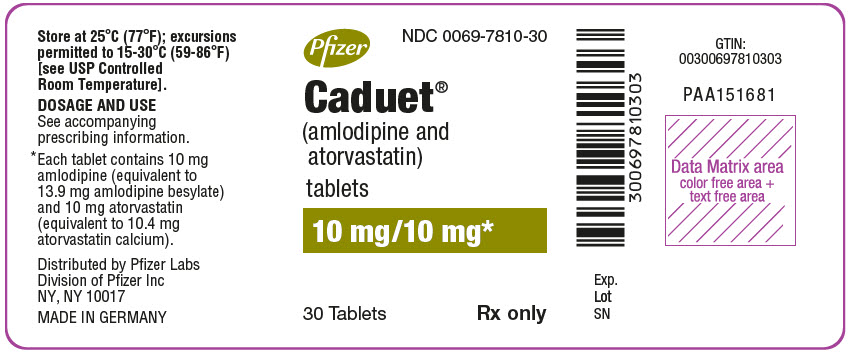
Caduet amlodipine and atorvastatin 10 mg; 10 mg Tablet, Film Coated, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Dihydropyridine Calcium Channel Blocker class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Amlodipine is used to treat high blood pressure and certain types of angina (chest pain) and coronary artery disease (narrowing of the blood vessels that supply blood to the heart). Amlodipine is in a class of medications called calcium channel blockers. It lowers blood pressure by relaxing the blood vessels so the heart does not have to pump as hard. It controls chest pain by increasing the supply of blood to the heart. If taken regularly, amlodipine controls chest pain, but it does not stop chest pain once it starts. Your doctor may prescribe a different medication to take when you have ches...
Read the full MedlinePlus article ↗- Your doctor has decided you need both a blood-pressure medicine (amlodipine) and a cholesterol-lowering medicine (atorvastatin) at the same time. Combining them into one tablet mak...
- Why am I taking two different medicines in one pill?
- You can take it at any time of day that works for you — morning, noon, or night — and you don't need food with it. Food can slightly slow how quickly atorvastatin is absorbed, but...
- Does it matter what time of day I take it, or whether I take it with food?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII H0G9379FGK
Calcium carbonate is a white mineral powder used as a filler and buffering agent in medicines. It helps give tablets their bulk and size while neutralizing stomach acid in some formulations.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII RFW2ET671P
Hydroxypropyl cellulose is a plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a film-former to coat tablets or control how fast the medicine releases.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII SA1B764746
A synthetic polymer commonly used as a solvent and binder in medicines. It helps dissolve active ingredients, improve texture, and ensure consistent tablet or capsule formation.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
13 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Amlodipine and atorvastatin 10 mg/1; 10 mg 00378-4517-93 | Mylan | 30 tablets | $0.996 | — | Availability likely | — |
| Amlodipine and Atorvastatin 10 mg/1; 10 mg 60505-3479-03 | Apotex | 30 tablets | $0.996 | AB | Availability likely | — |
| Amlodipine and Atorvastatin 10 mg/1; 10 mg 62332-0762-30 | Alembic | 30 tablets | $0.996 | AB | Availability likely | — |
| Amlodipine and Atorvastatin 10 mg/1; 10 mg 66993-0270-30 | Prasco | 30 tablets | $0.996 | AB | Availability likely | — |
| Caduet 10 mg/1; 10 mgthis 00069-7810-30 | Pfizer | 30 tablets | — | AB | FDA listed | — |
| Amlodipine besylate and Atorvastatin calcium 10 mg/1; 10 mg 43598-0321-05 | Dr. | 500 tablets | — | AB | FDA listed | — |
| Amlodipine and Atorvastatin 10 mg/1; 10 mg 46708-0762-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Amlodipine and Atorvastatin 10 mg/1; 10 mg 71335-2924-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Amlodipine and Atorvastatin 10 mg/1; 10 mg 71335-3076-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00069-7810-30 You're viewing this | 30 TABLET, FILM COATED in 1 BOTTLE (0069-7810-30) | 2022-06-06 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE CADUET (amlodipine and atorvastatin) is indicated in patients for whom treatment with both amlodipine and atorvastatin is appropriate. CADUET is a combination of amlodipine besylate, a calcium channel blocker, and atorvastatin calcium, a HMG-CoA-reductase inhibitor (statin), indicated in patients for whom treatment with both amlodipine and atorvastatin is appropriate ( 1 ). Amlodipine is indicated for the treatment of hypertension, to lower blood pressure.
Lowering blood pressure reduces the risk of fatal and non-fatal cardiovascular events, primarily strokes and myocardial infarctions. Amlodipine is indicated for the treatment of Coronary Artery Disease ( 1 ). Atorvastatin is indicated ( 1 ): • To reduce the risk of: o Myocardial infarction (MI), stroke, revascularization procedures, and angina in adults with multiple risk factors for coronary heart disease (CHD) but without clinically evident CHD. o MI and stroke in adults with type 2 diabetes mellitus with multiple risk factors for CHD but without clinically evident CHD. o Non-fatal MI, fatal and non-fatal stroke, revascularization procedures, hospitalization for congestive heart failure, and angina in adults with clinically evident CHD. • As an adjunct to diet to reduce low-density lipoprotein (LDL-C) in: o Adults with primary hyperlipidemia. o Adults and pediatric patients aged 10 years and older with heterozygous familial hypercholesterolemia (HeFH). • As an adjunct to other LDL-C-lowering therapies to reduce LDL-C in adults and pediatric patients aged 10 years and older with homozygous familial hypercholesterolemia. • As an adjunct to diet for the treatment of adults with: o Primary dysbetalipoproteinemia. o Hypertriglyceridemia.
Amlodipine Hypertension Amlodipine is indicated for the treatment of hypertension, to lower blood pressure. Lowering blood pressure reduces the risk of fatal and non-fatal cardiovascular events, primarily strokes and myocardial infarctions. These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes including amlodipine.
Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake. Many patients will require more than one drug to achieve blood pressure goals. For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program’s Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC).
Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits. The largest and most consistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality also have been seen regularly.
Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hypertension can provide substantial benefit. Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patients who are at higher risk independent of their hypertension (for example, patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to a lower blood pressure goal.
Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in black patients,…
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Usual starting dose (mg daily) Maximum dose (mg daily) Amlodipine 5 Start small adults or children, fragile, or elderly patients, or patients with hepatic insufficiency on 2.5 mg once daily ( 2 ). 10 Atorvastatin 10–20 Start patients requiring large LDL-C reduction (> 45%) at 40 mg once daily ( 2 ). 80 CADUET Dosage of CADUET must be individualized on the basis of both effectiveness and tolerance for each individual component in the treatment of hypertension/angina and hyperlipidemia.
Select doses of amlodipine and atorvastatin independently. CADUET may be substituted for its individually titrated components. Patients may be given the equivalent dose of CADUET or a dose of CADUET with increased amounts of amlodipine, atorvastatin, or both for additional antianginal effects, blood pressure lowering, or lipid-lowering effect.
CADUET may be used to provide additional therapy for patients already on one of its components. CADUET may be used to initiate treatment in patients with hyperlipidemia and either hypertension or angina. Important Dosage Information Take CADUET orally once daily at any time of the day, with or without food.
Amlodipine The usual initial antihypertensive oral dosage of amlodipine is 5 mg once daily, and the maximum dose is 10 mg once daily. Pediatric (age > 6 years), small adult, fragile, or elderly patients, or patients with hepatic insufficiency may be started on 2.5 mg once daily and this dose may be used when adding amlodipine to other antihypertensive therapy. Adjust dosage according to blood pressure goals.
In general, wait 7 to 14 days between titration steps. Titration may proceed more rapidly, however, if clinically warranted, provided the patient is assessed frequently. Angina The recommended dosage of amlodipine for chronic stable or vasospastic angina is 5–10 mg, with the lower dose suggested in the elderly and in patients with hepatic insufficiency.
Most patients will require 10 mg for adequate effect. Coronary Artery Disease The recommended dosage range of amlodipine for patients with CAD is 5–10 mg once daily. In clinical studies, the majority of patients required 10 mg [see Clinical Studies (14.4) ] .
Pediatrics The effective antihypertensive oral dose of amlodipine in pediatric patients ages 6–17 years is 2.5 mg to 5 mg once daily. Doses in excess of 5 mg daily have not been studied in pediatric patients [see Clinical Pharmacology (12.3) and Clinical Studies (14.1) ]. Atorvastatin Assess LDL-C when clinically appropriate, as early as 4 weeks after initiating atorvastatin, and adjust the dosage if necessary. Recommended Dosage in Adult Patients The recommended starting dosage of atorvastatin is 10 mg to 20 mg once daily.
The dosage range is 10 mg to 80 mg once daily. Patients who require reduction in LDL-C greater than 45% may be started at 40 mg once daily. Recommended Dosage in Pediatric Patients 10 Years of Age and Older with H e FH The recommended starting dosage of atorvastatin is 10 mg once daily.
The dosage range is 10 mg to 20 mg once daily. Recommended Dosage in Pediatric Patients 10 Years of Age and Older with HoFH The recommended starting dosage of atorvastatin is 10 mg to 20 mg once daily. The dosage range is 10 mg to 80 mg once daily.
Dosage Modifications Due to Drug Interactions Concomitant use of atorvastatin with the following drugs requires dosage modification of atorvastatin [see Warnings and Precautions (5.1) and Drug Interactions (7.1) ]. Anti-Viral Medications • In patients taking saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, fosamprenavir plus ritonavir, elbasvir plus grazoprevir or letermovir, do not exceed atorvastatin 20 mg once daily. • In patients taking nelfinavir, do not exceed atorvastatin 40 mg once daily. Select Azole Antifungals or Macrolide Antibiotics • In patients taking clarithromycin or itraconazole, do not exceed atorvastatin 20 mg once daily.
For additional recommendations regarding concomitant use…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS CADUET tablets are formulated for oral administration in the following strength combinations: Atorvastatin (mg) 10 20 40 80 Amlodipine (mg) 5 X X X X 10 X X X X Combinations of atorvastatin with 5 mg amlodipine are film-coated white tablets and combinations of atorvastatin with 10 mg amlodipine are film-coated blue tablets. Tablets contain amlodipine besylate equivalent to amlodipine 5 or 10 mg and atorvastatin calcium equivalent to atorvastatin 10, 20, 40, or 80 mg ( 3 ).
⛔ Contraindications ▾
4 CONTRAINDICATIONS • Acute liver failure or decompensated cirrhosis [see Warnings and Precautions (5.3) ] . • Hypersensitivity to amlodipine, atorvastatin or any excipients in CADUET. Hypersensitivity reactions, including anaphylaxis, angioneurotic edema, erythema multiforme, Stevens-Johnson syndrome, and toxic epidermal necrolysis, have been reported [see Adverse Reactions (6.2) ] . • Acute liver failure or decompensated cirrhosis ( 4 ). • Hypersensitivity to amlodipine, atorvastatin or any excipient in CADUET ( 4 ).
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Myopathy and Rhabdomyolysis: Risk factors include age 65 years or greater, uncontrolled hypothyroidism, renal impairment, concomitant use with certain other drugs, and higher CADUET dosage. Discontinue CADUET if markedly elevated CK levels occur or myopathy is diagnosed or suspected. Temporarily discontinue CADUET in patients experiencing an acute or serious condition at high risk of developing renal failure secondary to rhabdomyolysis.
Inform patients of the risk of myopathy and rhabdomyolysis when starting or increasing CADUET dosage. Instruct patients to promptly report unexplained muscle pain, tenderness, or weakness, particularly if accompanied by malaise or fever ( 2 , 5.1 , 7.3 , 8.5 , 8.6 ). • Immune-Mediated Necrotizing Myopathy (IMNM): Rare reports of IMNM, an autoimmune myopathy, have been reported with statin use. Discontinue CADUET if IMNM is suspected ( 5.2 ). • Hepatic Dysfunction: Increases in serum transaminases have occurred, some persistent.
Rare reports of fatal and non-fatal hepatic failure have occurred. Consider testing liver enzymes before initiating therapy and as clinically indicated thereafter. If serious hepatic injury with clinical symptoms and/or hyperbilirubinemia or jaundice occurs, promptly discontinue CADUET ( 5.3 ). • Angina or myocardial infarction may occur with initiation or dose increase ( 5.4 ) • Symptomatic hypotension is possible, particularly in patients with severe aortic stenosis.
However, acute hypotension is unlikely ( 5.5 ).
5.1Myopathy and Rhabdomyolysis CADUET may cause myopathy (muscle pain, tenderness, or weakness associated with elevated creatine kinase [CK] ) and rhabdomyolysis. Acute kidney injury secondary to myoglobinuria and rare fatalities have occurred as a result of rhabdomyolysis in patients treated with statins, including CADUET. Risk Factors for Myopathy Risk factors for myopathy include age 65 years or greater, uncontrolled hypothyroidism, renal impairment, concomitant use with certain other drugs (including other lipid-lowering therapies), and higher CADUET dosage [see Drug Interactions (7.3) and Use in Specific Populations ( 8.5 , 8.6 )].
Steps to Prevent or Reduce the Risk of Myopathy and Rhabdomyolysis CADUET exposure may be increased by drug interactions due to inhibition of cytochrome P450 enzyme 3A4 (CYP3A4) and/or transporters (e.g., breast cancer resistant protein [BCRP], organic anion-transporting polypeptide [OATP1B1/OATP1B3] and P-glycoprotein [P-gp]), resulting in an increased risk of myopathy and rhabdomyolysis. Concomitant use of cyclosporine, gemfibrozil, tipranavir plus ritonavir or glecaprevir plus pibrentasvir with CADUET is not recommended.
CADUET dosage modifications are recommended for patients taking certain anti-viral, azole antifungals, or macrolide antibiotic medications [see Dosage and Administration (2) ] . Cases of myopathy/rhabdomyolysis have been reported with atorvastatin co-administered with lipid modifying doses ( > 1 gram/day) of niacin, fibrates, colchicine, and ledipasvir plus sofosbuvir [see Adverse Reactions (6.1) ] . Consider if the benefit of use of these products outweighs the increased risk of myopathy and rhabdomyolysis [see Drug Interactions (7.3) ] .
Concomitant intake of large quantities, more than 1.2 liters daily, of grapefruit juice is not recommended in patients taking CADUET [see Drug Interactions (7.3) ] . Discontinue CADUET if markedly elevated CK levels occur or if myopathy is either diagnosed or suspected. Muscle symptoms and CK elevations may resolve if CADUET is discontinued.
Temporarily discontinue CADUET in patients experiencing an acute or serious condition at high risk of developing renal failure secondary to rhabdomyolysis (e.g., sepsis; shock; severe hypovolemia; major surgery; trauma; severe metabolic, endocrine, or electrolyte disorders; or uncontrolled epilepsy). Inform patients of the risk of myopathy and rhabdomyolysis when starting or increasing the CADUET dosage.…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following important adverse reactions are described below and elsewhere in the labeling: • Myopathy and Rhabdomyolysis [see Warnings and Precautions (5.1) ] • Immune-Mediated Necrotizing Myopathy [see Warnings and Precautions (5.2) ] • Hepatic Dysfunction [see Warnings and Precautions (5.3) ] • Increases in HbA1c and Fasting Serum Glucose Levels [see Warnings and Precautions (5.6) ] Most common adverse reaction to amlodipine is edema which occurred in a dose related manner ( 6.1 ). Most common adverse reactions (incidence ≥ 5%) are nasopharyngitis, arthralgia, diarrhea, pain in extremity, and urinary tract infection to atorvastatin ( 6.1 ).
To report SUSPECTED ADVERSE REACTIONS, contact Pfizer Inc. at 1-800-438-1985 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions,the adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. CADUET CADUET (amlodipine/atorvastatin) has been evaluated for safety in 1092 patients in double-blind placebo-controlled studies treated for co-morbid hypertension and dyslipidemia. In general, treatment with CADUET was well tolerated.
For the most part, adverse reactions have been mild or moderate in severity. In clinical trials with CADUET, no adverse reactions peculiar to this combination have been observed. Adverse reactions are similar in terms of nature, severity, and frequency to those reported previously with amlodipine and atorvastatin.
The following information is based on the clinical experience with amlodipine and atorvastatin. Amlodipine Amlodipine has been evaluated for safety in more than 11,000 patients in U.S. and foreign clinical trials. In general, treatment with amlodipine was well tolerated at doses up to 10 mg daily.
Most adverse reactions reported during therapy with amlodipine were of mild or moderate severity. In controlled clinical trials directly comparing amlodipine (N=1730) at doses up to 10 mg to placebo (N=1250), discontinuation of amlodipine because of adverse reactions was required in only about 1.5% of patients and was not significantly different from placebo (about 1%). The most commonly reported side effects more frequent than placebo are dizziness and edema.
The incidence (%) of side effects that occurred in a dose related manner are as follows: Amlodipine 2.5 mg 5 mg 10 mg Placebo N=275 N=296 N=268 N=520 Edema 1.8 3.0 10.8
0.6Dizziness 1.1 3.4 3.4
1.5Flushing 0.7 1.4 2.6
0.0Palpitations 0.7 1.4 4.5
0.6Other adverse reactions that were not clearly dose related but were reported at an incidence greater than 1.0% in placebo-controlled clinical trials include the following: Amlodipine (%) Placebo (%) (N=1730) (N=1250) Fatigue 4.5
2.8Nausea 2.9
1.9Abdominal Pain 1.6
0.3Somnolence 1.4
0.6Edema, flushing, palpitations, and somnolence appear to be more common in women than in men. The following events occurred in < 1% but > 0.1% of patients treated with amlodipine in controlled clinical trials or under conditions of open trials or marketing experience where a causal relationship is uncertain; they are listed to alert the physician to a possible relationship: Cardiovascular: arrhythmia (including ventricular tachycardia and atrial fibrillation), bradycardia, chest pain, peripheral ischemia, syncope, tachycardia, vasculitis.
Central and Peripheral Nervous System: hypoesthesia, neuropathy peripheral, paresthesia, tremor, vertigo. Gastrointestinal: anorexia, constipation, dysphagia, diarrhea, flatulence, pancreatitis, vomiting, gingival hyperplasia. General: allergic reaction, asthenia, 2 back pain, hot flushes, malaise, pain, rigors, weight gain, weight decrease.
Musculoskeletal System: arthralgia, arthrosis, muscle cramps, 2 myalgia. Psychiatric: sexual dysfunction (male 2 and female), insomnia, nervousness, depres…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Data from a drug-drug interaction study involving 10 mg of amlodipine and 80 mg of atorvastatin in healthy subjects indicate that the pharmacokinetics of amlodipine are not altered when the drugs are co-administered. The effect of amlodipine on the pharmacokinetics of atorvastatin showed no effect on the C max : 91% (90% confidence interval: 80 to 103%), but the AUC of atorvastatin increased by 18% (90% confidence interval: 109 to 127%) in the presence of amlodipine, which is not clinically meaningful.
No drug interaction studies have been conducted with CADUET and other drugs, although studies have been conducted in the individual amlodipine and atorvastatin components, as described below: • See full prescribing information for details regarding concomitant use of CADUET with other drugs or grapefruit juice that increase the risk of myopathy and rhabdomyolysis ( 2.5 , 7.3 ). • Rifampin: May reduce atorvastatin plasma concentrations. Administer simultaneously with atorvastatin ( 7.4 ). • Oral Contraceptives: May increase plasma levels of norethindrone and ethinyl estradiol; consider this effect when selecting an oral contraceptive ( 7.5 ). • Digoxin: May increase digoxin plasma levels; monitor patients appropriately ( 7.5 ).
Amlodipine
7.1Impact of Other Drugs on Amlodipine CYP3A Inhibitors Co-administration with CYP3A inhibitors (moderate and strong) results in increased systemic exposure to amlodipine and may require dose reduction. Monitor for symptoms of hypotension and edema when amlodipine is co-administered with CYP3A inhibitors to determine the need for dose adjustment [see Clinical Pharmacology (12.3) ] . CYP3A Inducers No information is available on the quantitative effects of CYP3A inducers on amlodipine.
Blood pressure should be closely monitored when amlodipine is co-administered with CYP3A inducers. Sildenafil Monitor for hypotension when sildenafil is co-administered with amlodipine [see Clinical Pharmacology (12.2) ] .
7.2Impact of Amlodipine on Other Drugs Immunosuppressants Amlodipine may increase the systemic exposure of cyclosporine or tacrolimus when co-administered. Frequent monitoring of trough blood levels of cyclosporine and tacrolimus is recommended and adjust the dose when appropriate [see Clinical Pharmacology (12.3) ] . Atorvastatin
7.3Drug Interactions that may Increase the Risk of Myopathy and Rhabdomyolysis with Atorvastatin Atorvastatin is a substrate of CYP3A4 and transporters (e.g., OATP1B1/1B3, P-gp, or BCRP). Atorvastatin plasma levels can be significantly increased with concomitant administration of inhibitors of CYP3A4 and transporters. Table 3 includes a list of drugs that may increase exposure to atorvastatin and may increase the risk of myopathy and rhabdomyolysis when used concomitantly and instructions for preventing or managing them [see Warnings and Precautions (5.1) and Clinical Pharmacology (12.3) ].
Table 3. Drug Interactions that may Increase the Risk of Myopathy and Rhabdomyolysis with Atorvastatin Cyclosporine or Gemfibrozil Clinical Impact: Atorvastatin plasma levels were significantly increased with concomitant administration of atorvastatin and cyclosporine, an inhibitor of CYP3A4 and OATP1B1 [see Clinical Pharmacology (12.3) ]. Gemfibrozil may cause myopathy when given alone.
The risk of myopathy and rhabdomyolysis is increased with concomitant use of cyclosporine or gemfibrozil with atorvastatin. Intervention: Concomitant use of cyclosporine or gemfibrozil with atorvastatin is not recommended. Anti-Viral Medications Clinical Impact: Atorvastatin plasma levels were significantly increased with concomitant administration of atorvastatin with many anti-viral medications, which are inhibitors of CYP3A4 and/or transporters (e.g., BCRP, OATP1B1/1B3, P-gp, MRP2, and/or OAT2) [see Clinical Pharmacology (12.3) ].
Cases of myopathy and rhabdomyolysis have been reported with concomitant use of ledipasvir plus sofosbuvir with atorvastatin. Intervention: • Conc…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Pregnancy: May cause fetal harm ( 8.1 ). • Lactation: Breastfeeding not recommended during treatment with CADUET ( 8.2 ).
8.1Pregnancy Risk Summary Atorvastatin Discontinue atorvastatin when pregnancy is recognized. Alternatively, consider the ongoing therapeutic needs of the individual patient. Atorvastatin decreases synthesis of cholesterol and possibly other biologically active substances derived from cholesterol; therefore, atorvastatin may cause fetal harm when administered to pregnant patients based on the mechanism of action [see Clinical Pharmacology (12.1) ] .
In addition, treatment of hyperlipidemia is not generally necessary during pregnancy. Atherosclerosis is a chronic process and the discontinuation of lipid-lowering drugs during pregnancy should have little impact on the outcome of long-term therapy of primary hyperlipidemia for most patients. Available data from case series and prospective and retrospective observational cohort studies over decades of use with statins in pregnant women have not identified a drug-associated risk of major congenital malformations.
Published data from prospective and retrospective observational cohort studies with atorvastatin use in pregnant women are insufficient to determine if there is a drug-associated risk of miscarriage (see Data ). In animal reproduction studies, no adverse developmental effects were observed in pregnant rats or rabbits orally administered atorvastatin at doses that resulted in up to 30 and 20 times, respectively, the human exposure at the maximum recommended human dose (MRHD) of 80 mg, based on body surface area (mg/m 2 ).
In rats administered atorvastatin during gestation and lactation, decreased postnatal growth and development delay were observed at doses ≥ 6 times the MRHD (see Data ). Amlodipine The limited available data based on postmarketing reports with amlodipine use in pregnant women are not sufficient to inform a drug-associated risk for major birth defects and miscarriage. There are risks to the mother and fetus associated with poorly controlled hypertension in pregnancy (see Clinical Considerations ) .
In animal reproduction studies, there was no evidence of adverse developmental effects when pregnant rats and rabbits were treated orally with amlodipine maleate during organogenesis at doses approximately 10 and 20-times MRHD, respectively. However for rats, litter size was significantly decreased (by about 50%) and the number of intrauterine deaths was significantly increased (about 5-fold). Amlodipine has been shown to prolong both the gestation period and the duration of labor in rats at this dose (see Data ) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section and post-partum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly.
Data Human Data Atorvastatin A Medicaid cohort linkage study of 1152 statin-exposed pregnant women compared to 886,996 controls did not find a significant teratogenic effect from maternal use of statins in the first trimester of pregnancy, after adjusting for potential confounders–including maternal age, diabetes mellitus, hypertension, obesity, and alcohol and tobacco use – using propensity score-based methods. The relative risk of congenital malformations between the grou…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Atorvastatin Discontinue atorvastatin when pregnancy is recognized. Alternatively, consider the ongoing therapeutic needs of the individual patient. Atorvastatin decreases synthesis of cholesterol and possibly other biologically active substances derived from cholesterol; therefore, atorvastatin may cause fetal harm when administered to pregnant patients based on the mechanism of action [see Clinical Pharmacology (12.1) ] .
In addition, treatment of hyperlipidemia is not generally necessary during pregnancy. Atherosclerosis is a chronic process and the discontinuation of lipid-lowering drugs during pregnancy should have little impact on the outcome of long-term therapy of primary hyperlipidemia for most patients. Available data from case series and prospective and retrospective observational cohort studies over decades of use with statins in pregnant women have not identified a drug-associated risk of major congenital malformations.
Published data from prospective and retrospective observational cohort studies with atorvastatin use in pregnant women are insufficient to determine if there is a drug-associated risk of miscarriage (see Data ). In animal reproduction studies, no adverse developmental effects were observed in pregnant rats or rabbits orally administered atorvastatin at doses that resulted in up to 30 and 20 times, respectively, the human exposure at the maximum recommended human dose (MRHD) of 80 mg, based on body surface area (mg/m 2 ).
In rats administered atorvastatin during gestation and lactation, decreased postnatal growth and development delay were observed at doses ≥ 6 times the MRHD (see Data ). Amlodipine The limited available data based on postmarketing reports with amlodipine use in pregnant women are not sufficient to inform a drug-associated risk for major birth defects and miscarriage. There are risks to the mother and fetus associated with poorly controlled hypertension in pregnancy (see Clinical Considerations ) .
In animal reproduction studies, there was no evidence of adverse developmental effects when pregnant rats and rabbits were treated orally with amlodipine maleate during organogenesis at doses approximately 10 and 20-times MRHD, respectively. However for rats, litter size was significantly decreased (by about 50%) and the number of intrauterine deaths was significantly increased (about 5-fold). Amlodipine has been shown to prolong both the gestation period and the duration of labor in rats at this dose (see Data ) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section and post-partum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly.
Data Human Data Atorvastatin A Medicaid cohort linkage study of 1152 statin-exposed pregnant women compared to 886,996 controls did not find a significant teratogenic effect from maternal use of statins in the first trimester of pregnancy, after adjusting for potential confounders–including maternal age, diabetes mellitus, hypertension, obesity, and alcohol and tobacco use – using propensity score-based methods. The relative risk of congenital malformations between the group with statin use and the group with no statin use in the first trimester was 1.07 (95% confidence interval 0.85 to 1.37) after controlling for confounder…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of CADUET have not been established in pediatric populations. Amlodipine Amlodipine (2.5 to 5 mg daily) is effective in lowering blood pressure in patients 6 to 17 years [see Clinical Studies (14.1) ] . The effect of amlodipine on blood pressure in patients less than 6 years of age is not known.
Atorvastatin The safety and effectiveness of atorvastatin as an adjunct to diet to reduce LDL-C have been established in pediatric patients 10 years of age and older with HeFH. Use of atorvastatin for this indication is based on a double-blind, placebo-controlled clinical trial in 187 pediatric patients 10 years of age and older with HeFH. In this limited controlled trial, there was no significant effect on growth or sexual maturation in the males or females, or on menstrual cycle length in females.
The safety and effectiveness of atorvastatin as an adjunct to other LDL-C-lowering therapies to reduce LDL-C have been established in pediatric patients 10 years of age and older with HoFH. Use of CADUET for this indication is based on a trial without a concurrent control group in 8 pediatric patients 10 years of age and older with HoFH [see Clinical Studies (14) ] . The safety and effectiveness of atorvastatin have not been established in pediatric patients younger than 10 years of age with HeFH or HoFH, or in pediatric patients with other types of hyperlipidemia (other than HeFH or HoFH).
🧓 Geriatric Use ▾
8.5Geriatric Use Safety and effectiveness of CADUET have not been established in geriatric populations. Amlodipine Clinical studies of amlodipine did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients.
In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy. Elderly patients have decreased clearance of amlodipine with a resulting increase of AUC of approximately 40–60%, and a lower initial dose may be required [see Dosage and Administration (2) ] . Atorvastatin Of the total number of atorvastatin-treated patients in clinical trials, 15813 (40%) were ≥ 65 years old and 2800 (7%) were ≥ 75 years old.
No overall differences in safety or effectiveness were observed between these patients and younger patients. Advanced age (≥65 years) is a risk factor for atorvastatin -associated myopathy and rhabdomyolysis. Dose selection for an elderly patient should be cautious, recognizing the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy and the higher risk of myopathy.
Monitor geriatric patients receiving CADUET for the increased risk of myopathy [see Warnings and Precautions (5.1) and Clinical Pharmacology (12.3 ) ].
🆘 Overdosage ▾
10 OVERDOSAGE There is no information on overdosage with CADUET in humans. Amlodipine Overdosage might be expected to cause excessive peripheral vasodilation with marked hypotension and possibly a reflex tachycardia. In humans, experience with intentional overdosage of amlodipine is limited.
Single oral doses of amlodipine maleate equivalent to 40 mg amlodipine/kg and 100 mg amlodipine/kg in mice and rats, respectively, caused deaths. Single oral amlodipine maleate doses equivalent to 4 or more mg amlodipine/kg or higher in dogs (11 or more times the MRHD on a mg/m 2 basis) caused a marked peripheral vasodilation and hypotension. If overdose should occur with amlodipine, initiate active cardiac and respiratory monitoring.
Perform frequent blood pressure measurements. Should hypotension occur, provide cardiovascular support including elevation of the extremities and administration of fluids. If hypotension remains unresponsive to these conservative measures, consider administration of vasopressors (such as phenylephrine) with specific attention to circulating volume and urine output.
As amlodipine is highly protein bound, hemodialysis is not likely to be of benefit. Atorvastatin No specific antidotes for atorvastatin are known. Contact Poison Control (1-800-222-1222) for latest recommendations.
Due to extensive drug binding to plasma proteins, hemodialysis is not expected to significantly enhance atorvastatin clearance.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action CADUET is a combination of two drugs, a dihydropyridine calcium channel blocker (amlodipine) and an HMG-CoA reductase inhibitor (atorvastatin). The amlodipine component of CADUET inhibits the transmembrane influx of calcium ions into vascular smooth muscle and cardiac muscle. The atorvastatin component of CADUET is a selective, competitive inhibitor of HMG-CoA reductase, the rate-limiting enzyme that converts 3-hydroxy-3-methylglutaryl-coenzyme A to mevalonate, a precursor of sterols, including cholesterol.
Amlodipine Amlodipine binds to both dihydropyridine and nondihydropyridine binding sites. The contractile processes of cardiac muscle and vascular smooth muscle are dependent upon the movement of extracellular calcium ions into these cells through specific ion channels. Amlodipine inhibits calcium ion influx across cell membranes selectively, with a greater effect on vascular smooth muscle cells than on cardiac muscle cells.
Negative inotropic effects can be detected in vitro but such effects have not been seen in intact animals at therapeutic doses. Serum calcium concentration is not affected by amlodipine. Amlodipine is a peripheral arterial vasodilator that acts directly on vascular smooth muscle to cause a reduction in peripheral vascular resistance and reduction in blood pressure.
The precise mechanisms by which amlodipine relieves angina have not been fully delineated, but are thought to include the following: Exertional Angina: In patients with exertional angina, amlodipine reduces the total peripheral resistance (afterload) against which the heart works and reduces the rate pressure product, and thus myocardial oxygen demand, at any given level of exercise. Vasospastic Angina: Amlodipine has been demonstrated to block constriction and restore blood flow in coronary arteries and arterioles in response to calcium, potassium epinephrine, serotonin, and thromboxane A2 analog in experimental animal models and in human coronary vessels in vitro .
This inhibition of coronary spasm is responsible for the effectiveness of amlodipine in vasospastic (Prinzmetal's or variant) angina. Atorvastatin Atorvastatin is a selective, competitive inhibitor of HMG-CoA reductase, the rate-limiting enzyme that converts 3-hydroxy-3-methylglutaryl-coenzyme A to mevalonate, a precursor of sterols, including cholesterol. In animal models, atorvastatin lowers plasma cholesterol and lipoprotein levels by inhibiting HMG-CoA reductase and cholesterol synthesis in the liver and by increasing the number of hepatic LDL receptors on the cell surface to enhance uptake and catabolism of LDL; atorvastatin also reduces LDL production and the number of LDL particles.
12.2Pharmacodynamics Amlodipine Following administration of therapeutic doses to patients with hypertension, amlodipine produces vasodilation resulting in a reduction of supine and standing blood pressures. These decreases in blood pressure are not accompanied by a significant change in heart rate or plasma catecholamine levels with chronic dosing. Although the acute intravenous administration of amlodipine decreases arterial blood pressure and increases heart rate in hemodynamic studies of patients with chronic stable angina, chronic oral administration of amlodipine in clinical trials did not lead to clinically significant changes in heart rate or blood pressures in normotensive patients with angina.
With chronic once daily oral administration, antihypertensive effectiveness is maintained for at least 24 hours. Plasma concentrations correlate with effect in both young and elderly patients. The magnitude of reduction in blood pressure with amlodipine is also correlated with the height of pretreatment elevation; thus, individuals with moderate hypertension (diastolic pressure 105–114 mmHg) had about a 50% greater response than patients with mild hypertension (diastolic pressure 90–104 mmHg).
Normotensive subjects experienced no clinically signi…
🧬 Mechanism of Action ▾
12.1Mechanism of Action CADUET is a combination of two drugs, a dihydropyridine calcium channel blocker (amlodipine) and an HMG-CoA reductase inhibitor (atorvastatin). The amlodipine component of CADUET inhibits the transmembrane influx of calcium ions into vascular smooth muscle and cardiac muscle. The atorvastatin component of CADUET is a selective, competitive inhibitor of HMG-CoA reductase, the rate-limiting enzyme that converts 3-hydroxy-3-methylglutaryl-coenzyme A to mevalonate, a precursor of sterols, including cholesterol.
Amlodipine Amlodipine binds to both dihydropyridine and nondihydropyridine binding sites. The contractile processes of cardiac muscle and vascular smooth muscle are dependent upon the movement of extracellular calcium ions into these cells through specific ion channels. Amlodipine inhibits calcium ion influx across cell membranes selectively, with a greater effect on vascular smooth muscle cells than on cardiac muscle cells.
Negative inotropic effects can be detected in vitro but such effects have not been seen in intact animals at therapeutic doses. Serum calcium concentration is not affected by amlodipine. Amlodipine is a peripheral arterial vasodilator that acts directly on vascular smooth muscle to cause a reduction in peripheral vascular resistance and reduction in blood pressure.
The precise mechanisms by which amlodipine relieves angina have not been fully delineated, but are thought to include the following: Exertional Angina: In patients with exertional angina, amlodipine reduces the total peripheral resistance (afterload) against which the heart works and reduces the rate pressure product, and thus myocardial oxygen demand, at any given level of exercise. Vasospastic Angina: Amlodipine has been demonstrated to block constriction and restore blood flow in coronary arteries and arterioles in response to calcium, potassium epinephrine, serotonin, and thromboxane A2 analog in experimental animal models and in human coronary vessels in vitro .
This inhibition of coronary spasm is responsible for the effectiveness of amlodipine in vasospastic (Prinzmetal's or variant) angina. Atorvastatin Atorvastatin is a selective, competitive inhibitor of HMG-CoA reductase, the rate-limiting enzyme that converts 3-hydroxy-3-methylglutaryl-coenzyme A to mevalonate, a precursor of sterols, including cholesterol. In animal models, atorvastatin lowers plasma cholesterol and lipoprotein levels by inhibiting HMG-CoA reductase and cholesterol synthesis in the liver and by increasing the number of hepatic LDL receptors on the cell surface to enhance uptake and catabolism of LDL; atorvastatin also reduces LDL production and the number of LDL particles.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING CADUET ® tablets contain amlodipine besylate and atorvastatin calcium equivalent to amlodipine and atorvastatin in the dose strengths described below. CADUET tablets are differentiated by tablet color/size and are engraved with a unique number on one side. Combinations of atorvastatin with 5 mg amlodipine are oval and film-coated white tablets and combinations of atorvastatin with 10 mg amlodipine are oval and are film-coated blue tablets.
CADUET tablets are supplied for oral administration in the following strengths and package configurations: Table 16. CADUET Packaging Configurations CADUET Package Configuration Tablet Strength mg (amlodipine / atorvastatin) NDC # Engraving Side 1 / Side 2 Tablet Color Tablet Shape Bottle of 30 5/10 0069-2150-30 or 0069-6180-30 CDT 051/Pfizer White Oval Bottle of 30 5/20 0069-2170-30 or 0069-6323-30 CDT 052/Pfizer White Oval Bottle of 30 5/40 0069-2190-30 or 0069-6565-30 CDT 054/Pfizer White Oval Bottle of 30 5/80 0069-2260-30 or 0069-6747-30 CDT 058/Pfizer White Oval Bottle of 30 10/10 0069-2160-30 or 0069-7810-30 CDT 101/Pfizer Blue Oval Bottle of 30 10/20 0069-2180-30 or 0069-7232-30 CDT 102/Pfizer Blue Oval Bottle of 30 10/40 0069-2250-30 or 0069-7654-30 CDT 104/Pfizer Blue Oval Bottle of 30 10/80 0069-2270-30 or 0069-7476-30 CDT 108/Pfizer Blue Oval Store at 25°C (77°F); excursions permitted to 15°C -30°C (59°F -86°F) [see USP Controlled Room Temperature].
📦 Storage and Handling ▾
Store at 25°C (77°F); excursions permitted to 15°C -30°C (59°F -86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION CADUET (amlodipine and atorvastatin) tablets combine the calcium channel blocker amlodipine besylate with the HMG-CoA-reductase inhibitor atorvastatin calcium. Amlodipine besylate is chemically described as 3-ethyl-5-methyl (±)-2-[(2-aminoethoxy)methyl]-4-(o-chlorophenyl)-1,4-dihydro-6-methyl-3,5-pyridinedicarboxylate, monobenzenesulphonate. Its empirical formula is C 20 H 25 ClN 2 O 5 ∙C 6 H 6 O 3 S.
Atorvastatin calcium is chemically described as [R-(R*, R*)]-2-(4-fluorophenyl)-ß, δ-dihydroxy-5-(1-methylethyl)-3-phenyl-4-[(phenylamino)carbonyl]-1H-pyrrole-1-heptanoic acid, calcium salt (2:1) trihydrate. Its empirical formula is (C 33 H 34 FN 2 O 5 ) 2 Ca∙3H 2 O. The structural formulae for amlodipine besylate and atorvastatin calcium are shown below.
Amlodipine besylate Atorvastatin calcium CADUET contains amlodipine besylate, a white to off-white crystalline powder, and atorvastatin calcium, also a white to off-white crystalline powder. Amlodipine besylate has a molecular weight of 567.1 and atorvastatin calcium has a molecular weight of 1209.42. Amlodipine besylate is slightly soluble in water and sparingly soluble in ethanol.
Atorvastatin calcium is insoluble in aqueous solutions of pH 4 and below. Atorvastatin calcium is very slightly soluble in distilled water, pH 7.4 phosphate buffer, and acetonitrile; slightly soluble in ethanol; and freely soluble in methanol. CADUET is available as film-coated tablets containing: • 5 mg amlodipine equivalent to 6.9 mg amlodipine besylate and 10 mg atorvastatin equivalent to 10.4 mg atorvastatin calcium. • 5 mg amlodipine equivalent to 6.9 mg amlodipine besylate and 20 mg atorvastatin equivalent to 20.7 mg atorvastatin calcium. • 5 mg amlodipine equivalent to 6.9 mg amlodipine besylate and 40 mg atorvastatin equivalent to 41.4 mg atorvastatin calcium. • 5 mg amlodipine equivalent to 6.9 mg amlodipine besylate and 80 mg atorvastatin equivalent to 82.9 mg atorvastatin calcium. • 10 mg amlodipine equivalent to 13.9 mg amlodipine besylate and 10 mg atorvastatin equivalent to 10.4 mg atorvastatin calcium. • 10 mg amlodipine equivalent to 13.9 mg amlodipine besylate and 20 mg atorvastatin equivalent to 20.7 mg atorvastatin calcium. • 10 mg amlodipine equivalent to 13.9 mg amlodipine besylate and 40 mg atorvastatin equivalent to 41.4 mg atorvastatin calcium. • 10 mg amlodipine equivalent to 13.9 mg amlodipine besylate and 80 mg atorvastatin equivalent to 82.9 mg atorvastatin calcium.
Each film-coated tablet also contains calcium carbonate, croscarmellose sodium, microcrystalline cellulose, pregelatinized starch, polysorbate 80, hydroxypropyl cellulose, purified water, colloidal silicon dioxide (anhydrous), magnesium stearate, Opadry ® II White 85F28751 (polyvinyl alcohol, titanium dioxide, PEG 3000, and talc) or Opadry ® II Blue 85F10919 (polyvinyl alcohol, titanium dioxide, PEG 3000, talc, and FD&C blue #2). Chemical Structure Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Myopathy and Rhabdomyolysis Advise patients that CADUET may cause myopathy and rhabdomyolysis. Inform patients that the risk is also increased when taking certain types of medication or consuming large quantities of grapefruit juice and they should discuss all medication, both prescription and over the counter, with their healthcare provider.
Instruct patients to promptly report any unexplained muscle pain, tenderness or weakness particularly if accompanied by malaise or fever [see Warnings and Precautions (5.1) , Drug Interactions (7.1) ]. Hepatic Dysfunction Inform patients that CADUET may cause liver enzyme elevations and possibly liver failure. Advise patients to promptly report fatigue, anorexia, right upper abdominal discomfort, dark urine, or jaundice [see Warnings and Precautions (5.3) ] .
Increases in HbA1c and Fasting Serum Glucose Levels Inform patients that increases in HbA1c and fasting serum glucose levels may occur with CADUET. Encourage patients to optimize lifestyle measures, including regular exercise, maintaining a healthy body weight, and making healthy food choices [see Warnings and Precautions (5.6) ]. Pregnancy Advise pregnant patients and patients who can become pregnant of the potential risk to a fetus.
Advise patients to inform their healthcare provider of a known or suspected pregnancy to discuss if CADUET should be discontinued [see Use in Specific Populations (8.1) ] . Lactation Advise patients that breastfeeding is not recommended during treatment with CADUET [see Use in Specific Populations (8.2) ] .