
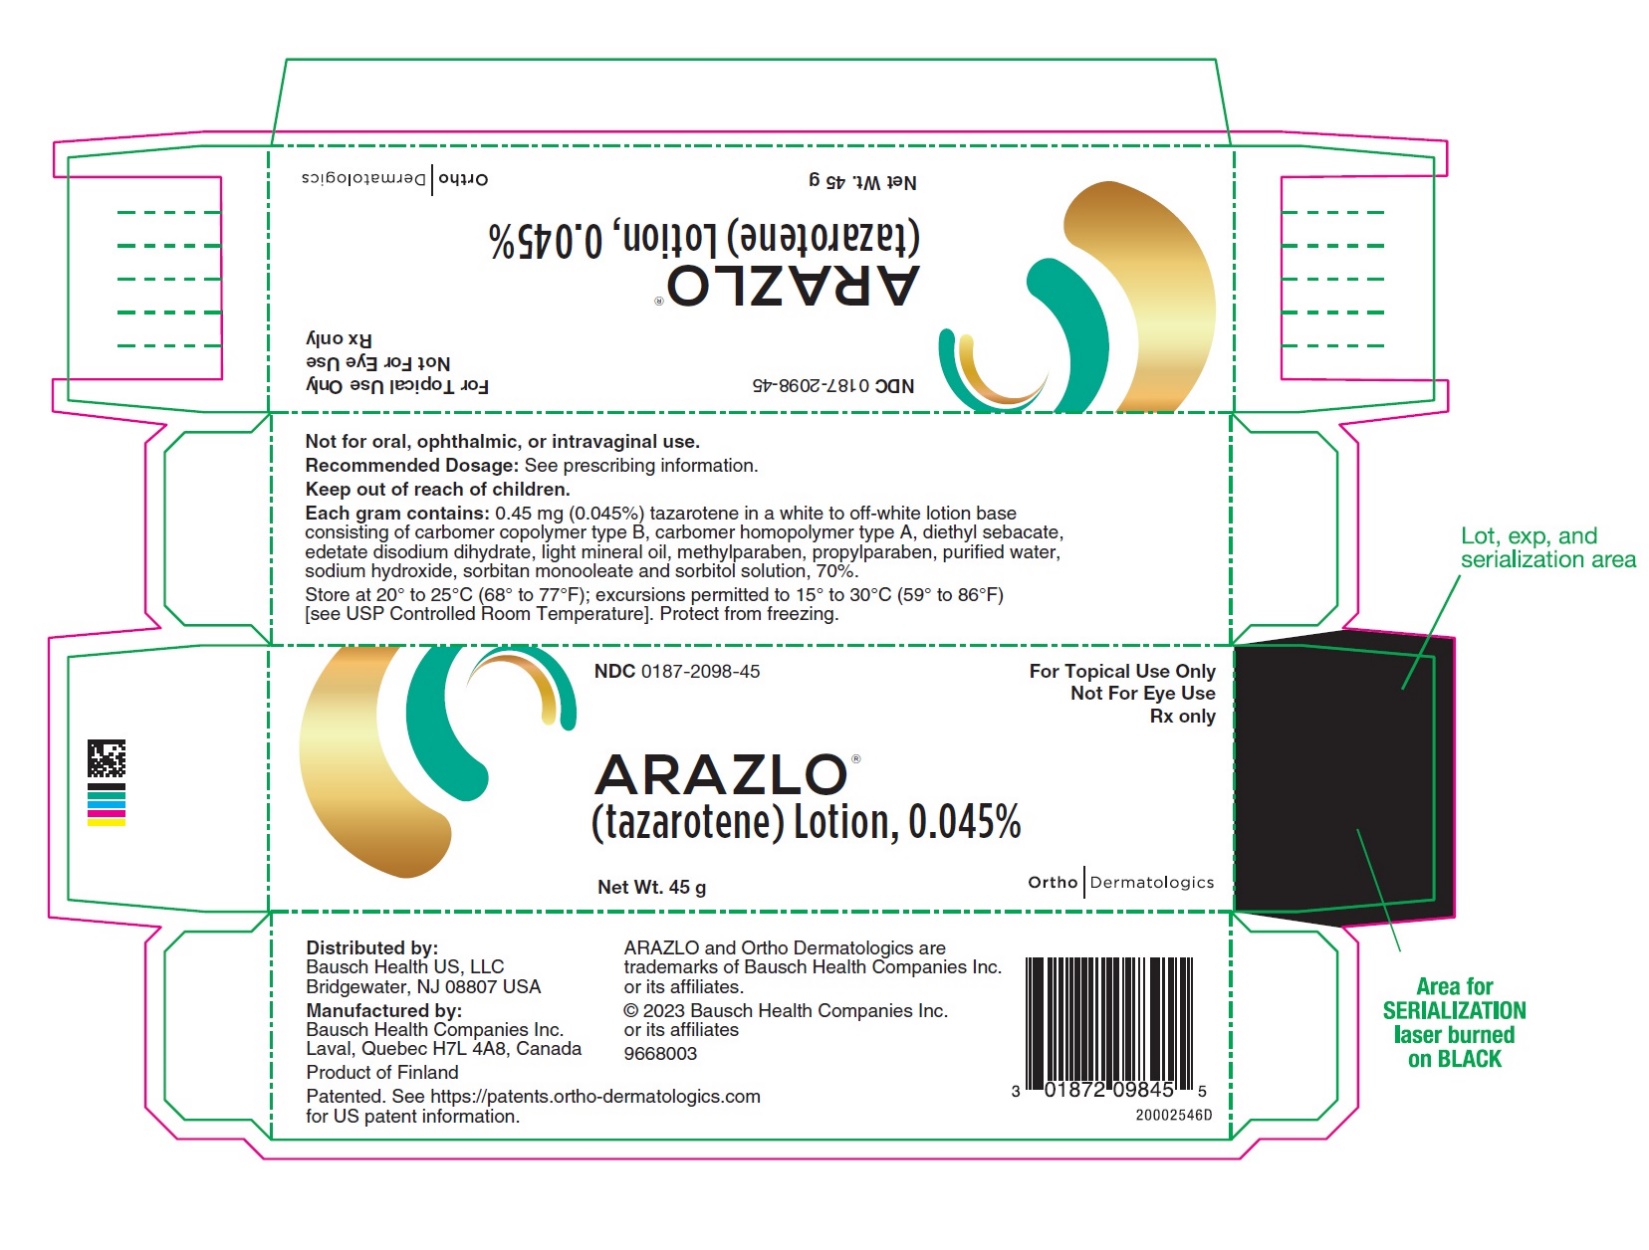
Arazlo tazarotene .45 mg/g Lotion
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Retinoid class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- It's designed to help reduce the look of fine facial wrinkles, uneven patches of lighter or darker skin, and flat age spots — but it works as part of a bigger picture that includes...
- What exactly is tazarotene cream supposed to do for my skin?
- Yes, some redness, peeling, burning, and dryness are very common when you first start using tazarotene, and they tend to be most noticeable in the beginning. Your skin often needs...
- My skin got really red and peely after I started using it — is that normal?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Tazarotene — tap one for details:
Tazarotene may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per g | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $11.315 | $509.18 / 45 g |
| Medicaid paysCMS SDUD · 12 mo | $11.62 | $522.82 / 45 g |
| Medicare drug plans payPart D · Q2 2026 | $12.12 | $545.31 / 45 g |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Arazlo .45 mg/gthis 00187-2098-45 | Bausch | 1 tube | $11.315 | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 11311482 ↗ | Method of use | U-2368 | May 11, 2038 |
| US 12128137 ↗ | Method of use | U-2368 | May 11, 2038 |
| US 11679116 ↗ | Drug product | — | Jun 6, 2036 |
Is there a generic version of ARAZLO 0.045% LOTION?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 00187-2098-10 | 10 TUBE in 1 CARTON (0187-2098-10) / 3 g in 1 TUBE (0187-2098-03) | — | — | 2019-12-19 | Active |
| 00187-2098-45 You're viewing this | 1 TUBE in 1 CARTON (0187-2098-45) / 45 g in 1 TUBE | $11.32 / g | $509.18 | 2019-12-19 | Active |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 00187-2098-45?
What NDC number is used to bill for this package of Arazlo tazarotene .45 mg/g Lotion?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ARAZLO ® (tazarotene) lotion, 0.045% is indicated for the topical treatment of acne vulgaris in patients 9 years of age and older. ARAZLO is a retinoid indicated for the topical treatment of acne vulgaris in patients 9 years of age and older. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Apply a thin layer of ARAZLO to the affected areas once daily. Avoid the eyes, mouth, paranasal creases, and mucous membranes. If ARAZLO gets in or near eyes, rinse thoroughly with water.
ARAZLO is for topical use only. Not for oral, ophthalmic, or intravaginal use. Wash hands thoroughly after applying ARAZLO.
Avoid concomitant use with oxidizing agents, such as benzoyl peroxide. If the concomitant use of ARAZLO with oxidizing agents is required, apply each at different times of the day (e.g. one in the morning and the other in the evening) [see Drug Interactions (7) ] . Use effective sunscreens and wear protective clothing while using ARAZLO [see Warnings and Precautions (5.3) ] .
Apply a thin layer of ARAZLO to the affected areas once daily. Avoid the eyes, mouth, paranasal creases, and mucous membranes. ( 2 ) Not for oral, ophthalmic, or intravaginal use.
( 2 )
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Lotion, 0.045% Each gram of ARAZLO contains 0.45 mg (0.045%) tazarotene in a white to off-white topical lotion. Lotion, 0.045% ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS ARAZLO is contraindicated in pregnancy. ARAZLO may cause fetal harm when administered to a pregnant patient [see Warnings and Precautions (5.1) , Use in Specific Populations (8.1, 8.3) ] . ARAZLO is contraindicated in pregnancy. ( 4 , 8.1 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Embryofetal Toxicity : May cause fetal harm when administered during pregnancy. Patients of childbearing potential should have a negative pregnancy test within 2 weeks prior to initiating treatment and use effective contraception during treatment. ( 5.1 ) Skin Irritation : Pain, dryness, exfoliation, erythema, and pruritus may occur with use of ARAZLO.
Avoid application to eczematous or sunburned skin. ( 5.2 ) Photosensitivity and Risk for Sunburn : Minimize exposure to sunlight and sunlamps. Use sunscreen and protective clothing when sun exposure cannot be avoided.
Administer with caution if the patient is also taking drugs known to be photosensitizers. ( 5.3 )
5.1Embryofetal Toxicity Based on data from animal reproduction studies, retinoid pharmacology and the potential for systemic absorption, ARAZLO may cause fetal harm when administered to a pregnant patient and is contraindicated during pregnancy . Safety in pregnant patients has not been established. The potential risk to the fetus outweighs the potential benefit to the mother; therefore, discontinue ARAZLO as soon as pregnancy is recognized.
Tazarotene elicits malformations and developmental effects associated with retinoids after topical and oral administration to pregnant rats and rabbits during organogenesis. However, limited case reports of pregnancy in females enrolled in clinical trials for ARAZLO have not reported a clear association with tazarotene and major birth defects or miscarriage risk [see Contraindications (4) , Use in Specific Populations (8.1) ] . Systemic exposure to tazarotenic acid is dependent upon the extent of the body surface area treated.
In patients treated topically over sufficient body surface area, exposure could be in the same order of magnitude as in orally treated animals. Tazarotene is a teratogenic substance in animals, and it is not known what level of exposure is required for teratogenicity in humans. Advise pregnant patients of the potential risk to a fetus.
Obtain a pregnancy test within 2 weeks prior to ARAZLO therapy. Initiate ARAZLO therapy during a menstrual period. Advise patients of childbearing potential to use effective contraception during treatment with ARAZLO [see Dosage and Administration (2) , Use in Specific Populations (8.3) ] .
5.2Skin Irritation Patients using ARAZLO may experience application site pain, dryness, exfoliation, erythema, and pruritus. Depending upon severity of these adverse reactions, instruct patients to use a moisturizer, reduce the frequency of the application of ARAZLO, or discontinue use. Therapy can be resumed, or the frequency of application can be increased, as the patient becomes able to tolerate treatment.
Avoid use of concomitant medications and cosmetics that have a strong drying effect. It is recommended to postpone treatment with ARAZLO until the drying effects of these products subside. Avoid application of ARAZLO to eczematous or sunburned skin.
5.3Photosensitivity and Risk for Sunburn Because of heightened burning susceptibility, minimize unprotected exposure to ultraviolet light including sunlight and sunlamps during the use of ARAZLO. Warn patients who normally experience high levels of sun exposure and those with inherent sensitivity to sun to exercise caution. Use sunscreen products and protective clothing over treated areas when sun exposure cannot be avoided.
Patients with sunburn should be advised not to use ARAZLO until fully recovered. ARAZLO should be administered with caution if the patient is taking drugs known to be photosensitizers (e.g., thiazides, tetracyclines, fluoroquinolones, phenothiazines, sulfonamides) because of the increased possibility of augmented photosensitivity. Weather extremes, such as wind or cold, may be more irritating to patients using ARAZLO.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed in more detail in other sections of the labeling: Embryofetal toxicity [see Warnings and Precautions (5.1) ] Photosensitivity and Risk of Sunburn [see Warnings and Precautions (5.3) ] The most common adverse reactions (occurring in ≥1% of the ARAZLO group and greater than the vehicle group) were application site reactions; pain, dryness, exfoliation, erythema and pruritus. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Bausch Health US, LLC at 1-800-321-4576 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. In 2 multicenter, randomized, double-blind, vehicle-controlled clinical trials, subjects age 9 years and older applied ARAZLO or vehicle once daily for 12 weeks. The majority of subjects were White (74%) and female (66%).
Approximately 22% were Hispanic/Latino and 42% were younger than 18 years of age, fourteen of 779 subjects (1.8%) treated with ARAZLO were between 9 years to less than 12 years of age. Adverse reactions reported by ≥1% of subjects treated with ARAZLO and more frequently than subjects treated with vehicle are summarized in Table 1. Most adverse reactions were mild to moderate in severity.
Severe adverse reactions represented 1.3% of the subjects treated. Overall, 2.4% (19/779) of subjects discontinued ARAZLO because of local skin reactions. Table 1:Adverse Reactions Reported by ≥1% of the ARAZLO Group and More Frequently than the Vehicle Group Adverse Reactions N (%) ARAZLO N=779 Vehicle N=791 Application site pain Application site pain defined as application site stinging, burning or pain 41 (5) 2 (<1) Application site dryness 30 (4) 1 (<1) Application site exfoliation 16 (2) 0 (0) Application site erythema 15 (2) 0 (0) Application site pruritus 10 (1) 0 (0) Skin irritation was evaluated by active assessment of erythema, scaling, itching, burning and stinging, with grades for none, mild, moderate, or severe.
The maximum severity generally peaked at Week 2 of therapy and decreased thereafter. The percentage of subjects with these signs and symptoms at any post-baseline visit are summarized in Table 2. Table 2: Incidence of Local Cutaneous Irritation at any Post-Baseline Visit ARAZLO Lotion N=774 Mild/Moderate/Severe Vehicle Lotion N=789 Mild/Moderate/Severe Erythema 49% 38% Scaling 51% 23% Itching 29% 14% Burning 30% 6% Stinging 22% 5%
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary ARAZLO is contraindicated in pregnancy. There are no available data on ARAZLO use in pregnant patients to inform a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. Based on data from animal reproduction studies, retinoid pharmacology, and the potential for systemic absorption, ARAZLO may cause fetal harm when administered to a pregnant patient and is contraindicated during pregnancy.
The potential risk to the fetus outweighs the potential benefit to the mother; therefore, ARAZLO should be discontinued as soon as pregnancy is recognized. In animal reproduction studies with pregnant rats, reduced fetal body weights and reduced skeletal ossification were observed after topical administration of a tazarotene gel formulation during the period of organogenesis at a dose equivalent to the maximum recommended human dose (MRHD) (based on AUC comparison). In animal reproduction studies with pregnant rabbits, single incidences of known retinoid malformations, including spina bifida, hydrocephaly, and heart anomalies were observed after topical administration of a tazarotene gel formulation at 15 times the MRHD (based on AUC comparison) (see Data) .
In animal reproduction studies with pregnant rats and rabbits, malformations, fetal toxicity, developmental delays, and/or behavioral delays were observed after oral administration of tazarotene during the period of organogenesis at doses 1 and 30 times, respectively, the MRHD (based on AUC comparison). In pregnant rats, decreased litter size, decreased numbers of live fetuses, decreased fetal body weights, and increased malformations were observed after oral administration of tazarotene prior to mating through early gestation at doses 6 times the MRHD (based on AUC comparison) (see Data) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of major birth defects, loss, and other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Data Animal Data In an embryofetal development study in rats, a tazarotene gel formulation, 0.5% (0.25 mg/kg/day tazarotene) was topically administered to pregnant rats during gestation days 6 through 17. Reduced fetal body weights and reduced skeletal ossification occurred at this dose (equivalent to the MRHD based on AUC comparison). In an embryofetal development study in rabbits, a tazarotene gel formulation, 0.5% (0.25 mg/kg/day tazarotene) was topically administered to pregnant rabbits during gestation days 6 through 18.
Single incidences of known retinoid malformations, including spina bifida, hydrocephaly, and heart anomalies were noted at this dose (15 times the MRHD based on AUC comparison). When tazarotene was given orally to animals, developmental delays were seen in rats; malformations and post- implantation loss were observed in rats and rabbits at doses producing 1 and 30 times, respectively, the MRHD (based on AUC comparison). In female rats orally administered 2 mg/kg/day of tazarotene from 15 days before mating through gestation day 7, classic developmental effects of retinoids including decreased number of implantation sites, decreased litter size, decreased numbers of live fetuses, and decreased fetal body weights were observed at this dose (6 times the MRHD based on AUC comparison).
A low incidence of retinoid-related malformations was observed at this dose. In a pre- and postnatal development toxicity study, topical administration of a tazarotene gel formulation (0.125 mg/kg/day) to pregnant female rats from gestation day 16 through lactation day 20 reduced pup survival, but did not affect the reproductive capacity of the offspring. Based on data from another study, the systemic drug exposure in the rat at this d…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary ARAZLO is contraindicated in pregnancy. There are no available data on ARAZLO use in pregnant patients to inform a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. Based on data from animal reproduction studies, retinoid pharmacology, and the potential for systemic absorption, ARAZLO may cause fetal harm when administered to a pregnant patient and is contraindicated during pregnancy.
The potential risk to the fetus outweighs the potential benefit to the mother; therefore, ARAZLO should be discontinued as soon as pregnancy is recognized. In animal reproduction studies with pregnant rats, reduced fetal body weights and reduced skeletal ossification were observed after topical administration of a tazarotene gel formulation during the period of organogenesis at a dose equivalent to the maximum recommended human dose (MRHD) (based on AUC comparison). In animal reproduction studies with pregnant rabbits, single incidences of known retinoid malformations, including spina bifida, hydrocephaly, and heart anomalies were observed after topical administration of a tazarotene gel formulation at 15 times the MRHD (based on AUC comparison) (see Data) .
In animal reproduction studies with pregnant rats and rabbits, malformations, fetal toxicity, developmental delays, and/or behavioral delays were observed after oral administration of tazarotene during the period of organogenesis at doses 1 and 30 times, respectively, the MRHD (based on AUC comparison). In pregnant rats, decreased litter size, decreased numbers of live fetuses, decreased fetal body weights, and increased malformations were observed after oral administration of tazarotene prior to mating through early gestation at doses 6 times the MRHD (based on AUC comparison) (see Data) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of major birth defects, loss, and other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Data Animal Data In an embryofetal development study in rats, a tazarotene gel formulation, 0.5% (0.25 mg/kg/day tazarotene) was topically administered to pregnant rats during gestation days 6 through 17. Reduced fetal body weights and reduced skeletal ossification occurred at this dose (equivalent to the MRHD based on AUC comparison). In an embryofetal development study in rabbits, a tazarotene gel formulation, 0.5% (0.25 mg/kg/day tazarotene) was topically administered to pregnant rabbits during gestation days 6 through 18.
Single incidences of known retinoid malformations, including spina bifida, hydrocephaly, and heart anomalies were noted at this dose (15 times the MRHD based on AUC comparison). When tazarotene was given orally to animals, developmental delays were seen in rats; malformations and post- implantation loss were observed in rats and rabbits at doses producing 1 and 30 times, respectively, the MRHD (based on AUC comparison). In female rats orally administered 2 mg/kg/day of tazarotene from 15 days before mating through gestation day 7, classic developmental effects of retinoids including decreased number of implantation sites, decreased litter size, decreased numbers of live fetuses, and decreased fetal body weights were observed at this dose (6 times the MRHD based on AUC comparison).
A low incidence of retinoid-related malformations was observed at this dose. In a pre- and postnatal development toxicity study, topical administration of a tazarotene gel formulation (0.125 mg/kg/day) to pregnant female rats from gestation day 16 through lactation day 20 reduced pup survival, but did not affect the reproductive capacity of the offspring. Based on data from another study, the systemic drug exposure in the rat at this dose would be equivalent to the…
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of ARAZLO for the topical treatment of acne vulgaris have been established in pediatric patients age 9 years and older based on evidence from two multicenter, randomized, double-blind, parallel-group, vehicle-controlled, 12-week clinical trials and an open-label pharmacokinetic study. A total of 300 pediatric subjects aged 9 to less than 17 years received ARAZLO in the clinical studies [see Clinical Pharmacology (12.3) and Clinical Studies (14) ] . The safety and effectiveness of ARAZLO in pediatric patients below the age of 9 years have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of ARAZLO did not include sufficient numbers of subjects age 65 years and older to determine whether they respond differently from younger subjects.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Tazarotene is a retinoid prodrug which is converted to its active form, tazarotenic acid, the carboxylic acid of tazarotene, by deesterification. Tazarotenic acid binds to all three members of the retinoic acid receptor (RAR) family: RARα, RARβ and RARγ, but shows relative selectivity for RARβ, and RARγ and may modify gene expression. The clinical significance of these findings for the treatment of acne vulgaris is unknown.
12.3Pharmacokinetics Following topical application, tazarotene undergoes esterase hydrolysis to form its active metabolite, tazarotenic acid. Tazarotenic acid is highly bound to plasma proteins (greater than 99%). Systemic exposure following topical application of ARAZLO was evaluated in 28 subjects in an open-label, randomized, pharmacokinetic study.
Subjects aged 9 years and older with moderate to severe acne applied approximately 4 grams of ARAZLO to the entire face (excluding eyes and lips), neck, upper chest, upper back and shoulders once daily for 14 Days. The majority of collected samples had concentrations below the limit of quantification (LOQ) for tazarotene (0.005 ng/mL). The mean C max and mean AUC (0-t) values for tazarotene from quantifiable samples were 0.007 ng/mL and 0.164 ng•hr/mL on Day 14 to 15, respectively.
The mean C max and AUC (0-t) of tazarotene in subjects aged 9 to less than 12 years was approximately 3.7 and 3.6 fold higher, respectively, compared to that observed in subjects 12 years and older. Tazarotenic acid concentrations were measurable in the majority of samples following single and repeated topical administration of ARAZLO (LOQ = 0.005 ng/mL). The mean C max and AUC (0-t) values for tazarotenic acid from quantifiable samples were 0.365 ng/mL and 5.72 ng•hr/mL on Days 14 to 15, respectively.
The mean C max and AUC (0-t) of tazarotenic acid in subjects aged 9 to less than 12 years was approximately 2.4 and 2.3 fold higher, respectively, compared to that observed in subjects 12 years and older.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Tazarotene is a retinoid prodrug which is converted to its active form, tazarotenic acid, the carboxylic acid of tazarotene, by deesterification. Tazarotenic acid binds to all three members of the retinoic acid receptor (RAR) family: RARα, RARβ and RARγ, but shows relative selectivity for RARβ, and RARγ and may modify gene expression. The clinical significance of these findings for the treatment of acne vulgaris is unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING ARAZLO (tazarotene) Lotion, 0.045% is a white to off-white lotion supplied in a white aluminum tube as follows: 45 g (NDC 0187-2098-45) Storage and Handling Conditions Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Protect from freezing.
📋 Description ▾
11 DESCRIPTION ARAZLO (tazarotene) is a white to off-white lotion containing 0.045% tazarotene by weight for topical administration. Tazarotene is a member of the acetylenic class of retinoids. The chemical name for tazarotene is 6-[(3,4-Dihydro-4,4-dimethyl-2H-1-benzothiopyran-6-yl)ethynyl]-3-pyridinecarboxylic acid ethyl ester.
The structural formula for tazarotene is represented below: Tazarotene: Molecular Formula: C 21 H 21 NO 2 S Molecular Weight: 351.46 Each gram of ARAZLO contains 0.45 mg (0.045%) tazarotene in a white to off-white lotion base consisting of carbomer copolymer type B, carbomer homopolymer type A, diethyl sebacate, edetate disodium dihydrate, light mineral oil, methylparaben, propylparaben, purified water, sodium hydroxide, sorbitan monooleate and sorbitol solution, 70%. chemstructure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Embryofetal Toxicity Inform patients of childbearing potential of the potential risk to a fetus. To avoid pregnancy, advise these patients to use effective contraception during treatment with ARAZLO.
Advise patients to discontinue the medication if pregnant and to inform their healthcare provider of a known or suspected pregnancy [see Contraindications (4.1) , Warnings and Precautions (5.1) , and Use in Specific Populations (8.1), (8.3) ] . Lactation Advise patients to use ARAZLO for the shortest duration possible while breastfeeding. Advise breastfeeding patients not to apply ARAZLO directly to the nipple and areola to avoid direct infant exposure [see Use in Specific Populations (8.2) ] .
Skin Irritation Advise patients to avoid applying ARAZLO to eczematous or sunburned skin. If undue irritation occurs, reduce frequency of application, temporarily interrupt treatment, or discontinue use. Treatment may be resumed once irritation subsides [see Warnings and Precautions (5.2) ] .
Photosensitivity and Risk of Sunburn Advise patients to minimize exposure to sunlight and sunlamps; recommend the use of sunscreen products and protective apparel (e.g., wide-brimmed hat) when sun exposure cannot be avoided. Advise patients to avoid using ARAZLO if also taking other medicines that may increase sensitivity to sunlight [see Warnings and Precautions (5.3) ] . Distributed by: Bausch Health US, LLC Bridgewater, NJ 08807 USA Manufactured by: Bausch Health Companies Inc.
Laval, Quebec H7L 4A8, Canada Patented. See https://patents.ortho-dermatologics.com for US patent information. ARAZLO is a trademark of Bausch Health Companies Inc. or its affiliates. © 2023 Bausch Health Companies Inc. or its affiliates 9701202