
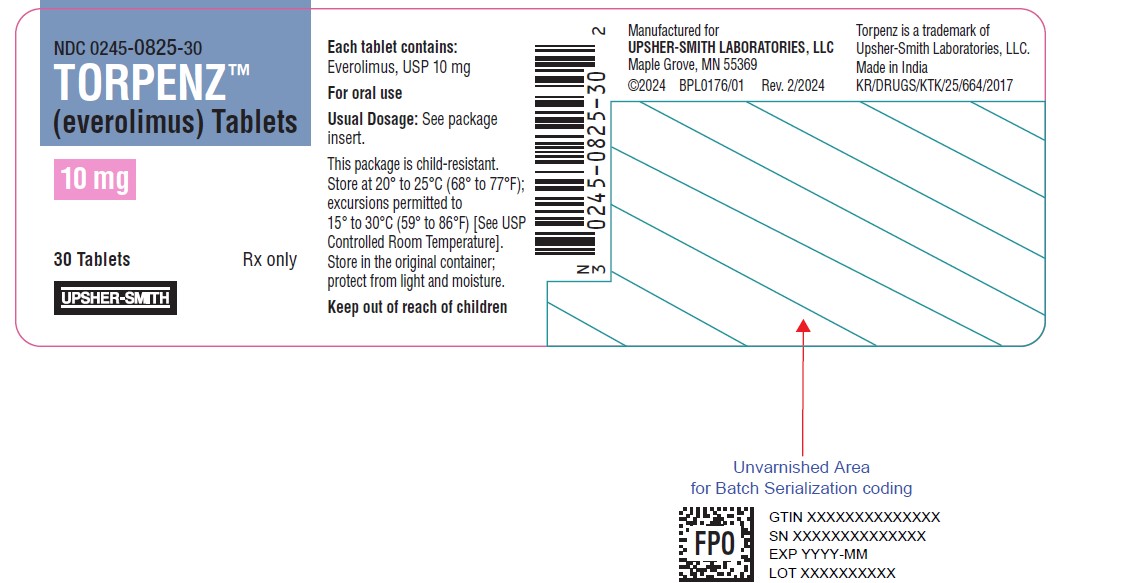
TORPENZ Everolimus 10 mg Tablet, 28-count — NDC 0245-0825-04 (Billing 00245-0825-04)
This is a package of 28 tablets of TORPENZ Everolimus 10 mg Tablet from Upsher-Smith Laboratories, LLC, marketed since Oct 2021 and currently FDA-listed; retail pharmacies pay about $26.32 per tablet (NADAC). It is the main listing for this product, which comes in 2 package sizes.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 064995
- GCN: 20844
- GPI-14 (Medi-Span): 21532530000330
- HICL (First Databank): 032975
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 845507
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Kinase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It depends on the product. Afinitor, Yulithira and generic everolimus tablets treat certain cancers and tuberous sclerosis complex conditions. Zortress and generic transplant table...
- Take it by mouth, the same way every time, either always with food or always without. The cancer and TSC products are usually once a day. The transplant products are usually twice...
- Mouth sores are very common, along with infections, rash, tiredness, diarrhea, swelling and low appetite. Mention mouth sores early, since they can be managed. Call your doctor rig...
- Check with me first. Many drugs change everolimus levels, including ketoconazole, clarithromycin, rifampin, St. John’s Wort and certain seizure medicines. Cannabidiol can raise lev...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Everolimus — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $26.324 | $737.08 / 28 tablet |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $203.23 | $5,690.42 / 28 tablet |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 2, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 00245-0825-04 You're viewing this Main listing | 28 BLISTER PACK in 1 CARTON / 1 TABLET in 1 BLISTER PACK | $26.32 / ea | $737.08 | 2025-10-21 | — | Active |
| 00245-0825-30 0245-0825-30 | 30 TABLET in 1 BOTTLE | $26.32 / ea | $789.73 | 2024-06-24 | — | Active |
This pack has the lowest per-ea cost of the 2 priced pack sizes ($26.32 NADAC).
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 00245-0825-30?
What NDC number is used to bill for this package of TORPENZ Everolimus 10 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Everolimus 10 mg 00054-0482-13 | Hikma | 30 tablets | $26.324 | AB | Availability likely | — |
| Everolimus 10 mg 00093-7769-24 | Teva | 28 tablets | $26.324 | AB | Discontinued | — |
| Torpenz 10 mgthis 00245-0825-04 | Upsher-Smith | 28 tablets | $26.324 | AB | Availability likely | — |
| Everolimus 10 mg 51991-0824-28 | Breckenridge | 28 tablets | $26.324 | AB | Availability likely | — |
| Everolimus 10 mg 70377-0013-22 | Biocon | 28 tablets | $26.324 | AB | Availability likely | — |
| Everolimus 10 mg 72603-0257-01 | NorthStar | 30 tablets | $26.324 | AB | Availability likely | — |
| Yulithira 10 mg 82249-0613-30 | CivicaScript, | 30 tablets | $26.324 | AB | Availability likely | — |
| Afinitor 10 mg 00078-0567-51 | Novartis | 28 tablets | — | AB | FDA listed | — |
| Everolimus 10 mg 63850-0061-01 | Natco | 28 tablets | — | AB | FDA listed | — |
| everolimus 10 mg 82293-0033-10 | Novugen | 28 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII 1P9D0Z171K
BHT is a synthetic antioxidant that prevents fats and oils in medicines from breaking down and becoming rancid. It helps keep the product stable and effective during storage.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII 9H4L916OBU
Hypromellose 2208 is a plant-derived cellulose that thickens and forms protective coats. It's used in medications as a binder to hold ingredients together and as a coating to control how fast the medicine dissolves.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE
1.1Hormone Receptor-Positive, HER2-Negative Breast Cancer TORPENZ tablets are indicated for the treatment of postmenopausal women with advanced hormone receptor-positive, HER2-negative breast cancer in combination with exemestane, after failure of treatment with letrozole or anastrozole. TORPENZ (everolimus) tablets are a kinase inhibitor indicated for the treatment of: Postmenopausal women with advanced hormone receptor-positive, HER2-negative breast cancer in combination with exemestane after failure of treatment with letrozole or anastrozole.
( 1.1 ) Adults with renal angiomyolipoma and tuberous sclerosis complex (TSC), not requiring immediate surgery. ( 1.4 ) Adult and pediatric patients aged 1 year and older with TSC who have subependymal giant cell astrocytoma (SEGA) that requires therapeutic intervention but cannot be curatively resected. ( 1.5 )
1.4Tuberous Sclerosis Complex (TSC)-Associated Renal Angiomyolipoma TORPENZ tablets are indicated for the treatment of adult patients with renal angiomyolipoma and TSC, not requiring immediate surgery.
1.5Tuberous Sclerosis Complex (TSC)-Associated Subependymal Giant Cell Astrocytoma (SEGA) TORPENZ tablets are indicated in adult and pediatric patients aged 1 year and older with TSC for the treatment of SEGA that requires therapeutic intervention but cannot be curatively resected.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Do not combine TORPENZ tablets and AFINITOR DISPERZ to achieve the total daily dose. ( 2.1 ) Modify the dose for patients with hepatic impairment or for patients taking drugs that inhibit or induce P-glycoprotein (P-gp) and CYP3A4. ( 2.1 ) Breast Cancer: 10 mg orally once daily.
( 2.2 ) TSC-Associated Renal Angiomyolipoma: 10 mg orally once daily. ( 2.5 ) TSC-Associated SEGA: 4.5 mg/m 2 orally once daily; adjust dose to attain trough concentrations of 5 to 15 ng/mL. ( 2.6 , 2.8 )
2.1Important Dosage Information TORPENZ tablets and AFINITOR DISPERZ are two different dosage forms. Select the recommended dosage form based on the indication [see Indications and Usage (1) ] . Do not combine TORPENZ tablets and AFINITOR DISPERZ to achieve the total dose.
Modify the dosage for patients with hepatic impairment or for patients taking drugs that inhibit or induce P-glycoprotein (P-gp) and CYP3A4 [see Dosage and Administration (2.10 , 2.11 , 2.12) ] .
2.2Recommended Dosage for Hormone Receptor-Positive, HER2-Negative Breast Cancer The recommended dosage of TORPENZ tablets is 10 mg orally once daily until disease progression or unacceptable toxicity.
2.5Recommended Dosage for Tuberous Sclerosis Complex (TSC)-Associated Renal Angiomyolipoma The recommended dosage of TORPENZ tablets is 10 mg orally once daily until disease progression or unacceptable toxicity.
2.6Recommended Dosage for Tuberous Sclerosis Complex (TSC)-Associated Subependymal Giant Cell Astrocytoma (SEGA) The recommended starting dosage of TORPENZ tablets is 4.5 mg/m 2 orally once daily until disease progression or unacceptable toxicity [see Dosage and Administration (2.8) ] .
2.8Therapeutic Drug Monitoring (TDM) and Dose Titration for Tuberous Sclerosis Complex (TSC)-Associated Subependymal Giant Cell Astrocytoma (SEGA) Monitor everolimus whole blood trough concentrations at time points recommended in Table 1. Titrate the dose to attain trough concentrations of 5 ng/mL to 15 ng/mL. Adjust the dose using the following equation: New dose The maximum dose increment at any titration must not exceed 5 mg.
Multiple dose titrations may be required to attain the target trough concentration. = current dose × (target concentration divided by current concentration) When possible, use the same assay and laboratory for TDM throughout treatment. Table 1: Recommended Timing of Therapeutic Drug Monitoring Event When to Assess Trough Concentrations After Event Abbreviation: P-gp, P-glycoprotein Initiation of TORPENZ 1 to 2 weeks Modification of TORPENZ dose 1 to 2 weeks Switch between TORPENZ tablets and AFINITOR DISPERZ 1 to 2 weeks Initiation or discontinuation of P-gp and moderate CYP3A4 inhibitor 2 weeks Initiation or discontinuation of P-gp and strong CYP3A4 inducer 2 weeks Change in hepatic function 2 weeks Stable dose with changing body surface area (BSA) Every 3 to 6 months Stable dose with stable BSA Every 6 to 12 months
2.9Dosage Modifications for Adverse Reactions Table 2 summarizes recommendations for dosage modifications of TORPENZ tablets for the management of adverse reactions. Table 2: Recommended Dosage Modifications for TORPENZ for Adverse Reactions Adverse Reaction Severity Dosage modification Non-infectious pneumonitis [see Warnings and Precautions (5.1) ] Grade 2 Withhold until improvement to Grade 0 or 1. Resume at 50% of previous dose; change to every other day dosing if the reduced dose is lower than the lowest available strength.
Permanently discontinue if toxicity does not resolve or improve to Grade 1 within 4 weeks. Grade 3 Withhold until improvement to Grade 0 or 1. Resume at 50% of previous dose; change to every other day dosing if the reduced dose is lower than the lowest available strength.
If toxicity recurs at Grade 3, permanently discontinue. Grade 4 Permanently discontinue. Stomatitis [see Warnings and Precautions (5.5) ] Grade 2 Withhold until improvement to Grade 0 or 1.
Resume at same dose. If recurs at Grade 2, withho… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS TORPENZ tablets are available containing 2.5 mg, 5 mg, 7.5 mg or 10 mg of everolimus. The 2.5 mg tablets are white to off white, capsule shaped, flat faced, beveled edged tablets debossed with "B 2.5" on one side and plain on the other side. The 5 mg tablets are white to off white, capsule shaped, flat faced, beveled edged tablets debossed with "B 5" on one side and plain on the other side.
The 7.5 mg tablets are white to off white, capsule shaped, flat faced, beveled edged tablets debossed with "B 7.5" on one side and plain on the other side. The 10 mg tablets are white to off white, capsule shaped, flat faced, beveled edged tablets debossed with "B 10" on one side and plain on the other side. TORPENZ tablets: 2.5 mg, 5 mg, 7.5 mg, and 10 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS TORPENZ tablets are contraindicated in patients with clinically significant hypersensitivity to everolimus or to other rapamycin derivatives [see Warnings and Precautions (5.3) ] . Clinically significant hypersensitivity to everolimus or to other rapamycin derivatives. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Non-Infectious Pneumonitis: Monitor for clinical symptoms or radiological changes. Withhold or permanently discontinue based on severity. ( 2.9 , 5.1 ) Infections: Monitor for signs and symptoms of infection.
Withhold or permanently discontinue based on severity. ( 2.9 , 5.2 ) Severe Hypersensitivity Reactions: Permanently discontinue for clinically significant hypersensitivity. ( 5.3 ) Angioedema: Patients taking concomitant angiotensin-converting-enzyme (ACE) inhibitors may be at increased risk for angioedema.
Permanently discontinue for angioedema. ( 5.4 , 7.2 ) Stomatitis: Initiate dexamethasone alcohol-free mouthwash when starting treatment. ( 5.5 , 6.1 ) Renal Failure: Monitor renal function prior to treatment and periodically thereafter.
( 5.6 ) Risk of Impaired Wound Healing: Withhold for at least 1 week prior to elective surgery. Do not administer for at least 2 weeks following major surgery and until adequate wound healing. The safety of resumption of treatment after resolution of wound healing complications has not been established.
( 5.7 ) Geriatric Patients: Monitor and adjust dose for adverse reactions. ( 5.8 ) Metabolic Disorders: Monitor serum glucose and lipids prior to treatment and periodically thereafter. Withhold or permanently discontinue based on severity.
( 2.9 , 5.9 ) Myelosuppression: Monitor hematologic parameters prior to treatment and periodically thereafter. Withhold or permanently discontinue based on severity. ( 2.9 , 5.10 ) Risk of Infection or Reduced Immune Response with Vaccination: Avoid live vaccines and close contact with those who have received live vaccines.
Complete recommended childhood vaccinations prior to starting treatment. ( 5.11 ) Radiation Sensitization and Radiation Recall: Severe radiation reactions may occur. ( 5.12 , 6.2 ) Embryo-Fetal Toxicity: Can cause fetal harm.
Advise patients of reproductive potential of the potential risk to a fetus and to use effective contraception. ( 5.13 , 8.1 , 8.3 )
5.1Non-infectious Pneumonitis Non-infectious pneumonitis is a class effect of rapamycin derivatives. Non-infectious pneumonitis was reported in up to 19% of patients treated with everolimus in clinical trials, some cases were reported with pulmonary hypertension (including pulmonary arterial hypertension) as a secondary event. The incidence of Grade 3 and 4 non-infectious pneumonitis was up to 4% and up to 0.2%, respectively [see Adverse Reactions (6.1) ] .
Fatal outcomes have been observed. Consider a diagnosis of non-infectious pneumonitis in patients presenting with non-specific respiratory signs and symptoms. Consider opportunistic infections, such as pneumocystis jiroveci pneumonia (PJP) in the differential diagnosis.
Advise patients to report promptly any new or worsening respiratory symptoms. Continue TORPENZ without dose alteration in patients who develop radiological changes suggestive of non-infectious pneumonitis and have few or no symptoms. Imaging appears to overestimate the incidence of clinical pneumonitis.
For Grade 2 to 4 non-infectious pneumonitis, withhold or permanently discontinue TORPENZ based on severity [see Dosage and Administration (2.9) ] . Corticosteroids may be indicated until clinical symptoms resolve. Administer prophylaxis for PJP when concomitant use of corticosteroids or other immunosuppressive agents are required.
The development of pneumonitis has been reported even at a reduced dose.
5.2Infections TORPENZ has immunosuppressive properties and may predispose patients to bacterial, fungal, viral, or protozoal infections, including infections with opportunistic pathogens [see Adverse Reactions (6.1) ] . Localized and systemic infections, including pneumonia, mycobacterial infections, other bacterial infections, invasive fungal infections (e.g., aspergillosis, candidiasis, or PJP), and viral infections (e.g., reactivation of hepatitis B virus) have occurred. Some of these infections have been severe (e.g., sepsis, septic… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described elsewhere in the labeling: Non-Infectious Pneumonitis [see Warnings and Precautions (5.1) ] Infections [see Warnings and Precautions (5.2) ] Severe Hypersensitivity Reactions [see Warnings and Precautions (5.3) ] Angioedema with Concomitant Use of ACE inhibitors [see Warnings and Precautions (5.4) ] Stomatitis [see Warnings and Precautions (5.5) ] Renal Failure [see Warnings and Precautions (5.6) ] Impaired Wound Healing [see Warnings and Precautions (5.7) ] Metabolic Disorders [see Warnings and Precautions (5.9) ] Myelosuppression [see Warnings and Precautions (5.10) ] Radiation Sensitization and Radiation Recall [see Warnings and Precautions (5.12) ] Breast cancer: Most common adverse reactions (incidence ≥ 30%) include stomatitis, infections, rash, fatigue, diarrhea, edema, abdominal pain, nausea, fever, asthenia, cough, headache, and decreased appetite.
( 6.1 ) TSC-Associated Renal Angiomyolipoma: Most common adverse reaction (incidence ≥ 30%) is stomatitis. ( 6.1 ) TSC-Associated SEGA: Most common adverse reactions (incidence ≥ 30%) are stomatitis and respiratory tract infection. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Upsher-Smith Laboratories, LLC at 1-855-899-9180 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.2Post marketing Experience The following adverse reactions have been identified during post approval use of everolimus. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate frequency or establish a causal relationship to drug exposure: Blood and Lymphatic Disorders: Thrombotic microangiopathy Cardiac: Cardiac failure with some cases reported with pulmonary hypertension (including pulmonary arterial hypertension) as a secondary event Gastrointestinal: Acute pancreatitis Hepatobiliary: Cholecystitis and cholelithiasis Infections: Sepsis and septic shock Nervous System: Reflex sympathetic dystrophy Vascular: Arterial thrombotic events, lymphedema Injury, Poisoning and Procedural Complications: Radiation sensitization and radiation recall
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, the adverse reaction rates observed cannot be directly compared to rates in other trials and may not reflect the rates observed in clinical practice. Hormone Receptor-Positive, HER2-Negative Breast Cancer The safety of everolimus tablets (10 mg orally once daily) in combination with exemestane (25 mg orally once daily) (n = 485) vs. placebo in combination with exemestane (n = 239) was evaluated in a randomized, controlled trial (BOLERO-2) in patients with advanced or metastatic hormone receptor-positive, HER2-negative breast cancer.
The median age of patients was 61 years (28 to 93 years), and 75% were white. The median follow-up was approximately 13 months. The most common adverse reactions (incidence ≥ 30%) were stomatitis, infections, rash, fatigue, diarrhea, and decreased appetite.
The most common Grade 3 to 4 adverse reactions (incidence ≥ 2%) were stomatitis, infections, hyperglycemia, fatigue, dyspnea, pneumonitis, and diarrhea. The most common laboratory abnormalities (incidence ≥ 50%) were hypercholesterolemia, hyperglycemia, increased aspartate transaminase (AST), anemia, leukopenia, thrombocytopenia, lymphopenia, increased alanine transaminase (ALT), and hypertriglyceridemia. The most common Grade 3 to 4 laboratory abnormalities (incidence ≥ 3%) were lymphopenia, hyperglycemia, anemia, hypokalemia, increased AST, increased ALT, and thrombocytopenia.
Fatal adverse reactions occurred in 2% of patients who received everolimus tablets. The rate of adverse reactions resulting in permanent discontinuation was 24% for the everolimus tablets arm. Dose adjustments (interruptions or reductions) occurred in 63% of patients in the everolimus tablets arm.
Adverse reactions reported with an incidence of ≥ 10% for… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS P-gp and strong CYP3A4 inhibitors: Avoid concomitant use. ( 2.11 , 7.1 ) P-gp and moderate CYP3A4 inhibitors: Reduce the dose as recommended. ( 2.11 , 7.1 ) P-gp and strong CYP3A4 inducers: Increase the dose as recommended. ( 2.12 , 7.1 )
7.1Effect of Other Drugs on TORPENZ Inhibitors Avoid the concomitant use of P-gp and strong CYP3A4 inhibitors [see Dosage and Administration (2.11) , Clinical Pharmacology (12.3) ] . Reduce the dose for patients taking TORPENZ with a P-gp and moderate CYP3A4 inhibitor as recommended [see Dosage and Administration (2.11) , Clinical Pharmacology (12.3) ] . Inducers Increase the dose for patients taking TORPENZ with a P-gp and strong CYP3A4 inducer as recommended [see Dosage and Administration (2.12) , Clinical Pharmacology (12.3) ] .
7.2Effects of Combination Use of Angiotensin-Converting Enzyme (ACE) Inhibitors Patients taking concomitant ACE inhibitors with TORPENZ may be at increased risk for angioedema. Avoid the concomitant use of ACE inhibitors with TORPENZ [see Warnings and Precautions (5.4) ] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS For breast cancer or TSC-associated renal angiomyolipoma, patients with hepatic impairment, reduce the dose. ( 2.10 , 8.6 ) For patients with TSC-associated SEGA and severe hepatic impairment, reduce the starting dose and adjust dose to attain target trough concentrations. ( 2.8 , 2.10 , 8.6 )
8.1Pregnancy Risk Summary Based on animal studies and the mechanism of action [see Clinical Pharmacology (12.1) ] , everolimus can cause fetal harm when administered to a pregnant woman. There are limited case reports of everolimus use in pregnant women; however, these reports are not sufficient to inform about risks of birth defects or miscarriage. In animal studies, everolimus caused embryo-fetal toxicities in rats when administered during the period of organogenesis at maternal exposures that were lower than human exposures at the recommended dose of everolimus tablets 10 mg orally once daily (see Data ) .
Advise pregnant women of the potential risk to the fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage is 2% to 4% and 15% to 20% of clinically recognized pregnancies, respectively. Data Animal Data In animal reproductive studies, oral administration of everolimus to female rats before mating and through organogenesis induced embryo-fetal toxicities, including increased resorption, pre-implantation and post-implantation loss, decreased numbers of live fetuses, malformation (e.g., sternal cleft), and retarded skeletal development.
These effects occurred in the absence of maternal toxicities. Embryo-fetal toxicities in rats occurred at doses ≥ 0.1 mg/kg (0.6 mg/m 2 ) with resulting exposures of approximately 4% of the human exposure at the recommended dose of everolimus tablets 10 mg orally once daily based on area under the curve (AUC). In rabbits, embryo-toxicity evident as an increase in resorptions occurred at an oral dose of 0.8 mg/kg (9.6 mg/m 2 ), approximately 1.6 times the recommended dose of everolimus tablets 10 mg orally once daily or the median dose administered to patients with tuberous sclerosis complex (TSC)-associated subependymal giant cell astrocytoma (SEGA).
The effect in rabbits occurred in the presence of maternal toxicities. In a pre- and post-natal development study in rats, animals were dosed from implantation through lactation. At the dose of 0.1 mg/kg (0.6 mg/m 2 ), there were no adverse effects on delivery and lactation or signs of maternal toxicity; however, there were reductions in body weight (up to 9% reduction from the control) and in survival of offspring (~5% died or missing).
There were no drug-related effects on the developmental parameters (morphological development, motor activity, learning, or fertility assessment) in the offspring.
8.2Lactation Risk Summary There are no data on the presence of everolimus or its metabolites in human milk, the effects of everolimus on the breastfed infant or on milk production. Everolimus and its metabolites passed into the milk of lactating rats at a concentration 3.5 times higher than in maternal serum. Because of the potential for serious adverse reactions in breastfed infants from everolimus, advise women not to breastfeed during treatment with everolimus and for 2 weeks after the last dose.
8.3Females and Males of Reproductive Potential Pregnancy Testing Verify the pregnancy status of females of reproductive potential prior to starting TORPENZ [see Use in Specific Populations (8.1) ] . Contraception TORPENZ can cause fetal harm when administered to pregnant women [see Use in Specific Populations (8.1) ] . Females Advise female patients of reproductive potential to use effective contraception during treatment with TORPENZ and for 8 weeks after the last dose.
Males Advise male patients with female partners of reproductive potential to use effective contraception during treatment with TORPENZ and for 4 weeks after the last dose. Infertility Females Menstrual irregularities,… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on animal studies and the mechanism of action [see Clinical Pharmacology (12.1) ] , everolimus can cause fetal harm when administered to a pregnant woman. There are limited case reports of everolimus use in pregnant women; however, these reports are not sufficient to inform about risks of birth defects or miscarriage. In animal studies, everolimus caused embryo-fetal toxicities in rats when administered during the period of organogenesis at maternal exposures that were lower than human exposures at the recommended dose of everolimus tablets 10 mg orally once daily (see Data ) .
Advise pregnant women of the potential risk to the fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage is 2% to 4% and 15% to 20% of clinically recognized pregnancies, respectively. Data Animal Data In animal reproductive studies, oral administration of everolimus to female rats before mating and through organogenesis induced embryo-fetal toxicities, including increased resorption, pre-implantation and post-implantation loss, decreased numbers of live fetuses, malformation (e.g., sternal cleft), and retarded skeletal development.
These effects occurred in the absence of maternal toxicities. Embryo-fetal toxicities in rats occurred at doses ≥ 0.1 mg/kg (0.6 mg/m 2 ) with resulting exposures of approximately 4% of the human exposure at the recommended dose of everolimus tablets 10 mg orally once daily based on area under the curve (AUC). In rabbits, embryo-toxicity evident as an increase in resorptions occurred at an oral dose of 0.8 mg/kg (9.6 mg/m 2 ), approximately 1.6 times the recommended dose of everolimus tablets 10 mg orally once daily or the median dose administered to patients with tuberous sclerosis complex (TSC)-associated subependymal giant cell astrocytoma (SEGA).
The effect in rabbits occurred in the presence of maternal toxicities. In a pre- and post-natal development study in rats, animals were dosed from implantation through lactation. At the dose of 0.1 mg/kg (0.6 mg/m 2 ), there were no adverse effects on delivery and lactation or signs of maternal toxicity; however, there were reductions in body weight (up to 9% reduction from the control) and in survival of offspring (~5% died or missing).
There were no drug-related effects on the developmental parameters (morphological development, motor activity, learning, or fertility assessment) in the offspring.
🧒 Pediatric Use ▾
8.4Pediatric Use TSC-Associated SEGA The safety and effectiveness of everolimus have been established in pediatric patients age 1 year and older with TSC-associated SEGA that requires therapeutic intervention but cannot be curatively resected. Use of everolimus for this indication is supported by evidence from a randomized, double-blind, placebo-controlled trial in adult and pediatric patients (EXIST-1); an open-label, single-arm trial in adult and pediatric patients (Study 2485); and additional pharmacokinetic data in pediatric patients [see Adverse Reactions (6.1) , Clinical Pharmacology (12.3) , Clinical Studies (14.5) ] .
The safety and effectiveness of everolimus have not been established in pediatric patients less than 1 year of age with TSC-associated SEGA. In EXIST-1, the incidence of infections and serious infections were reported at a higher frequency in patients < 6 years of age. Ninety-six percent of 23 everolimus tablets-treated patients < 6 years had at least one infection compared to 67% of 55 everolimus tablets-treated patients ≥ 6 years.
Thirty-five percent of 23 everolimus tablets-treated patients < 6 years of age had at least 1 serious infection compared to 7% of 55 everolimus tablets-treated patients ≥ 6 years. Although a conclusive determination cannot be made due to the limited number of patients and lack of a comparator arm in the open label follow-up periods of EXIST-1 and Study 2485, everolimus tablets did not appear to adversely impact growth and pubertal development in the 115 pediatric patients treated with everolimus tablets for a median duration of 4.1 years.
Other Indications The safety and effectiveness of everolimus in pediatric patients have not been established in: Hormone receptor-positive, HER2-negative breast cancer TSC-associated renal angiomyolipoma
🧓 Geriatric Use ▾
8.5Geriatric Use In BOLERO-2, 40% of patients with breast cancer treated with everolimus tablets were ≥ 65 years of age, while 15% were ≥ 75 years of age. No overall differences in effectiveness were observed between elderly and younger patients. The incidence of deaths due to any cause within 28 days of the last everolimus tablets dose was 6% in patients ≥ 65 years of age compared to 2% in patients < 65 years of age.
Adverse reactions leading to permanent treatment discontinuation occurred in 33% of patients ≥ 65 years of age compared to 17% in patients < 65 years of age.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Everolimus is an inhibitor of mammalian target of rapamycin (mTOR), a serine-threonine kinase, downstream of the PI3K/AKT pathway. The mTOR pathway is dysregulated in several human cancers and in tuberous sclerosis complex (TSC). Everolimus binds to an intracellular protein, FKBP-12, resulting in an inhibitory complex formation with mTOR complex 1 (mTORC1) and thus inhibition of mTOR kinase activity.
Everolimus reduced the activity of S6 ribosomal protein kinase (S6K1) and eukaryotic initiation factor 4E-binding protein (4E-BP1), downstream effectors of mTOR, involved in protein synthesis. S6K1 is a substrate of mTORC1 and phosphorylates the activation domain 1 of the estrogen receptor which results in ligand-independent activation of the receptor. In addition, everolimus inhibited the expression of hypoxia-inducible factor (e.g., HIF-1) and reduced the expression of vascular endothelial growth factor (VEGF).
Inhibition of mTOR by everolimus has been shown to reduce cell proliferation, angiogenesis, and glucose uptake in in vitro and/or in vivo studies. Constitutive activation of the PI3K/Akt/mTOR pathway can contribute to endocrine resistance in breast cancer. In vitro studies show that estrogen-dependent and HER2+ breast cancer cells are sensitive to the inhibitory effects of everolimus, and that combination treatment with everolimus and Akt, HER2, or aromatase inhibitors enhances the anti-tumor activity of everolimus in a synergistic manner.
Two regulators of mTORC1 signalling are the oncogene suppressors tuberin-sclerosis complexes 1 and 2 ( TSC1, TSC2 ). Loss or inactivation of either TSC1 or TSC2 leads to activation of downstream signalling. In TSC, a genetic disorder, inactivating mutations in either the TSC1 or the TSC2 gene lead to hamartoma formation throughout the body as well as seizures and epileptogenesis.
Overactivation of mTOR results in neuronal dysplasia, aberrant axonogenesis and dendrite formation, increased excitatory synaptic currents, reduced myelination, and disruption of the cortical laminar structure causing abnormalities in neuronal development and function. Treatment with an mTOR inhibitor in animal models of mTOR dysregulation in the brain resulted in seizure suppression, prevention of the development of new-onset seizures, and prevention of premature death.
12.2Pharmacodynamics Exposure-Response Relationship In patients with TSC-associated subependymal giant cell astrocytoma (SEGA), the magnitude of the reduction in SEGA volume was correlated with the everolimus trough concentration. Cardiac Electrophysiology In a randomized, placebo-controlled, cross-over study, 59 healthy subjects were administered a single oral dose of everolimus tablets (20 mg and 50 mg) and placebo. Everolimus tablets at single doses up to 50 mg did not prolong the QT/QTc interval.
12.3Pharmacokinetics Absorption After administration of everolimus tablets in patients with advanced solid tumors, peak everolimus concentrations are reached 1 to 2 hours after administration of oral doses ranging from 5 mg to 70 mg. Following single doses, C max is dose-proportional with daily dosing between 5 mg and 10 mg. With single doses of 20 mg and higher, the increase in C max is less than dose-proportional; however, AUC shows dose-proportionality over the 5 mg to 70 mg dose range.
Steady-state was achieved within 2 weeks following once-daily dosing. In patients with TSC-associated SEGA, everolimus C min was approximately dose-proportional within the dose range from 1.35 mg/m 2 to 14.4 mg/m 2 . Effect of Food In healthy subjects, a high-fat meal (containing approximately 1,000 calories and 55 grams of fat) reduced systemic exposure to everolimus tablets 10 mg (as measured by AUC) by 22% and the peak blood concentration C max by 54%.
Light-fat meals (containing approximately 500 calories and 20 grams of fat) reduced AUC by 32% and C max by 42%. Distribution The blood-to-plasma ratio of ever… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Everolimus is an inhibitor of mammalian target of rapamycin (mTOR), a serine-threonine kinase, downstream of the PI3K/AKT pathway. The mTOR pathway is dysregulated in several human cancers and in tuberous sclerosis complex (TSC). Everolimus binds to an intracellular protein, FKBP-12, resulting in an inhibitory complex formation with mTOR complex 1 (mTORC1) and thus inhibition of mTOR kinase activity.
Everolimus reduced the activity of S6 ribosomal protein kinase (S6K1) and eukaryotic initiation factor 4E-binding protein (4E-BP1), downstream effectors of mTOR, involved in protein synthesis. S6K1 is a substrate of mTORC1 and phosphorylates the activation domain 1 of the estrogen receptor which results in ligand-independent activation of the receptor. In addition, everolimus inhibited the expression of hypoxia-inducible factor (e.g., HIF-1) and reduced the expression of vascular endothelial growth factor (VEGF).
Inhibition of mTOR by everolimus has been shown to reduce cell proliferation, angiogenesis, and glucose uptake in in vitro and/or in vivo studies. Constitutive activation of the PI3K/Akt/mTOR pathway can contribute to endocrine resistance in breast cancer. In vitro studies show that estrogen-dependent and HER2+ breast cancer cells are sensitive to the inhibitory effects of everolimus, and that combination treatment with everolimus and Akt, HER2, or aromatase inhibitors enhances the anti-tumor activity of everolimus in a synergistic manner.
Two regulators of mTORC1 signalling are the oncogene suppressors tuberin-sclerosis complexes 1 and 2 ( TSC1, TSC2 ). Loss or inactivation of either TSC1 or TSC2 leads to activation of downstream signalling. In TSC, a genetic disorder, inactivating mutations in either the TSC1 or the TSC2 gene lead to hamartoma formation throughout the body as well as seizures and epileptogenesis.
Overactivation of mTOR results in neuronal dysplasia, aberrant axonogenesis and dendrite formation, increased excitatory synaptic currents, reduced myelination, and disruption of the cortical laminar structure causing abnormalities in neuronal development and function. Treatment with an mTOR inhibitor in animal models of mTOR dysregulation in the brain resulted in seizure suppression, prevention of the development of new-onset seizures, and prevention of premature death.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING TORPENZtablets® for oral use are available containing 2.5 mg, 5 mg, 7.5 mg, or 10 mg of everolimus. The 2.5 mg tablets are white to off white, capsule shaped, flat faced, beveled edged tablets debossed with "B 2.5" on one side and plain on the other side. They are supplied as follows: Bottles of 30 with a child-resistant closure, NDC 0245-0822-30 Unit-Dose cartons of 28, NDC 0245-0822-04 (4 blister cards with embedded desiccants containing 7 tablets each) The 5 mg tablets are white to off white, capsule shaped, flat faced, beveled edged tablets debossed with "B 5" on one side and plain on the other side.
They are supplied as follows: Bottles of 30 with a child-resistant closure, NDC 0245-0823-30 Unit-Dose cartons of 28, NDC 0245-0823-04 (4 blister cards with embedded desiccants containing 7 tablets each) The 7.5 mg tablets are white to off white, capsule shaped, flat faced, beveled edged tablets debossed with "B 7.5" on one side and plain on the other side. They are supplied as follows: Bottles of 30 with a child-resistant closure, NDC 0245-0824-30 Unit-Dose cartons of 28, NDC 0245-0824-04 (4 blister cards with embedded desiccants containing 7 tablets each) The 10 mg tablets are white to off white, capsule shaped, flat faced, beveled edged tablets debossed with "B 10" on one side and plain on the other side.
They are supplied as follows: Bottles of 30 with a child-resistant closure, NDC 0245-0825-30 Unit-Dose cartons of 28, NDC 0245-0825-04 (4 blister cards with embedded desiccants containing 7 tablets each)
📦 Storage and Handling ▾
Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature]. Store in the original container, protect from light and moisture. Follow special handling and disposal procedures for anti-cancer pharmaceuticals. 1
📋 Description ▾
11 DESCRIPTION TORPENZ (everolimus) tablets are a kinase inhibitor. The chemical name of everolimus is (1R,9S,12S,15R,16E,18R,19R,21R,23S,24E,26E,28E,30S,32S,35R)-1,18- dihydroxy-12-{(1R)-2-[(1S,3R,4R)-4-(2-hydroxyethoxy)-3-methoxycyclohexyl]-1-methylethyl}-19,30-dimethoxy- 15,17,21,23,29,35-hexamethyl-11,36-dioxa-4-aza-tricyclo[30.3.1.0 4,9 ]hexatriaconta-16,24,26,28-tetraene-2,3,10,14,20-pentaone. The molecular formula is C 53 H 83 NO 14 and the molecular weight is 958.2 g/mol.
The structural formula is: TORPENZ tablets for oral administration contains 2.5 mg, 5 mg, 7.5 mg, or 10 mg of everolimus and the following inactive ingredients: anhydrous lactose, butylated hydroxytoluene, crospovidone, hypromellose, lactose monohydrate, and magnesium stearate. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Non-infectious Pneumonitis Advise patients of the risk of developing non-infectious pneumonitis and to immediately report any new or worsening respiratory symptoms to their healthcare provider [see Warnings and Precautions (5.1) ] . Infections Advise patients that they are more susceptible to infections and that they should immediately report any signs or symptoms of infections to their healthcare provider [see Warnings and Precautions (5.2) ] .
Hypersensitivity Reactions Advise patients of the risk of clinically significant hypersensitivity reactions and to promptly contact their healthcare provider or seek emergency care for signs of hypersensitivity reaction, including rash, itching, hives, difficulty breathing or swallowing, flushing, chest pain, or dizziness [see Contraindications (4) , Warnings and Precautions (5.3) ] . Angioedema with Concomitant Use of ACE Inhibitors Advise patients to avoid ACE inhibitors and to promptly contact their healthcare provider or seek emergency care for signs or symptoms of angioedema [see Warnings and Precautions (5.4) ] .
Stomatitis Advise patients of the risk of stomatitis and to use alcohol-free mouthwashes during treatment [see Warnings and Precautions (5.5) ] . Renal Impairment Advise patients of the risk of developing kidney failure and the need to monitor their kidney function periodically during treatment [see Warnings and Precautions (5.6) ] . Risk of Impaired Wound Healing Advise patients that TORPENZ may impair wound healing.
Advise patients to inform their healthcare provider of any planned surgical procedure [see Warnings and Precautions (5.7) ] . Geriatric Patients Inform patients that in a study conducted in patients with breast cancer, the incidence of deaths and adverse reactions leading to permanent discontinuation was higher in patients ≥ 65 years compared to patients < 65 years [see Warnings and Precautions (5.8) , Use in Specific Populations (8.5) ]. Metabolic Disorders Advise patients of the risk of metabolic disorders and the need to monitor glucose and lipids periodically during therapy [see Warnings and Precautions (5.9) ] .
Myelosuppression Advise patients of the risk of myelosuppression and the need to monitor CBCs periodically during therapy [see Warnings and Precautions (5.10) ] . Risk of Infection or Reduced Immune Response with Vaccination Advise patients to avoid the use of live vaccines and close contact with those who have received live vaccines [see Warnings and Precautions (5.11) ] . Embryo-Fetal Toxicity Advise females of reproductive potential of the potential risk to a fetus.
Advise females of reproductive potential to use effective contraception during treatment and for 8 weeks after the last dose. Advise patients to inform their healthcare provider of a known or suspected pregnancy. Advise males with female partners of reproductive potential to use effective contraception during treatment and for 4 weeks after the last dose [see Warnings and Precautions (5.13) , Use in Specific Populations (8.1 , 8.3) ] .
Radiation Sensitization and Radiation Recall Radiation sensitization and recall can occur in patients treated with radiation prior to, during, or subsequent to TORPENZ treatment. Advise patients to inform their healthcare provider if they have had or are planning to receive radiation therapy [see Warnings and Precautions (5.12) ] . Lactation Advise women not to breastfeed during treatment with TORPENZ and for 2 weeks after the last dose [see Use in Specific Populations (8.2) ] .
Infertility Advise males and females of reproductive potential of the potential risk for impaired fertility [see Use in Specific Populations (8.3) ] .
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption After administration of everolimus tablets in patients with advanced solid tumors, peak everolimus concentrations are reached 1 to 2 hours after administration of oral doses ranging from 5 mg to 70 mg. Following single doses, C max is dose-proportional with daily dosing between 5 mg and 10 mg. With single doses of 20 mg and higher, the increase in C max is less than dose-proportional; however, AUC shows dose-proportionality over the 5 mg to 70 mg dose range.
Steady-state was achieved within 2 weeks following once-daily dosing. In patients with TSC-associated SEGA, everolimus C min was approximately dose-proportional within the dose range from 1.35 mg/m 2 to 14.4 mg/m 2 . Effect of Food In healthy subjects, a high-fat meal (containing approximately 1,000 calories and 55 grams of fat) reduced systemic exposure to everolimus tablets 10 mg (as measured by AUC) by 22% and the peak blood concentration C max by 54%.
Light-fat meals (containing approximately 500 calories and 20 grams of fat) reduced AUC by 32% and C max by 42%. Distribution The blood-to-plasma ratio of everolimus, which is concentration-dependent over the range of 5 to 5,000 ng/mL, is 17% to 73%. The amount of everolimus confined to the plasma is approximately 20% at blood concentrations observed in cancer patients given everolimus tablets 10 mg orally once daily.
Plasma protein binding is approximately 74% both in healthy subjects and in patients with moderate hepatic impairment. Elimination The mean elimination half-life of everolimus is approximately 30 hours. Metabolism Everolimus is a substrate of CYP3A4.
Following oral administration, everolimus is the main circulating component in human blood. Six main metabolites of everolimus have been detected in human blood, including three monohydroxylated metabolites, two hydrolytic ring-opened products, and a phosphatidylcholine conjugate of everolimus. These metabolites were also identified in animal species used in toxicity studies and showed approximately 100-times less activity than everolimus itself.
Excretion No specific elimination studies have been undertaken in cancer patients. Following the administration of a 3 mg single dose of radiolabeled everolimus in patients who were receiving cyclosporine, 80% of the radioactivity was recovered from the feces, while 5% was excreted in the urine. The parent substance was not detected in urine or feces.
Specific Populations No relationship was apparent between oral clearance and age or sex in patients with cancer. Patients with Renal Impairment No significant influence of creatinine clearance (25 to 178 mL/min) was detected on oral clearance (CL/F) of everolimus. Patients with Hepatic Impairment Compared to normal subjects, there was a 1.8-fold, 3.2-fold, and 3.6-fold increase in AUC for subjects with mild (Child-Pugh class A), moderate (Child-Pugh class B), and severe (Child-Pugh class C) hepatic impairment, respectively.
In another study, the average AUC of everolimus in subjects with moderate hepatic impairment (Child-Pugh class B) was twice that found in subjects with normal hepatic function [see Dosage and Administration (2.10) , Use in Specific Populations (8.6) ] . Pediatric Patients In patients with TSC-associated SEGA, the mean C min values normalized to mg/m 2 dose in pediatric patients (< 18 years of age) were lower than those observed in adults, suggesting that everolimus clearance adjusted to BSA was higher in pediatric patients as compared to adults.
Race or Ethnicity Based on a cross-study comparison, Japanese patients had on average exposures that were higher than non-Japanese patients receiving the same dose. Oral clearance (CL/F) is on average 20% higher in black patients than in white patients. Drug Interaction Studies Effect of CYP3A4 and P-glycoprotein (P-gp) Inhibitors on Everolimus Everolimus exposure increased when everolimus tablets were coadministered with: ketoconazole (a P-gp and strong CYP3A4 inhibitor) – C max… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Exposure-Response Relationship In patients with TSC-associated subependymal giant cell astrocytoma (SEGA), the magnitude of the reduction in SEGA volume was correlated with the everolimus trough concentration. Cardiac Electrophysiology In a randomized, placebo-controlled, cross-over study, 59 healthy subjects were administered a single oral dose of everolimus tablets (20 mg and 50 mg) and placebo. Everolimus tablets at single doses up to 50 mg did not prolong the QT/QTc interval.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Hormone Receptor-Positive, HER2-Negative Breast Cancer A randomized, double-blind, multicenter study (BOLERO-2, NCT00863655) of everolimus tablets in combination with exemestane vs. placebo in combination with exemestane was conducted in 724 postmenopausal women with estrogen receptor-positive, HER2-negative advanced breast cancer with recurrence or progression following prior therapy with letrozole or anastrozole. Randomization was stratified by documented sensitivity to prior hormonal therapy (yes vs. no) and by the presence of visceral metastasis (yes vs. no).
Sensitivity to prior hormonal therapy was defined as either (1) documented clinical benefit (complete response [CR], partial response [PR], stable disease ≥ 24 weeks) to at least one prior hormonal therapy in the advanced setting or (2) at least 24 months of adjuvant hormonal therapy prior to recurrence. Patients were permitted to have received 0 to 1 prior lines of chemotherapy for advanced disease. The major efficacy outcome measure was progression-free survival (PFS) evaluated by RECIST (Response Evaluation Criteria in Solid Tumors), based on investigator (local radiology) assessment.
Other outcome measures included overall survival (OS) and objective response rate (ORR). Patients were randomized 2:1 to everolimus tablets 10 mg orally once daily in combination with exemestane 25 mg once daily (n = 485) or to placebo in combination with exemestane 25 mg orally once daily (n = 239). The two treatment groups were generally balanced with respect to baseline demographics and disease characteristics.
Patients were not permitted to cross over to everolimus tablets at the time of disease progression. The trial demonstrated a statistically significant improvement in PFS by investigator assessment (Table 20 and Figure 1). The results of the PFS analysis based on independent central radiological assessment were consistent with the investigator assessment.
PFS results were also consistent across the subgroups of age, race, presence and extent of visceral metastases, and sensitivity to prior hormonal therapy. ORR was higher in the everolimus tablets in combination with exemestane arm vs. the placebo in combination with exemestane arm (Table 20). There were 3 complete responses (0.6%) and 58 partial responses (12%) in the everolimus tablets arm.
There were no complete responses and 4 partial responses (1.7%) in the placebo in combination with exemestane arm. After a median follow-up of 39.3 months, there was no statistically significant difference in OS between the everolimus tablets in combination with exemestane arm and the placebo in combination with exemestane arm [HR 0.89 (95% CI: 0.73, 1.10)]. Table 20: Efficacy Results in Hormone-Receptor Positive, HER-2 Negative Breast Cancer in BOLERO-2 Analysis Everolimus Tablets with Exemestane N=485 Placebo with Exemestane N=239 Hazard ratio p-value Median progression-free survival (months, 95% CI) Investigator 7.8 3.2
0.4Hazard ratio is obtained from the stratified Cox proportional-hazards model by sensitivity to prior hormonal therapy and presence of visceral metastasis <0.0001 p-value is obtained from the one-sided log-rank test stratified by sensitivity to prior hormonal therapy and presence of visceral metastasis Radiological review (6.9, 8.5) (2.8, 4.1) (0.38, 0.54) Independent 11.0 4.1 0.38 <0.0001 Radiological review (9.7, 15.0) (2.9, 5.6) (0.3, 0.5) Best overall response (%, 95 CI) Objective response 12.6% 1.7% n/a Not applicable Rate (ORR) Objective response rate = proportion of patients with CR or PR (9.8, 15.9) (0.5, 4.2) Figure 1: Kaplan-Meier Curves for Progression-Free Survival by Investigator Radiological Review in Hormone Receptor-Positive, HER-2 Negative Breast Cancer in BOLERO-2 Figure 1
14.4Tuberous Sclerosis Complex (TSC)-Associated Renal Angiomyolipoma A randomized (2:1), double-blind, placebo-controlled trial (EXIST-2, NCT00790400) of everolimus tablets was conducted in 118 patients w… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Administration of everolimus for up to 2 years did not indicate oncogenic potential in mice and rats up to the highest doses tested (0.9 mg/kg) corresponding, respectively to 3.9 and 0.2 times the estimated human exposure based on AUC at the recommended dose of everolimus 10 mg orally once daily. Everolimus was not genotoxic in a battery of in vitroassays (Ames mutation test in Salmonella, mutation test in L5178Y mouse lymphoma cells, and chromosome aberration assay in V79 Chinese hamster cells).
Everolimus was not genotoxic in an in vivomouse bone marrow micronucleus test at doses up to 500 mg/kg/day (1,500 mg/m 2/day, approximately 255-fold the recommended dose of everolimus tablets 10 mg orally once daily, and approximately 200-fold the median dose administered to patients with TSC-associated SEGA, based on the BSA), administered as 2 doses, 24 hours apart. Based on non-clinical findings, TORPENZ may impair male fertility. In a 13-week male fertility study in rats, testicular morphology was affected at doses of 0.5 mg/kg and above.
Sperm motility, sperm count, and plasma testosterone levels were diminished in rats treated with 5 mg/kg. The exposures at these doses (52 ng∙hr/mL and 414 ng∙hr/mL, respectively) were within the range of human exposure at the recommended dose of everolimus tablets 10 mg orally once daily (560 ng∙hr/mL) and resulted in infertility in the rats at 5 mg/kg. Effects on male fertility occurred at AUC 0–24hvalues 10% to 81% lower than human exposure at the recommended dose of everolimus tablets 10 mg orally once daily.
After a 10 to 13 week non-treatment period, the fertility index increased from zero (infertility) to 60%. Oral doses of everolimus in female rats at doses ≥ 0.1 mg/kg (approximately 4% the human exposure based on AUC at the recommended dose of everolimus tablets 10 mg orally once daily) resulted in increased incidence of pre-implantation loss, suggesting that the drug may reduce female fertility.
13.2Animal Toxicology and/or Pharmacology In juvenile rat toxicity studies, dose-related delayed attainment of developmental landmarks, including delayed eye-opening, delayed reproductive development in males and females and increased latency time during the learning and memory phases were observed at doses as low as 0.15 mg/kg/day.
📚 References ▾
15 REFERENCES OSHA Hazardous Drugs. OSHA . http://www.osha.gov/SLTC/hazardousdrugs/index.html.
📄 Patient Package Insert ▾
Patient Information TORPENZ ® (TOR-penz) (everolimus) Tablets for oral use Read this Patient Information leaflet that comes with TORPENZ tablets before you start taking it and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your medical condition or treatment.
What is the most important information I should know about TORPENZ tablets? TORPENZ tablets can cause serious side effects, including: 1. You may develop lung or breathing problems.
In some people lung or breathing problems may be severe and can lead to death. Tell your healthcare provider right away if you have any of these symptoms: New or worsening cough Shortness of breath Chest pain Difficulty breathing or wheezing 2 . You may be more likely to develop an infection, such as pneumonia, or a bacterial, fungal or viral infection.
Viral infections may include active hepatitis B in people who have had hepatitis B in the past (reactivation). In some people (including adults and children) these infections may be severe and can lead to death. You may need to be treated as soon as possible.
Tell your healthcare provider right away if you have a temperature of 100.5°F or above, chills, or do not feel well. Symptoms of hepatitis B or infection may include the following: Fever Chills Skin rash Joint pain and swelling Tiredness Loss of appetite Nausea Pale stools or dark urine Yellowing of the skin Pain in the upper right side of the stomach 3. Severe allergic reactions.
Call your healthcare provider or get medical help right away if you get signs and symptoms of a severe allergic reaction, including: rash, itching, hives, flushing, trouble breathing or swallowing, chest pain or dizziness 4. Possible increased risk for a type of allergic reaction called angioedema, in people who take an Angiotensin-Converting Enzyme (ACE) inhibitor medicine during treatment with TORPENZ tablets. Talk with your healthcare provider before taking TORPENZ tablets if you are not sure if you take an ACE inhibitor medicine.
Get medical help right away if you have trouble breathing or develop swelling of your tongue, mouth, or throat during treatment with TORPENZ tablets. 5. Mouth ulcers and sores.
Mouth ulcers and sores are common during treatment with TORPENZ tablets but can also be severe. When you start treatment with TORPENZ tablets, your healthcare provider may tell you to also start a prescription mouthwash to reduce the likelihood of getting mouth ulcers or sores and to reduce their severity. Follow your healthcare provider's instructions on how to use this prescription mouthwash.
If you develop pain, discomfort, or open sores in your mouth, tell your healthcare provider. Your healthcare provider may tell you to restart this mouthwash or to use a special mouthwash or mouth gel that does not contain alcohol, peroxide, iodine, or thyme. 6 .
You may develop kidney failure. In some people this may be severe and can lead to death. Your healthcare provider should do tests to check your kidney function before and during your treatment with TORPENZ tablets.
If you have any of the serious side effects listed above, you may need to stop taking TORPENZ tablets for a while or use a lower dose. Follow your healthcare provider's instructions. What are TORPENZ tablets?
TORPENZ tablets are a prescription medicine used to treat: advanced hormone receptor-positive, HER2-negative breast cancer, along with the medicine exemestane, in postmenopausal women who have already received certain other medicines for their cancer. TORPENZ tablets are not for use in people with carcinoid tumors that actively produce hormones. people with the following types of tumors that are seen with a genetic condition called tuberous sclerosis complex (TSC): adults with a kidney tumor called angiomyolipoma, when their kidney tumor does not require surgery right away. adults and children 1 year of age and older with a genetic condition called tu… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 2.5 mg Unit-Dose Tablet Carton NDC 0245-0822-04 TORPENZ™ (everolimus) Tablets 2.5 mg 28 Tablets Rx only UPSHER-SMITH Principal Display Panel - 2.5 mg Unit-Dose Carton
PRINCIPAL DISPLAY PANEL - 5 mg Unit-Dose Tablet Carton NDC 0245-0823-04 TORPENZ™ (everolimus) Tablets 5 mg 28 Tablets Rx only UPSHER-SMITH Principal Display Panel - 5 mg Unit-Dose Carton
PRINCIPAL DISPLAY PANEL - 7.5 mg Unit-Dose Tablet Carton NDC 0245-0824-04 TORPENZ™ (everolimus) Tablets 7.5 mg 28 Tablets Rx only UPSHER-SMITH Principal Display Panel - 7.5 mg Unit-Dose Tablet Carton
PRINCIPAL DISPLAY PANEL - 10 mg Unit-dose Tablet Carton NDC 0245-0825-04 TORPENZ™ (everolimus) Tablets 10 mg 28 Tablets Rx only UPSHER-SMITH Principal Display Panel - 10 mg Unit-dose Tablet Carton