
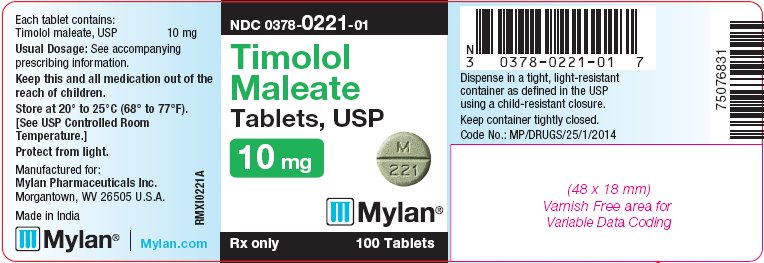
Timolol Maleate 10 mg Tablet, 100-count — NDC 0378-0221-01 (Billing 00378-0221-01)
This is a package of 100 tablets of Timolol Maleate 10 mg Tablet from Mylan Pharmaceuticals Inc., marketed since Jun 1990 and currently FDA-listed, this package's marketing is listed to end Mar 2027. It is this product's only package size.
Other active recalls for Timolol Maleate (different manufacturers) — 6 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 005140
- GCN: 20670
- GPI-14 (Medi-Span): 33100050100310
- HICL (First Databank): 002105
- AHFS class code: 12:16.08.04
- RxCUI (RxNorm): 198284
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the beta-Adrenergic Blocker class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Timolol is used to treat high blood pressure and to improve survival after a heart attack. It is also used to prevent migraine headaches. Timolol is in a class of medications called beta blockers. It works by relaxing blood vessels and slowing heart rate to improve blood flow and decrease blood pressure.
Read the full MedlinePlus article ↗- It depends on the form. The eye drops lower high pressure in the eye from ocular hypertension or open-angle glaucoma. The tablets treat high blood pressure, lower the risk of death...
- Put the drop in the affected eye as directed, usually once or twice a day depending on your product. If yours is a gel-forming type, shake the closed bottle once first. Wait at lea...
- Burning or stinging right after the drops go in is the most common. Blurred vision, redness, itching and headache can also happen. Call your doctor if you notice wheezing, a very s...
- If your drops contain benzalkonium chloride, soft lenses can absorb it. Take your lenses out before using the drops and wait 15 minutes before putting them back in.
Patient education
Supplement & herbal interactions
Timolol may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $1.16 | $116.11 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00378-0221-01 You're viewing this Main listing | 100 TABLET in 1 BOTTLE, PLASTIC | 1990-06-08 | Mar 31, 2027 | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Timolol Maleate 10 mgthis 00378-0221-01 | Mylan | 100 tablets | — | AB | FDA listed | — |
| Timolol Maleate 10 mg 16571-0224-01 | Rising | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Hypertension Timolol maleate tablets are indicated for the treatment of hypertension. They may be used alone or in combination with other antihypertensive agents, especially thiazide-type diuretics. Myocardial Infarction Timolol is indicated in patients who have survived the acute phase of myocardial infarction, and are clinically stable, to reduce cardiovascular mortality and the risk of reinfarction.
Migraine Timolol is indicated for the prophylaxis of migraine headache.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Hypertension The usual initial dosage of timolol maleate is 10 mg twice a day, whether used alone or added to diuretic therapy. Dosage may be increased or decreased depending on heart rate and blood pressure response. The usual total maintenance dosage is 20 to 40 mg per day.
Increases in dosage to a maximum of 60 mg per day divided into two doses may be necessary. There should be an interval of at least 7 days between increases in dosages. Timolol maleate tablets may be used with a thiazide diuretic or with other antihypertensive agents.
Patients should be observed carefully during initiation of such concomitant therapy. Myocardial Infarction The recommended dosage for long-term prophylactic use in patients who have survived the acute phase of a myocardial infarction is 10 mg given twice daily (see CLINICAL PHARMACOLOGY ). Migraine The usual initial dosage of timolol maleate is 10 mg twice a day.
During maintenance therapy the 20 mg daily dosage may be administered as a single dose. Total daily dosage may be increased to a maximum of 30 mg, given in divided doses, or decreased to 10 mg once per day, depending on clinical response and tolerability. If a satisfactory response is not obtained after 6 to 8 weeks use of the maximum daily dosage, therapy with timolol should be discontinued.
⛔ Contraindications ▾
CONTRAINDICATIONS Timolol maleate is contraindicated in patients with bronchial asthma or with a history of bronchial asthma, or severe chronic obstructive pulmonary disease (see WARNINGS ); sinus bradycardia; second- and third-degree atrioventricular block; overt cardiac failure (see WARNINGS ); cardiogenic shock; hypersensitivity to this product.
⚠️ Warnings ▾
WARNINGS Cardiac Failure Sympathetic stimulation may be essential for support of the circulation in individuals with diminished myocardial contractility, and its inhibition by beta-adrenergic receptor blockade may precipitate more severe failure. Although beta-blockers should be avoided in overt congestive heart failure, they can be used, if necessary, with caution in patients with a history of failure who are well compensated, usually with digitalis and diuretics. Both digitalis and timolol maleate slow AV conduction.
If cardiac failure persists, therapy with timolol maleate should be withdrawn. In Patients Without a History of Cardiac Failure Continued depression of the myocardium with beta-blocking agents over a period of time can, in some cases, lead to cardiac failure. At the first sign or symptom of cardiac failure, patients receiving timolol should be digitalized and/or be given a diuretic, and the response observed closely.
If cardiac failure continues, despite adequate digitalization and diuretic therapy, timolol should be withdrawn. Exacerbation of Ischemic Heart Disease Following Abrupt Withdrawal Hypersensitivity to catecholamines has been observed in patients withdrawn from beta-blocker therapy; exacerbation of angina and, in some cases, myocardial infarction have occurred after abrupt discontinuation of such therapy. When discontinuing chronically administered timolol maleate, particularly in patients with ischemic heart disease, the dosage should be gradually reduced over a period of one to two weeks and the patient should be carefully monitored.
If angina markedly worsens or acute coronary insufficiency develops, timolol maleate administration should be reinstituted promptly, at least temporarily, and other measures appropriate for the management of unstable angina should be taken. Patients should be warned against interruption or discontinuation of therapy without the physician’s advice. Because coronary artery disease is common and may be unrecognized, it may be prudent not to discontinue timolol maleate therapy abruptly even in patients treated only for hypertension.
Obstructive Pulmonary Disease PATIENTS WITH CHRONIC OBSTRUCTIVE PULMONARY DISEASE (e.g., CHRONIC BRONCHITIS, EMPHYSEMA) OF MILD OR MODERATE SEVERITY, BRONCHOSPASTIC DISEASE OR A HISTORY OF BRONCHOSPASTIC DISEASE (OTHER THAN BRONCHIAL ASTHMA OR A HISTORY OF BRONCHIAL ASTHMA, IN WHICH ‘TIMOLOL MALEATE’ IS CONTRAINDICATED, see CONTRAINDICATIONS ), SHOULD IN GENERAL NOT RECEIVE BETA-BLOCKERS, INCLUDING ‘TIMOLOL’. However, if timolol is necessary in such patients, then the drug should be administered with caution since it may block bronchodilation produced by endogenous and exogenous catecholamine stimulation of beta 2 receptors.
Major Surgery The necessity or desirability of withdrawal of beta-blocking therapy prior to major surgery is controversial. Beta-adrenergic receptor blockade impairs the ability of the heart to respond to beta-adrenergically mediated reflex stimuli. This may augment the risk of general anesthesia in surgical procedures.
Some patients receiving beta-adrenergic receptor blocking agents have been subject to protracted severe hypotension during anesthesia. Difficulty in restarting and maintaining the heartbeat has also been reported. For these reasons, in patients undergoing elective surgery, some authorities recommend gradual withdrawal of beta-adrenergic receptor blocking agents.
If necessary during surgery, the effects of beta-adrenergic blocking agents may be reversed by sufficient doses of such agonists as isoproterenol, dopamine, dobutamine or norepinephrine (see OVERDOSAGE ). Diabetes Mellitus Timolol should be administered with caution in patients subject to spontaneous hypoglycemia or to diabetic patients (especially those with labile diabetes) who are receiving insulin or oral hypoglycemic agents. Beta-adrenergic receptor blocking agents may mask the signs and symptoms of acute hypoglycemia.
Thyrotoxicosis Beta-adrener… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Timolol maleate tablets are usually well tolerated in properly selected patients. Most adverse effects have been mild and transient. In a multi-center (12 week) clinical trial comparing timolol maleate and placebo in hypertensive patients, the following adverse reactions were reported spontaneously and considered to be causally related to timolol maleate: Timolol Maleate (n=176) % Placebo (n=168) % BODY AS A WHOLE fatigue/tiredness 3.4 0.6 headache 1.7 1.8 chest pain 0.6 0 asthenia 0.6 0 CARDIOVASCULAR bradycardia 9.1 0 arrhythmia 1.1 0.6 syncope 0.6 0 edema 0.6
1.2DIGESTIVE dyspepsia 0.6 0.6 nausea 0.6 0 SKIN pruritus 1.1 0 NERVOUS SYSTEM dizziness 2.3 1.2 vertigo 0.6 0 paresthesia 0.6 0 PSYCHIATRIC decreased libido 0.6 0 RESPIRATORY dyspnea 1.7 0.6 bronchial spasm 0.6 0 rales 0.6 0 SPECIAL SENSES eye irritation 1.1 0.6 tinnitus 0.6 0 These data are representative of the incidence of adverse effects that may be observed in properly selected patients treated with timolol maleate, i.e., excluding patients with bronchospastic disease, congestive heart failure or other contraindications to beta-blocker therapy.
In patients with migraine the incidence of bradycardia was 5 percent. In a coronary artery disease population studied in the Norwegian multi-center trial (see CLINICAL PHARMACOLOGY ), the frequency of the principal adverse reactions and the frequency with which these resulted in discontinuation of therapy in the timolol and placebo groups were: Adverse Reaction When an adverse reaction recurred in a patient, it is listed only once. Withdrawal Only principal reason for withdrawal in each patient is listed.
These adverse reactions can also occur in patients treated for hypertension. Timolol Placebo Timolol Placebo (n=945) (n=939) (n=945) (n=939) % % % % Asthenia or Fatigue 5 1 <1 <1 Heart Rate < 40 beats/minute 5 <1 4 <1 Cardiac Failure-Nonfatal 8 7 3 2 Hypotension 3 2 3 1 Pulmonary Edema-Nonfatal 2 <1 <1 <1 Claudication 3 3 1 <1 AV Block 2nd or 3rd Degree <1 <1 <1 <1 Sinoatrial Block <1 <1 <1 <1 Cold Hands and Feet 8 <1 <1 0 Nausea or Digestive Disorders 8 6 1 <1 Dizziness 6 4 1 0 Bronchial Obstruction 2 <1 1 <1 The following additional adverse effects have been reported in clinical experience with the drug: Body as a Whole: anaphylaxis, extremity pain, decreased exercise tolerance, weight loss, fever; Cardiovascular: cardiac arrest, cardiac failure, cerebral vascular accident, worsening of angina pectoris, worsening of arterial insufficiency, Raynaud’s phenomenon, palpitations, vasodilatation; Digestive: gastrointestinal pain, hepatomegaly, vomiting, diarrhea, dyspepsia; Hematologic: nonthrombocytopenic purpura; Endocrine: hyperglycemia, hypoglycemia; Skin: rash, skin irritation, increased pigmentation, sweating, alopecia; Musculoskeletal: arthralgia; Nervous System: local weakness, increase in signs and symptoms of myasthenia gravis; Psychiatric: depression, nightmares, somnolence, insomnia, nervousness, diminished concentration, hallucinations; Respiratory: cough; Special Senses: visual disturbances, diplopia, ptosis, dry eyes; Urogenital: impotence, urination difficulties.
There have been reports of retroperitoneal fibrosis in patients receiving timolol maleate and in patients receiving other beta-adrenergic blocking agents. A causal relationship between this condition and therapy with beta-adrenergic blocking agents has not been established. Potential Adverse Effects In addition, a variety of adverse effects not observed in clinical trials with timolol maleate, but reported with other beta-adrenergic blocking agents, should be considered potential adverse effects of timolol.
Nervous System: Reversible mental depression progressing to catatonia; an acute reversible syndrome characterized by disorientation for time and place, short-term memory loss, emotional lability, slightly clouded sensorium, and decreased performance on neuropsychometrics; Cardiovascular: Intensification of AV block (see CONTRAIND… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
Drug Interactions Catecholamine-Depleting Drugs Close observation of the patient is recommended when timolol is administered to patients receiving catecholamine-depleting drugs such as reserpine, because of possible additive effects and the production of hypotension and/or marked bradycardia, which may produce vertigo, syncope, or postural hypotension. Non-Steroidal Anti-Inflammatory Drugs Blunting of the antihypertensive effect of beta-adrenoceptor blocking agents by non-steroidal anti-inflammatory drugs has been reported.
When using these agents concomitantly, patients should be observed carefully to confirm that the desired therapeutic effect has been obtained. Calcium Antagonists Literature reports suggest that oral calcium antagonists may be used in combination with beta-adrenergic blocking agents when heart function is normal, but should be avoided in patients with impaired cardiac function. Hypotension, AV conduction disturbances, and left ventricular failure have been reported in some patients receiving beta-adrenergic blocking agents when an oral calcium antagonist was added to the treatment regimen.
Hypotension was more likely to occur if the calcium antagonist were a dihydropyridine derivative, e.g., nifedipine, while left ventricular failure and AV conduction disturbances were more likely to occur with either verapamil or diltiazem. Intravenous calcium antagonists should be used with caution in patients receiving beta-adrenergic blocking agents. Digitalis and Either Diltiazem or Verapamil The concomitant use of beta-adrenergic blocking agents with digitalis and either diltiazem or verapamil may have additive effects in prolonging AV conduction time.
Quinidine Potentiated systemic beta-blockade (e.g., decreased heart rate) has been reported during combined treatment with quinidine and timolol, possibly because quinidine inhibits the metabolism of timolol via the P-450 enzyme, CYP2D6. Clonidine Beta-adrenergic blocking agents may exacerbate the rebound hypertension which can follow the withdrawal of clonidine. If the two drugs are coadministered, the beta-adrenergic blocking agent should be withdrawn several days before the gradual withdrawal of clonidine.
If replacing clonidine by beta-blocker therapy, the introduction of beta-adrenergic blocking agents should be delayed for several days after clonidine administration has stopped.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects Teratogenicity studies with timolol in mice, rats and rabbits at doses up to 50 mg/kg/day (approximately 40 times * the maximum recommended daily human dose) showed no evidence of fetal malformations. Although delayed fetal ossification was observed at this dose in rats, there were no adverse effects on postnatal development of offspring. Doses of 1000 mg/kg/day (approximately 830 times * the maximum recommended daily human dose) were maternotoxic in mice and resulted in an increased number of fetal resorptions.
Increased fetal resorptions were also seen in rabbits at doses of approximately 40 times * the maximum recommended daily human dose, in this case without apparent maternotoxicity. There are no adequate and well controlled studies in pregnant women. Timolol should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of timolol for the treatment of hypertension or migraine did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In a clinical study of timolol in patients who had survived the acute phase of a myocardial infarction, approximately 350 patients (37%) were 65 to 75 years of age. Safety and efficacy were not different between these patients and younger patients (see CLINICAL PHARMACOLOGY: Pharmacodynamics ).
Other reported clinical experience has not identified differences in response between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal or cardiac function, and of concomitant disease or other drug therapy. This drug is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function.
Because elderly patients are likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function. (See PRECAUTIONS: Impaired Hepatic or Renal Function and Dosing in the Presence of Marked Renal Failure .) The results from 5 single- and/or multiple-dose PK studies comparing the impact of age on the PK of hydrochlorothiazide, when given in combination with other antihypertensive drugs, were consistent. They indicated a mean median increase in C max and AUC of 38% and 99% respectively, in elderly relative to younger subjects. * Based on patient weight of 50 kg.
🆘 Overdosage ▾
OVERDOSAGE Overdosage has been reported with timolol maleate tablets. A 30 year old female ingested 650 mg of timolol maleate (maximum recommended daily dose - 60 mg) and experienced second- and third-degree heart block. She recovered without treatment but approximately 2 months later developed irregular heart beat, hypertension, dizziness, tinnitus, faintness, increased pulse rate and borderline first degree heart block.
The oral LD 50 of the drug is 1190 and 900 mg/kg in female mice and female rats, respectively. An in vitro hemodialysis study, using 14 C timolol added to human plasma or whole blood, showed that timolol was readily dialyzed from these fluids; however, a study of patients with renal failure showed that timolol did not dialyze readily. The most common signs and symptoms to be expected with overdosage with a beta-adrenergic receptor blocking agent are symptomatic bradycardia, hypotension, bronchospasm, and acute cardiac failure.
Therapy with timolol should be discontinued and the patient observed closely. The following additional therapeutic measures should be considered: (1) Gastric lavage. (2) Symptomatic bradycardia: Use atropine sulfate intravenously in a dosage of 0.25 mg to 2 mg to induce vagal blockade.
If bradycardia persists, intravenous isoproterenol hydrochloride should be administered cautiously. In refractory cases the use of a transvenous cardiac pacemaker may be considered. (3) Hypotension: Use sympathomimetic pressor drug therapy, such as dopamine, dobutamine or norepinephrine.
In refractory cases the use of glucagon hydrochloride has been reported to be useful. (4) Bronchospasm: Use isoproterenol hydrochloride. Additional therapy with aminophylline may be considered.
(5) Acute cardiac failure: Conventional therapy with digitalis, diuretics, and oxygen should be instituted immediately. In refractory cases the use of intravenous aminophylline is suggested. This may be followed if necessary by glucagon hydrochloride which has been reported to be useful.
(6) Heart block (second- or third-degree): Use isoproterenol hydrochloride or a transvenous cardiac pacemaker.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Timolol maleate is a beta 1 and beta 2 (nonselective) adrenergic receptor blocking agent that does not have significant intrinsic sympathomimetic, direct myocardial depressant, or local anesthetic activity. Pharmacodynamics Clinical pharmacology studies have confirmed the beta-adrenergic blocking activity as shown by (1) changes in resting heart rate and response of heart rate to changes in posture; (2) inhibition of isoproterenol-induced tachycardia; (3) alteration of the response to the Valsalva maneuver and amyl nitrite administration; and (4) reduction of heart rate and blood pressure changes on exercise.
Timolol decreases the positive chronotropic, positive inotropic, bronchodilator, and vasodilator responses caused by beta-adrenergic receptor agonists. The magnitude of this decreased response is proportional to the existing sympathetic tone and the concentration of timolol at receptor sites. In normal volunteers, the reduction in heart rate response to a standard exercise was dose dependent over the test range of 0.5 to 20 mg, with a peak reduction at 2 hours of approximately 30% at higher doses.
Beta-adrenergic receptor blockade reduces cardiac output in both healthy subjects and patients with heart disease. In patients with severe impairment of myocardial function beta-adrenergic receptor blockade may inhibit the stimulatory effect of the sympathetic nervous system necessary to maintain adequate cardiac function. Beta-adrenergic receptor blockade in the bronchi and bronchioles results in increased airway resistance from unopposed parasympathetic activity.
Such an effect in patients with asthma or other bronchospastic conditions is potentially dangerous. Clinical studies indicate that timolol maleate at a dosage of 20 to 60 mg/day reduces blood pressure without causing postural hypotension in most patients with essential hypertension. Administration of timolol to patients with hypertension results initially in a decrease in cardiac output, little immediate change in blood pressure, and an increase in calculated peripheral resistance.
With continued administration of timolol, blood pressure decreases within a few days, cardiac output usually remains reduced, and peripheral resistance falls toward pretreatment levels. Plasma volume may decrease or remain unchanged during therapy with timolol. In the majority of patients with hypertension timolol also decreases plasma renin activity.
Dosage adjustment to achieve optimal antihypertensive effect may require a few weeks. When therapy with timolol is discontinued, the blood pressure tends to return to pretreatment levels gradually. In most patients the antihypertensive activity of timolol is maintained with long-term therapy and is well tolerated.
The mechanism of the antihypertensive effects of beta-adrenergic receptor blocking agents is not established at this time. Possible mechanisms of action include reduction in cardiac output, reduction in plasma renin activity, and a central nervous system sympatholytic action. A Norwegian multi-center, double-blind study, which included patients 20 to 75 years of age, compared the effects of timolol maleate with placebo in 1,884 patients who had survived the acute phase of a myocardial infarction.
Patients with systolic blood pressure below 100 mm Hg, sick sinus syndrome and contraindications to beta-blockers, including uncontrolled heart failure, second- or third-degree AV block and bradycardia (< 50 beats per minute), were excluded from the multi-center trial. Therapy with timolol, begun 7 to 28 days following infarction, was shown to reduce overall mortality; this was primarily attributable to a reduction in cardiovascular mortality. Timolol significantly reduced the incidence of sudden deaths (deaths occurring without symptoms or within 24 hours of the onset of symptoms), including those occurring within one hour, and particularly instantaneous deaths (those occurring without preceding symptoms).
The protecti… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Timolol Maleate Tablets, USP are available containing 5 mg, 10 mg and 20 mg of timolol maleate, USP. The 5 mg tablets are green, round, flat-faced, unscored tablets debossed with M over 55 on one side of the tablet and blank on the other side. They are available as follows: NDC 0378-0055-01 bottles of 100 tablets The 10 mg tablets are green, round, flat-faced, scored tablets debossed with M above the score and 221 below the score on one side of the tablet and blank on the other side.
They are available as follows: NDC 0378-0221-01 bottles of 100 tablets The 20 mg tablets are green, capsule-shaped, scored tablets debossed with M to the left of the score and 715 to the right of the score on one side of the tablet and blank on the other side. They are available as follows: NDC 0378-0715-01 bottles of 100 tablets Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Protect from light. Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure.
Mylan Pharmaceuticals Inc. Morgantown, WV 26505 Revised: 7/2020 TIM:R16
📋 Description ▾
DESCRIPTION Timolol maleate is a nonselective beta-adrenergic receptor blocking agent. The chemical name for timolol maleate is ( S )-1-[(1,1-dimethylethyl)amino]-3-[[4-(4-morpholinyl)-1,2,5-thiadiazol-3-yl]oxy]-2-propanol ( Z )-2-butenedioate (1:1) salt. It possesses an asymmetric carbon atom in its structure and is provided as the levo isomer.
Its molecular formula is C 13 H 24 N 4 O 3 S•C 4 H 4 O 4 and its structural formula is: Timolol maleate has a molecular weight of 432.50. It is a white, odorless, crystalline powder which is soluble in water, methanol, and alcohol. Timolol maleate is supplied as tablets containing 5 mg, 10 mg and 20 mg timolol maleate for oral administration.
Inactive ingredients are: colloidal silicon dioxide, croscarmellose sodium, magnesium stearate, microcrystalline cellulose, pregelatinized starch (corn), sodium lauryl sulfate, FD&C Blue No. 2 aluminum lake, and D&C Yellow No. 10 aluminum lake.
Timolol Maleate Structural Formula
⚠️ Precautions ▾
PRECAUTIONS General Impaired Hepatic or Renal Function Since timolol is partially metabolized in the liver and excreted mainly by the kidneys, dosage reductions may be necessary when hepatic and/or renal insufficiency is present. Dosing in the Presence of Marked Renal Failure Although the pharmacokinetics of timolol are not greatly altered by renal impairment, marked hypotensive responses have been seen in patients with marked renal impairment undergoing dialysis after 20 mg doses. Dosing in such patients should therefore be especially cautious.
Muscle Weakness Beta-adrenergic blockade has been reported to potentiate muscle weakness consistent with certain myasthenic symptoms (e.g., diplopia, ptosis, and generalized weakness). Timolol has been reported rarely to increase muscle weakness in some patients with myasthenia gravis or myasthenic symptoms. Cerebrovascular Insufficiency Because of potential effects of beta-adrenergic blocking agents relative to blood pressure and pulse, these agents should be used with caution in patients with cerebrovascular insufficiency.
If signs or symptoms suggesting reduced cerebral blood flow are observed, consideration should be given to discontinuing these agents. Drug Interactions Catecholamine-Depleting Drugs Close observation of the patient is recommended when timolol is administered to patients receiving catecholamine-depleting drugs such as reserpine, because of possible additive effects and the production of hypotension and/or marked bradycardia, which may produce vertigo, syncope, or postural hypotension. Non-Steroidal Anti-Inflammatory Drugs Blunting of the antihypertensive effect of beta-adrenoceptor blocking agents by non-steroidal anti-inflammatory drugs has been reported.
When using these agents concomitantly, patients should be observed carefully to confirm that the desired therapeutic effect has been obtained. Calcium Antagonists Literature reports suggest that oral calcium antagonists may be used in combination with beta-adrenergic blocking agents when heart function is normal, but should be avoided in patients with impaired cardiac function. Hypotension, AV conduction disturbances, and left ventricular failure have been reported in some patients receiving beta-adrenergic blocking agents when an oral calcium antagonist was added to the treatment regimen.
Hypotension was more likely to occur if the calcium antagonist were a dihydropyridine derivative, e.g., nifedipine, while left ventricular failure and AV conduction disturbances were more likely to occur with either verapamil or diltiazem. Intravenous calcium antagonists should be used with caution in patients receiving beta-adrenergic blocking agents. Digitalis and Either Diltiazem or Verapamil The concomitant use of beta-adrenergic blocking agents with digitalis and either diltiazem or verapamil may have additive effects in prolonging AV conduction time.
Quinidine Potentiated systemic beta-blockade (e.g., decreased heart rate) has been reported during combined treatment with quinidine and timolol, possibly because quinidine inhibits the metabolism of timolol via the P-450 enzyme, CYP2D6. Clonidine Beta-adrenergic blocking agents may exacerbate the rebound hypertension which can follow the withdrawal of clonidine. If the two drugs are coadministered, the beta-adrenergic blocking agent should be withdrawn several days before the gradual withdrawal of clonidine.
If replacing clonidine by beta-blocker therapy, the introduction of beta-adrenergic blocking agents should be delayed for several days after clonidine administration has stopped. Risk of Anaphylactic Reaction While taking beta-blockers, patients with a history of atopy or a history of severe anaphylactic reaction to a variety of allergens may be more reactive to repeated accidental, diagnostic, or therapeutic challenge with such allergens. Such patients may be unresponsive to the usual doses of epinephrine used to treat anaphylactic reactions.
Carcinogenesis, Mutagenesis… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Timolol maleate has been detected in human milk. Because of the potential for serious adverse reactions from timolol in nursing infants, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
🧬 Pharmacokinetics ▾
Pharmacokinetics and Metabolism Timolol maleate is rapidly and nearly completely absorbed (about 90%) following oral ingestion. Detectable plasma levels of timolol occur within one-half hour and peak plasma levels occur in about one to two hours. The drug half-life in plasma is approximately 4 hours and this is essentially unchanged in patients with moderate renal insufficiency.
Timolol is partially metabolized by the liver and timolol and its metabolites are excreted by the kidney. Timolol is not extensively bound to plasma proteins; i.e., < 10% by equilibrium dialysis and approximately 60% by ultrafiltration. An in vitro hemodialysis study, using 14 C timolol added to human plasma or whole blood, showed that timolol was readily dialyzed from these fluids; however, a study of patients with renal failure showed that timolol did not dialyze readily.
Plasma levels following oral administration are about half those following intravenous administration indicating approximately 50% first pass metabolism. The level of beta sympathetic activity varies widely among individuals, and no simple correlation exists between the dose or plasma level of timolol maleate and its therapeutic activity. Therefore, objective clinical measurements such as reduction of heart rate and/or blood pressure should be used as guides in determining the optimal dosage for each patient.
🧬 Pharmacodynamics ▾
Pharmacodynamics Clinical pharmacology studies have confirmed the beta-adrenergic blocking activity as shown by (1) changes in resting heart rate and response of heart rate to changes in posture; (2) inhibition of isoproterenol-induced tachycardia; (3) alteration of the response to the Valsalva maneuver and amyl nitrite administration; and (4) reduction of heart rate and blood pressure changes on exercise. Timolol decreases the positive chronotropic, positive inotropic, bronchodilator, and vasodilator responses caused by beta-adrenergic receptor agonists.
The magnitude of this decreased response is proportional to the existing sympathetic tone and the concentration of timolol at receptor sites. In normal volunteers, the reduction in heart rate response to a standard exercise was dose dependent over the test range of 0.5 to 20 mg, with a peak reduction at 2 hours of approximately 30% at higher doses. Beta-adrenergic receptor blockade reduces cardiac output in both healthy subjects and patients with heart disease.
In patients with severe impairment of myocardial function beta-adrenergic receptor blockade may inhibit the stimulatory effect of the sympathetic nervous system necessary to maintain adequate cardiac function. Beta-adrenergic receptor blockade in the bronchi and bronchioles results in increased airway resistance from unopposed parasympathetic activity. Such an effect in patients with asthma or other bronchospastic conditions is potentially dangerous.
Clinical studies indicate that timolol maleate at a dosage of 20 to 60 mg/day reduces blood pressure without causing postural hypotension in most patients with essential hypertension. Administration of timolol to patients with hypertension results initially in a decrease in cardiac output, little immediate change in blood pressure, and an increase in calculated peripheral resistance. With continued administration of timolol, blood pressure decreases within a few days, cardiac output usually remains reduced, and peripheral resistance falls toward pretreatment levels.
Plasma volume may decrease or remain unchanged during therapy with timolol. In the majority of patients with hypertension timolol also decreases plasma renin activity. Dosage adjustment to achieve optimal antihypertensive effect may require a few weeks.
When therapy with timolol is discontinued, the blood pressure tends to return to pretreatment levels gradually. In most patients the antihypertensive activity of timolol is maintained with long-term therapy and is well tolerated. The mechanism of the antihypertensive effects of beta-adrenergic receptor blocking agents is not established at this time.
Possible mechanisms of action include reduction in cardiac output, reduction in plasma renin activity, and a central nervous system sympatholytic action. A Norwegian multi-center, double-blind study, which included patients 20 to 75 years of age, compared the effects of timolol maleate with placebo in 1,884 patients who had survived the acute phase of a myocardial infarction. Patients with systolic blood pressure below 100 mm Hg, sick sinus syndrome and contraindications to beta-blockers, including uncontrolled heart failure, second- or third-degree AV block and bradycardia (< 50 beats per minute), were excluded from the multi-center trial.
Therapy with timolol, begun 7 to 28 days following infarction, was shown to reduce overall mortality; this was primarily attributable to a reduction in cardiovascular mortality. Timolol significantly reduced the incidence of sudden deaths (deaths occurring without symptoms or within 24 hours of the onset of symptoms), including those occurring within one hour, and particularly instantaneous deaths (those occurring without preceding symptoms). The protective effect of timolol was consistent regardless of age, sex or site of infarction.
The effect was clearest in patients with a first infarction who were considered at a high risk of dying, defined as those with one or more of the f… [Excerpted — this section continues on DailyMed.]
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility In a 2 year study of timolol maleate in rats, there was a statistically significant increase in the incidence of adrenal pheochromocytomas in male rats administered 300 mg/kg/day (250 times * the maximum recommended human dose). Similar differences were not observed in rats administered doses equivalent to approximately 20 or 80 times * the maximum recommended human dose. In a lifetime study in mice, there were statistically significant increases in the incidence of benign and malignant pulmonary tumors, benign uterine polyps and mammary adenocarcinoma in female mice at 500 mg/kg/day (approximately 400 times * the maximum recommended human dose), but not at a 5 or 50 mg/kg/day.
In a subsequent study in female mice, in which postmortem examinations were limited to uterus and lungs, a statistically significant increase in the incidence of pulmonary tumors was again observed at 500 mg/kg/day. The increased occurrence of mammary adenocarcinoma was associated with elevations in serum prolactin that occurred in female mice administered timolol maleate at 500 mg/kg/day, but not at doses of 5 or 50 mg/kg/day. An increased incidence of mammary adenocarcinomas in rodents has been associated with administration of several other therapeutic agents which elevate serum prolactin, but no correlation between serum prolactin levels and mammary tumors has been established in man.
Furthermore, in adult human female subjects who received oral dosages of up to 60 mg of timolol maleate, the maximum recommended daily human oral dosage, there were no clinically meaningful changes in serum prolactin. Timolol maleate was devoid of mutagenic potential when elevated in vivo (mouse) in the micronucleus test and cytogenetic assay (doses up to 800 mg/kg) and in vitro in a neoplastic cell transformation assay (up to 100 mcg/mL). In Ames tests the highest concentrations of timolol employed, 5,000 or 10,000 mcg/plate, were associated with statistically significant elevations of revertants observed with tester strain TA100 (in seven replicate assays), but not in three additional strains.
In the assays with tester strain TA100, no consistent dose-response relationship was observed, nor did the ratio of test to control revertants reach 2. A ratio of 2 is usually considered the criterion for a positive Ames test. Reproduction and fertility studies in rats showed no adverse effect on male or female fertility at doses up to 125 times * the maximum recommended human dose.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 5 mg NDC 0378-0055-01 Timolol Maleate Tablets, USP 5 mg Rx only 100 Tablets Each tablet contains: Timolol maleate, USP 5 mg Usual Dosage: See accompanying prescribing information. Keep this and all medication out of the reach of children. Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Protect from light.
Manufactured for: Mylan Pharmaceuticals Inc. Morgantown, WV 26505 U.S.A. Made in India Mylan.com RMXI0055A Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure.
Keep container tightly closed. Code No.: MP/DRUGS/25/1/2014 Timolol Maleate Tablets 5 mg Bottle Label
PRINCIPAL DISPLAY PANEL - 10 mg NDC 0378-0221-01 Timolol Maleate Tablets, USP 10 mg Rx only 100 Tablets Each tablet contains: Timolol maleate, USP 10 mg Usual Dosage: See accompanying prescribing information. Keep this and all medication out of the reach of children. Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Protect from light.
Manufactured for: Mylan Pharmaceuticals Inc. Morgantown, WV 26505 U.S.A. Made in India Mylan.com RMXI0221A Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure.
Keep container tightly closed. Code No.: MP/DRUGS/25/1/2014 Timolol Maleate Tablets 10 mg Bottle Label
PRINCIPAL DISPLAY PANEL - 20 mg NDC 0378-0715-01 Timolol Maleate Tablets, USP 20 mg Rx only 100 Tablets Each tablet contains: Timolol maleate, USP 20 mg Usual Dosage: See accompanying prescribing information. Keep this and all medication out of the reach of children. Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Protect from light.
Manufactured for: Mylan Pharmaceuticals Inc. Morgantown, WV 26505 U.S.A. Made in India Mylan.com RMXI0715A Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure.
Keep container tightly closed. Code No.: MP/DRUGS/25/1/2014 Timolol Maleate Tablets 20 mg Bottle Label
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |