
BREYNA Budesonide and Formoterol Fumarate 80 ug; 4.5 ug Aerosol, Metered — NDC 0378-7502-32 (Billing 00378-7502-32)
This is a package of BREYNA Budesonide and Formoterol Fumarate 80 ug; 4.5 ug Aerosol, Metered from Mylan Pharmaceuticals Inc., marketed since Jul 2023 and currently FDA-listed; retail pharmacies pay about $18.54 per g (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0378-7502-32 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0378 labeler · 7502 product · 32 package
- Package marketed since
- Jul 31, 2023
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 0378750232 4
- Medicaid fills, this package
- 72,979 prescriptions in the last four reported quarters
- FDA record last changed
- Oct 1, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 062725
- GCN: 98499
- GPI-14 (Medi-Span): 44209902413220
- HICL (First Databank): 021993
- AHFS class code: 12:12.08.12
- RxCUI (RxNorm): 1246288
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Corticosteroid class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Budesonide and formoterol is used to prevent and treat difficulty breathing, wheezing, shortness of breath, coughing, and chest tightness caused by asthma and to treat chronic obstructive pulmonary (COPD; a group of diseases that affect the lungs and airways, that includes chronic bronchitis and emphysema) in adults. Budesonide is in a class of medications called steroids. It works by reducing swelling in the airways. Formoterol is in a class of medications called long-acting beta agonists (LABAs). It works by relaxing and opening air passages in the lungs, making it easier to breathe.
Read the full MedlinePlus article ↗- This is a controller inhaler — it works by reducing inflammation and keeping your airways open over time, not by acting fast enough to stop a sudden attack. You absolutely still ne...
- Is this my rescue inhaler, or do I still need a separate one for sudden attacks?
- The steroid in this inhaler (budesonide) can leave a small amount of residue in your mouth and throat. That residue can allow a yeast called Candida to grow, causing a mouth infect...
- Why do I have to rinse my mouth after using it?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per g | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $18.537 | — |
| Medicaid paysCMS SDUD · 12 mo | $13.96 | — |
| Medicare drug plans payPart D · Q2 2026 | $14.07 | — |
Where does this data come from?
- CMS NADAC weekly file · file of Oct 7, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00378-7502-32 You're viewing this Main listing | 1 POUCH in 1 CARTON / 1 CANISTER in 1 POUCH / 120 AEROSOL, METERED in 1 CANISTER | 2023-07-31 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Budesonide and Formoterol Fumarate Dihydrate 80 ug/1; 4.5 ug 00310-7372-20 | AstraZeneca | 1 pouch | $15.669 | AB | Availability likely | save 15% |
| Budesonide and formoterol fumarate dihydrate 80 ug/1; 4.5 ug 00480-3080-31 | Teva | 1 pouch | $15.669 | AB | Availability likely | save 15% |
| Breyna 80 ug/1; 4.5 ugthis 00378-7502-32 | Mylan | 1 pouch | $18.537 | AB | Availability likely | — |
| Symbicort 80 ug/1; 4.5 ug 00186-0372-20 | AstraZeneca | 1 pouch | $19.245 | AB | Availability likely | +4% |
| Budesonide and Formoterol Fumarate Dihydrate 80 ug/1; 4.5 ug 50090-6382-00 | A-S | 1 canister | — | AB | FDA listed | — |
| Budesonide and Formoterol Fumarate Dihydrate 80 ug/1; 4.5 ug 85766-0113-12 | Sportpharm | 1 pouch | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Oct 7, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Budesonide / Formoterol inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII R40P36GDK6
A fluorinated volatile liquid used as an anesthetic agent in inhalation medicines. It helps deliver consistent anesthesia during surgical procedures and medical sedation.
-
UNII U076Q6Q621
Polyethylene glycol 1000 is a synthetic compound made from ethylene oxide. It serves as a solvent, lubricant, and humectant in medicines, helping dissolve active ingredients and improve how the product flows and feels.
-
UNII K0KQV10C35
Povidone K25 is a synthetic polymer made from vinyl pyrrolidone. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach for better absorption.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Mylan Pharmaceuticals Inc. labeler code 00378
- Norethindrone and Ethinyl Estradiol and Ferrous Fumarate Kit NDC 0378-7297-53
- Drospirenone and Ethinyl Estradiol Kit NDC 0378-7300-53
- Norethindrone Acetate and Ethinyl Estradiol and Ferrous Fumarate Kit NDC 0378-7303-53
- Ethynodiol Diacetate and Ethinyl Estradiol Kit NDC 0378-7306-53
- Ethynodiol Diacetate and Ethinyl Estradiol Kit NDC 0378-7307-53
- Levonorgestrel and Ethinyl Estradiol Kit NDC 0378-7316-85
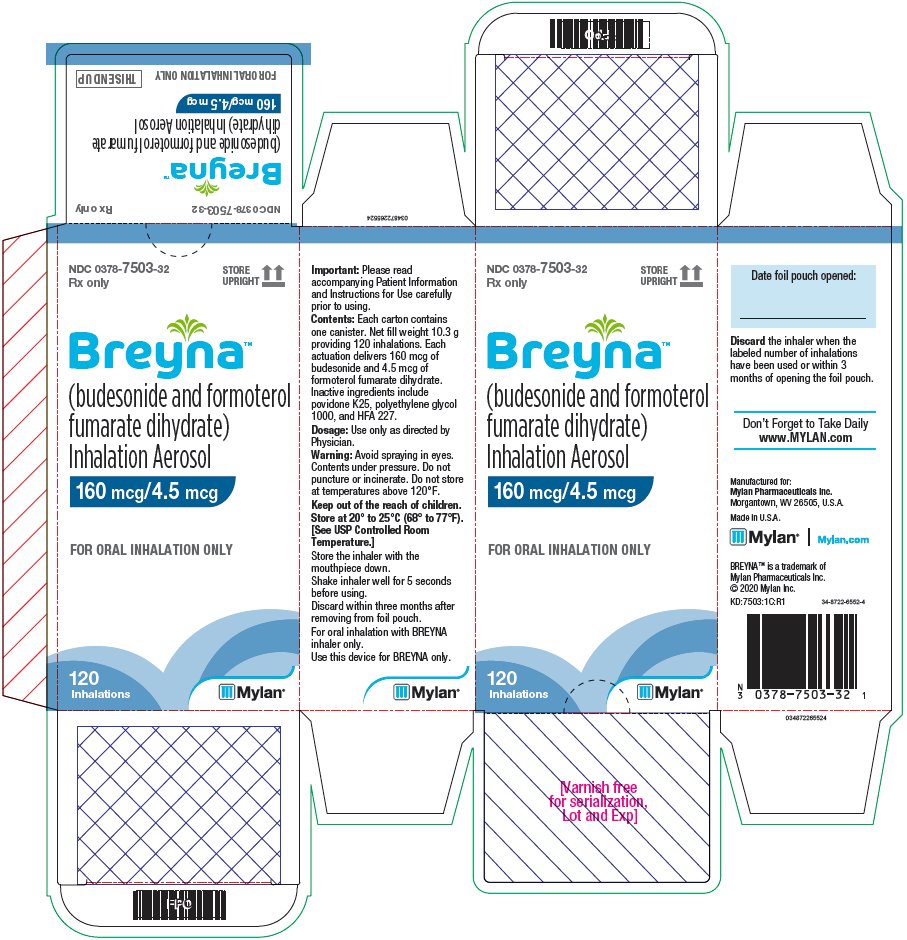
- BREYNA Budesonide and Formoterol Fumarate 160 ug; 4.5 ug Aerosol, Metered NDC 0378-7503-32
- Difluprednate .5 mg/mL Emulsion NDC 0378-7518-35
- Ipratropium Bromide .5 mg/2.5mL Solution NDC 0378-7970-52
- Lansoprazole 15 mg Capsule, Delayed Release Pellets NDC 0378-8015-93
- Fluvastatin Sodium 20 mg Capsule NDC 0378-8020-77
- Fluvastatin Sodium 40 mg Capsule NDC 0378-8021-77
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE BREYNA is a combination product containing a corticosteroid and a long-acting beta 2 -adrenergic agonist indicated for: • Treatment of asthma in patients 6 years of age and older. ( 1.1 ) • Maintenance treatment of airflow obstruction and reducing exacerbations in patients with chronic obstructive pulmonary disease (COPD) including chronic bronchitis and/or emphysema. ( 1.2 ) Important limitations: • Not indicated for the relief of acute bronchospasm.
( 1.1 , 1.2 )
1.1Treatment of Asthma BREYNA is indicated for the treatment of asthma in patients 6 years of age and older. BREYNA should be used for patients not adequately controlled on a long-term asthma-control medication such as an inhaled corticosteroid (ICS) or whose disease warrants initiation of treatment with both an inhaled corticosteroid and long-acting beta 2 -adrenergic agonist (LABA). Important Limitations of Use: • BREYNA is NOT indicated for the relief of acute bronchospasm.
1.2Maintenance Treatment of Chronic Obstructive Pulmonary Disease BREYNA 160 mcg/4.5 mcg is indicated for the maintenance treatment of airflow obstruction in patients with chronic obstructive pulmonary disease (COPD) including chronic bronchitis and/or emphysema. BREYNA 160 mcg/4.5 mcg is also indicated to reduce exacerbations of COPD. BREYNA 160 mcg/4.5 mcg is the only strength indicated for the treatment of COPD.
Important Limitations of Use: • BREYNA is NOT indicated for the relief of acute bronchospasm.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION For oral inhalation only. • Treatment of asthma in patients 12 years and older: 2 inhalations of BREYNA 80 mcg/4.5 mcg or 160 mcg/4.5 mcg twice daily. Starting dosage is based on asthma severity. ( 2.2 ) • Treatment of asthma in patients aged 6 to less than 12 years: 2 inhalations of BREYNA 80 mcg/4.5 mcg twice daily. ( 2.2 ) • Maintenance treatment in COPD: 2 inhalations of BREYNA 160 mcg/4.5 mcg twice daily. ( 2.3 )
2.1Administration Information BREYNA should be administered as 2 inhalations twice daily (morning and evening, approximately 12 hours apart), every day by the orally inhaled route only. After inhalation, the patient should rinse the mouth with water without swallowing. Prime BREYNA before using for the first time by releasing two test sprays into the air away from the face, shaking well for 5 seconds before each spray.
In cases where the inhaler has not been used for more than 7 days or when it has been dropped, prime the inhaler again by shaking well before each spray and releasing two test sprays into the air away from the face. More frequent administration or a higher number of inhalations (more than 2 inhalations twice daily) of the prescribed strength of BREYNA is not recommended as some patients are more likely to experience adverse effects with higher doses of formoterol. Patients using BREYNA should not use additional LABA for any reason [see Warnings and Precautions (5.3 , 5.12) ] .
2.2Asthma If asthma symptoms arise in the period between doses, an inhaled, short-acting beta 2 -agonist should be taken for immediate relief. Adult and Adolescent Patients 12 Years of Age and Older For patients 12 years of age and older, the dosage is 2 inhalations of BREYNA 80 mcg/4.5 mcg or BREYNA 160 mcg/4.5 mcg twice daily. The recommended starting dosages for BREYNA for patients 12 years of age and older are based upon patients’ asthma severity or level of control of asthma symptoms, and risk of exacerbations on current inhaled corticosteroids.
The maximum recommended dosage in adult and adolescent patients 12 years and older is BREYNA 160 mcg/4.5 mcg, two inhalations twice daily. Improvement in asthma control following inhaled administration of BREYNA can occur within 15 minutes of beginning treatment, although maximum benefit may not be achieved for 2 weeks or longer after beginning treatment. Individual patients will experience a variable time to onset and degree of symptom relief.
For patients who do not respond adequately to the starting dose after 1-2 weeks of therapy with BREYNA 80 mcg/4.5 mcg, replacement with BREYNA 160 mcg/4.5 mcg may provide additional asthma control. If a previously effective dosage regimen of BREYNA fails to provide adequate control of asthma, the therapeutic regimen should be re-evaluated and additional therapeutic options, (e.g., replacing the lower strength of BREYNA with the higher strength, adding additional inhaled corticosteroid, or initiating oral corticosteroids) should be considered.
Pediatric Patients Aged 6 to Less than 12 Years For patients 6 to less than 12 years of age, the dosage is 2 inhalations of BREYNA 80 mcg/4.5 mcg twice daily.
2.3Chronic Obstructive Pulmonary Disease For patients with COPD the recommended dose is BREYNA 160 mcg/4.5 mcg, two inhalations twice daily. If shortness of breath occurs in the period between doses, an inhaled, short-acting beta 2 -agonist should be taken for immediate relief.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS BREYNA is available as a metered-dose inhaler containing a combination of budesonide (80 mcg or 160 mcg) and formoterol fumarate dihydrate (4.5 mcg) as an inhalation aerosol in the following two strengths: 80 mcg/4.5 mcg and 160 mcg/4.5 mcg. Each dosage strength contains 120 actuations per/canister. Each strength of BREYNA is supplied with a blue plastic actuator with a grey dust cap.
Metered-dose inhaler containing a combination of budesonide (80 mcg or 160 mcg) and formoterol fumarate dihydrate (4.5 mcg) as an inhalation aerosol. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS The use of BREYNA is contraindicated in the following conditions: • Primary treatment of status asthmaticus or other acute episodes of asthma or COPD where intensive measures are required. • Hypersensitivity to any of the ingredients in BREYNA. • Primary treatment of status asthmaticus or acute episodes of asthma or COPD requiring intensive measures ( 4 ) • Hypersensitivity to any of the ingredients in BREYNA ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Serious asthma-related events: Long-acting beta 2 -adrenergic agonists as monotherapy increase the risk. ( 5.1 ) • Deterioration of disease and acute episodes: Do not initiate in acutely deteriorating asthma or COPD or to treat acute symptoms. ( 5.2 ) • Use with additional long-acting beta 2 -agonist: Do not use in combination because of risk of overdose.
( 5.3 ) • Localized infections: Candida albicans infection of the mouth and throat may occur. Monitor patients periodically for signs of adverse effects on the oral cavity. Advise the patient to rinse his/her mouth with water without swallowing after inhalation to help reduce the risk.
( 5.4 ) • Pneumonia: Increased risk in patients with COPD. Monitor patients for signs and symptoms of pneumonia and other potential lung infections. ( 5.5 ) • Immunosuppression: Potential worsening of infections (e.g., existing tuberculosis, fungal, bacterial, viral, or parasitic infection; or ocular herpes simplex).
Use with caution in patients with these infections. More serious or even fatal course of chickenpox or measles can occur in susceptible patients. ( 5.6 ) • Transferring patients from systemic corticosteroids: Risk of impaired adrenal function when transferring from oral steroids.
Taper patients slowly from systemic corticosteroids if transferring to BREYNA. ( 5.7 ) • Hypercorticism and adrenal suppression: May occur with very high dosages or at the regular dosage in susceptible individuals. If such changes occur, discontinue BREYNA slowly.
( 5.8 ) • Strong cytochrome P450 3A4 inhibitors (e.g., ritonavir): Risk of increased systemic corticosteroid effects. Exercise caution when used with BREYNA. ( 5.9 ) • Paradoxical bronchospasm: Discontinue BREYNA and institute alternative therapy if paradoxical bronchospasm occurs.
( 5.10 ) • Patients with cardiovascular or central nervous system disorders: Use with caution because of beta-adrenergic stimulation. ( 5.12 ) • Decreases in bone mineral density: Assess bone mineral density initially and periodically thereafter. ( 5.13 ) • Effects on growth: Monitor growth of pediatric patients.
( 5.14 ) • Glaucoma and cataracts: Close monitoring is warranted. ( 5.15 ) • Metabolic effects: Be alert to eosinophilic conditions, hypokalemia, and hyperglycemia. ( 5.16 , 5.18 ) • Coexisting conditions: Use with caution in patients with convulsive disorders, thyrotoxicosis, diabetes mellitus, and ketoacidosis.
( 5.17 )
5.1Serious Asthma-Related Events – Hospitalizations, Intubations and Death Use of LABA as monotherapy (without ICS) for asthma is associated with an increased risk of asthma-related death [see Salmeterol Multicenter Asthma Research Trial (SMART) ]. Available data from controlled clinical trials also suggest that use of LABA as monotherapy increases the risk of asthma-related hospitalization in pediatric and adolescent patients. These findings are considered a class effect of LABA.
When LABA are used in fixed-dose combination with ICS, data from large clinical trials do not show a significant increase in the risk of serious asthma-related events (hospitalizations, intubations, death) compared to ICS alone (see Serious Asthma-Related Events with ICS/LABA ). Serious Asthma-Related Events with ICS/LABA Four large, 26-week, randomized, blinded, active-controlled clinical safety trials were conducted to evaluate the risk of serious asthma-related events when LABA were used in fixed-dose combination with ICS compared to ICS alone in patients with asthma.
Three trials included adult and adolescent patients aged ≥ 12 years: one trial compared budesonide/formoterol (budesonide and formoterol fumarate dihydrate inhalation aerosol) to budesonide [see Clinical Studies (14.1) ] ; one trial compared fluticasone propionate/salmeterol inhalation powder to fluticasone propionate inhalation powder; and one trial compared mometasone furoate/formoterol to mometasone furoate. The fourth trial included pediatric patients 4 to 11 years… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS LABA use may result in the following: • Serious asthma-related events – hospitalizations, intubations, death [see Warnings and Precautions (5.1) ] . • Cardiovascular and central nervous system effects [see Warnings and Precautions (5.12) ] . Systemic and inhaled corticosteroid use may result in the following: • Candida albicans infection [see Warnings and Precautions (5.4) ] • Pneumonia or lower respiratory tract infections in patients with COPD [see Warnings and Precautions (5.5) ] • Immunosuppression [see Warnings and Precautions (5.6) ] • Hypercorticism and adrenal suppression [see Warnings and Precautions (5.8) ] • Growth effects in pediatric patients [see Warnings and Precautions (5.14) ] • Glaucoma and cataracts [see Warnings and Precautions (5.15) ] Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
Most common adverse reactions (incidence ≥ 3%) are: • Asthma: nasopharyngitis, headache, upper respiratory tract infection, pharyngolaryngeal pain, sinusitis, influenza, back pain, nasal congestion, stomach discomfort, vomiting, and oral candidiasis. ( 6.1 ) • COPD: nasopharyngitis, oral candidiasis, bronchitis, sinusitis, upper respiratory tract infections. ( 6.2 ) To report SUSPECTED ADVERSE REACTIONS, contact Viatris at 1-877-446-3679 (1-877-4-INFO-RX) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience in Asthma Adult and Adolescent Patients 12 Years of Age and Older The overall safety data in adults and adolescents are based upon 10 active- and placebo-controlled clinical trials in which 3393 patients ages 12 years and older (2052 females and 1341 males) with asthma of varying severity were treated with budesonide and formoterol fumarate dihydrate inhalation aerosol 80 mcg/4.5 mcg or 160 mcg/4.5 mcg taken 2 inhalations once or twice daily for 12 to 52 weeks. In these trials, the patients on budesonide and formoterol fumarate dihydrate inhalation aerosol had a mean age of 38 years and were predominantly Caucasian (82%).
The incidence of common adverse events in Table 2 below is based upon pooled data from three 12‑week, double-blind, placebo-controlled clinical studies in which 401 adult and adolescent patients (148 males and 253 females) age 12 years and older were treated with 2 inhalations of budesonide and formoterol fumarate dihydrate inhalation aerosol 80 mcg/4.5 mcg or budesonide and formoterol fumarate dihydrate inhalation aerosol 160 mcg/4.5 mcg twice daily. The budesonide and formoterol fumarate dihydrate inhalation aerosol group was composed of mostly Caucasian (84%) patients with a mean age of 38 years, and a mean percent predicted FEV 1 at baseline of 76 and 68 for the 80 mcg/4.5 mcg and 160 mcg/4.5 mcg treatment groups, respectively.
Control arms for comparison included 2 inhalations of budesonide HFA metered dose inhaler (MDI) 80 mcg or 160 mcg, formoterol dry powder inhaler (DPI) 4.5 mcg, or placebo (MDI and DPI) twice daily. Table 2 includes all adverse events that occurred at an incidence of ≥ 3% in any one budesonide and formoterol fumarate dihydrate inhalation aerosol group and more commonly than in the placebo group with twice-daily dosing. In considering these data, the increased average duration of patient exposure for budesonide and formoterol fumarate dihydrate inhalation aerosol patients should be taken into account, as incidences are not adjusted for an imbalance of treatment duration.
Table 2. Adverse Reactions Occurring at an Incidence of ≥ 3% and More Commonly Than Placebo in the Budesonide and Formoterol Fumarate Dihydrate Inhalation Aerosol Groups: Pooled Data from Three 12-week, Double-blind, Placebo-controlled Clinical Asthma Trials in Patients 12 Years and Older Treatment All treatments were administered as 2 inhalations twice da… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS In clinical studies, concurrent administration of budesonide and formoterol fumarate dihydrate inhalation aerosol and other drugs, such as short-acting beta 2 -agonists, intranasal corticosteroids, and antihistamines/decongestants has not resulted in an increased frequency of adverse reactions. No formal drug interaction studies have been performed with budesonide and formoterol fumarate dihydrate inhalation aerosol. • Strong cytochrome P450 3A4 inhibitors (e.g., ritonavir): Use with caution. May cause increased systemic corticosteroid effects.
( 7.1 ) • Monoamine oxidase inhibitors and tricyclic antidepressants: Use with extreme caution. May potentiate effect of formoterol on vascular system. ( 7.2 ) • Beta-blockers: Use with caution.
May block bronchodilatory effects of beta-agonists and produce severe bronchospasm. ( 7.3 ) • Diuretics: Use with caution. Electrocardiographic changes and/or hypokalemia associated with non-potassium-sparing diuretics may worsen with concomitant beta-agonists.
( 7.4 )
7.1Inhibitors of Cytochrome P4503A4 The main route of metabolism of corticosteroids, including budesonide, a component of BREYNA, is via cytochrome P450 (CYP) isoenzyme 3A4 (CYP3A4). After oral administration of ketoconazole, a strong inhibitor of CYP3A4, the mean plasma concentration of orally administered budesonide increased. Concomitant administration of CYP3A4 may inhibit the metabolism of, and increase the systemic exposure to, budesonide.
Caution should be exercised when considering the coadministration of BREYNA with long-term ketoconazole and other known strong CYP3A4 inhibitors (e.g., ritonavir, atazanavir, clarithromycin, indinavir, itraconazole, nefazodone, nelfinavir, saquinavir, telithromycin) [see Warnings and Precautions (5.9) ] .
7.2Monoamine Oxidase Inhibitors and Tricyclic Antidepressants BREYNA should be administered with caution to patients being treated with monoamine oxidase inhibitors or tricyclic antidepressants, or within 2 weeks of discontinuation of such agents, because the action of formoterol, a component of BREYNA, on the vascular system may be potentiated by these agents. In clinical trials with budesonide and formoterol fumarate dihydrate inhalation aerosol, a limited number of COPD and asthma patients received tricyclic antidepressants, and, therefore, no clinically meaningful conclusions on adverse events can be made.
7.3Beta-Adrenergic Receptor Blocking Agents Beta-blockers (including eye drops) may not only block the pulmonary effect of beta-agonists, such as formoterol, a component of BREYNA, but may produce severe bronchospasm in patients with asthma. Therefore, patients with asthma should not normally be treated with beta-blockers. However, under certain circumstances, there may be no acceptable alternatives to the use of beta-adrenergic blocking agents in patients with asthma.
In this setting, cardioselective beta-blockers could be considered, although they should be administered with caution.
7.4Diuretics The ECG changes and/or hypokalemia that may result from the administration of non-potassium-sparing diuretics (such as loop or thiazide diuretics) can be acutely worsened by beta-agonists, especially when the recommended dose of the beta-agonist is exceeded. Although the clinical significance of these effects is not known, caution is advised in the coadministration of BREYNA with non-potassium-sparing diuretics.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Hepatic impairment: Monitor patients for signs of increased drug exposure. ( 8.6 )
8.1Pregnancy Risk Summary There are no adequate and well-controlled studies of budesonide and formoterol fumarate dihydrate inhalation aerosol or one of its individual components, formoterol fumarate, in pregnant women; however studies are available for the other component budesonide. In animal reproduction studies, budesonide and formoterol fumarate dihydrate, administered by the inhalation route, was teratogenic, embryocidal, and reduced fetal weights in rats at less than the maximum recommended human daily inhalation dose (MRHDID) on a mcg/m 2 basis.
Budesonide alone, administered by the subcutaneous route, was teratogenic, embryocidal, and reduced fetal weights in rats and rabbits at less than the MRHDID, but these effects were not seen in rats that received inhaled doses up to 4 times the MRHDID. Studies of pregnant women have not shown that inhaled budesonide alone increases the risk of abnormalities when administered during pregnancy. Experience with oral corticosteroids suggests that rodents are more prone to teratogenic effects from corticosteroid exposure than humans.
Formoterol fumarate alone, administered by the oral route, was teratogenic in rats and rabbits at 1600 and 65,000 times the MRHDID, respectively. Formoterol fumarate was also embryocidal, increased pup loss at birth and during lactation, and decreased pup weight in rats at 110 times the MRHDID. These adverse effects generally occurred at large multiples of the MRHDID when formoterol fumarate was administered by the oral route to achieve high systemic exposures.
No teratogenic, embryocidal, or developmental effects were seen in rats that received inhalation doses up to 375 times the MRHDID. The estimated background risk of major birth defects and miscarriage of the indicated populations is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk In women with poorly or moderately controlled asthma, there is an increased risk of several perinatal adverse outcomes such as preeclampsia in the mother and prematurity, low birth weight, and small for gestational age in the neonate. Pregnant women with asthma should be closely monitored and medication adjusted as necessary to maintain optimal asthma control. Labor or Delivery There are no well-controlled human studies that have investigated the effects of budesonide and formoterol fumarate dihydrate inhalation aerosol during labor and delivery.
Because of the potential for beta-agonist interference with uterine contractility, use of BREYNA during labor should be restricted to those patients in whom the benefits clearly outweigh the risk. Data Human Data Studies of pregnant women have not shown that inhaled budesonide increases the risk of abnormalities when administered during pregnancy. The results from a large population-based prospective cohort epidemiological study reviewing data from three Swedish registries covering approximately 99% of the pregnancies from 1995-1997 (i.e., Swedish Medical Birth Registry; Registry of Congenital Malformations; Child Cardiology Registry) indicate no increased risk for congenital malformations from the use of inhaled budesonide during early pregnancy.
Congenital malformations were studied in 2014 infants born to mothers reporting the use of inhaled budesonide for asthma in early pregnancy (usually 10-12 weeks after the last menstrual period), the period when most major organ malformations occur. The rate of recorded congenital malformations was similar compared to the general population rate (3.8% vs. 3.5%, respectively).
In addition, after exposure to inhaled budesonide, the number of infants born with orofacial clefts was similar to the expected number in… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate and well-controlled studies of budesonide and formoterol fumarate dihydrate inhalation aerosol or one of its individual components, formoterol fumarate, in pregnant women; however studies are available for the other component budesonide. In animal reproduction studies, budesonide and formoterol fumarate dihydrate, administered by the inhalation route, was teratogenic, embryocidal, and reduced fetal weights in rats at less than the maximum recommended human daily inhalation dose (MRHDID) on a mcg/m 2 basis.
Budesonide alone, administered by the subcutaneous route, was teratogenic, embryocidal, and reduced fetal weights in rats and rabbits at less than the MRHDID, but these effects were not seen in rats that received inhaled doses up to 4 times the MRHDID. Studies of pregnant women have not shown that inhaled budesonide alone increases the risk of abnormalities when administered during pregnancy. Experience with oral corticosteroids suggests that rodents are more prone to teratogenic effects from corticosteroid exposure than humans.
Formoterol fumarate alone, administered by the oral route, was teratogenic in rats and rabbits at 1600 and 65,000 times the MRHDID, respectively. Formoterol fumarate was also embryocidal, increased pup loss at birth and during lactation, and decreased pup weight in rats at 110 times the MRHDID. These adverse effects generally occurred at large multiples of the MRHDID when formoterol fumarate was administered by the oral route to achieve high systemic exposures.
No teratogenic, embryocidal, or developmental effects were seen in rats that received inhalation doses up to 375 times the MRHDID. The estimated background risk of major birth defects and miscarriage of the indicated populations is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk In women with poorly or moderately controlled asthma, there is an increased risk of several perinatal adverse outcomes such as preeclampsia in the mother and prematurity, low birth weight, and small for gestational age in the neonate. Pregnant women with asthma should be closely monitored and medication adjusted as necessary to maintain optimal asthma control. Labor or Delivery There are no well-controlled human studies that have investigated the effects of budesonide and formoterol fumarate dihydrate inhalation aerosol during labor and delivery.
Because of the potential for beta-agonist interference with uterine contractility, use of BREYNA during labor should be restricted to those patients in whom the benefits clearly outweigh the risk. Data Human Data Studies of pregnant women have not shown that inhaled budesonide increases the risk of abnormalities when administered during pregnancy. The results from a large population-based prospective cohort epidemiological study reviewing data from three Swedish registries covering approximately 99% of the pregnancies from 1995-1997 (i.e., Swedish Medical Birth Registry; Registry of Congenital Malformations; Child Cardiology Registry) indicate no increased risk for congenital malformations from the use of inhaled budesonide during early pregnancy.
Congenital malformations were studied in 2014 infants born to mothers reporting the use of inhaled budesonide for asthma in early pregnancy (usually 10-12 weeks after the last menstrual period), the period when most major organ malformations occur. The rate of recorded congenital malformations was similar compared to the general population rate (3.8% vs. 3.5%, respectively).
In addition, after exposure to inhaled budesonide, the number of infants born with orofacial clefts was similar to the expected number in the normal population (4 children vs. 3.3, respectively). These same data were utilized in a second study bringin… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of budesonide and formoterol fumarate dihydrate inhalation aerosol in asthma patients 12 years of age and older have been established in studies up to 12 months. In the two 12-week, double-blind, placebo-controlled US pivotal studies 25 patients 12 to 17 years of age were treated with budesonide and formoterol fumarate dihydrate inhalation aerosol twice daily [see Clinical Studies (14.1) ] . Efficacy results in this age group were similar to those observed in patients 18 years and older.
There were no obvious differences in the type or frequency of adverse events reported in this age group compared with patients 18 years of age and older. The safety and effectiveness of budesonide and formoterol fumarate dihydrate inhalation aerosol 80 mcg/4.5 mcg in asthma patients 6 to less than 12 years of age have been established in studies of up to 12-week duration [see Clinical Studies (14.1) ] . The safety profile in these patients was consistent to that observed in patients 12 years of age and older who also received budesonide and formoterol fumarate dihydrate inhalation aerosol [see Adverse Reactions (6.1) ] .
The safety and effectiveness of budesonide and formoterol fumarate dihydrate inhalation aerosol in asthma patients less than 6 years of age have not been established. Controlled clinical studies have shown that orally inhaled corticosteroids including budesonide, a component of BREYNA, may cause a reduction in growth velocity in pediatric patients. This effect has been observed in the absence of laboratory evidence of HPA-axis suppression, suggesting that growth velocity is a more sensitive indicator of systemic corticosteroid exposure in pediatric patients than some commonly used tests of HPA-axis function.
The long-term effect of this reduction in growth velocity associated with orally inhaled corticosteroids, including the impact on final height are unknown. The potential for “catch-up” growth following discontinuation of treatment with orally inhaled corticosteroids has not been adequately studied. In a study of asthmatic children 5 to 12 years of age, those treated with budesonide DPI 200 mcg twice daily (n = 311) had a 1.1 centimeter reduction in growth compared with those receiving placebo (n = 418) at the end of one year; the difference between these two treatment groups did not increase further over three years of additional treatment.
By the end of 4 years, children treated with budesonide DPI and children treated with placebo had similar growth velocities. Conclusions drawn from this study may be confounded by the unequal use of corticosteroids in the treatment groups and inclusion of data from patients attaining puberty during the course of the study. The growth of pediatric patients receiving orally inhaled corticosteroids, including BREYNA, should be monitored.
If a child or adolescent on any corticosteroid appears to have growth suppression, the possibility that he/she is particularly sensitive to this effect should be considered. The potential growth effects of prolonged treatment should be weighed against the clinical benefits obtained. To minimize the systemic effects of orally inhaled corticosteroids, including BREYNA, each patient should be titrated to the lowest strength that effectively controls his/her asthma [see Dosage and Administration (2) ] .
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of asthma patients treated with budesonide and formoterol fumarate dihydrate inhalation aerosol twice daily in two 12-week studies and a 26-week postmarketing study, 791 were 65 years of age or older, of whom 141 were 75 years of age or older. In the COPD studies of 6 to 12 months duration, 810 patients treated with budesonide and formoterol fumarate dihydrate inhalation aerosol 160 mcg/4.5 mcg, two inhalations twice daily were 65 years old and above and of those, 177 patients were 75 years of age and older.
No overall differences in safety or effectiveness were observed between these patients and younger patients, and other reported clinical experience has not identified differences in responses between the elderly and younger patients. As with other products containing beta 2 -agonists, special caution should be observed when using BREYNA in geriatric patients who have concomitant cardiovascular disease that could be adversely affected by beta 2 -agonists. Based on available data for budesonide and formoterol fumarate dihydrate inhalation aerosol or its active components, no adjustment of dosage of BREYNA in geriatric patients is warranted.
🆘 Overdosage ▾
10 OVERDOSAGE BREYNA BREYNA contains both budesonide and formoterol fumarate dihydrate; therefore, the risks associated with overdosage for the individual components described below apply to BREYNA. In pharmacokinetic studies, single doses of 960/54 mcg (12 actuations of budesonide and formoterol fumarate dihydrate inhalation aerosol 80 mcg/4.5 mcg) and 1280/36 mcg (8 actuations of 160 mcg/4.5 mcg), were administered to patients with COPD. A total of 1920/54 mcg (12 actuations of budesonide and formoterol fumarate dihydrate inhalation aerosol 160 mcg/4.5 mcg) was administered as a single dose to both healthy subjects and patients with asthma.
In a long-term active-controlled safety study in adolescent and adult asthma patients 12 years of age and older, budesonide and formoterol fumarate dihydrate inhalation aerosol 160 mcg/4.5 mcg was administered for up to 12 months at doses up to twice the highest recommended daily dose. There were no clinically significant adverse reactions observed in any of these studies. Budesonide The potential for acute toxic effects following overdose of budesonide is low.
If used at excessive doses for prolonged periods, systemic corticosteroid effects such as hypercorticism may occur [see Warnings and Precautions (5) ] . Budesonide at five times the highest recommended dose (3200 mcg daily) administered to humans for 6 weeks caused a significant reduction (27%) in the plasma cortisol response to a 6-hour infusion of ACTH compared with placebo (+1%). The corresponding effect of 10 mg prednisone daily was a 35% reduction in the plasma cortisol response to ACTH.
Formoterol An overdose of formoterol would likely lead to an exaggeration of effects that are typical for beta 2 ‑agonists: seizures, angina, hypertension, hypotension, tachycardia, atrial and ventricular tachyarrhythmias, nervousness, headache, tremor, palpitations, muscle cramps, nausea, dizziness, sleep disturbances, metabolic acidosis, hyperglycemia, hypokalemia. As with all sympathomimetic medications, cardiac arrest and even death may be associated with abuse of formoterol. No clinically significant adverse reactions were seen when formoterol was delivered to adult patients with acute bronchoconstriction at a dose of 90 mcg/day over 3 hours or to stable asthmatics 3 times a day at a total dose of 54 mcg/day for 3 days.
Treatment of formoterol overdosage consists of discontinuation of the medication together with institution of appropriate symptomatic and/or supportive therapy. The judicious use of a cardioselective beta-receptor blocker may be considered, bearing in mind that such medication can produce bronchospasm. There is insufficient evidence to determine if dialysis is beneficial for overdosage of formoterol.
Cardiac monitoring is recommended in cases of overdosage.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action BREYNA BREYNA contains both budesonide and formoterol fumarate dihydrate; therefore, the mechanisms of action described below for the individual components apply to BREYNA. These drugs represent two classes of medications (a synthetic corticosteroid and a long-acting selective beta 2 -adrenoceptor agonist) that have different effects on clinical, physiological, and inflammatory indices of COPD and asthma. Budesonide Budesonide is an anti-inflammatory corticosteroid that exhibits potent glucocorticoid activity and weak mineralocorticoid activity.
In standard in vitro and animal models, budesonide has approximately a 200-fold higher affinity for the glucocorticoid receptor and a 1000-fold higher topical anti-inflammatory potency than cortisol (rat croton oil ear edema assay). As a measure of systemic activity, budesonide is 40 times more potent than cortisol when administered subcutaneously and 25 times more potent when administered orally in the rat thymus involution assay. In glucocorticoid receptor affinity studies, the 22R form of budesonide was two times as active as the 22S epimer.
In vitro studies indicated that the two forms of budesonide do not interconvert. Inflammation is an important component in the pathogenesis of COPD and asthma. Corticosteroids have a wide range of inhibitory activities against multiple cell types (e.g., mast cells, eosinophils, neutrophils, macrophages, and lymphocytes) and mediators (e.g., histamine, eicosanoids, leukotrienes, and cytokines) involved in allergic and non–allergic-mediated inflammation.
These anti-inflammatory actions of corticosteroids may contribute to their efficacy in COPD and asthma. Studies in asthmatic patients have shown a favorable ratio between topical anti-inflammatory activity and systemic corticosteroid effects over a wide range of doses of budesonide. This is explained by a combination of a relatively high local anti-inflammatory effect, extensive first pass hepatic degradation of orally absorbed drug (85%-95%), and the low potency of formed metabolites.
Formoterol Formoterol fumarate dihydrate is a long-acting selective beta 2 -adrenergic agonist (beta 2 -agonist) with a rapid onset of action. Inhaled formoterol fumarate dihydrate acts locally in the lung as a bronchodilator. In vitro studies have shown that formoterol has more than 200-fold greater agonist activity at beta 2 -receptors than at beta 1 -receptors.
The in vitro binding selectivity to beta 2 - over beta 1 -adrenoceptors is higher for formoterol than for albuterol (5 times), whereas salmeterol has a higher (3 times) beta 2 -selectivity ratio than formoterol. Although beta 2 -receptors are the predominant adrenergic receptors in bronchial smooth muscle and beta 1 -receptors are the predominant receptors in the heart, there are also beta 2 -receptors in the human heart comprising 10% to 50% of the total beta-adrenergic receptors. The precise function of these receptors has not been established, but they raise the possibility that even highly selective beta 2 -agonists may have cardiac effects.
The pharmacologic effects of beta 2 -adrenoceptor agonist drugs, including formoterol, are at least in part attributable to stimulation of intracellular adenyl cyclase, the enzyme that catalyzes the conversion of adenosine triphosphate (ATP) to cyclic-3', 5’-adenosine monophosphate (cyclic AMP). Increased cyclic AMP levels cause relaxation of bronchial smooth muscle and inhibition of release of mediators of immediate hypersensitivity from cells, especially from mast cells. In vitro tests show that formoterol is an inhibitor of the release of mast cell mediators, such as histamine and leukotrienes, from the human lung.
Formoterol also inhibits histamine-induced plasma albumin extravasation in anesthetized guinea pigs and inhibits allergen-induced eosinophil influx in dogs with airway hyper-responsiveness. The relevance of these in vitro and animal findings to humans… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action BREYNA BREYNA contains both budesonide and formoterol fumarate dihydrate; therefore, the mechanisms of action described below for the individual components apply to BREYNA. These drugs represent two classes of medications (a synthetic corticosteroid and a long-acting selective beta 2 -adrenoceptor agonist) that have different effects on clinical, physiological, and inflammatory indices of COPD and asthma. Budesonide Budesonide is an anti-inflammatory corticosteroid that exhibits potent glucocorticoid activity and weak mineralocorticoid activity.
In standard in vitro and animal models, budesonide has approximately a 200-fold higher affinity for the glucocorticoid receptor and a 1000-fold higher topical anti-inflammatory potency than cortisol (rat croton oil ear edema assay). As a measure of systemic activity, budesonide is 40 times more potent than cortisol when administered subcutaneously and 25 times more potent when administered orally in the rat thymus involution assay. In glucocorticoid receptor affinity studies, the 22R form of budesonide was two times as active as the 22S epimer.
In vitro studies indicated that the two forms of budesonide do not interconvert. Inflammation is an important component in the pathogenesis of COPD and asthma. Corticosteroids have a wide range of inhibitory activities against multiple cell types (e.g., mast cells, eosinophils, neutrophils, macrophages, and lymphocytes) and mediators (e.g., histamine, eicosanoids, leukotrienes, and cytokines) involved in allergic and non–allergic-mediated inflammation.
These anti-inflammatory actions of corticosteroids may contribute to their efficacy in COPD and asthma. Studies in asthmatic patients have shown a favorable ratio between topical anti-inflammatory activity and systemic corticosteroid effects over a wide range of doses of budesonide. This is explained by a combination of a relatively high local anti-inflammatory effect, extensive first pass hepatic degradation of orally absorbed drug (85%-95%), and the low potency of formed metabolites.
Formoterol Formoterol fumarate dihydrate is a long-acting selective beta 2 -adrenergic agonist (beta 2 -agonist) with a rapid onset of action. Inhaled formoterol fumarate dihydrate acts locally in the lung as a bronchodilator. In vitro studies have shown that formoterol has more than 200-fold greater agonist activity at beta 2 -receptors than at beta 1 -receptors.
The in vitro binding selectivity to beta 2 - over beta 1 -adrenoceptors is higher for formoterol than for albuterol (5 times), whereas salmeterol has a higher (3 times) beta 2 -selectivity ratio than formoterol. Although beta 2 -receptors are the predominant adrenergic receptors in bronchial smooth muscle and beta 1 -receptors are the predominant receptors in the heart, there are also beta 2 -receptors in the human heart comprising 10% to 50% of the total beta-adrenergic receptors. The precise function of these receptors has not been established, but they raise the possibility that even highly selective beta 2 -agonists may have cardiac effects.
The pharmacologic effects of beta 2 -adrenoceptor agonist drugs, including formoterol, are at least in part attributable to stimulation of intracellular adenyl cyclase, the enzyme that catalyzes the conversion of adenosine triphosphate (ATP) to cyclic-3', 5’-adenosine monophosphate (cyclic AMP). Increased cyclic AMP levels cause relaxation of bronchial smooth muscle and inhibition of release of mediators of immediate hypersensitivity from cells, especially from mast cells. In vitro tests show that formoterol is an inhibitor of the release of mast cell mediators, such as histamine and leukotrienes, from the human lung.
Formoterol also inhibits histamine-induced plasma albumin extravasation in anesthetized guinea pigs and inhibits allergen-induced eosinophil influx in dogs with airway hyper-responsiveness. The relevance of these in vitro and animal findings to humans is unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING BREYNA (budesonide and formoterol fumarate dihydrate) Inhalation Aerosol is available in two strengths and is supplied in the following package sizes: Dosage Forms and Strengths Package Size NDC BREYNA Inhalations 80 mcg/4.5 mcg 120 0378-7502-32 BREYNA Inhalations 160 mcg/4.5 mcg 120 0378-7503-32 Each strength is supplied as a pressurized aluminum canister with an attached counting device, a blue plastic actuator body with a blue mouthpiece, and attached grey dust cap. Each 120 inhalation canister has a net fill weight of 10.3 grams.
Each canister is packaged in a foil overwrap pouch with desiccant sachet and placed into a carton. Each carton contains one canister and a Patient Information leaflet. The BREYNA canister should only be used with the BREYNA actuator, and the BREYNA actuator should not be used with any other inhalation drug product.
The correct amount of medication in each inhalation cannot be ensured after the labeled number of inhalations from the canister have been used, even though the inhaler may not feel completely empty and may continue to operate. The inhaler should be discarded when the labeled number of inhalations have been used or within 3 months after removal from the foil pouch. Never immerse the canister into water to determine the amount remaining in the canister (“float test”).
Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. Store the inhaler with the mouthpiece down. For best results, the canister should be at room temperature before use.
Shake well for 5 seconds before using. Keep out of the reach of children. Avoid spraying in eyes.
CONTENTS UNDER PRESSURE. Do not puncture or incinerate. Do not store near heat or open flame.
Exposure to temperatures over 120ºF may cause bursting. Never throw container into fire or incinerator.
📋 Description ▾
11 DESCRIPTION BREYNA 80 mcg/4.5 mcg and BREYNA 160 mcg/4.5 mcg each contain micronized budesonide and micronized formoterol fumarate dihydrate for oral inhalation only. Each BREYNA 80 mcg/4.5 mcg and BREYNA 160 mcg/4.5 mcg canister is formulated as a hydrofluoroalkane (HFA 227; 1,1,1,2,3,3,3-heptafluoropropane)-propelled pressurized metered dose inhaler containing 120 actuations [see Dosage Forms and Strengths (3) and How Supplied/Storage and Handling (16) ] . After priming, each actuation meters either 91/5.1 mcg or 181/5.1 mcg from the valve and delivers either 80/4.5 mcg, or 160/4.5 mcg (budesonide micronized/formoterol fumarate dihydrate micronized) from the actuator.
The actual amount of drug delivered to the lung may depend on patient factors, such as the coordination between actuation of the device and inspiration through the delivery system. BREYNA also contains povidone K25 USP as a suspending agent and polyethylene glycol 1000 NF as a lubricant. BREYNA should be primed before using for the first time by releasing two test sprays into the air away from the face, shaking well for 5 seconds before each spray.
In cases where the inhaler has not been used for more than 7 days or when it has been dropped, prime the inhaler again by shaking well for 5 seconds before each spray and releasing two test sprays into the air away from the face. One active component of BREYNA is budesonide, a corticosteroid designated chemically as (RS)‑11β, 16α, 17,21-Tetrahydroxypregna-1,4-diene-3,20-dione cyclic 16,17-acetal with butyraldehyde. Budesonide is provided as a mixture of two epimers (22R and 22S).
The empirical formula of budesonide is C 25 H 34 O 6 and its molecular weight is 430.5. Its structural formula is: Budesonide is a white to off-white, tasteless, odorless powder which is practically insoluble in water and in heptane, sparingly soluble in ethanol, and freely soluble in chloroform. Its partition coefficient between octanol and water at pH 7.4 is 1.6 x 10 3 .
The other active component of BREYNA is formoterol fumarate dihydrate, a selective beta 2 -agonist designated chemically as (R*,R*)-(±)-N-[2-hydroxy-5-[1-hydroxy-2-[[2-(4-methoxyphenyl)-1-methylethyl]amino]ethyl]phenyl]formamide, (E)-2-butendioate(2:1), dihydrate. The empirical formula of formoterol is C 42 H 56 N 4 O 14 and its molecular weight is 840.9. Its structural formula is: Formoterol fumarate dihydrate is a powder which is slightly soluble in water.
Its octanol-water partition coefficient at pH 7.4 is 2.6. The pKa of formoterol fumarate dihydrate at 25°C is 7.9 for the phenolic group and 9.2 for the amino group. Budesonide Structural Formula Formoterol Fumarate Dihydrate Structrual Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Patient Information and Instructions for Use ). Serious Asthma-Related Events: Inform patients with asthma that LABA when used alone increases the risk of asthma-related hospitalization or asthma-related death. Available data show that when ICS and LABA are used together, such as with BREYNA, there is not a significant increase in risk of these events.
Not for Acute Symptoms: Inform patients that BREYNA is not meant to relieve acute symptoms of asthma or COPD and extra doses should not be used for that purpose. Advise patients to treat acute symptoms with an inhaled, short-acting beta 2 -agonist such as albuterol. Provide patients with such medication and instruct the patient in how it should be used.
Instruct patients to seek medical attention immediately if they experience any of the following: • Decreasing effectiveness of inhaled, short-acting beta 2 -agonists • Need for more inhalations than usual of inhaled, short-acting beta 2 -agonists • Significant decrease in lung function as outlined by the physician Tell patients they should not stop therapy with BREYNA without physician/provider guidance since symptoms may recur after discontinuation. Do Not Use Additional Long-Acting Beta 2 -Agonists: Instruct patients not to use other LABA for asthma and COPD.
Local Effects: Inform patients that localized infections with Candida albicans occurred in the mouth and pharynx in some patients. If oropharyngeal candidiasis develops, it should be treated with appropriate local or systemic (i.e., oral) antifungal therapy while still continuing therapy with BREYNA, but at times therapy with BREYNA may need to be temporarily interrupted under close medical supervision. Rinsing the mouth with water without swallowing after inhalation is advised to reduce the risk of thrush.
Pneumonia: Patients with COPD have a higher risk of pneumonia; instruct them to contact their healthcare provider if they develop symptoms of pneumonia. Immunosuppression: Warn patients who are on immunosuppressant doses of corticosteroids to avoid exposure to chicken pox or measles and, if exposed, to consult their physician without delay. Inform patients of potential worsening of existing tuberculosis, fungal, bacterial, viral, or parasitic infections, or ocular herpes simplex.
Hypercorticism and Adrenal Suppression: Advise patients that BREYNA may cause systemic corticosteroid effects of hypercorticism and adrenal suppression. Additionally, inform patients that deaths due to adrenal insufficiency have occurred during and after transfer from systemic corticosteroids. Patients should taper slowly from systemic corticosteroids if transferring to BREYNA.
Reduction in Bone Mineral Density: Advise patients who are at an increased risk for decreased BMD that the use of corticosteroids may pose an additional risk. Reduced Growth Velocity: Inform patients that orally inhaled corticosteroids, a component of BREYNA, may cause a reduction in growth velocity when administered to pediatric patients. Physicians should closely follow the growth of children and adolescents taking corticosteroids by any route.
Ocular Effects: Long-term use of inhaled corticosteroids may increase the risk of some eye problems (cataracts or glaucoma); consider regular eye examinations. Risks Associated with Beta-Agonist Therapy: Inform patients of adverse effects associated with beta 2 -agonists, such as palpitations, chest pain, rapid heart rate, tremor, or nervousness. BREYNA is a registered trademark of Mylan Pharmaceuticals Inc., a Viatris Company. © 2025 Viatris Inc.
Distributed by: Mylan Pharmaceuticals Inc., a Viatris Company Morgantown, WV 26505 U.S.A. Revised: 11/2025 KD:BUFOIA:R3 3200001786
🍼 Nursing Mothers ▾
Nursing Mothers The disposition of budesonide when delivered by inhalation from a dry powder inhaler at doses of 200 or 400 mcg twice daily for at least 3 months was studied in eight lactating women with asthma from 1 to 6 months postpartum. Systemic exposure to budesonide in these women appears to be comparable to that in non-lactating women with asthma from other studies. Breast milk obtained over eight hours post-dose revealed that the maximum concentration of budesonide for the 400 and 800 mcg total daily doses was 0.39 and 0.78 nmol/L, respectively, and occurred within 45 minutes after dosing.
The estimated oral daily dose of budesonide from breast milk to the infant is approximately 0.007 and 0.014 mcg/kg/day for the two dose regimens used in this study, which represents approximately 0.3% to 1% of the dose inhaled by the mother. Budesonide levels in plasma samples obtained from five infants at about 90 minutes after breastfeeding (and about 140 minutes after drug administration to the mother) were below quantifiable levels (< 0.02 nmol/L in four infants and < 0.04 nmol/L in one infant) [see Use in Specific Populations (8.2) ] .
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Budesonide and Formoterol Fumarate Dihydrate Inhalation Aerosol Absorption Budesonide Healthy Subjects: Orally inhaled budesonide is rapidly absorbed in the lungs and peak concentration is typically reached within 20 minutes. After oral administration of budesonide peak plasma concentration was achieved in about 1 to 2 hours and the absolute systemic availability was 6%-13% due to extensive first pass metabolism. In contrast, most of the budesonide delivered to the lungs was systemically absorbed.
In healthy subjects, 34% of the metered dose was deposited in the lung (as assessed by plasma concentration method and using a budesonide-containing dry powder inhaler) with an absolute systemic availability of 39% of the metered dose. Following administration of budesonide and formoterol fumarate dihydrate inhalation aerosol 160 mcg/4.5 mcg, two or four inhalations twice daily for 5 days in healthy subjects, plasma concentration of budesonide generally increased in proportion to dose. The accumulation index for the group that received 2 inhalations twice daily was 1.32 for budesonide.
Asthma Patients: In a single-dose study, higher than recommended doses of budesonide and formoterol fumarate dihydrate inhalation aerosol (12 inhalations of budesonide and formoterol fumarate dihydrate inhalation aerosol 160 mcg/4.5 mcg) were administered to patients with moderate asthma. Peak budesonide plasma concentration of 4.5 nmol/L occurred at 20 minutes following dosing. This study demonstrated that the total systemic exposure to budesonide from budesonide and formoterol fumarate dihydrate inhalation aerosol was approximately 30% lower than from inhaled budesonide via a dry powder inhaler (DPI) at the same delivered dose.
Following administration of budesonide and formoterol fumarate dihydrate inhalation aerosol, the half-life of the budesonide component was 4.7 hours. In a repeat dose study, the highest recommended dose of budesonide and formoterol fumarate dihydrate inhalation aerosol (160 mcg/4.5 mcg, two inhalations twice daily) was administered to patients with moderate asthma and healthy subjects for 1 week. Peak budesonide plasma concentration of 1.2 nmol/L occurred at 21 minutes in asthma patients.
Peak budesonide plasma concentration was 27% lower in asthma patients compared to that in healthy subjects. However, the total systemic exposure of budesonide was comparable to that in asthma patients. Peak steady-state plasma concentrations of budesonide administered by DPI in adults with asthma averaged 0.6 and 1.6 nmol/L at doses of 180 mcg and 360 mcg twice daily, respectively.
In asthmatic patients, budesonide showed a linear increase in AUC and C max with increasing dose after both single and repeated dosing of inhaled budesonide. COPD Patients: In a single-dose study, 12 inhalations of budesonide and formoterol fumarate dihydrate inhalation aerosol 80 mcg/4.5 mcg (total dose 960/54 mcg) were administered to patients with COPD. Mean budesonide peak plasma concentration of 3.3 nmol/L occurred at 30 minutes following dosing.
Budesonide systemic exposure was comparable between budesonide and formoterol fumarate dihydrate pMDI and coadministration of budesonide via a metered-dose inhaler and formoterol via a dry powder inhaler (budesonide 960 mcg and formoterol 54 mcg). In the same study, an open-label group of moderate asthma patients also received the same higher dose of budesonide and formoterol fumarate dihydrate inhalation aerosol. For budesonide, COPD patients exhibited 12% greater AUC and 10% lower C max compared to asthma patients.
In the 6-month pivotal lung function clinical study, steady-state pharmacokinetic data of budesonide was obtained in a subset of COPD patients with treatment arms of budesonide and formoterol fumarate dihydrate pMDI 160 mcg/4.5 mcg, budesonide and formoterol fumarate dihydrate pMDI 80 mcg/4.5 mcg, budesonide 160 mcg, budesonide 160 mcg and formoterol 4.5 mcg given together, all admin… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Asthma Cardiovascular Effects In a single-dose cross-over study involving 201 patients with persistent asthma, single-dose treatments of 4.5, 9, and 18 mcg of formoterol in combination with 320 mcg of budesonide delivered via budesonide and formoterol fumarate dihydrate inhalation aerosol were compared to budesonide 320 mcg alone. Dose-ordered improvements in FEV 1 were demonstrated when compared with budesonide. ECGs and blood samples for glucose and potassium were obtained post-dose.
For budesonide and formoterol fumarate dihydrate inhalation aerosol, small mean increases in serum glucose and decreases in serum potassium (+0.44 mmol/L and -0.18 mmol/L at the highest dose, respectively) were observed with increasing doses of formoterol, compared to budesonide. In ECGs, budesonide and formoterol fumarate dihydrate inhalation aerosol produced small dose-related mean increases in heart rate (approximately 3 bpm at the highest dose), and QTc intervals (3-6 msec) compared to budesonide alone. No subject had a QT or QTc value ≥ 500 msec.
In the United States, five 12-week, active- and placebo-controlled studies and one 6-month active-controlled study evaluated 2976 patients aged 6 years and older with asthma. Systemic pharmacodynamic effects of formoterol (heart/pulse rate, blood pressure, QTc interval, potassium, and glucose) were similar in patients treated with budesonide and formoterol fumarate dihydrate inhalation aerosol, compared with patients treated with formoterol dry inhalation powder 4.5 mcg, 2 inhalations twice daily. No patient had a QT or QTc value ≥ 500 msec during treatment.
In three placebo-controlled studies in adolescents and adults with asthma, aged 12 years and older, a total of 1232 patients (553 patients in the budesonide and formoterol fumarate dihydrate inhalation aerosol group) had evaluable continuous 24‑hour electrocardiographic monitoring. Overall, there were no important differences in the occurrence of ventricular or supraventricular ectopy and no evidence of increased risk for clinically significant dysrhythmia in the budesonide and formoterol fumarate dihydrate inhalation aerosol group compared to placebo.
HPA-axis Effects Overall, no clinically important effects on HPA-axis, as measured by 24-hour urinary cortisol, were observed for budesonide and formoterol fumarate dihydrate inhalation aerosol treated adult or adolescent patients at doses up to 640/18 mcg/day compared to budesonide. Chronic Obstructive Pulmonary Disease Cardiovascular Effects In two COPD lung function studies, 6 months and 12 months in duration including 3668 COPD patients, no clinically important differences were seen in pulse rate, blood pressure, potassium, and glucose between budesonide and formoterol fumarate dihydrate inhalation aerosol, the individual components of budesonide and formoterol fumarate dihydrate inhalation aerosol, and placebo [see Clinical Studies (14.2) ] .
ECGs recorded at multiple clinic visits on treatment in both studies showed no clinically important differences for heart rate, PR interval, QRS duration, heart rate, signs of cardiac ischemia or arrhythmias between budesonide and formoterol fumarate dihydrate inhalation aerosol 160 mcg/4.5 mcg, the monoproducts and placebo, all administered as 2 inhalations twice daily. Based on ECGs, 6 patients treated with budesonide and formoterol fumarate dihydrate inhalation aerosol 160 mcg/4.5 mcg, 6 patients treated with formoterol 4.5 mcg, and 6 patients in the placebo group experienced atrial fibrillation or flutter that was not present at baseline.
There were no cases of nonsustained ventricular tachycardia in the budesonide and formoterol fumarate dihydrate inhalation aerosol 160 mcg/4.5 mcg, formoterol 4.5 mcg, or placebo groups. In the 12-month study, 520 patients had evaluable continuous 24-hour ECG (Holter) monitoring prior to the first dose and after approximately 1 and 4 months on treatment. No clinically important differences in… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Asthma Patients with Asthma 12 Years of Age and Older In two clinical studies comparing budesonide and formoterol fumarate dihydrate inhalation aerosol with the individual components, improvements in most efficacy end points were greater with budesonide and formoterol fumarate dihydrate inhalation aerosol than with the use of either budesonide or formoterol alone. In addition, one clinical study showed similar results between budesonide and formoterol fumarate dihydrate inhalation aerosol and the concurrent use of budesonide and formoterol at corresponding doses from separate inhalers.
The safety and efficacy of budesonide and formoterol fumarate dihydrate inhalation aerosol were demonstrated in two randomized, double-blind, placebo-controlled US clinical studies involving 1076 patients 12 years of age and older. Fixed budesonide and formoterol fumarate dihydrate inhalation aerosol dosages of 160/9 mcg, and 320/9 mcg twice daily (each dose administered as 2 inhalations of the 80 mcg/4.5 mcg and 160 mcg/4.5 mcg strengths, respectively) were compared with the monocomponents (budesonide and formoterol) and placebo to provide information about appropriate dosing to cover a range of asthma severity.
Study 1: Clinical Study with Budesonide and Formoterol Fumarate Dihydrate Inhalation Aerosol 160 mcg/4.5 mcg This 12-week study evaluated 596 patients 12 years of age and older by comparing budesonide and formoterol fumarate dihydrate inhalation aerosol 160 mcg/4.5 mcg, the free combination of budesonide 160 mcg plus formoterol 4.5 mcg in separate inhalers, budesonide 160 mcg, formoterol 4.5 mcg, and placebo; each administered as 2 inhalations twice daily. The study included a 2-week run-in period with budesonide 80 mcg, 2 inhalations twice daily.
Most patients had moderate to severe asthma and were using moderate to high doses of inhaled corticosteroids prior to study entry. Randomization was stratified by previous inhaled corticosteroid treatment (71.6% on moderate- and 28.4% on high-dose inhaled corticosteroid). Mean percent predicted FEV 1 at baseline was 68.1% and was similar across treatment groups.
The co-primary efficacy end points were 12-hour-average post-dose FEV 1 at week 2, and pre-dose FEV 1 averaged over the course of the study. The study also required that patients who satisfied a predefined asthma-worsening criterion be withdrawn. The predefined asthma-worsening criteria were a clinically important decrease in FEV 1 or PEF, increase in rescue albuterol use, nighttime awakening due to asthma, emergency intervention or hospitalization due to asthma, or requirement for asthma medication not allowed by the protocol.
For the criterion of nighttime awakening due to asthma, patients were allowed to remain in the study at the discretion of the investigator if none of the other asthma-worsening criteria were met. The percentage of patients withdrawing due to or meeting predefined criteria for worsening asthma is shown in Table 4. Table 4.
The Number and Percentage of Patients Withdrawing Due to or Meeting Predefined Criteria for Worsening Asthma (Study 1) Budesonide and Formoterol Fumarate Dihydrate Inhalation Aerosol 160 mcg/4.5 mcg n = 124 Budesonide 160 mcg plus Formoterol 4.5 mcg n = 115 Budesonide 160 mcg n = 109 Formoterol 4.5 mcg n = 123 Placebo n = 125 Patients withdrawn due to predefined asthma event These criteria were assessed on a daily basis irrespective of the timing of the clinic visit, with the exception of FEV1, which was assessed at each clinic visit.
13 (10.5) 13 (11.3) 22 (20.2) 44 (35.8) 62 (49.6) Patients with a predefined asthma event , Individual criteria are shown for patients meeting any predefined asthma event, regardless of withdrawal status. 37 (29.8) 24 (20.9) 48 (44.0) 68 (55.3) 84 (67.2) Decrease in FEV 1 4 (3.2) 8 (7.0) 7 (6.4) 15 (12.2) 14 (11.2) Rescue medication use 2 (1.6) 0 3 (2.8) 3 (2.4) 7 (5.6) Decrease in AM PEF 2 (1.6) 5 (4.3) 5 (4.6) 17 (13.8) 15 (12.0) Nightti… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Budesonide Long-term studies were conducted in rats and mice using oral administration to evaluate the carcinogenic potential of budesonide. In a 2-year study in Sprague-Dawley rats, budesonide caused a statistically significant increase in the incidence of gliomas in male rats at an oral dose of 50 mcg/kg (approximately equivalent to the MRHDID in adults and children on a mcg/m 2 basis). No tumorigenicity was seen in male and female rats at respective oral doses up to 25 and 50 mcg/kg (approximately equivalent to the MRHDID in adults and children on a mcg/m 2 basis).
In two additional 2-year studies in male Fischer and Sprague-Dawley rats, budesonide caused no gliomas at an oral dose of 50 mcg/kg (approximately equivalent to the MRHDID in adults and children on a mcg/m 2 basis). However, in the male Sprague-Dawley rats, budesonide caused a statistically significant increase in the incidence of hepatocellular tumors at an oral dose of 50 mcg/kg (approximately equivalent to the MRHDID in adults and children on a mcg/m 2 basis). The concurrent reference corticosteroids (prednisolone and triamcinolone acetonide) in these two studies showed similar findings.
In a 91-week study in mice, budesonide caused no treatment-related carcinogenicity at oral doses up to 200 mcg/kg (approximately 2 times the MRHDID in adults and children on a mcg/m 2 basis). Budesonide was not mutagenic or clastogenic in six different test systems: Ames Salmonella /microsome plate test, mouse micronucleus test, mouse lymphoma test, chromosome aberration test in human lymphocytes, sex-linked recessive lethal test in Drosophila melanogaster , and DNA repair analysis in rat hepatocyte culture. Fertility and reproductive performance were unaffected in rats at subcutaneous doses up to 80 mcg/kg (approximately equal to the MRHDID on a mcg/m 2 basis).
However, it caused a decrease in prenatal viability and viability in the pups at birth and during lactation, along with a decrease in maternal body-weight gain, at subcutaneous doses of 20 mcg/kg and above (less than the MRHDID on a mcg/m 2 basis). No such effects were noted at 5 mcg/kg (less than the MRHDID on a mcg/m 2 basis). Formoterol Long-term studies were conducted in mice using oral administration and rats using inhalation administration to evaluate the carcinogenic potential of formoterol fumarate.
In a 24-month carcinogenicity study in CD-1 mice, formoterol at oral doses of 100 mcg/kg and above (approximately 30 and 15 times the MRHDID in adults and children, respectively, on a mcg/m 2 basis) caused a dose-related increase in the incidence of uterine leiomyomas. In a 24-month carcinogenicity study in Sprague-Dawley rats, an increased incidence of mesovarian leiomyoma and uterine leiomyosarcoma were observed at the inhaled dose of 130 mcg/kg (approximately 70 and 35 times the MRHDID in adults and children, respectively, on a mcg/m 2 basis).
No tumors were seen at 22 mcg/kg (approximately 12 and 6 times the MRHDID in adults and children, respectively, on a mcg/m 2 basis). Other beta-agonist drugs have similarly demonstrated increases in leiomyomas of the genital tract in female rodents. The relevance of these findings to human use is unknown.
Formoterol was not mutagenic or clastogenic in Ames Salmonella /microsome plate test, mouse lymphoma test, chromosome aberration test in human lymphocytes, and rat micronucleus test. A reduction in fertility and/or reproductive performance was identified in male rats treated with formoterol at an oral dose of 15,000 mcg/kg (approximately 2200 times the MRHDID on an AUC basis). No such effect was seen at 3000 mcg/kg (approximately 1600 times the MRHDID on a mcg/m 2 basis).
In a separate study with male rats treated with an oral dose of 15,000 mcg/kg (approximately 8000 times the MRHDID on a mcg/m 2 basis), there were findings of testicular tubular atrophy and spermatic debris in the testes a… [Excerpted — this section continues on DailyMed.]
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Budesonide Long-term studies were conducted in rats and mice using oral administration to evaluate the carcinogenic potential of budesonide. In a 2-year study in Sprague-Dawley rats, budesonide caused a statistically significant increase in the incidence of gliomas in male rats at an oral dose of 50 mcg/kg (approximately equivalent to the MRHDID in adults and children on a mcg/m 2 basis). No tumorigenicity was seen in male and female rats at respective oral doses up to 25 and 50 mcg/kg (approximately equivalent to the MRHDID in adults and children on a mcg/m 2 basis).
In two additional 2-year studies in male Fischer and Sprague-Dawley rats, budesonide caused no gliomas at an oral dose of 50 mcg/kg (approximately equivalent to the MRHDID in adults and children on a mcg/m 2 basis). However, in the male Sprague-Dawley rats, budesonide caused a statistically significant increase in the incidence of hepatocellular tumors at an oral dose of 50 mcg/kg (approximately equivalent to the MRHDID in adults and children on a mcg/m 2 basis). The concurrent reference corticosteroids (prednisolone and triamcinolone acetonide) in these two studies showed similar findings.
In a 91-week study in mice, budesonide caused no treatment-related carcinogenicity at oral doses up to 200 mcg/kg (approximately 2 times the MRHDID in adults and children on a mcg/m 2 basis). Budesonide was not mutagenic or clastogenic in six different test systems: Ames Salmonella /microsome plate test, mouse micronucleus test, mouse lymphoma test, chromosome aberration test in human lymphocytes, sex-linked recessive lethal test in Drosophila melanogaster , and DNA repair analysis in rat hepatocyte culture. Fertility and reproductive performance were unaffected in rats at subcutaneous doses up to 80 mcg/kg (approximately equal to the MRHDID on a mcg/m 2 basis).
However, it caused a decrease in prenatal viability and viability in the pups at birth and during lactation, along with a decrease in maternal body-weight gain, at subcutaneous doses of 20 mcg/kg and above (less than the MRHDID on a mcg/m 2 basis). No such effects were noted at 5 mcg/kg (less than the MRHDID on a mcg/m 2 basis). Formoterol Long-term studies were conducted in mice using oral administration and rats using inhalation administration to evaluate the carcinogenic potential of formoterol fumarate.
In a 24-month carcinogenicity study in CD-1 mice, formoterol at oral doses of 100 mcg/kg and above (approximately 30 and 15 times the MRHDID in adults and children, respectively, on a mcg/m 2 basis) caused a dose-related increase in the incidence of uterine leiomyomas. In a 24-month carcinogenicity study in Sprague-Dawley rats, an increased incidence of mesovarian leiomyoma and uterine leiomyosarcoma were observed at the inhaled dose of 130 mcg/kg (approximately 70 and 35 times the MRHDID in adults and children, respectively, on a mcg/m 2 basis).
No tumors were seen at 22 mcg/kg (approximately 12 and 6 times the MRHDID in adults and children, respectively, on a mcg/m 2 basis). Other beta-agonist drugs have similarly demonstrated increases in leiomyomas of the genital tract in female rodents. The relevance of these findings to human use is unknown.
Formoterol was not mutagenic or clastogenic in Ames Salmonella /microsome plate test, mouse lymphoma test, chromosome aberration test in human lymphocytes, and rat micronucleus test. A reduction in fertility and/or reproductive performance was identified in male rats treated with formoterol at an oral dose of 15,000 mcg/kg (approximately 2200 times the MRHDID on an AUC basis). No such effect was seen at 3000 mcg/kg (approximately 1600 times the MRHDID on a mcg/m 2 basis).
In a separate study with male rats treated with an oral dose of 15,000 mcg/kg (approximately 8000 times the MRHDID on a mcg/m 2 basis), there were findings of testicular tubular atrophy and spermatic debris in the testes and oligospermia in the epi… [Excerpted — this section continues on DailyMed.]
📄 Patient Package Insert ▾
Patient Information BREYNA (brehy-nah) (budesonide 80 mcg and formoterol fumarate dihydrate 4.5 mcg) Inhalation Aerosol BREYNA (brehy-nah) (budesonide 160 mcg and formoterol fumarate dihydrate 4.5 mcg) Inhalation Aerosol What is BREYNA? BREYNA combines an inhaled corticosteroid medicine (ICS), budesonide and a long-acting beta 2 -adrenergic agonist (LABA) medicine, formoterol. • Inhaled corticosteroids help to decrease inflammation in the lungs. Inflammation in the lungs can lead to breathing problems. • LABA medicines are used in people with chronic obstructive pulmonary disease (COPD) and asthma.
LABA medicines help the muscles around the airways in your lungs stay relaxed to prevent symptoms such as wheezing, cough, chest tightness, and shortness of breath. These symptoms can happen when the muscles around the airways tighten. This makes it hard to breathe.
In severe cases, wheezing can stop your breathing and may lead to death if not treated right away. BREYNA is not used to relieve sudden breathing problems and will not replace a rescue inhaler. BREYNA is used for asthma and COPD as follows: • Asthma: BREYNA is used to control symptoms of asthma, and prevent symptoms such as wheezing in adults and children ages 6 and older.
BREYNA contains formoterol. LABA medicines such as formoterol when used alone increase the risk of death and hospitalizations from asthma problems. BREYNA contains an ICS and a LABA.
When an ICS and LABA are used together, there is not a significant increased risk in hospitalizations and death from asthma problems. BREYNA is not for adults and children with asthma who are well controlled with an asthma-control medicine, such as a low to medium dose of an ICS. BREYNA is for adults and children with asthma who need both an ICS and LABA medicine.
It is not known if BREYNA is safe and effective in children less than 6 years of age with asthma. • COPD: COPD is a long-term (chronic) lung disease that includes chronic bronchitis, emphysema, or both. BREYNA 160 mcg/4.5 mcg is used long-term, as 2 inhalations 2 times each day, to improve symptoms of COPD for better breathing and to reduce the number of flare-ups (the worsening of your COPD symptoms for several days). Do not use BREYNA: • to treat sudden severe symptoms of asthma or COPD. • if you are allergic to any of the ingredients in BREYNA.
See the end of this leaflet for a list of ingredients in BREYNA. Before you use BREYNA, tell your healthcare provider about all of your medical conditions, including if you: • have heart problems. • have high blood pressure. • have seizures. • have thyroid problems. • have diabetes. • have liver problems. • have osteoporosis. • have an immune system problem. • have eye problems such as increased pressure in the eye, glaucoma, or cataracts. • are allergic to any medicines. • have any type of viral, bacterial, fungal, or parasitic infection. • are exposed to chicken pox or measles. • are pregnant or plan to become pregnant.
It is not known if BREYNA may harm your unborn baby. • are breastfeeding. Budesonide, one of the active ingredients in BREYNA, passes into breast milk. You and your healthcare provider should decide if you will take BREYNA while breastfeeding.
Tell your healthcare provider about all the medicines you take including prescription and over-the-counter medicines, vitamins, and herbal supplements. BREYNA and certain other medicines may interact with each other. This may cause serious side effects.
Especially tell your healthcare provider if you take antifungal or anti-HIV medicines. Know all the medicines you take. Keep a list and show it to your healthcare provider and pharmacist each time you get a new medicine.
How should I use BREYNA? See the step-by-step instructions for using BREYNA at the end of this Patient Information leaflet. Do not use BREYNA unless your healthcare provider has taught you and you understand everything.
Ask your healthcare provider or pharmacist if you have any questions. • Use BR… [Excerpted — this section continues on DailyMed.]
📖 Instructions for Use ▾
Instructions for Use BREYNA (brehy-nah) (budesonide 80 mcg and formoterol fumarate dihydrate 4.5 mcg) Inhalation Aerosol BREYNA (brehy-nah) (budesonide 160 mcg and formoterol fumarate dihydrate 4.5 mcg) Inhalation Aerosol Figure 1 Upright Position How to Use BREYNA Follow the instructions below for using BREYNA. You will breathe-in (inhale) the medicine. If you have any questions, ask your doctor or pharmacist.
Preparing your BREYNA inhaler for use 1. Take your BREYNA out of the moisture-protective foil pouch before you use it for the first time and throw the foil away. Write the date that you open the foil pouch on the box.
2. The inhaler comes with a counter (see Figure 1). The counter will count down each time you release a puff of BREYNA.
The counter will show the number of inhalations (puffs) left in the canister. The counter will stop counting at zero (“0”). 3.
Use the BREYNA canister only with the blue BREYNA inhaler supplied with the product. Parts of the BREYNA inhaler should not be used with parts from any other inhalation product. 4.
Shake your BREYNA inhaler well for 5 seconds right before each use. Remove the mouthpiece cover by squeezing gently at both sides, then pulling out (see Figure 2). Check the mouthpiece for foreign objects before use.
Figure 2 5. Priming your BREYNA inhaler Before you use BREYNA for the first time, you will need to prime it. To prime BREYNA, hold it in the upright position (see Figure 1).
Shake the BREYNA inhaler well for 5 seconds. Hold your BREYNA inhaler facing away from you and press down the top of the canister firmly until fully depressed to release a test spray. Then shake it again for 5 seconds and release a second test spray.
Your BREYNA inhaler is now primed and ready for use. After you have primed the BREYNA inhaler for the first time, the counter will read 120. If you do not use your BREYNA inhaler for more than 7 days or if you drop it, you will need to prime again.
Ways to hold the BREYNA inhaler for use Figure 3 or Figure 4 Using your BREYNA inhaler 6. Shake your BREYNA inhaler well for 5 seconds. Remove the mouthpiece cover.
Check the mouthpiece for foreign objects. 7. Breathe out fully (exhale).
Hold the BREYNA inhaler up to your mouth. Place the blue mouthpiece fully into your mouth and close your lips around it. Make sure that the BREYNA inhaler is upright and that the opening of the mouthpiece is pointing towards the back of your throat (see Figure 5).
Figure 5 8. Breathe in (inhale) deeply and slowly through your mouth. Press down the top of the canister firmly until fully depressed to release the medicine (see Figure 6).
Figure 6 9. Continue to breathe in (inhale) and hold your breath for about 10 seconds, or for as long as is comfortable. Before you breathe out (exhale), release your finger from the top of the canister.
Keep the BREYNA inhaler upright and remove from your mouth. 10. Shake the BREYNA inhaler again for 5 seconds and repeat steps 7 to 9.
After using your BREYNA inhaler 11. After use, close the mouthpiece cover by pushing until it clicks in place. 12.
After you finish taking BREYNA (2 puffs), rinse your mouth with water. Spit out the water. Do not swallow it.
Reading the counter • The counter shows the number of inhalations (puffs) left in your inhaler. Counter • The counter will count down each time you release a puff of medicine (either when priming your BREYNA inhaler or when taking the medicine). • When the counter reads 20, it is time to call your healthcare provider for a refill. • It is important that you pay attention to the number of inhalations (puffs) left in your BREYNA inhaler by reading the counter. Throw away BREYNA when the counter shows zero (“0”) or 3 months after you take your BREYNA inhaler out of its foil pouch, whichever comes first.
Your BREYNA inhaler may not feel empty and it may continue to operate, but you will not get the right amount of medicine if you keep using it. Use a new BREYNA inhaler and follow the instructions for… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL – 80 mcg/4.5 mcg NDC 0378-7502-32 Rx only STORE UPRIGHT Breyna ® (budesonide and formoterol fumarate dihydrate) Inhalation Aerosol 80 mcg/4.5 mcg FOR ORAL INHALATION ONLY 120 Inhalations Important: Please read accompanying Patient Information and Instructions for Use carefully prior to using. Contents: Each carton contains one canister. Net fill weight 10.3 g providing 120 inhalations.
Each actuation delivers 80 mcg of budesonide and 4.5 mcg of formoterol fumarate dihydrate. Inactive ingredients include povidone K25, polyethylene glycol 1000, and HFA 227. Dosage: Use only as directed by Physician.
Warning: Avoid spraying in eyes. Contents under pressure. Do not puncture or incinerate.
Do not store at temperatures above 120°F. Keep out of the reach of children. Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Store the inhaler with the mouthpiece down.
Shake inhaler well for 5 seconds before using. Discard within three months after removing from foil pouch. For oral inhalation with BREYNA inhaler only.
Use this device for BREYNA only. Date foil pouch opened: ________ Discard the inhaler when the labeled number of inhalations have been used or within 3 months of opening the foil pouch. Don’t Forget to Take Daily www.VIATRIS.com Distributed by: Mylan Pharmaceuticals Inc., a Viatris Company Morgantown, WV 26505, U.S.A.
BREYNA is a registered trademark of Mylan Pharmaceuticals Inc., a Viatris Company. © 2025 Viatris Inc. KD:7502:1C:R2 3200001785 Breyna Inhalation Aerosol 80 mcg/4.5 mcg Carton
PRINCIPAL DISPLAY PANEL – 160 mcg/4.5 mcg NDC 0378-7503-32 Rx only STORE UPRIGHT Breyna ® (budesonide and formoterol fumarate dihydrate) Inhalation Aerosol 160 mcg/4.5 mcg FOR ORAL INHALATION ONLY 120 Inhalations Important: Please read accompanying Patient Information and Instructions for Use carefully prior to using. Contents: Each carton contains one canister. Net fill weight 10.3 g providing 120 inhalations.
Each actuation delivers 160 mcg of budesonide and 4.5 mcg of formoterol fumarate dihydrate. Inactive ingredients include povidone K25, polyethylene glycol 1000, and HFA 227. Dosage: Use only as directed by Physician.
Warning: Avoid spraying in eyes. Contents under pressure. Do not puncture or incinerate.
Do not store at temperatures above 120°F. Keep out of the reach of children. Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Store the inhaler with the mouthpiece down.
Shake inhaler well for 5 seconds before using. Discard within three months after removing from foil pouch. For oral inhalation with BREYNA inhaler only.
Use this device for BREYNA only. Date foil pouch opened: ________ Discard the inhaler when the labeled number of inhalations have been used or within 3 months of opening the foil pouch. Don’t Forget to Take Daily www.VIATRIS.com Distributed by: Mylan Pharmaceuticals Inc., a Viatris Company Morgantown, WV 26505, U.S.A.
BREYNA is a registered trademark of Mylan Pharmaceuticals Inc., a Viatris Company. © 2025 Viatris Inc. KD:7503:1C:R2 3200001790 Breyna Inhalation Aerosol 160 mcg/4.5 mcg Carton