
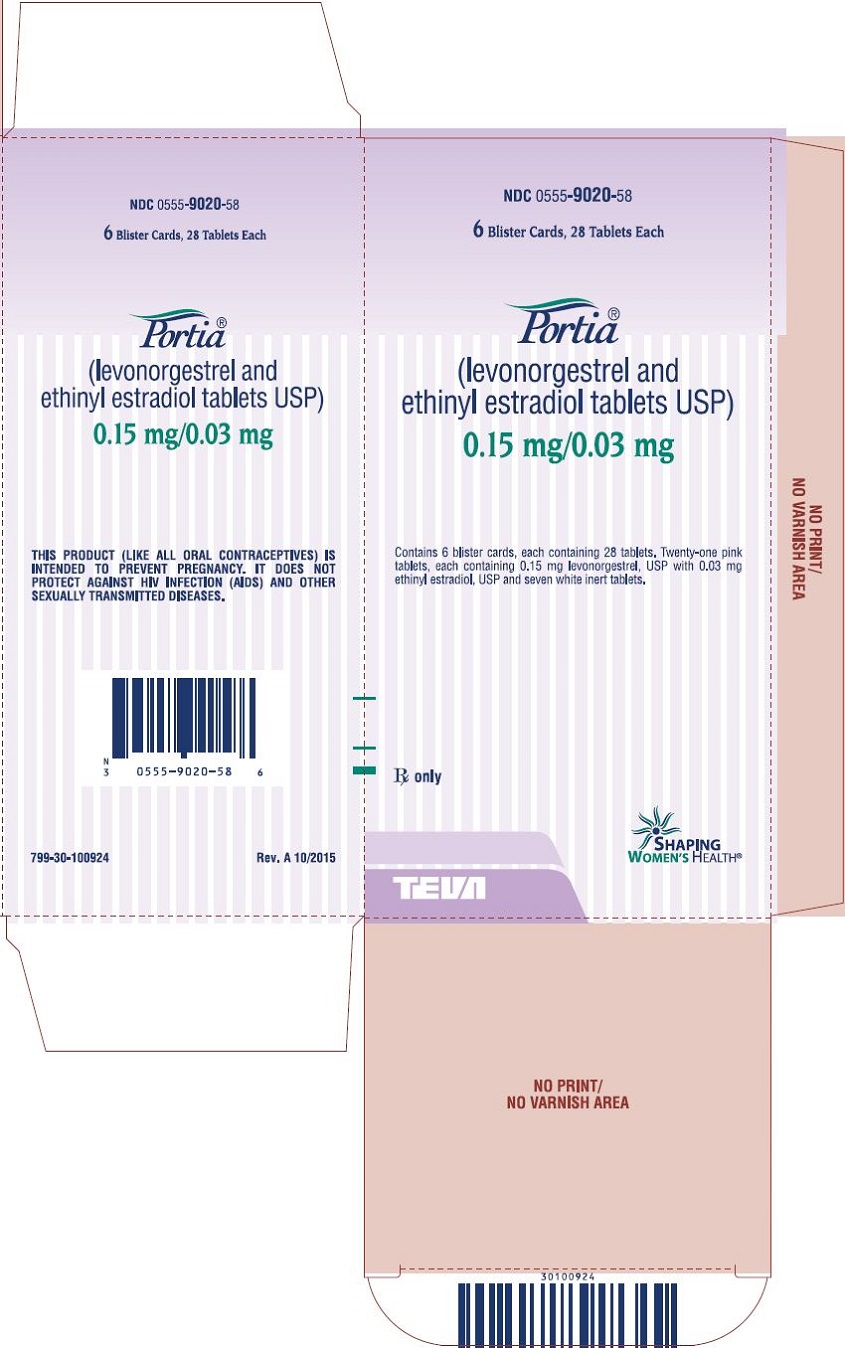
Portia Levonorgestrel and Ethinyl Estradiol Kit, 6 pouches — NDC 0555-9020-58 (Billing 00555-9020-58)
This is a package of 6 pouches of Portia Levonorgestrel and Ethinyl Estradiol Kit from Teva Pharmaceuticals USA, Inc., marketed since Jun 2002 and currently FDA-listed; retail pharmacies pay about $0.1135 per pouche (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0555-9020-58 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0555 labeler · 9020 product · 58 package
- Package marketed since
- Jun 27, 2002
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 6 EA per package
- Barcode (UPC-A, from the NDC)
- 3 0555902058 6
- Medicaid fills, this package
- 11,508 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 003314
- GCN: 11530
- GPI-14 (Medi-Span): 25990002400310
- HICL (First Databank): 001460
- AHFS class code: 68:12.00.00
- RxCUI (RxNorm): 238019
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Estrogen class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Oral contraceptives (birth-control pills) containing ethinyl estradiol (an estrogen) and levonorgestrel (a progestin) are used to prevent pregnancy. Estrogen and progestin are two female sex hormones. Combinations of estrogen and progestin work by preventing ovulation (the release of eggs from the ovaries). Oral contraceptives are an effective method of birth control, but they do not prevent the spread of human immunodeficiency virus (HIV, the virus that causes acquired immunodeficiency syndrome [AIDS]) and other sexually transmitted diseases.
Read the full MedlinePlus article ↗- It prevents pregnancy. It is a combined hormonal birth control with an estrogen and a progestin. It comes as daily tablets or as the weekly Twirla patch.
- With tablets, you take one at the same time every day, no more than 24 hours apart. With the Twirla patch, you wear one patch for a week, three weeks in a row, then take a patch-fr...
- Headache, nausea, acne, breast tenderness, mood changes, and irregular bleeding are the common ones. Bleeding changes often settle with time. Call your doctor if they persist.
- Get help for chest pain, sudden shortness of breath, leg swelling or pain, vision loss, or severe new headaches. These can signal a blood clot or stroke. Also report yellowing of y...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.114 | $0.68 / 6 kit |
| Medicaid paysCMS SDUD · 12 mo | $0.2561 | $1.54 / 6 kit |
| Medicare drug plans payPart D · Q2 2026 | $0.1709 | $1.03 / 6 kit |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00555-9020-58 You're viewing this Main listing | 6 POUCH in 1 CARTON / 1 BLISTER PACK in 1 POUCH / 1 KIT in 1 BLISTER PACK | 2002-06-27 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Levonorgestrel And Ethinyl Estradiol 00378-6550-53 | Mylan | 3 pouches | $0.113 | AB | Discontinued | save 1% |
| Altavera 70700-0116-85 | Xiromed, | 1 kit | $0.114 | AB | Availability likely | — |
| Ayuna 65862-0848-88 | Aurobindo | 3 pouches | $0.114 | AB | Availability likely | — |
| Chateal EQ 50102-0230-23 | Afaxys | 3 pouches | $0.114 | AB | Availability likely | — |
| Marlissa 68462-0388-29 | Glenmark | 1 kit | $0.114 | AB | Availability likely | — |
| Kurvelo 68180-0844-73 | Lupin | 63 tablets | $0.114 | AB | Availability likely | — |
| Portiathis 00555-9020-58 | Teva | 6 pouches | $0.114 | — | Availability likely | — |
| Daysee 68180-0846-13 | Lupin | 2 pouches | $0.125 | AB | Availability likely | +10% |
| Levora 51862-0097-06 | Mayne | 1 kit | $0.145 | AB | Discontinued | +27% |
| Levonorgestrel And Ethinyl Estradiol 00378-7287-53 | Mylan | 3 pouches | $0.151 | AB1 | Availability likely | +33% |
| Lutera 51862-0028-06 | Mayne | 1 kit | $0.152 | AB1 | Discontinued | +34% |
| Lessina 00555-9014-67 | Teva | 3 pouches | $0.154 | — | Availability likely | +35% |
| Aubra EQ 50102-0220-23 | Afaxys | 3 pouches | $0.154 | AB1 | Availability likely | +35% |
| Levonorgestrel and Ethinyl Estradiol 68180-0854-73 | Lupin | 1 kit | $0.154 | AB1 | Availability likely | +35% |
| Aviane 00555-9045-58 | Teva | 6 pouches | $0.154 | — | Availability likely | +35% |
| Vienva 70700-0118-85 | Xiromed, | 1 kit | $0.154 | AB1 | Availability likely | +35% |
| Falmina 16714-0359-01 | Northstar | 1 packet | $0.154 | AB1 | Availability likely | +35% |
| Sronyx 51862-0545-06 | Mayne | 1 kit | $0.174 | AB2 | Discontinued | +53% |
| Introvale 70700-0117-87 | Xiromed, | 1 kit | $0.184 | AB | FDA listed | +62% |
| Afirmelle 65862-0849-88 | Aurobindo | 3 pouches | $0.225 | AB1 | FDA listed | +98% |
| Iclevia 65862-0865-83 | Aurobindo | 3 pouches | $0.227 | AB | FDA listed | +100% |
| Setlakin 16714-0366-03 | Northstar | 3 pouches | $0.227 | AB | Availability likely | +100% |
| Levonorgestrel and Ethinyl Estradiol 68180-0843-13 | Lupin | 1 kit | $0.227 | AB | Availability likely | +100% |
| levonorgestrel and ethinyl estradiol 68462-0672-95 | Glenmark | 3 pouches | $0.227 | AB | Availability likely | +100% |
| Levonorgestrel and Ethinyl Estradiol and Ethinyl Estradiol 68180-0848-13 | Lupin | 2 pouches | $0.239 | AB | Availability likely | +111% |
| Levonest 16714-0340-01 | Northstar | 1 packet | $0.324 | AB | Availability likely | +185% |
| Levonorgestrel and Ethinyl Estradiol 68180-0857-73 | Lupin | 1 kit | $0.324 | AB | Availability likely | +185% |
| Tyblume 00642-7471-01 | Exeltis | 1 kit | $0.828 | — | Availability likely | +629% |
| levonorgestrel and ethinyl estradiol 42192-0623-03 | Acella | 1 kit | $3.445 | AB3 | Availability likely | +2935% |
| Levonest 50090-2505-00 | A-S | 1 kit | — | AB | FDA listed | — |
| Kurvelo 50090-6374-00 | A-S | 21 tablets | — | AB | FDA listed | — |
| Altavera 63629-2343-01 | Bryant | 1 kit | — | AB | FDA listed | — |
| Lutera 55741-0005-06 | Dr. | 1 kit | — | AB1 | FDA listed | — |
| Balcoltra 75854-0602-02 | Avion | 1 kit | — | AB3 | FDA listed | — |
| Vienva Tm 50090-5580-00 | A-S | 1 kit | — | AB1 | FDA listed | — |
| Levonorgestrel and Ethinyl Estradiol 79929-0003-07 | Naari | 1 kit | — | AB | FDA listed | — |
| Levonorgestrel and Ethinyl Estradiol 60505-4898-08 | Apotex | 1 kit | — | AB1 | FDA listed | — |
| Levonorgestrel and Ethinyl Estradiol 60505-4899-08 | Apotex | 1 kit | — | AB | FDA listed | — |
| Vienva TM 63629-2344-01 | Bryant | 1 kit | — | AB1 | FDA listed | — |
| Levonorgestrel and Ethinyl Estradiol 79929-0004-07 | Naari | 1 kit | — | AB1 | FDA listed | — |
| Aviane 63187-0889-28 | Proficient | 1 pouch | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Teva Pharmaceuticals USA, Inc. labeler code 00555
- Nortrel 21 Day Norethindrone and Ethinyl Estradiol 1 mg; .035 mg Tablet NDC 0555-9009-42
- Nortrel 28 Day Norethindrone and Ethinyl Estradiol Kit NDC 0555-9010-58
- Nortrel 7/7/7 (28 Day Regimen) Norethindrone and Ethinyl Estradiol Kit NDC 0555-9012-58
- Lessina Levonorgestrel and Ethinyl Estradiol Kit NDC 0555-9014-67
- Sprintec Norgestimate and Ethinyl Estradiol Kit NDC 0555-9016-58
- Tri-Sprintec norgestimate and ethinyl estradiol Kit NDC 0555-9018-58
- Junel 21 Day Norethindrone Acetate and Ethinyl Estradiol 1 mg; 20 ug Tablet NDC 0555-9025-42
- Junel Fe 28 Day Norethindrone Acetate and Ethinyl Estradiol and Ferrous Fumarate Kit NDC 0555-9026-58
- Junel 21 Day Norethindrone Acetate and Ethinyl Estradiol 1.5 mg; 30 ug Tablet NDC 0555-9027-42
- Junel Fe 28 Day Norethindrone Acetate and Ethinyl Estradiol and Ferrous Fumarate Kit NDC 0555-9028-58
- Tri-Legest Fe 28 Day Norethindrone Acetate and Ethinyl Estradiol Kit NDC 0555-9032-70
- Balziva Norethindrone and Ethinyl Estradiol Kit NDC 0555-9034-58
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: CIGARETTE SMOKING AND SERIOUS CARDIOVASCULAR EVENTS Cigarette smoking increases the risk of serious cardiovascular events from combination oral contraceptive (COC) use. This risk increases with age, particularly in women over 35 years of age, and with the number of cigarettes smoked. For this reason, COCs, including Portia ® , are contraindicated in women who are over 35 years of age and smoke [see CONTRAINDICATIONS and WARNINGS (1) ] .
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Portia ® (levonorgestrel and ethinyl estradiol tablets USP) is indicated for use by females of reproductive potential to prevent pregnancy.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION 1. How to Start and Take Portia ® Portia ® is dispensed in a blister card containing 28 tablets (see HOW SUPPLIED ). Portia ® may be started using either a Day 1 start or a Sunday start (see Table 3).
For the first cycle of a Sunday start regimen, an additional method of contraception should be used until after the first 7 consecutive days of administration. Table 3: Instructions for Administration of Portia® Starting Portia ® in females with no current use of hormonal contraception Day 1 start Take first tablet without regard to meals on the first day of menses Take subsequent tablets once daily at the same time each day Begin each subsequent pack on the same day of the week as the first cycle pack (i.e., on the day after taking the last tablet) Sunday start Take first tablet without regard to meals on the first Sunday after the onset of menstrual period Take subsequent tablets once daily at the same time each day Use additional nonhormonal contraception for the first seven days of product use Begin each subsequent pack on the same day of the week as the first cycle pack (i.e., on the day after taking the last tablet) Switching from another contraceptive method A COC Start Portia ® : On the day when the new pack of the previous COC would have been started Transdermal patch On the day when next application would have been scheduled Vaginal ring On the day when next insertion would have been scheduled Injection On the day when next injection would have been scheduled Intrauterine contraceptive On the day of removal Implant On the day of removal Starting Portia ® after Abortion or Miscarriage First-trimester After a first-trimester abortion or miscarriage, Portia ® may be started immediately.
An additional method of contraception is not needed if Portia ® is started immediately. If Portia ® is not started within 5 days after termination of the pregnancy, the patient should use additional non-hormonal contraception (such as condoms or spermicide) for the first seven days of her first cycle of Portia ® . Second-trimester Do not start until 4 weeks after a second-trimester abortion or miscarriage, due to the increased risk of thromboembolic disease.
Start Portia ® following the instructions in Table 3 for Day 1 or Sunday start. Use additional non-hormonal contraception (such as condoms or spermicide) for the first seven days of the patient’s first cycle of Portia ® (see CONTRAINDICATIONS , WARNINGS (1) , PRECAUTIONS (10) and FDA-APPROVED PATIENT LABELING ) . Starting Portia ® after Childbirth Do not start until 4 weeks after delivery, due to the increased risk of thromboembolic disease.
Start contraceptive therapy with Portia ® following the instructions in Table 3 for women not currently using hormonal contraception. Portia ® is not recommended for use in lactating women (see PRECAUTIONS (7) and FDA-APPROVED PATIENT LABELING ). If the woman has not yet had a period postpartum, consider the possibility of ovulation and conception occurring prior to use of Portia ® (see CONTRAINDICATIONS , WARNINGS (9) , PRECAUTIONS (6) and FDA-APPROVED PATIENT LABELING ) .
2. Dosing Portia ® Instruct patients to take one tablet by mouth at the same time every day. To achieve maximum contraceptive effectiveness, patients must take Portia ® as directed, in the order directed on the blister pack.
The failure rate may increase when pills are missed or taken incorrectly. 3. Missed doses Instruct patients about the handling of missed doses (e.g., to take single missed pills as soon as possible) and to follow the dosing instructions provided in the FDA-approved patient labeling.
Table 4: Instructions for Missed Portia® Tablets If one active tablet is missed in Weeks 1, 2, or 3 Take the tablet as soon as possible. Continue taking one tablet a day until the pack is finished. If two active tablets are missed in Week 1 or Week 2 Take the two missed tablets as soon as possible and the next two active tablets the next day.
Continue tak… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Portia ® (levonorgestrel and ethinyl estradiol tablets USP) is contraindicated in females who are known to have the following conditions: A high risk of arterial or venous thrombotic diseases. Examples include women who are known to: Smoke, if over age 35 [see BOXED WARNING and WARNINGS (1) ]. Have current or history of deep vein thrombosis or pulmonary embolism [see WARNINGS (1) ] .
Have cerebrovascular disease [see WARNINGS (1) ] . Have coronary artery disease [see WARNINGS (1) ] . Have thrombogenic valvular or thrombogenic rhythm diseases of the heart (for example, subacute bacterial endocarditis with valvular disease, or atrial fibrillation) [see WARNINGS (1) ] .
Have inherited or acquired hypercoagulopathies [see WARNINGS (1) ] . Have uncontrolled hypertension or hypertension with vascular disease [see WARNINGS (3) ] . Have diabetes mellitus and are over age 35, diabetes mellitus with hypertension or vascular disease or other end-organ damage, or diabetes mellitus of >20 years duration [see WARNINGS (7) ] .
Have headaches with focal neurological symptoms, migraine headaches with aura, or over age 35 with any migraine headaches [see WARNINGS (8) ] . Current diagnosis of, or history of, breast cancer, which may be hormone-sensitive. Liver tumors, acute viral hepatitis, or severe (decompensated) cirrhosis [see WARNINGS (2) ] .
Use of Hepatitis C drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir, due to the potential for ALT elevations [see WARNINGS (5) ] . Undiagnosed abnormal uterine bleeding [see WARNINGS (9) ] .
⚠️ Warnings ▾
WARNINGS 1. Thromboembolic Disorders and Other Vascular Conditions Stop levonorgestrel and ethinyl estradiol tablets if an arterial or venous thrombotic/thromboembolic event occurs. Stop levonorgestrel and ethinyl estradiol tablets if there is unexplained loss of vision, proptosis, diplopia, papilledema, or retinal vascular lesions and evaluate for retinal vein thrombosis immediately.
Discontinue levonorgestrel and ethinyl estradiol tablets during prolonged immobilization. If feasible, stop levonorgestrel and ethinyl estradiol tablets at least four weeks before and through two weeks after major surgery, or other surgeries known to have an elevated risk of thromboembolism. Start levonorgestrel and ethinyl estradiol tablets no earlier than four weeks after delivery in females who are not breast-feeding.
The risk of postpartum thromboembolism decreases after the third postpartum week, whereas the likelihood of ovulation increases after the third postpartum week. Before starting levonorgestrel and ethinyl estradiol tablets evaluate any past medical history or family history of thrombotic or thromboembolic disorders and consider whether the history suggests an inherited or acquired hypercoagulopathy. Levonorgestrel and ethinyl estradiol tablets are contraindicated in females with a high risk of arterial or venous thrombotic/thromboembolic diseases (see CONTRAINDICATIONS ).
Arterial Events COCs increase the risk of cardiovascular events and cerebrovascular events, such as myocardial infarction and stroke. The risk is greater among older women (> 35 years of age), smokers, and females with hypertension, dyslipidemia, diabetes, or obesity. Levonorgestrel and ethinyl estradiol tablets are contraindicated in women over 35 years of age who smoke (see CONTRAINDICATIONS ).
Cigarette smoking increases the risk of serious cardiovascular events from COC use. This risk increases with age, particularly in women over 35 years of age, and with the number of cigarettes smoked. Venous Events Use of COCs increases the risk of venous thromboembolic events (VTEs), such as deep vein thrombosis and pulmonary embolism.
Risk factors for VTEs include smoking, obesity, and family history of VTE, in addition to other factors that contraindicate use of COCs (see CONTRAINDICATIONS ). While the increased risk of VTE associated with use of COCs is well-established, the rates of VTE are even greater during pregnancy, and especially during the postpartum period (see Figure 1). The rate of VTE in females using COCs has been estimated to be 3 to 9 cases per 10,000 woman-years.
The risk of VTE is highest during the first year of use of a COC and when restarting hormonal contraception after a break of four weeks or longer. Based on results from a few studies, there is some evidence that this is true for non-oral products as well. The risk of thromboembolic disease due to COCs gradually disappears after COC use is discontinued.
Figure 1 shows the risk of developing a VTE for females who are not pregnant and do not use oral contraceptives, for females who use oral contraceptives, for pregnant females, and for females in the postpartum period. To put the risk of developing a VTE into perspective: If 10,000 females who are not pregnant and do not use oral contraceptives are followed for one year, between 1 and 5 of these females will develop a VTE. Figure 1: Likelihood of Developing a VTE 1 2.
Liver Disease Elevated Liver Enzymes Levonorgestrel and ethinyl estradiol tablets are contraindicated in females with acute viral hepatitis or severe (decompensated) cirrhosis of liver (see CONTRAINDICATIONS ). Discontinue levonorgestrel and ethinyl estradiol tablets if jaundice develops. Acute liver test abnormalities may necessitate the discontinuation of COC use until the liver tests return to normal and COC causation has been excluded.
Liver Tumors Levonorgestrel and ethinyl estradiol tablets are contraindicated in females with benign or malignant liver tumors (see CONTRAINDICAT… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The following serious adverse reactions with the use of COCs are discussed elsewhere in the labeling: Serious cardiovascular adverse events [see BOXED WARNING and WARNINGS (1) ] Vascular events [see WARNINGS (1) ] Liver disease [see WARNINGS (2) ] Hypertension [see WARNINGS (3) ] Gallbladder disease [see WARNINGS (6) ] Carbohydrate and lipid effects [see WARNINGS (7) ] Headache [see WARNINGS (8) ] Carcinoma of the cervix [see WARNINGS (11) ] Adverse reactions reported by COC users and described elsewhere in the labeling are: Bleeding irregularities and amenorrhea [see WARNINGS (9) ] Mood changes, including depression [see WARNINGS (10) ] Melasma/chloasma which may persist [see WARNINGS (14) ] Edema/fluid retention [see PRECAUTIONS (2) ] Diminution in lactation when given immediately postpartum [see PRECAUTIONS (7) ] Post Marketing Experience Five studies that compared breast cancer risk between ever-users (current or past use) of COCs and never-users of COCs reported no association between ever use of COCs and breast cancer risk, with effect estimates ranging from 0.90 to 1.12 (Figure 2).
Three studies compared breast cancer risk between current or recent COC users (<6 months since last use) and never users of COCs (Figure 2). One of these studies reported no association between breast cancer risk and COC use. The other two studies found an increased relative risk of 1.19 to 1.33 with current or recent use.
Both of these studies found an increased risk of breast cancer with current use of longer duration, with relative risks ranging from 1.03 with less than one year of COC use to approximately 1.4 with more than 8 to 10 years of COC use. Figure 2: Relevant Studies of Risk of Breast Cancer with Combined Oral Contraceptives RR = relative risk; OR = odds ratio; HR = hazard ratio. “ever COC” are females with current or past COC use; “never COC use” are females that never used COCs. The following adverse reactions have been reported in patients receiving oral contraceptives and are believed to be drug-related: Breast tenderness, pain, enlargement, secretion; Nausea, vomiting and gastrointestinal symptoms (such as abdominal pain, cramps and bloating); Change in menstrual flow; Temporary infertility after discontinuation of treatment; Change in weight or appetite (increase or decrease); Change in cervical erosion and secretion; Cholestatic jaundice; Rash (allergic); Vaginitis, including candidiasis; Change in corneal curvature (steepening); Intolerance to contact lenses; Mesenteric thrombosis; Decrease in serum folate levels; Exacerbation of systemic lupus erythematosus; Exacerbation of porphyria; Exacerbation of chorea; Aggravation of varicose veins; Anaphylactic/anaphylactoid reactions, including urticaria, angioedema, and severe reactions with respiratory and circulatory symptoms.
The following adverse reactions have been reported in users of oral contraceptives, and the association has been neither confirmed nor refuted: Congenital anomalies; Premenstrual syndrome; Cataracts; Optic neuritis, which may lead to partial or complete loss of vision; Cystitis-like syndrome; Nervousness; Dizziness; Hirsutism; Loss of scalp hair; Erythema multiforme; Erythema nodosum; Hemorrhagic eruption; Impaired renal function; Hemolytic uremic syndrome; Budd-Chiari syndrome; Acne; Changes in libido; Colitis; Sickle-cell disease; Cerebral-vascular disease with mitral valve prolapse; Lupus-like syndromes; Pancreatitis; Dysmenorrhea.
To report SUSPECTED ADVERSE REACTIONS, contact Teva at 1-888-838-2872 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch. figure-2
🔄 Drug Interactions ▾
4. Drug Interactions The sections below provide information on substances for which data on drug interactions with COCs are available. There is little information available about the clinical effect of most drug interactions that may affect COCs.
However, based on the known pharmacokinetic effects of these drugs, clinical strategies to minimize any potential adverse effect on contraceptive effectiveness or safety are suggested. Consult the approved product labeling of all concurrently used drugs to obtain further information about interactions with COCs or the potential for metabolic enzyme or transporter system alterations . No drug-drug interaction studies were conducted with levonorgestrel and ethinyl estradiol tablets.
4.1Effects of Other Drugs on Combined Oral Contraceptives Substances Decreasing the Plasma Concentrations of COCs and Potentially Diminishing the Efficacy of COCs: Table 1 includes substances that demonstrated an important drug interaction with levonorgestrel and ethinyl estradiol tablets. Table 1: Significant Drug Interactions Involving Substances That Affect COCs Metabolic Enzyme Inducers Clinical effect Concomitant use of COCs with metabolic enzyme inducers may decrease the plasma concentrations of the estrogen and/or progestin component of COCs.
Decreased exposure of the estrogen and/or progestin component of COCs may potentially diminish the effectiveness of COCs and may lead to contraceptive failure or an increase in breakthrough bleeding. Prevention or management Counsel females to use an alternative method of contraception or a backup method when enzyme inducers are used with COCs. Continue backup contraception for 28 days after discontinuing the enzyme inducer to maintain contraceptive reliability.
Examples Aprepitant, barbiturates, bosentan, carbamazepine, efavirenz, felbamate, griseofulvin, oxcarbazepine, phenytoin, rifampin, rifabutin, rufinamide, topiramate, products containing St. John’s wort a , and certain protease inhibitors (see separate section on protease inhibitors below). Colesevelam Clinical effect Concomitant use of COCs with colesevelam significantly decreases systemic exposure of ethinyl estradiol.
Decreased exposure of the estrogen component of COCs may potentially reduce contraceptive efficacy or result in an increase in breakthrough bleeding, depending on the strength of ethinyl estradiol in the COC. Prevention or management Administer 4 or more hours apart to attenuate this drug interaction. a Induction potency of St. John’s wort may vary widely based on preparation.
Substances increasing the systemic exposure of COCs: Co-administration of atorvastatin or rosuvastatin and COCs containing ethinyl estradiol increase systemic exposure of ethinyl estradiol by approximately 20 to 25 percent. Ascorbic acid and acetaminophen may increase systemic exposure of ethinyl estradiol, possibly by inhibition of conjugation. CYP3A inhibitors such as itraconazole, voriconazole, fluconazole, grapefruit juice, 7 or ketoconazole may increase systemic exposure of the estrogen and/or progestin component of COCs.
Human immunodeficiency virus (HIV)/hepatitis C virus (HCV) protease inhibitors and non-nucleoside reverse transcriptase inhibitors: Significant decreases in systemic exposure of the estrogen and/or progestin have been noted when COCs are co-administered with some HIV protease inhibitors (e.g., nelfinavir, ritonavir, darunavir/ritonavir, (fos) amprenavir/ritonavir, lopinavir/ritonavir, and tipranavir/ritonavir), some HCV protease inhibitors (e.g., boceprevir and telaprevir), and some non-nucleoside reverse transcriptase inhibitors (e.g., nevirapine).
In contrast, significant increases in systemic exposure of the estrogen and/or progestin have been noted when COCs are co-administered with certain other HIV protease inhibitors (e.g., indinavir and atazanavir/ritonavir) and with other non-nucleoside reverse transcriptase inhibitors (e.g., etravirine).
4.2Effects of Combined Oral Contraceptives o… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
6. Pregnancy Risk Summary Discontinue levonorgestrel and ethinyl estradiol tablets if pregnancy occurs because there is no reason to use COCs in pregnancy. Epidemiologic studies and meta-analyses have not found an increased risk of genital or nongenital birth defects (including cardiac anomalies and limb-reduction defects) following exposure to COCs before conception or during early pregnancy.
Animal studies to evaluate embryo/fetal toxicity were not conducted. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4 percent and 15 to 20 percent, respectively.
🧒 Pediatric Use ▾
8. Pediatric Use Safety and efficacy of levonorgestrel and ethinyl estradiol tablets have been established in females of reproductive potential. Use of levonorgestrel and ethinyl estradiol tablets before menarche is not indicated.
🆘 Overdosage ▾
OVERDOSAGE There have been no reports of serious adverse outcomes from overdose of COCs, including ingestion by children. Overdose may cause uterine bleeding in females and nausea.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Combination oral contraceptives prevent pregnancy primarily by suppressing ovulation.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED/STORAGE AND HANDLING Portia ® (levonorgestrel and ethinyl estradiol tablets USP, 0.15 mg/ 0.03 mg) 28 tablets are packaged in cartons of six blister cards (NDC 0555-9020-58), each card containing 28 tablets: 21 Active Tablets: Pink, round, film-coated, biconvex, unscored active tablets, debossed with stylized b on one side and 992 on the other side. 7 Inert Tablets: White, round, biconvex, unscored inert tablets, debossed with stylized b on one side and 208 on the other side. Store at 20º to 25°C (68° to 77º F) (See USP Controlled Room Temperature).
Keep this and all medications out of the reach of children. Teva Pharmaceuticals USA, Inc. North Wales, PA 19454 Rev.
H 3/2025
📋 Description ▾
DESCRIPTION Portia ® (levonorgestrel and ethinyl estradiol tablets USP) is a combination oral contraceptive (COC) consisting of 21 pink active tablets, each containing 0.15 mg of levonorgestrel, USP, a synthetic progestin and 30 mcg of ethinyl estradiol, USP, an estrogen, and 7 white inert tablets (without hormones). The structural formulas for the active components are: Levonorgestrel, USP C 21 H 28 O 2 M.W. 312.45 Levonorgestrel, USP is chemically 18,19-Dinorpregn-4-en-20-yn-3-one, 13-ethyl-17-hydroxy-,(17α)-(-)-.
Ethinyl Estradiol, USP C 20 H 24 O 2 M.W. 296.40 Ethinyl Estradiol, USP is 19-nor-17α-pregna-1,3,5(10)-trien-20-yne-3, 17-diol. Each pink active tablet contains the following inactive ingredients: anhydrous lactose, hypromellose, magnesium stearate, and microcrystalline cellulose.
The ingredients in the film-coating include FD&C Blue No. 1 Aluminum Lake, FD&C Red No. 40 Aluminum Lake, hypromellose, polyethylene glycol, polysorbate 80, and titanium dioxide.
Each white inert tablet contains the following inactive ingredients: anhydrous lactose, hypromellose, magnesium stearate, and microcrystalline cellulose. Levonorgestrel Structure Ethinyl Estradiol Structure
⚠️ Precautions ▾
PRECAUTIONS 1. Lipid Disorders Women who are being treated for hyperlipidemias should be followed closely if they elect to use oral contraceptives. Some progestogens may elevate LDL levels and may render the control of hyperlipidemias more difficult [see WARNINGS (7) ].
In patients with familial defects of lipoprotein metabolism receiving estrogen-containing preparations, there have been case reports of significant elevations of plasma triglycerides leading to pancreatitis. 2. Fluid Retention Oral contraceptives may cause some degree of fluid retention.
They should be prescribed with caution, and only with careful monitoring, in patients with conditions which might be aggravated by fluid retention. 3. Gastrointestinal Motility Diarrhea and/or vomiting may reduce hormone absorption (see DOSAGE AND ADMINISTRATION ).
4. Drug Interactions The sections below provide information on substances for which data on drug interactions with COCs are available. There is little information available about the clinical effect of most drug interactions that may affect COCs.
However, based on the known pharmacokinetic effects of these drugs, clinical strategies to minimize any potential adverse effect on contraceptive effectiveness or safety are suggested. Consult the approved product labeling of all concurrently used drugs to obtain further information about interactions with COCs or the potential for metabolic enzyme or transporter system alterations . No drug-drug interaction studies were conducted with levonorgestrel and ethinyl estradiol tablets.
4.1Effects of Other Drugs on Combined Oral Contraceptives Substances Decreasing the Plasma Concentrations of COCs and Potentially Diminishing the Efficacy of COCs: Table 1 includes substances that demonstrated an important drug interaction with levonorgestrel and ethinyl estradiol tablets. Table 1: Significant Drug Interactions Involving Substances That Affect COCs Metabolic Enzyme Inducers Clinical effect Concomitant use of COCs with metabolic enzyme inducers may decrease the plasma concentrations of the estrogen and/or progestin component of COCs.
Decreased exposure of the estrogen and/or progestin component of COCs may potentially diminish the effectiveness of COCs and may lead to contraceptive failure or an increase in breakthrough bleeding. Prevention or management Counsel females to use an alternative method of contraception or a backup method when enzyme inducers are used with COCs. Continue backup contraception for 28 days after discontinuing the enzyme inducer to maintain contraceptive reliability.
Examples Aprepitant, barbiturates, bosentan, carbamazepine, efavirenz, felbamate, griseofulvin, oxcarbazepine, phenytoin, rifampin, rifabutin, rufinamide, topiramate, products containing St. John’s wort a , and certain protease inhibitors (see separate section on protease inhibitors below). Colesevelam Clinical effect Concomitant use of COCs with colesevelam significantly decreases systemic exposure of ethinyl estradiol.
Decreased exposure of the estrogen component of COCs may potentially reduce contraceptive efficacy or result in an increase in breakthrough bleeding, depending on the strength of ethinyl estradiol in the COC. Prevention or management Administer 4 or more hours apart to attenuate this drug interaction. a Induction potency of St. John’s wort may vary widely based on preparation.
Substances increasing the systemic exposure of COCs: Co-administration of atorvastatin or rosuvastatin and COCs containing ethinyl estradiol increase systemic exposure of ethinyl estradiol by approximately 20 to 25 percent. Ascorbic acid and acetaminophen may increase systemic exposure of ethinyl estradiol, possibly by inhibition of conjugation. CYP3A inhibitors such as itraconazole, voriconazole, fluconazole, grapefruit juice, 7 or ketoconazole may increase systemic exposure of the estrogen and/or progestin component of COCs.
Human immunodeficiency virus (HIV)/hepatitis C virus (HCV) protease inhibitors… [Excerpted — this section continues on DailyMed.]
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
5. Carcinogenesis See WARNINGS (11) .
📄 Patient Package Insert ▾
PATIENT INFORMATION Portia ® (levonorgestrel and ethinyl estradiol tablets) What is the most important information I should know about Portia ® ? Do not use Portia ® if you smoke cigarettes and are over 35 years old. Smoking increases your risk of serious cardiovascular side effects from hormonal birth control pills, including death from heart attack, blood clots or stroke.
This risk increases with age and the number of cigarettes you smoke. What is Portia ® ? Portia ® is a birth control pill (oral contraceptive) used by women to prevent pregnancy.
How does Portia ® work for contraception? Your chance of getting pregnant depends on how well you follow the directions for taking your birth control pills. The better you follow the directions, the less chance you have of getting pregnant.
Based on the results of clinical studies, about 1 to 5 out of 100 women may get pregnant during the first year they use Portia ® . The following chart shows the chance of getting pregnant for women who use different methods of birth control. Each box on the chart contains a list of birth control methods that are similar in effectiveness.
The most effective methods are at the top of the chart. The box on the bottom of the chart shows the chance of getting pregnant for women who do not use birth control and are trying to get pregnant. Who should not take Portia ® ?
Do not take Portia ® if you: smoke and are over 35 years of age had blood clots in your arms, legs, lungs, or eyes had a problem with your blood that makes it clot more than normal have certain heart valve problems or irregular heart beat had a stroke had a heart attack have high blood pressure that cannot be controlled by medicine have diabetes with kidney, eye, nerve, or blood vessel damage have certain kinds of severe migraine headaches with aura, numbness, weakness or changes in vision, or any migraine headaches if you are over 35 years of age had breast cancer or any cancer that is sensitive to female hormones have liver problems, including liver tumors have any unexplained vaginal bleeding are pregnant take any Hepatitis C drug combination containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir.
This may increase levels of the liver enzyme “alanine aminotransferase” (ALT) in the blood. If any of these conditions happen while you are taking Portia ® , stop taking Portia ® right away and talk to your healthcare provider. Use non-hormonal contraception when you stop taking Portia ® .
What should I tell my healthcare provider before taking Portia ® ? Tell your healthcare provider if you: are pregnant or think you may be pregnant are depressed now or have been depressed in the past had yellowing of your skin or eyes (jaundice) caused by pregnancy (cholestasis of pregnancy) are breastfeeding or plan to breastfeed. Portia ® may decrease the amount of breast milk you make.
A small amount of the hormones in Portia ® may pass into your breast milk. Talk to your healthcare provider about the best birth control method for you while breastfeeding. Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins and herbal supplements.
Portia ® may affect the way other medicines work, and other medicines may affect how well Portia ® works. Know the medicines you take. Keep a list of them to show your healthcare provider and pharmacist when you get a new medicine.
How should I take Portia ® ? Read the Instructions for Use at the end of this Patient Information. What are the possible serious side effects of Portia ® ?
Like pregnancy, Portia ® may cause serious side effects, including blood clots in your lungs, heart attack, or a stroke that may lead to death. Some other examples of serious blood clots include blood clots in the legs or eyes. Serious blood clots can happen especially if you smoke, are obese, or are older than 35 years of age.
Serious blood clots are more likely to happen when you: first start taking birt… [Excerpted — this section continues on DailyMed.]
📖 Instructions for Use ▾
INSTRUCTIONS FOR USE Portia ® (levonorgestrel and ethinyl estradiol tablets) Important Information about taking Portia ® Take 1 pill every day at the same time. Take the pills in the order directed on your pill pack. Do not skip your pills, even if you do not have sex often.
If you miss pills (including starting the pack late) you could get pregnant . The more pills you miss, the more likely you are to get pregnant. If you have trouble remembering to take Portia ® , talk to your healthcare provider.
When you first start taking Portia ® , spotting or light bleeding in between your periods may occur. Contact your healthcare provider if this does not go away after a few months. You may feel sick to your stomach (nauseous), especially during the first few months of taking Portia ® .
If you feel sick to your stomach, do not stop taking the pill. The problem will usually go away. If your nausea does not go away, call your healthcare provider.
Missing pills can also cause spotting or light bleeding, even when you take the missed pills later. On the days you take 2 pills to make up for missed pills (see What should I do if I miss any Portia ® pills? below), you could also feel a little sick to your stomach. It is not uncommon to miss a period.
However, if you miss a period and have not taken Portia ® according to directions, or feel like you may be pregnant, call your healthcare provider. If you have a positive pregnancy test, you should stop taking Portia ® . If you have vomiting or diarrhea within 3 to 4 hours of taking a pink pill, take another pink pill as soon as possible.
Continue taking all your remaining pills in order. Start the first pill of your next pill pack the day after finishing your current pill pack. This will be 1 day earlier than originally scheduled.
Continue on your new schedule. If you have vomiting or diarrhea for more than 1 day, your birth control pills may not work as well. Use an additional birth control method, like condoms or spermicide, until you check with your healthcare provider.
Stop taking Portia ® at least 4 weeks before you have major surgery and do not restart after the surgery without asking your healthcare provider. Be sure to use other forms of contraception (like condoms or spermicide) during this time period. Before you start taking Portia ® : Decide what time of day you want to take your pill.
It is important to take it at the same time every day and in the order as directed on your pill pack. Look at your pill pack. Your pill pack consists of 1 card that holds 28 individually sealed pills.
The 28 pills consist of 21 pink pills (3 rows of 7 pills) and 7 white pills (1 row of 7 pills). See Figure A . Figure A Also find: Where on the card to start taking pills (upper left corner) and In what order to take the pills (follow the weeks) Be sure you have ready at all times another kind of birth control (such as condoms or spermicide), to use as a back-up in case you miss pills.
When should I start taking Portia ® ? If you start taking Portia ® and you have not used a hormonal birth control method before: There are 2 ways to start taking your birth control pills. You can either start on a Sunday (Sunday Start) or on the first day (Day 1) of your natural menstrual period (Day 1 Start).
Your healthcare provider should tell you when to start taking your birth control pill. If you use the Sunday Start, use non-hormonal back-up contraception such as condoms or spermicide for the first 7 days that you take Portia ® . You do not need back-up contraception if you use the Day 1 Start.
If you start taking Portia ® and you are switching from another birth control pill: Start your new Portia ® pack on the same day that you would start the next pack of your previous birth control method. Do not continue taking the pills from your previous birth control pill pack. If you start taking Portia ® and previously used a vaginal ring: Start using Portia ® on the day you would have started the next ring.
If you start t… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
Package/Label Display Panel NDC 0555-9020-58 6 Blister Cards, 28 Tablets Each Portia ® (levonorgestrel and ethinyl estradiol tablets USP) 0.15 mg/0.03 mg Contains 6 blister cards, each containing 28 tablets. Twenty-one pink tablets, each containing 0.15 mg levonorgestrel, USP with 0.03 mg ethinyl estradiol, USP and seven white inert tablets. Rx only SHAPING WOMEN’S HEALTH ® 1 2
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Where does this data come from?
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |