
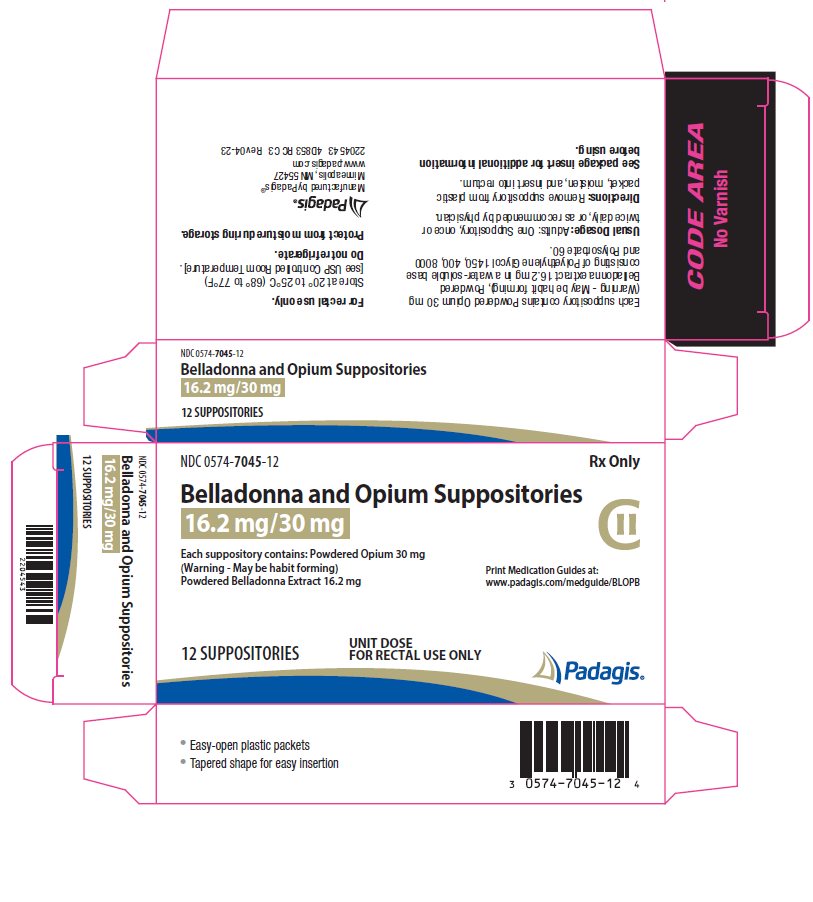
Belladonna and Opium 16.2 mg; 30 mg Suppository, 12 suppositories — NDC 0574-7045-12 (Billing 00574-7045-12)
This is a package of 12 suppositories of Belladonna and Opium 16.2 mg; 30 mg Suppository from Padagis US LLC, marketed since May 1994 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 0574-7045-12 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0574 labeler · 7045 product · 12 package
- Package marketed since
- May 1, 1994
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 12 EA per package
- Barcode (UPC-A, from the NDC)
- 3 0574704512 4
- FDA record last changed
- Oct 1, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 004257
- GCN: 70741
- GPI-14 (Medi-Span): 49109902155210
- HICL (First Databank): 001758
- AHFS class code: 28:08.08.00
- RxCUI (RxNorm): 312104
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
Clinical
This is a rectal suppository containing belladonna alkaloids and opium powder. Belladonna is an anticholinergic agent typically used to reduce muscle spasms and secretions, while opium is an opioid commonly used for pain relief and to slow intestinal movement. This combination product is marketed as an unapproved drug and is not supported by an approved FDA application.
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 4, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00574-7045-04 0574-7045-04 Main listing | 4 PACKET in 1 BOX / 1 SUPPOSITORY in 1 PACKET | 2018-08-22 | — | Active |
| 00574-7045-12 You're viewing this | 12 PACKET in 1 BOX / 1 SUPPOSITORY in 1 PACKET | 1994-05-01 | — | Active |
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 00574-7045-04?
What NDC number is used to bill for this package of Belladonna and Opium 16.2 mg; 30 mg Suppository?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Belladonna and Opium 16.2 mg/1; 30 mgthis 00574-7045-12 | Padagis | 12 suppositories | — | — | FDA listed | — |
| Belladonna and Opium 16.2 mg/1; 30 mg 63629-8436-01 | Bryant | 4 suppositories | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OJ4Z5Z32L4
A synthetic polymer made by linking ethylene glycol units together. It serves as a solvent, humectant to retain moisture, and film-forming agent in tablets and coatings to improve texture and drug delivery.
-
UNII B697894SGQ
Polyethylene glycol 400 is a clear, thick liquid made from petroleum-derived polymers. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII Q662QK8M3B
Polyethylene glycol 8000 is a synthetic polymer made from ethylene oxide. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and add bulk to the medicine.
-
UNII CAL22UVI4M
A synthetic emulsifier derived from sorbitol and fatty acids. It helps mix oil and water-based ingredients together and improves the texture and stability of the medicine.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Padagis US LLC labeler code 00574
- BRINZOLAMIDE 10 mg/mL Suspension/ Drops NDC 0574-4012-10
- TOBRAMYCIN AND DEXAMETHASONE 3 mg/mL; 1 mg/mL Suspension/ Drops NDC 0574-4031-05
- LOTEPREDNOL ETABONATE 2 mg/mL Suspension/ Drops NDC 0574-4080-05
- LOTEPREDNOL ETABONATE 5 mg/mL Suspension/ Drops NDC 0574-4135-05
- aspirin 300 mg Suppository NDC 0574-7034-12
- Belladonna and Opium 16.2 mg; 60 mg Suppository NDC 0574-7040-04
- Bisacodyl 10 mg Suppository NDC 0574-7050-12
- Hydrocortisone Acetate 25 mg Suppository NDC 0574-7090-12
- Hydrocortisone Acetate 30 mg Suppository NDC 0574-7093-12
- Morphine Sulfate 5 mg Suppository NDC 0574-7110-12
- Morphine Sulfate 10 mg Suppository NDC 0574-7112-12
- Morphine Sulfate 20 mg Suppository NDC 0574-7114-12
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: ADDICTION, ABUSE, AND MISUSE; LIFE-THREATENING RESPIRATORY DEPRESSION; ACCIDENTAL EXPOSURE; NEONATAL OPIOID WITHDRAWAL SYNDROME; and RISKS FROM CONCOMITANT USE WITH BENZODIAZEPINES OR OTHER CNS DEPRESSANTS Addiction, Abuse, and Misuse Belladonna and opium suppositories expose patients and other users to the risks of opioid addiction, abuse, and misuse, which can lead to overdose and death. Assess each patient’s risk prior to prescribing belladonna and opium suppositories, and monitor all patients regularly for the development of these behaviors or conditions [see Warnings and Precautions ( 5.1 )] .
Life-Threatening Respiratory Depression Serious, life-threatening, or fatal respiratory depression may occur with use of belladonna and opium suppositories. Monitor for respiratory depression, especially during initiation of belladonna and opium suppositories or following a dose increase [see Warnings and Precautions ( 5.2 )] . Accidental Exposure Accidental exposure of even one dose of belladonna and opium suppositories, especially by children, can result in a fatal overdose of opium [see Warnings and Precautions ( 5.2 )] .
Neonatal Opioid Withdrawal Syndrome Prolonged use of belladonna and opium suppositories during pregnancy can result in neonatal opioid withdrawal syndrome, which may be life-threatening if not recognized and treated, and requires management according to protocols developed by neonatology experts. If opioid use is required for a prolonged period in a pregnant woman, advise the patient of the risk of neonatal opioid withdrawal syndrome and ensure that appropriate treatment will be available [see Warnings and Precautions ( 5.3 )] .
Risks From Concomitant Use With Benzodiazepines Or Other CNS Depressants Concomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death [see Warnings and Precautions ( 5.4 ), Drug Interactions ( 7 )] . • Reserve concomitant prescribing of belladonna and opium suppositories and benzodiazepines or other CNS depressants for use in patients for whom alternative treatment options are inadequate. • Limit dosages and durations to the minimum required. • Follow patients for signs and symptoms of respiratory depression and sedation.
WARNING: ADDICTION, ABUSE, AND MISUSE; LIFE-THREATENING RESPIRATORY DEPRESSION; ACCIDENTAL EXPOSURE; NEONATAL OPIOID WITHDRAWAL SYNDROME; and RISKS FROM CONCOMITANT USE WITH BENZODIAZEPINES OR OTHER CNS DEPRESSANTS See full prescribing information for complete boxed warning. • Belladonna and opium suppositories expose users to risks of opioid addiction, abuse, and misuse, which can lead to overdose and death. Assess patient’s risk before prescribing and monitor regularly for these behaviors or conditions. ( 5.1 ) • Serious, life-threatening, or fatal respiratory depression may occur.
Monitor closely, especially upon initiation or following a dose increase. ( 5.2 ) • Accidental exposure of belladonna and opium suppositories, especially by children, can result in a fatal overdose of opium. ( 5.2 ) • Prolonged use of belladonna and opium suppositories during pregnancy can result in neonatal opioid withdrawal syndrome, which may be life-threatening if not recognized and treated.
If prolonged opioid use is required in a pregnant woman, advise the patient of the risk of neonatal opioid withdrawal syndrome and ensure that appropriate treatment will be available. ( 5.3 ) • Concomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing for use in patients for whom alternative treatment options are inadequate; limit dosages and durations to the minimum required; and follow patients for signs and symptoms of respiratory depression and sedation.
( 5.4 , 7 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Belladonna and opium suppositories are indicated for the management of ureteral spasm pain severe enough to require an opioid analgesic and for which alternative treatments are inadequate. Limitations of Use Because of the risks of addiction, abuse, and misuse with opioids, even at recommended doses [see Warnings and Precautions ( 5.1 )] , reserve belladonna and opium suppositories for use in patients for whom alternative treatment options [e.g., non-opioid analgesics or opioid combination products]: • Have not been tolerated, or are not expected to be tolerated, • Have not provided adequate analgesia, or are not expected to provide adequate analgesia Belladonna and opium suppositories are an opioid agonist indicated for the management of ureteral spasm pain severe enough to require an opioid analgesic and for which alternative treatments are inadequate.
( 1 ) Limitations of Use ( 1 ) Because of the risks of addiction, abuse, and misuse with opioids, even at recommended doses, reserve belladonna and opium suppositories for use in patients for whom alternative treatment options (e.g., non-opioid analgesics or opioid combination products): • Have not been tolerated, or are not expected to be tolerated, • Have not provided adequate analgesia, or are not expected to provide adequate analgesia
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Use the lowest effective dosage for the shortest duration consistent with individual patient treatment goals. ( 2.1 ) • Individualize dosing based on the severity of pain, patient response, and prior analgesic experience, and risk factor for addiction, abuse, and misuse. ( 2.1 ) • Discuss availability of naloxone with the patient and caregiver and assess each patient's need for access to naloxone, both when initiating and renewing treatment with belladonna and opium suppositories.
Consider prescribing naloxone based on the patient's risk factors for overdose. ( 2.2 , 5.1 , 5.2 , 5.4 ) • Initiate dosing with one suppository once or twice daily as needed for pain. ( 2.3 ) • Do not abruptly discontinue belladonna and opium suppositories in a physically-dependent patient because rapid discontinuation of opioid analgesics has resulted in serious withdrawal symptoms, uncontrolled pain, and suicide.
( 2.5 )
2.1Important Dosage and Administration Instructions Use the lowest effective dosage for the shortest duration consistent with individual patient treatment goals [see Warnings and Precautions ( 5 )] . Initiate the dosing regimen for each patient individually, taking into account the patient's severity of pain, patient response, prior analgesic treatment experience, and risk factors for addiction, abuse, and misuse [see Warnings and Precautions ( 5.1 )] . Monitor patients closely for respiratory depression, especially within the first 24-72 hours of initiating therapy and following dosage increases with belladonna and opium suppositories and adjust the dosage accordingly [see Warnings and Precautions ( 5.2 )] .
2.2Patient Access to Naloxone for the Emergency Treatment of Opioid Overdose Discuss the availability of naloxone for the emergency treatment of opioid overdose with the patient and caregiver and assess the potential need for access to naloxone, both when initiating and renewing treatment with belladonna and opium suppositories [see Warnings and Precautions ( 5.2 ), Patient Counseling Information ( 17 )] . Inform patients and caregivers about the various ways to obtain naloxone as permitted by individual state naloxone dispensing and prescribing requirements or guidelines (e.g., by prescription, directly from a pharmacist, or as part of a community-based program).
Consider prescribing naloxone, based on the patient's risk factors for overdose, such as concomitant use of CNS depressants, a history of opioid use disorder, or prior opioid overdose. The presence of risk factors for overdose should not prevent the proper management of pain in any given patient [see Warnings and Precautions ( 5.1 , 5.2 , 5.4 )] . Consider prescribing naloxone if the patient has household members (including children) or other close contacts at risk for accidental ingestion or overdose.
2.3Dosing One belladonna and opium suppository rectally once or twice daily, not to exceed four doses daily or as recommended by the physician. Moisten finger and suppository with water before inserting. Absorption is dependent on body hydration and not on body temperature.
Not recommended for use in children 12 years of age and under. Conversion from Other Opioids to Belladonna and Opium Suppositories There is inter-patient variability in the potency of opioid drugs and opioid formulations. Therefore, a conservative approach is advised when determining the total daily dosage of belladonna and opium suppositories.
It is safer to underestimate a patient’s 24-hour belladonna and opium suppositories dosage than to overestimate the 24-hour belladonna and opium suppositories dosage and manage an adverse reaction due to overdose. Conversion from Belladonna and Opium suppositories to Extended-Release Opioid The relative bioavailability of belladonna and opium suppositories compared to extended-release opioid is unknown, so conversion to extended-release drug product must be accompanied by close observation for signs of excessive sedation and… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Belladonna and Opium Suppositories are available in two strengths. • Belladonna 16.2 mg and opium 30 mg • Belladonna 16.2 mg and opium 60 mg Suppositories: • Belladonna 16.2 mg and opium 30 mg • Belladonna 16.2 mg and opium 60 mg
⛔ Contraindications ▾
4 CONTRAINDICATIONS Belladonna and opium suppositories are contraindicated in patients with: • Significant respiratory depression [see Warnings and Precautions ( 5.2 )] • Acute or severe bronchial asthma in an unmonitored setting or in the absence of resuscitative equipment [see Warnings and Precautions ( 5.5 )] • Concurrent use of monoamine oxidase inhibitors (MAOIs) or use of MAOIs within the last 14 days [see Warnings and Precautions ( 5.6 ), Drug Interactions ( 7 )] • Known or suspected gastrointestinal obstruction, including paralytic ileus [see Warnings and Precautions ( 5.10 )] • Hypersensitivity to opium or belladonna [see Adverse Events ( 6 )] • Glaucoma 2 • Severe hepatic or renal disease 2 • Narcotic idiosyncrasies 2 • Convulsive disorders 2 • Acute alcoholism 2 • Delirium tremens 2 • Premature labor 2 • Significant respiratory depression.
( 4 ) • Acute or severe bronchial asthma in an unmonitored setting or in absence of resuscitative equipment. ( 4 ) • Concurrent use of monoamine oxidase inhibitors (MAOIs) or use of MAOIs within the last 14 days. ( 4 ) • Known or suspected gastrointestinal obstruction, including paralytic ileus.
( 4 ) • Known hypersensitivity to opium or belladonna. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS These preparations are not recommended for use in children. • Life-Threatening Respiratory Depression in Patients with Chronic Pulmonary Disease or in Elderly, Cachectic, or Debilitated Patients: Monitor closely, particularly during initiation and titration. ( 5.5 ) • Adrenal Insufficiency: If diagnosed, treat with physiologic replacement of corticosteroids, and wean patient off of the opioid. ( 5.7 ) • Severe Hypotension: Monitor during dosage initiation and titration.
Avoid use of belladonna and opium suppositories in patients with circulatory shock. ( 5.8 ) • Risks of Use in Patients with Increased Intracranial Pressure, Brain Tumors, Head Injury, or Impaired Consciousness: Monitor for sedation and respiratory depression. Avoid use of belladonna and opium suppositories in patients with impaired consciousness or coma.
( 5.9 )
5.1Addiction, Abuse, and Misuse Belladonna and opium suppositories contains opium, a Schedule II controlled substance. As an opioid, belladonna and opium suppositories expose users to the risks of addiction, abuse, and misuse [see Drug Abuse and Dependence ( 9 )] . Although the risk of addiction in any individual is unknown, it can occur in patients appropriately prescribed belladonna and opium suppositories.
Addiction can occur at recommended dosages and if the drug is misused or abused. Assess each patient’s risk for opioid addiction, abuse, or misuse prior to prescribing belladonna and opium suppositories, and monitor all patients receiving belladonna and opium suppositories for the development of these behaviors or conditions. Risks are increased in patients with a personal or family history of substance abuse (including drug or alcohol abuse or addiction) or mental illness (e.g., major depression).
The potential for these risks should not, however, prevent the proper management of pain in any given patient. Patients at increased risk may be prescribed opioids such as belladonna and opium suppositories, but use in such patients necessitates intensive counseling about the risks and proper use of belladonna and opium suppositories along with intensive monitoring for signs of addiction, abuse, and misuse. Consider prescribing naloxone for the emergency treatment of opioid overdose [see Dosage and Administration ( 2.2 ), Warnings and Precautions ( 5.4 )] .
Opioids are sought by drug abusers and people with addiction disorders and are subject to criminal diversion. Consider these risks when prescribing or dispensing belladonna and opium suppositories. Strategies to reduce these risks include prescribing the drug in the smallest appropriate quantity and advising the patient on the proper disposal of unused drug [see Patient Counseling Information ( 17 )] .
Contact local state professional licensing board or state controlled substances authority for information on how to prevent and detect abuse or diversion of this product.
5.2Life-Threatening Respiratory Depression Serious, life-threatening, or fatal respiratory depression has been reported with the use of opioids, even when used as recommended. Respiratory depression, if not immediately recognized and treated, may lead to respiratory arrest and death. Management of respiratory depression may include close observation, supportive measures, and use of opioid antagonists, depending on the patient’s clinical status [see Overdosage ( 10 )] .
Carbon dioxide (CO 2 ) retention from opioid-induced respiratory depression can exacerbate the sedating effects of opioids. While serious, life-threatening, or fatal respiratory depression can occur at any time during the use of belladonna and opium suppositories, the risk is greatest during the initiation of therapy or following a dosage increase. Monitor patients closely for respiratory depression, especially within the first 24-72 hours of initiating therapy with and following dosage increases of belladonna and opium suppositories.
To reduce the risk of respiratory depression, proper dosin… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Belladonna may cause drowsiness, dry mouth, urinary retention, photophobia, rapid pulse, dizziness and blurred vision 7 . Opium usage may result in constipation, nausea or vomiting. Pruritis and urticaria may occasionally occur.
Hypersensitivity to opium or belladonna may occur. The following serious adverse reactions are described, or described in greater detail, in other sections: • Addiction, Abuse, and Misuse [see Warnings and Precautions ( 5.1 )] • Life-Threatening Respiratory Depression [see Warnings and Precautions ( 5.2 )] • Neonatal Opioid Withdrawal Syndrome [see Warnings and Precautions ( 5.3 )] • Interactions with Benzodiazepines and Other CNS Depressants [see Warnings and Precautions ( 5.4 )] • Adrenal Insufficiency [see Warnings and Precautions ( 5.7 )] • Severe Hypotension [see Warnings and Precautions ( 5.8 )] • Gastrointestinal Adverse Reactions [see Warnings and Precautions ( 5.10 )] • Seizures [see Warnings and Precautions ( 5.11 )] • Withdrawal [see Warnings and Precautions ( 5.12 )] Most common adverse reactions are drowsiness, dry mouth, urinary retention, photophobia, rapid pulse, dizziness and blurred vision, constipation, nausea and vomiting.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Padagis ® at 1-866-634-9120 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.2Postmarketing Experience The following adverse reactions have been identified during post-approval use of opioids. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Serotonin syndrome: Cases of serotonin syndrome, a potentially life-threatening condition, have been reported during concomitant use of opioids with serotonergic drugs.
Adrenal insufficiency: Cases of adrenal insufficiency have been reported with opioid use, more often following greater than one month of use. Anaphylaxis: Anaphylaxis has been reported with products containing opioids. Androgen deficiency: Cases of androgen deficiency have occurred with chronic use of opioids.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 1 includes clinically significant drug interactions with belladonna and opium suppositories. Table 1: Clinically Significant Drug Interactions with Belladonna and Opium Suppositories Benzodiazepines and Other Central Nervous System (CNS) Depressants Clinical Impact: Due to additive pharmacologic effect, the concomitant use of benzodiazepines or other CNS depressants, including alcohol, can increase the risk of hypotension, respiratory depression, profound sedation, coma, and death. Intervention: Reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are inadequate.
Limit dosages and durations to the minimum required. Follow patients closely for signs of respiratory depression and sedation. If concomitant use is warranted, consider prescribing naloxone for the emergency treatment of opioid overdose [see Dosage and Administration ( 2.2 ), Warnings and Precautions ( 5.1 , 5.2 , 5.4 )] .
Examples: Benzodiazepines and other sedatives/hypnotics, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, other opioids, alcohol. Serotonergic Drugs Clinical Impact: The concomitant use of opioids with other drugs that affect the serotonergic neurotransmitter system has resulted in serotonin syndrome. Intervention: If concomitant use is warranted, carefully observe the patient, particularly during treatment initiation and dose adjustment.
Discontinue belladonna and opium suppositories if serotonin syndrome is suspected. Examples: Selective serotonin reuptake inhibitors (SSRIs), serotonin and norepinephrine reuptake inhibitors (SNRIs), tricyclic antidepressants (TCAs), triptans, 5-HT3 receptor antagonists, drugs that effect the serotonin neurotransmitter system (e.g., mirtazapine, trazodone, tramadol), monoamine oxidase (MAO) inhibitors (those intended to treat psychiatric disorders and also others, such as linezolid and intravenous methylene blue). Monoamine Oxidase Inhibitors (MAOIs) Clinical Impact: MAOI interactions with opioids may manifest as serotonin syndrome or opioid toxicity (e.g., respiratory depression, coma) [see Warnings and Precautions ( 5.2 )] If urgent use of an opioid is necessary, use test doses and frequent titration of small doses to treat pain while closely monitoring blood pressure and signs and symptoms of CNS and respiratory depression.
Intervention: The use of belladonna and opium suppositories is not recommended for patients taking MAOIs or within 14 days of stopping such treatment. Examples: phenelzine, tranylcypromine, linezolid Mixed Agonist/Antagonist and Partial Agonist Opioid Analgesics Clinical Impact: May reduce the analgesic effect of belladonna and opium suppositories and/or precipitate withdrawal symptoms. Intervention: Avoid concomitant use.
Examples: butorphanol, nalbuphine, pentazocine, buprenorphine Muscle Relaxants Clinical Impact: Opium may enhance the neuromuscular blocking action of skeletal muscle relaxants and produce an increased degree of respiratory depression. Intervention: Monitor patients for signs of respiratory depression that may be greater than otherwise expected and decrease the dosage of belladonna and opium suppositories and/or the muscle relaxant as necessary. Due to the risk of respiratory depression with concomitant use of skeletal muscle relaxants and opioids, consider prescribing naloxone for the emergency treatment of opioid overdose [see Dosage and Administration ( 2.2 ), Warnings and Precautions ( 5.2 , 5.4 )] .
Diuretics Clinical Impact: Opioids can reduce the efficacy of diuretics by inducing the release of antidiuretic hormone. Intervention: Monitor patients for signs of diminished diuresis and/or effects on blood pressure and increase the dosage of the diuretic as needed. Anticholinergic Drugs Clinical Impact: The concomitant use of anticholinergic drugs may increase risk of urinary retention and/or severe constipation, which may lead to paralytic ileus.
Intervention… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy : May cause fetal harm. ( 8.1 )
8.1Pregnancy Risk Summary Prolonged use of opioid analgesics during pregnancy may cause neonatal opioid withdrawal syndrome. There are no available data with belladonna and opium suppositories in pregnant women to inform a drug associated risk for major birth defects and miscarriage. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions Prolonged use of opioid analgesics during pregnancy for medical or nonmedical purposes can result in physical dependence in the neonate and neonatal opioid withdrawal syndrome shortly after birth.
Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea and failure to gain weight. The onset, duration, and severity of neonatal opioid withdrawal syndrome vary based on the specific opioid used, duration of use, timing and amount of last maternal use, and rate of elimination of the drug by the newborn. Observe newborns for symptoms of neonatal opioid withdrawal syndrome and manage accordingly [see Warnings and Precautions ( 5.3 )] .
Belladonna refers to plant alkaloids that contain anticholinergic agents such as atropine. Atropine used in human pregnancies has not been associated with birth defects or adverse fetal effects although the drug readily crosses the placenta. Use during pregnancy may increase risk of respiratory abnormalities, hypospadias, and eye or ear malformations but causal relationship is unclear.
The Collaborative Perinatal Project found no relationship between first trimester use of atropine and birth defects in the offspring but found an increase in birth defects in general in the offspring of pregnancies where the mother had taken belladonna. There was no relationship to any particular syndrome of anomalies. A statistically significant (although weak) association was discovered between congenital anomalies and maternal use of belladonna.
A study was conducted based on the infants of 554 women who took belladonna during the first four months of pregnancy. The study was conducted in the Collaborative Perinatal Project and showed that belladonna is unlikely to cause minor congenital abnormalities. The estimated maximum risk is most likely less than 3% if maternal belladonna is used early in pregnancy.
1 Labor or Delivery Opioids cross the placenta and may produce respiratory depression and psycho-physiologic effects in neonates. An opioid antagonist, such as naloxone, must be available for reversal of opioid-induced respiratory depression in the neonate. Belladonna and opium suppositories is not recommended for use in pregnant women during or immediately prior to labor, when other analgesic techniques are more appropriate.
Opioid analgesics, including belladonna and opium suppositories, can prolong labor through actions which temporarily reduce the strength, duration, and frequency of uterine contractions. However, this effect is not consistent and may be offset by an increased rate of cervical dilation, which tends to shorten labor. Monitor neonates exposed to opioid analgesics during labor for signs of excess sedation and respiratory depression.
8.2Lactation Risk Summary The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for belladonna and opium suppositories and any potential adverse effects on the breastfed infant from belladonna and opium suppositories or from the underlying maternal condition. Clinical Considerations Infants exposed to belladonna and opium suppositories through… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Prolonged use of opioid analgesics during pregnancy may cause neonatal opioid withdrawal syndrome. There are no available data with belladonna and opium suppositories in pregnant women to inform a drug associated risk for major birth defects and miscarriage. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions Prolonged use of opioid analgesics during pregnancy for medical or nonmedical purposes can result in physical dependence in the neonate and neonatal opioid withdrawal syndrome shortly after birth.
Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea and failure to gain weight. The onset, duration, and severity of neonatal opioid withdrawal syndrome vary based on the specific opioid used, duration of use, timing and amount of last maternal use, and rate of elimination of the drug by the newborn. Observe newborns for symptoms of neonatal opioid withdrawal syndrome and manage accordingly [see Warnings and Precautions ( 5.3 )] .
Belladonna refers to plant alkaloids that contain anticholinergic agents such as atropine. Atropine used in human pregnancies has not been associated with birth defects or adverse fetal effects although the drug readily crosses the placenta. Use during pregnancy may increase risk of respiratory abnormalities, hypospadias, and eye or ear malformations but causal relationship is unclear.
The Collaborative Perinatal Project found no relationship between first trimester use of atropine and birth defects in the offspring but found an increase in birth defects in general in the offspring of pregnancies where the mother had taken belladonna. There was no relationship to any particular syndrome of anomalies. A statistically significant (although weak) association was discovered between congenital anomalies and maternal use of belladonna.
A study was conducted based on the infants of 554 women who took belladonna during the first four months of pregnancy. The study was conducted in the Collaborative Perinatal Project and showed that belladonna is unlikely to cause minor congenital abnormalities. The estimated maximum risk is most likely less than 3% if maternal belladonna is used early in pregnancy.
1 Labor or Delivery Opioids cross the placenta and may produce respiratory depression and psycho-physiologic effects in neonates. An opioid antagonist, such as naloxone, must be available for reversal of opioid-induced respiratory depression in the neonate. Belladonna and opium suppositories is not recommended for use in pregnant women during or immediately prior to labor, when other analgesic techniques are more appropriate.
Opioid analgesics, including belladonna and opium suppositories, can prolong labor through actions which temporarily reduce the strength, duration, and frequency of uterine contractions. However, this effect is not consistent and may be offset by an increased rate of cervical dilation, which tends to shorten labor. Monitor neonates exposed to opioid analgesics during labor for signs of excess sedation and respiratory depression.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of belladonna and opium suppositories in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Elderly patients (aged 65 years or older) may have increased sensitivity to belladonna and opium. In general, use caution when selecting a dosage for an elderly patient, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function and of concomitant disease or other drug therapy. Respiratory depression is the chief risk for elderly patients treated with opioids, and has occurred after large initial doses were administered to patients who were not opioid-tolerant or when opioids were co-administered with other agents that depress respiration.
Titrate the dosage of belladonna and opium suppositories slowly in geriatric patients [see Warnings and Precautions ( 5.2 )] .
🆘 Overdosage ▾
10 OVERDOSAGE Clinical Presentation Acute overdose with belladonna and opium suppositories can be manifested by respiratory depression, somnolence progressing to stupor or coma, skeletal muscle flaccidity, cold and clammy skin, constricted pupils, and, in some cases, pulmonary edema, bradycardia, hypotension, partial or complete airway obstruction, atypical snoring, and death. Marked mydriasis rather than miosis may be seen with hypoxia in overdose situations [see Clinical Pharmacology ( 12 )] . Treatment of Overdose In case of overdose, priorities are the reestablishment of a patent and protected airway and institution of assisted or controlled ventilation, if needed.
Employ other supportive measures (including oxygen and vasopressors) in the management of circulatory shock and pulmonary edema as indicated. Cardiac arrest or arrhythmias will require advanced life-support techniques. Opioid antagonists, such as naloxone or nalmefene, are specific antidotes to respiratory depression resulting from opioid overdose.
For clinically significant respiratory or circulatory depression secondary to opium overdose, administer an opioid antagonist. Because the duration of opioid reversal is expected to be less than the duration of action of opium in belladonna and opium suppositories, carefully monitor the patient until spontaneous respiration is reliably re-established. If the response to an opioid antagonist is suboptimal or only brief in nature, administer additional antagonist as directed by the product’s prescribing information.
In an individual physically dependent on opioids, administration of the recommended usual dosage of the antagonist will precipitate an acute withdrawal syndrome. The severity of the withdrawal symptoms experienced will depend on the degree of physical dependence and the dose of the antagonist administered. If a decision is made to treat serious respiratory depression in the physically dependent patient, administration of the antagonist should be initiated with care and by titration with smaller than usual doses of the antagonist.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Belladonna/opium rectal suppository is a combination narcotic analgesic/antispasmodic agent. The belladonna extract component of the rectal suppository provides the active alkaloids atropine and scopolamine, while the opium component provides primarily morphine (among more than 20 alkaloids). The atropine alkaloid is parasympatholytic, exerting antispasmodic activity by relaxation of smooth muscle that is stimulated by the parasympathetic nervous system.
The atropine alkaloid is also the dl isomer of l-hyoscyamine and exerts the same pharmacologic activity; however, it exerts about one-half the activity peripherally as l-hyoscyamine. Atropine activity also counteracts morphine induced smooth muscle spasm without affecting the analgesia. The morphine alkaloid of opium exerts analgesic activity by increasing the pain threshold and decreasing the sensitivity to pain.
The oxidative dealkylated nor-metabolites of morphine begin the analgesic process. Additionally, the side effect of euphoria may contribute to sense of pain relief.
12.2Pharmacodynamics Through its parasympatholytic action, atropine (belladonna) relaxes smooth muscle resulting from parasympathetic stimulation. It is the dl isomer of l-hyoscyamine and therefore exhibits the same clinical effects. It is, however, approximately one-half as active peripherally as l-hyoscyamine, the latter being the major active plant alkaloid.
The dl isomer atropine is formed during the process of isolation of the belladonna extract. 1 Morphine, the major active principle of powdered opium, is responsible for the action of powdered opium although the other alkaloids present also contribute to it. The sedative and analgesic action of morphine, the effect desired by inclusion in belladonna and opium suppositories of powdered opium, are thought to be due to the depressant effect on the cerebral cortex, hypothalamus and medullary centers.
In large doses, the opiates and their analogs also exhibit synaptic conduction in the spinothalamic tracts, depress the function of the reticular formation, the lemniscus and the thalamic relays, and inhibit spinal synaptic reflexes: but these inhibitor actions should not be elicited with therapeutic doses of the drug. Moderate doses of powdered opium should not alter the electroencephalogram. The action of morphine consists mainly of a descending depression of the central nervous system.
It exerts its analgesic action by increasing the pain threshold or the magnitude of stimulus required to evoke pain and by dulling the sensibility or reaction to pain. In addition to its action in abolishing pain, morphine induces a sense of well-being (euphoria) facilitating certain mental processes while retarding others.
12.3Pharmacokinetics Upon absorption of morphine, oxidative dealkylation to produce nor-compounds appears to be the first step in the reaction sequence which imparts analgesia. Morphine is conjugated in the liver to form the 3-glucuronide which passes into the bile and is reabsorbed and excreted in the urine. The atropine effect of the belladonna extract serves to eliminate morphine induced smooth muscle spasm without affecting the sedative analgesic action of powdered opium.
1
🧬 Mechanism of Action ▾
12.1Mechanism of Action Belladonna/opium rectal suppository is a combination narcotic analgesic/antispasmodic agent. The belladonna extract component of the rectal suppository provides the active alkaloids atropine and scopolamine, while the opium component provides primarily morphine (among more than 20 alkaloids). The atropine alkaloid is parasympatholytic, exerting antispasmodic activity by relaxation of smooth muscle that is stimulated by the parasympathetic nervous system.
The atropine alkaloid is also the dl isomer of l-hyoscyamine and exerts the same pharmacologic activity; however, it exerts about one-half the activity peripherally as l-hyoscyamine. Atropine activity also counteracts morphine induced smooth muscle spasm without affecting the analgesia. The morphine alkaloid of opium exerts analgesic activity by increasing the pain threshold and decreasing the sensitivity to pain.
The oxidative dealkylated nor-metabolites of morphine begin the analgesic process. Additionally, the side effect of euphoria may contribute to sense of pain relief.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Belladonna (16.2 mg) and Opium (30 mg) suppositories are brown, bullet shaped suppositories. NDC 0574-7045-04: Carton of 4 suppositories NDC 0574-7045-12: Carton of 12 suppositories Belladonna (16.2 mg) and Opium (60 mg) suppositories are brown, bullet shaped suppositories. NDC 0574-7040-04: Carton of 4 suppositories NDC 0574-7040-12: Carton of 12 suppositories Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
DO NOT REFRIGERATE. PROTECT FROM MOISTURE DURING STORAGE. Rx Only
📋 Description ▾
11 DESCRIPTION Each belladonna and opium suppository contains (in a water-soluble base consisting of polyethylene glycol 400, 1450, 8000 and polysorbate 60): Belladonna (16.2 mg) and Opium (30 mg): Powdered belladonna extract 16.2 mg and powdered opium 30 mg. Belladonna (16.2 mg) and Opium (60 mg): Powdered belladonna extract 16.2 mg and powdered opium 60 mg. This drug falls into the pharmacological/therapeutic class of narcotic analgesic/antispasmotic agents.
The pharmacologically active principles present in the belladonna extract component of belladonna and opium suppositories are: Established Name: Atropine Chemical Name: dl Tropyl Tropate Established Name: Scopolamine Chemical Name: dl Scopolamine Opium contains more than twenty alkaloids, the principle ones being morphine (10%), narcotine (6%), papaverine (1%) and codeine (0.5%). The major pharmacologically active principle of the powdered opium component of belladonna and opium suppositories, however, is: Name: Morphine Chemical Name: 7, 8-Didehydro-4, 5-epoxy-17-Methyl-morphinan-3, 6-diol table 1 table 2 table 3
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the patient labeling (Medication Guide). Storage and Disposal Because of the risks associated with accidental ingestion, misuse, and abuse, advise patients to store belladonna and opium suppositories securely, out of sight and reach of children, and in a location not accessible by others, including visitors to the home [see Warnings and Precautions ( 5.1 , 5.2 ), Drug Abuse and Dependence ( 9.2 )] . Inform patients that leaving belladonna and opium suppositories unsecured can pose a deadly risk to others in the home.
Advise patients and caregivers that when medicines are no longer needed, they should be disposed of promptly. Expired, unwanted, or unused belladonna and opium suppositories should be disposed of by flushing the unused medication down the toilet if a drug take-back option is not readily available. Inform patients that they can visit www.fda.gov/drugdisposal for a complete list of medicines recommended for disposal by flushing, as well as additional information on disposal of unused medicines.
Addiction, Abuse, and Misuse Inform patients that the use of belladonna and opium suppositories, even when taken as recommended, can result in addiction, abuse, and misuse, which can lead to overdose and death [see Warnings and Precautions ( 5.1 )] . Instruct patients not to share belladonna and opium suppositories with others and to take steps to protect belladonna and opium suppositories from theft or misuse. Life-Threatening Respiratory Depression Inform patients of the risk of life-threatening respiratory depression, including information that the risk is greatest when starting belladonna and opium suppositories or when the dosage is increased, and that it can occur even at recommended dosages.
Educate patients and caregivers on how to recognize respiratory depression and emphasize the importance of calling 911 or getting emergency medical help right away in the event of a known or suspected overdose [see Warnings and Precautions ( 5.2 )] . Patient Access to Naloxone for the Emergency Treatment of Opioid Overdose Discuss with the patient and caregiver the availability of naloxone for the emergency treatment of opioid overdose, both when initiating and renewing treatment with belladonna and opium suppositories.
Inform patients and caregivers about the various ways to obtain naloxone as permitted by individual state naloxone dispensing and prescribing requirements or guidelines (e.g., by prescription, directly from a pharmacist, or as part of a community-based program [see Dosage and Administration ( 2.2 ), Warnings and Precautions ( 5.1 )] . Educate patients and caregivers on how to recognize the signs and symptoms of an overdose. Explain to patients and caregivers that naloxone's effects are temporary, and that they must call 911 or get emergency medical help right away in all cases of known or suspected opioid overdose, even if naloxone is administered [see Overdosage ( 10 )] .
If naloxone is prescribed, also advise patients and caregivers: • How to treat with naloxone in the event of an opioid overdose • To tell family and friends about their naloxone and to keep it in a place where family and friends can access it in an emergency • To read the Patient Information (or other educational material) that will come with their naloxone. Emphasize the importance of doing this before an opioid emergency happens, so the patient and caregiver will know what to do. Accidental Exposure Inform patients that accidental exposure (including ingestion), especially by children, may result in respiratory depression or death [see Warnings and Precautions ( 5.2 )] .
Interactions with Benzodiazepines and Other CNS Depressants Inform patients and caregivers that potentially fatal additive effects may occur if belladonna and opium suppositories are used with benzodiazepines or other CNS depressants, including alcohol, and not to use these concomitantly unless supervised by a healthca… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
Medication Guide Medication Guide Belladonna (bell ah DON ah) and Opium (OH pee um) Suppositories, CII Belladonna and opium suppositories are: • A strong prescription pain medicine that contains an opioid (narcotic) that is used to manage ureteral spasm pain severe enough to require an opioid analgesic, when other pain treatments such as non-opioid pain medicines do not treat your pain well enough or you cannot tolerate them. • An opioid pain medicine that can put you at risk for overdose and death. Even if you take your dose correctly as prescribed you are at risk for opioid addiction, abuse, and misuse that can lead to death.
Important information about belladonna and opium suppositories: • Get emergency help or call 911 right away if you take too much belladonna and opium suppositories (overdose). When you first start taking belladonna and opium suppositories, when your dose is changed, or if you take too much (overdose), serious or life-threatening breathing problems that can lead to death may occur. Talk to your healthcare provider about naloxone, a medicine for the emergency treatment of an opioid overdose. • Taking belladonna and opium suppositories with other opioid medicines, benzodiazepines, alcohol, or other central nervous system depressants (including street drugs) can cause severe drowsiness, decreased awareness, breathing problems, coma, and death. • Never give anyone else your belladonna and opium suppositories.
They could die from taking them. Selling or giving away belladonna and opium suppositories is against the law. • Store belladonna and opium suppositories securely, out of sight and reach of children, and in a location not accessible by others, including visitors to the home. Do not take belladonna and opium suppositories if you have: • severe asthma, trouble breathing, or other lung problems. • a bowel blockage or have narrowing of the stomach or intestines.
Before taking belladonna and opium suppositories, tell your healthcare provider if you have a history of: • head injury, seizures • liver, kidney, thyroid problems • problems urinating • pancreas or gallbladder problems • abuse of street or prescription drugs, alcohol addiction, opioid overdose, or mental health problems. Tell your healthcare provider if you are: • pregnant or planning to become pregnant. Prolonged use of belladonna and opium suppositories during pregnancy can cause withdrawal symptoms in your newborn baby that could be life-threatening if not recognized and treated. • breastfeeding.
Opium passes into breastmilk and may harm your baby. • living in a household where there are small children or someone who has abused street or prescription drugs. • taking prescription or over-the-counter medicines, vitamins, or herbal supplements. Taking belladonna and opium suppositories with certain other medicines can cause serious side effects that could lead to death. When taking belladonna and opium suppositories: • Do not change your dose.
Take belladonna and opium suppositories exactly as prescribed by your healthcare provider. Use the lowest dose possible for the shortest time needed. • Do not take more than your prescribed dose. If you miss a dose, consult with your healthcare provider. • Call your healthcare provider if the dose you are taking does not control your pain. • If you have been taking belladonna and opium suppositories regularly, do not stop taking belladonna and opium suppositories without talking to your healthcare provider. • After you stop taking belladonna and opium suppositories, return unused suppositories to the pharmacy or deliver to an accredited disposal site.
Visit www.fda.gov/drugdisposal for additional information on disposal of unused medicines. • Unwrap suppository, then moisten finger and suppository with water before inserting. While taking belladonna and opium suppositories DO NOT: • Drive or operate heavy machinery, until you know how belladonna and opium suppositories affects you. Belladonna and opium suppos… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Upon absorption of morphine, oxidative dealkylation to produce nor-compounds appears to be the first step in the reaction sequence which imparts analgesia. Morphine is conjugated in the liver to form the 3-glucuronide which passes into the bile and is reabsorbed and excreted in the urine. The atropine effect of the belladonna extract serves to eliminate morphine induced smooth muscle spasm without affecting the sedative analgesic action of powdered opium.
1
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Through its parasympatholytic action, atropine (belladonna) relaxes smooth muscle resulting from parasympathetic stimulation. It is the dl isomer of l-hyoscyamine and therefore exhibits the same clinical effects. It is, however, approximately one-half as active peripherally as l-hyoscyamine, the latter being the major active plant alkaloid.
The dl isomer atropine is formed during the process of isolation of the belladonna extract. 1 Morphine, the major active principle of powdered opium, is responsible for the action of powdered opium although the other alkaloids present also contribute to it. The sedative and analgesic action of morphine, the effect desired by inclusion in belladonna and opium suppositories of powdered opium, are thought to be due to the depressant effect on the cerebral cortex, hypothalamus and medullary centers.
In large doses, the opiates and their analogs also exhibit synaptic conduction in the spinothalamic tracts, depress the function of the reticular formation, the lemniscus and the thalamic relays, and inhibit spinal synaptic reflexes: but these inhibitor actions should not be elicited with therapeutic doses of the drug. Moderate doses of powdered opium should not alter the electroencephalogram. The action of morphine consists mainly of a descending depression of the central nervous system.
It exerts its analgesic action by increasing the pain threshold or the magnitude of stimulus required to evoke pain and by dulling the sensibility or reaction to pain. In addition to its action in abolishing pain, morphine induces a sense of well-being (euphoria) facilitating certain mental processes while retarding others.
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.1Controlled Substance Belladonna and opium suppositories contains opium, a Schedule II controlled substance.
9.2Abuse Belladonna and opium suppositories contains opium, a substance with a high potential for abuse similar to other opioids including fentanyl, hydrocodone, hydromorphone, methadone, morphine, oxycodone, oxymorphone, and tapentadol. Belladonna and opium suppositories can be abused and is subject to misuse, addiction, and criminal diversion [see Warnings and Precautions ( 5.1 )] . All patients treated with opioids require careful monitoring for signs of abuse and addiction, since use of opioid analgesic products carries the risk of addiction even under appropriate medical use.
Prescription drug abuse is the intentional non-therapeutic use of a prescription drug, even once, for its rewarding psychological or physiological effects. Drug addiction is a cluster of behavioral, cognitive, and physiological phenomena that develop after repeated substance use and includes: a strong desire to take the drug, difficulties in controlling its use, persisting in its use despite harmful consequences, a higher priority given to drug use than to other activities and obligations, increased tolerance, and sometimes a physical withdrawal. “Drug-seeking” behavior is very common in persons with substance use disorders.
Drug-seeking tactics include emergency calls or visits near the end of office hours, refusal to undergo appropriate examination, testing, or referral, repeated “loss” of prescriptions, tampering with prescriptions and reluctance to provide prior medical records or contact information for other treating health care provider(s). “Doctor shopping” (visiting multiple prescribers) to obtain additional prescriptions is common among drug abusers and people suffering from untreated addiction. Preoccupation with achieving adequate pain relief can be appropriate behavior in a patient with poor pain control.
Abuse and addiction are separate and distinct from physical dependence and tolerance. Health care providers should be aware that addiction may not be accompanied by concurrent tolerance and symptoms of physical dependence in all addicts. In addition, abuse of opioids can occur in the absence of true addiction.
Belladonna and opium suppositories, like other opioids, can be diverted for non-medical use into illicit channels of distribution. Careful record-keeping of prescribing information, including quantity, frequency, and renewal requests, as required by state and federal law, is strongly advised. Proper assessment of the patient, proper prescribing practices, periodic re-evaluation of therapy, and proper dispensing and storage are appropriate measures that help to limit abuse of opioid drugs.
Risks Specific to Abuse of Belladonna and Opium Suppositories Belladonna and opium suppositories are for rectal use only. Abuse of belladonna and opium suppositories poses a risk of overdose and death. The risk is increased with concurrent abuse of belladonna and opium suppositories with alcohol and other central nervous system depressants.
Parenteral drug abuse is commonly associated with transmission of infectious diseases such as hepatitis and HIV.
9.3Dependence Both tolerance and physical dependence can develop during chronic opioid therapy. Tolerance is the need for increasing doses of opioids to maintain a defined effect such as analgesia (in the absence of disease progression or other external factors). Tolerance may occur to both the desired and undesired effects of drugs, and may develop at different rates for different effects.
Physical dependence results in withdrawal symptoms after abrupt discontinuation or a significant dosage reduction of a drug. Withdrawal also may be precipitated through the administration of drugs with opioid antagonist activity (e.g., naloxone, nalmefene), mixed agonist/antagonist analgesics (pentazocine, butorphanol, nalbuphine), or partial agonists (buprenorphine). Physi… [Excerpted — this section continues on DailyMed.]
🔒 Controlled Substance ▾
9.1Controlled Substance Belladonna and opium suppositories contains opium, a Schedule II controlled substance.
📚 References ▾
15 REFERENCES 1. Belladonna. DrugPoints Summary. Micromedex 2.0. Truven Health Analytics, Inc. Greenwood Village, CO. Accessed October 2, 2017. 2. Olin BR. Drug Facts and Comparisons, 50th ed. Facts and Comparisons, St Louis, MO; 1999.
📄 Recent Major Changes ▾
Dosage and Administration ( 2.2 ) 04/2023 Warnings and Precautions ( 5.1 , 5.2 , 5.4 ) 04/2023
📄 Package Label / Principal Display Panel ▾
PACKAGE/LABEL PRINCIPAL DISPLAY PANEL – Belladonna and Opium Suppository 16.2 mg/30 mg NDC 0574-7045-12 Rx Only Belladonna and Opium Suppositories 16.2 mg/30 mg CII Each suppository contains: Powdered Opium 30 mg (Warning – May be habit forming) Powdered Belladonna Extract 16.2 mg Print Medication Guides at: www.padagis.com/medguide/BLOPB 12 Suppositories UNIT DOSE FOR RECTAL USE ONLY The following image is a placeholder representing the product identifier that is either affixed or imprinted on the drug package label during the packaging operation.
16.2 mg/30 mg Carton serialization
PRINCIPAL DISPLAY PANEL – Belladonna and Opium Suppository 16.2 mg/60 mg 0574-7040 - 12 Rx Only Belladonna and Opium Suppositories 16.2 mg/60 mg CII Each suppository contains: Powdered Opium 60 mg (Warning – May be habit forming) Powdered Belladonna Extract 16.2 mg Print Medication Guides at: www.padagis.com/medguide/BLOPB 12 Suppositories UNIT DOSE FOR RECTAL USE ONLY The following image is a placeholder representing the product identifier that is either affixed or imprinted on the drug package label during the packaging operation.
16.2 mg/60 mg Carton serialization
Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
Listed without an FDA application
This product's marketing category indicates it is marketed without an approved FDA application (no NDA, ANDA, or BLA on file). Having an NDC does not by itself establish FDA approval — the NDC Directory is a listing system, not an approval decision. Approval-linked data such as Orange Book therapeutic-equivalence ratings therefore does not apply.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |