
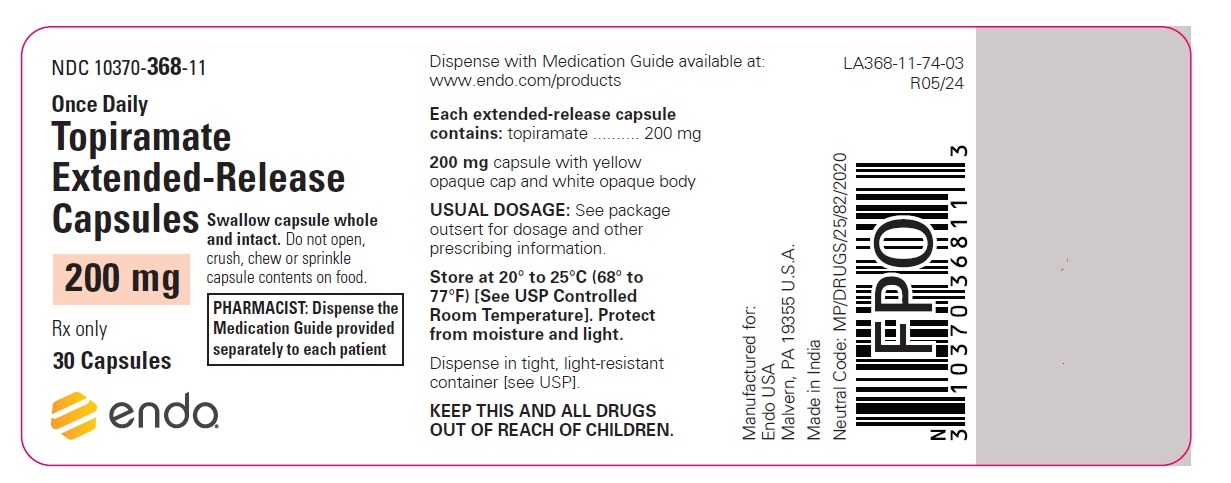
Topiramate 200 mg Capsule, Extended Release, 30-count
Other active recalls for Topiramate (different manufacturers) — 2 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Centrally acting antiobesity products class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Topiramate — tap one for details:
Topiramate may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII 3DYK7UYZ62
Ethylcellulose is a plant-fiber derivative used as a binder and film-coating agent in tablets and capsules. It helps hold ingredients together and can create a protective coating that controls how quickly the medicine dissolves.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII WZB9127XOA
A synthetic red dye used to color medications and make them easier to identify. It serves as a colorant in tablets, capsules, and liquid formulations.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII R75537T0T4
Hypromellose 2910 is a plant-derived thickening agent made from cellulose. It serves as a binder that holds tablet ingredients together, a film-coating for pills, and a viscosity controller in liquids.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
16 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $23.128 | $693.85 / 30 capsules |
| Medicaid paysCMS SDUD · 12 mo | $25.15 | $754.55 / 30 capsules |
| Medicare drug plans payPart D · Q2 2026 | $22.54 | $676.18 / 30 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Topiramate 200 mg 70710-1043-03 | Zydus | 30 capsules | $9.671 | AB2 | Availability likely | save 58% |
| Topiramate 200 mg 72603-0124-01 | NorthStar | 30 capsules | $9.671 | AB2 | Availability likely | save 58% |
| Topiramate 200 mg 69680-0181-30 | Vitruvias | 30 capsules | $9.671 | AB2 | Availability likely | save 58% |
| Topiramate 200 mg 00480-2359-01 | Teva | 100 capsules | $23.128 | AB1 | Availability likely | — |
| Topiramate 200 mgthis 10370-0368-11 | Par | 30 capsules | $23.128 | AB1 | Availability likely | — |
| Topiramate 200 mg 70748-0278-06 | Lupin | 30 capsules | $23.128 | AB1 | Availability likely | — |
| Qudexy Xr 200 mg 00245-1073-30 | Upsher-Smith | 30 capsules | $32.876 | AB2 | Availability likely | +42% |
| Trokendi XR 200 mg 17772-0104-01 | Supernus | 100 capsules | $41.565 | AB1 | FDA listed | +80% |
| Topiramate 200 mg 27241-0230-01 | Ajanta | 100 capsules | — | AB1 | FDA listed | — |
| Topiramate 200 mg 31722-0550-30 | Camber | 30 capsules | — | AB1 | FDA listed | — |
| Topiramate 200 mg 42291-0958-30 | AvKARE | 30 capsules | — | AB1 | FDA listed | — |
| Topiramate 200 mg 43598-0942-01 | Dr. | 100 capsules | — | AB1 | FDA listed | — |
| Topiramate 200 mg 68382-0358-01 | Zydus | 100 capsules | — | AB1 | FDA listed | — |
| Topiramate 200 mg 70771-1858-01 | Zydus | 100 capsules | — | AB1 | FDA listed | — |
| Topiramate 200 mg 70771-1660-03 | Zydus | 30 capsules | — | AB2 | FDA listed | — |
| Topiramate 200 mg 27241-0300-30 | Ajanta | 30 capsules | — | AB2 | FDA listed | — |
| Topiramate 200 mg 68462-0371-05 | Glenmark | 500 capsules | — | AB2 | FDA listed | — |
| Topiramate 200 mg 00832-1073-15 | Upsher-Smith | 500 capsules | — | AB2 | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 10370-0368-01 | 100 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (10370-368-01) | $23.13 / ea | $2,312.83 | 2023-03-24 | Active |
| 10370-0368-05 | 500 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (10370-368-05) | — | — | 2023-03-24 | Discontinued by firm |
| 10370-0368-11 You're viewing this | 30 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (10370-368-11) | $23.13 / ea | $693.85 | 2023-03-24 | Active |
You're viewing the smallest of 3 pack sizes for this product.
This pack effectively ties for the lowest per-ea cost of the 2 priced pack sizes ($23.13 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 96% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 10370-0368-11?
What is the difference between NDC 10370-0368-11 and NDC 10370-0368-01?
What NDC number is used to bill for this package of Topiramate 200 mg Capsule, Extended Release?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Topiramate extended-release capsules are indicated for: Epilepsy: initial monotherapy for the treatment of partial-onset or primary generalized tonic-clonic seizures in patients 6 years of age and older ( 1.1) ; adjunctive therapy for the treatment of partial-onset, primary generalized tonic-clonic seizures, or seizures associated with Lennox-Gastaut syndrome (LGS) in patients 6 years of age and older (1.2) Preventive treatment of migraine in patients 12 years of age and older ( 1.3 )
1.1Monotherapy Epilepsy Topiramate extended-release capsules are indicated as initial monotherapy for the treatment of partial-onset or primary generalized tonic-clonic seizures in patients 6 years of age and older [see Clinical Studies (14.2) ] .
1.2Adjunctive Therapy Epilepsy Topiramate extended-release capsules are indicated as adjunctive therapy for the treatment of partial-onset seizures, primary generalized tonic-clonic seizures, and seizures associated with Lennox-Gastaut syndrome in patients 6 years of age and older [ see Clinical Studies (14.3) ] .
1.3Migraine Topiramate extended-release capsules are indicated for the preventive treatment of migraine in patients 12 years of age and older [see Clinical Studies (14.4) ] .
1.1Monotherapy Epilepsy Topiramate extended-release capsules are indicated as initial monotherapy for the treatment of partial-onset or primary generalized tonic-clonic seizures in patients 6 years of age and older [see Clinical Studies (14.2) ] .
1.2Adjunctive Therapy Epilepsy Topiramate extended-release capsules are indicated as adjunctive therapy for the treatment of partial-onset seizures, primary generalized tonic-clonic seizures, and seizures associated with Lennox-Gastaut syndrome in patients 6 years of age and older [ see Clinical Studies (14.3) ] .
1.3Migraine Topiramate extended-release capsules are indicated for the preventive treatment of migraine in patients 12 years of age and older [see Clinical Studies (14.4) ] .
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Topiramate extended-release capsules initial dose, titration, and recommended maintenance dose varies by indication and age group. See Full Prescribing Information for recommended dosage, and dosing considerations in patients with renal impairment, geriatric patients, and patients undergoing hemodialysis ( 2.1, 2.2 , 2.3 , 2.4 , 2.5 , 2.6 ) Swallow capsule whole and intact. Do not sprinkle on food, chew, or crush (2.7 )
2.1Dosing in Monotherapy Epilepsy Adults and Pediatric Patients 10 Years of Age and Older with Partial Onset or Primary Generalized Tonic-Clonic Seizures The recommended dose for topiramate extended-release capsules monotherapy in adults and in pediatric patients 10 years of age and older is 400 mg orally once daily. Titrate topiramate extended-release capsules according to the following schedule: Week 1: 50 mg once daily Week 2: 100 mg once daily Week 3: 150 mg once daily Week 4: 200 mg once daily Week 5: 300 mg once daily Week 6: 400 mg once daily Pediatric Patients Ages 6 to 9 Years of Age Dosing in patients 6 to 9 years of age is based on weight.
During the titration period, the initial dose of topiramate extended-release capsules is 25 mg/day nightly for the first week. Based upon tolerability, the dosage can be increased to 50 mg/day in the second week. Dosage can be increased by 25 mg/day to 50 mg/day each subsequent week as tolerated.
Titration to the minimum maintenance dose should be attempted over 5 to 7 weeks of the total titration period. Based upon tolerability and clinical response, additional titration to a higher dose (up to the maximum maintenance dose) can be attempted at 25 mg/day to 50 mg/day weekly increments. The total daily dose should not exceed the maximum maintenance dose for each range of body weight (see Table 1).
Table 1: Monotherapy Target Total Daily Maintenance Dosing for Patients 6 to 9 Years of Age Weight (kg) Total Daily Dose (mg/day) Minimum Maintenance Dose Total Daily Dose (mg/day) Maximum Maintenance Dose Up to 11 150 250 12 to 22 200 300 23 to 31 200 350 32 to 38 250 350 Greater than 38 250 400
2.2Dosing in Adjunctive Therapy Epilepsy Adults (17 Years of Age and Older) The recommended total daily dose of topiramate extended-release capsules as adjunctive therapy in adults with partial-onset seizures or Lennox-Gastaut Syndrome is 200 mg to 400 mg orally once daily and with primary generalized tonic-clonic seizures is 400 mg orally once daily. Initiate therapy at 25 mg to 50 mg once daily followed by titration to an effective dose in increments of 25 mg to 50 mg every week. Titrating in increments of 25 mg/day every week may delay the time to reach an effective dose.
Doses above 400 mg/day have not been shown to improve responses in adults with partial-onset seizures. Pediatric Patients 6 to 16 Years of Age The recommended total daily dose of topiramate extended-release capsules as adjunctive therapy for patients 6 to 16 years of age with partial-onset seizures, primary generalized tonic-clonic seizures, or seizures associated with Lennox-Gastaut syndrome is approximately 5 mg/kg to 9 mg/kg orally once daily. Begin titration at 25 mg once daily (or less, based on a range of 1 mg/kg/day to 3 mg/kg/day) given nightly for the first week.
Subsequently, increase the dosage at 1- or 2-week intervals by increments of 1 mg/kg/day to 3 mg/kg/day to achieve optimal clinical response. Dose titration should be guided by clinical outcome. The total daily dose should not exceed 400 mg/day.
2.3Dosing for the Preventive Treatment of Migraine The recommended total daily dose of topiramate extended-release capsules as treatment for the preventive treatment of migraine in patients 12 years of age and older is 100 mg once daily. Titrate topiramate extended-release capsules for the preventive treatment of migraine according to the following schedule: Week 1: 25 mg once daily Week 2: 50 mg once daily Week 3: 75 mg once daily Week 4: 100 mg once daily Dose and titr…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Topiramate extended-release capsules are available in the following strength and colors: 200 mg: Hard gelatin capsule with yellow opaque cap and white opaque body, imprinted with “par” on the cap and “C368” on the body in black ink, containing white to off-white spherical-shaped film-coated pellets. Extended-release capsules: 200 mg ( 3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Topiramate extended-release capsules are contraindicated in patients with: recent alcohol use (i.e., within 6 hours prior to and 6 hours after topiramate extended-release capsules use) [see Warnings and Precautions ( 5.5 )]. a history of hypersensitivity reaction to topiramate, topiramate extended-release capsules, or any of the inactive ingredients of topiramate extended-release capsules. Anaphylaxis and angioedema have occurred [see Warnings and Precautions ( 5.14 )] . With recent alcohol use, i.e., within 6 hours prior to and 6 hours after topiramate extended-release capsules use ( 4 , 5.5 ) History of hypersensitivity reaction to topiramate.
Topiramate extended-release capsules, or any of the inactive ingredients of topiramate extended-release capsules ( 4 , 5.14 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Acute myopia and secondary angle closure glaucoma: can lead to permanent visual loss; discontinue topiramate extended-release capsules as soon as possible ( 5.1 ) Visual field defects: consider discontinuation of topiramate extended-release capsules ( 5.2 ) Oligohydrosis and hyperthermia: monitor decreased sweating and increased body temperature, especially in pediatric patients ( 5.3 ) Metabolic acidosis: baseline and periodic measurement of serum bicarbonate is recommended; consider dose reduction or discontinuation of topiramate extended-release capsules if clinically appropriate ( 5.4 ) Suicidal behavior and ideation: antiepileptic drugs increase the risk of suicidal behavior or ideation ( 5.6 ) Cognitive/neuropsychiatric adverse reactions: use caution when operating machinery including cars; depression and mood problems may occur ( 5.7 ) Fetal toxicity: use during pregnancy can cause major congenital malformations, including but not limited to cleft lip and/or palate, and being small for gestational age (5.8) Withdrawal of AEDs: withdraw topiramate extended-release capsules gradually (5.9) Decrease in Bone Mineral Density: has been shown to decrease bone mineral density and bone mineral content in pediatric patients ( 5.10) Negative effects on growth (height and weight): may slow height increase and weight gain; carefully monitor children receiving prolonged therapy (5.11) Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)/Multiorgan Hypersensitivity, serious skin reactions, anaphylaxis, and angioedema: Discontinue topiramate extended-release capsules if an alternative etiology cannot be established ( 5.12 , 5.13 , 5.14 ) Hyperammonemia/encephalopathy: measure ammonia if encephalopathic symptoms occur ( 5.15 ) Kidney stones: avoid use with other carbonic anhydrase inhibitors, other drugs causing metabolic acidosis, or in patients on a ketogenic diet ( 5.16 ) Hypothermia has been reported with and without hyperammonemia during topiramate treatment with concomitant valproic acid use ( 5.17 )
5.1Acute Myopia and Secondary Angle Closure Glaucoma Syndrome A syndrome consisting of acute myopia associated with secondary angle closure glaucoma has been reported in patients receiving topiramate. Symptoms include acute onset of decreased visual acuity and/or ocular pain. Ophthalmologic findings can include some or all of the following: myopia, mydriasis, anterior chamber shallowing, ocular hyperemia (redness), choroidal detachments, retinal pigment epithelial detachments, macular striae, and increased intraocular pressure.
This syndrome may be associated with supraciliary effusion resulting in anterior displacement of the lens and iris, with secondary angle closure glaucoma. Symptoms typically occur within 1 month of initiating topiramate therapy. In contrast to primary narrow angle glaucoma, which is rare under 40 years of age, secondary angle closure glaucoma associated with topiramate has been reported in pediatric patients as well as adults.
The primary treatment to reverse symptoms is discontinuation of topiramate extended-release capsules as rapidly as possible, according to the judgment of the treating physician. Other measures, in conjunction with discontinuation of topiramate extended-release capsules, may be helpful. Elevated intraocular pressure of any etiology, if left untreated, can lead to serious sequelae including permanent vision loss.
5.2Visual Field Defects Visual field defects (independent of elevated intraocular pressure) have been reported in clinical trials and in postmarketing experience in patients receiving topiramate. In clinical trials, most of these events were reversible after topiramate discontinuation. If visual problems occur at any time during treatment with topiramate extended-release capsules, consideration should be given to discontinuing the drug.
5.3Oligohydrosis and Hyperthermia Oligohydrosis (decreased sweating), resulting in hospitalization in some c…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed in more detail in other sections of the labeling: Acute Myopia and Secondary Angle Closure Glaucoma [see Warnings and Precautions (5.1 )] Visual Field Defects [see Warnings and Precautions ( 5.2 )] Oligohydrosis and Hyperthermia [see Warnings and Precautions ( 5.3 )] Metabolic Acidosis [see Warnings and Precautions ( 5.4) ] Interaction With Alcohol [see Warnings and Precautions ( 5.5) ] Suicidal Behavior and Ideation [see Warnings and Precautions ( 5.6 )] Cognitive/Neuropsychiatric Adverse Reactions [see Warnings and Precautions ( 5.7 )] Fetal Toxicity [see Warnings and Precautions ( 5.8 )] Withdrawal of Antiepileptic Drugs [see Warnings and Precautions ( 5.9) ] Decrease of Bone Mineral Density [see Warnings and Precautions ( 5.10) ] Negative Effects on Growth (Height and Weight) [see Warnings and Precautions ( 5.11 )] Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)/Multiorgan Hypersensitivity Reactions [see Warnings and Precautions ( 5.12 )] Serious Skin Reactions [see Warnings and Precautions ( 5.13 )] Anaphylaxis and Angioedema [see Warnings and Precautions ( 5.14 )] Hyperammonemia and Encephalopathy (Without and With Concomitant Valproic Acid Use) [see Warnings and Precautions ( 5.15 )] Kidney Stones [see Warnings and Precautions ( 5.16 )] Hypothermia With Concomitant Valproic Acid Use [see Warnings and Precautions ( 5.17 )] The data described in the following sections were obtained using immediate-release topiramate tablets.
Topiramate extended-release capsules have not been studied in a randomized, placebo-controlled Phase III clinical study; however, it is expected that topiramate extended-release capsules would produce a similar adverse reaction profile as immediate-release topiramate. Epilepsy: Most common (≥10% more frequent than placebo or low-dose topiramate) adverse reactions in adult and pediatric patients were paresthesia, anorexia, weight loss, speech disorders/related speech problems, fatigue, dizziness, somnolence, nervousness, psychomotor slowing, abnormal vision, and fever ( 6.1 ).
Migraine: Most common (≥5% more frequent than placebo) adverse reactions in adult and pediatric patients were: paresthesia, anorexia, weight loss, difficulty with memory, taste perversion, diarrhea, hypoesthesia, nausea, abdominal pain, and upper respiratory tract infection ( 6.1 ). To report SUSPECTED ADVERSE REACTIONS, contact Par Health at 1-800-828-9393 or the FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Monotherapy Epilepsy Adults 16 Years of Age and Older The most common adverse reactions in the controlled trial (Study 1) that occurred in adults in the 400 mg/day topiramate group and at an incidence higher (≥10%) than in the 50 mg per day group were: paresthesia, weight loss, and anorexia (see Table 3).
Approximately 21% of the 159 adult patients in the 400 mg/day group who received topiramate as monotherapy in Study 1 discontinued therapy due to adverse reactions. The most common (≥2% more frequent than low-dose 50 mg/day topiramate) adverse reactions causing discontinuation were difficulty with memory, fatigue, asthenia, insomnia, somnolence, and paresthesia. Pediatric Patients 6 Years to 15 Years of Age The most common adverse reactions in the controlled trial (Study 1) that occurred in pediatric patients in the 400 mg/day topiramate group and at an incidence higher (≥10%) than in the 50 mg/day group were fever and weight loss (see Table 3).
Approximately 14% of the 77 pediatric patients in the 400 mg/day group who received topiramate as monotherapy in the controlled clinical trial discontinued therapy due to adverse reactions. The most common…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Contraceptives: Decreased contraceptive efficacy and increased breakthrough bleeding, especially at doses greater than 200 mg per day ( 7.5 ) Monitor lithium levels if lithium is used with high-dose topiramate extended-release capsules ( 7.8 )
7.1Alcohol Alcohol use is contraindicated within 6 hours prior to and 6 hours after topiramate extended-release capsules administration [see Contraindications (4) and Warnings and Precautions ( 5.5 )] .
7.2Antiepileptic Drugs Concomitant administration of phenytoin or carbamazepine with topiramate resulted in a clinically significant decrease in plasma concentrations of topiramate when compared to topiramate given alone. A dosage adjustment may be needed [see Dosage and Administration ( 2.1 ), Clinical Pharmacology ( 12.3) ] . Concomitant administration of valproic acid and topiramate has been associated with hypothermia and hyperammonemia with and without encephalopathy.
Examine blood ammonia levels in patients in whom the onset of hypothermia has been reported [see Warnings and Precautions ( 5.15 , 5.17 ) and Clinical Pharmacology ( 12.3 )] .
7.3Other Carbonic Anhydrase Inhibitors Concomitant use of topiramate, a carbonic anhydrase inhibitor, with any other carbonic anhydrase inhibitor (e.g., zonisamide or acetazolamide) may increase the severity of metabolic acidosis and may also increase the risk of kidney stone formation. Patients should be monitored for the appearance or worsening of metabolic acidosis when topiramate extended-release capsules is given concomitantly with another carbonic anhydrase inhibitor [see Clinical Pharmacology ( 12.3) ] .
7.4CNS Depressants Concomitant administration of topiramate with other CNS depressant drugs or alcohol has not been evaluated in clinical studies. Because of the potential of topiramate to cause CNS depression, as well as other cognitive and/or neuropsychiatric adverse reactions, topiramate extended-release capsules should be used with extreme caution if used in combination with alcohol and other CNS depressants [see Contraindications (4) and Warnings and Precautions ( 5.7) ] .
7.5Contraceptives The possibility of decreased contraceptive efficacy and increased breakthrough bleeding may occur in patients taking contraceptive products with topiramate extended-release capsules. Patients taking estrogen-containing or progestin-only contraceptives should be asked to report any change in their bleeding patterns. Contraceptive efficacy can be decreased even in the absence of breakthrough bleeding [see Clinical Pharmacology ( 12.3 )] .
7.6Hydrochlorothiazide (HCTZ) Topiramate C max and AUC increased when HCTZ was added to immediate-release topiramate. The clinical significance of this change is unknown. The addition of HCTZ to topiramate extended-release capsules may require a decrease in the topiramate extended-release capsules dose [see Clinical Pharmacology (12.3) ] .
7.7Pioglitazone A decrease in the exposure of pioglitazone and its active metabolites were noted with the concurrent use of pioglitazone and immediate-release topiramate in a clinical trial. The clinical relevance of these observations is unknown; however, when topiramate extended-release capsules are added to pioglitazone therapy or pioglitazone is added to topiramate extended-release capsules therapy, careful attention should be given to the routine monitoring of patients for adequate control of their diabetic disease state [see Clinical Pharmacology ( 12.3 )] .
7.8Lithium An increase in systemic exposure of lithium following topiramate doses of up to 600 mg/day can occur. Lithium levels should be monitored when co-administered with high-dose topiramate extended-release capsules [see Clinical Pharmacology ( 12.3 )] .
7.9Amitriptyline Some patients may experience a large increase in amitriptyline concentration in the presence of topiramate extended-release capsules and any adjustments in amitriptyline dose should be made according to the patients’ clin…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antiepileptic drugs (AEDs), such as topiramate extended-release capsules, during pregnancy. Patients should be encouraged to enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry if they become pregnant. This registry is collecting information about the safety of antiepileptic drugs during pregnancy.
To enroll, patients can call the toll-free number 1-888-233-2334. Information about the North American Drug Pregnancy Registry can be found at http://www.aedpregnancyregistry.org/. Risk Summary Topiramate extended-release capsules can cause fetal harm when administered to a pregnant woman.
Data from pregnancy registries indicate that infants exposed to topiramate in utero have increased risk of major congenital malformations, including but not limited to cleft lip and/or cleft palate (oral clefts), and of being small for gestational age (SGA) [see Human Data] . SGA has been observed at all doses and appears to be dose-dependent. The prevalence of SGA is greater in infants of women who received higher doses of topiramate during pregnancy.
In addition, the prevalence of SGA in infants of women who continued topiramate use until later in pregnancy is higher compared to the prevalence in infants of women who stopped topiramate use before the third trimester. In multiple animal species, topiramate demonstrated developmental toxicity, including increased incidences of fetal malformations, in the absence of maternal toxicity at clinically relevant doses [see Animal Data] . All pregnancies have a background risk of birth defects, loss, or other adverse outcomes.
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies are 2 to 4% and 15 to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse reactions Consider the benefits and risks of topiramate when prescribing this drug to women of childbearing potential, particularly when topiramate is considered for a condition not usually associated with permanent injury or death.
Because of the risk of oral clefts to the fetus, which occur in the first trimester of pregnancy before many women know they are pregnant, all women of childbearing potential should be informed of the potential risk to the fetus from exposure to topiramate. Women who are planning a pregnancy should be counseled regarding the relative risks and benefits of topiramate use during pregnancy, and alternative therapeutic options should be considered for these patients. Labor or Delivery Although the effect of topiramate on labor and delivery in humans has not been established, the development of topiramate-induced metabolic acidosis in the mother and/or in the fetus might affect the fetus’ ability to tolerate labor.
Topiramate extended-release capsules treatment can cause metabolic acidosis [see Warnings and Precautions ( 5.4) ] . The effect of topiramate-induced metabolic acidosis has not been studied in pregnancy; however, metabolic acidosis in pregnancy (due to other causes) can cause decreased fetal growth, decreased fetal oxygenation, and fetal death, and may affect the fetus’ ability to tolerate labor. Pregnant patients should be monitored for metabolic acidosis and treated as in the nonpregnant state [see Warnings and Precautions (5.4 )] .
Newborns of mothers treated with topiramate extended-release capsules should be monitored for metabolic acidosis because of transfer of topiramate to the fetus and possible occurrence of transient metabolic acidosis following birth. Based on limited information, topiramate has also been associated with pre-term labor and premature delivery. Data Human Data Data from pregnancy registries indicate an incre…
🆘 Overdosage ▾
10 OVERDOSAGE Overdoses of topiramate have been reported. Signs and symptoms included convulsions, drowsiness, speech disturbance, blurred vision, diplopia, impaired mentation, lethargy, abnormal coordination, stupor, hypotension, abdominal pain, agitation, dizziness, and depression. The clinical consequences were not severe in most cases, but deaths have been reported after overdoses involving topiramate.
Topiramate overdose has resulted in severe metabolic acidosis [see Warnings and Precautions ( 5.4) ] . A patient who ingested a dose of immediate-release topiramate between 96 g and 110 g was admitted to a hospital with a coma lasting 20 to 24 hours followed by full recovery after 3 to 4 days. Similar signs, symptoms, and clinical consequences are expected to occur with overdosage of topiramate extended-release capsules.
In the event of overdose, topiramate extended-release capsules should be discontinued and general supportive treatment given until clinical toxicity has been diminished or resolved. Hemodialysis is an effective means of removing topiramate from the body.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The precise mechanisms by which topiramate exerts its anticonvulsant and preventive migraine effects are unknown; however, preclinical studies have revealed four properties that may contribute to topiramate’s efficacy for epilepsy and the preventive treatment of migraine. Electrophysiological and biochemical evidence suggests that topiramate, at pharmacologically relevant concentrations, blocks voltage-dependent sodium channels, augments the activity of the neurotransmitter gamma-aminobutyrate at some subtypes of the GABA-A receptor, antagonizes the AMPA/kainate subtype of the glutamate receptor, and inhibits the carbonic anhydrase enzyme, particularly isozymes II and IV.
12.2Pharmacodynamics Topiramate has anticonvulsant activity in rat and mouse maximal electroshock seizure (MES) tests. Topiramate is only weakly effective in blocking clonic seizures induced by the GABA-A receptor antagonist, pentylenetetrazole. Topiramate is also effective in rodent models of epilepsy, which include tonic and absence-like seizures in the spontaneous epileptic rat (SER) and tonic and clonic seizures induced in rats by kindling of the amygdala or by global ischemia.
Changes (increases and decreases) from baseline in vital signs (systolic blood pressure-SBP, diastolic blood pressure-DBP, pulse) occurred more frequently in pediatric patients (6 to 17 years) treated with various daily doses of topiramate (50 mg, 100 mg, 200 mg, 2 mg/kg to 3 mg/kg) than in patients treated with placebo in controlled trials for the preventive treatment of migraine. The most notable changes were SBP < 90 mm Hg, DBP < 50 mm Hg, SBP or DBP increases or decreases ≥ 20 mm Hg, and pulse increases or decreases ≥ 30 beats per minute.
These changes were often dose-related, and were most frequently associated with the greatest treatment difference at the 200 mg dose level. Systematic collection of orthostatic vital signs has not been conducted. The clinical significance of these various changes in vital signs has not been clearly established.
12.3Pharmacokinetics Absorption and Distribution Linear pharmacokinetics of topiramate from topiramate extended-release capsules were observed following a single oral dose over the range of 50 mg to 200 mg. At 25 mg, the pharmacokinetics of topiramate extended-release capsules are nonlinear possibly due to the binding of topiramate to carbonic anhydrase in red blood cells. The peak plasma concentrations (C max ) of topiramate occurred at approximately 24 hours following a single 200 mg oral dose of topiramate extended-release capsules.
At steady-state, the (AUC 0-24 , C max , and C min ) of topiramate from topiramate extended-release capsules administered once-daily and the immediate-release tablet administered twice-daily were shown to be bioequivalent. Fluctuation of topiramate plasma concentrations at steady-state for topiramate extended-release capsules administered once-daily was approximately 26% and 42% in healthy subjects and in epileptic patients, respectively, compared to approximately 40% and 51%, respectively, for immediate-release topiramate [see Clinical Pharmacology ( 12.6 )].
Compared to the fasted state, high-fat meal increased the C max of topiramate by 37% and shortened the T max to approximately 8 hours following a single dose of topiramate extended-release capsules, while having no effect on the AUC. Modeling of the observed single dose fed data with simulation to steady state showed that the effect on C max is significantly reduced following repeat administrations. Topiramate extended-release capsules can be taken without regard to meals.
Topiramate is 15% to 41% bound to human plasma proteins over the blood concentration range of 0.5 mcg/mL to 250 mcg/mL. The fraction bound decreased as blood concentration increased. Carbamazepine and phenytoin do not alter the binding of immediate-release topiramate.
Sodium valproate, at 500 mcg/mL (a concentration 5 to 10 times…
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Topiramate extended-release capsules are available in the following strength and colors: 200 mg (yellow opaque cap and white opaque body) topiramate extended-release capsules (black print “par” on the cap and “C368” on the body) Bottles of 30….NDC-10370-368-11 Bottles of 100…NDC-10370-368-01 Bottles of 500...NDC-10370-368-05
16.2Storage and Handling Topiramate extended-release capsules should be stored in well closed containers at 20º to 25°C (68º to 77°F) [see USP Controlled Room Temperature]. Protect from moisture and light.
16.1How Supplied Topiramate extended-release capsules are available in the following strength and colors: 200 mg (yellow opaque cap and white opaque body) topiramate extended-release capsules (black print “par” on the cap and “C368” on the body) Bottles of 30….NDC-10370-368-11 Bottles of 100…NDC-10370-368-01 Bottles of 500...NDC-10370-368-05
16.2Storage and Handling Topiramate extended-release capsules should be stored in well closed containers at 20º to 25°C (68º to 77°F) [see USP Controlled Room Temperature]. Protect from moisture and light.
📋 Description ▾
11 DESCRIPTION Topiramate, USP, is a sulfamate-substituted monosaccharide. Topiramate extended-release capsules are available as 200 mg capsules for oral administration. Topiramate, USP is a white to off-white powder.
Topiramate, USP is freely soluble in dichloromethane. Topiramate, USP has the molecular formula C 12 H 21 NO 8 S and a molecular weight of 339.36. Topiramate, USP is designated chemically as 2,3:4,5-Di- O -isopropylidene-β-D-fructopyranose sulfamate and has the following structural formula: Topiramate extended-release capsules are an extended-release capsule.
Topiramate extended-release capsules contain the following inactive ingredients: Sugar Spheres (contains sucrose and corn starch) Hypromellose Povidone Ethylcellulose Titanium Dioxide Talc The capsule shells contain gelatin, titanium dioxide and colorants. The colorants are: FD&C Red #40 FD&C Yellow #6 Capsule shells are imprinted with black print that contains shellac, black iron oxide, propylene glycol, FD&C red #40, FD&C blue #2, FD&C blue #1 and D&C yellow #10 Chemical_Structure.jpg
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Administration Instructions Counsel patients to swallow topiramate extended-release capsules whole and intact. Topiramate extended-release capsules should not be sprinkled on food, chewed, or crushed [see Dosage and Administration ( 2.7 )] .
Consumption of Alcohol Advise patients to completely avoid consumption of alcohol at least 6 hours prior to and 6 hours after taking topiramate extended-release capsules [see Warnings and Precautions ( 5.5 )] . Eye Disorders Advise patients taking topiramate extended-release capsules to seek immediate medical attention if they experience blurred vision, visual disturbances, or periorbital pain [see Warnings and Precautions ( 5.1 , 5.2 )] . Oligohydrosis and Hyperthermia Counsel patients that topiramate extended-release capsules, especially pediatric patients, can cause decreased sweating and increased body temperature, especially in hot weather, and they should seek medical attention if this is noticed [see Warnings and Precautions ( 5.3 )] .
Metabolic Acidosis Inform patients about the potentially significant risk for metabolic acidosis that may be asymptomatic and may be associated with adverse effects on kidneys (e.g., kidney stones, nephrocalcinosis), bones (e.g., osteoporosis, osteomalacia, and/or rickets in children), and growth (e.g., growth delay/retardation) in pediatric patients, and on the fetus [see Warnings and Precautions ( 5.4 )] . Suicidal Behavior and Ideation Counsel patients, their caregivers, and families that AEDs, including topiramate extended-release capsules, may increase the risk of suicidal thoughts and behavior and they should be advised of the need to be alert for the emergence or worsening of the signs and symptoms of depression, any unusual changes in mood or behavior or the emergence of suicidal thoughts, behavior, or thoughts about self-harm.
Behaviors of concern should be reported immediately to healthcare providers [see Warnings and Precautions ( 5.6 )] . Interference With Cognitive and Motor Performance Warn patients about the potential for somnolence, dizziness, confusion, difficulty concentrating, or visual effects and advise them not to drive or operate machinery until they have gained sufficient experience on topiramate extended-release capsules to gauge whether it adversely affects their mental performance, motor performance, and/or vision [see Warnings and Precautions ( 5.7 )] .
Advise patients that even when taking topiramate extended-release capsules or other anticonvulsants, some patients with epilepsy will continue to have unpredictable seizures. Therefore, counsel all patients taking topiramate extended-release capsules for epilepsy to exercise appropriate caution when engaging in any activities where loss of consciousness could result in serious danger to themselves or those around them (including swimming, driving a car, climbing in high places, etc.). Some patients with refractory epilepsy will need to avoid such activities altogether.
Physicians should discuss the appropriate level of caution with their patients, before patients with epilepsy engage in such activities. Fetal Toxicity Counsel pregnant women and women of childbearing potential that use of topiramate extended-release capsules during pregnancy can cause fetal harm. Topiramate extended-release capsules increases the risk of major congenital malformations, including but not limited to cleft lip and/or cleft palate (oral clefts), which occur early in pregnancy before many women know they are pregnant.
Also inform patients that infants exposed to topiramate monotherapy in utero may be SGA [see Use in Specific Populations ( 8.1 )] . There may also be risks to the fetus from chronic metabolic acidosis with use of topiramate extended-release capsules during pregnancy [see Warnings and Precautions ( 5.4 , 5.8 )] . When appropriate, prescribers should counsel pregnant women…
💬 Medication Guide ▾
MEDICATION GUIDE Topiramate (toe pyre’ a mate) Extended-Release Capsules What is the most important information I should know about topiramate extended-release capsules? Take topiramate extended-release capsules whole. Do not sprinkle topiramate extended-release capsules on food, or break, crush, dissolve, or chew topiramate extended-release capsules before swallowing.
If you cannot swallow topiramate extended-release capsules whole, tell your healthcare provider. You may need a different medicine. Do not drink alcohol within 6 hours prior to and 6 hours after topiramate extended-release capsules administration.
Topiramate extended-release capsules may cause eye problems. Serious eye problems include: any sudden decrease in vision with or without eye pain and redness, a blockage of fluid in the eye causing increased pressure in the eye (secondary angle closure glaucoma). These eye problems can lead to permanent loss of vision if not treated.
You should call your healthcare provider right away if you have any new eye symptoms, including any new problems with your vision. Topiramate extended-release capsules may cause decreased sweating and increased body temperature (fever). People, especially children, should be watched for signs of decreased sweating and fever, especially in hot temperatures.
Some people may need to be hospitalized for this condition. If a high fever, a fever that does not go away, or decreased sweating develops, call your healthcare provider right away. Topiramate extended-release capsules can increase the level of acid in your blood (metabolic acidosis).
If left untreated, metabolic acidosis can cause brittle or soft bones (osteoporosis, osteomalacia, osteopenia), kidney stones, can slow the rate of growth in children, and may possibly harm your baby if you are pregnant. Metabolic acidosis can happen with or without symptoms. Sometimes people with metabolic acidosis will: feel tired not feel hungry (loss of appetite) feel changes in heartbeat have trouble thinking clearly Your healthcare provider should do a blood test to measure the level of acid in your blood before and during your treatment with topiramate extended-release capsules.
If you are pregnant, you should talk to your healthcare provider about whether you have metabolic acidosis. Like other antiepileptic drugs, topiramate extended-release capsules may cause suicidal thoughts or actions in a very small number of people, about 1 in 500. Call a healthcare provider right away if you have any of these symptoms, especially if they are new, worse, or worry you: thoughts about suicide or dying trouble sleeping (insomnia) attempts to commit suicide new or worse irritability new or worse depression acting aggressive, being angry, or violent new or worse anxiety acting on dangerous impulses feeling agitated or restless an extreme increase in activity and talking (mania) panic attacks other unusual changes in behavior or mood Do not stop topiramate extended-release capsules without first talking to a healthcare provider.
Stopping topiramate extended-release capsules suddenly can cause serious problems. Suicidal thoughts or actions can be caused by things other than medicines. If you have suicidal thoughts or actions, your healthcare provider may check for other causes.
How can I watch for early symptoms of suicidal thoughts and actions? Pay attention to any changes, especially sudden changes in mood, behaviors, thoughts, or feelings. Keep all follow-up visits with your healthcare provider as scheduled.
Call your healthcare provider between visits as needed, especially if you are worried about symptoms. Topiramate extended-release capsules can harm your unborn baby. If you take topiramate extended-release capsules during pregnancy, your baby has a higher risk for birth defects including cleft lip and cleft palate.
These defects can begin early in pregnancy, even before you know you are pregnant. Birth defects may happen even in children born to women who are…