
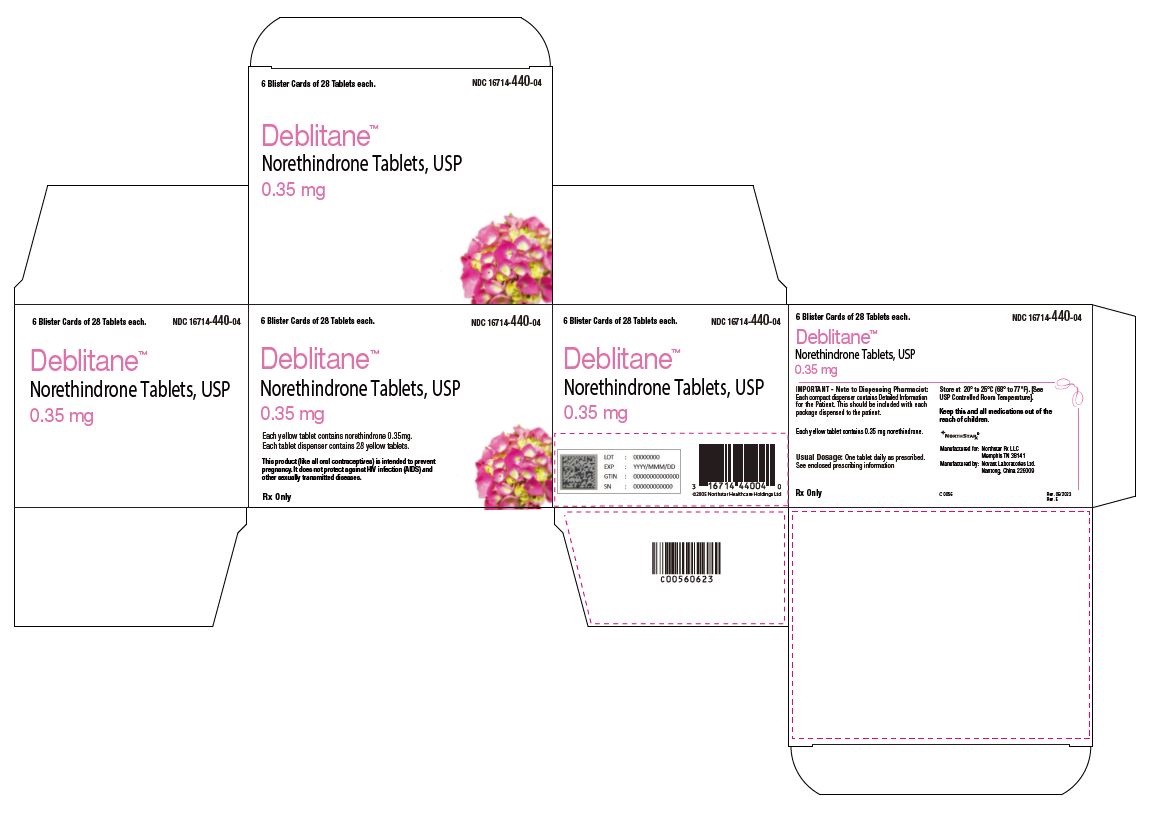
DEBLITANE Norethindrone Kit, 1 packet — NDC 16714-440-01 (Billing 16714-0440-01)
This is a package of 1 packet of DEBLITANE Norethindrone Kit from Northstar Rx LLC, marketed since Sep 2013 and currently FDA-listed; retail pharmacies pay about $0.0924 per packet (NADAC).
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 003313
- GCN: 11520
- GPI-14 (Medi-Span): 25100010000305
- HICL (First Databank): 001459
- AHFS class code: 68:12.00.00
- RxCUI (RxNorm): 198042
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Progestin class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Norethindrone is used to treat endometriosis (a condition in which the type of tissue that lines the uterus [womb] grows in other areas of the body and causes pain, heavy or irregular menstruation [periods], and other symptoms). Norethindrone is also used to treat abnormal periods or bleeding and to bring on a normal menstrual cycle in women who menstruated normally in the past but have not menstruated for at least 3 months and who are not pregnant or experiencing menopause (change of life; the end of monthly menstrual periods). Norethindrone is in a class of medications called progestins. It...
Read the full MedlinePlus article ↗- Most norethindrone products, like Errin, Camila and Emzahh, are progestin-only birth control pills that prevent pregnancy. Norethindrone acetate tablets, such as Gallifrey, are use...
- Take one tablet by mouth every day at the same time. Don't take a break between packs. Following the schedule exactly gives you the best protection, so follow your label and the pa...
- Changes in your bleeding are the most common, including irregular or frequent bleeding. Some people get headache, breast tenderness, nausea or dizziness. Call me or your doctor if...
- It's best not to. Smoking greatly raises the risk of heart attack and stroke in women using oral contraceptives. If you smoke, let's talk about options and quitting.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Norethindrone — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.092 | $0.09 / 1 kit |
| Medicaid paysCMS SDUD · 12 mo | $0.2844 | $0.28 / 1 kit |
| Medicare drug plans payPart D · Q2 2026 | $0.1328 | $0.13 / 1 kit |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 16714-0440-01 You're viewing this | 1 BLISTER PACK in 1 PACKET / 1 KIT in 1 BLISTER PACK | $0.0924 / ea | $0.09 | 2013-09-13 | — | Active |
| 16714-0440-02 16714-440-02 | 1 BLISTER PACK in 1 CARTON / 1 KIT in 1 BLISTER PACK | — | — | 2020-01-01 | — | Active |
| 16714-0440-03 16714-440-03 | 3 BLISTER PACK in 1 CARTON / 1 KIT in 1 BLISTER PACK | — | — | 2020-01-01 | — | Active |
| 16714-0440-04 16714-440-04 Main listing | 6 BLISTER PACK in 1 CARTON / 1 KIT in 1 BLISTER PACK | $0.0924 / ea | $0.55 | 2013-09-13 | — | Active |
This pack has the lowest per-ea cost of the 2 priced pack sizes ($0.0924 NADAC).
This pack accounts for about 1.5% of this product's recent Medicaid fills; most go to a different pack size. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 16714-0440-02?
What NDC number is used to bill for this package of DEBLITANE Norethindrone Kit?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Sharobel 16714-0441-01 | Northstar | 1 packet | $0.092 | AB2 | Availability likely | — |
| Deblitanethis 16714-0440-01 | Northstar | 1 packet | $0.092 | AB1 | Availability likely | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
Cigarette smoking greatly increases the possibility of suffering heart attacks and strokes. Women who use oral contraceptives are strongly advised not to smoke.
Cigarette smoking greatly increases the possibility of suffering heart attacks and strokes. Women who use oral contraceptives are strongly advised not to smoke.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE 1. Indications. Progestin-only oral contraceptives are indicated for the prevention of pregnancy. 2. Efficacy. If used perfectly, the first-year failure rate for progestin-only oral contraceptives is 0.5%. However, the typical failure rate is estimated to be closer to 5%, due to late or omitted pills. The following table lists the pregnancy rates for users of all major methods of contraception.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION To achieve maximum contraceptive effectiveness, DEBLITANE TM must be taken exactly as directed. One tablet is taken every day, at the same time. Administration is continuous, with no interruption between pill packs. See PATIENT LABELING for detailed instructions.
⛔ Contraindications ▾
CONTRAINDICATIONS Progestin-only oral contraceptives (POPs) should not be used by women who currently have the following conditions: Known or suspected pregnancy Known or suspected carcinoma of the breast Undiagnosed abnormal genital bleeding Hypersensitivity to any component of this product Benign or malignant liver tumors Acute liver disease
⚠️ Warnings ▾
WARNINGS Cigarette smoking greatly increases the possibility of suffering heart attacks and strokes. Women who use oral contraceptives are strongly advised not to smoke. DEBLITANE TM does not contain estrogen and, therefore, this insert does not discuss the serious health risks that have been associated with the estrogen component of combined oral contraceptives.
The health care provider is referred to the prescribing information of combined oral contraceptives for a discussion of those risks, including, but not limited to, an increased risk of serious cardiovascular disease in women who smoke, carcinoma of the breast and reproductive organs, hepatic neoplasia, and changes in carbohydrate and lipid metabolism. The relationship between progestin-only oral contraceptives and these risks have not been established and there are no studies definitely linking progestin-only pill (POP) use to an increased risk of heart attack or stroke.
The physician should remain alert to the earliest manifestation of symptoms of any serious disease and discontinue oral contraceptive therapy when appropriate. 1. Ectopic Pregnancy The incidence of ectopic pregnancies for progestin-only oral contraceptive users is 5 per 1000 woman-years.
Up to 10% of pregnancies reported in clinical studies of progestin-only oral contraceptive users are extrauterine. Although symptoms of ectopic pregnancy should be watched for, a history of ectopic pregnancy need not be considered a contraindication to use of this contraceptive method. Health providers should be alert to the possibility of an ectopic pregnancy in women who become pregnant or complain of lower abdominal pain while on progestin-only oral contraceptives.
2. Delayed follicular atresia/Ovarian cysts If follicular development occurs, atresia of the follicle is sometimes delayed, and the follicle may continue to grow beyond the size it would attain in a normal cycle. Generally these enlarged follicles disappear spontaneously.
Often they are asymptomatic; in some cases they are associated with mild abdominal pain. Rarely they may twist or rupture, requiring surgical intervention. 3.
Irregular genital bleeding Irregular menstrual patterns are common among women using progestin-only oral contraceptives. If genital bleeding is suggestive of infection, malignancy or other abnormal conditions, such nonpharmacologic causes should be ruled out. If prolonged amenorrhea occurs, the possibility of pregnancy should be evaluated.
4. Carcinoma of the breast and reproductive organs Some epidemiologic studies of oral contraceptive users have reported an increased relative risk of developing breast cancer, particularly at a younger age and apparently related to duration of use. These studies have predominantly involved combined oral contraceptives and there is insufficient data to determine whether the use of POPs similarly increase the risk.
Women with breast cancer should not use oral contraceptives because the role of female hormone in breast cancer has not been fully determined. Some studies suggest that oral contraceptive use has been associated with an increase in the risk of cervical intraepithelial neoplasia in some populations of women. However, there continues to be controversy about the extent to which such findings may be due to differences in sexual behavior and other factors.
There is insufficient data to determine whether the use of POPs increases the risk of developing cervical intraepithelial neoplasia. 5. Hepatic Neoplasia Benign hepatic adenomas are associated with combined oral contraceptive use, although the incidence of benign tumors is rare in the United States.
Rupture of benign, hepatic adenomas may cause death through intraabdominal hemorrhage. Studies from Britain and the U.S. have shown an increased risk of developing hepatocellular carcinoma in combined oral contraceptive users. However, these cancers are rare.
There is insufficient data to determine whether POPs increase the risk of developing h… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Menstrual irregularity is the most frequently reported side effect. Frequent and irregular bleeding are common, while long duration of bleeding episodes and amenorrhea are less likely. Headache, breast tenderness, nausea, and dizziness are increased among progestin-only oral contraceptive users in some studies. Androgenic side effects such as acne, hirsutism, and weight gain occur rarely.
🆘 Overdosage ▾
OVERDOSAGE There have been no reports of serious ill effects from overdosage, including ingestion by children.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY 1. Mode of Action DEBLITANE TM progestin-only oral contraceptives prevent conception by suppressing ovulation in approximately half of users, thickening the cervical mucus to inhibit sperm penetration, lowering the mid-cycle LH and FSH peaks, slowing the movement of the ovum through the fallopian tubes, and altering the endometrium. 2.
Pharmacokinetics Absorption: Norethindrone is rapidly absorbed with maximum plasma concentrations occurring within 1 to 2 hours after DEBLITANE TM administration (see Table 1). Norethindrone appears to be completely absorbed following oral administration; however, it is subject to first pass metabolism resulting in an absolute bioavailability of approximately 65%. Peak plasma concentrations occur approximately 1 hour after administration (mean T max 1.2 hours).
The mean (SD) C max was 4816.8 (1532.6) pg/mL and generally occurred within 1 hour (mean) of tablet administration, ranging from 0.5 to 2 hours. The mean (SD) C avg was 885 (250) pg/mL, however, the mean concentration at 24 hrs was 130 (47) pg/mL. Table 1 provides summary statistics of the pharmacokinetic parameters associated with single dose Norethindrone Tablets administration.
The food effect on the rate and extent of norethindrone absorption after DEBLITANE TM administration has not been evaluated. Distribution: Following oral administration, norethindrone is 36% bound to sex hormone-binding globulin (SHBG) and 61% bound to albumin. Volume of distribution of norethindrone is approximately 4 L/kg.
Metabolism: Norethindrone undergoes extensive biotransformation, primarily via reduction, followed by sulfate and glucuronide conjugation; less than 5% of a norethindrone dose is excreted unchanged; greater than 50% and 20 to 40% of a dose is excreted in urine and feces, respectively. The majority of metabolites in the circulation are sulfate, with glucuronides accounting for most of the urinary metabolites. Excretion: Plasma clearance rate for norethindrone has been estimated to be approximately 600 L/day.
Norethindrone is excreted in both urine and feces, primarily as metabolites. The mean terminal elimination half-life of norethindrone following single dose administration of Norethindrone Tablet is approximately 8 hours. Figure 1
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED DEBLITANE TM (Norethindrone Tablets, USP) contain 28 round yellow tablets in a blister card (NDC 16714-440-01). Each yellow tablet, debossed with “K2” on one side, contains 0.35 mg norethindrone. DEBLITANE TM tablets are available in the following configurations: Carton of 1 NDC 16714-440-02 Carton of 3 NDC 16714-440-03 Carton of 6 NDC 16714-440-04 STORAGE Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature].
📋 Description ▾
DESCRIPTION Each yellow DEBLITANE TM tablet provides a continuous oral contraceptive regimen of 0.35 mg norethindrone daily, and the inactive ingredients include polyvinyl alcohol, titanium dioxide, talc, macrogol/polyethylene glycol 3350 NF, D&C Yellow No. 10 Aluminum Lake, lecithin (soya), FD&C Red No. 40 Aluminum Lake, FD&C Blue No.
2 Aluminum Lake, lactose monohydrate, magnesium stearate, and pregelatinized starch. The chemical name for norethindrone is 17-Hydroxy-19-Nor-17-alpha-pregn-4-en-20-yn-3-one. The structural formula follows: Therapeutic class = Oral Contraceptive Norethindrone Structure
⚠️ Precautions ▾
PRECAUTIONS 1. General Patients should be counseled that oral contraceptives do not protect against transmission of HIV (AIDS) and other sexually transmitted diseases (STDs) such as Chlamydia, genital herpes, genital warts, gonorrhea, hepatitis B, and syphilis. 2.
Physical examination and follow up It is considered good medical practice for sexually active women using oral contraceptives to have annual history and physical examinations. The physical examination may be deferred until after initiation of oral contraceptives if requested by the woman and judged appropriate by the clinician. 3.
Carbohydrate and Lipid Metabolism Some users may experience slight deterioration in glucose tolerance, with increases in plasma insulin, but women with diabetes mellitus who use progestin-only oral contraceptives do not generally experience changes in their insulin requirements. Nonetheless, prediabetic and diabetic women in particular should be carefully monitored while taking POPs. Lipid metabolism is occasionally affected in that HDL, HDL 2 , and apolipoprotein A-I and A-II may be decreased; hepatic lipase may be increased.
There is no effect on total cholesterol, HDL 3 , LDL, or VLDL. 4. Drug Interactions Change in contraceptive effectiveness associated with co-administration of other products: a.
Anti-infective agents and anticonvulsants . Contraceptive effectiveness may be reduced when hormonal contraceptives are co-administered with antibiotics, anticonvulsants, and other drugs that increase the metabolism of contraceptive steroids. This could result in unintended pregnancy or breakthrough bleeding.
Examples include rifampin, barbiturates, phenylbutazone, phenytoin, carbamazepine, felbamate, oxcarbazepine, topiramate, and griseofulvin. b. Anti-HIV protease inhibitors . Several of the anti-HIV protease inhibitors have been studied with co-administration of oral contraceptives; significant changes (increase and decrease) in the plasma levels of the estrogen and progestin have been noted in some cases.
The safety and efficacy of OC products may be affected with the co-administration of anti-HIV protease inhibitors. Health care providers should refer to the label of the individual anti-HIV protease inhibitors for further drug-drug interaction information. c. Herbal products .
Herbal products containing St. John's Wort (hypericum perforatum) may induce hepatic enzymes (cytochrome P450) and p-glycoprotein transporter and may reduce the effectiveness of contraceptive steroids. This may also result in breakthrough bleeding.
5. Interactions with Laboratory Tests The following endocrine tests may be affected by progestin-only oral contraceptive use: Sex hormone-binding globulin (SHBG) concentrations may be decreased. Thyroxine concentrations may be decreased, due to a decrease in thyroid binding globulin (TBG).
6. Carcinogenesis See WARNINGS section. 7.
Pregnancy Many studies have found no effects on fetal development associated with long-term use of contraceptive doses of oral progestins. The few studies of infant growth and development that have been conducted have not demonstrated significant adverse effects. It is nonetheless prudent to rule out suspected pregnancy before initiating any hormonal contraceptive use.
8. Nursing Mothers Small amounts of progestin pass into the breast milk, resulting in steroid levels in infant plasma of 1 - 6% of the levels of maternal plasma. 6 However, isolated post-market cases of decreased milk production have been reported in POPs.
Very rarely, adverse effects in the infant/child have been reported, including jaundice. 9. Fertility Following Discontinuation The limited available data indicate a rapid return of normal ovulation and fertility following discontinuation of progestin-only oral contraceptives.
10. Headache/Migraine If you have a headache or a worsening migraine headache with a new pattern that is recurrent, persistent, or severe, this requires discontinuation of oral contraceptives and evaluati… [Excerpted — this section continues on DailyMed.]
📄 Patient Package Insert ▾
DETAILED INFORMATION FOR THE PATIENT Patients should be counseled that oral contraceptives do not protect against transmission of HIV (AIDS) and other sexually transmitted diseases (STDs) such as Chlamydia, genital herpes, genital warts, gonorrhea, hepatitis B, and syphilis. INTRODUCTION This leaflet is about birth control pills that contain one hormone, a progestin. Please read this leaflet before you begin to take your pills.
It is meant to be used along with talking with your doctor or clinic. Progestin-only pills are often called "POPs" or "the minipill." POPs have less progestin than the combined birth control pill (or "the pill") which contains both an estrogen and a progestin. HOW EFFECTIVE ARE POPS?
About 1 in 200 (0.5%) POPs users will get pregnant in the first year if they all take POPs perfectly (that is, on time, every day). About 1 in 20 (5%) "typical" POPs users (including women who are late taking pills or miss pills) gets pregnant in the first year of use. The following table will help you compare the efficacy of different methods.
HOW DO POPS WORK? They make the cervical mucus at the entrance to the womb (the uterus) too thick for the sperm to get through to the egg. They prevent ovulation (release of the egg from the ovary) in about half the time.
They also affect other hormones, the fallopian tubes and the lining of the uterus. YOU SHOULD NOT TAKE POPS If there is any chance you may be pregnant. If you have breast cancer.
If you have bleeding between your periods which has not been diagnosed. If you are taking certain drugs for epilepsy (seizures) or for TB. (See USING POPS WITH OTHER MEDICINES below.) If you are hypersensitive or allergic to any component of this product.
If you have liver tumors, either benign or cancerous. If you have acute liver disease. RISKS OF TAKING POPS WARNING: If you have sudden or severe pain in your lower abdomen or stomach area, you may have an ectopic pregnancy or an ovarian cyst.
If this happens, you should contact your doctor or clinic immediately. 1. Ectopic pregnancy.
An ectopic pregnancy is a pregnancy outside the womb. Because POPs protect against pregnancy, the chance of having pregnancy outside the womb is very low. If you do get pregnant while taking POPs, you have a slightly higher chance that the pregnancy will be ectopic than do users of some other birth control methods.
2. Ovarian cysts. These cysts are small sacs of fluid in the ovary.
They are more common among POP users than among users of most other birth control methods. They usually disappear without treatment and rarely cause problems. 3.
Cancer of the reproductive organs and breasts. Some studies in women who use combined oral contraceptives that contain both estrogen and a progestin have reported an increase in the risk of developing breast cancer, particularly at a younger age and apparently related to duration of use. There is insufficient data to determine whether the use of POPs similarly increases this risk.
Some studies have found an increase in the incidence of cancer of the cervix in women who use oral contraceptives. However, this finding may be related to factors other than the use of oral contraceptives and there is insufficient data to determine whether the use of POPs increases the risk of developing cancer of the cervix. 4.
Liver tumors. In rare cases, combined oral contraceptives can cause benign but dangerous liver tumors. These benign liver tumors can rupture and cause fatal internal bleeding.
In addition, a possible but not definite association has been found with combined oral contraceptives and liver cancers in studies in which a few women who developed these very rare cancers were found to have used combined oral contraceptives for long periods of time. There is insufficient data to determine whether POPs increase the risk of liver tumors. SEXUALLY TRANSMITTED DISEASES (STDS) WARNING: POPs do not protect against getting or giving someone HIV (AIDS) or any other STD, such as Chlamydia,… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL DEBLITANE (Norethindrone Tablet USP, 0.35 mg) 6-cycle Carton Table 1 Table 2 Table IUD
Medicaid utilization & spend
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |