
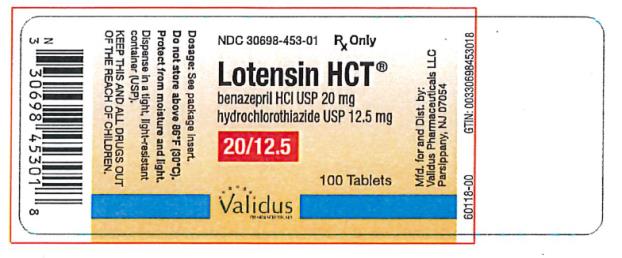
Lotensin HCT benazepril hydrochloride and hydrochlorothiazide 20 mg; 12.5 mg Tablet, 100-count — NDC 30698-453-01 (Billing 30698-0453-01)
This is a package of 100 tablets of Lotensin HCT benazepril hydrochloride and hydrochlorothiazide 20 mg; 12.5 mg Tablet from Validus Pharmaceuticals LLC, marketed since May 1992 and currently FDA-listed. It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 021725
- GCN: 33193
- GPI-14 (Medi-Span): 36991802150330
- HICL (First Databank): 008962
- AHFS class code: 24:32.04.00
- RxCUI (RxNorm): 898362
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Angiotensin Converting Enzyme Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
The combination of benazepril and hydrochlorothiazide is used to treat high blood pressure. Benazepril is in a class of medications called angiotensin-converting enzyme (ACE) inhibitors. It works by decreasing certain chemicals that tighten the blood vessels, so blood flows more smoothly. Hydrochlorothiazide is in a class of medications called diuretics ('water pills'). It works by causing the kidneys to get rid of unneeded water and salt from the body into the urine. High blood pressure is a common condition, and when not treated it can cause damage to the brain, heart, blood vessels, kidneys...
Read the full MedlinePlus article ↗- It treats high blood pressure. It combines two medicines that work in different ways. It is not usually the first medicine tried.
- Take it by mouth once a day, with or without food. Follow your prescriber's directions. Your doctor may adjust your dose after a few weeks.
- Tiredness, dizziness (especially when standing), headache, and a dry cough are the most common. Most are mild and short-lived. Call your doctor if they bother you or don't go away.
- Get help right away for swelling of your face, lips, tongue, or throat, or trouble breathing. Also call for fainting, yellow skin or eyes, sudden vision changes or eye pain, or sev...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 30698-0453-01 You're viewing this Main listing | 100 TABLET in 1 BOTTLE | 1992-05-30 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Benazepril Hydrochloride and Hydrochlorothiazide 20 mg/1; 12.5 mg 00185-0211-01 | Sandoz | 100 tablets | $0.222 | AB | Availability likely | — |
| benazepril hydrochloride and hydrochlorothiazide 20 mg/1; 12.5 mg 00574-0229-01 | Padagis | 100 tablets | $0.222 | AB | Availability likely | — |
| Benazepril Hydrochloride and Hydrochlorothiazide 20 mg/1; 12.5 mg 62559-0416-01 | ANI | 100 tablets | $0.222 | AB | Availability likely | — |
| Benazepril Hydrochloride and Hydrochlorothiazide 20 mg/1; 12.5 mg 68462-0578-01 | Glenmark | 100 tablets | $0.222 | AB | Availability likely | — |
| benazepril hydrochloride and hydrochlorothiazide 20 mg/1; 12.5 mg 72888-0221-01 | Advagen | 100 tablets | $0.222 | AB | Availability likely | — |
| Lotensin HCT 20 mg/1; 12.5 mgthis 30698-0453-01 | Validus | 100 tablets | — | AB | FDA listed | — |
| benazepril hydrochloride and hydrochlorothiazide 20 mg/1; 12.5 mg 72162-2328-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII ZF94AP8MEY
Hydrogenated castor oil is a processed plant oil made by adding hydrogen to castor oil. It's used as a binder to help hold tablet ingredients together and as a lubricant to prevent sticking during manufacturing.
-
UNII J2B2A4N98G
Lactose is a natural sugar derived from milk. In medications, it serves as a filler and binder to add bulk and help hold tablet or capsule ingredients together during manufacturing.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY When pregnancy is detected, discontinue Lotensin HCT as soon as possible. Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus (see WARNINGS: Fetal Toxicity ).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Lotensin HCT USP is indicated for the treatment of hypertension. This fixed combination drug is not indicated for the initial therapy of hypertension ( see DOSAGE AND ADMINISTRATION ).
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Dose once daily. The dosage may then be increased after 2 to 3 weeks as needed to help achieve blood pressure goals. The maximum recommended dose is 20/25 mg.
Switch Therapy: A patient whose blood pressure is not adequately controlled with benazepril alone or with hydrochlorothiazide alone may be switched to combination therapy with Lotensin HCT. The usual recommended starting dose is 10/12.5 mg once daily to control blood pressure. Replacement Therapy: The combination may be substituted for the titrated individual components.
⛔ Contraindications ▾
CONTRAINDICATIONS Lotensin HCT is contraindicated in patients who are anuric. Lotensin HCT is also contraindicated in patients who are hypersensitive to benazepril, to any other ACE inhibitor, to hydrochlorothiazide, or to other sulfonamide-derived drugs. Hypersensitivity reactions are more likely to occur in patients with a history of allergy or bronchial asthma.
Lotensin HCT is also contraindicated in patients with a history of angioedema with or without previous ACE inhibitor treatment. Lotensin HCT is contraindicated in combination with a neprilysin inhibitor (e.g., sacubitril). Do not administer Lotensin HCT within 36 hours of switching to or from sacubitril/valsartan, a neprilysin inhibitor (see WARNINGS and PRECAUTIONS ).
Do not coadminister aliskiren with angiotensin receptor blockers, ACE inhibitors, including Lotensin HCT in patients with diabetes.
⚠️ Warnings ▾
WARNINGS Anaphylactoid and Possibly Related Reactions Presumably because angiotensin-converting enzyme inhibitors affect the metabolism of eicosanoids and polypeptides, including endogenous bradykinin, patients receiving ACE inhibitors (including benazepril) may be subject to a variety of adverse reactions, some of them serious. Head and Neck Angioedema: Angioedema of the face, extremities, lips, tongue, glottis, and larynx has been reported in patients treated with angiotensin-converting enzyme inhibitors. In U.S. clinical trials, symptoms consistent with angioedema were seen in none of the subjects who received placebo and in about 0.5% of the subjects who received benazepril.
Angioedema associated with laryngeal edema can be fatal. If laryngeal stridor or angioedema of the face, tongue, or glottis occurs, treatment with Lotensin HCT should be discontinued and appropriate therapy instituted immediately. When involvement of the tongue, glottis, or larynx appears likely to cause airway obstruction, appropriate therapy, e.g., subcutaneous epinephrine injection 1:1000 (0.3 - 0.5 mL) should be promptly administered ( see PRECAUTIONS and ADVERSE REACTIONS ).
Black patients receiving ACE inhibitors have been reported to have a higher incidence of angioedema compared to nonblacks. Patients receiving coadministration of ACE inhibitor and mTOR (mammalian target of rapamycin) inhibitor (e.g., tesmsirolimus, sirolimus, everolimus) therapy or a neprilysin inhibitor may be at increased risk for angioedema (see PRECAUTIONS ) . Intestinal Angioedema: Intestinal angioedema has been reported in patients treated with ACE inhibitors.
These patients presented with abdominal pain (with or without nausea or vomiting); in some cases there was no prior history of facial angioedema and C-1 esterase levels were normal. The angioedema was diagnosed by procedures including abdominal CT scan or ultrasound, or at surgery, and symptoms resolved after stopping the ACE inhibitor. Intestinal angioedema should be included in the differential diagnosis of patients on ACE inhibitors presenting with abdominal pain.
Anaphylactoid Reactions During Desensitization: Two patients undergoing desensitizing treatment with hymenoptera venom while receiving ACE inhibitors sustained life-threatening anaphylactoid reactions. In the same patients, these reactions were avoided when ACE inhibitors were temporarily withheld, but they reappeared upon inadvertent rechallenge. Anaphylactoid Reactions During Membrane Exposure: Anaphylactoid reactions have been reported in patients dialyzed with high-flux membranes and treated concomitantly with an ACE inhibitor.
Anaphylactoid reactions have also been reported in patients undergoing low-density lipoprotein apheresis with dextran sulfate absorption. Hypersensitivity reactions to hydrochlorothiazide are more likely in patients with allergy and asthma. Hypotension Lotensin HCT can cause symptomatic hypotension.
Like other ACE inhibitors, benazepril has been only rarely associated with hypotension in uncomplicated hypertensive patients. Symptomatic hypotension is most likely to occur in patients who have been volume and/or salt depleted as a result of prolonged diuretic therapy, dietary salt restriction, dialysis, diarrhea, or vomiting. Volume and/or salt depletion should be corrected before initiating therapy with Lotensin HCT.
Lotensin HCT should be used cautiously in patients receiving concomitant therapy with other antihypertensives. The thiazide component of Lotensin HCT may potentiate the action of other antihypertensive drugs, especially ganglionic or peripheral adrenergic-blocking drugs. The antihypertensive effects of the thiazide component may also be enhanced in the postsympathectomy patient.
In patients with congestive heart failure, with or without associated renal insufficiency, ACE inhibitor therapy may cause excessive hypotension, which may be associated with oliguria, azotemia, and (rarely) with acute renal failure and d… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Lotensin HCT has been evaluated for safety in over 2500 patients with hypertension; over 500 of these patients were treated for at least 6 months, and over 200 were treated for more than 1 year. The reported side effects were generally mild and transient, and there was no relationship between side effects and age, sex, race, or duration of therapy. Discontinuation of therapy due to side effects was required in approximately 7% of U.S. patients treated with Lotensin HCT and in 4% of patients treated with placebo.
The most common reasons for discontinuation of therapy with Lotensin HCT in U.S. studies were cough (1.0%; see PRECAUTIONS ) , “dizziness” (1.0%), headache (0.6%), and fatigue (0.6%). The side effects considered possibly or probably related to study drug that occurred in U.S. placebo-controlled trials in more than 1% of patients treated with Lotensin HCT are shown in the table below. Reactions Possibly or Probably Drug Related Patients in U.S.
Placebo-Controlled Studies LOTENSIN HCT N = 665 Placebo N = 235 N % N % “Dizziness” 41 6.3 8
3.4Fatigue 34 5.2 6
2.6Postural Dizziness 23 3.5 1
0.4Headache 20 3.1 10
4.3Cough 14 2.1 3
1.3Hypertonia 10 1.5 3
1.3Vertigo 10 1.5 2
0.9Nausea 9 1.4 2
0.9Impotence 8 1.2 0
0.0Somnolence 8 1.2 1
0.4Other side effects considered possibly or probably related to study drug that occurred in U.S. placebo-controlled trials in 0.3% to 1.0% of patients treated with Lotensin HCT were the following: Cardiovascular: Palpitations, flushing. Gastrointestinal: Vomiting, diarrhea, dyspepsia, anorexia, and constipation. Neurologic and Psychiatric: Insomnia, nervousness, paresthesia, libido decrease, dry mouth, taste perversion, and tinnitus.
Dermatologic: Rash and sweating. Other: Urinary frequency, arthralgia, myalgia, asthenia, and pain (including chest pain and abdominal pain). Other adverse experiences reported in 0.3% or more of Lotensin HCT patients in U.S. controlled clinical trials, and rarer events seen in post-marketing experience, were the following; asterisked entries occurred in more than 1% of patients (in some, a causal relationship to Lotensin HCT is uncertain): Cardiovascular: Syncope, peripheral vascular disorder, and tachycardia.
Body as a Whole: Infection, back pain*, flu syndrome*, fever, chills, and neck pain. Dermatologic: Photosensitivity and pruritus. Gastrointestinal: Gastroenteritis, flatulence, and tooth disorder.
Neurologic and Psychiatric: Hypesthesia, abnormal vision, abnormal dreams, and retinal disorder. Respiratory: Upper respiratory infection*, epistaxis, bronchitis, rhinitis*, sinusitis*, and voice alteration. Other: Conjunctivitis, arthritis, urinary tract infection, alopecia, and urinary frequency*.
Post-Marketing Experience The following adverse reactions have been identified during post-approval use of either benazepril or hydrochlorothiazide. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to estimate their frequency or establish a causal relationship to drug exposure: Non-melanoma Skin Cancer: Hydrochlorothiazide is associated with an increased risk of non-melanoma skin cancer. In a study conducted in the Sentinel System, increased risk was predominantly for squamous cell carcinoma (SCC) and in white patients taking large cumulative doses.
The increased risk for SCC in the overall population was approximately 1 additional case per 16,000 patients per year, and for white patients taking a cumulative dose of ≥50,000mg the risk increase was approximately 1 additional SCC case for every 6,700 patients per year. Benazepril Stevens-Johnson syndrome, pancreatitis, hemolytic anemia, pemphigus, and thrombocytopenia, eosinophilic pneumonitis Hydrochlorothiazide Digestive: Pancreatitis, small bowel angioedema, jaundice (intrahepatic cholestatic), sialadenitis, vomiting, diarrhea, cramping, nausea, gastric irritation, constipation, and anorexia.
Neurologic: Vertigo, lightheadedness, t… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
Drug Interactions Neprilysin Inhibitors: Patients taking concomitant neprilysin inhibitors may be at increased risk for angioedema. Interactions Common for Both Benazepril and Hydrochlorothiazide Potassium Supplements and Potassium -Sparing Diuretics: Concomitant use with Lotensin HCT may effect potassium levels. Monitor potassium periodically. mTOR (mammalian target of rapamycin) inhibitor s : Patients receiving coadministration of ACE inhibitor and mTOR inhibitor (e.g., temsirolimus, sirolimus, everolimus) therapy may be at increased risk for angioedema ( see WARNINGS ).
Lithium: Renal clearance of lithium is reduced by thiazides and increase the risk of lithium toxicity. Increased serum lithium levels and symptoms of lithium toxicity have been reported in patients receiving ACE inhibitors during therapy with lithium. Monitor lithium levels when used concomitantly with Lotensin HCT.
Dual Blockade of the Renin-Angiotensin System (RAS): Dual Blockade of the RAS with angiotensin receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypertension, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy. Most patients receiving the combination of two RAS inhibitors do not obtain any additional benefit compared to monotherapy. In general, avoid combined use of RAS inhibitors.
Closely monitor blood pressure, renal function and electrolytes in patients on Lotensin HCT and other agents that affect the RAS. Do not coadminister aliskiren with Lotensin HCT in patients with diabetes. Avoid use of aliskiren with Lotensin HCT in patients with renal impairment (GFR < 60 mL/min).
NSAIDs and Cox-2 selective agents: In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, coadministration of NSAIDs, including selective COX-2 inhibitors, with ACE inhibitors, including benazepril, may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible. Monitor renal function periodically in patients receiving benazepril and NSAID therapy.
The antihypertensive effect of benazepril and hydrochlorothiazide may be attenuated by NSAIDs. Benazepril Benazepril has been used concomitantly with beta-adrenergic-blocking agents, calcium-blocking agents, cimetidine, diuretics, digoxin, hydralazine, and naproxen without evidence of clinically important adverse interactions. Other ACE inhibitors have had less than additive effects with beta-adrenergic blockers, presumably because drugs of both classes lower blood pressure by inhibiting parts of the renin-angiotensin system.
Interaction studies with warfarin and acenocoumarol have failed to identify any clinically important effects of benazepril on the serum concentrations or clinical effects of these anticoagulants. Gold: Nitritoid reactions (symptoms include facial flushing, nausea, vomiting and hypotension) have been reported rarely in patients on therapy with injectable gold (sodium aurothiomalate) and concomitant ACE inhibitor therapy. Hydrochlorothiazide Ion exchange resins: Stagger the dosage of hydrochlorothiazide and ion exchange resins such that hydrochlorothiazide is administered at least 4 hours before or 4 to 6 hours after the administration of resins.
Single doses of either cholestyramine or colestipol resins bind the hydrochlorothiazide and reduce its absorption from the gastrointestinal tract by up to 85% and 43%, respectively. Digitalis glycosides: Thiazide-induced hypokalemia or hypomagnesemia may predispose the patients to digoxin toxicity Skeletal muscle relaxants: Possible increased responsiveness to muscle relaxants such as curare derivatives. Antidiabetic agents: Dosage adjustment of antidiabetic drug may be required.
Antineoplastic agents (e.g., cyclophosphamide, methotrexate) : Concomitant use of thiazide diuretics may reduce renal excretion of cytotoxic agents and enhance their myelosuppressive eff… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
Pediatric Use Neonates with a history of in utero exposure to Lotensin HCT : If oliguria or hypotension occurs, direct attention toward support of blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and/or substituting for disordered renal function. Benazepril, which crosses the placenta, can theoretically be removed from the neonatal circulation by these means; there are occasional reports of benefit from these maneuvers with another ACE inhibitor, but experience is limited.
Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
Geriatric Use Of the total number of patients who received Lotensin HCT in U.S. clinical studies of Lotensin HCT, 19% were 65 or older while about 1.5% were 75 or older. Overall differences in effectiveness or safety were not observed between these patients and younger patients. A limited amount of data suggests that the systemic clearance of hydrochlorothiazide is reduced in both healthy and hypertensive elderly subjects compared to young healthy volunteers.
🆘 Overdosage ▾
OVERDOSAGE No specific information is available on the treatment of overdosage with Lotensin HCT; treatment should be symptomatic and supportive. Therapy with Lotensin HCT should be discontinued, and the patient should be observed. Dehydration, electrolyte imbalance, and hypotension should be treated by established procedures.
Single oral doses of 1 g/kg of benazepril caused reduced activity in mice, and doses of 3 g/kg were associated with significant lethality. Reduction of activity in rats was not seen until they had received doses of 5 g/kg, and doses of 6 g/kg were not lethal. In single-dose studies of hydrochlorothiazide, most rats survived doses up to 2.75 g/kg.
Data from human overdoses of benazepril are scanty, but the most common manifestation of human benazepril overdosage is likely to be hypotension. In human hydrochlorothiazide overdose, the most common signs and symptoms observed have been those of dehydration and electrolyte depletion (hypokalemia, hypochloremia, hyponatremia). If digitalis has also been administered, hypokalemia may accentuate cardiac arrhythmias.
Laboratory determinations of serum levels of benazepril and its metabolites are not widely available, and such determinations have, in any event, no established role in the management of benazepril overdose. No data are available to suggest physiological maneuvers (e.g., maneuvers to change the pH of the urine) that might accelerate elimination of benazepril and its metabolites. Benazeprilat is only slightly dialyzable, but dialysis might be considered in overdosed patients with severely impaired renal function ( see WARNINGS ).
Angiotensin II could presumably serve as a specific antagonist-antidote in the setting of benazepril overdose, but angiotensin II is essentially unavailable outside of scattered research facilities. Because the hypotensive effect of benazepril is achieved through vasodilation and effective hypovolemia, it is reasonable to treat benazepril overdose by infusion of normal saline solution.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Benazepril and benazeprilat inhibit angiotensin-converting enzyme (ACE) in human subjects and in animals. ACE is a peptidyl dipeptidase that catalyzes the conversion of angiotensin I to the vasoconstrictor substance, angiotensin II. Angiotensin II also stimulates aldosterone secretion by the adrenal cortex.
Inhibition of ACE results in decreased plasma angiotensin II, which leads to decreased vasopressor activity and to decreased aldosterone secretion. The latter decrease may result in a small increase of serum potassium. Hypertensive patients treated with benazepril alone for up to 52 weeks had elevations of serum potassium of up to 0.2 mEq/L.
Similar patients treated with benazepril and hydrochlorothiazide for up to 24 weeks had no consistent changes in their serum potassium ( see PRECAUTIONS ). Removal of angiotensin II negative feedback on renin secretion leads to increased plasma renin activity. In animal studies, benazepril had no inhibitory effect on the vasopressor response to angiotensin II and did not interfere with the hemodynamic effects of the autonomic neurotransmitters acetylcholine, epinephrine, and norepinephrine.
ACE is identical to kininase, an enzyme that degrades bradykinin. Whether increased levels of bradykinin, a potent vasodepressor peptide, play a role in the therapeutic effects of Lotensin HCT remains to be elucidated. While the mechanism through which benazepril lowers blood pressure is believed to be primarily suppression of the renin-angiotensin-aldosterone system, benazepril has an antihypertensive effect even in patients with low-renin hypertension.
Hydrochlorothiazide is a thiazide diuretic. Thiazides affect the renal tubular mechanisms of electrolyte reabsorption, directly increasing excretion of sodium and chloride in approximately equivalent amounts. Indirectly, the diuretic action of hydrochlorothiazide reduces plasma volume, with consequent increases in plasma renin activity, increases in aldosterone secretion, increases in urinary potassium loss, and decreases in serum potassium.
The renin-aldosterone link is mediated by angiotensin, so coadministration of an ACE inhibitor tends to reverse the potassium loss associated with these diuretics. The mechanism of the antihypertensive effect of thiazides is unknown. Pharmacokinetics and Metabolism Following oral administration of Lotensin HCT, peak plasma concentrations of benazepril are reached within 0.5 to 1.0 hour.
As determined by urinary recovery, the extent of absorption is at least 37%. In fasting subjects, the rate and extent of absorption of benazepril and hydrochlorothiazide from Lotensin HCT are not different, respectively, from the rate and extent of absorption of benazepril and hydrochlorothiazide from immediate-release monotherapy formulations. The estimated absolute bioavailability of hydrochlorothiazide after oral administration is about 70%.
Peak plasma hydrochlorothiazide concentrations (C max ) are reached within 2 to 5 hours after oral administration. Hydrochlorothiazide binds to albumin (40% to 70%) and distributes into erythrocytes. The absorption of benazepril from Lotensin tablets is not influenced by the presence of food in the gastrointestinal tract.
There is no clinically significant effect of food on the bioavailability of hydrochlorothiazide. Cleavage of the ester group (primarily in the liver) converts benazepril to its active metabolite, benazeprilat. Peak plasma concentrations of benazeprilat are reached 1 to 2 hours after drug intake in the fasting state and 2 to 4 hours after drug intake in the nonfasting state.
The serum protein binding of benazepril is about 96.7% and that of benazeprilat about 95.3%, as measured by equilibrium dialysis; on the basis of in vitro studies, the degree of protein binding should be unaffected by age, hepatic dysfunction, or – over the concentration range of 0.24 to 23.6 µmol/L – concentration. In studies of rats given 14 C-benazepril, bena… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
Mechanism of Action Benazepril and benazeprilat inhibit angiotensin-converting enzyme (ACE) in human subjects and in animals. ACE is a peptidyl dipeptidase that catalyzes the conversion of angiotensin I to the vasoconstrictor substance, angiotensin II. Angiotensin II also stimulates aldosterone secretion by the adrenal cortex.
Inhibition of ACE results in decreased plasma angiotensin II, which leads to decreased vasopressor activity and to decreased aldosterone secretion. The latter decrease may result in a small increase of serum potassium. Hypertensive patients treated with benazepril alone for up to 52 weeks had elevations of serum potassium of up to 0.2 mEq/L.
Similar patients treated with benazepril and hydrochlorothiazide for up to 24 weeks had no consistent changes in their serum potassium ( see PRECAUTIONS ). Removal of angiotensin II negative feedback on renin secretion leads to increased plasma renin activity. In animal studies, benazepril had no inhibitory effect on the vasopressor response to angiotensin II and did not interfere with the hemodynamic effects of the autonomic neurotransmitters acetylcholine, epinephrine, and norepinephrine.
ACE is identical to kininase, an enzyme that degrades bradykinin. Whether increased levels of bradykinin, a potent vasodepressor peptide, play a role in the therapeutic effects of Lotensin HCT remains to be elucidated. While the mechanism through which benazepril lowers blood pressure is believed to be primarily suppression of the renin-angiotensin-aldosterone system, benazepril has an antihypertensive effect even in patients with low-renin hypertension.
Hydrochlorothiazide is a thiazide diuretic. Thiazides affect the renal tubular mechanisms of electrolyte reabsorption, directly increasing excretion of sodium and chloride in approximately equivalent amounts. Indirectly, the diuretic action of hydrochlorothiazide reduces plasma volume, with consequent increases in plasma renin activity, increases in aldosterone secretion, increases in urinary potassium loss, and decreases in serum potassium.
The renin-aldosterone link is mediated by angiotensin, so coadministration of an ACE inhibitor tends to reverse the potassium loss associated with these diuretics. The mechanism of the antihypertensive effect of thiazides is unknown.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Lotensin HCT USP is available in tablets of three different strengths: Benazepril HCl Hydrochlorothiazide Tablet Color 10 mg 12.5 mg light pink 20 mg 12.5 mg grayish violet 20 mg 25 mg red Tablets of each strength are supplied in bottles that contain a desiccant and 100 tablets. The National Drug Codes for the various packages are: Dose Bottle of 100 Tablet Imprint 10/12.5 NDC 30698-452-01 452 20/12.5 NDC 30698-453-01 453 20/25 NDC 30698-454-01 454 Tablets are oblong and scored, with “LOTENSIN HCT” on one side and appropriate number imprinted on the other side.
Storage: Do not store above 86°F (30°C). Protect from moisture and light. Dispense in a tight, light -resistant container (USP).
Manufactured for and Distributed by: Validus Pharmaceuticals LLC Parsippany, NJ 07054 [email protected] www.validuspharma.com 1-866-982-5438 © 2023 Validus Pharmaceuticals LLC 60024-06 March 2023
📋 Description ▾
DESCRIPTION Benazepril hydrochloride USP is a white to off-white crystalline powder, soluble (>100 mg/mL) in water, in ethanol, and in methanol. Benazepril hydrochloride’s chemical name is 3-[[1-(ethoxycarbonyl)-3-phenyl-(1S)-propyl] amino]-2,3,4,5-tetrahydro-2-oxo-1 H -1-(3S)-benzazepine-1-acetic acid monohydrochloride; its structural formula is Its empirical formula is C 24 H 28 N 2 O 5 ·HCl, and its molecular weight is 460.96. Benazeprilat, the active metabolite of benazepril, is a nonsulfhydryl angiotensin-converting enzyme inhibitor.
Benazepril is converted to benazeprilat by hepatic cleavage of the ester group. Hydrochlorothiazide USP is a white or practically white, practically odorless, crystalline powder. It is slightly soluble in water; freely soluble in sodium hydroxide solution, in n -butylamine, and in dimethylformamide; sparingly soluble in methanol; and insoluble in ether, in chloroform, and in dilute mineral acids.
Hydrochlorothiazide’s chemical name is 6-chloro-3,4-dihydro-2 H -1,2,4- benzothiadiazine-7-sulfonamide 1,1-dioxide; its structural formula is Its empirical formula is C 7 H 8 ClN 3 O 4 S 2 , and its molecular weight is 297.73. Hydrochlorothiazide is a thiazide diuretic. Lotensin HCT is a combination of benazepril and hydrochlorothiazide USP.
The tablets are formulated for oral administration with a combination of 10 or 20 mg of benazepril and 12.5 or 25 mg of hydrochlorothiazide USP. The inactive ingredients of the tablets are cellulose compounds, crospovidone, hydrogenated castor oil, iron oxides (10/12.5 mg, 20/12.5 mg, and 20/25 mg tablets), lactose, polyethylene glycol, talc, and titanium dioxide. Benazepril hydrochloride structural formula.
Hydrochlorothiazide structural formula.
💬 Information for Patients ▾
Information for Patients Angioedema: Angioedema, including laryngeal edema, can occur at any time with treatment with ACE inhibitors. A patient receiving Lotensin HCT should be told to report immediately any signs or symptoms suggesting angioedema (swelling of face, eyes, lips, or tongue, or difficulty in breathing) and to take no more drugs until after consulting with the prescribing physician. Pregnancy: Female patients of childbearing age should be told about the consequences of exposure to Lotensin HCT during pregnancy.
Discuss treatment options with women planning to become pregnant. Patients should be asked to report pregnancies to their physicians as soon as possible. Symptomatic Hypotension: A patient receiving Lotensin HCT should be cautioned that lightheadedness can occur, especially during the first days of therapy, and that it should be reported to the prescribing physician.
The patient should be told that if syncope occurs, Lotensin HCT should be discontinued until the physician has been consulted. All patients should be cautioned that inadequate fluid intake, excessive perspiration, diarrhea, or vomiting can lead to an excessive fall in blood pressure, with the same consequences of lightheadedness and possible syncope. Hyperkalemia: A patient receiving Lotensin HCT should be told not to use potassium supplements or salt substitutes containing potassium without consulting the prescribing physician.
Neutropenia: Patients should be told to promptly report any indication of infection (e.g., sore throat, fever), which could be a sign of neutropenia. Non-melanoma Skin Cancer: Instruct patients taking hydrochlorothiazide to protect skin from the sun and undergo regular skin cancer screening.
⚠️ Precautions ▾
PRECAUTIONS General Serum Electrolyte Abnormalities In clinical trials of Lotensin HCT, the average change in serum potassium was near zero in subjects who received 5/6.25 mg or 20/12.5 mg, but the average subject who received 10/12.5 mg or 20/25 mg experienced a mild reduction in serum potassium, similar to that experienced by the average subject receiving the same dose of hydrochlorothiazide monotherapy. Hydrochlorothiazide can cause hypokalemia and hyponatremia. Hypomagnesemia can result in hypokalemia which appears difficult to treat despite potassium repletion.
Drugs that inhibit the renin-angiotensin system can cause hyperkalemia. Monitor serum electrolytes periodically. Metabolic Disturbances Hydrochlorothiazide Hydrochlorothiazide may alter glucose tolerance and raise serum levels of cholesterol and triglycerides.
Hydrochlorothiazide may raise the serum uric acid level due to reduced clearance of uric acid and may cause or exacerbate hyperuricemia and precipitate gout in susceptible patients. Thiazides decrease urinary calcium excretion and may cause mild elevation of serum calcium. Avoid using Lotensin HCT in patients with hypercalcemia.
Cough: Presumably due to the inhibition of the degradation of endogenous bradykinin, persistent nonproductive cough has been reported with all ACE inhibitors, always resolving after discontinuation of therapy. ACE inhibitor-induced cough should be considered in the differential diagnosis of cough. Surgery/Anesthesia: In patients undergoing surgery or during anesthesia with agents that produce hypotension, benazepril will block the angiotensin II formation that could otherwise occur secondary to compensatory renin release.
Hypotension that occurs as a result of this mechanism can be corrected by volume expansion. Information for Patients Angioedema: Angioedema, including laryngeal edema, can occur at any time with treatment with ACE inhibitors. A patient receiving Lotensin HCT should be told to report immediately any signs or symptoms suggesting angioedema (swelling of face, eyes, lips, or tongue, or difficulty in breathing) and to take no more drugs until after consulting with the prescribing physician.
Pregnancy: Female patients of childbearing age should be told about the consequences of exposure to Lotensin HCT during pregnancy. Discuss treatment options with women planning to become pregnant. Patients should be asked to report pregnancies to their physicians as soon as possible.
Symptomatic Hypotension: A patient receiving Lotensin HCT should be cautioned that lightheadedness can occur, especially during the first days of therapy, and that it should be reported to the prescribing physician. The patient should be told that if syncope occurs, Lotensin HCT should be discontinued until the physician has been consulted. All patients should be cautioned that inadequate fluid intake, excessive perspiration, diarrhea, or vomiting can lead to an excessive fall in blood pressure, with the same consequences of lightheadedness and possible syncope.
Hyperkalemia: A patient receiving Lotensin HCT should be told not to use potassium supplements or salt substitutes containing potassium without consulting the prescribing physician. Neutropenia: Patients should be told to promptly report any indication of infection (e.g., sore throat, fever), which could be a sign of neutropenia. Non-melanoma Skin Cancer: Instruct patients taking hydrochlorothiazide to protect skin from the sun and undergo regular skin cancer screening.
Laboratory Tests The hydrochlorothiazide component of Lotensin HCT may decrease serum PBI levels without signs of thyroid disturbance. Therapy with Lotensin HCT should be interrupted for a few days before carrying out tests of parathyroid function. Drug Interactions Neprilysin Inhibitors: Patients taking concomitant neprilysin inhibitors may be at increased risk for angioedema.
Interactions Common for Both Benazepril and Hydrochlorothiazide Potassium Supplements and Potassium -Spari… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Minimal amounts of unchanged benazepril and benazeprilat are excreted into the breast milk of lactating women treated with benazepril, so that a newborn child ingesting nothing but breast milk would receive less than 0.1% of the maternal doses of benazepril and benazeprilat. Thiazides, on the other hand, are definitely excreted into breast milk. Because of the potential for serious adverse reactions in nursing infants from hydrochlorothiazide and the unknown effects of benazepril in infants, a decision should be made whether to discontinue nursing or to discontinue Lotensin HCT, taking into account the importance of the drug to the mother.
🧬 Pharmacokinetics ▾
Pharmacokinetics and Metabolism Following oral administration of Lotensin HCT, peak plasma concentrations of benazepril are reached within 0.5 to 1.0 hour. As determined by urinary recovery, the extent of absorption is at least 37%. In fasting subjects, the rate and extent of absorption of benazepril and hydrochlorothiazide from Lotensin HCT are not different, respectively, from the rate and extent of absorption of benazepril and hydrochlorothiazide from immediate-release monotherapy formulations.
The estimated absolute bioavailability of hydrochlorothiazide after oral administration is about 70%. Peak plasma hydrochlorothiazide concentrations (C max ) are reached within 2 to 5 hours after oral administration. Hydrochlorothiazide binds to albumin (40% to 70%) and distributes into erythrocytes.
The absorption of benazepril from Lotensin tablets is not influenced by the presence of food in the gastrointestinal tract. There is no clinically significant effect of food on the bioavailability of hydrochlorothiazide. Cleavage of the ester group (primarily in the liver) converts benazepril to its active metabolite, benazeprilat.
Peak plasma concentrations of benazeprilat are reached 1 to 2 hours after drug intake in the fasting state and 2 to 4 hours after drug intake in the nonfasting state. The serum protein binding of benazepril is about 96.7% and that of benazeprilat about 95.3%, as measured by equilibrium dialysis; on the basis of in vitro studies, the degree of protein binding should be unaffected by age, hepatic dysfunction, or – over the concentration range of 0.24 to 23.6 µmol/L – concentration. In studies of rats given 14 C-benazepril, benazepril and its metabolites crossed the blood-brain barrier only to an extremely low extent.
Multiple doses of benazepril did not result in accumulation in any tissue except the lung, where, as with other ACE inhibitors in similar studies, there was a slight increase in concentration due to slow elimination in that organ. Benazepril is almost completely metabolized to benazeprilat, which has much greater ACE inhibitory activity than benazepril, and to the glucuronide conjugates of benazepril and benazeprilat. Only trace amounts of an administered dose of benazepril can be recovered unchanged in the urine; about 20% of the dose is excreted as benazeprilat, 4% as benazepril glucuronide, and 8% as benazeprilat glucuronide.
In patients with hepatic dysfunction due to cirrhosis, levels of benazeprilat are essentially unaltered. Similarly, the pharmacokinetics of benazepril and benazeprilat do not appear to be influenced by age. The kinetics of benazepril are dose-proportional within the dosage range of 5 mg to 20 mg.
Small deviations from dose proportionality were observed when the broader range of 2 mg to 80 mg was studied, possibly due to the saturable binding of the compound to ACE. The effective half-life of accumulation of benazeprilat following multiple dosing of benazepril is 10 to11 hours. Thus, steady-state concentrations of benazeprilat should be reached after 2 or 3 doses of benazepril given once daily.
During chronic administration (28 days) of once-daily doses of benazepril between 5 mg and 20 mg, the kinetics did not change, and there was no significant accumulation. Accumulation ratios based on AUC and urinary recovery of benazeprilat were 1.19 and 1.27, respectively. When dialysis was started 2 hours after ingestion of 10 mg of benazepril, approximately 6% of benazeprilat was removed in 4 hours of dialysis.
The parent compound, benazepril, was not detected in the dialysate. Benazepril and benazeprilat are cleared predominantly by renal excretion in healthy subjects with normal renal function. Nonrenal (i.e., biliary) excretion accounts for approximately 11% to 12% of benazeprilat excretion in healthy subjects.
In patients with renal failure, biliary clearance may compensate to an extent for deficient renal clearance. The disposition of benazepril and benazeprilat in patients with… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
Pharmacodynamics Benazepril Single and multiple doses of 10 mg or more of benazepril cause inhibition of plasma ACE activity by at least 80% to 90% for at least 24 hours after dosing. For up to 4 hours after a 10 mg dose, pressor responses to exogenous angiotensin I were inhibited by 60% to 90%. In normal human volunteers, single doses of benazepril caused an increase in renal blood flow but had no effect on glomerular filtration rate.
Hydrochlorothiazide After oral administration of hydrochlorothiazide, diuresis begins within 2 hours, peaks in about 4 hours and lasts about 6 to 12 hours. Drug Interactions Lotensin HCT potentiates the antihypertensive action of other antihypertensive drugs (e.g., curare derivatives, guanethidine, methyldopa, beta-blockers, vasodilators, calcium channel blockers ACE inhibitors and ARBs and DRIs).
🔬 Clinical Studies ▾
CLINICAL STUDIES In single-dose studies, benazepril lowered blood pressure within 1 hour, with peak reductions achieved 2 to 4 hours after dosing. The antihypertensive effect of a single dose persisted for 24 hours. In multiple-dose studies, once-daily doses of 20 mg to 80 mg decreased seated pressure (systolic/diastolic) 24 hours after dosing by about 6-12/4-7 mm Hg.
The reductions at trough are about 50% of those seen at peak. Four dose-response studies of benazepril monotherapy using once-daily dosing were conducted in 470 mild-to-moderate hypertensive patients not using diuretics. The minimal effective once-daily dose of benazepril was 10 mg; further falls in blood pressure, especially at morning trough, were seen with higher doses in the studied dosing range (10 mg to 80 mg).
In studies comparing the same daily dose of benazepril given as a single morning dose or as a twice-daily dose, blood pressure reductions at the time of morning trough blood levels were greater with the divided regimen. The antihypertensive effects of benazepril were not appreciably different in patients receiving high- or low-sodium diets. Benazepril -Hydrochlorothiazide In 15 controlled clinical trials, 1453 healthy or hypertensive patients were exposed to benazepril and hydrochlorothiazide of which 459 were exposed for at least 6 months, 214 for at least 12 months and 25 for at least 24 months.
The combination of benazepril-hydrochlorothiazide resulted in mean placebo-adjusted decreases in sitting systolic and diastolic blood pressures of 10/6 mm Hg with 5/6.25 mg and 10/12.5 mg doses, and 20/10 mm Hg with 20/25 mg dose. In clinical trials of benazepril/hydrochlorothiazide using benazepril doses of 5/20 mg and hydrochlorothiazide doses of 6.25/25 mg, the antihypertensive effects were sustained for at least 24 hours, and they increased with increasing dose of either component. Although benazepril monotherapy is somewhat less effective in blacks than in nonblacks, the efficacy of combination therapy appears to be independent of race.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenicity, Fertility No evidence of carcinogenicity was found when benazepril was given to rats and mice for 104 weeks at doses up to 150 mg/kg/day. On a body-surface-area basis, this dose is 18 times (rats) and 9 times (mice) the maximum recommended human dose. No mutagenic activity was detected in the Ames test in bacteria (with or without metabolic activation), in an in vitro test for forward mutations in cultured mammalian cells, or in a nucleus anomaly test.
At doses of 50-500 mg/kg/day (6 to 61 times the maximum recommended dose on a body-surface-area basis), benazepril had no adverse effect on the reproductive performance of male and female rats. Under the auspices of the National Toxicology Program, rats and mice received hydrochlorothiazide in their feed for 2 years, at doses up to 600 mg/kg/day in mice and up to 100 mg/kg/day in rats. These studies uncovered no evidence of a carcinogenic potential of hydrochlorothiazide in rats or female mice, but there was equivocal evidence of hepatocarcinogenicity in male mice.
Hydrochlorothiazide was not genotoxic in in vitro assays using strains TA 98, TA 100, TA 1535, TA 1537, and TA 1538 of Salmonella typhimurium (the Ames test); in the Chinese Hamster Ovary (CHO) test for chromosomal aberrations; or in in vivo assays using mouse germinal cell chromosomes, Chinese hamster bone marrow chromosomes, and the Drosophila sex-linked recessive lethal trait gene. Positive test results were obtained in the in vitro CHO Sister Chromatid Exchange (clastogenicity) test and in the Mouse Lymphoma Cell (mutagenicity) assays, using concentrations of hydrochlorothiazide of 43 to 1300 µg/mL.
Positive test results were also obtained in the Aspergillus nidulans nondisjunction assay, using an unspecified concentration of hydrochlorothiazide.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL 10 mg benazepril/12.5 mg hydrochlorothiazide Tablet NDC 30698-452-01 Lotensin HCT ® benazepril HCl USP 10 mg hydrochlorothiazide USP 12.5 mg 10/12.5 100 Tablets Rx Only PRINCIPAL DISPLAY PANEL 10 mg benazepril/12.5 mg hydrochlorothiazide Tablet NDC 30698-452-01 Lotensin HCT® benazepril HCl USP 10 mg hydrochlorothiazide USP 12.5 mg 10/12.5 100 Tablets Rx Onl
PRINCIPAL DISPLAY PANEL 20 mg benazepril/12.5 mg hydrochlorothiazide Tablet NDC 30698-453-01 Lotensin HCT ® 20/12.5 benazepril HCl USP 20 mg hydrochlorothiazide USP 12.5 mg 20/12.5 100 Tablets Rx Only PRINCIPAL DISPLAY PANEL 20 mg benazepril/12.5 mg hydrochlorothiazide Tablet NDC 30698-453-01 Lotensin HCT® 20/12.5 benazepril HCl USP 20 mg hydrochlorothiazide USP 12.5 mg 20/12.5 100 Tablets
PRINCIPAL DISPLAY PANEL 20 mg benazepril/25 mg hydrochlorothiazide Tablet NDC 30698-454-01 Lotensin HCT ® 20/25 benazepril HCl USP 20 mg hydrochlorothiazide USP 25 mg 20/25 100 Tablets Rx Only PRINCIPAL DISPLAY PANEL 20 mg benazepril/25 mg hydrochlorothiazide Tablet NDC 30698-454-01 Lotensin HCT® 20/25 benazepril HCl USP 20 mg hydrochlorothiazide USP 25 mg 20/25 100 Tablets Rx Only
Medicare Part D spend CMS · PART D · 2025 (Q1-Q4)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |