
Rizatriptan 10 mg Tablet, Film Coated — NDC 33342-088-41 (Billing 33342-0088-41)
This is a package of Rizatriptan 10 mg Tablet, Film Coated from Macleods Pharmaceuticals Limited, marketed since Mar 2014 and currently FDA-listed; retail pharmacies pay about $0.3355 per unit (NADAC). It is the main listing for this product, which comes in 7 package sizes.
NDC database record
One package, one record: these facts belong to NDC 33342-088-41 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 33342 labeler · 088 product · 41 package
- Package marketed since
- Sep 3, 2018
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC)
- 0333342088468, 0333342087072, 0333342088079, 0333342087461
- Medicaid fills, this package
- 157,237 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Past resolved recalls for this product (1)
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 040222
- GCN: 19592
- GPI-14 (Medi-Span): 67406060100320
- HICL (First Databank): 018535
- AHFS class code: 28:32.28.00
- RxCUI (RxNorm): 312840
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Serotonin-1b and Serotonin-1d Receptor Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It treats a migraine attack once it has started, with or without aura. It works for adults and for children 6 to 17. It does not prevent migraines and is not for cluster headache.
- Take it by mouth when a migraine begins. Tablets are swallowed, while the dissolving tablets and Rizafilm melt in your mouth. You can take it with or without food. If the headache...
- The most common are tiredness, sleepiness, dizziness, tingling and pain or pressure sensations. Tightness in the chest, throat or jaw can happen and is usually not heart-related, b...
- Seek emergency help for chest pain, sudden weakness or trouble speaking, a racing heartbeat, swelling of the face or throat, or severe stomach pain with bloody diarrhea. Also seek...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Rizatriptan — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.336 | $6.04 / 18 tablets |
| Medicaid paysCMS SDUD · 12 mo | $1.27 | $22.86 / 18 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.9419 | $16.95 / 18 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 33342-0088-07 33342-088-07 | 30 TABLET, FILM COATED in 1 CONTAINER | — | — | 2014-03-11 | — | Active |
| 33342-0088-12 33342-088-12 | 10 BLISTER PACK in 1 CARTON / 10 TABLET, FILM COATED in 1 BLISTER PACK | — | — | 2014-03-11 | — | Active |
| 33342-0088-41 You're viewing this Main listing | 3 BLISTER PACK in 1 CARTON / 6 TABLET, FILM COATED in 1 BLISTER PACK | $0.3355 / ea | $6.04 | 2018-09-03 | — | Active |
| 33342-0088-45 33342-088-45 | 2 BLISTER PACK in 1 CARTON / 6 TABLET, FILM COATED in 1 BLISTER PACK | $0.3355 / ea | $4.03 | 2018-09-03 | — | Active |
| 33342-0088-46 33342-088-46 | 200 TABLET, FILM COATED in 1 CONTAINER | — | — | 2014-03-11 | — | Active |
| 33342-0088-50 33342-088-50 | 4 BLISTER PACK in 1 CARTON / 3 TABLET, FILM COATED in 1 BLISTER PACK | $0.3658 / ea | $4.39 | 2014-03-11 | — | Active |
| 33342-0088-72 33342-088-72 | 6 BLISTER PACK in 1 CARTON / 3 TABLET, FILM COATED in 1 BLISTER PACK | $0.3658 / ea | $6.58 | 2014-03-11 | — | Active |
This pack has the lowest per-ea cost of the 4 priced pack sizes ($0.3355 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 96% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Rizatriptan 10 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Rizatriptan Benzoate 10 mg 00093-7472-43 | Teva | 18 tablets | $0.335 | AB | Availability likely | — |
| Rizatriptan 10 mgthis 33342-0088-41 | Macleods | 6 tablets | $0.335 | AB | Availability likely | — |
| Rizatriptan Benzoate 10 mg 57237-0088-34 | Rising | 12 tablets | $0.335 | AB | Availability likely | — |
| Rizatriptan Benzoate 10 mg 65862-0600-12 | Aurobindo | 12 tablets | $0.335 | AB | Availability likely | — |
| Rizatriptan Benzoate 10 mg 69097-0866-17 | Cipla | 6 tablets | $0.366 | — | FDA listed | +9% |
| Maxalt 10 mg 78206-0142-01 | Organon | 18 tablets | $44.477 | AB | Availability likely | +13159% |
| Rizatriptan Benzoate 10 mg 29300-0317-21 | Unichem | 12 tablets | — | — | FDA listed | — |
| Rizatriptan Benzoate 10 mg 50090-3343-00 | A-S | 18 tablets | — | AB | FDA listed | — |
| Rizatriptan Benzoate 10 mg 50090-3367-00 | A-S | 18 tablets | — | AB | FDA listed | — |
| Rizatriptan 10 mg 50090-7747-00 | A-S | 6 tablets | — | AB | FDA listed | — |
| Rizatriptan Benzoate 10 mg 51407-0682-12 | Golden | 12 tablets | — | AB | FDA listed | — |
| Rizatriptan Benzoate 10 mg 61919-0656-12 | DIRECT | 12 tablets | — | AB | FDA listed | — |
| Rizatriptan Benzoate 10 mg 67877-0262-01 | Ascend | 100 tablets | — | AB | FDA listed | — |
| rizatriptan benzoate 10 mg 68462-0466-72 | Glenmark | 12 tablets | — | — | FDA listed | — |
| Rizatriptan Benzoate 10 mg 71205-0644-12 | Proficient | 12 tablets | — | AB | FDA listed | — |
| Rizatriptan 10 mg 71335-1352-01 | Bryant | 10 tablets | — | AB | FDA listed | — |
| Rizatriptan Benzoate 10 mg 71335-1912-01 | Bryant | 10 tablets | — | AB | FDA listed | — |
| Rizatriptan 10 mg 71335-2980-01 | Bryant | 12 tablets | — | AB | FDA listed | — |
| Rizatriptan Benzoate 10 mg 72189-0258-12 | direct | 12 tablets | — | AB | FDA listed | — |
| Rizatriptan Benzoate 10 mg 72189-0447-18 | Direct_Rx | 18 tablets | — | AB | FDA listed | — |
| Rizatriptan Benzoate 10 mg 82619-0112-01 | Creekwood | 30 tablets | — | AB | FDA listed | — |
| Rizatriptan Benzoate 10 mg 82804-0202-12 | Proficient | 12 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Macleods Pharmaceuticals Limited labeler code 33342
- Valsartan and Hydrochlorothiazide 320 mg; 25 mg Tablet, Film Coated NDC 33342-078-10
- Olanzapine 5 mg Tablet, Orally Disintegrating NDC 33342-083-07
- Olanzapine 10 mg Tablet, Orally Disintegrating NDC 33342-084-07
- Olanzapine 15 mg Tablet, Orally Disintegrating NDC 33342-085-07
- Olanzapine 20 mg Tablet, Orally Disintegrating NDC 33342-086-07
- Rizatriptan 5 mg Tablet, Film Coated NDC 33342-087-07
- Rivastigmine Tartrate 1.5 mg Capsule NDC 33342-089-06
- Rivastigmine Tartrate 3 mg Capsule NDC 33342-090-06
- Rivastigmine Tartrate 4.5 mg Capsule NDC 33342-091-06
- Rivastigmine Tartrate 6 mg Capsule NDC 33342-092-06
- rizatriptan benzoate 5 mg Tablet, Orally Disintegrating NDC 33342-093-04
- rizatriptan benzoate 10 mg Tablet, Orally Disintegrating NDC 33342-094-04
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS & USAGE Ri zatriptan benzoate tablets are indicated for the acute treatment of migraine with or without aura in adults and in pediatric patients 6 to 17 years old. Limitations of Use • Rizatriptan benzoate tablets should only be used where a clear diagnosis of migraine has been established. If a patient has no response for the first migraine attack treated with rizatriptan benzoate tablets, the diagnosis of migraine should be reconsidered before rizatriptan benzoate tablets are administered to treat any subsequent attacks. • Rizatriptan benzoate tablets are not indicated for use in the management of hemiplegic or basilar migraine [see Contraindications (4) ]. • Rizatriptan benzoate tablets are not indicated for the prevention of migraine attacks. • Safety and effectiveness of rizatriptan benzoate tablets have not been established for cluster headache.
Rizatriptan benzoate is a serotonin (5-HT)1B/1D receptor agonist (triptan) indicated for the acute treatment of migraine with or without aura in adults and in pediatric patients 6 to 17 years of age (1) Limitations of Use: • Use only after clear diagnosis of migraine has been established ( 1 ) • Not indicated for the prophylactic therapy of migraine ( 1 ) • Not indicated for the treatment of cluster headache ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE & ADMINISTRATION Adults: 5 mg or 10 mg single dose; separate repeat doses by at least two hours; maximum dose in a 24-hour period: 30 mg (2.1) Pediatric patients 6 to 17 years: 5 mg single dose in patients less than 40 kg (88 lb); 10 mg single dose in patients 40 kg (88 lb) or more ( 2.2 ) Adjust dose if co-administered with propranolol ( 2.4 )
2.1Dosing Information in Adults The recommended starting dose of rizatriptan benzoate tablets is either 5 mg or 10 mg for the acute treatment of migraines in adults. The 10-mg dose may provide a greater effect than the 5-mg dose, but may have a greater risk of adverse reactions [see Clinical Studies (14.1) ]. Redosing in Adults Although the effectiveness of a second dose or subsequent doses has not been established in placebo-controlled trials, if the migraine headache returns, a second dose may be administered 2 hours after the first dose.
The maximum daily dose should not exceed 30 mg in any 24-hour period. The safety of treating, on average, more than four headaches in a 30-day period has not been established.
2.2Dosing Information in Pediatric Patients (Age 6 to 17 Years) Dosing in pediatric patients is based on the patient's body weight. The recommended dose of rizatriptan benzoate tablets is 5-mg in patients weighing less than 40 kg (88 lb), and 10 mg in patients weighing 40 kg (88 lb) or more. The efficacy and safety of treatment with more than one dose of rizatriptan benzoate tablets within 24 hours in pediatric patients 6 to 17 years of age have not been established.
2.4Dosage Adjustment for Patients on Propranolol Adult Patients In adult patients taking propranolol, only the 5-mg dose of rizatriptan benzoate tablets is recommended, up to a maximum of 3 doses in any 24-hour period (15 mg) [see Drug Interactions (7.1) and Clinical Pharmacology ( 12.3 )]. Pediatric Patients For pediatric patients weighing 40 kg (88 lb) or more, taking propranolol, only a single 5-mg dose of rizatriptan benzoate tablets is recommended (maximum dose of 5 mg in a 24-hour period). Rizatriptan benzoate tablets should not be prescribed to propranolol-treated pediatric patients who weigh less than 40 kg (88 lb) [ see Drug Interactions ( 7.1 ) and Clinical Pharmacology ( 12.3 ) ].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS & STRENGTHS Rizatriptan Benzoate Tablets, USP: • The 5 mg tablets are pale pink, capsule-shaped, compressed tablets debossed with 'CL 33' on one side and plain on the other • The 10 mg tablets are pale pink, capsule-shaped, compressed tablets debossed "CL 34" on one side and plain on the other • Rizatriptan Benzoate Tablets: 5 mg and 10 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Rizatriptan benzoate tablets are contraindicated in patients with: • Ischemic coronary artery disease (angina pectoris, history of myocardial infarction, or documented silent ischemia), or other significant underlying cardiovascular disease [see Warnings and Precautions ( 5.1 )]. • Coronary artery vasospasm including Prinzmetal's angina [see Warnings and Precautions ( 5.1 )]. • History of stroke or transient ischemic attack (TIA) [see Warnings and Precautions ( 5.4 )]. • Peripheral vascular disease (PVD) [see Warnings and Precautions ( 5.5 )]. • Ischemic bowel disease [see Warnings and Precautions ( 5.5 )]. • Uncontrolled hypertension [see Warnings and Precautions ( 5.8 )]. • Recent use (i.e., within 24 hours) of another 5-HT 1 agonist, ergotamine-containing medication, or ergot-type medication (such as dihydroergotamine or methysergide) [see Drug Interactions ( 7.2 and 7.3 )]. • Hemiplegic or basilar migraine [see Indications and Usage ( 1 )]. . • Concurrent administration or recent discontinuation (i.e., within 2 weeks) of a MAO-A inhibitor [see Drug Interactions ( 7.5 ) and Clinical Pharmacology ( 12.3 )]. • Hypersensitivity to rizatriptan or any of the excipients (angioedema and anaphylaxis seen) [see Adverse Reactions ( 6.2 )]. • History of ischemic heart disease or coronary artery vasospasm ( 4 ) • History of stroke or transient ischemic attack ( 4 ) • Peripheral vascular disease ( 4 ) • Ischemic bowel disease ( 4 ) • Uncontrolled hypertension ( 4 ) • Recent (within 24 hours) use of another 5-HT 1 agonist (e.g., another triptan), or of an ergotamine-containing medication ( 4 ) • Hemiplegic or basilar migraine ( 4 ) • MAO-A inhibitor used in the past 2 weeks ( 4 ) • Hypersensitivity to rizatriptan or any of the excipients ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Myocardial ischemia, myocardial infarction, and Prinzmetal's angina: Perform cardiac evaluation in patients with multiple cardiovascular risk factors ( 5.1 ) • Arrhythmias: Discontinue dosing if occurs ( 5.2 ) • Chest/throat/neck/jaw pain, tightness, pressure, or heaviness; Generally not associated with myocardial ischemia; Evaluate patients at high risk ( 5.3 ) • Cerebral hemorrhage, subarachnoid hemorrhage, and stroke: Discontinue dosing if occurs ( 5.4 ) • Gastrointestinal ischemic events, peripheral vasospastic reactions: Discontinue dosing if occurs ( 5.5 ) • Medication overuse headache: Detoxification may be necessary ( 5.6 ) • Serotonin syndrome: Discontinue dosing if occurs ( 5.7 )
5.1Myocardial Ischemia, Myocardial Infarction, and Prinzmetal's Angina Rizatriptan benzoate should not be given to patients with ischemic or vasospastic coronary artery disease. There have been rare reports of serious cardiac adverse reactions, including acute myocardial infarction, occurring within a few hours following administration of rizatriptan benzoate. Some of these reactions occurred in patients without known coronary artery disease (CAD).
5-HT 1 agonists, including rizatriptan benzoate may cause coronary artery vasospasm (Prinzmetal's Angina), even in patients without a history of CAD. Triptan-naïve patients who have multiple cardiovascular risk factors (e.g., increased age, diabetes, hypertension, smoking, obesity, strong family history of CAD) should have a cardiovascular evaluation prior to receiving rizatriptan benzoate. If there is evidence of CAD or coronary artery vasospasm, rizatriptan benzoate should not be administered [see Contraindications ( 4 )].
For patients who have a negative cardiovascular evaluation, consideration should be given to administration of the first rizatriptan benzoate dose in a medically-supervised setting and performing an electrocardiogram (ECG) immediately following rizatriptan benzoate administration. Periodic cardiovascular evaluation should be considered in intermittent long-term users of rizatriptan benzoate who have cardiovascular risk factors.
5.2Arrhythmias Life-threatening disturbances of cardiac rhythm, including ventricular tachycardia and ventricular fibrillation leading to death, have been reported within a few hours following the administration of 5-HT 1 agonists. Discontinue rizatriptan benzoate if these disturbances occur.
5.3Chest, Throat, Neck and/or Jaw Pain/Tightness/Pressure As with other 5-HT 1 agonists, sensations of tightness, pain, pressure, and heaviness in the precordium, throat, neck and jaw commonly occur after treatment with rizatriptan benzoate and are usually non-cardiac in origin. However, if a cardiac origin is suspected, patients should be evaluated. Patients shown to have CAD and those with Prinzmetal's variant angina should not receive 5-HT 1 agonists.
5.4Cerebrovascular Events Cerebral hemorrhage, subarachnoid hemorrhage, and stroke have occurred in patients treated with 5-HT 1 agonists, and some have resulted in fatalities. In a number of cases, it appears possible that the cerebrovascular events were primary, the 5-HT 1 agonist having been administered in the incorrect belief that the symptoms experienced were a consequence of migraine, when they were not. Also, patients with migraine may be at increased risk of certain cerebrovascular events (e.g., stroke, hemorrhage, transient ischemic attack).
Discontinue rizatriptan benzoate if a cerebrovascular event occurs. As with other acute migraine therapies, before treating headaches in patients not previously diagnosed as migraineurs, and in migraineurs who present with atypical symptoms, care should be taken to exclude other potentially serious neurological conditions. Rizatriptan benzoate should not be administered to patients with a history of stroke or transient ischemic attack [see Contraindications ( 4 )] .
5.5Other Vasospasm Reactions 5-HT 1 agonists, including rizatriptan b… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in more detail in other sections of the labeling: • Myocardial Ischemia, Myocardial Infarction, and Prinzmetal's Angina [see Warnings and Precautions ( 5.1 )]. • Arrhythmias [see Warnings and Precautions ( 5.2 )]. • Chest, Throat, Neck and/or Jaw Pain/Tightness/Pressure [see Warnings and Precautions ( 5.3 )]. • Cerebrovascular Events [see Warnings and Precautions ( 5.4 )]. • Other Vasospasm Reactions [see Warnings and Precautions ( 5.5 )]. • Medication Overuse Headache [see Warnings and Precautions ( 5.6 )]. • Serotonin Syndrome [see Warnings and Precautions ( 5.7 )]. • Increase in Blood Pressure [see Warnings and Precautions ( 5.8 )].
The most common adverse reactions in adults were (incidence ≥ 5% and greater than placebo): asthenia/fatigue, somnolence, pain/pressure sensation and dizziness (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Macleods Pharma USA, Inc. at 1-888-943-3210 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. Adults Incidence in Controlled Clinical Trials Adverse reactions to rizatriptan benzoate were assessed in controlled clinical trials that included over 3700 adult patients who received single or multiple doses of rizatriptan benzoate tablets.
The most common adverse reactions during treatment with rizatriptan benzoate (≥ 5% in either treatment group and greater than placebo) were asthenia/fatigue, somnolence, pain/pressure sensation and dizziness. These adverse reactions appeared to be dose related. Table 1 lists the adverse reactions (incidence ≥ 2% and greater than placebo) after a single dose of rizatriptan benzoate in adults.
Table 1: Incidence (≥ 2% and Greater than Placebo) of Adverse Reactions After a Single Dose of Rizatriptan Benzoate Tablets or Placebo in Adults Adverse Reactions % of Patients Rizatriptan Benzoate Tablets 5 mg (N=977) Rizatriptan Benzoate Tablets 10 mg (N=1,167) Placebo (N=627) Atypical Sensations 4 5 4 Paresthesia 3 4 <2 Pain and other Pressure Sensations 6 9 3 Chest Pain: tightness/pressure and/or heaviness <2 3 1 Neck/throat/jaw: pain/tightness/pressure <2 2 1 Regional Pain: tightness/pressure and/or heaviness <1 2 0 Pain, location unspecified 3 3 <2 Digestive 9 13 8 Dry Mouth 3 3 1 Nausea 4 6 4 Neurological 14 20 11 Dizziness 4 9 5 Headache <2 2 <1 Somnolence 4 8 4 Other Asthenia/fatigue 4 7 2 The frequencies of adverse reactions in clinical trials did not increase when up to three doses were taken within 24 hours.
Adverse reaction frequencies were also unchanged by concomitant use of drugs commonly taken for migraine prophylaxis (including propranolol), oral contraceptives, or analgesics. The incidences of adverse reactions were not affected by age or gender. There were insufficient data to assess the impact of race on the incidence of adverse reactions.
Other Events Observed in Association with the Administration of Rizatriptan Benzoate in Adults In the following section, the frequencies of less commonly reported adverse events are presented that were not reported in other sections of the labeling. Because the reports include events observed in open studies, the role of rizatriptan benzoate in their causation cannot be reliably determined. Furthermore, variability associated with adverse event reporting, the terminology used to describe adverse events, limit the value of the quantitative frequency estimates provided.
Event frequencies are calculated as the number of patients who used rizatriptan benzoate and reported an event divided by the total number of patients exposed to rizatriptan benzoate (N= 3716). All reported events occurred at an incidence ≥ 1%, or are believed to be reasonably associated with… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS
7.1Propranolol The dose of rizatriptan benzoate should be adjusted in propranolol-treated patients, as propranolol has been shown to increase the plasma AUC of rizatriptan by 70% [see Dosage and Administration ( 2.4 ) and Clinical Pharmacology ( 12.3 )] .
7.2Ergot-Containing Drugs Ergot-containing drugs have been reported to cause prolonged vasospastic reactions. Because these effects may be additive, use of ergotamine-containing or ergot-type medications (like dihydroergotamine or methysergide) and rizatriptan benzoate within 24 hours is contraindicated [see Contraindications ( 4 )] .
7.3Other 5-HT 1 Agonists Because their vasospastic effects may be additive, co-administration of rizatriptan benzoate and other 5-HT 1 agonists within 24 hours of each other is contraindicated [see Contraindications ( 4 )] .
7.4SSRIs/SNRIs and Serotonin Syndrome Cases of serotonin syndrome have been reported during co-administration of triptans and selective serotonin reuptake inhibitors (SSRIs) or serotonin norepinephrine reuptake inhibitors (SNRIs) [see Warnings and Precautions ( 5.7 )] .
7.5Monoamine Oxidase Inhibitors Rizatriptan benzoate is contraindicated in patients taking MAO-A inhibitors and non-selective MAO inhibitors. A specific MAO-A inhibitor increased the systemic exposure of rizatriptan and its metabolite [see Contraindications (4) and Clinical Pharmacology ( 12.3 )] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Pregnancy: Based on animal data, may cause fetal harm (8.1)
8.1Pregnancy Risk Summary Available human data on the use of rizatriptan benzoate in pregnant women are not sufficient to draw conclusions about drug-associated risk for major birth defects and miscarriage. In animal studies, developmental toxicity was observed following oral administration of rizatriptan during pregnancy (decreased fetal body weight in rats) or throughout pregnancy and lactation (increased mortality, decreased body weight, and neurobehavioral impairment in rat offspring) at maternal plasma exposures greater than that expected at therapeutic doses in humans [see Animal Data].
In the U.S. general population, the estimated background risk of major birth defects and of miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. The reported rate of major birth defects among deliveries to women with migraine range from 2.2% to 2.9% and the reported rate of miscarriage was 17%, which are similar to rates reported in women without migraine. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk In women with migraine, there is an increased risk of adverse perinatal outcomes in the mother, including pre-eclampsia and gestational hypertension.
Data Human Data The Pregnancy Registry for rizatriptan benzoate did not identify any pattern of congenital anomalies or other adverse birth outcomes over the period of 1998 to 2018. However, the lack of identification of any pattern should be viewed with caution, as the number of prospective reports with outcome information was low and did not provide sufficient power to detect an increased risk of individual birth defects associated with the use of rizatriptan benzoate. Additionally, there was significant loss to follow-up in the prospective pregnancy reports, further complicating this assessment of an association between rizatriptan benzoate and any pattern of congenital anomalies or other adverse birth outcomes.
In a study using data from the Swedish Medical Birth Register, live births to women who reported using triptans or ergots during pregnancy were compared with those of women who did not. Of the 157 births with first-trimester exposure to rizatriptan, 7 infants were born with malformations (relative risk 1.01 [95% CI: 0.40 to 2.08]). A study using linked data from the Medical Birth Registry of Norway to the Norwegian Prescription Database compared pregnancy outcomes in women who redeemed prescriptions for triptans during pregnancy, as well as a migraine disease comparison group who redeemed prescriptions for triptans before pregnancy only, compared with a population control group.
Of the 310 women who redeemed prescriptions for rizatriptan during the first trimester, 10 had infants with major congenital malformations (OR 1.03 [95% CI: 0.55 to 1.93]), while for the 271 women who redeemed prescriptions for rizatriptan before, but not during, pregnancy, 12 had infants with major congenital malformations (OR 1.48 [95% CI: 0.83 to 2.64]), each compared with the population comparison group. Animal Data When rizatriptan (0, 2, 10, or 100 mg/kg/day) was administered orally to pregnant rats throughout organogenesis, a decrease in fetal body weight was observed at the highest doses tested.
At the mid dose (10 mg/kg/day), which was a no-effect dose for adverse effects on embryofetal development, plasma exposure (AUC) was approximately 15 times that in humans at the maximum recommended human dose (MRHD) of 30 mg/day. When rizatriptan (0, 5, 10, or 50 mg/kg/day) was administered orally to pregnant rabbits throughout organogenesis, no adverse fetal effects were observed. Plasma exposure (AUC) at the highest dose tested was 115 times that in humans at the MRHD.
Placental transfer of drug to the fetus was demonstrated in both species. Oral administration of rizatriptan (0, 2, 10, or 100 mg/kg/day) to female rats prior to and during mating and… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available human data on the use of rizatriptan benzoate in pregnant women are not sufficient to draw conclusions about drug-associated risk for major birth defects and miscarriage. In animal studies, developmental toxicity was observed following oral administration of rizatriptan during pregnancy (decreased fetal body weight in rats) or throughout pregnancy and lactation (increased mortality, decreased body weight, and neurobehavioral impairment in rat offspring) at maternal plasma exposures greater than that expected at therapeutic doses in humans [see Animal Data].
In the U.S. general population, the estimated background risk of major birth defects and of miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. The reported rate of major birth defects among deliveries to women with migraine range from 2.2% to 2.9% and the reported rate of miscarriage was 17%, which are similar to rates reported in women without migraine. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk In women with migraine, there is an increased risk of adverse perinatal outcomes in the mother, including pre-eclampsia and gestational hypertension.
Data Human Data The Pregnancy Registry for rizatriptan benzoate did not identify any pattern of congenital anomalies or other adverse birth outcomes over the period of 1998 to 2018. However, the lack of identification of any pattern should be viewed with caution, as the number of prospective reports with outcome information was low and did not provide sufficient power to detect an increased risk of individual birth defects associated with the use of rizatriptan benzoate. Additionally, there was significant loss to follow-up in the prospective pregnancy reports, further complicating this assessment of an association between rizatriptan benzoate and any pattern of congenital anomalies or other adverse birth outcomes.
In a study using data from the Swedish Medical Birth Register, live births to women who reported using triptans or ergots during pregnancy were compared with those of women who did not. Of the 157 births with first-trimester exposure to rizatriptan, 7 infants were born with malformations (relative risk 1.01 [95% CI: 0.40 to 2.08]). A study using linked data from the Medical Birth Registry of Norway to the Norwegian Prescription Database compared pregnancy outcomes in women who redeemed prescriptions for triptans during pregnancy, as well as a migraine disease comparison group who redeemed prescriptions for triptans before pregnancy only, compared with a population control group.
Of the 310 women who redeemed prescriptions for rizatriptan during the first trimester, 10 had infants with major congenital malformations (OR 1.03 [95% CI: 0.55 to 1.93]), while for the 271 women who redeemed prescriptions for rizatriptan before, but not during, pregnancy, 12 had infants with major congenital malformations (OR 1.48 [95% CI: 0.83 to 2.64]), each compared with the population comparison group. Animal Data When rizatriptan (0, 2, 10, or 100 mg/kg/day) was administered orally to pregnant rats throughout organogenesis, a decrease in fetal body weight was observed at the highest doses tested.
At the mid dose (10 mg/kg/day), which was a no-effect dose for adverse effects on embryofetal development, plasma exposure (AUC) was approximately 15 times that in humans at the maximum recommended human dose (MRHD) of 30 mg/day. When rizatriptan (0, 5, 10, or 50 mg/kg/day) was administered orally to pregnant rabbits throughout organogenesis, no adverse fetal effects were observed. Plasma exposure (AUC) at the highest dose tested was 115 times that in humans at the MRHD.
Placental transfer of drug to the fetus was demonstrated in both species. Oral administration of rizatriptan (0, 2, 10, or 100 mg/kg/day) to female rats prior to and during mating and continuing throughout gestation and lactation resulted in reduced body weight in offspring… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients under 6 years of age have not been established. The efficacy and safety of riztriptan benzoate tablets in the acute treatment of migraine in patients aged 6 to 17 years was established in an adequate and well-controlled study [ see Clinical Studies ( 14.2 ) ]. The incidence of adverse reactions reported for pediatric patients in the acute clinical trial was similar in patients who received riztriptan benzoate tablets to those who received placebo.
The adverse reaction pattern in pediatric patients is expected to be similar to that in adults.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of rizatriptan benzoate did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. Although the pharmacokinetics of rizatriptan were similar in elderly (aged ≥ 65 years) and in younger adults (n = 17), in general, dose selection for an elderly patient should be cautious, starting at the low end of the dosing range.
This reflects the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy. Geriatric patients who have other cardiovascular risk factors (e.g., diabetes, hypertension, smoking, obesity, strong family history of coronary artery disease) should have a cardiovascular evaluation prior to receiving rizatriptan benzoate [see Warnings and Precautions ( 5.1 )] .
🆘 Overdosage ▾
10 OVERDOSAGE No overdoses of rizatriptan benzoate were reported during clinical trials in adults. Some adult patients who received 40 mg of rizatriptan benzoate either a single dose or as two doses with a 2-hour interdose interval had dizziness and somnolence. In a clinical pharmacology study in which 12 adult subjects received rizatriptan benzoate, at total cumulative doses of 80 mg (given within four hours), two of the subjects experienced syncope, dizziness, bradycardia including third degree AV block, vomiting, and/or incontinence.
In the long-term, open label study, involving 606 treated pediatric migraineurs 12 to 17 years of age (of which 432 were treated for at least 12 months), 151 patients (25%) took two 10-mg doses of rizatriptan benzoate orally disintegrating tablets within a 24-hour period. Adverse reactions for 3 of these patients included abdominal discomfort, fatigue, and dyspnea. In addition, based on the pharmacology of rizatriptan benzoate, hypertension or myocardial ischemia could occur after overdosage.
Gastrointestinal decontamination, (i.e., gastric lavage followed by activated charcoal) should be considered in patients suspected of an overdose with rizatriptan benzoate. Clinical and electrocardiographic monitoring should be continued for at least 12 hours, even if clinical symptoms are not observed. The effects of hemo- or peritoneal dialysis on serum concentrations of rizatriptan are unknown.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Rizatriptan binds with high affinity to human cloned 5-HT 1B/1D receptors. Rizatriptan presumably exerts its therapeutic effects in the treatment of migraine headache by binding to 5-HT 1B/1D receptors located on intracranial blood vessels and sensory nerves of the trigeminal system.
12.3Pharmacokinetics Absorption Rizatriptan is completely absorbed following oral administration. The mean oral absolute bioavailability of the rizatriptan benzoate tablet is about 45%, and mean peak plasma concentrations (C max ) are reached in approximately 1 to 1.5 hours (T max ). The presence of a migraine headache did not appear to affect the absorption or pharmacokinetics of rizatriptan.
Food has no significant effect on the bioavailability of rizatriptan but delays the time to reach peak concentration by an hour. In clinical trials, rizatriptan benzoate was administered without regard to food. The bioavailability and C max of rizatriptan were similar following administration of rizatriptan benzoate tablets and rizatriptan benzoate orally disintegrating tablets, but the rate of absorption is somewhat slower with rizatriptan benzoate orally disintegrating tablets, with T max delayed by up to 0.7 hour.
AUC of rizatriptan is approximately 30% higher in females than in males. No accumulation occurred on multiple dosing. Distribution The mean volume of distribution is approximately 140 liters in male subjects and 110 liters in female subjects.
Rizatriptan is minimally bound (14%) to plasma proteins. Metabolism The primary route of rizatriptan metabolism is via oxidative deamination by monoamine oxidase-A (MAO-A) to the indole acetic acid metabolite, which is not active at the 5-HT 1B/1D receptor. N-monodesmethyl-rizatriptan, a metabolite with activity similar to that of parent compound at the 5-HT 1B/1D receptor, is formed to a minor degree.
Plasma concentrations of N-monodesmethyl-rizatriptan are approximately 14% of those of parent compound, and it is eliminated at a similar rate. Other minor metabolites, the N-oxide, the 6-hydroxy compound, and the sulfate conjugate of the 6-hydroxy metabolite are not active at the 5-HT 1B/1D receptor. Elimination The total radioactivity of the administered dose recovered over 120 hours in urine and feces was 82% and 12%, respectively, following a single 10-mg oral administration of 14 C-rizatriptan.
Following oral administration of 14 C-rizatriptan, rizatriptan accounted for about 17% of circulating plasma radioactivity. Approximately 14% of an oral dose is excreted in urine as unchanged rizatriptan while 51% is excreted as indole acetic acid metabolite, indicating substantial first pass metabolism. The plasma half-life of rizatriptan in males and females averages 2 to 3 hours.
Cytochrome P450 Isoforms Rizatriptan is not an inhibitor of the activities of human liver cytochrome P450 isoforms 3A4/5, 1A2, 2C9, 2C19, or 2E1; rizatriptan is a competitive inhibitor (K i = 1400 nM) of cytochrome P450 2D6, but only at high, clinically irrelevant concentrations. Special Populations Geriatric: Rizatriptan pharmacokinetics in healthy elderly non-migraineur volunteers (age 65 to 77 years) were similar to those in younger non-migraineur volunteers (age 18 to 45 years). Pediatric: The pharmacokinetics of rizatriptan was determined in pediatric migraineurs 6 to 17 years of age.
Exposures following single dose administration of 5 mg rizatriptan orally disintegrating tablets to pediatric patients weighing 20 to 39 kg (44-87 lb) or 10 mg rizatriptan orally disintegrating tablets to pediatric patients weighing ≥40 kg (88 lb) were similar to those observed following single dose administration of 10 mg rizatriptan orally disintegrating tablets to adults. Gender: The mean AUC 0-∞ and C max of rizatriptan (10 mg orally) were about 30% and 11% higher in females as compared to males, respectively, while T max occurred at approximately the same time.
Hepatic impairment: Following oral… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Rizatriptan binds with high affinity to human cloned 5-HT 1B/1D receptors. Rizatriptan presumably exerts its therapeutic effects in the treatment of migraine headache by binding to 5-HT 1B/1D receptors located on intracranial blood vessels and sensory nerves of the trigeminal system.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Rizatriptan benzoate tablets, USP are available in strengths of 5 mg and 10 mg containing 7.265 mg or 14.53 mg of rizatriptan benzoate, USP equivalent to 5 mg or 10 mg of rizatriptan, respectively. The 5 mg tablets are pale pink, capsule-shaped, compressed tablets debossed with 'CL 33' on one side and plain on the other. They are available as follows: NDC 33342-087-07 container of 30 tablets NDC 33342-087-46 container of 200 tablets NDC 33342-087-12 Unit Dose Blister Package of 100 (10 x 10) tablets NDC 33342-087-50 Unit Dose Blister Package of 12 (4 x 3) tablets NDC 33342-087-72 Unit Dose Blister Package of 18 (6 x 3) tablets NDC 33342-087-45 Unit Dose Blister Package of 12 (2 x 6) tablets NDC 33342-087-41 Unit Dose Blister Package of 18 (3 x 6) tablets The 10 mg tablets are pale pink, capsule-shaped, compressed tablets debossed "CL 34" on one side and plain on the other.
They are available as follows: NDC 33342-088-07 container of 30 tablets NDC 33342-088-46 container of 200 tablets NDC 33342-088-12 Unit Dose Blister Package of 100 (10 x 10) tablets NDC 33342-088-50 Unit Dose Blister Package of 12 (4 x 3) tablets NDC 33342-088-72 Unit Dose Blister Package of 18 (6 x 3) tablets NDC 33342-088-45 Unit Dose Blister Package of 12 (2 x 6) tablets NDC 33342-088-41 Unit Dose Blister Package of 18 (3 x 6) tablets Store between 68ºF to 77ºF (20ºC to 25ºC). [See USP Controlled Room Temperature.] Preserve in well-closed, light-resistant containers.
📋 Description ▾
11 DESCRIPTION Rizatriptan benzoate tablets, USP contain rizatriptan benzoate, USP a selective 5-hydroxytryptamine 1B/1D (5-HT 1B/1D ) receptor agonist. Rizatriptan benzoate, USP is described chemically as: N,N -dimethyl-5-(1 H -1,2,4-triazol-1-ylmethyl)-1 H -indole-3-ethanamine monobenzoate and its structural formula is: Its molecular formula is C 15 H 19 N 5 C 7 H 6 O 2 , representing a molecular weight of the free base of 269.4. Rizatriptan benzoate, USP is a white to off-white, crystalline solid that is soluble in water at about 42 mg per mL (expressed as free base) at 25°C.
Rizatriptan benzoate tablets, USP are available for oral administration in strengths of 5 mg and 10 mg (corresponding to 7.265 mg or 14.53 mg of the benzoate salt, respectively). Each compressed tablet contains the following inactive ingredients: lactose monohydrate, microcrystalline cellulose, pregelatinized maize starch, ferric oxide (red), and magnesium stearate. 1
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Risk of Myocardial Ischemia and/or Infarction, Prinzmetal's Angina, Other Vasospasm-Related Events, and Cerebrovascular Events Inform patients that rizatriptan benzoate may cause serious cardiovascular side effects such as myocardial infarction or stroke. Although serious cardiovascular events can occur without warning symptoms, patients should be alert for the signs and symptoms of chest pain, shortness of breath, weakness, slurring of speech, and should ask for medical advice when observing any indicative sign or symptoms.
Patients should be apprised of the importance of this follow-up [see Warnings and Precautions ( 5.1 , 5.2 , 5.4 , 5.5 )] . Serotonin Syndrome Patients should be cautioned about the risk of serotonin syndrome with the use of rizatriptan benzoate or other triptans, particularly during combined use with selective serotonin reuptake inhibitors (SSRIs) or serotonin norepinephrine reuptake inhibitors (SNRIs) [see Warnings and Precautions ( 5.7 ), Drug Interactions ( 7.4 ), and Clinical Pharmacology ( 12.3 )] . Pregnancy Inform patients that rizatriptan benzoate should not be used during pregnancy unless the potential benefit justifies the potential risk to the fetus [see Use in Specific Populations ( 8.1 )] .
Lactation Advise patients to notify their healthcare provider if they are breastfeeding or plan to breastfeed [see Use in Specific Populations ( 8.2 )]. Ability to Perform Complex Tasks Since migraines or treatment with rizatriptan benzoate may cause somnolence and dizziness, instruct patients to evaluate their ability to perform complex tasks during migraine attacks and after administration of rizatriptan benzoate. Medication Overuse Headache Inform patients that use of acute migraine drugs for 10 or more days per month may lead to an exacerbation of headache, and encourage patients to record headache frequency and drug use (e.g., by keeping a headache diary) [see Warnings and Precautions ( 5.6 )] .
Manufactured for : Macleods Pharma USA, Inc. Princeton, NJ 08540 Manufactured by : Macleods Pharmaceuticals Ltd. Baddi, Himachal Pradesh, India.
Revised: 07/2022 .
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption Rizatriptan is completely absorbed following oral administration. The mean oral absolute bioavailability of the rizatriptan benzoate tablet is about 45%, and mean peak plasma concentrations (C max ) are reached in approximately 1 to 1.5 hours (T max ). The presence of a migraine headache did not appear to affect the absorption or pharmacokinetics of rizatriptan.
Food has no significant effect on the bioavailability of rizatriptan but delays the time to reach peak concentration by an hour. In clinical trials, rizatriptan benzoate was administered without regard to food. The bioavailability and C max of rizatriptan were similar following administration of rizatriptan benzoate tablets and rizatriptan benzoate orally disintegrating tablets, but the rate of absorption is somewhat slower with rizatriptan benzoate orally disintegrating tablets, with T max delayed by up to 0.7 hour.
AUC of rizatriptan is approximately 30% higher in females than in males. No accumulation occurred on multiple dosing. Distribution The mean volume of distribution is approximately 140 liters in male subjects and 110 liters in female subjects.
Rizatriptan is minimally bound (14%) to plasma proteins. Metabolism The primary route of rizatriptan metabolism is via oxidative deamination by monoamine oxidase-A (MAO-A) to the indole acetic acid metabolite, which is not active at the 5-HT 1B/1D receptor. N-monodesmethyl-rizatriptan, a metabolite with activity similar to that of parent compound at the 5-HT 1B/1D receptor, is formed to a minor degree.
Plasma concentrations of N-monodesmethyl-rizatriptan are approximately 14% of those of parent compound, and it is eliminated at a similar rate. Other minor metabolites, the N-oxide, the 6-hydroxy compound, and the sulfate conjugate of the 6-hydroxy metabolite are not active at the 5-HT 1B/1D receptor. Elimination The total radioactivity of the administered dose recovered over 120 hours in urine and feces was 82% and 12%, respectively, following a single 10-mg oral administration of 14 C-rizatriptan.
Following oral administration of 14 C-rizatriptan, rizatriptan accounted for about 17% of circulating plasma radioactivity. Approximately 14% of an oral dose is excreted in urine as unchanged rizatriptan while 51% is excreted as indole acetic acid metabolite, indicating substantial first pass metabolism. The plasma half-life of rizatriptan in males and females averages 2 to 3 hours.
Cytochrome P450 Isoforms Rizatriptan is not an inhibitor of the activities of human liver cytochrome P450 isoforms 3A4/5, 1A2, 2C9, 2C19, or 2E1; rizatriptan is a competitive inhibitor (K i = 1400 nM) of cytochrome P450 2D6, but only at high, clinically irrelevant concentrations. Special Populations Geriatric: Rizatriptan pharmacokinetics in healthy elderly non-migraineur volunteers (age 65 to 77 years) were similar to those in younger non-migraineur volunteers (age 18 to 45 years). Pediatric: The pharmacokinetics of rizatriptan was determined in pediatric migraineurs 6 to 17 years of age.
Exposures following single dose administration of 5 mg rizatriptan orally disintegrating tablets to pediatric patients weighing 20 to 39 kg (44-87 lb) or 10 mg rizatriptan orally disintegrating tablets to pediatric patients weighing ≥40 kg (88 lb) were similar to those observed following single dose administration of 10 mg rizatriptan orally disintegrating tablets to adults. Gender: The mean AUC 0-∞ and C max of rizatriptan (10 mg orally) were about 30% and 11% higher in females as compared to males, respectively, while T max occurred at approximately the same time.
Hepatic impairment: Following oral administration in patients with hepatic impairment caused by mild to moderate alcoholic cirrhosis of the liver, plasma concentrations of rizatriptan were similar in patients with mild hepatic insufficiency compared to a control group of subjects with normal hepatic function; plasma concentrations of rizatriptan were approximately 30… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Adults The efficacy of rizatriptan benzoate tablets was established in four multicenter, randomized, placebo-controlled trials. Patients enrolled in these studies were primarily female (84%) and Caucasian (88%), with a mean age of 40 years (range of 18 to 71). Patients were instructed to treat a moderate to severe headache.
Headache response, defined as a reduction of moderate or severe headache pain to no or mild headache pain, was assessed for up to 2 hours (Study 1) or up to 4 hours after dosing (Studies 2, 3 and 4). Associated symptoms of nausea, photophobia, and phonophobia and maintenance of response up to 24 hours post-dose were evaluated. A second dose of rizatriptan benzoate tablets was allowed 2 to 24 hours after dosing for treatment of recurrent headache in Studies 1 and 2.
Additional analgesics and/or antiemetics were allowed 2 hours after initial treatment for rescue in all four studies. In all studies, the percentage of patients achieving headache response 2 hours after treatment was significantly greater in patients who received either rizatriptan benzoate 5 mg or 10 mg compared to those who received placebo. In a separate study, doses of 2.5 mg were not different from placebo.
Doses greater than 10 mg were associated with an increased incidence of adverse effects. The results from the four controlled studies are summarized in Table 2. Table 2: Response Rates 2 Hours Following Treatment of Initial Headache in Studies 1, 2, 3, and 4 Study Placebo Rizatriptan Benzoate Tablets 5 mg Rizatriptan Benzoate Tablets 10 mg 1 35% (n=304) 62% * (n=458) 71% *,† (n=456) 2 ‡ 37% (n=82) — 77% * (n=320) 3 23% (n=80) 63% * (n=352) — 4 40% (n=159) 60% * (n=164) 67% * (n=385) * p-value < 0.05 in comparison with placebo. † p-value < 0.05 in comparison with 5 mg. ‡ Results for initial headache only.
Comparisons of drug performance based upon results obtained in different clinical trials may not be reliable. Because studies are conducted at different times, with different samples of patients, by different investigators, employing different criteria and/or different interpretations of the same criteria, under different conditions (dose, dosing regimen, etc.), quantitative estimates of treatment response and the timing of response may be expected to vary considerably from study to study. The estimated probability of achieving an initial headache response within 2 hours following treatment in pooled Studies 1, 2, 3, and 4 is depicted in Figure 1.
Figure 1: Estimated Probability of Achieving an Initial Headache Response by 2 Hours in Pooled Studies 1, 2, 3, and 4 * * Figure 1 shows the Kaplan-Meier plot of the probability over time of obtaining headache response (no or mild pain) following treatment with rizatriptan benzoate or placebo. The averages displayed are based on pooled data from 4 placebo-controlled, outpatient trials providing evidence of efficacy (Studies 1, 2, 3, and 4). Patients taking additional treatment or not achieving headache response prior to 2 hours were censored at 2 hours.
For patients with migraine-associated photophobia, phonophobia, and nausea at baseline, there was a decreased incidence of these symptoms following administration of rizatriptan benzoate compared to placebo. Two to 24 hours following the initial dose of study treatment, patients were allowed to use additional treatment for pain response in the form of a second dose of study treatment or other medication. The estimated probability of patients taking a second dose or other medication for migraine over the 24 hours following the initial dose of study treatment is summarized in Figure 2.
Figure 2: Estimated Probability of Patients Taking a Second Dose of Rizatriptan Benzoate Tablets or Other Medication for Migraines Over the 24 Hours Following the Initial Dose of Study Treatment in Pooled Studies 1, 2, 3, and 4* *This Kaplan-Meier plot is based on data obtained in 4 placebo-controlled outpatient clinical trials (Studies 1, 2,… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Oral carcinogenicity studies of rizatriptan were conducted in mice (100 weeks) and rats (106 weeks) at doses of up to 125 mg/kg/day. There was no evidence of an increase in tumor incidence related to rizatriptan in either species. Plasma exposures (AUC) at the highest dose tested were approximately 150 (mice) and 240 times (rats) that in humans at the maximum recommended human dose (MRHD) of 30 mg/day.
Mutagenesis Rizatriptan was neither mutagenic nor clastogenic in a battery of in vitro and in vivo genetic toxicity studies, including: the microbial mutagenesis (Ames) assay, in vitro mammalian cell mutagenesis and chromosomal aberration assays, and the in vivo chromosomal aberration assay in mouse. Impairment of Fertility Oral administration of rizatriptan (0, 2, 10, or 100 mg/kg/day) to female rats prior to and during mating and continuing throughout gestation and lactation resulted in no effect on fertility; however, altered estrous cyclicity and delays in time to mating were observed at the highest dose tested.
Plasma exposure at the no-effect dose (10 mg/kg/day) for reproductive toxicity was approximately 15 times that in humans at the MRHD. Oral administration of rizatriptan (0, 5, 35, or 250 mg/kg/day) to male rats prior to and during mating resulted in no impairment of fertility or reproductive performance. Plasma exposure (AUC) at the highest dose tested was approximately 550 times that in humans at the MRHD.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Oral carcinogenicity studies of rizatriptan were conducted in mice (100 weeks) and rats (106 weeks) at doses of up to 125 mg/kg/day. There was no evidence of an increase in tumor incidence related to rizatriptan in either species. Plasma exposures (AUC) at the highest dose tested were approximately 150 (mice) and 240 times (rats) that in humans at the maximum recommended human dose (MRHD) of 30 mg/day.
Mutagenesis Rizatriptan was neither mutagenic nor clastogenic in a battery of in vitro and in vivo genetic toxicity studies, including: the microbial mutagenesis (Ames) assay, in vitro mammalian cell mutagenesis and chromosomal aberration assays, and the in vivo chromosomal aberration assay in mouse. Impairment of Fertility Oral administration of rizatriptan (0, 2, 10, or 100 mg/kg/day) to female rats prior to and during mating and continuing throughout gestation and lactation resulted in no effect on fertility; however, altered estrous cyclicity and delays in time to mating were observed at the highest dose tested.
Plasma exposure at the no-effect dose (10 mg/kg/day) for reproductive toxicity was approximately 15 times that in humans at the MRHD. Oral administration of rizatriptan (0, 5, 35, or 250 mg/kg/day) to male rats prior to and during mating resulted in no impairment of fertility or reproductive performance. Plasma exposure (AUC) at the highest dose tested was approximately 550 times that in humans at the MRHD.
📄 Patient Package Insert ▾
SPL PATIENT PACKAGE INSERT .
📄 Package Label / Principal Display Panel ▾
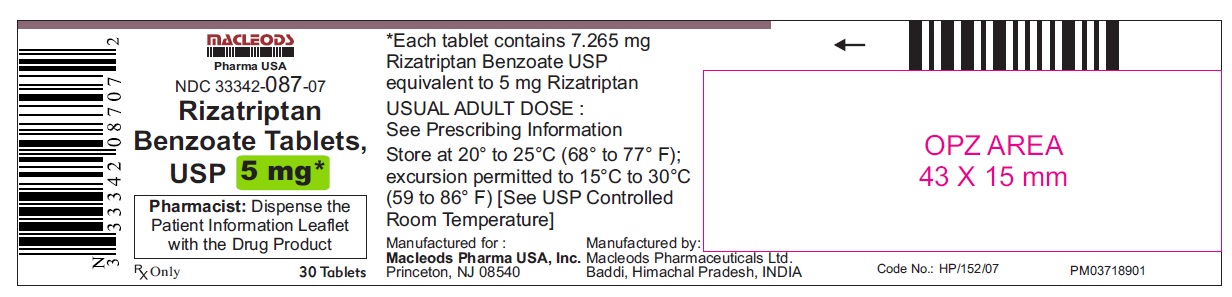
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL Rx Only NDC 33342-087-07 Rizatriptan Benzoate Tablets 5 mg 30 tablets Rx Only NDC 33342-087-46 Rizatriptan Benzoate Tablets 5 mg 200 tablets 505 Rx Only NDC 33342-088-07 Rizatriptan Benzoate Tablets 10 mg 30 tablets 505 Rx Only NDC 33342-088-46 Rizatriptan Benzoate Tablets 10 mg 200 tablets 505 Rx Only NDC 33342-087-50 Rizatriptan Benzoate Tablets 5 mg 12 (4x3)unit dose tablets Rx Only NDC 33342-087-45 Rizatriptan Benzoate Tablets 5 mg 12 (2x6)unit dose tablets 505 505 Rx Only NDC 33342-087-72 Rizatriptan Benzoate Tablets 5 mg 18 (6x3)unit dose tablets Rx Only NDC 33342-087-41 Rizatriptan Benzoate Tablets 5 mg 18 (3x6)unit dose tablets 505 505 Rx Only NDC 33342-088-50 Rizatriptan Benzoate Tablets 10 mg 12 (4x3)unit dose tablets Rx Only NDC 33342-088-45 Rizatriptan Benzoate Tablets 10 mg 12 (2x6)unit dose tablets 505 505 Rx Only NDC 33342-088-72 Rizatriptan Benzoate Tablets 10 mg 18 (6x3)unit dose tablets Rx Only NDC 33342-088-41 Rizatriptan Benzoate Tablets 10 mg 18 (3x6)unit dose tablets 505 505 505