
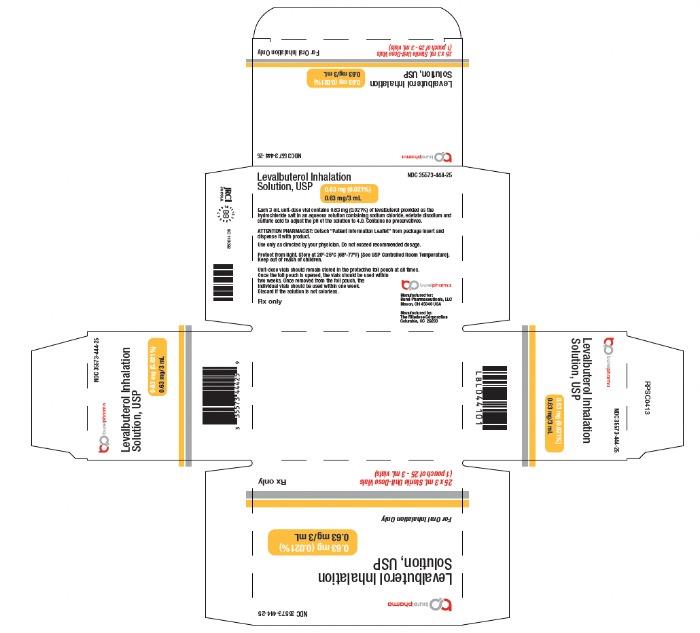
Levalbuterol .63 mg/3mL Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the beta2-Adrenergic Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Levalbuterol is a rescue bronchodilator — it's used to quickly open up your airways when they tighten up, like during an asthma attack or a flare of bronchospasm. Xopenex inhalatio...
- The concentrate form has to be diluted with sterile normal saline before you put it in the nebulizer — never use it straight from the vial without diluting first. You then breathe...
- How do I use the nebulizer solution correctly?
- The most common ones are shakiness (tremor), nervousness, a faster heartbeat, headache, and dizziness — especially when you first start using it. These are usually mild and tend to...
Patient education
Supplement & herbal interactions
Levalbuterol may be associated with lower levels of 2 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.241 | $452.06 / 1875 ml |
| Medicaid paysCMS SDUD · 12 mo | $0.3133 | $587.44 / 1875 ml |
| Medicare drug plans payPart D · Q2 2026 | $0.3242 | $607.88 / 1875 ml |
| Medicare Part B allowsASP · J7614 | $0.075 / J7614 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Levalbuterol .63 mg/3mL 00115-9931-78 | Amneal | 1 pouch | $0.241 | AN | Availability likely | — |
| Levalbuterol .63 mg/3mL 00378-9691-52 | Mylan | 1 pouch | $0.241 | AN | Availability likely | — |
| Levalbuterol .63 mg/3mLthis 35573-0444-25 | Burel | 25 pouches | $0.241 | AN | Availability likely | — |
| Levalbuterol .63 mg/3mL 65862-0944-24 | Aurobindo | 2 pouches | $0.334 | AN | FDA listed | +38% |
| Levalbuterol .63 mg/3mL 00093-4146-56 | Teva | 6 pouches | $0.344 | AN | Availability likely | +43% |
| Levalbuterol .63 mg/3mL 76204-0800-01 | Ritedose | 30 pouches | $0.344 | AN | Availability likely | +43% |
| Levalbuterol Inhalation Solution .63 mg/3mL 47335-0746-01 | Sun | 5 pouches | — | — | FDA listed | — |
| Levalbuterol .63 mg/3mL 50090-6377-00 | A-S | 1 pouch | — | AN | FDA listed | — |
| Levalbuterol .63 mg/3mL 63187-0953-24 | Proficient | 24 vials | — | AN | FDA listed | — |
| Levalbuterol .63 mg/3mL 72162-2082-02 | Bryant | 1 pouch | — | AN | FDA listed | — |
| Levalbuterol .63 mg/3mL 81894-0102-25 | Luoxin | 5 pouches | — | AN | FDA listed | — |
| Levalbuterol .63 mg/3mL 67296-2271-02 | Redpharm | 1 pouch | — | AN | FDA listed | — |
| Levalbuterol .63 mg/3mL 67296-2304-02 | Redpharm | 25 pouches | — | AN | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 35573-0444-25 You're viewing this | 25 POUCH in 1 CARTON (35573-444-25) / 25 VIAL, SINGLE-DOSE in 1 POUCH / 3 mL in 1 VIAL, SINGLE-DOSE | 2021-04-01 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Levalbuterol Inhalation Solution, USP is indicated for the treatment or prevention of bronchospasm in adults, adolescents, and children 6 years of age and older with reversible obstructive airway disease. Levalbuterol Inhalation Solution, USP is a beta 2 -adrenergic agonist indicated for: Treatment or prevention of bronchospasm in adults, adolescents, and children 6 years of age and older with reversible obstructive airway disease. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Levalbuterol Inhalation Solution, USP is for oral inhalation only. Administer by nebulization using with a standard jet nebulizer (with a face mask or mouthpiece) connected to an air compressor. Do not exceed recommended dose.
Children 6-11 years old: The recommended dosage of Levalbuterol Inhalation Solution, USP for patients 6-11 years old is 0.31 mg administered three times a day, by nebulization. Routine dosing should not exceed 0.63 mg three times a day. Adults and Adolescents ≥ 12 years old: The recommended starting dosage of Levalbuterol Inhalation Solution, USP for patients 12 years of age and older is 0.63 mg administered three times a day, every 6 to 8 hours, by nebulization.
Patients 12 years of age and older with more severe asthma or patients who do not respond adequately to a dose of 0.63 mg of Levalbuterol Inhalation Solution, USP may benefit from a dosage of 1.25 mg three times a day. Patients receiving the highest dose of Levalbuterol Inhalation Solution, USP should be monitored closely for adverse systemic effects, and the risks of such effects should be balanced against the potential for improved efficacy. The use of Levalbuterol Inhalation Solution, USP can be continued as medically indicated to help control recurring bouts of bronchospasm.
During this time, most patients gain optimal benefit from regular use of the inhalation solution. If a previously effective dosage regimen fails to provide the usual response this may be a marker of destabilization of asthma and requires reevaluation of the patient and the treatment regimen, giving special consideration to the possible need for anti-inflammatory treatment, e.g., corticosteroids. The drug compatibility (physical and chemical), efficacy, and safety of Levalbuterol Inhalation Solution, USP when mixed with other drugs in a nebulizer have not been established.
The safety and efficacy of Levalbuterol Inhalation Solution, USP have been established in clinical trials when administered using the PARI LC Jet™ and PARI LC Plus™ nebulizers, and the PARI Master ® Dura-Neb ® 2000 and Dura-Neb ® 3000 compressors. The safety and efficacy of Levalbuterol Inhalation Solution, USP when administered using other nebulizer systems have not been established. FOR ORAL INHALATION ONLY ( 2 ) Children 6-11 years old: 0.31 mg administered three times a day, by nebulization.
Routine dosing should not exceed 0.63 mg three times a day. ( 2 ) Adults and Adolescents ≥ 12 years old: 0.63 mg administered three times a day, every 6 to 8 hours, by nebulization. The maximum recommended dose is 1.25 mg three times a day.
( 2 ) For use with a standard jet nebulizer (with a face mask or mouthpiece) connected to an air compressor. ( 2 )
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Inhalation Solution 3 mL unit-dose, vials in three dosage strengths of levalbuterol; 0.31 mg, 0.63 mg, 1.25 mg. Each strength of Levalbuterol Inhalation Solution, USP is available in a shelf carton containing one or more foil pouches, each pouch containing one or more unit-dose vials. Inhalation Solution (unit-dose vial for nebulization): 0.31 mg/3 mL, 0.63 mg/3 mL and 1.25 mg/3 mL. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Levalbuterol Inhalation Solution, USP is contraindicated in patients with a history of hypersensitivity to levalbuterol or racemic albuterol. Reactions have included urticaria, angioedema, rash, bronchospasm, anaphylaxis, and oropharyngeal edema [see Warnings and Precautions ( 5.6 ) ]. Hypersensitivity to levalbuterol or racemic albuterol. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Life-threatening paradoxical bronchospasm may occur. Discontinue Levalbuterol Inhalation Solution, USP immediately and treat with alternative therapy. ( 5.1 ) Need for more doses of Levalbuterol Inhalation Solution, USP than usual may be a sign of deterioration of asthma and requires reevaluation of treatment.
( 5.2 ) Levalbuterol Inhalation Solution, USP is not a substitute for corticosteroids. ( 5.3 ) Cardiovascular effects may occur. Consider discontinuation of Levalbuterol Inhalation Solution, USP if these effects occur.
Use with caution in patients with underlying cardiovascular disorders. ( 5.4 ) Excessive use may be fatal. Do not exceed recommended dose.
( 5.5 ) Immediate hypersensitivity reactions may occur. Discontinue Levalbuterol Inhalation Solution, USP immediately. ( 5.6 ) Hypokalemia and changes in blood glucose may occur.
( 5.7 , 5.8 )
5.1Paradoxical Bronchospasm Levalbuterol Inhalation Solution, USP can produce paradoxical bronchospasm, which may be life-threatening. If paradoxical bronchospasm occurs, Levalbuterol Inhalation Solution, USP should be discontinued immediately and alternative therapy instituted. It should be recognized that paradoxical bronchospasm, when associated with inhaled formulations, frequently occurs with the first use of a new vial.
5.2Deterioration of Asthma Asthma may deteriorate acutely over a period of hours or chronically over several days or longer. If the patient needs more doses of Levalbuterol Inhalation Solution, USP than usual, this may be a marker of destabilization of asthma and requires reevaluation of the patient and treatment regimen, giving special consideration to the possible need for anti-inflammatory treatment, e.g., corticosteroids.
5.3Use of Anti-Inflammatory Agents Levalbuterol Inhalation Solution, USP is not a substitute for corticosteroids. The use of beta-adrenergic agonist alone may not be adequate to control asthma in many patients. Early consideration should be given to adding anti-inflammatory agents, e.g., corticosteroids, to the therapeutic regimen.
5.4Cardiovascular Effects Levalbuterol Inhalation Solution, USP, like other beta-adrenergic agonists, can produce clinically significant cardiovascular effects in some patients, as measured by heart rate, blood pressure, and symptoms. Although such effects are uncommon after administration of Levalbuterol Inhalation Solution, USP at recommended doses, if they occur, the drug may need to be discontinued. In addition, beta-agonists have been reported to produce electrocardiogram (ECG) changes, such as flattening of the t-wave, prolongation of the QTc interval, and ST segment depression.
The clinical significance of these findings is unknown. Therefore, Levalbuterol Inhalation Solution, USP, like all sympathomimetic amines, should be used with caution in patients with cardiovascular disorders, especially coronary insufficiency, cardiac arrhythmias, and hypertension.
5.5Do Not Exceed Recommended Dose Do not exceed the recommended dose. Fatalities have been reported in association with excessive use of inhaled sympathomimetic drugs in patients with asthma. The exact cause of death is unknown, but cardiac arrest following an unexpected development of a severe acute asthmatic crisis and subsequent hypoxia is suspected.
5.6Immediate Hypersensitivity Reactions Immediate hypersensitivity reactions may occur after administration of levalbuterol or racemic albuterol. Reactions have included urticaria, angioedema, rash, bronchospasm, anaphylaxis, and oropharyngeal edema. The potential for hypersensitivity must be considered in the clinical evaluation of patients who experience immediate hypersensitivity reactions while receiving Levalbuterol Inhalation Solution, USP.
5.7Coexisting Conditions Levalbuterol Inhalation Solution, USP, like all sympathomimetic amines, should be used with caution in patients with cardiovascular disorders, especially coronary insufficiency, hypertension, and cardi…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described below and elsewhere in the labeling: Paradoxical bronchospasm [see Warnings and Precautions ( 5.1) ] Cardiovascular effects [see Warnings and Precautions ( 5.4 ) ] Immediate hypersensitivity reactions [see Warnings and Precautions ( 5.6 ) ] Hypokalemia [see Warnings and Precautions ( 5.8 ) ] Most common adverse reactions are: palpitations, chest pain, tachycardia, headache, dizziness, tremor and nervousness. ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact The Ritedose Corporation, LLC at 1-855-806-3300 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of the drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adults and Adolescents 12 Years of Age and Older Adverse reaction information concerning Levalbuterol Inhalation Solution, USP in adults and adolescents is derived from one 4-week, multicenter, randomized, double-blind, active-, and placebo-controlled trial in 362 patients with asthma 12 years of age and older.
Adverse reactions reported in ≥ 2% of patients receiving Levalbuterol Inhalation Solution, USP or racemic albuterol and more frequently than in patients receiving placebo are listed in Table 1. Table 1 - Adverse Reactions Reported in a 4-Week, Controlled Clinical Trial in Adults and Adolescents ≥ 12 Years Old Percent of Patients a Body System Preferred Term Placebo (n = 75) Levalbuterol Inhalation Solution, USP 1.25 mg (n = 73) Levalbuterol Inhalation Solution, USP 0.63 mg (n = 72) Racemic albuterol 2.5 mg (n = 74) Body as a Whole Allergic reaction 1.3 0 0
2.7Flu syndrome 0 1.4 4.2
2.7Accidental injury 0 2.7 0 0 Pain 1.3 1.4 2.8
2.7 Back pain 0 0 0
2.7Cardiovascular System Tachycardia 0 2.7 2.8
2.7Migraine 0 2.7 0 0 Digestive System Dyspepsia 1.3 2.7 1.4
1.4Musculoskeletal System Leg cramps 1.3 2.7 0
1.4Central Nervous System Dizziness 1.3 2.7 1.4 0 Hypertonia 0 0 0
2.7Nervousness 0 9.6 2.8
8.1Tremor 0 6.8 0
2.7Anxiety 0 2.7 0 0 Respiratory System Cough increased 2.7 4.1 1.4
2.7Infection viral 9.3 12.3 6.9
12.2Rhinitis 2.7 2.7 11.1
6.8Sinusitis 2.7 1.4 4.2
2.7Turbinate edema 0 1.4 2.8 0 a One treatment group, racemic albuterol 1.25 mg, with 68 subjects is omitted. The incidence of certain systemic beta-adrenergic adverse reactions (e.g., tremor, nervousness) was slightly less in the Levalbuterol Inhalation Solution, USP 0.63 mg group compared with the other active treatment groups. The clinical significance of these small differences is unknown.
Changes in heart rate 15 minutes after drug administration and in plasma glucose and potassium 1 hour after drug administration on day 1 and day 29 were clinically comparable in the Levalbuterol Inhalation Solution, USP 1.25 mg and racemic albuterol 2.5 mg groups (see Table 2). Changes in heart rate and plasma glucose were slightly less in the Levalbuterol Inhalation Solution, USP 0.63 mg group compared with the other active treatment groups (see Table 2). The clinical significance of these small differences is unknown.
After 4 weeks, effects on heart rate, plasma glucose, and plasma potassium were generally diminished compared with day 1 in all active treatment groups. Table 2 - Mean Changes from Baseline Heart Rate at 15 Minutes and Glucose and Potassium at 1 Hour after First Dose (Day 1) in Adults and Adolescents ≥ 12 Years Old Mean Changes (Day 1) Treatment Heart Rate (bpm) Glucose (mg/dL) Potassium (mEq/L) Levalbuterol Inhalation Solution, USP 0.63 mg, n = 72 2.4 4.6 -0.2 Levalbuterol Inhalation Solution, USP 1.25 mg, n = 73 6.9 10.3 -0.3 Racemic albuterol 2.5 mg, n = 74 5.7 8.2 -0.3 Placebo, n = 75 -2.8 -0.2 -0.2 No other clinically relevant laboratory abnormalities related to administration of Levalbuterol Inhalation Solution, USP were obse…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Other short-acting sympathomimetic aerosol bronchodilators and adrenergic drugs: May potentiate effect. ( 7.1 ) Beta-blockers: May block bronchodilatory effects of beta-agonists and produce severe bronchospasm. Patients with asthma should not normally be treated with beta-blockers.
( 7.2 ) Diuretic: May worsen electrocardiographic changes or hypokalemia associated with diuretic may worsen. Consider monitoring potassium levels. ( 7.3 ) Digoxin: May decrease serum digoxin levels.
Consider monitoring digoxin levels. ( 7.4 ) Monoamine oxidase inhibitors (MAOs) or tricyclic antidepressants: May potentiate effect of albuterol on the cardiovascular system. ( 7.5 )
7.1Short-Acting Bronchodilators Avoid concomitant use of other short-acting sympathomimetic bronchodilators or epinephrine in patients being treated with Levalbuterol Inhalation Solution, USP. If additional adrenergic drugs are to be administered by any route, they should be used with caution to avoid deleterious cardiovascular effects.
7.2Beta-blockers Beta-adrenergic receptor blocking agents not only block the pulmonary effect of beta-adrenergic agonists such as Levalbuterol Inhalation Solution, USP, but may produce severe bronchospasm in asthmatic patients. Therefore, patients with asthma should not normally be treated with beta-blockers. However, under certain circumstances, e.g., prophylaxis after myocardial infarction, there may be no acceptable alternatives to the use of beta-adrenergic blocking agents in patients with asthma.
In this setting, cardioselective beta-blockers should be considered, although they should be administered with caution.
7.3Diuretics The ECG changes or hypokalemia that may result from the administration of non-potassium-sparing diuretics (such as loop and thiazide diuretics) can be acutely worsened by beta-agonists, especially when the recommended dose of the beta-agonist is exceeded. Although the clinical significance of these effects is not known, caution is advised in the coadministration of beta-agonists with non-potassium-sparing diuretics. Consider monitoring potassium levels.
7.4Digoxin Mean decreases of 16% and 22% in serum digoxin levels were demonstrated after single-dose intravenous and oral administration of racemic albuterol, respectively, to normal volunteers who had received digoxin for 10 days. The clinical significance of these findings for patients with obstructive airway disease who are receiving Levalbuterol Inhalation Solution, USP and digoxin on a chronic basis is unclear. Nevertheless, it would be prudent to carefully evaluate the serum digoxin levels in patients who are currently receiving digoxin and Levalbuterol Inhalation Solution, USP.
7.5Monoamine Oxidase Inhibitors or Tricyclic Antidepressants Levalbuterol Inhalation Solution, USP should be administered with extreme caution to patients being treated with monoamine oxidase inhibitors or tricyclic antidepressants, or within 2 weeks of discontinuation of such agents, because the action of levalbuterol on the vascular system may be potentiated. Consider alternative therapy in patients taking MAO inhibitors or tricyclic antidepressants.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no adequate and well-controlled studies of Levalbuterol Inhalation Solution, USP in pregnant women. There are clinical considerations with the use of Levalbuterol Inhalation Solution, USP in pregnant women [see Clinical Considerations] . Following oral administration of levalbuterol HCl to pregnant rabbits, there was no evidence of teratogenicity at doses up to 25 mg/kg/day [approximately 108 times the maximum recommended human daily inhalation dose (MRHDID) of levalbuterol HCl for adults on a mg/m 2 basis]; however, racemic albuterol sulfate was teratogenic in mice (cleft palate) and rabbits (cramioschisis) at doses slightly higher than the human therapeutic range ( see Data ).
The estimated background risk of major birth defects and miscarriage for the indicated population(s) are unknown. In the U.S. general population, the estimated risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20% respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk In women with poorly or moderately controlled asthma, there is an increased risk of preeclampsia in the mother and prematurity, low birth weight, and small for gestational age in the neonate.
Pregnant women should be closely monitored and medication adjusted as necessary to maintain optimal control. Labor or Delivery Because of the potential for beta-adrenergic agonists to interfere with uterine contractility, the use of Levalbuterol Inhalation Solution, USP for the treatment of bronchospasm during labor should be restricted to those patients for whom the benefits clearly outweigh the risk. Levalbuterol Inhalation Solution, USP has not been approved for the management of preterm labor.
The benefit-risk ratio when Levalbuterol Inhalation Solution, USP is administered for tocolysis has not been established. Serious adverse reactions, including maternal pulmonary edema, have been reported during or following treatment of premature labor with beta 2 -agonists, including racemic albuterol. Data Animal Data The oral administration of levalbuterol HCl to pregnant New Zealand White rabbits during the period of organogenesis found no evidence of teratogenicity at doses up to 25 mg/kg/day (approximately 108 times the MRHDID of levalbuterol HCl for adults on a mg/m 2 basis).
In a rat developmental study, racemic albuterol sulfate administered by inhalation did not produce any teratogenic effects at exposures approximately 63 times the MRHDID (on a mg/m 2 basis at a maternal dose of 10.5 mg/kg). However, other developmental studies with the racemic albuterol sulfate, did result in teratogenic effects in mice and rabbits at doses slightly higher than the human therapeutic range. In a rabbit developmental study, orally administered albuterol sulfate induced cranioschisis in 7 of 19 fetuses (37%) at approximately 215 times the MRHDID for adults (on a mg/m 2 basis at a maternal dose of 50 mg/kg).
In a mouse developmental study, subcutaneously administered albuterol sulfate produced cleft palate formation in 5 of 111 (4.5%) fetuses at an exposure approximately 0.3 times the MRHDID for adults (on a mg/m 2 basis at a maternal dose of 0.25 mg/kg/day) and in 10 of 108 (9.3%) fetuses at approximately 3 times the MRHDID (on a mg/m 2 basis at a maternal dose of 2.5 mg/kg/day). Similar effects were not observed at approximately 0.03 times the MRHDID for adults on a mg/m 2 basis at a maternal dose of 0.025 mg/kg/day (i.e., less than the therapeutic dose).
Cleft palate also occurred in 22 of 72 (30.5%) fetuses from females treated subcutaneously with isoproterenol (positive control).
8.2Lactation Risk Summary There are no available data on the presence of levalbuterol in human milk, the effects on the breastfed child, or the effects on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical ne…
🆘 Overdosage ▾
10 OVERDOSAGE The expected symptoms with overdosage are those of excessive beta-adrenergic receptor stimulation and/or occurrence or exaggeration of any of the symptoms listed under Adverse Reactions ( 6 ) , e.g., seizures, angina, hypertension or hypotension, tachycardia with rates up to 200 beats/min., arrhythmias, nervousness, headache, tremor, dry mouth, palpitation, nausea, dizziness, fatigue, malaise, and sleeplessness. Hypokalemia also may occur. As with all sympathomimetic medications, cardiac arrest and even death may be associated with the abuse of Levalbuterol Inhalation Solution, USP.
Treatment consists of discontinuation of Levalbuterol Inhalation Solution, USP together with appropriate symptomatic therapy. The judicious use of a cardioselective beta-receptor blocker may be considered, bearing in mind that such medication can produce bronchospasm. There is insufficient evidence to determine if dialysis is beneficial for overdosage of Levalbuterol Inhalation Solution, USP.
🧬 Clinical Pharmacology ▾
12 Clinical Pharmacology
12.1Mechanism of Action Activation of beta 2 -adrenergic receptors on airway smooth muscle leads to the activation of adenylate cyclase and to an increase in the intracellular concentration of cyclic-3′, 5′-adenosine monophosphate (cyclic AMP). The increase in cyclic AMP is associated with the activation of protein kinase A, which in turn inhibits the phosphorylation of myosin and lowers intracellular ionic calcium concentrations, resulting in muscle relaxation. Levalbuterol relaxes the smooth muscles of all airways, from the trachea to the terminal bronchioles.
Increased cyclic AMP concentrations are also associated with the inhibition of release of mediators from mast cells in the airway. Levalbuterol acts as a functional antagonist to relax the airway irrespective of the spasmogen involved, thus protecting against all bronchoconstrictor challenges. While it is recognized that beta 2 -adrenergic receptors are the predominant receptors on bronchial smooth muscle, data indicate that there are beta-receptors in the human heart, 10% to 50% of which are beta 2 -adrenergic receptors.
The precise function of these receptors has not been established [see Warnings and Precautions (5.4) ]. However, all beta-adrenergic agonist drugs can produce a significant cardiovascular effect in some patients, as measured by pulse rate, blood pressure, symptoms, and/or electrocardiographic changes.
12.2Pharmacodynamics Adults and Adolescents ≥ 12 Years Old In a randomized, double-blind, placebo-controlled, cross-over study, 20 adults with mild-to-moderate asthma received single doses of Levalbuterol Inhalation Solution, USP (0.31 mg, 0.63 mg, and 1.25 mg) and racemic albuterol sulfate inhalation solution (2.5 mg). All doses of active treatment produced a significantly greater degree of bronchodilation (as measured by percent change from pre-dose mean FEV 1 ) than placebo, and there were no significant differences between any of the active treatment arms.
The bronchodilator responses to 1.25 mg of Levalbuterol Inhalation Solution, USP and 2.5 mg of racemic albuterol sulfate inhalation solution were clinically comparable over the 6-hour evaluation period, except for a slightly longer duration of action (> 15% increase in FEV 1 from baseline) after administration of 1.25 mg of Levalbuterol Inhalation Solution, USP. Systemic beta-adrenergic adverse effects were observed with all active doses and were generally dose-related for (R)-albuterol. Levalbuterol Inhalation Solution, USP at a dose of 1.25 mg produced a slightly higher rate of systemic beta-adrenergic adverse effects than the 2.5 mg dose of racemic albuterol sulfate inhalation solution.
In a randomized, double-blind, placebo-controlled, cross-over study, 12 adults with mild-to-moderate asthma were challenged with inhaled methacholine chloride 20 and 180 minutes following administration of a single dose of 2.5 mg of racemic albuterol sulfate, 1.25 mg of Levalbuterol Inhalation Solution, USP, 1.25 mg of (S)-albuterol, or placebo using a Pari LC Jet™ nebulizer. Racemic albuterol sulfate, Levalbuterol Inhalation Solution, USP, and (S)-albuterol had a protective effect against methacholine-induced bronchoconstriction 20 minutes after administration, although the effect of (S)-albuterol was minimal.
At 180 minutes after administration, the bronchoprotective effect of 1.25 mg of Levalbuterol Inhalation Solution, USP was comparable to that of 2.5 mg of racemic albuterol sulfate. At 180 minutes after administration, 1.25 mg of (S)-albuterol had no bronchoprotective effect. In a clinical study in adults with mild-to-moderate asthma, comparable efficacy (as measured by change from baseline FEV 1 ) and safety (as measured by heart rate, blood pressure, ECG, serum potassium, and tremor) were demonstrated after a cumulative dose of 5 mg of Levalbuterol Inhalation Solution, USP (four consecutive doses of 1.25 mg administered every 30 minutes) and 10 mg of racemic albuterol sulfate in…
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Levalbuterol Inhalation Solution, USP is supplied in 3 mL unit-dose, low-density polyethylene (LDPE) vials as a clear, colorless, sterile, preservative-free, aqueous solution, in three different strengths of levalbuterol (0.31 mg, 0.63 mg, 1.25 mg). Each strength of Levalbuterol Inhalation Solution, USP is available in a shelf-carton containing one foil pouch of 25 unit-dose LDPE vials. Levalbuterol Inhalation Solution, USP, 0.31 mg/3 mL ( foil pouch label color green ) contains 0.31 mg/3 mL (0.0103%) of levalbuterol (as 0.36 mg/3 mL of levalbuterol HCl) and is available in cartons as listed below.
NDC 35573-443-25 25 vials per carton / 25 vials per foil pouch Levalbuterol Inhalation Solution, USP, 0.63 mg/3 mL ( foil pouch label color yellow ) contains 0.63 mg/3 mL (0.021%) of levalbuterol (as 0.73 mg/3 mL of levalbuterol HCl) and is available in cartons as listed below. NDC 35573-444-25 25 vials per carton / 25 vials per foil pouch Levalbuterol Inhalation Solution, USP, 1.25 mg/3 mL ( foil pouch label color red ) contains 1.25 mg/3 mL (0.042%) of levalbuterol (as 1.44 mg/3 mL of levalbuterol HCl) and is available in cartons as listed below.
NDC 35573-445-25 25 vials per carton / 25 vials per foil pouch Store Levalbuterol Inhalation Solution, USP in the protective foil pouch at 20°- 25°C (68°- 77°F) [see USP Controlled Room Temperature]. Protect from light and excessive heat. Keep unopened vials in the foil pouch.
Once the foil pouch is opened, the vials should be used within 2 weeks. Vials removed from the pouch, if not used immediately, should be protected from light and used within 1 week. Discard any vial if the solution is not colorless.
Rx only
📋 Description ▾
11 DESCRIPTION Levalbuterol Inhalation Solution, USP is a sterile, clear, colorless, preservative-free solution of the hydrochloride salt of levalbuterol, the (R)-enantiomer of the drug substance racemic albuterol. Levalbuterol HCl is a relatively selective beta 2 -adrenergic receptor agonist [see Clinical Pharmacology ( 12 ) ]. The chemical name for levalbuterol HCl is (R)-α 1 -[[(1,1-dimethylethyl)amino]methyl]-4-hydroxy-1,3-benzenedimethanol hydrochloride, and its established chemical structure is as follows: The molecular weight of levalbuterol HCl is 275.8, and its empirical formula is C 13 H 21 NO 3 •HCl.
It is a white to off-white, crystalline solid, with a melting point of approximately 187°C and solubility of approximately 180 mg/mL in water. Levalbuterol HCl is the USAN modified name for (R)-albuterol HCl in the United States. Levalbuterol Inhalation Solution, USP is supplied in unit-dose vials and requires no dilution before administration by nebulization.
Each 3 mL unit-dose vial contains 0.31 mg/3 mL (0.0103%) of levalbuterol (as 0.36 mg/3 mL of levalbuterol HCl) or 0.63 mg/3 mL (0.021%) of levalbuterol (as 0.73 mg/3 mL of levalbuterol HCl) or 1.25 mg/3 mL (0.042%) of levalbuterol (as 1.44 mg/3 mL of levalbuterol HCl), sodium chloride to adjust tonicity, edetate disodium (EDTA) as a stabilizer for the active pharmaceutical ingredient, and sulfuric acid to adjust the pH to 4.0 (3.3 to 4.5). Chem Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA-approved patient labeling (Patient Information Leaflet and Instructions for Using Levalbuterol Inhalation Solution, USP). Patients should be given the following information: Hypersensitivity Query patients about previously experienced hypersensitivity to levalbuterol or racemic albuterol and counsel patients to report any hypersensitivity reactions to their physician. Frequency of Use Inform patients not to increase the dose or use Levalbuterol Inhalation Solution, USP more frequently than recommended without consulting their physician.
If patients find that treatment with Levalbuterol Inhalation Solution, USP becomes less effective for symptomatic relief, symptoms become worse, or they need to use the product more frequently than usual, they should seek medical attention immediately. Paradoxical Bronchospasm Inform patients that Levalbuterol Inhalation Solution, USP can produce paradoxical bronchospasm. Instruct patients to discontinue Levalbuterol Inhalation Solution, USP if paradoxical bronchospasm occurs.
Concomitant Drug Use Inform patients using Levalbuterol Inhalation Solution, USP, that other inhaled drugs and asthma medications should be taken only as directed by their physician. Common Adverse Reactions Advise patients of the common adverse reactions of treatment with Levalbuterol Inhalation Solution, USP include palpitations, chest pain, fast heart rate, headache, dizziness, tremor and nervousness. Pregnancy Advise patients who are pregnant or nursing to contact their physician about the use of Levalbuterol Inhalation Solution, USP.
General Information on Storage and Use Advise patients to store Levalbuterol Inhalation Solution, USP in the foil pouch at 20°- 25°C (68°-77°F) protected from light and excessive heat. Do not use after the expiration date stamped on the container. Store unused vials in the protective foil pouch.
Once the foil pouch is opened, use the vials within 2 weeks. Use vials removed from the pouch immediately, or protect from light and use within 1 week. Discard any vial if the solution is not colorless.
Advise patients not to mix Levalbuterol Inhalation Solution, USP with other drugs in a nebulizer. Manufactured for: Burel Pharmaceuticals,LLC Mason, OH 45040 USA Manufactured by: The Ritedose Corporation Columbia, SC 29203 USA To report SUSPECTED ADVERSE REACTIONS, contact The Ritedose Corporation at 1-855-806-3300 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch . Revised: 07/2021 RPIN0147 logo