
PHENYTOIN SODIUM 50 mg/mL Injection
Past resolved recalls for this product (2)
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Anti-epileptic Agent class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Phenytoin is an antiseizure medication — it's used to treat and prevent different types of seizures, including tonic-clonic (grand mal) seizures, complex partial seizures, and seiz...
- The most important thing is to take it exactly as prescribed and not skip doses. If you're on chewable tablets or the liquid suspension, those are not once-a-day medications — they...
- How do I take phenytoin correctly — are there any tricks I should know?
- The most common side effects involve your nervous system — things like dizziness, unsteady walking, slurred speech, drowsiness, and rapid eye movements. These are often dose-relate...
Patient education
Supplement & herbal interactions
Phenytoin may be associated with lower levels of 13 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
0.1 mL / 1 mL
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
0.4 mL / 1 mL
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Phenytoin Sodium 50 mg/mL 51662-1250-01 | HF | 5 ml | — | AP | FDA listed | — |
| Phenytoin Sodium 50 mg/mL 71872-7079-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Phenytoin Sodium 50 mg/mL 00641-6138-25 | Hikma | 25 vials | — | AP | FDA listed | — |
| Phenytoin Sodium 50 mg/mLthis 42192-0614-03 | Acella | 25 vials | — | AP | FDA listed | — |
| Phenytoin Sodium 50 mg/mL 84549-0093-25 | ProPharma | 2 ml | — | AP | FDA listed | — |
| Phenytoin Sodium 50 mg/mL 51662-1251-01 | HF | 2 ml | — | AP | FDA listed | — |
| Phenytoin Sodium 50 mg/mL 00404-9932-02 | Henry | 1 vial | — | AP | FDA listed | — |
| Phenytoin Sodium 50 mg/mL 00641-2555-45 | Hikma | 25 vials | — | AP | FDA listed | — |
| Phenytoin Sodium 50 mg/mL 00404-9808-05 | Henry | 1 vial | — | AP | FDA listed | — |
| Phenytoin Sodium 50 mg/mL 00641-0493-25 | Hikma | 25 vials | — | AP | FDA listed | — |
| Phenytoin Sodium 50 mg/mL 00641-6139-25 | Hikma | 25 vials | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 42192-0614-03 You're viewing this | 25 VIAL in 1 CARTON (42192-614-03) / 2 mL in 1 VIAL | 2021-12-30 | Active |
| 42192-0614-06 | 25 VIAL in 1 CARTON (42192-614-06) / 5 mL in 1 VIAL | 2021-12-30 | Active |
| 42192-0614-10 | 10 VIAL in 1 CARTON (42192-614-10) / 2 mL in 1 VIAL | 2021-12-30 | Active |
| 42192-0614-30 | 10 VIAL in 1 CARTON (42192-614-30) / 5 mL in 1 VIAL | 2021-12-30 | Active |
Pack size FAQ
What quantity is in NDC 42192-0614-03?
What NDC number is used to bill for this package of PHENYTOIN SODIUM 50 mg/mL Injection?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: CARDIOVASCULAR RISK ASSOCIATED WITH RAPID INFUSION The rate of intravenous phenytoin sodium injection administration should not exceed 50 mg per minute in adults and 1 to 3 mg/kg/min (or 50 mg per minute, whichever is slower) in pediatric patients because of the risk of severe hypotension and cardiac arrhythmias. Careful cardiac monitoring is needed during and after administering intravenous phenytoin sodium injection. Although the risk of cardiovascular toxicity increases with infusion rates above the recommended infusion rate, these events have also been reported at or below the recommended infusion rate.
Reduction in rate of administration or discontinuation of dosing may be needed [see Dosage and Administration (2.1) and Warnings and Precautions (5.1) ]. WARNING: CARDIOVASCULAR RISK ASSOCIATED WITH RAPID INFUSION See full prescribing information for complete boxed warning. The rate of intravenous phenytoin sodium injection administration should not exceed 50 mg per minute in adults and 1 to 3 mg/kg/min (or 50 mg per minute, whichever is slower) in pediatric patients because of the risk of severe hypotension and cardiac arrhythmias.
Careful cardiac monitoring is needed during and after administering intravenous phenytoin sodium injection. Reduction in rate of administration or discontinuation of dosing may be needed ( 2.1 , 5.1 ).
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Parenteral Phenytoin Sodium Injection is indicated for the treatment of generalized tonic-clonic status epilepticus, and prevention and treatment of seizures occurring during neurosurgery. Intravenous Phenytoin Sodium Injection can also be substituted, as short-term use, for oral phenytoin. Parenteral Phenytoin should be used only when oral phenytoin administration is not possible [ see Dosage and Administration ( 2.1 , 2.3 ) and Warnings and Precautions (5.1) ].
Parenteral phenytoin sodium injection is indicated for the treatment of generalized tonic-clonic status epilepticus and prevention and treatment of seizures occurring during neurosurgery. Intravenous phenytoin can also be substituted, as short-term use, for oral phenytoin. Parenteral phenytoin should be used only when oral phenytoin administration is not possible.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION For Status Epilepticus and Non-emergent Loading Dose: Adult loading dose is 10 to 15 mg/kg at a rate not exceeding 50 mg/min. ( 2.2 ) Pediatric loading dose is 15 to 20 mg/kg at a rate not exceeding 1 to 3 mg/kg/min or 50 mg/min, whichever is slower. ( 2.8 ) Continuous monitoring of the electrocardiogram, blood pressure, and respiratory function is essential.
( 2.2 ) Maintenance Dosing: Initial loading dose should be followed by maintenance doses of oral or intravenous phenytoin sodium injection every 6 to 8 hours. ( 2.2 , 2.3 ) Intramuscular Administration: Because of erratic absorption and local toxicity, phenytoin sodium injection should ordinarily not be given intramuscularly. ( 2.2 , 2.3 )
2.1General Dosing Information Because of the increased risk of adverse cardiovascular reactions associated with rapid administration, intravenous administration should not exceed 50 mg per minute in adults. In pediatric patients, the drug should be administered at a rate not exceeding 1 to 3 mg/kg/min or 50 mg per minute, whichever is slower. As non-emergency therapy, phenytoin sodium injection should be administered more slowly as either a loading dose or by intermittent infusion.
Because of the risks of cardiac and local toxicity associated with intravenous phenytoin sodium injection, oral phenytoin should be used whenever possible. Because adverse cardiovascular reactions have occurred during and after infusions, careful cardiac monitoring is needed during and after the administration of intravenous phenytoin sodium injection. Reduction in rate of administration or discontinuation of dosing may be needed.
Because of the risk of local toxicity, intravenous phenytoin sodium injection should be administered directly into a large peripheral or central vein through a large-gauge catheter. Prior to the administration, the patency of the intravenous (IV) catheter should be tested with a flush of sterile saline. Each injection of parenteral phenytoin sodium injection should then be followed by a flush of sterile saline through the same catheter to avoid local venous irritation due to the alkalinity of the solution.
Phenytoin sodium injection can be given diluted with normal saline. The addition of parenteral phenytoin sodium injection to dextrose and dextrose-containing solutions should be avoided due to lack of solubility and resultant precipitation. Treatment with phenytoin sodium injection can be initiated either with a loading dose or an infusion: Loading Dose: A loading dose of parenteral phenytoin sodium injection should be injected slowly, not exceeding 50 mg per minute in adults and 1 to 3 mg/kg/min (or 50 mg per minute, whichever is slower) in pediatric patients.
Infusion: For infusion administration, parenteral phenytoin sodium injection should be diluted in normal saline with the final concentration of phenytoin sodium in the solution no less than 5 mg/mL. Administration should commence immediately after the mixture has been prepared and must be completed within 1 to 4 hours (the infusion mixture should not be refrigerated). An in-line filter (0.22 to 0.55 microns) should be used.
Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution or container permit. The diluted infusion mixture (phenytoin sodium injection plus normal saline) should not be refrigerated. If the undiluted parenteral phenytoin sodium injection is refrigerated or frozen, a precipitate might form: this will dissolve again after the solution is allowed to stand at room temperature.
The product is still suitable for use. A faint yellow coloration may develop, however this has no effect on the potency of the solution. For single-dose only.
After opening, any unused product should be discarded. Monitoring Levels: Trough levels provide information about clinically effective serum level range and are obtained just prior to the patient’s next scheduled dose. Pe…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Phenytoin Sodium Injection, USP: 50 mg phenytoin sodium per milliliter, colorless to slightly yellow solution available as: 2-mL single-dose vials (100 mg/2 mL (50 mg/mL)) 5-mL single-dose vials (250 mg/5 mL (50 mg/mL)) Injection: 50 mg phenytoin sodium per milliliter in: 2 mL and 5 mL single dose vials ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Phenytoin sodium injection is contraindicated in patients with: A history of hypersensitivity to phenytoin, its inactive ingredients, or other hydantoins [see Warnings and Precautions (5.5) ] . Sinus bradycardia, sino-atrial block, second and third degree A-V block, and Adams-Stokes syndrome because of the effect of parenteral phenytoin on ventricular automaticity. A history of prior acute hepatotoxicity attributable to phenytoin [see Warnings and Precautions (5.6) ] .
Coadministration with delavirdine because of the potential for loss of virologic response and possible resistance to delavirdine or to the class of non-nucleoside reverse transcriptase inhibitors. Hypersensitivity to phenytoin, its ingredients, or other hydantoins ( 4 ) Sinus bradycardia, sino-atrial block, second and third degree A-V block, and Adams-Stokes syndrome ( 4 ) A history of prior acute hepatotoxicity attributable to phenytoin ( 4 , 5.6 ) Coadministration with delavirdine ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Withdrawal Precipitated Seizure: May precipitate status epilepticus. Dose reductions or discontinuation should be done gradually. ( 5.2 ) Serious Dermatologic Reactions: Discontinue Phenytoin sodium injection at the first sign of a rash, unless the rash is clearly not drug-related.
If signs or symptoms suggest SJS/TEN, use of this drug should not be resumed and alternative therapy should be considered. ( 5.3 ) Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)/Multiorgan Hypersensitivity: If signs or symptoms of hypersensitivity are present, evaluate the patient immediately. Discontinue if an alternative etiology cannot be established.
( 5.4 ) Hematopoietic Complications: If occurs, follow-up observation is indicated and an alternative antiepileptic treatment should be used. ( 5.7 )
5.1Cardiovascular Risk Associated with Rapid Infusion Rapid intravenous administration of phenytoin sodium injection increases the risk of adverse cardiovascular reactions, including severe hypotension and cardiac arrhythmias. Cardiac arrhythmias have included bradycardia, heart block, ventricular tachycardia, and ventricular fibrillation which have resulted in asystole, cardiac arrest, and death. Severe complications are most commonly encountered in critically ill patients, elderly patients, and patients with hypotension and severe myocardial insufficiency.
However, cardiac events have also been reported in adults and children without underlying cardiac disease or comorbidities and at recommended doses and infusion rates. Intravenous administration should not exceed 50 mg per minute in adults. In pediatric patients, administer the drug at a rate not exceeding 1 to 3 mg/kg/min or 50 mg per minute, whichever is slower.
Although the risk of cardiovascular toxicity increases with infusion rates above the recommended infusion rate, these events have also been reported at or below the recommended infusion rate. As non-emergency therapy, phenytoin sodium injection should be administered more slowly as either a loading dose or by intermittent infusion. Because of the risks of cardiac and local toxicity associated with intravenous phenytoin sodium injection, oral phenytoin should be used whenever possible.
Because adverse cardiovascular reactions have occurred during and after infusions, careful cardiac and respiratory monitoring is needed during and after the administration of intravenous phenytoin sodium injection. Reduction in rate of administration or discontinuation of dosing may be needed.
5.2Withdrawal Precipitated Seizure, Status Epilepticus Antiepileptic drugs should not be abruptly discontinued because of the possibility of increased seizure frequency, including status epilepticus. When, in the judgment of the clinician, the need for dosage reduction, discontinuation, or substitution of alternative antiepileptic medication arises, this should be done gradually. However, in the event of an allergic or hypersensitivity reaction, rapid substitution of alternative therapy may be necessary.
In this case, alternative therapy should be an antiepileptic drug not belonging to the hydantoin chemical class.
5.3Serious Dermatologic Reactions Serious and sometimes fatal dermatologic reactions, including toxic epidermal necrolysis (TEN) and Stevens- Johnson syndrome (SJS), have been reported with phenytoin treatment. The onset of symptoms is usually within 28 days, but can occur later. Phenytoin should be discontinued at the first sign of a rash, unless the rash is clearly not drug-related.
If signs or symptoms suggest SJS/TEN, use of this drug should not be resumed and alternative therapy should be considered. If a rash occurs, the patient should be evaluated for signs and symptoms of Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS) [ see Warnings and Precautions (5.4) ]. Studies in patients of Chinese ancestry have found a strong association between the risk of developing SJS/TEN and the presence of HLA-B…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described elsewhere in the labeling: Cardiovascular Risk Associated with Rapid Infusion [see Warnings and Precautions (5.1) ] Withdrawal Precipitated Seizure, Status Epilepticus [see Warnings and Precautions (5.2) ] Serious Dermatologic Reactions [see Warnings and Precautions (5.3) ] Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)/Multiorgan Hypersensitivity [see Warnings and Precautions (5.4) ] Hypersensitivity [see Warnings and Precautions (5.5) ] Hepatic Injury [see Warnings and Precautions (5.6) ] Hematopoietic Complications [see Warnings and Precautions (5.7) ] Local toxicity (Including Purple Glove Syndrome) [see Warnings and Precautions (5.8) ] Exacerbation of Porphyria [see Warnings and Precautions (5.10) ] Teratogenicity and Other Harm to the Newborn [see Warnings and Precautions (5.11) ] Hyperglycemia [see Warnings and Precautions (5.12) ] The following adverse reactions associated with the use of phenytoin sodium injection were identified in clinical studies or postmarketing reports.
Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. The most notable signs of toxicity associated with the intravenous use of this drug are cardiovascular collapse and/or central nervous system depression. Hypotension does occur when the drug is administered rapidly by the intravenous route.
The rate of administration is very important; it should not exceed 50 mg per minute in adults, and 1 to 3 mg/kg/min (or 50 mg per minute, whichever is slower) in pediatric patients [See Boxed Warning, Dosage and Administration (2.1) , and Warnings and Precautions (5.1) ] . Body As a Whole: Allergic reactions in the form of rash and rarely more serious forms (see Skin and Appendages paragraph below) and DRESS [see Warnings and Precautions (5.4) ] have been observed. Anaphylaxis has also been reported.
There have also been reports of coarsening of facial features, systemic lupus erythematosus, periarteritis nodosa, and immunoglobulin abnormalities. Cardiovascular: Severe cardiovascular events and fatalities have been reported with atrial and ventricular conduction depression and ventricular fibrillation. Severe complications are most commonly encountered in elderly or critically ill patients [see Boxed Warning and Warnings and Precautions (5.1) ] .
Digestive System: Acute hepatic failure [see Warnings and Precautions (5.6) ] , toxic hepatitis, liver damage, nausea, vomiting, constipation, enlargement of the lips, and gingival hyperplasia. Hematologic and Lymphatic System: Hematopoietic complications, some fatal, have occasionally been reported in association with administration of phenytoin [see Warnings and Precautions (5.7) ] . These have included thrombocytopenia, leukopenia, granulocytopenia, agranulocytosis, and pancytopenia with or without bone marrow suppression.
While macrocytosis and megaloblastic anemia have occurred, these conditions usually respond to folic acid therapy. Lymphadenopathy, including benign lymph node hyperplasia, pseudolymphoma, lymphoma, and Hodgkin's Disease have been reported [see Warnings and Precautions (5.7) ] . Laboratory Test Abnormality: Phenytoin may decrease serum concentrations of thyroid hormone (T4 and T3), sometimes with an accompanying increase in thyroid-stimulating hormone (TSH), but usually in the absence of clinical hypothyroidism.
Phenytoin may also produce lower than normal values for dexamethasone or metyrapone tests. Phenytoin may also cause increased serum levels of glucose, alkaline phosphatase, and gamma glutamyl transpeptidase (GGT). Nervous System: The most common adverse reactions encountered with phenytoin therapy are nervous system reactions and are usually dose-related.
Reactions include nystagmus, ataxia, slurred speech, decreased coordination, somnolence, and mental…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Phenytoin is extensively bound to plasma proteins and is prone to competitive displacement. Phenytoin is primarily metabolized by hepatic cytochrome P450 enzymes CYP2C9 and to a lesser extent by CYP2C19 and is particularly susceptible to inhibitory drug interactions because it is subject to saturable metabolism. Inhibition of metabolism may produce significant increases in circulating phenytoin concentrations and enhance the risk of drug toxicity.
Monitoring of phenytoin serum levels is recommended when a drug interaction is suspected. Phenytoin is a potent inducer of hepatic drug-metabolizing enzymes. Multiple drug interactions because of extensive plasma protein binding, saturable metabolism and potent induction of hepatic enzymes.
( 7.1 , 7.2 )
7.1Drugs that Affect Phenytoin Concentrations Table 1 includes commonly occurring drug interactions that affect phenytoin concentrations. However, this list is not intended to be inclusive or comprehensive. Individual prescribing information from relevant drugs should be consulted.
The addition or withdrawal of these agents in patients on phenytoin therapy may require an adjustment of the phenytoin dose to achieve optimal clinical outcome. Table 1: Drugs That Affect Phenytoin Concentrations Interacting Agent Examples Drugs that may increase phenytoin serum levels Antiepileptic drugs Ethosuximide, felbamate, oxcarbazepine, methsuximide, topiramate Azoles Fluconazole, ketoconazole, itraconazole, miconazole, voriconazole Antineoplastic agents Capecitabine, fluorouracil Antidepressants Fluoxetine, fluvoxamine, sertraline Gastric acid reducing agents H2 antagonists (cimetidine), omeprazole Sulfonamides Sulfamethizole, sulfaphenazole, sulfadiazine, sulfamethoxazole trimethoprim Other Acute alcohol intake, amiodarone, chloramphenicol, chlordiazepoxide, disulfiram, estrogen, fluvastatin, isoniazid, methylphenidate, phenothiazines, salicylates, ticlopidine, tolbutamide, trazodone, warfarin Drugs that may decrease phenytoin serum levels Antineoplastic agents usually in combination Bleomycin, carboplatin, cisplatin, doxorubicin, methotrexate Antiviral agents Fosamprenavir, nelfinavir, ritonavir Antiepileptic drugs Carbamazepine, vigabatrin Other Chronic alcohol abuse, diazepam, diazoxide, folic acid, reserpine, rifampin, St.
John’s wortb, theophylline Drugs that may either increase or decrease phenytoin serum levels Antiepileptic drugs Phenobarbital, valproate sodium, valproic acid b The induction potency of St. John’s wort may vary widely based on preparation.
7.2Drugs Affected by Phenytoin Table 2 includes commonly occurring drug interactions affected by phenytoin. However, this list is not intended to be inclusive or comprehensive. Individual drug package inserts should be consulted.
The addition or withdrawal of phenytoin during concomitant therapy with these agents may require adjustment of the dose of these agents to achieve optimal clinical outcome. Table 2: Drugs Affected by Phenytoin Interacting Agent Examples Drugs whose efficacy is impaired by phenytoin Azoles Fluconazole, ketoconazole, itraconazole, posaconazole, voriconazole Antineoplastic agents Irinotecan, paclitaxel, teniposide Delavirdine Phenytoin can substantially reduce the concentrations of delavirdine. This can lead to loss of virologic response and possible resistance [see Contraindications (4) ] .
Neuromuscular blocking agents Cisatracurium, pancuronium, rocuronium and vecuronium: resistance to the neuromuscular blocking action of the nondepolarizing neuromuscular blocking agents has occurred in patients chronically administered phenytoin. Whether or not phenytoin has the same effect on other non-depolarizing agents is unknown. Prevention or Management: Patients should be monitored closely for more rapid recovery from neuromuscular blockade than expected, and infusion rate requirements may be higher.
Warfarin Increased and decreased PT/INR responses have been reported when phenytoin is coadminister…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Prenatal exposure to phenytoin may increase the risks for congenital malformations and other adverse developmental outcomes. ( 5.11 , 8.1 ) Renal and/or Hepatic Impairment or Hypoalbuminemia: Monitor unbound phenytoin concentrations in these patients. ( 8.6 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antiepileptic drugs (AEDs), such as Phenytoin Sodium Injection, during pregnancy. Physicians are advised to recommend that pregnant patients taking phenytoin enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry. This can be done by calling the toll free number 1-888-233-2334, and must be done by patients themselves.
Information on the registry can also be found at the website http://www.aedpregnancyregistry.org/ . Risk Summary In humans, prenatal exposure to phenytoin may increase the risks for congenital malformations and other adverse developmental outcomes. An increased incidence of major malformations (such as orofacial clefts and cardiac defects) and abnormalities characteristic of fetal hydantoin syndrome (dysmorphic skull and facial features, nail and digit hypoplasia, growth abnormalities [including microcephaly], and cognitive deficits) has been reported among children born to epileptic women who took phenytoin alone or in combination with other antiepileptic drugs during pregnancy.
There have been several reported cases of malignancies, including neuroblastoma, in children whose mothers received phenytoin during pregnancy. Administration of phenytoin to pregnant animals resulted in an increased incidence of fetal malformations and other manifestations of developmental toxicity (including embryofetal death, growth impairment, and behavioral abnormalities) in multiple species at clinically relevant doses [see Data]. In the U.S. general population, the estimated background risk of major birth defects and of miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
The overall incidence of malformations for children of epileptic women treated with antiepileptic drugs (phenytoin and /or others) during pregnancy is about 10%, or two- to three-fold that in the general population. Clinical Considerations Disease-associated maternal risk An increase in seizure frequency may occur during pregnancy because of altered phenytoin pharmacokinetics. Periodic measurement of serum phenytoin concentrations may be valuable in the management of pregnant women as a guide to appropriate adjustment of dosage [see Dosage and Administration ( 2.1 , 2.7 )] .
However, postpartum restoration of the original dosage will probably be indicated. Fetal/Neonatal adverse reactions A potentially life-threatening bleeding disorder related to decreased levels of vitamin K-dependent clotting factors may occur in newborns exposed to phenytoin in utero. This drug-induced condition can be prevented with vitamin K administration to the mother before delivery and to the neonate after birth.
Data Animal Data Administration of phenytoin to pregnant rats, rabbits, and mice during organogenesis resulted in embryofetal death, fetal malformations, and decreased fetal growth retardation. Malformations (including craniofacial, cardiovascular, neural, limb, and digit abnormalities) were observed in rats, rabbits, and mice at doses as low as 100, 75, and 12.5 mg/kg, respectively.
8.2Lactation Risk Summary Phenytoin is secreted in human milk. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for phenytoin sodium injection and any potential adverse effects on the breastfed infant from phenytoin sodium injection or from the underlying maternal condition.
8.4Pediatric Use A loading dose of 15 to 20 mg/kg of phenytoin sodium injection intravenously will usually produce serum concentrations of phenytoin within the generally accepted serum…
🆘 Overdosage ▾
10 OVERDOSAGE The lethal dose in pediatric patients is not known. The lethal dose in adults is estimated to be 2 to 5 grams. The initial symptoms are nystagmus, ataxia, and dysarthria.
Other signs are tremor, hyperreflexia, lethargy, slurred speech, blurred vision, nausea, and vomiting. The patient may become comatose and hypotensive. Death is caused by respiratory and circulatory depression.
There are marked variations among individuals with respect to phenytoin serum levels where toxicity may occur. Nystagmus, on lateral gaze, usually appears at 20 mcg/mL, ataxia at 30 mcg/mL, dysarthria and lethargy appear when the serum concentration is over 40 mcg/mL, but as high a concentration as 50 mcg/mL has been reported without evidence of toxicity. As much as 25 times the therapeutic dose has been taken to result in a serum concentration over 100 mcg/mL with complete recovery.
Irreversible cerebellar dysfunction and atrophy have been reported. Treatment: Treatment is nonspecific since there is no known antidote. The adequacy of the respiratory and circulatory systems should be carefully observed and appropriate supportive measures employed.
Hemodialysis can be considered since phenytoin is not completely bound to plasma proteins. Total exchange transfusion has been used in the treatment of severe intoxication in pediatric patients. In acute overdosage the possibility of other CNS depressants, including alcohol, should be borne in mind.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The precise mechanism by which phenytoin exerts its therapeutic effect has not been established but is thought to involve the voltage-dependent blockade of membrane sodium channels resulting in a reduction in sustained high-frequency neuronal discharges.
12.3Pharmacokinetics Absorption A fall in serum levels may occur when patients are changed from oral to intramuscular administration. The drop is caused by slower absorption, as compared to oral administration, because of the poor water solubility of phenytoin. Intravenous administration is the preferred route for producing rapid therapeutic serum levels.
Patients stabilized on a daily oral regimen of phenytoin experience a drop in peak blood levels to 50 to 60 percent of stable levels if crossed over to an equal dose administered intramuscularly. However, the intramuscular depot of poorly soluble material is eventually absorbed, as determined by urinary excretion of 5-(p-hydroxyphenyl)-5-phenylhydantoin (HPPH), the principal metabolite, as well as the total amount of drug eventually appearing in the blood. As phenytoin is highly protein bound, free phenytoin levels may be altered in patients whose protein binding characteristics differ from normal.
A short-term (one week) study indicates that patients do not experience the expected drop in blood levels when crossed over to the intramuscular route if the phenytoin sodium injection IM dose is increased by 50 percent over the previously established oral dose. To avoid drug accumulation caused by absorption from the muscle depots, it is recommended that for the first week back on oral phenytoin, the dose be reduced to half of the original oral dose (one-third of the IM dose). Experience for periods greater than one week is lacking and blood level monitoring is recommended.
Therapeutic effect without clinical signs of toxicity occurs most often with serum total concentrations between 10 and 20 mcg/mL (unbound phenytoin concentrations of 1 to 2 mcg/mL). Distribution Phenytoin is extensively bound to plasma proteins and is prone to competitive displacement. Elimination The serum half-life in man after intravenous administration ranges from 10 to 15 hours.
Metabolism Phenytoin is metabolized by the hepatic cytochrome P450 enzymes CYP2C9 and to a lesser extent by CYP2C19. Excretion Most of the drug is excreted in the bile as inactive metabolites. Urinary excretion of phenytoin and its metabolites occurs partly by glomerular filtration but, more importantly, by tubular secretion.
Specific Populations Age: Geriatric Population: Phenytoin clearance tends to decrease with increasing age (20% less in patients over 70 years of age relative to that in patients 20 to 30 years of age). Since phenytoin clearance is decreased slightly in elderly patients, lower or less frequent dosing may be required [see Dosage and Administration (2.6) ] . Sex/Race: Gender and race have no significant impact on phenytoin pharmacokinetics.
Renal or Hepatic Impairment: Increased fraction of unbound phenytoin in patients with renal or hepatic disease, or in those with hypoalbuminemia has been reported. Pregnancy: It has been reported in the literature that the plasma clearance of phenytoin generally increased during pregnancy, reached a peak in the third trimester and returned to the level of pre-pregnancy after few weeks or months of delivery. Drug Interaction Studies Phenytoin is primarily metabolized by the hepatic cytochrome P450 enzymes CYP2C9 and to a lesser extent by CYP2C19.
Phenytoin is a potent inducer of hepatic drug-metabolizing enzymes [see Drug Interactions ( 7.1 , 7.2 )] .
12.4Pharmacogenomics CYP2C9 activity is decreased in individuals with genetic variants such as the CYP2C9*2 and CYP2C9*3 alleles. Carriers of variant alleles, resulting in intermediate (e.g., *1/*3, *2/*2) or poor metabolism (e.g., *2/*3, *3/*3) have decreased clearance of phenytoin. Other decreased or nonfunctional CYP2C9 allele…
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
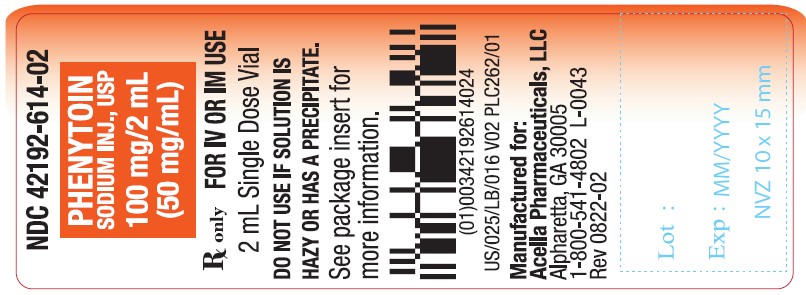
16.1How Supplied Phenytoin Sodium Injection, USP - 100 mg/2 mL (50 mg/mL) – in 2 mL vials (NDC 42192-614-02) packaged in cartons of 25 (NDC 42192-614-03) and cartons of 10 (NDC 42192-614-10). Phenytoin Sodium Injection, USP - 250 mg/5 mL (50 mg/mL) – in 5 mL vials (NDC 42192-614-05) packaged in cartons of 25 (NDC 42192-614-06) and cartons of 10 (NDC 42192-614-30).
16.2Storage and Handling For single-dose only. After opening, any unused product should be discarded. Store at 20° to 25°C (68° to 77°F), excursions permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature ].
📋 Description ▾
11 DESCRIPTION Phenytoin Sodium Injection, USP is a sterile solution of 50 mg phenytoin sodium per milliliter for intravenous or intramuscular administration. The solution is in a vehicle containing 40% propylene glycol and 10% alcohol in water for injection, adjusted to pH 12 with sodium hydroxide. Phenytoin sodium is related to the barbiturates in chemical structure, but has a five-membered ring.
The chemical name is sodium 5,5-diphenyl-2, 4- imidazolidinedione represented by the following structural formula: C 15 H 11 N 2 NaO 2 MW 274.25 structural formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Withdrawal of Antiepileptic Drugs Advise patients not to discontinue use of phenytoin sodium injection without consulting with their healthcare provider. phenytoin sodium injection should normally be gradually withdrawn to reduce the potential for increased seizure frequency and status epilepticus [see Warnings and Precautions (5.2) ] . Potential Signs of Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS) and Other Systemic Reactions Advise patients of the early toxic signs and symptoms of potential hematologic, dermatologic, hypersensitivity, or hepatic reactions.
These symptoms may include, but are not limited to, fever, sore throat, rash, ulcers in the mouth, easy bruising, lymphadenopathy, facial swelling, and petechial or purpuric hemorrhage, and in the case of liver reactions, anorexia, nausea/vomiting, or jaundice. Advise the patient that, because these signs and symptoms may signal a serious reaction, that they must report any occurrence immediately to a physician. In addition, advise the patient that these signs and symptoms should be reported even if mild or when occurring after extended use [see Warnings and Precautions ( 5.3 , 5.4 , 5.5 , 5.6 , 5.7 )] .
Effects of Alcohol Use and Other Drugs and Over-the-Counter Drug Interactions Caution patients against the use of other drugs or alcoholic beverages without first seeking their physician’s advice [see Warnings and Precautions (5.9) and Drug Interactions ( 7.1 , 7.2 )] . Inform patients that certain over-the-counter medications (e.g., cimetidine and omeprazole), vitamins (e.g., folic acid), and herbal supplements (e.g., St. John’s wort) can alter their phenytoin levels.
Hyperglycemia Advise patients that phenytoin may cause an increase in blood glucose levels [see Warnings and Precautions (5.12 ) ] . Gingival Hyperplasia Advise patients of the importance of good dental hygiene in order to minimize the development of gingival hyperplasia and its complications. Neurologic Effects Counsel patients that phenytoin sodium injection may cause dizziness, gait disturbance, decreased coordination and somnolence.
Advise patients taking phenytoin sodium injection not to drive, operate complex machinery, or engage in other hazardous activities until they have become accustomed to any such effects associated with phenytoin sodium injection. Use in Pregnancy Inform pregnant women and women of childbearing potential that use of phenytoin sodium injection during pregnancy can cause fetal harm, including an increased risk for cleft lip and/or cleft palate (oral clefts), cardiac defects, dysmorphic skull and facial features, nail and digit hypoplasia, growth abnormalities (including microcephaly), and cognitive deficits.
When appropriate, counsel pregnant women and women of childbearing potential about alternative therapeutic options. Advise women of childbearing potential who are not planning a pregnancy to use effective contraception while using phenytoin sodium injection, keeping in mind that there is a potential for decreased hormonal contraceptive efficacy [see Drug Interactions (7.2) ] . Instruct patients to notify their physician if they become pregnant or intend to become pregnant during therapy, and to notify their physician if they are breastfeeding or intend to breastfeed during therapy [see Use in Specific Populations ( 8.1 , 8.2 )] .
Encourage patients to enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry if they become pregnant. This registry is collecting information about the safety of antiepileptic drugs during pregnancy [see Use in Specific Populations (8.1) ] . Caution - Federal law prohibits dispensing without prescription.
Warning- Manufactured with CFC-12, a substance which harms public health and the environment by destroying ozone in the upper atmosphere. Rx only Manufactured by: Maiva Pharma Private Limited Plot NO. 32, SIPCOT Industrial Complex, Phase I, Hosur-635126, India Distributed by: Ac…