
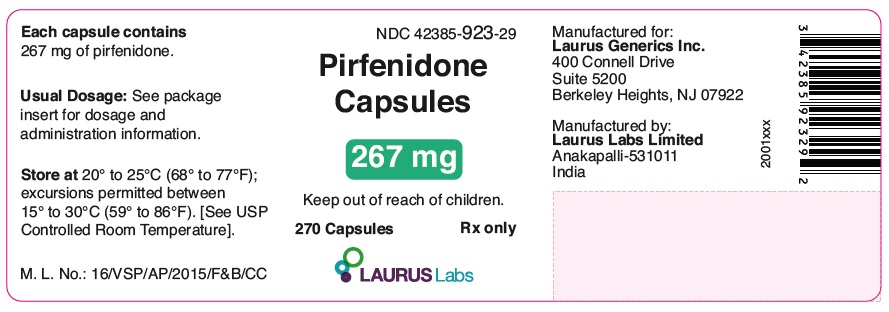
Pirfenidone 267 mg Capsule, 270-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Pyridone class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Pirfenidone is used for the treatment of idiopathic pulmonary fibrosis (scarring of the lungs with an unknown cause). Pirfenidone is in a class of medications called pyridones. It works by blocking the action of a certain natural substance in the body that is involved in causing fibrosis.
Read the full MedlinePlus article ↗- Pirfenidone is used specifically to treat idiopathic pulmonary fibrosis — or IPF — a condition where the lungs gradually develop scar tissue, making breathing harder over time. It'...
- What exactly is pirfenidone used for, and how does it help?
- Yes — it really does matter. You should always take pirfenidone with food, every time. Taking it on an empty stomach raises the peak level of the drug in your blood too quickly, wh...
- The most common ones — especially in the first few months — are nausea, stomach pain, diarrhea, decreased appetite, fatigue, and rash. Most of these tend to ease up over time, and...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Pirfenidone — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 1N032N7MFO
A brown-colored mineral form of iron oxide used as a colorant in tablets and capsules. It gives medicines their brown or tan appearance without affecting how the drug works.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII S870P55O2W
Isomalt is a sugar alcohol made from sugar that's used as a sweetener and bulking agent in medicines. It helps give tablets and powders the right texture and sweetness while having minimal calories.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII MB5IUD6JUA
Shellac is a natural resin secreted by lac beetles, purified and processed into a coating material. It seals and protects tablets and capsules, controls how quickly the medicine dissolves, and gives pills their glossy finish.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $1.652 | $445.91 / 270 capsules |
| Medicaid paysCMS SDUD · 12 mo | $1.72 | $465.26 / 270 capsules |
| Medicare drug plans payPart D · Q2 2026 | $24.12 | $6,512.40 / 270 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Pirfenidone 267 mg 00781-2158-32 | Sandoz | 270 capsules | $1.652 | AB | Availability likely | — |
| Pirfenidone 267 mgthis 42385-0923-29 | Laurus | 270 capsules | $1.652 | AB | Availability likely | — |
| Pirfenidone 267 mg 60219-1642-07 | Amneal | 270 capsules | $1.652 | AB | Availability likely | — |
| Pirfenidone 267 mg 76282-0715-27 | EXELAN | 270 capsules | $1.652 | AB | Availability likely | — |
| Pirfenidone Capsule, 267 mg 33342-0461-38 | Macleods | 63 capsules | — | AB | FDA listed | — |
| Pirfenidone 267 mg 42291-0490-27 | AvKARE | 270 capsules | — | AB | FDA listed | — |
| Pirfenidone 267 mg 50228-0441-05 | ScieGen | 500 capsules | — | AB | FDA listed | — |
| Pirfenidone 267 mg 59651-0244-27 | Aurobindo | 270 capsules | — | AB | FDA listed | — |
| Pirfenidone 267 mg 69097-0940-04 | Cipla | 90 capsules | — | AB | FDA listed | — |
| Pirfenidone 267 mg 69238-1642-07 | Amneal | 270 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 42385-0923-29 You're viewing this | 270 CAPSULE in 1 BOTTLE (42385-923-29) | $1.65 / ea | $445.91 | 2022-07-19 | Active |
| 42385-0923-54 | 4 BLISTER PACK in 1 CARTON (42385-923-54) / 63 CAPSULE in 1 BLISTER PACK | — | — | 2022-07-19 | Active |
| 42385-0923-63 | 2 BLISTER PACK in 1 CARTON (42385-923-63) / 21 BLISTER PACK in 1 BLISTER PACK / 42 CAPSULE in 1 BLISTER PACK | — | — | 2022-07-19 | Active |
Pack size FAQ
What quantity is in NDC 42385-0923-29?
What is the difference between NDC 42385-0923-29 and NDC 42385-0923-54?
What NDC number is used to bill for this package of Pirfenidone 267 mg Capsule?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Pirfenidone is indicated for the treatment of idiopathic pulmonary fibrosis (IPF). Pirfenidone is a pyridone indicated for the treatment of idiopathic pulmonary fibrosis (IPF). ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Take with food. Recommended dosage: 801 mg three times daily (2,403 mg/day). ( 2 ) Upon initiation of treatment, titrate to the full dosage of 2,403 mg/day over a 14-day period as follows: Treatment days Dosage Days 1 through 7 267 mg three times daily (801 mg/day) Days 8 through 14 534 mg three times daily (1,602 mg/day) Days 15 onward 801 mg three times daily (2,403 mg/day) Consider temporary dosage reduction, treatment interruption, or discontinuation for management of adverse reactions.
( 2.3 , 5.1 , 5.2 , 5.3 , 5.4 ) Prior to treatment, conduct liver function tests. ( 2.1 )
2.1Testing Prior to Pirfenidone Administration Conduct liver function tests prior to initiating treatment with pirfenidone [see Warnings and Precautions (5.1) ].
2.2Recommended Dosage The recommended daily maintenance dosage of pirfenidone is 801 mg three times daily for a total of 2,403 mg/day. Doses should be taken with food at the same time each day. Upon initiation of treatment, titrate to the full dosage of 2,403 mg/day over a 14-day period as follows: Table 1.
Dosage Titration for Pirfenidone in Patients with IPF Treatment days Dosage Days 1 through 7 267 mg three times daily (801 mg/day) Days 8 through 14 534 mg three times daily (1,602 mg/day) Days 15 onward 801 mg three times daily (2,403 mg/day) Dosages above 2,403 mg/day are not recommended for any patient. Patients should not take 2 doses at the same time to make up for a missed dose. Patients should not take more than 3 doses per day.
2.3Dosage Modifications due to Adverse Reactions Patients who miss 14 or more days of pirfenidone should re-initiate treatment by undergoing the initial 2-week titration regimen up to the full maintenance dosage [see Dosage and Administration (2.2) ] . For treatment interruption of less than 14 days, the dosage prior to the interruption can be resumed. If patients experience significant adverse reactions (i.e., gastrointestinal, photosensitivity reaction or rash, severe cutaneous adverse reactions (SCAR)), consider temporary dosage reductions or interruptions of pirfenidone to allow for resolution of symptoms.
If a SCAR is confirmed, permanently discontinue pirfenidone [see Warnings and Precautions (5.1, 5.2 , 5.3 , 5.4) ]. Dosage Modification due to Elevated Liver Enzymes Dosage modifications or interruptions may also be necessary when liver enzyme and bilirubin elevations are exhibited. For liver enzyme elevations, modify the dosage as follows: If a patient exhibits >3 but ≤5 × the upper limit of normal (ULN) ALT and/or AST without symptoms or hyperbilirubinemia after starting pirfenidone therapy: Discontinue confounding medications, exclude other causes, and monitor the patient closely.
Repeat liver chemistry tests as clinically indicated. The full daily dosage may be maintained, if clinically appropriate, or reduced or interrupted (e.g., until liver chemistry tests are within normal limits) with subsequent re-titration to the full dosage as tolerated. If a patient exhibits >3 but ≤5 × ULN ALT and/or AST accompanied by symptoms or hyperbilirubinemia: Permanently discontinue pirfenidone.
Do not rechallenge patient with pirfenidone. If a patient exhibits >5 × ULN ALT and/or AST: Permanently discontinue pirfenidone. Do not rechallenge patient with pirfenidone.
2.4Dosage Modification due to Drug Interactions Strong CYP1A2 Inhibitors (e.g., fluvoxamine, enoxacin) Reduce pirfenidone to 267 mg three times a day (801 mg/day). Moderate CYP1A2 Inhibitors (e.g., ciprofloxacin) With use of ciprofloxacin at a dosage of 750 mg twice daily, reduce pirfenidone to 534 mg three times a day (1,602 mg/day).
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Capsules: 267 mg, white opaque hard gelatin capsules containing white to off-white powder and “LA267” printed with brown ink on the cap of the capsule. Film-coated tablets: 267 mg - Yellow colored, oval shaped, biconvex film-coated tablets, debossed with “LP2” on one side and plain on other side. 534 mg - Orange colored, oval shaped, biconvex film-coated tablets, debossed with “LP5” on one side and plain on other side.
801 mg - Brown colored, oval shaped, biconvex film-coated tablets, debossed with “LP8” on one side and plain on other side. Capsules: 267 mg (3) Tablets: 267 mg, 534 mg and 801 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Elevated liver enzymes and drug-induced liver injury: ALT, AST, and bilirubin elevations have occurred with pirfenidone including cases of drug-induced liver injury. In the postmarketing setting, non-serious and serious cases of drug-induced liver injury, including severe liver injury with fatal outcomes, have been reported. Monitor ALT, AST, and bilirubin before and during treatment.
Temporary dosage reductions or discontinuations may be required. ( 2.1 , 5.1 ) Photosensitivity and rash: Photosensitivity and rash have been noted with pirfenidone. Avoid exposure to sunlight and sunlamps.
Wear sunscreen and protective clothing daily. Temporary dosage reductions or discontinuations may be required. ( 5.2 ) Severe Cutaneous Adverse Reactions (SCAR): Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), and drug reactions with eosinophilia and systemic symptoms (DRESS) have been reported in association with the use of pirfenidone in the postmarketing setting.
Interrupt pirfenidone in case of signs or symptoms of SCAR. Permanently discontinue pirfenidone if a SCAR is confirmed. ( 5.3 ) Gastrointestinal disorders: Nausea, vomiting, diarrhea, dyspepsia, gastro-esophageal reflux disease, and abdominal pain have occurred with pirfenidone.
Temporary dosage reductions or discontinuations may be required. (5.4)
5.1Elevated Liver Enzymes and Drug-Induced Liver Injury Cases of drug-induced liver injury (DILI) have been observed with pirfenidone. In the postmarketing period, non-serious and serious cases of DILI, including severe liver injury with fatal outcome, have been reported. Patients treated with pirfenidone 2,403 mg/day in three Phase 3 trials had a higher incidence of elevations in ALT or AST ≥3x ULN than placebo patients (3.7% vs 0.8%, respectively).
Elevations ≥10xULN in ALT or AST occurred in 0.3% of patients in the pirfenidone 2,403 mg/day group and in 0.2% of patients in the placebo group. Increases in ALT and AST ≥3x ULN were reversible with dose modification or treatment discontinuation. Conduct liver function tests (ALT, AST, and bilirubin) prior to the initiation of therapy with pirfenidone, monthly for the first 6 months, every 3 months thereafter, and as clinically indicated.
Measure liver function tests promptly in patients who report symptoms that may indicate liver injury, including fatigue, anorexia, right upper abdominal discomfort, dark urine, or jaundice. Dosage modification or interruption may be necessary for liver enzyme elevations [see Dosage and Administration (2.1 , 2.3) ].
5.2Photosensitivity Reaction or Rash Patients treated with pirfenidone 2,403 mg/day in the three Phase 3 studies had a higher incidence of photosensitivity reactions (9%) compared with patients treated with placebo (1%). The majority of the photosensitivity reactions occurred during the initial 6 months. Instruct patients to avoid or minimize exposure to sunlight (including sunlamps), to use a sunblock (SPF 50 or higher), and to wear clothing that protects against sun exposure.
Additionally, instruct patients to avoid concomitant medications known to cause photosensitivity. Dosage reduction or discontinuation may be necessary in some cases of photosensitivity reaction or rash [see Dosage and Administration (2.3) ] .
5.3Severe Cutaneous Adverse Reactions Severe cutaneous adverse reactions (SCAR), including Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), and drug reaction with eosinophilia and systemic symptoms (DRESS), have been reported in association with the use of pirfenidone in the postmarketing setting. If signs or symptoms of SCAR occur, interrupt pirfenidone treatment until the etiology of the reaction has been determined. Consultation with a dermatologist is recommended.
If a SCAR is confirmed, permanently discontinue pirfenidone.
5.4Gastrointestinal Disorders In the clinical studies, gastrointestinal events of nausea, diarrhea, dyspepsia, vomiting, gastro- esophageal ref…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the labeling: Liver Enzyme Elevations and Drug-Induced Liver Injury [see Warnings and Precautions (5.1) ] Photosensitivity Reaction or Rash [see Warnings and Precautions (5.2) ] Severe Cutaneous Adverse Reactions [see Warnings and Precautions (5.3) ] Gastrointestinal Disorders [see Warnings and Precautions (5.4) ] The most common adverse reactions (≥10%) are nausea, rash, abdominal pain, upper respiratory tract infection, diarrhea, fatigue, headache, decreased appetite, dyspepsia, dizziness, vomiting, gastro-esophageal reflux disease, sinusitis, insomnia, weight decreased, and arthralgia.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Laurus Generics Inc. at 1-833-3-LAURUS (1-833-352-8787) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety of pirfenidone has been evaluated in more than 1,400 subjects with over 170 subjects exposed to pirfenidone for more than 5 years in clinical trials. Pirfenidone was studied in 3 randomized, double-blind, placebo-controlled trials (Studies 1, 2, and 3) in which a total of 623 patients received 2,403 mg/day of pirfenidone and 624 patients received placebo.
Subjects ages ranged from 40 to 80 years (mean age of 67 years). Most patients were male (74%) and Caucasian (95%). The mean duration of exposure to pirfenidone was 62 weeks (range: 2 to 118 weeks) in these 3 trials.
At the recommended dosage of 2,403 mg/day, 14.6% of patients on pirfenidone compared to 9.6% on placebo permanently discontinued treatment because of an adverse event. The most common (>1%) adverse reactions leading to discontinuation were rash and nausea. The most common (>3%) adverse reactions leading to dosage reduction or interruption were rash, nausea, diarrhea, and photosensitivity reaction.
The most common adverse reactions with an incidence of ≥10% and more frequent in the pirfenidone than placebo treatment group are listed in Table 2. Table 2. Adverse Reactions Occurring in ≥10% of Pirfenidone-Treated Patients and More Commonly Than Placebo in Studies 1, 2, and 3 Adverse Reaction % of Patients (0 to 118 Weeks) Pirfenidone 2,403 mg/day (N = 623) Placebo (N = 624) Nausea 36% 16% Rash 30% 10% Abdominal Pain 1 24% 15% Upper Respiratory Tract Infection 27% 25% Diarrhea 26% 20% Fatigue 26% 19% Headache 22% 19% Decreased Appetite 21% 8% Dyspepsia 19% 7% Dizziness 18% 11% Vomiting 13% 6% Gastro-esophageal Reflux Disease 11% 7% Sinusitis 11% 10% Insomnia 10% 7% Weight Decreased 10% 5% Arthralgia 10% 7% 1 Includes abdominal pain, upper abdominal pain, abdominal distension, and stomach discomfort.
Adverse reactions occurring in ≥5 to <10% of pirfenidone-treated patients and more commonly than placebo are photosensitivity reaction (9% vs. 1%), pruritus (8% vs. 5%), asthenia (6% vs.
4%), dysgeusia (6% vs. 2%), and non-cardiac chest pain (5% vs. 4%).
6.2Postmarketing Experience In addition to adverse reactions identified from clinical trials the following adverse reactions have been identified during post-approval use of pirfenidone. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency. Blood and Lymphatic System Disorders: Agranulocytosis Hepatobiliary Disorders: Drug-induced liver injury Immune System Disorders: Angioedema Skin and Subcutaneous Tissue Disorders: Severe Cutaneous Adverse Reactions (SCAR)
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Moderate (e.g., ciprofloxacin) and strong inhibitors of CYP1A2 (e.g., fluvoxamine) increase systemic exposure of pirfenidone and may alter the adverse reaction profile of pirfenidone. Discontinue fluvoxamine prior to administration of pirfenidone or reduce to 267 mg three times a day. Consider dosage reduction with use of ciprofloxacin. ( 7.1 )
7.1CYP1A2 Inhibitors Pirfenidone is metabolized primarily (70 to 80%) via CYP1A2 with minor contributions from other CYP isoenzymes including CYP2C9, 2C19, 2D6 and 2E1. Strong CYP1A2 Inhibitors The concomitant administration of pirfenidone and fluvoxamine or other strong CYP1A2 inhibitors (e.g., enoxacin) is not recommended because it significantly increases exposure to pirfenidone [see Clinical Pharmacology (12.3) ]. Use of fluvoxamine or other strong CYP1A2 inhibitors should be discontinued prior to administration of pirfenidone and avoided during pirfenidone treatment.
In the event that fluvoxamine or other strong CYP1A2 inhibitors are the only drug of choice, dosage reductions are recommended. Monitor for adverse reactions and consider discontinuation of pirfenidone as needed [ see Dosage and Administration (2.4) ] . Moderate CYP1A2 Inhibitors Concomitant administration of pirfenidone and ciprofloxacin (a moderate inhibitor of CYP1A2) moderately increases exposure to pirfenidone [see Clinical Pharmacology (12.3) ] .
If ciprofloxacin at the dosage of 750 mg twice daily cannot be avoided, dosage reductions are recommended [see Dosage and Administration (2.4) ]. Monitor patients closely when ciprofloxacin is used at a dosage of 250 mg or 500 mg once daily. Concomitant CYP1A2 and other CYP Inhibitors Agents or combinations of agents that are moderate or strong inhibitors of both CYP1A2 and one or more other CYP isoenzymes involved in the metabolism of pirfenidone (i.e., CYP2C9, 2C19, 2D6, and 2E1) should be discontinued prior to and avoided during pirfenidone treatment.
7.2CYP1A2 Inducers The concomitant use of pirfenidone and a CYP1A2 inducer may decrease the exposure of pirfenidone and this may lead to loss of efficacy. Therefore, discontinue use of strong CYP1A2 inducers prior to pirfenidone treatment and avoid the concomitant use of pirfenidone and a strong CYP1A2 inducer [see Clinical Pharmacology (12.3) ] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Hepatic Impairment: Monitor for adverse reactions and consider dosage modification or discontinuation of pirfenidone as needed. Pirfenidone is not recommended for use in patients with severe hepatic impairment. ( 8.6 , 12.3 ) Renal Impairment: Monitor for adverse reactions and consider dosage modification or discontinuation of pirfenidone as needed.
Pirfenidone is not recommended for use in patients with end stage renal disease on dialysis. ( 8.7 , 12.3 ) Smokers: Decreased exposure has been noted in smokers which may alter the efficacy profile of pirfenidone. ( 8.8 )
8.1Pregnancy Risk Summary The data with pirfenidone use in pregnant women are insufficient to inform on drug associated risks for major birth defects and miscarriage. In animal reproduction studies, pirfenidone was not teratogenic in rats and rabbits at oral doses up to 3 and 2 times, respectively, the maximum recommended daily dose (MRDD) in adults [see Data] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data Animal reproductive studies were conducted in rats and rabbits. In a combined fertility and embryofetal development study, female rats received pirfenidone at oral doses of 0, 50, 150, 450, and 1,000 mg/kg/day from 2 weeks prior to mating, during the mating phase, and throughout the periods of early embryonic development from gestation days (GD) 0 to 5 and organogenesis from GD 6 to 17. In an embryofetal development study, pregnant rabbits received pirfenidone at oral doses of 0, 30, 100, and 300 mg/kg/day throughout the period of organogenesis from GD 6 to 18.
In these studies, pirfenidone at doses up to 3 and 2 times, respectively, the maximum recommended daily dose (MRDD) in adults (on mg/m 2 basis at maternal oral doses up to 1,000 mg/kg/day in rats and 300 mg/kg/day in rabbits, respectively) revealed no evidence of impaired fertility or harm to the fetus due to pirfenidone. In the presence of maternal toxicity, acyclic/irregular cycles (e.g., prolonged estrous cycle) were seen in rats at doses approximately equal to and higher than the MRDD in adults (on a mg/m 2 basis at maternal doses of 450 mg/kg/day and higher).
In a pre- and post-natal development study, female rats received pirfenidone at oral doses of 0, 100, 300, and 1,000 mg/kg/day from GD 7 to lactation day 20. Prolongation of the gestation period, decreased numbers of live newborn, and reduced pup viability and body weights were seen in rats at an oral dosage approximately 3 times the MRDD in adults (on a mg/m 2 basis at a maternal oral dose of 1,000 mg/kg/day).
8.2Lactation Risk Summary No information is available on the presence of pirfenidone in human milk, the effects of the drug on the breastfed infant, or the effects of the drug on milk production. The lack of clinical data during lactation precludes clear determination of the risk of pirfenidone to an infant during lactation; therefore, the developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for pirfenidone and the potential adverse effects on the breastfed child from pirfenidone or from the underlying maternal condition.
Data Animal Data: A study with radio-labeled pirfenidone in rats has shown that pirfenidone or its metabolites are excreted in milk. There are no data on the presence of pirfenidone or its metabolites in human milk, the effects of pirfenidone on the breastfed child, or its effects on milk production.
8.4Pediatric Use Safety and effectiveness of pirfenidone in pediatric patients have not been established.
8.5Geriatric Use Of the total number of subjects in the clinical studies receiving pirfenidone, 714 (67%) were 65 years old and over, while 231 (22%) were 75 years old and over. No overall differences in safety or effectiveness were observed between older and younger patients. No dos…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary The data with pirfenidone use in pregnant women are insufficient to inform on drug associated risks for major birth defects and miscarriage. In animal reproduction studies, pirfenidone was not teratogenic in rats and rabbits at oral doses up to 3 and 2 times, respectively, the maximum recommended daily dose (MRDD) in adults [see Data] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data Animal reproductive studies were conducted in rats and rabbits. In a combined fertility and embryofetal development study, female rats received pirfenidone at oral doses of 0, 50, 150, 450, and 1,000 mg/kg/day from 2 weeks prior to mating, during the mating phase, and throughout the periods of early embryonic development from gestation days (GD) 0 to 5 and organogenesis from GD 6 to 17. In an embryofetal development study, pregnant rabbits received pirfenidone at oral doses of 0, 30, 100, and 300 mg/kg/day throughout the period of organogenesis from GD 6 to 18.
In these studies, pirfenidone at doses up to 3 and 2 times, respectively, the maximum recommended daily dose (MRDD) in adults (on mg/m 2 basis at maternal oral doses up to 1,000 mg/kg/day in rats and 300 mg/kg/day in rabbits, respectively) revealed no evidence of impaired fertility or harm to the fetus due to pirfenidone. In the presence of maternal toxicity, acyclic/irregular cycles (e.g., prolonged estrous cycle) were seen in rats at doses approximately equal to and higher than the MRDD in adults (on a mg/m 2 basis at maternal doses of 450 mg/kg/day and higher).
In a pre- and post-natal development study, female rats received pirfenidone at oral doses of 0, 100, 300, and 1,000 mg/kg/day from GD 7 to lactation day 20. Prolongation of the gestation period, decreased numbers of live newborn, and reduced pup viability and body weights were seen in rats at an oral dosage approximately 3 times the MRDD in adults (on a mg/m 2 basis at a maternal oral dose of 1,000 mg/kg/day).
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of pirfenidone in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of subjects in the clinical studies receiving pirfenidone, 714 (67%) were 65 years old and over, while 231 (22%) were 75 years old and over. No overall differences in safety or effectiveness were observed between older and younger patients. No dosage adjustment is required based upon age.
🆘 Overdosage ▾
10 OVERDOSAGE There is limited clinical experience with overdosage. Multiple dosages of pirfenidone up to a maximum tolerated dose of 4,005 mg per day were administered as five 267 mg capsules three times daily to healthy adult volunteers over a 12-day dose escalation. In the event of a suspected overdosage, appropriate supportive medical care should be provided, including monitoring of vital signs and observation of the clinical status of the patient.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism of action of pirfenidone in the treatment of IPF has not been established.
12.2Pharmacodynamics Cardiac Electrophysiology: The effect of pirfenidone on QT interval was evaluated in a randomized, placebo, and positive controlled parallel study in 160 healthy adult volunteers. Volunteers received pirfenidone 2,403 mg/day (recommended dose) and 4,005 mg/day (1.6 times recommended dose) or placebo for 10 days or a single dose of 400 mg moxifloxacin (active control). Relative to placebo, the maximum mean change from baseline in study-specific QT interval was 3.2 milliseconds (ms) and 2.2 ms for pirfenidone 2,403 mg/day and 4,005 mg/day, respectively.
No volunteer had a QTc interval greater than 480 ms or change from baseline greater than 60 ms. Although there was no evidence that pirfenidone prolonged the QTc interval in this study, a definitive conclusion may not be drawn as the positive control (moxifloxacin) did not perform as expected in this study, and pirfenidone at 4,005 mg/day (1.7 times the maximum recommended dose) did not cover the maximum pirfenidone exposure increase with co-administration of fluvoxamine, a strong CYP1A2 inhibitor.
12.3Pharmacokinetics Absorption: After single oral-dose administration of 801 mg pirfenidone (three 267 mg capsules), the maximum observed plasma concentration (C max ) was achieved between 30 minutes and 4 hours (median time of 0.5 hours). Food decreased the rate and extent of absorption. Median T max increased from 0.5 hours to 3 hours with food.
Maximum plasma concentrations (C max ) and AUC 0 to inf decreased by approximately 49% and 16% with food, respectively. Bioequivalence was demonstrated in the fasted state when comparing the 801 mg tablet to three 267 mg capsules. The effect of food on pirfenidone exposure was consistent between the tablet and capsule formulations.
A reduced incidence of adverse reactions was observed in the fed group when compared to the fasted group. In controlled studies with IPF patients, pirfenidone was taken with food [see Dosage and Administration (2) and Clinical Studies (14) ] . The absolute bioavailability of pirfenidone has not been determined in humans.
Distribution: Pirfenidone binds to human plasma proteins, primarily to serum albumin, in a concentration-independent manner over the range of concentrations observed in clinical trials. The overall mean binding was 58% at concentrations observed in clinical studies (1 to 10 mcg/mL). Mean apparent oral volume of distribution is approximately 59 to 71 liters.
Metabolism: In vitro profiling studies in hepatocytes and liver microsomes have shown that pirfenidone is primarily metabolized in the liver by CYP1A2 and multiple other CYPs (CYP2C9, 2C19, 2D6, and 2E1). Oral administration of pirfenidone results in the formation of four metabolites. In humans, only pirfenidone and 5-carboxy-pirfenidone are present in plasma in significant quantities.
The mean metabolite-to-parent ratio ranged from approximately 0.6 to 0.7. No formal radiolabeled studies have assessed the metabolism of pirfenidone in humans. In vitro data suggests that metabolites are not expected to be pharmacologically active at observed metabolite concentrations.
Elimination: The mean terminal half-life is approximately 3 hours in healthy subjects. Pirfenidone is excreted predominantly as metabolite 5-carboxy-pirfenidone, mainly in the urine (approximately 80% of the dose). The majority of pirfenidone was excreted as the 5-carboxy metabolite (approximately 99.6% of that recovered).
Specific Populations: Hepatic Impairment The pharmacokinetics of pirfenidone and the 5-carboxy-pirfenidone metabolite were studied in 12 subjects with moderate hepatic impairment (Child Pugh Class B) and in 12 subjects with normal hepatic function. Results showed that the mean exposure, AUC 0 to inf and C max of pirfenidone increased approximately 1.6- and approximately 1.4-fold in subjects with moderate…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of action of pirfenidone in the treatment of IPF has not been established.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Pirfenidone capsules, USP are available in 267 mg and supplied as follows: 267 mg - white opaque hard gelatin capsules containing white to off-white powder and “LA267” printed with brown ink on the cap of the capsule. NDC 42385-923-29, bottle for a 30-day supply containing 270 capsules and closed with a child-resistant closure NDC 42385-923-63, 14-day titration blister pack, carton containing a total of 63 capsules in two blister cards – a Week 1 blister card containing 21 capsules and a Week 2 blister card containing 42 capsules NDC 42385-923-54, 4-week maintenance blister pack, carton containing a total of 252 capsules in four blister cards each with 63 capsules Pirfenidone tablets, USP are available in 267 mg, 534 mg and 801 mg strengths and supplied as follows: 267 mg - Yellow colored, oval shaped, biconvex film-coated tablets, debossed with “LP2” on one side and plain on other side.
NDC 42385-924-99, carton containing 3 bottles, each containing ninety 267 mg tablets (270 tablets total) with a child-resistant closure NDC 42385-924-29, bottle containing two hundred and seventy 267 mg tablets, with a child-resistant closure 534 mg - Orange colored, oval shaped, biconvex film-coated tablets, debossed with “LP5” on one side and plain on other side. NDC 42385-925-90, bottle containing ninety 534 mg tablets, with a child-resistant closure 801 mg - Brown colored, oval shaped, biconvex film-coated tablets, debossed with “LP8” on one side and plain on other side.
NDC 42385-926-90, bottle containing ninety 801 mg tablets, with a child-resistant closure Store at 20° to 25°C (68° to 77°F), excursions permitted between 15° to 30°C (59° to 86°F). [See USP Controlled Room Temperature.] Keep the bottle tightly closed. Do not use if the seal over the bottle opening is broken or missing. Safely throw away any pirfenidone capsules and tablets that are out of date or no longer needed.
📋 Description ▾
11 DESCRIPTION Pirfenidone belongs to the chemical class of pyridone. Pirfenidone is available as a white opaque hard gelatin capsules containing 267 mg of pirfenidone USP for oral administration and as film-coated tablets containing 267 mg (yellow), 534 mg (orange) and 801 mg (brown) pirfenidone USP. Pirfenidone has a molecular formula of C 12 H 11 NO and a molecular weight of 185.23.
Pirfenidone has the following structural formula, which has been referred to as 5-Methyl-1-Phenyl-1 H -pyridin-2-one or 5-Methyl-1-phenylpyridin-2(1 H )-one. Pirfenidone USP is a white to pale yellow or pink color solid, non-hygroscopic powder. It is more soluble in methanol, ethyl alcohol, acetone and chloroform than in water and
1.0N HCl. The melting point is approximately 109°C. Pirfenidone capsules, USP contain pirfenidone USP and the following inactive ingredients: croscarmellose sodium, isomalt, and magnesium stearate.
In addition, the capsule shell contains gelatin and titanium dioxide. The capsule brown printing ink includes black iron oxide, brown iron oxide, propylene glycol, and shellac. Pirfenidone tablets, USP contain pirfenidone USP and the following inactive ingredients: Colloidal silicon dioxide, croscarmellose sodium, mannitol, microcrystalline cellulose, povidone, and sodium stearyl fumarate.
The film-coating material contains polyethylene glycol, polyvinyl alcohol, talc, and titanium dioxide. Additionally 267 mg tablets contain iron oxide yellow. 534 mg tablets contain FD&C yellow #6.
801 mg tablets contain black iron oxide and iron oxide red. Pirfenidone Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Liver Enzyme Elevations Advise patients that they may be required to undergo liver function testing periodically. Instruct patients to immediately report any symptoms of a liver problem (e.g., skin or the white of eyes turn yellow, urine turns dark or brown [tea colored], pain on the right side of stomach, bleed or bruise more easily than normal, lethargy) [see Warnings and Precautions (5.1) ] .
Photosensitivity Reaction or Rash Advise patients to avoid or minimize exposure to sunlight (including sunlamps) during use of pirfenidone because of concern for photosensitivity reactions or rash. Instruct patients to use a sunblock and to wear clothing that protects against sun exposure. Instruct patients to report symptoms of photosensitivity reaction or rash to their physician.
Temporary dosage reductions or discontinuations may be required [see Warnings and Precautions (5.2) ] . Severe Cutaneous Adverse Reactions Advise patients about signs and symptoms of severe cutaneous adverse reactions (SCAR). Advise patients to contact their healthcare provider immediately if they experience signs and symptoms of SCAR [see Warnings and Precautions (5.3) ].
Gastrointestinal Events Instruct patients to report symptoms of persistent gastrointestinal effects including nausea, diarrhea, dyspepsia, vomiting, gastro-esophageal reflux disease, and abdominal pain. Temporary dosage reductions or discontinuations may be required [see Warnings and Precautions (5.4) ]. Smokers Encourage patients to stop smoking prior to treatment with pirfenidone and to avoid smoking when using pirfenidone [see Clinical Pharmacology (12.3) ] .
Take with Food Instruct patients to take pirfenidone with food to help decrease nausea and dizziness. Manufactured for: Laurus Generics Inc. 400 Connell Drive Suite 5200 Berkeley Heights, NJ 07922 Manufactured by: Laurus Labs Limited Anakapalli- 531011 India Revised: 1/2025