
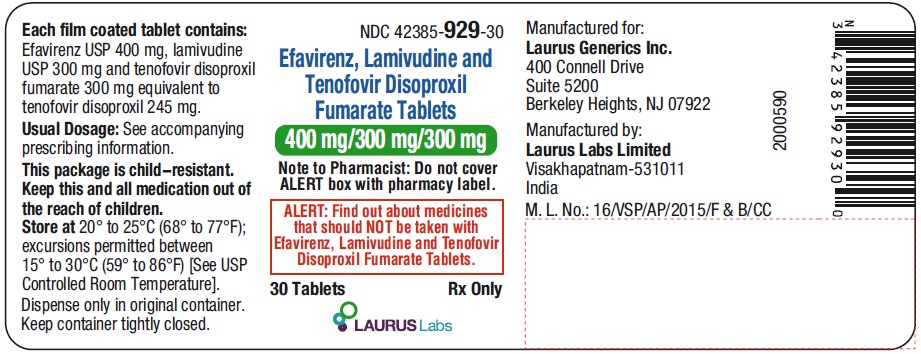
Efavirenz, Lamivudine and Tenofovir Disoproxil Fumarate 400 mg; 300 mg; 300 mg Tablet, Film Coated, 180-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Human Immunodeficiency Virus 1 Non-Nucleoside Analog Reverse Transcriptase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Efavirenz — one of the three drugs in this tablet — commonly causes dizziness, unusual dreams, and trouble concentrating, especially in the first few weeks. Taking it at bedtime me...
- Why do I have to take this on an empty stomach at bedtime?
- This is really important: if you have hepatitis B, you should never stop this medication suddenly without talking to your doctor first. Two of the drugs in this tablet — lamivudine...
- What should I do if I also have hepatitis B?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII RFW2ET671P
Hydroxypropyl cellulose is a plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a film-former to coat tablets or control how fast the medicine releases.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII G2M7P15E5P
Polyethylene glycol 3350 is a synthetic polymer used as a solvent, humectant, and thickening agent in medicines. It helps dissolve other ingredients, retain moisture in the product, and achieve the desired consistency.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $41.62 | $7,490.70 / 180 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Efavirenz, Lamivudine and Tenofovir Disoproxil Fumarate 400 mg/1; 300 mg/1; 300 mgthis 42385-0929-18 | Laurus | 180 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
💊 Medicaid utilization by pack size
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 42385-0929-18 You're viewing this | 180 TABLET, FILM COATED in 1 BOTTLE (42385-929-18) | 2020-05-14 | Active |
| 42385-0929-30 | 30 TABLET, FILM COATED in 1 BOTTLE (42385-929-30) | 2020-05-14 | Active |
| 42385-0929-31 | 30 TABLET, FILM COATED in 1 BOTTLE (42385-929-31) | 2020-05-14 | Active |
| 42385-0929-82 | 180 TABLET, FILM COATED in 1 BOTTLE (42385-929-82) | 2020-05-14 | Active |
| 42385-0929-90 | 90 TABLET, FILM COATED in 1 BOTTLE (42385-929-90) | 2020-05-14 | Active |
| 42385-0929-91 | 90 TABLET, FILM COATED in 1 BOTTLE (42385-929-91) | 2020-05-14 | Active |
Pack size FAQ
What quantity is in NDC 42385-0929-18?
What is the difference between NDC 42385-0929-18 and NDC 42385-0929-30?
What NDC number is used to bill for this package of Efavirenz, Lamivudine and Tenofovir Disoproxil Fumarate 400 mg; 300 mg; 300 mg Tablet, Film Coated?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: POST TREATMENT ACUTE EXACERBATIONS OF HEPATITIS B Severe acute exacerbations of hepatitis B have been reported in patients who are co-infected with hepatitis B virus (HBV) and human immunodeficiency virus (HIV-1) and have discontinued lamivudine or tenofovir disoproxil fumarate, two components of efavirenz, lamivudine and tenofovir disoproxil fumarate tablets. Monitor hepatic function closely in these patients and, if appropriate, initiate anti-hepatitis B treatment [see Warnings and Precautions (5.1) ]. WARNING: POST TREATMENT ACUTE EXACERBATIONS OF HEPATITIS B See full prescribing information for complete boxed warning. • Severe acute exacerbations of hepatitis B have been reported in patients who are co-infected with HBV and human immunodeficiency virus (HIV-1) and have discontinued lamivudine and tenofovir disoproxil fumarate.
Monitor hepatic function closely in these patients and, if appropriate, initiate anti-hepatitis B treatment. ( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Efavirenz, lamivudine and tenofovir disoproxil fumarate tablets are indicated as a complete regimen for the treatment of human immunodeficiency virus type 1 (HIV-1) infection in adult and pediatric patients weighing at least 35 kg. Efavirenz, lamivudine and tenofovir disoproxil fumarate tablets are three-drug combination of efavirenz (EFV), a non-nucleoside reverse transcriptase inhibitor, and lamivudine (3TC) and tenofovir disoproxil fumarate (TDF), both nucleo(t)side reverse transcriptase inhibitors and are indicated as a complete regimen for the treatment of human immunodeficiency virus type 1 (HIV-1) infection in adult and pediatric patients weighing at least 35 kg.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Testing: Prior to initiation and during treatment with efavirenz, lamivudine and tenofovir disoproxil fumarate tablets, patients should be tested for hepatitis B virus infection, and estimated creatinine clearance, urine glucose, and urine protein should be obtained. ( 2.1 ) Recommended dose: One tablet taken orally once daily on an empty stomach, preferably at bedtime. ( 2.2 ) Renal Impairment: Not recommended in patients with CrCL less than 50 mL/min or patients with end-stage renal disease requiring hemodialysis.
( 2.3 ) Hepatic Impairment: Not recommended for patients with moderate or severe hepatic impairment. Use caution in patients with mild hepatic impairment. ( 2.4 )
2.1Testing Prior to Initiation and During Treatment with Efavirenz, Lamivudine and Tenofovir Disoproxil Fumarate Tablets Prior to initiation of efavirenz, lamivudine and tenofovir disoproxil fumarate tablets, test patients for hepatitis B virus infection [see Warnings and Precautions (5.1) ] . It is recommended that serum creatinine, serum phosphorus, estimated creatinine clearance, urine glucose, and urine protein be assessed before initiating efavirenz, lamivudine and tenofovir disoproxil fumarate tablets and during therapy in all patients as clinically appropriate [see Warnings and Precautions (5.4) ].
Monitor hepatic function prior to and during treatment with efavirenz, lamivudine and tenofovir disoproxil fumarate tablets [see Warnings and Precautions (5.9) ] .
2.2Recommended Dosage for Adult and Pediatric Patients Weighing at Least 35 kg Efavirenz, lamivudine and tenofovir disoproxil fumarate tablets are a three-drug fixed-dose combination product containing 400 mg of efavirenz (EFV), 300 mg of lamivudine (3TC), and 300 mg of tenofovir disoproxil fumarate (TDF). The recommended dosage of efavirenz, lamivudine and tenofovir disoproxil fumarate tablets in HIV-1-infected adults and pediatric patients weighing at least 35 kg is one tablet taken orally once daily. Efavirenz, lamivudine and tenofovir disoproxil fumarate tablets should be taken on an empty stomach, preferably at bedtime.
Dosing at bedtime may improve the tolerability of nervous system symptoms [see Warnings and Precautions (5.6) and Adverse Reactions (6.1)].
2.3Not Recommended in Renal Impairment Because efavirenz, lamivudine and tenofovir disoproxil fumarate tablets are a fixed-dose combination tablet and cannot be dose adjusted, they are not recommended for patients with impaired renal function (creatinine clearance less than 50 mL/min) or patients with end-stage renal disease (ESRD) requiring hemodialysis [see Use in Specific Populations (8.6) ] .
2.4Not Recommended in Moderate to Severe Hepatic Impairment Efavirenz, lamivudine and tenofovir disoproxil fumarate tablets are not recommended in patients with moderate or severe hepatic impairment (Child-Pugh B or C) [see Warnings and Precautions (5.9) and Use in Specific Populations (8.7)] .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 400 mg of efavirenz, 300 mg of lamivudine, and 300 mg of tenofovir disoproxil fumarate (equivalent to 245 mg of tenofovir disoproxil). The 400 mg/300 mg/300 mg tablets are white to off-white, film-coated, oval, biconvex tablets debossed with “L40” on one side and plain on other side. Tablets: 400 mg efavirenz, 300 mg lamivudine and 300 mg tenofovir disoproxil fumarate (equivalent to 245 mg of tenofovir disoproxil).
( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Efavirenz, lamivudine and tenofovir disoproxil fumarate tablets are contraindicated: in patients with a previous hypersensitivity reaction (e.g., Stevens-Johnson syndrome, erythema multiforme, or toxic skin eruptions) to any of the components contained in the formulation [see Warnings and Precautions (5.8) ] . when coadministered with elbasvir and grazoprevir [see Warnings and Precautions (5.3) and Drug Interactions (7.5)]. Efavirenz, lamivudine and tenofovir disoproxil fumarate tablets are contraindicated in patients with previous hypersensitivity (e.g., Stevens-Johnson syndrome, erythema multiforme, or toxic skin eruptions) to any of the components of this product.
( 4 ) Coadministration with elbasvir/grazoprevir. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Lactic Acidosis/Severe Hepatomegaly with Steatosis: Discontinue treatment in patients who develop symptoms or laboratory findings suggestive of lactic acidosis or pronounced hepatotoxicity. ( 5.2 ) New Onset or Worsening Renal Impairment: Can include acute renal failure and Fanconi syndrome. Avoid administering efavirenz, lamivudine and tenofovir disoproxil fumarate tablets with concurrent or recent use of nephrotoxic drugs.
( 5.4 ) Serious Psychiatric Symptoms: Immediate medical evaluation is recommended for serious psychiatric symptoms such as severe depression or suicidal ideation. ( 5.5 ) Nervous System Symptoms (NSS): NSS are frequent, usually begin 1 to 2 days after initiating therapy and resolve in 2 to 4 weeks. Dosing at bedtime may improve tolerability.
NSS are not predictive of onset of psychiatric symptoms. ( 5.6 ) Rash: Rash usually begins within 1 to 2 weeks after initiating therapy and resolves within 4 weeks. Discontinue if severe rash develops.
( 5.8 ) Hepatotoxicity: Monitor liver function tests before and during treatment in patients with underlying hepatic disease, including hepatitis B or C coinfection, marked transaminase elevations, or who are taking medications associated with liver toxicity. Among reported cases of hepatic failure, a few occurred in patients with no pre-existing hepatic disease. ( 5.9 , 8.7 ) Pancreatitis: Use with caution in pediatric patients with a history of pancreatitis or other significant risk factors for pancreatitis.
Discontinue efavirenz, lamivudine and tenofovir disoproxil fumarate as clinically appropriate. ( 5.10 ) Convulsions: Use caution in patients with a history of seizures. ( 5.11 ) Lipids: Total cholesterol and triglyceride elevations.
Monitor before therapy and periodically thereafter. ( 5.12 ) Decreases in Bone Mineral Density (BMD): Observed in HIV-infected patients. Consider assessment of BMD in patients with a history of pathologic fracture or other risk factors for osteoporosis or bone loss.
( 5.13 ) Immune Reconstitution Syndrome: Observed in HIV-infected patients. May necessitate further evaluation and treatment. ( 5.14 ) Redistribution/Accumulation of Body Fat: Observed in HIV-infected patients receiving antiretroviral combination therapy.
( 5.15 )
5.1Severe Acute Exacerbation of Hepatitis B in Patients Coinfected with HIV-1 and HBV Posttreatment Exacerbations of Hepatitis: All patients with HIV-1 should be tested for the presence of chronic hepatitis B virus (HBV) before initiating antiretroviral therapy therapy [see Dosage and Administration (2.1) ] . Discontinuation of anti-HBV therapy, including 3TC and TDF, may be associated with severe acute exacerbations of hepatitis B. Patients infected with HBV who discontinue efavirenz, lamivudine and tenofovir disoproxil fumarate should be closely monitored with both clinical and laboratory follow-up for at least several months after stopping treatment.
If appropriate, resumption of anti-hepatitis B therapy may be warranted. Important Differences Among Lamivudine-Containing Products: Efavirenz, lamivudine and tenofovir disoproxil fumarate tablets contain a higher dose of the same active ingredient, 3TC, than EPIVIR-HBV ® tablets. EPIVIR-HBV was developed for patients with chronic hepatitis B.
The formulation and dosage of 3TC in EPIVIR- HBV are not appropriate for patients co-infected with HIV-1 and HBV. Safety and efficacy of 3TC have not been established for treatment of chronic hepatitis B in patients co-infected with HIV-1 and HBV. If treatment with EPIVIR-HBV, TDF, or a tenofovir alafenamide (TAF)-containing product is prescribed for chronic hepatitis B for a patient with unrecognized or untreated HIV-1 infection, rapid emergence of HIV-1 resistance is likely to result because of the subtherapeutic dose and the inappropriateness of monotherapy HIV-1 treatment.
5.2Lactic Acidosis and Severe Hepatomegaly with Steatosis Lactic acidosis and severe hepatomegaly with steatosis, including…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in other sections of the labeling: Exacerbations of Hepatitis B [see Boxed Warning , Warnings and Precautions (5.1) ] . Lactic Acidosis/Severe Hepatomegaly with Steatosis [see Warnings and Precautions (5.2) ] . New Onset or Worsening Renal Impairment [see Warnings and Precautions (5.4) ] .
Psychiatric Symptoms [see Warnings and Precautions (5.5) ] . Nervous System Symptoms [see Warnings and Precautions (5.6) ] . Skin and Systemic Hypersensitivity Reaction [see Warnings and Precautions (5.8) ] .
Hepatotoxicity [see Warnings and Precautions (5.9) ]. Pancreatitis [see Warnings and Precautions (5.10) ] . Bone Loss and Mineralization Effects [see Warnings and Precautions (5.13) ] .
Immune Reconstitution Syndrome [see Warnings and Precautions (5.14) ] . Fat Redistribution [see Warnings and Precautions (5.15) ] . Most common adverse reactions (>5% with efavirenz, lamivudine and tenofovir disoproxil fumarate) are rash and dizziness.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Laurus Generics Inc. at 1-833-3-LAURUS (1-833-352-8787) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, the adverse reaction rates observed in clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Efavirenz, Lamivudine and Tenofovir Disoproxil Fumarate Clinical Trials in Treatment-Naïve HIV-1 Infected Adult Subjects In Trial 903, 600 antiretroviral-naïve subjects received TDF (N = 299) or stavudine (d4T) (N = 301) administered in combination with 3TC and EFV for 144 weeks.
The most common adverse reactions were mild to moderate gastrointestinal events and dizziness. Mild adverse reactions (Grade 1) were common with a similar incidence in both arms and included dizziness, diarrhea, and nausea. Table 1 provides the treatment-emergent adverse reactions (Grades 2 to 4) occurring in greater than or equal to 5% of subjects treated in any treatment group.
Table 1. Selected Adverse Reactions a (Grades 2 to 4) Reported in ≥ 5% in Any Treatment Group in Trial 903 (0 to 144 Weeks) a Frequencies of adverse reactions are based on all treatment-emergent adverse events, regardless of relationship to study drug. b Rash event includes rash, pruritus, maculopapular rash, urticaria, vesiculobullous rash, and pustular rash. c Lipodystrophy represents a variety of investigator-described adverse events not a protocol-defined syndrome. d Peripheral neuropathy includes peripheral neuritis and neuropathy.
TDF + 3TC + EFV d4T + 3TC + EFV N = 299 N = 301 Rash event b 18% 12% Headache 14% 17% Pain 13% 12% Diarrhea 11% 13% Depression 11% 10% Back pain 9% 8% Nausea 8% 9% Fever 8% 7% Abdominal pain 7% 12% Asthenia 6% 7% Anxiety 6% 6% Vomiting 5% 9% Insomnia 5% 8% Arthralgia 5% 7% Pneumonia 5% 5% Dyspepsia 4% 5% Dizziness 3% 6% Myalgia 3% 5% Lipodystrophy c 1% 8% Peripheral neuropathy d 1% 5% ENCORE1 Study - Adverse Reactions: The most common adverse reactions seen in a double-blind comparative controlled study in which 630 treatment-naïve subjects received EFV 400 mg (N = 321) or EFV 600 mg (N = 309) in combination with fixed-dose emtricitabine (FTC)/TDF for 48 weeks were mild to moderate gastrointestinal events, dizziness, abnormal dreams, and rash.
Selected clinical adverse reactions of moderate or severe intensity reported in ≥ 2% of treatment-naive patients receiving combination therapy including EFV 400 mg and EFV 600 mg are presented in Table 2. Table 2. Selected Adverse Reactions a (Grades 2 to 4) Reported in ≥ 2% in Either Treatment Group in the ENCORE1 Study through Week 48 a Frequencies of adverse reactions are based on all treatment-emergent adverse events, regardless of relationship to study drug. b Rash events include dermatitis allergic, drug hypersensitivity, pruritus generalized, eosinophilic pustular f…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Efavirenz, lamivudine and tenofovir disoproxil fumarate should not be administered with other antiretroviral medications for the treatment of HIV-1 infection. ( 7.1 ) Coadministration of efavirenz, lamivudine and tenofovir disoproxil fumarate can alter the concentrations of other drugs and other drugs may alter the concentration of efavirenz, lamivudine and tenofovir disoproxil fumarate. The potential for drug-drug interactions should be considered before and during therapy.
( 5.3 , 7 )
7.1Not Recommended with Other Antiretroviral Medications Efavirenz, lamivudine and tenofovir disoproxil fumarate is a complete regimen for the treatment of HIV-1 infection; therefore, it should not be administered with other antiretroviral medications for treatment of HIV-1 infection.
7.2QT Prolonging Drugs There is limited information available on the potential for a pharmacodynamic interaction between EFV and drugs that prolong the QTc interval. QTc prolongation has been observed with the use of EFV [see Clinical Pharmacology (12.2) ] . Consider alternatives to EFV when coadministered with a drug with a known risk of Torsade de Pointes.
7.3Drugs Affecting Renal Function Tenofovir is primarily eliminated by the kidneys [see Clinical Pharmacology (12.3) ] . Coadministration of EFV/3TC/TDF with drugs that are eliminated by active tubular secretion may increase concentrations of tenofovir and/or the coadministered drugs. Some examples include, but are not limited to, acyclovir, cidofovir, ganciclovir, valacyclovir, valganciclovir, aminoglycosides (e.g., gentamicin), and high-dose or multiple NSAIDs [see Warnings and Precautions (5.4) ] .
Drugs that decrease renal function may increase concentrations of tenofovir.
7.4Cannabinoid Test Interaction EFV does not bind to cannabinoid receptors. False-positive urine cannabinoid test results have been reported with some screening assays in uninfected and HIV-infected subjects receiving EFV. Confirmation of positive screening tests for cannabinoids by a more specific method is recommended.
7.5Established and Other Potentially Significant Interactions EFV has been shown in vivo to induce CYP3A and CYP2B6. Other compounds that are substrates of CYP3A or CYP2B6 may have decreased plasma concentrations when coadministered with EFV. Drugs that induce CYP3A activity (e.g., phenobarbital, rifampin, rifabutin) would be expected to increase the clearance of EFV resulting in lowered plasma concentrations.
No drug interaction studies have been conducted using efavirenz, lamivudine and tenofovir disoproxil fumarate tablets. However, drug interaction studies have been conducted with the individual components of efavirenz, lamivudine and tenofovir disoproxil fumarate tablets (EFV, 3TC, and TDF) [see Clinical Pharmacology (12.3) ] . Drug interactions with EFV are summarized in Table 5 [for pharmacokinetics data see Clinical Pharmacology (12.3, Tables 8 and 9) ].
This table includes potentially significant interactions, but is not all inclusive. Table 5. Established and Other Potentially Significant Drug Interactions with EFV: Alteration in Dose or Regimen May Be Recommended Based on Drug Interaction Studies or Predicted Interaction * The interaction between EFV and the drug was evaluated in a clinical study.
All other drug interactions shown are predicted. This table is not all-inclusive. Concomitant Drug Class: Drug Name Effect Clinical Comment Anticoagulant: Warfarin ↑ or ↓ warfarin Monitor INR and adjust warfarin dosage if necessary.
Anticonvulsants: Carbamazepine ↓carbamazepine* ↓EFV* There are insufficient data to make a dose recommendation for EFV. Alternative anticonvulsant treatment should be used. Phenytoin Phenobarbital ↓ anticonvulsant ↓ EFV Monitor anticonvulsant plasma levels periodically because of potential for reduction in anticonvulsant and/or EFV plasma levels.
Antidepressants: Bupropion Sertraline ↓ bupropion* ↓ sertraline* Increases in bupropion dosage should be guided by cli…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Women should avoid pregnancy during EFV therapy, a component of efavirenz, lamivudine and tenofovir disoproxil fumarate tablets, and for 12 weeks after discontinuation. ( 5.7 , 8.1 , 8.3 ) Lactation: Breastfeeding not recommended due to potential for HIV transmission. ( 8.2 ) Females and Males of Reproductive Potential: Pregnancy testing and contraception are recommended. ( 8.3 )
8.1Pregnancy Pregnancy Exposure Registry: There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to efavirenz, lamivudine and tenofovir disoproxil fumarate during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary: There are retrospective case reports of neural tube defects in infants whose mothers were exposed to EFV-containing regimens in the first trimester of pregnancy.
Although a causal relationship has not been established between exposure to EFV in the first trimester and neural tube defects, similar malformations have been observed in studies conducted in monkeys at doses similar to the human dose. In addition, fetal and embryonic toxicities occurred in rats, at a dose ten times less than the human exposure at recommended clinical dose. Because of the potential risk of neural tube defects, EFV should not be used in the first trimester of pregnancy.
Advise pregnant women of the potential risk to a fetus. Prospective pregnancy data from the APR are not sufficient to adequately assess this risk of birth defects or miscarriage. EFV and 3TC have been evaluated in a limited number of women as reported to the APR.
Available data from the APR show no difference in the risk of major birth defects for EFV and 3TC compared to the background rate for major birth defects of 2.7% in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP). Available data from the APR also show no increase in the overall risk of major birth defects with first trimester exposure for TDF (2.1%) compared with the background rate for major birth defects of 2.7% in a U.S. reference population of the MACDP (see Data) . 3TC produced embryonic toxicity in rabbits at a dose that produced similar human exposures as the recommended clinical dose.
The relevance of animal findings to human pregnancy registry data is not known. The rate of miscarriage is not reported in the APR. The estimated background rate of miscarriage in clinically recognized pregnancies in the U.S. general population is 15% to 20%.
The background risk for major birth defects and miscarriage for the indicated population is unknown. The APR uses the MACDP as the U.S. reference population for birth defects in the general population. The MACDP evaluates women and infants from a limited geographic area and does not include outcomes for births that occurred at less than 20 weeks’ gestation.
Human Data: Efavirenz: There are retrospective postmarketing reports of findings consistent with neural tube defects, including meningomyelocele, all in infants of mothers exposed to EFV- containing regimens in the first trimester [see Warnings and Precautions (5.7) ] . Based on prospective reports from the APR of approximately 1,000 live births following exposure to EFV-containing regimens (including over 800 live births exposed in the first trimester), there was no difference between EFV and overall birth defects compared with the background birth defect rate of 2.7% in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program.
As of the interim APR report issued December 2014, the prevalence of birth defects following first-trimester exposure was 2.3% (95% CI: 1.4% to 3.6%). One of these prospectively reported defects with first-trimester exposure was a neural tube defect. A single case of anophthalmia with first-trimester exposure to EFV has also been prospectively reported.
This case also inc…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry: There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to efavirenz, lamivudine and tenofovir disoproxil fumarate during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary: There are retrospective case reports of neural tube defects in infants whose mothers were exposed to EFV-containing regimens in the first trimester of pregnancy.
Although a causal relationship has not been established between exposure to EFV in the first trimester and neural tube defects, similar malformations have been observed in studies conducted in monkeys at doses similar to the human dose. In addition, fetal and embryonic toxicities occurred in rats, at a dose ten times less than the human exposure at recommended clinical dose. Because of the potential risk of neural tube defects, EFV should not be used in the first trimester of pregnancy.
Advise pregnant women of the potential risk to a fetus. Prospective pregnancy data from the APR are not sufficient to adequately assess this risk of birth defects or miscarriage. EFV and 3TC have been evaluated in a limited number of women as reported to the APR.
Available data from the APR show no difference in the risk of major birth defects for EFV and 3TC compared to the background rate for major birth defects of 2.7% in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP). Available data from the APR also show no increase in the overall risk of major birth defects with first trimester exposure for TDF (2.1%) compared with the background rate for major birth defects of 2.7% in a U.S. reference population of the MACDP (see Data) . 3TC produced embryonic toxicity in rabbits at a dose that produced similar human exposures as the recommended clinical dose.
The relevance of animal findings to human pregnancy registry data is not known. The rate of miscarriage is not reported in the APR. The estimated background rate of miscarriage in clinically recognized pregnancies in the U.S. general population is 15% to 20%.
The background risk for major birth defects and miscarriage for the indicated population is unknown. The APR uses the MACDP as the U.S. reference population for birth defects in the general population. The MACDP evaluates women and infants from a limited geographic area and does not include outcomes for births that occurred at less than 20 weeks’ gestation.
Human Data: Efavirenz: There are retrospective postmarketing reports of findings consistent with neural tube defects, including meningomyelocele, all in infants of mothers exposed to EFV- containing regimens in the first trimester [see Warnings and Precautions (5.7) ] . Based on prospective reports from the APR of approximately 1,000 live births following exposure to EFV-containing regimens (including over 800 live births exposed in the first trimester), there was no difference between EFV and overall birth defects compared with the background birth defect rate of 2.7% in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program.
As of the interim APR report issued December 2014, the prevalence of birth defects following first-trimester exposure was 2.3% (95% CI: 1.4% to 3.6%). One of these prospectively reported defects with first-trimester exposure was a neural tube defect. A single case of anophthalmia with first-trimester exposure to EFV has also been prospectively reported.
This case also included severe oblique facial clefts and amniotic banding, which have a known association with anophthalmia. Lamivudine: Based on prospective reports from the APR of over 11,000 exposures to 3TC during pregnancy resulting in live births (including over 4,300 exposed in the first trimester), there was no difference between 3TC and overall risk of birth defects for 3TC compared with the background birth defect rate of 2.7% i…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of efavirenz, lamivudine and tenofovir disoproxil fumarate as a fixed-dose tablet in pediatric patients infected with HIV-1 and weighing at least 35 kg have been established based on clinical studies using the individual components (efavirenz, lamivudine, and tenofovir disoproxil fumarate).
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of efavirenz, lamivudine and tenofovir disoproxil fumarate did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In general, caution should be exercised in the administration of 3TC in elderly patients reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE If overdose occurs, the patient must be monitored for evidence of toxicity, and standard supportive treatment applied as necessary. Efavirenz: Some patients accidentally taking 600 mg twice daily have reported increased nervous system symptoms. One patient experienced involuntary muscle contractions.
Treatment of overdose with EFV should consist of general supportive measures, including monitoring of vital signs and observation of the patient’s clinical status. Administration of activated charcoal may be used to aid removal of unabsorbed drug. There is no specific antidote for overdose with efavirenz.
Since efavirenz is highly protein bound, dialysis is unlikely to significantly remove the drug from blood. Lamivudine: There is no known specific treatment for overdose with 3TC. If overdose occurs, the patient should be monitored and standard supportive treatment applied as required because a negligible amount of 3TC was removed via (4-hour) hemodialysis, continuous ambulatory peritoneal dialysis, and automated peritoneal dialysis, it is not known if continuous hemodialysis would provide clinical benefit in a 3TC overdose event.
Tenofovir Disoproxil Fumarate: Limited clinical experience at doses higher than the therapeutic dose of TDF 300 mg is available. Tenofovir is efficiently removed by hemodialysis with an extraction coefficient of approximately 54%. Following a single 300 mg dose of tenofovir disoproxil fumarate, a 4-hour hemodialysis session removed approximately 10% of the administered tenofovir dose.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Efavirenz, lamivudine and tenofovir disoproxil fumarate tablets are a fixed-dose combination of antiviral drugs EFV, 3TC, and TDF with antiviral activity against HIV-1 [see Microbiology (12.4) ].
12.2Pharmacodynamics Cardiac Electrophysiology: The effect of EFV on the QTc interval was evaluated in an open- label, positive and placebo-controlled, fixed single sequence 3-period, 3-treatment crossover QT study in 58 healthy subjects enriched for CYP2B6 polymorphisms. The mean C max of EFV in subjects with CYP2B6 *6/*6 genotype following the administration of 600 mg daily dose for 14 days was 2.25-fold the mean C max observed in subjects with CYP2B6 *1/*1 genotype. A positive relationship between EFV concentration and QTc prolongation was observed.
Based on the concentration-QTc relationship, the mean QTc prolongation and its upper bound 90% confidence interval are 8.7 ms and 11.3 ms in subjects with CYP2B6*6/*6 genotype following the administration of 600 mg daily dose for 14 days [see Warnings and Precautions (5.16) ] .
12.3Pharmacokinetics The effect of food on efavirenz, lamivudine and tenofovir disoproxil fumarate has not been evaluated. Efavirenz: In HIV-1-infected subjects, time-to-peak plasma concentrations were approximately 3 to 5 hours and steady-state plasma concentrations were reached in 6 to 10 days. EFV is highly bound (approximately 99.5 to 99.75%) to human plasma proteins, predominantly albumin.
Following administration of 14C-labeled EFV, 14 to 34% of the dose was recovered in the urine (mostly as metabolites) and 16 to 61% was recovered in feces (mostly as parent drug). In vitro studies suggest CYP3A and CYP2B6 are the major isozymes responsible for EFV metabolism. EFV has been shown to induce CYP enzymes, resulting in induction of its own metabolism.
EFV has a terminal half-life of 52 to 76 hours after single doses and 40 to 55 hours after multiple doses. Lamivudine: After oral administration of 2 mg/kg of 3TC twice a day to 9 adults with HIV-1, the peak serum 3TC concentration (Cmax) was 1.5 ± 0.5 mcg/mL (mean ± SD). The area under the plasma concentration versus time curve (AUC) and Cmax increased in proportion to oral dose over the range from 0.25 to 10 mg/kg and absolute bioavailability in 12 adult patients was 86% ± 16% (mean ± SD) for the 150-mg tablet and 87% ± 13% for the oral solution.
Binding of 3TC to human plasma proteins is low (< 36%). Within 12 hours after a single oral dose of 3TC in 6 HIV-l-infected adults, 5.2% ± 1.4% (mean ± SD) of the dose was excreted as the trans-sulfoxide metabolite in the urine. The majority of 3TC is eliminated unchanged in urine by active organic cationic secretion and the observed mean elimination half-life (t1/2) ranged from 5 to 7 hours in most single-dose studies with serum sampling for 24 hours after dosing.
Tenofovir Disoproxil Fumarate: Following oral administration of a single 300 mg dose of TDF to HIV-1-infected subjects in the fasted state, maximum serum concentrations (Cmax) were achieved in 1.0 ± 0.4 hrs (mean ± SD) and Cmax and AUC values were 296 ± 90 ng/mL and 2,287 ± 685 ng•hr/mL, respectively. The oral bioavailability of tenofovir from TDF in fasted subjects is approximately 25%. Less than 0.7% of tenofovir binds to human plasma proteins in vitro and the binding is independent of concentration over the range of 0.01 to 25 mcg/mL.
Approximately 70 to 80% of the intravenous dose of tenofovir is recovered as unchanged drug in the urine. Tenofovir is eliminated by a combination of glomerular filtration and active tubular secretion with a renal clearance in adults with normal renal function of 243 ± 33 mL/min (mean ± SD). Following a single oral dose, the terminal elimination half-life of tenofovir is approximately 17 hours.
Special Populations: Race: Efavirenz and Lamivudine: There are no significant or clinically relevant racial differences in EFV and 3TC pharmacokinetics. Tenofovir Disoproxil Fumarate:…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Efavirenz, lamivudine and tenofovir disoproxil fumarate tablets are a fixed-dose combination of antiviral drugs EFV, 3TC, and TDF with antiviral activity against HIV-1 [see Microbiology (12.4) ].
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Efavirenz, lamivudine and tenofovir disoproxil fumarate tablets are supplied as fixed-dose combination tablets containing efavirenz USP 400 mg, lamivudine USP 300 mg and tenofovir disoproxil fumarate 300 mg equivalent to tenofovir disoproxil 245 mg. Efavirenz, lamivudine and tenofovir disoproxil fumarate tablets are white to off-white, film-coated, oval, biconvex tablets debossed with “L40” on one side and plain on other side. They are supplied as follows: HDPE bottles with Molecular sieve desiccant Bottles of 30 NDC 42385-929-30 Bottles of 90 NDC 42385-929-90 Bottles of 180 NDC 42385-929-18 HDPE bottles with Silica gel canister desiccant Bottles of 30 NDC 42385-929-31 Bottles of 90 NDC 42385-929-91 Bottles of 180 NDC 42385-929-82 Store at 20° to 25°C (68° to 77°F), excursions permitted between 15° to 30°C (59° to 86°F). [See USP Controlled Room Temperature.] Dispense in original container.
📋 Description ▾
11 DESCRIPTION Efavirenz, lamivudine and tenofovir disoproxil fumarate is a fixed-dose combination tablet for oral administration. Each film coated tablet contains efavirenz USP 400 mg, lamivudine USP 300 mg and tenofovir disoproxil fumarate 300 mg equivalent to tenofovir disoproxil 245 mg. Each tablet contains the following inactive ingredients: croscarmellose sodium, ferric oxide yellow, hydroxypropyl cellulose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, polyethylene glycol, polyvinyl alcohol, sodium lauryl sulfate, talc and titanium dioxide.
Efavirenz: Efavirenz (EFV) is an HIV-1 specific, non-nucleoside, reverse transcriptase inhibitor (NNRTI). Efavirenz is chemically described as ( S )-6-Chloro-4-(cyclopropylethynyl)-1,4-dihydro-4-(trifluoromethyl)-2 H -3,1-benzoxazin-2-one. Its molecular formula is C 14 H 9 ClF 3 NO 2 and its structural formula is: Efavirenz USP is a white to off white powder with a molecular mass of 315.67.
It is soluble in methanol and practically insoluble in water (< 10 microgram/mL). Lamivudine: Lamivudine (also known as 3TC) is a synthetic nucleoside analogue with activity against HIV-1 and HBV.The chemical name of lamivudine is (-)-1-[(2 R ,5 S )-2-(Hydroxy methyl)-1,3-oxathiolan-5-yl]cytosine. Lamivudine is the (-)enantiomer of a dideoxy analogue of cytidine.
Lamivudine has also been referred to as (-)2′,3′-dideoxy, 3′-thiacytidine. It has a molecular formula of C 8 H 11 N 3 O 3 S and a molecular weight of 229.26 g per mol. It has the following structural formula: Lamivudine USP is a white or almost white powder and is soluble in water.
Tenofovir Disoproxil Fumarate: Tenofovir disoproxil fumarate (TDF) (a prodrug of tenofovir) is a fumaric acid salt of bis-isopropoxycarbonyloxymethyl ester derivative of tenofovir. TDF is converted in vivo to tenofovir , an acyclic nucleoside phosphonate (nucleotide) analog of adenosine 5' -monophosphate. Tenofovir exhibits activity against HIV-1 reverse transcriptase.
The chemical name of tenofovir disoproxil fumarateis 9-[( R )-2- [[bis[[(isopropoxycarbonyl)oxy]methoxy]phosphinyl]methoxy]propyl]adenine fumarate (1:1). It has a molecular formula of C 19 H 30 N 5 O 10 P•C 4 H 4 O 4 and a molecular weight of 635.52. It has the following structural formula: Tenofovir disoproxil fumarate is a white to off white powder freely soluble in dimethyl formamide, soluble in methanol and slightly soluble in water at 25°C.
It has a partition coefficient (log p) of 0.75. efavirenz-structure lamivudine-structure tenofovir-structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Drug Interactions: Efavirenz, lamivudine and tenofovir disoproxil fumarate may interact with many drugs; therefore, advise patients to report to their healthcare provider the use of any other prescription, nonprescription medication, or herbal products, particularly St. John’s wort [see Contraindications (4) and Drug Interactions (7) ] .
Post Treatment Acute Exacerbation of Hepatitis B in Patients with HBV Co-Infection: Inform patients that severe acute exacerbations of hepatitis have been reported in patients who are infected with HBV or coinfected with HBV and HIV-1 and have discontinued 3TC and TDF, components of efavirenz, lamivudine and tenofovir disoproxil fumarate tablets. Test patients with HIV-1 for hepatitis B virus (HBV) before initiating antiretroviral therapy. In patients with chronic hepatitis B, it is important to obtain HIV antibody testing prior to initiating 3TC and TDF, components of efavirenz, lamivudine and tenofovir disoproxil fumarate tablets [see Warnings and Precautions (5.1) ] .
Lactic Acidosis and Severe Hepatomegaly: Inform patients that lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported. Treatment with efavirenz, lamivudine and tenofovir disoproxil fumarate should be suspended in any patient who develops clinical symptoms suggestive of lactic acidosis or pronounced hepatotoxicity (including nausea, vomiting, unusual or unexpected stomach discomfort, and weakness) [see Warnings and Precautions (5.2) ] . New Onset or Worsening Renal Impairment: Inform patients that renal impairment, including cases of acute renal failure and Fanconi syndrome, has been reported.
Advise patients with impaired renal function (i.e., creatinine clearance less than 50 mL/min) or patients with end-stage renal disease (ESRD) requiring hemodialysis to avoid efavirenz, lamivudine and tenofovir disoproxil fumarate with concurrent or recent use of a nephrotoxic agent (e.g., high-dose or multiple NSAIDs) for patients [see Dosage and Administration (2.3) , Warnings and Precautions (5.4) ] . Psychiatric Symptoms: Inform patients that serious psychiatric symptoms including severe depression, suicide attempts, aggressive behavior, delusions, paranoia, psychosis-like symptoms and catatonia have been reported in patients receiving EFV [see Warnings and Precautions (5.5)] .
Advise patients to seek immediate medical evaluation if they experience severe psychiatric adverse experiences. Advise patients to inform their physician of any history of mental illness or substance abuse. Nervous System Symptoms: Inform patients that central nervous system symptoms (NSS) including dizziness, insomnia, impaired concentration, drowsiness, and abnormal dreams are commonly reported during the first weeks of therapy with EFV, a component of efavirenz, lamivudine and tenofovir disoproxil fumarate tablets [see Warnings and Precautions (5.6) ] .
Dosing at bedtime may improve the tolerability of these symptoms, which are likely to improve with continued therapy. Alert patients to the potential for additive effects when used concomitantly with alcohol or psychoactive drugs. Instruct patients that if they experience NSS they should avoid potentially hazardous tasks such as driving or operating machinery.
Inform patients that there is a risk of developing late-onset neurotoxicity, including ataxia and encephalopathy, which may occur months to years after beginning efavirenz therapy [see Warnings and Precautions (5.6) ] . Embryo-Fetal Toxicity: Advise female patients that EFV, a component of efavirenz, lamivudine and tenofovir disoproxil fumarate tablets may cause fetal harm when administered during the first trimester to a pregnant woman. Advise females of reproductive potential to use effective contraception as well as a barrier method during treatment with efavirenz, lamivudine and tenofovir diso…