
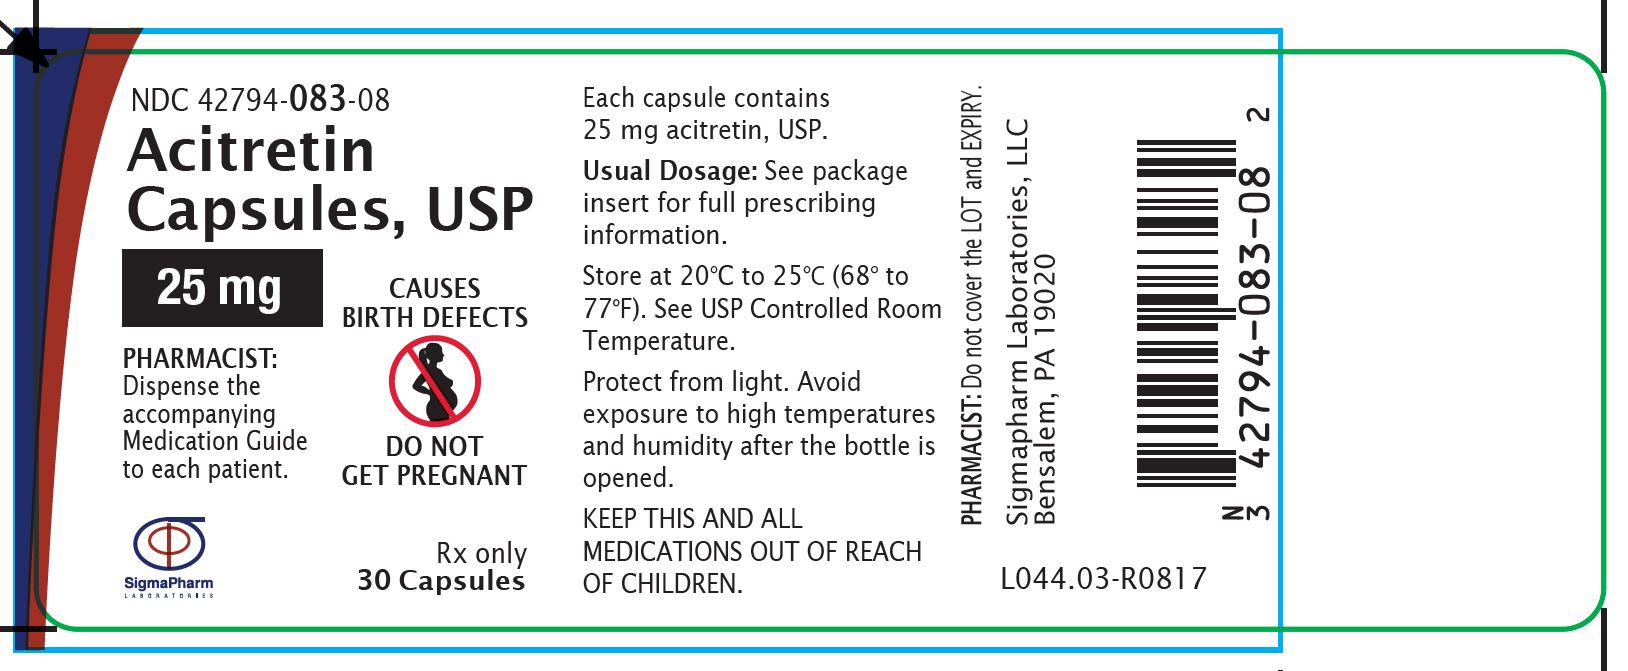
ACITRETIN 25 mg Capsule, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Retinoid class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Acitretin is used to treat severe psoriasis (abnormal growth of skin cells that causes red, thickened, or scaly skin). Acitretin is in a class of medications called retinoids. The way acitretin works is not known.
Read the full MedlinePlus article ↗- Acitretin is a retinoid — a vitamin A-related compound — that helps slow down the out-of-control skin cell growth that causes psoriasis plaques. It's used for severe psoriasis when...
- What exactly is acitretin supposed to do for my psoriasis?
- Yes, it really does matter. Taking acitretin with your main meal — not just a snack — significantly improves how much of the drug your body actually absorbs. All the clinical studi...
- Why do I have to take this with food, and does it matter how much I eat?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Acitretin — tap one for details:
Acitretin may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 7CVR7L4A2D
A starch-derived carbohydrate produced by breaking down corn, potato, or tapioca starch. It functions as a filler and binder to give the medicine bulk and texture, and sometimes as a mild sweetener or texture enhancer in powders and tablets.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII S033EH8359
Sodium ascorbate is a salt form of vitamin C. It serves as an antioxidant to prevent degradation of other ingredients and as a pH buffer to maintain stable acidity in the medicine.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $3.602 | $108.06 / 30 capsules |
| Medicaid paysCMS SDUD · 12 mo | $5.95 | $178.52 / 30 capsules |
| Medicare drug plans payPart D · Q2 2026 | $8.25 | $247.60 / 30 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Acitretin 25 mg 00093-1136-56 | Teva | 30 capsules | $3.602 | AB | Availability likely | — |
| Acitretin 25 mg 00115-1753-08 | Amneal | 30 capsules | $3.602 | AB | Discontinued | — |
| Acitretin 25 mg 00378-7023-93 | Mylan | 30 capsules | $3.602 | AB | Availability likely | — |
| Acitretin 25 mgthis 42794-0083-08 | Sigmapharm | 30 capsules | $3.602 | AB | Availability likely | — |
| Acitretin 25 mg 62332-0743-30 | Alembic | 30 capsules | $3.602 | AB | Availability likely | — |
| Acitretin 25 mg 42291-0088-30 | AvKARE | 30 capsules | — | AB | FDA listed | — |
| Acitretin 25 mg 46708-0743-30 | Alembic | 30 capsules | — | AB | FDA listed | — |
| Acitretin 25 mg 72162-2223-03 | Bryant | 30 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 42794-0083-08 You're viewing this | 30 CAPSULE in 1 BOTTLE (42794-083-08) | 2015-09-16 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
CONTRAINDICATIONS AND WARNINGS: Pregnancy Acitretin must not be used by females who are pregnant, or who intend to become pregnant during therapy or at any time for at least 3 years following discontinuation of therapy. Acitretin also must not be used by females who may not use reliable contraception while undergoing treatment and for at least 3 years following discontinuation of treatment. Acitretin is a metabolite of etretinate (TEGISON), and major human fetal abnormalities have been reported with the administration of acitretin and etretinate.
Potentially, any fetus exposed can be affected. Clinical evidence has shown that concurrent ingestion of acitretin and ethanol has been associated with the formation of etretinate, which has a significantly longer elimination half-life than acitretin. Because the longer elimination half-life of etretinate would increase the duration of teratogenic potential for female patients, ethanol must not be ingested by female patients of childbearing potential either during treatment with acitretin or for 2 months after cessation of therapy.
This allows for elimination of acitretin, thus removing the substrate for transesterification to etretinate. The mechanism of the metabolic process for conversion of acitretin to etretinate has not been fully defined. It is not known whether substances other than ethanol are associated with transesterification.
Acitretin has been shown to be embryotoxic and/or teratogenic in rabbits, mice, and rats at oral doses of 0.6, 3, and 15 mg per kg, respectively. These doses are approximately 0.2, 0.3, and 3 times the maximum recommended therapeutic dose, respectively, based on a mg-per-m 2 comparison. Major human fetal abnormalities associated with acitretin and/or etretinate administration have been reported including meningomyelocele; meningoencephalocele; multiple synostoses; facial dysmorphia; syndactyly; absence of terminal phalanges; malformations of hip, ankle, and forearm; low-set ears; high palate; decreased cranial volume; cardiovascular malformation; and alterations of the skull and cervical vertebrae.
Acitretin should be prescribed only by those who have special competence in the diagnosis and treatment of severe psoriasis, are experienced in the use of systemic retinoids, and understand the risk of teratogenicity. Because of the teratogenicity of acitretin, a program called P.P.E.T., P regnancy P revention is E ssential with T reatment, has been developed to educate women of childbearing potential and their healthcare providers about the serious risks associated with acitretin and to help prevent pregnancies from occurring with the use of this drug and for 3 years after its discontinuation.
The P.P.E.T. program requirements are described below and program materials are available at www.sigmapharm.com/PPET or may be requested by calling 1-855-273-0150 (see also PRECAUTIONS section). Important Information for Women of Childbearing Potential: Acitretin should be considered only for women with severe psoriasis unresponsive to other therapies or whose clinical condition contraindicates the use of other treatments. Females of reproductive potential must not be given a prescription for acitretin until pregnancy is excluded.
Acitretin is contraindicated in females of reproductive potential unless the patient meets ALL of the following conditions : Must have had 2 negative urine or serum pregnancy tests with a sensitivity of at least 25 mIU per mL before receiving the initial prescription for acitretin. The first test (a screening test) is obtained by the prescriber when the decision is made to pursue therapy with acitretin. The second pregnancy test (a confirmation test) should be done during the first 5 days of the menstrual period immediately preceding the beginning of therapy with acitretin.
For patients with amenorrhea, the second test should be done at least 11 days after the last act of unprotected sexual intercourse (without using 2 effective forms of c…
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Acitretin Capsules, USP are indicated for the treatment of severe psoriasis in adults. Because of significant adverse effects associated with its use, Acitretin Capsules, USP should be prescribed only by those knowledgeable in the systemic use of retinoids. In females of reproductive potential, Acitretin Capsules, USP should be reserved for non-pregnant patients who are unresponsive to other therapies or whose clinical condition contraindicates the use of other treatments (see boxed CONTRAINDICATIONS AND WARNINGS — Acitretin Capsules, USP can cause severe birth defects).
Most patients experience relapse of psoriasis after discontinuing therapy. Subsequent courses, when clinically indicated, have produced efficacy results similar to the initial course of therapy.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION There is intersubject variation in the pharmacokinetics, clinical efficacy, and incidence of side effects with Acitretin Capsules, USP. A number of the more common side effects are dose-related. Individualization of dosage is required to achieve sufficient therapeutic response while minimizing side effects.
Therapy with Acitretin Capsules, USP should be initiated at 25 to 50 mg per day, given as a single dose with the main meal. Maintenance doses of 25 to 50 mg per day may be given dependent upon an individual patient’s response to initial treatment. Relapses may be treated as outlined for initial therapy.
When Acitretin Capsules, USP are used with phototherapy, the prescriber should decrease the phototherapy dose, dependent on the patient’s individual response (see PRECAUTIONS: General ). Females who have taken TEGISON (etretinate) must continue to follow the contraceptive recommendations for TEGISON. TEGISON is no longer marketed in the US; for information, call 1-855-273-0150.
Information for Pharmacists: Acitretin Capsules, USP must only be dispensed in no more than a month supply. An Acitretin Capsules, USP Medication Guide must be given to the patient each time acitretin capsules are dispensed, as required by law.
⛔ Contraindications ▾
CONTRAINDICATIONS Pregnancy: S ee boxed CONTRAINDICATIONS AND WARNINGS . Acitretin is contraindicated in patients with severely impaired liver or kidney function and in patients with chronic abnormally elevated blood lipid values (see boxed WARNINGS: Hepatotoxicity , WARNINGS: Lipids and Possible Cardiovascular Effects , and PRECAUTIONS ). An increased risk of hepatitis has been reported to result from combined use of methotrexate and etretinate.
Consequently, the combination of methotrexate with acitretin is also contraindicated (see PRECAUTIONS: Drug Interactions ). Since both acitretin and tetracyclines can cause increased intracranial pressure, their combined use is contraindicated (see WARNINGS: Pseudotumor Cerebri ). Acitretin is contraindicated in cases of hypersensitivity (e.g., angioedema, urticaria) to the preparation (acitretin or excipients) or to other retinoids .
⚠️ Warnings ▾
WARNINGS ( See also boxed CONTRAINDICATIONS AND WARNINGS .) Hepatotoxicity: Of the 525 subjects treated in US clinical trials, 2 had clinical jaundice with elevated serum bilirubin and transaminases considered related to treatment with acitretin. Liver function test results in these subjects returned to normal after acitretin was discontinued. Two of the 1,289 subjects treated in European clinical trials developed biopsy-confirmed toxic hepatitis.
A second biopsy in one of these subjects revealed nodule formation suggestive of cirrhosis. One subject in a Canadian clinical trial of 63 subjects developed a 3-fold increase of transaminases. A liver biopsy of this subject showed mild lobular disarray, multifocal hepatocyte loss, and mild triaditis of the portal tracts compatible with acute reversible hepatic injury.
The subject’s transaminase levels returned to normal 2 months after acitretin was discontinued. The potential of therapy with acitretin to induce hepatotoxicity was prospectively evaluated using liver biopsies in an open-label trial of 128 subjects. Pretreatment and posttreatment biopsies were available for 87 subjects.
A comparison of liver biopsy findings before and after therapy revealed 49 (58%) subjects showed no change, 21 (25%) improved, and 14 (17%) subjects had a worsening of their liver biopsy status. For 6 subjects, the classification changed from class 0 (no pathology) to class I (normal fatty infiltration; nuclear variability and portal inflammation; both mild); for 7 subjects, the change was from class I to class II (fatty infiltration, nuclear variability, portal inflammation, and focal necrosis; all moderate to severe); and for 1 subject, the change was from class II to class IIIb (fibrosis, moderate to severe).
No correlation could be found between liver function test result abnormalities and the change in liver biopsy status, and no cumulative dose relationship was found. Elevations of AST (SGOT), ALT (SGPT), GGT (GGTP), or LDH have occurred in approximately 1 in 3 subjects treated with acitretin. Of the 525 subjects treated in clinical trials in the US, treatment was discontinued in 20 (3.8%) due to elevated liver function test results.
If hepatotoxicity is suspected during treatment with acitretin, the drug should be discontinued and the etiology further investigated. Ten of 652 subjects treated in US clinical trials of etretinate, of which acitretin is the active metabolite, had clinical or histologic hepatitis considered to be possibly or probably related to etretinate treatment. There have been reports of hepatitis-related deaths worldwide; a few of these subjects had received etretinate for a month or less before presenting with hepatic symptoms or signs.
Skeletal Abnormalities: In adults receiving long-term treatment with acitretin, appropriate examinations should be periodically performed in view of possible ossification abnormalities (see ADVERSE REACTIONS ). Because the frequency and severity of iatrogenic bony abnormality in adults is low, periodic radiography is only warranted in the presence of symptoms or long-term use of acitretin. If such disorders arise, the continuation of therapy should be discussed with the patient on the basis of a careful risk/benefit analysis.
In clinical trials with acitretin, subjects were prospectively evaluated for evidence of development or change in bony abnormalities of the vertebral column, knees, and ankles. Of 380 subjects treated with acitretin, 15% had preexisting abnormalities of the spine which showed new changes or progression of preexisting findings. Changes included degenerative spurs, anterior bridging of spinal vertebrae, diffuse idiopathic skeletal hyperostosis, ligament calcification, and narrowing and destruction of a cervical disc space.
De novo changes (formation of small spurs) were seen in 3 subjects after 1½ to 2½ years. Six of 128 subjects treated with acitretin showed abnormalities in the knees and ankles before treatment that progre…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Hypervitaminosis A produces a wide spectrum of signs and symptoms primarily of the mucocutaneous, musculoskeletal, hepatic, neuropsychiatric, and central nervous systems. Many of the clinical adverse reactions reported to date with administration of acitretin resemble those of the hypervitaminosis A syndrome. Adverse Events/Postmarketing Reports: In addition to the events listed in the tables for the clinical trials, the following adverse events have been identified during postapproval use of acitretin.
Because these events are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Cardiovascular: Acute myocardial infarction, thromboembolism (see WARNINGS ), stroke. Immune System Disorders: Hypersensitivity, including angioedema and urticaria (see CONTRAINDICATIONS ).
Nervous System: Myopathy with peripheral neuropathy has been reported during therapy with acitretin. Both conditions improved with discontinuation of the drug. Psychiatric: Aggressive feelings and/or suicidal thoughts have been reported.
These events, including self-injurious behavior, have been reported in patients taking other systemically administered retinoids, as well as in patients taking acitretin. Since other factors may have contributed to these events, it is not known if they are related to acitretin (see PRECAUTIONS ). Reproductive: Vulvo-vaginitis due to Candida albicans.
Skin and Appendages: Thinning of the skin, skin fragility, and scaling may occur all over the body, particularly on the palms and soles; nail fragility is frequently observed. Madarosis and exfoliative dermatitis/erythroderma have been reported (see WARNINGS ). Vascular Disorders: Capillary leak syndrome (see WARNINGS ).
Clinical Trials: During clinical trials with acitretin, 513 of 525 (98%) subjects reported a total of 3,545 adverse events. One-hundred sixteen subjects (22%) left trials prematurely, primarily because of adverse experiences involving the mucous membranes and skin. Three subjects died.
Two of the deaths were not drug-related (pancreatic adenocarcinoma and lung cancer); the other subject died of an acute myocardial infarction, considered remotely related to drug therapy. In clinical trials, acitretin was associated with elevations in liver function test results or triglyceride levels and hepatitis. The tables below list by body system and frequency the adverse events reported during clinical trials of 525 subjects with psoriasis.
Table 3. Adverse Events Frequently Reported during Clinical Trials Percent of Subjects Reporting (N=525) Body System >75% 50% to 75% 25% to 50% 10% to 25% CNS Rigors Eye Disorders Xerophthalmia Mucous Membranes Cheilitis Rhinitis Dry mouth Epistaxis Musculoskeletal Arthralgia Spinal hyperostosis (progression of existing lesions) Skin and Appendages Alopecia Skin peeling Dry skin Nail disorder Pruritus Erythematous rash Hyperesthesia Paresthesia Paronychia Skin atrophy Sticky skin Table 4. Adverse Events Less Frequently Reported during Clinical Trials (Some of Which May Bear No Relationship to Therapy) Percent of Subjects Reporting (N=525) Body Sytem 1% to 10% ≤ 1% Body as a Whole Anorexia Edema Fatigue Hot flashes Increased appetite Alcohol intolerance Dizziness Fever Influenza-like symptoms Malaise Moniliasis Muscle weakness Weight increase Cardiovascular Flushing Chest pain Cyanosis Increased bleeding time Intermittent claudication Peripheral ischemia CNS (also see Psychiatric) Headache Pain Abnormal gait Migraine Neuritis Pseudotumor cerebri (intracranial hypertension) Eye Disorders Abnormal/ blurred vision Blepharitis Conjunctivitis/ irritation Corneal epithelial abnormality Decreased night vision/night blindness Eye abnormality Eye pain Photophobia Abnormal lacrimation Chalazion Conjunctival hemorrhage Corneal ulceration Diplopia Ectropion Itchy eyes and lids Papilledema Recurrent sties Subepithelial co…
🔄 Drug Interactions ▾
Pharmacokinetic Drug Interactions (see also boxed CONTRAINDICATIONS AND WARNINGS and PRECAUTIONS : Drug Interactions ): In studies of in vivo pharmacokinetic drug interactions, no interaction was seen between acitretin and cimetidine, digoxin, phenprocoumon, or glyburide. Ethanol: Clinical evidence has shown that etretinate (a retinoid with a much longer half-life, see below) can be formed with concurrent ingestion of acitretin and ethanol. In a 2-way crossover trial, all 10 subjects formed etretinate with concurrent ingestion of a single 100-mg oral dose of acitretin during a 3-hour period of ethanol ingestion (total ethanol, approximately 1.4 g per kg body weight).
A mean peak etretinate concentration of 59 ng per mL (range: 22 to 105 ng per mL) was observed, and extrapolation of AUC values indicated that the formation of etretinate in this trial was comparable to a single 5-mg oral dose of etretinate. There was no detectable formation of etretinate when a single 100-mg oral dose of acitretin was administered without concurrent ethanol ingestion, although the formation of etretinate without concurrent ethanol ingestion cannot be excluded (see boxed CONTRAINDICATIONS AND WARNINGS ).
Of 93 evaluable psoriatic subjects on acitretin therapy in several foreign trials (10 to 80 mg per day), 16% had measurable etretinate levels (>5 ng per mL). Etretinate has a much longer elimination half-life compared with that of acitretin. In one trial the apparent mean terminal half-life after 6 months of therapy was approximately 120 days (range: 84 to 168 days).
In another trial of 47 subjects treated chronically with etretinate, 5 had detectable serum drug levels (in the range of 0.5 to 12 ng per mL) 2.1 to 2.9 years after therapy was discontinued. The long half-life appears to be due to storage of etretinate in adipose tissue. Progestin-only Contraceptives: It has not been established if there is a pharmacokinetic interaction between acitretin and combined oral contraceptives.
However, it has been established that acitretin interferes with the contraceptive effect of microdosed progestin preparations. 1 Microdosed “minipill” progestin preparations are not recommended for use with acitretin. It is not known whether other progestin-only contraceptives, such as implants and injectables, are adequate methods of contraception during acitretin therapy.
Drug Interactions: Ethanol: Clinical evidence has shown that etretinate can be formed with concurrent ingestion of acitretin and ethanol (see boxed CONTRAINDICATIONS AND WARNINGS and CLINICAL PHARMACOLOGY: Pharmacokinetics ). Glyburide: In a trial of 7 healthy male volunteers, acitretin treatment potentiated the blood glucose-lowering effect of glyburide (a sulfonylurea similar to chlorpropamide) in 3 of the 7 subjects. Repeating the trial with 6 healthy male volunteers in the absence of glyburide did not detect an effect of acitretin on glucose tolerance.
Careful supervision of diabetic patients under treatment with acitretin is recommended (see CLINICAL PHARMACOLOGY : Pharmacokinetics and DOSAGE AND ADMINISTRATION ). Hormonal Contraceptives: It has not been established if there is a pharmacokinetic interaction between acitretin and combined oral contraceptives. However, it has been established that acitretin interferes with the contraceptive effect of microdosed progestin “minipill” preparations.
Microdosed “minipill” progestin preparations are not recommended for use with acitretin (see CLINICAL PHARMACOLOGY : Pharmacokinetic Drug Interactions ). It is not known whether other progestin-only contraceptives, such as implants and injectables, are adequate methods of contraception during acitretin therapy . Methotrexate: An increased risk of hepatitis has been reported to result from combined use of methotrexate and etretinate.
Consequently, the combination of methotrexate with acitretin is also contraindicated (see CONTRAINDICATIONS ). Phenytoin: If acitretin is given concurrently with phenytoin,…
🤰 Pregnancy ▾
Pregnancy:
🧒 Pediatric Use ▾
Pediatric Use: Safety and effectiveness in pediatric patients have not been established. No clinical trials have been conducted in pediatric subjects. Ossification of interosseous ligaments and tendons of the extremities, skeletal hyperostoses, decreases in bone mineral density, and premature epiphyseal closure have been reported in children taking other systemic retinoids, including etretinate, a metabolite of acitretin.
A causal relationship between these effects and acitretin has not been established. While it is not known that these occurrences are more severe or more frequent in children, there is special concern in pediatric patients because of the implications for growth potential (see WARNINGS: Hyperostosis ).
🧓 Geriatric Use ▾
Geriatric Use: Clinical trials of acitretin did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently than younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger subjects. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
A 2-fold increase in acitretin plasma concentrations was seen in healthy elderly subjects compared with young subjects, although the elimination half-life did not change (see CLINICAL PHARMACOLOGY: Special Populations ).
🆘 Overdosage ▾
OVERDOSAGE In the event of acute overdosage, acitretin must be withdrawn at once. Symptoms of overdose are identical to acute hypervitaminosis A (e.g., headache and vertigo). The acute oral toxicity (LD 50 ) of acitretin in both mice and rats was greater than 4,000 mg per kg.
In one reported case of overdose, a 32-year-old male with Darier’s disease took 21 x 25-mg capsules (525-mg single dose). He vomited several hours later but experienced no other ill effects. All female patients of childbearing potential who have taken an overdose of acitretin must: Have a pregnancy test at the time of overdose; Be counseled as per the boxed CONTRAINDICATIONS AND WARNINGS and PRECAUTIONS sections regarding birth defects and contraceptive use for at least 3 years’ duration after the overdose.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY The mechanism of action of acitretin is unknown. Pharmacokinetics: Absorption: Oral absorption of acitretin is optimal when given with food. For this reason, acitretin was given with food in all of the following trials.
After administration of a single 50-mg oral dose of acitretin to 18 healthy subjects, maximum plasma concentrations ranged from 196 to 728 ng per mL (mean: 416 ng per mL) and were achieved in 2 to 5 hours (mean: 2.7 hours). The oral absorption of acitretin is linear and proportional with increasing doses from 25 to 100 mg. Approximately 72% (range: 47% to 109%) of the administered dose was absorbed after a single 50-mg dose of acitretin was given to 12 healthy subjects.
Distribution: Acitretin is more than 99.9% bound to plasma proteins, primarily albumin. Metabolism: ( See Pharmacokinetic Drug Interactions: Ethanol . ) Following oral absorption, acitretin undergoes extensive metabolism and interconversion by simple isomerization to its 13-cis form (cis-acitretin). The formation of cis-acitretin relative to parent compound is not altered by dose or fed/fast conditions of oral administration of acitretin.
Both parent compound and isomer are further metabolized into chain-shortened breakdown products and conjugates, which are excreted. Following multiple-dose administration of acitretin, steady-state concentrations of acitretin and cis-acitretin in plasma are achieved within approximately 3 weeks. Elimination: The chain-shortened metabolites and conjugates of acitretin and cis-acitretin are ultimately excreted in the feces (34% to 54%) and urine (16% to 53%).
The terminal elimination half-life of acitretin following multiple-dose administration is 49 hours (range: 33 to 96 hours), and that of cis-acitretin under the same conditions is 63 hours (range: 28 to 157 hours). The accumulation ratio of the parent compound is 1.2; that of cis-acitretin is 6.6. Special Populations: Psoriasis: In an 8-week trial of acitretin pharmacokinetics in subjects with psoriasis, mean steady-state trough concentrations of acitretin increased in a dose-proportional manner with dosages ranging from 10 to 50 mg daily.
Acitretin plasma concentrations were nonmeasurable (<4 ng per mL) in all subjects 3 weeks after cessation of therapy. Elderly: In a multiple-dose trial in healthy young (n = 6) and elderly (n = 8) subjects, a 2-fold increase in acitretin plasma concentrations were seen in elderly subjects, although the elimination half-life did not change. Renal Failure: Plasma concentrations of acitretin were significantly (59.3%) lower in subjects with end-stage renal failure (n = 6) when compared with age-matched controls, following single 50-mg oral doses.
Acitretin was not removed by hemodialysis in these subjects. Pharmacokinetic Drug Interactions (see also boxed CONTRAINDICATIONS AND WARNINGS and PRECAUTIONS : Drug Interactions ): In studies of in vivo pharmacokinetic drug interactions, no interaction was seen between acitretin and cimetidine, digoxin, phenprocoumon, or glyburide. Ethanol: Clinical evidence has shown that etretinate (a retinoid with a much longer half-life, see below) can be formed with concurrent ingestion of acitretin and ethanol.
In a 2-way crossover trial, all 10 subjects formed etretinate with concurrent ingestion of a single 100-mg oral dose of acitretin during a 3-hour period of ethanol ingestion (total ethanol, approximately 1.4 g per kg body weight). A mean peak etretinate concentration of 59 ng per mL (range: 22 to 105 ng per mL) was observed, and extrapolation of AUC values indicated that the formation of etretinate in this trial was comparable to a single 5-mg oral dose of etretinate. There was no detectable formation of etretinate when a single 100-mg oral dose of acitretin was administered without concurrent ethanol ingestion, although the formation of etretinate without concurrent ethanol ingestion cannot be excluded (see boxed CONTRAINDICATIONS AND WARNINGS ).
Of 93 evaluable pso…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED: Acitretin Capsules, USP 10 mg (opaque yellow and opaque white) are imprinted “Σ 80” on body and cap; Bottles of 30 (NDC 42794-080-08). Acitretin Capsules, USP 17.5 mg (opaque orange) are imprinted “Σ 81” on body and cap; Bottles of 30 (NDC 42794-081-08). Acitretin Capsules, USP 25 mg (opaque yellow) are imprinted “Σ 83” on body and cap; Bottles of 30 (NDC 42794-083-08).
Store at 20 to 25°C (68 to 77°F). See USP Controlled Room Temperature. Protect from light.
Avoid exposure to high temperatures and humidity after the bottle is opened. KEEP THIS AND ALL MEDICATIONS OUT OF REACH OF CHILDREN. All brand names listed are the registered trade names of their respective owners and are not trademarks of Sigmapharm Laboratories, LLC.
📋 Description ▾
DESCRIPTION Acitretin, USP, a retinoid, is available in 10-mg, 17.5-mg, and 25-mg gelatin capsules for oral administration. Chemically, acitretin is all-trans-9-(4-methoxy-2,3,6-trimethylphenyl)-3,7-dimethyl-2,4,6,8-nonatetraenoic acid. It is a metabolite of etretinate and is related to both retinoic acid and retinol (vitamin A).
It is a yellow to greenish-yellow powder with a molecular weight of 326.43. The structural formula is: Each capsule contains acitretin, USP 10-mg, 17.5-mg, and 25-mg. Inactive ingredients are microcrystalline cellulose, sodium lauryl sulfate, maltodextrin, povidone and sodium ascorbate.
The 10-mg, 17.5-mg, and 25-mg gelatin capsule shells contain gelatin, iron oxide (yellow), titanium dioxide, sodium lauryl sulfate and black imprinting ink. In addition, the 17.5-mg gelatin capsule shells also contain iron oxide (red). structure
💬 Medication Guide ▾
MEDICATION GUIDE ACITRETIN CAPSULES, USP [ A-si-TRE-tin] Read this Medication Guide carefully before you start taking acitretin capsules and read it each time you get more acitretin capsules. There may be new information. The first information in this Medication Guide is about birth defects and how to avoid pregnancy.
After this section there is important safety information about possible effects for any patient taking acitretin capsules. All patients should read this entire Medication Guide carefully. This information does not take the place of talking with your prescriber about your medical condition or treatment.
What is the most important information I should know about acitretin capsules? Acitretin capsules can cause serious side effects, including: Severe birth defects. If you are a female who can get pregnant, you should use acitretin capsules only if you are not pregnant now, can avoid becoming pregnant for at least 3 years, and other medicines do not work for your severe psoriasis or you cannot use other psoriasis medicines.
Information about effects on unborn babies and about how to avoid pregnancy is found in the next section: “What are the important warnings and instructions for females taking acitretin capsules?” Liver problems, including abnormal liver function tests and inflammation of your liver (hepatitis). Your prescriber should do blood tests to check how your liver is working before you start taking and during treatment with acitretin capsules. Stop taking acitretin capsules and call your prescriber right away if you have any of the following signs or symptoms of a serious liver problem: yellowing of your skin or the whites of your eyes nausea and vomiting loss of appetite dark urine What are the important warnings and instructions for females taking acitretin capsules?
Before you receive your first prescription for acitretin capsules, you should have discussed and signed a Patient Agreement/Informed Consent for Female Patients form with your prescriber. This is to help make sure you understand the risk of birth defects and how to avoid getting pregnant. If you did not talk to your prescriber about this and sign the form, contact your prescriber.
Important: If you are a female who can become pregnant: You must not take acitretin capsules if you are pregnant or might become pregnant during treatment or at any time for at least 3 years after you stop treatment because acitretin capsules can cause severe birth defects. During treatment with acitretin capsules and for 2 months after you stop treatment with acitretin capsules, you must avoid drinks, foods, and all medicines that contain alcohol. This includes over-the-counter products that contain alcohol.
Avoiding alcohol is very important, because alcohol changes acitretin capsules into a drug that may take longer than 3 years to leave your body. The chance of birth defects may last longer than 3 years if you swallow any form of alcohol during treatment with acitretin capsules and for 2 months after you stop taking acitretin capsules. You and your prescriber must be sure you are not pregnant before you start therapy with acitretin capsules.
You must have negative results from 2 pregnancy tests before you start treatment with acitretin capsules. A negative result shows you are not pregnant. Because it takes a few days after pregnancy begins for a test to show that you are pregnant, the first negative test may not ensure you are not pregnant.
Do not start acitretin capsules until you have negative results from 2 pregnancy tests. The first pregnancy test (urine or blood) will be done at the time you and your prescriber decide if acitretin capsules might be right for you. The second pregnancy test will usually be done during the first 5 days of your menstrual period.
You must start taking acitretin capsules within 7 days of when the urine or blood for the second pregnancy test is collected. After you start taking acitretin capsules, you must have a pregnancy test…