
valganciclovir hydrochloride 450 mg Tablet, 60-count — NDC 43598-356-60 (Billing 43598-0356-60)
This is a package of 60 tablets of valganciclovir hydrochloride 450 mg Tablet from Dr. Reddy's Laboratories Inc, marketed since Dec 2017 and currently FDA-listed.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 313566
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Cytomegalovirus Nucleoside Analog DNA Polymerase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It treats CMV retinitis, a CMV eye infection, in adults with AIDS. It also helps prevent CMV disease in high-risk transplant patients, including some children. CMV can be serious w...
- Take it by mouth exactly as your prescriber directs. The oral solution should be taken with food. Don't change your schedule on your own. Treatment length depends on your condition...
- Diarrhea, nausea, vomiting, fever, tiredness, headache, tremor, and trouble sleeping are common. Call me or your doctor for fever, infection signs, unusual bruising or bleeding, mu...
- Valganciclovir can lower your white cells, red cells, and platelets, sometimes severely. Regular blood counts catch problems early. Your kidney function is checked too, since it af...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $3.50 | $209.97 / 60 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 43598-0356-30 43598-356-30 Main listing | 30 TABLET in 1 BOTTLE | 2017-12-12 | — | Active |
| 43598-0356-60 You're viewing this | 60 TABLET in 1 BOTTLE | 2017-12-12 | — | Active |
You're viewing the largest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 43598-0356-30?
What NDC number is used to bill for this package of valganciclovir hydrochloride 450 mg Tablet?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Valganciclovir 450 mg 00904-6796-04 | Major | 1 tablet | $1.915 | AB | Availability likely | — |
| Valganciclovir 450 mg 27241-0158-60 | Ajanta | 60 tablets | $1.915 | AB | Availability likely | — |
| Valganciclovir 450 mg 50268-0787-12 | AvPAK | 1 tablet | $1.915 | AB | Availability likely | — |
| Valganciclovir 450 mg 64380-0153-01 | Strides | 60 tablets | $1.915 | AB | Availability likely | — |
| Valganciclovir 450 mg 64380-0161-01 | Strides | 60 tablets | $1.915 | AB | Availability likely | — |
| Valganciclovir 450 mg 68084-0965-25 | American | 1 tablet | $1.915 | AB | Availability likely | — |
| Valganciclovir Hydrochloride 450 mg 72603-0750-01 | NorthStar | 60 tablets | $1.915 | AB | Availability likely | — |
| Valganciclovir 450 mg 31722-0832-31 | Camber | 10 tablets | — | AB | FDA listed | — |
| Valganciclovir 450 mg 42291-0973-60 | AvKARE | 60 tablets | — | AB | FDA listed | — |
| valganciclovir hydrochloride 450 mgthis 43598-0356-60 | Dr. | 60 tablets | — | AB | FDA listed | — |
| Valganciclovir 450 mg 55111-0762-05 | Dr. | 500 tablets | — | AB | FDA listed | — |
| Valganciclovir 450 mg 60429-0846-60 | Golden | 60 tablets | — | AB | Discontinued | — |
| Valcyte 450 mg 61269-0480-60 | H2-Pharma, | 60 tablets | — | AB | FDA listed | — |
| Valganciclovir Hydrochloride 450 mg 65862-0753-01 | Aurobindo | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 68401960MK
Crospovidone is a synthetic polymer made from polyvinylpyrrolidone. It acts as a disintegrant, helping tablets break apart quickly in the stomach so the medicine dissolves and absorbs into the body.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: HEMATOLOGIC TOXICITY, IMPAIRMENT OF FERTILITY, FETAL TOXICITY, MUTAGENESIS AND CARCINOGENESIS • Hematologic Toxicity: Severe leukopenia, neutropenia, anemia, thrombocytopenia, pancytopenia, and bone marrow failure including aplastic anemia have been reported in patients treated with valganciclovir [see Warnings and Precautions ( 5.1 )]. • Impairment of Fertility: Based on animal data and limited human data, valganciclovir may cause temporary or permanent inhibition of spermatogenesis in males and suppression of fertility in females [see Warnings and Precautions ( 5.3 )]. • Fetal Toxicity: Based on animal data, valganciclovir has the potential to cause birth defects in humans [see Warnings and Precautions ( 5.4 )]. • Mutagenesis and Carcinogenesis: Based on animal data, valganciclovir has the potential to cause cancers in humans [see Warnings and Precautions ( 5.5 )].
WARNING: HEMATOLOGIC TOXICITY, IMPAIRMENT OF FERTILITY, FETAL TOXICITY, MUTAGENESIS AND CARCINOGENESIS See full prescribing information for complete boxed warning . Hematologic Toxicity: Severe leukopenia, neutropenia, anemia, thrombocytopenia, pancytopenia, and bone marrow failure including aplastic anemia have been reported in patients treated with valganciclovir. ( 5.1 ) Impairment of Fertility: Based on animal data and limited human data, valganciclovir may cause temporary or permanent inhibition of spermatogenesis in males and suppression of fertility in females.
( 5.3 ) Fetal Toxicity: Based on animal data, valganciclovir has the potential to cause birth defects in humans. ( 5.4 ) Mutagenesis and Carcinogenesis: Based on animal data, valganciclovir has the potential to cause cancers in humans. ( 5.5 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Valganciclovir tablet is a deoxynucleoside analogue cytomegalovirus (CMV) DNA polymerase inhibitor indicated for: Adult Patients (1.1) Treatment of CMV retinitis in patients with acquired immunodeficiency syndrome (AIDS). Prevention of CMV disease in kidney, heart, and kidney-pancreas transplant patients at high risk. Pediatric Patients (1.2) Prevention of CMV disease in kidney and heart transplant patients at high risk.
1.1Adult Patients Treatment of Cytomegalovirus (CMV) Retinitis : Valganciclovir tablets are indicated for the treatment of CMV retinitis in patients with acquired immunodeficiency syndrome (AIDS) [see Clinical Studies ( 14.1 ) ]. Prevention of CMV Disease : Valganciclovir tablets are indicated for the prevention of CMV disease in kidney, heart, and kidney-pancreas transplant patients at high risk (Donor CMV seropositive/Recipient CMV seronegative [D+/R-]) [see Clinical Studies ( 14.1 ) ].
1.2Pediatric Patients Prevention of CMV Disease :Valganciclovir tablets are indicated for the prevention of CMV disease in kidney transplant patients (4 months to 16 years of age) and heart transplant patients (1 month to 16 years of age) at high risk [see Clinical Studies ( 14.2 ) ].
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Adult Dosage ( 2.2 ) Treatment of CMV retinitis Induction: 900 mg (two 450 mg tablets) twice a day for 21 days Maintenance: 900 mg (two 450 mg tablets) once a day Prevention of CMV disease in heart or kidney-pancreas transplant patients 900 mg (two 450 mg tablets) once a day within 10 days of transplantation until 100 days post-transplantation Prevention of CMV disease in kidney transplant patients 900 mg (two 450 mg tablets) once a day within 10 days of transplantation until 200 days post-transplantation Pediatric Dosage ( 2.3 ) Prevention of CMV disease in kidney transplant patients 4 months to 16 years of age Dose once a day within 10 days of transplantation until 200 days post-transplantation according to dosage algorithm (note the calculation of creatinine clearance using a modified Schwartz formula in children) Prevention of CMV disease in heart transplant patients 1 month to 16 years of age Dose once a day within 10 days of transplantation until 100 days post-transplantation according to dosage algorithm (note the calculation of creatinine clearance using a modified Schwartz formula in children) • Valganciclovir tablets should be taken with food.
( 2.1 , 12.3 ) • Valganciclovir tablets should not be broken or crushed. ( 2.6 ) • Adult patients should use valganciclovir tablets, not valganciclovir for oral solution. ( 2.1 ) •Adults with renal impairment: Adjust dose based on creatinine clearance.
For adult patients receiving hemodialysis a dose recommendation cannot be given. ( 2.5 , 8.6 , 12.3 )
2.1General Dosing Information Adult patients should use valganciclovir tablets, not valganciclovir for oral solution. Valganciclovir tablets should be taken with food [see Clinical Pharmacology ( 12.3 ) ].
2.2Recommended Dosage in Adult Patients with Normal Renal Function For dosage recommendations in adult patients with renal impairment [see Dosage and Administration ( 2.5 )] . Treatment of CMV Retinitis: Induction: The recommended dosage is 900 mg (two 450 mg tablets) taken orally twice a day for 21 days. Maintenance: Following induction treatment, or in adult patients with inactive CMV retinitis, the recommended dosage is 900 mg (two 450 mg tablets) taken orally once a day.
Prevention of CMV Disease: For adult patients who have received a heart or kidney-pancreas transplant, the recommended dosage is 900 mg (two 450 mg tablets) taken orally once a day starting within 10 days of transplantation until 100 days post-transplantation. For adult patients who have received a kidney transplant, the recommended dosage is 900 mg (two 450 mg tablets) taken orally once a day starting within 10 days of transplantation until 200 days post-transplantation.
2.3Recommended Dosage in Pediatric Patients Prevention of CMV Disease in Pediatric Kidney Transplant Patients: For pediatric kidney transplant patients 4 months to 16 years of age, the recommended once daily mg dose (7 x BSA x CrCl) should start within 10 days of post-transplantation until 200 days post-transplantation. Prevention of CMV Disease in Pediatric Heart Transplant Patients : For pediatric heart transplant patients 1 month to 16 years of age, the recommended once daily mg dose (7 x BSA x CrCl) should start within 10 days of transplantation until 100 days post-transplantation.
The recommended once daily dosage of valganciclovir tablets is based on body surface area (BSA) and creatinine clearance (CrCl) derived from a modified Schwartz formula, and is calculated using the equation below: Pediatric Dose (mg) = 7 x BSA x CrCl (calculated using a modified Schwartz formula). If the calculated Schwartz creatinine clearance exceeds 150 mL/min/1.73m 2 , then a maximum value of 150 mL/min/1.73m 2 should be used in the equation.The k values used in the modified Schwartz formula are based on pediatric patient age, as shown in Table 1.
Table 1 k Values According to Pediatric Patient Age* k value Pediatric Patient Age
0.33Infants less than 1 year of age with low… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Valganciclovir Tablets: Valganciclovir Tablets USP, 450 mg are pink colored, modified capsule shaped, film coated tablets debossed with ‘RDY’ on one side and ‘762’ on other side. • Tablets: 450 mg. (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Valganciclovir tablets are contraindicated in patients who have had a demonstrated clinically significant hypersensitivity reaction (e.g., anaphylaxis) to valganciclovir, ganciclovir, or any component of the formulation [see Adverse Reactions ( 6.1 ) ]. Hypersensitivity to valganciclovir or ganciclovir. (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Acute renal failure: Acute renal failure may occur in elderly patients (with or without reduced renal function), patients who receive concomitant nephrotoxic drugs, or inadequately hydrated patients. Use with caution in elderly patients or those taking nephrotoxic drugs, reduce dosage in patients with renal impairment, and monitor renal function ( 2.5 , 5.2 , 8.5 , 8.6 ).
5.1Hematologic Toxicity Severe leukopenia, neutropenia, anemia, thrombocytopenia, pancytopenia, and bone marrow failure including aplastic anemia have been reported in patients treated with valganciclovir or ganciclovir. Valganciclovir should be avoided if the absolute neutrophil count is less than 500 cells/μL, the platelet count is less than 25,000/μL, or the hemoglobin is less than 8 g/dL . Valganciclovir should also be used with caution in patients with pre-existing cytopenias and in patients receiving myelosuppressive drugs or irradiation.
Cytopenia may occur at any time during treatment and may worsen with continued dosing. Cell counts usually begin to recover within 3 to 7 days after discontinuing drug. In patients with severe leukopenia, neutropenia, anemia and/or thrombocytopenia, treatment with hematopoietic growth factors may be considered.
Due to the frequency of neutropenia, anemia, and thrombocytopenia in patients receiving valganciclovir [see Adverse Reactions ( 6.1 ) ], complete blood counts with differential and platelet counts should be performed frequently, especially in infants, in patients with renal impairment and in patients in whom ganciclovir or other nucleoside analogues have previously resulted in leukopenia, or in whom neutrophil counts are less than 1,000 cells/μL at the beginning of treatment. Increased monitoring for cytopenias may be warranted if therapy with oral ganciclovir is changed to valganciclovir because of increased plasma concentrations of ganciclovir after valganciclovir administration [see Clinical Pharmacology ( 12.3 ) ].
5.2Acute Renal Failure Acute renal failure may occur in: • Elderly patients with or without reduced renal function. Caution should be exercised when administering valganciclovir to geriatric patients, and dosage reduction is recommended for those with impaired renal function [see Dosage and Administration ( 2.5 ), Use in Specific Populations ( 8.5 , 8.6 ) ]. • Patients receiving potential nephrotoxic drugs. Caution should be exercised when administering valganciclovir to patients receiving potential nephrotoxic drugs. • Patients without adequate hydration.
Adequate hydration should be maintained for all patients.
5.3Impairment of Fertility Based on animal data and limited human data, valganciclovir at the recommended human doses may cause temporary or permanent inhibition of spermatogenesis in males, and may cause suppression of fertility in females. Advise patients that fertility may be impaired with use of valganciclovir [see Use in Specific Populations ( 8.1 , 8.3 ), Nonclinical Toxicology ( 13.1 )] .
5.4Fetal Toxicity Ganciclovir may cause fetal toxicity when administered to pregnant women based on findings in animal studies. When given to pregnant rabbits at dosages resulting in 2 times the human exposure (based on AUC), ganciclovir caused malformations in multiple organs of the fetuses. Maternal and fetal toxicity were also observed in pregnant mice and rabbits.
Therefore, valganciclovir has the potential to cause birth defects. Pregnancy should be avoided in female patients taking valganciclovir and in females with male partners taking valganciclovir. Females of reproductive potential should be advised to use effective contraception during treatment and for at least 30 days following treatment with valganciclovir because of the potential risk to the fetus.
Similarly, males should be advised to use condoms during and for at least 90 days following treatment with valganciclovir [see Dosage and Administration ( 2.6 ), Use in Specific Populations ( 8.1 , 8.3 ), No… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed in greater detail in other sections of the labeling: Hematologic Toxicity [see Warnings and Precautions (5.1) ]. Acute Renal Failure [see Warnings and Precautions ( 5.2 ) ]. Impairment of Fertility [see Warnings and Precautions ( 5.3 )] .
Fetal Toxicity [see Warnings and Precautions ( 5.4 )] . Mutagenesis and Carcinogenesis [see Warnings and Precautions ( 5.5 )] . The most common adverse reactions and laboratory abnormalities reported in at least one indication by greater than or equal to 20% of adult patients treated with valganciclovir tablets are diarrhea, pyrexia, fatigue, nausea, tremor, neutropenia, anemia, leukopenia, thrombocytopenia, headache, insomnia, urinary tract infection, and vomiting.
The most common reported adverse reactions and laboratory abnormalities reported in greater than or equal to 20% of pediatric solid organ transplant recipients treated with valganciclovir tablets are diarrhea, pyrexia, upper respiratory tract infection, urinary tract infection, vomiting, neutropenia, leukopenia, and headache. Adult patients: Most common adverse reactions and laboratory abnormalities (reported in at least one indication by greater than or equal to 20% of patients) are diarrhea, pyrexia, fatigue, nausea, tremor, neutropenia, anemia, leukopenia, thrombocytopenia, headache, insomnia, urinary tract infection, and vomiting ( 6.1) .
Pediatric patients: Most common adverse reactions and laboratory abnormalities (reported in greater than or equal to 20% of pediatric solid organ transplant recipients) are diarrhea, pyrexia, upper respiratory tract infection, urinary tract infection, vomiting, neutropenia, leukopenia, and headache ( 6.1 ). To report SUSPECTED ADVERSE REACTIONS, contact Dr. Reddy’s Laboratories Inc., at 1-888-375-3784 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect rates observed in practice. Valganciclovir, a prodrug of ganciclovir, is rapidly converted to ganciclovir after oral administration. Adverse reactions known to be associated with ganciclovir usage can therefore be expected to occur with valganciclovir.
Adverse Reactions in Adults: Treatment of CMV Retinitis in AIDS Patients : In a clinical study for the treatment of CMV retinitis in HIV-infected patients, the adverse reactions reported by patients receiving valganciclovir tablets (n=79) or intravenous ganciclovir (n=79) for 28 days of randomized therapy (21 days induction dose and 7 days maintenance dose), respectively, included diarrhea (16%, 10%), nausea (8%, 14%), and headache (9%, 5%). The incidence of adverse reactions was similar between the group who received valganciclovir tablets and the group who received intravenous ganciclovir.
The frequencies of neutropenia (ANC less than 500/μL) were 11% for patients receiving valganciclovir tablets compared with 13% for patients receiving intravenous ganciclovir. Anemia (Hgb less than 8 g/dL) occurred in 8% of patients in each group. Other laboratory abnormalities occurred with similar frequencies in the two groups.
Adverse reactions and laboratory abnormalities are available for 370 patients who received maintenance therapy with valganciclovir tablets 900 mg once daily in two open-label clinical trials. Approximately 252 (68%) of these patients received valganciclovir tablets for more than nine months (maximum duration was 36 months). Table 3 and Table 4 show pooled selected adverse reactions and abnormal laboratory values from these patients.
Table 3 Pooled Selected Adverse Reactions Reported in greater than or equal to 5% of Patients who Received Valganciclovir Tablets Maintenance Therapy for CMV Retinitis Patients with CMV Retinitis Adverse Reactions according to B… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS In vivo drug-drug interaction studies were not conducted with valganciclovir. However, because valganciclovir is rapidly and extensively converted to ganciclovir, drug-drug interactions associated with ganciclovir will be expected for valganciclovir. Drug-drug interaction studies with ganciclovir were conducted in patients with normal renal function.
Following concomitant administration of valganciclovir and other renally excreted drugs, patients with impaired renal function may have increased concentrations of ganciclovir and the coadministered drug. Therefore, these patients should be closely monitored for toxicity of ganciclovir and the coadministered drug. Established and other potentially significant drug interactions conducted with ganciclovir are listed in Table 9.
Table 9 Established and Other Potentially Significant Drug Interactions with Ganciclovir Name of the Concomitant Drug Change in the Concentration of Ganciclovir or Concomitant Drug Clinical Comment Imipenem-cilastatin Unknown Coadministration with imipenemcilastatin is not recommended because generalized seizures have been reported in patients who received ganciclovir and imipenem-cilastatin. Cyclosporine or amphotericin B Unknown Monitor renal function when valganciclovir is coadministered with cyclosporine or amphotericin B because of potential increase in serum creatinine [see Warnings and Precautions (5.2)].
Mycophenolate mofetil (MMF) ↔ Ganciclovir (in patients with normal renal function) ↔ MMF (in patients with normal renal function) Based on increased risk, patients should be monitored for hematological and renal toxicity. Other drugs associated with myelosuppression or nephrotoxicity (e.g., adriamycin, dapsone, doxorubicin, flucytosine, hydroxyurea, pentamidine, tacrolimus, trimethoprim/ sulfamethoxazole, vinblastine, vincristine, and zidovudine) Unknown Because of potential for higher toxicity, coadministration with valganciclovir should be considered only if the potential benefits are judged to outweigh the risks.
Didanosine ↔ Ganciclovir ↑ Didanosine Patients should be closely monitored for didanosine toxicity (e.g., pancreatitis) Probenecid ↑ Ganciclovir Valganciclovir dose may need to be reduced. Monitor for evidence of ganciclovir toxicity. Imipenem-cilastatin: Seizures were reported in patients receiving ganciclovir and imipenem-cilastatin.
Concomitant use is not recommended unless the potential benefits outweigh the risks. ( 7 ) Cyclosporine or amphotericin B: When coadministered with valganciclovir, the risk of nephrotoxicity may be increased. Monitor renal function.
( 5.2 , 7 ) Mycophenolate mofetil (MMF): When coadministered with valganciclovir, the risk of hematological and renal toxicity may be increased. Monitor for ganciclovir and MMF toxicity. ( 7 ) Other drugs associated with myelosuppression or nephrotoxicity: Due to potential for increased toxicity, consider for concomitant use with valganciclovir only if the potential benefits are judged to outweigh the risks.
( 7 ) Didanosine: Ganciclovir coadministered with didanosine may increase didanosine levels. Monitor for didanosine toxicity (e.g., pancreatitis). ( 7 ) Probenecid: May increase ganciclovir levels.
Monitor for evidence of ganciclovir toxicity. ( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Lactation: Breastfeeding is not recommended with use of valganciclovir ( 8.2 ).
8.1Pregnancy Risk Summary After oral administration, valganciclovir (prodrug) is converted to ganciclovir (active drug) and, therefore, valganciclovir is expected to have reproductive toxicity effects similar to ganciclovir. In animal studies, ganciclovir caused maternal and fetal toxicity and embryo-fetal mortality in pregnant mice and rabbits as well as teratogenicity in rabbits at exposures two-times the human exposure. There are no available human data on use of valganciclovir or ganciclovir in pregnant women to establish the presence or absence of drug-associated risk.
The background risk of major birth defects and miscarriage for the indicated populations is unknown. However, the background risk in the U.S. general population of major birth defects is 2 to 4% and the risk of miscarriage is 15 to 20% of clinically recognized pregnancies. Advise pregnant women of the potential risk to the fetus [see Warnings and Precautions ( 5.3 ), Use in Specific Populations ( 8.3 ) ].
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Most maternal CMV infections are asymptomatic or they may be associated with a self-limited mononucleosis-like syndrome. However, in immunocompromised patients (i.e., transplant patients or patients with AIDS) CMV infections may be symptomatic and may result in significant maternal morbidity and mortality. The transmission of CMV to the fetus is a result of maternal viremia and transplacental infection.
Perinatal infection can also occur from exposure of the neonate to CMV shedding in the genital tract. Approximately 10% of children with congenital CMV infection are symptomatic at birth. Mortality in these infants is about 10% and approximately 50 to 90% of symptomatic surviving newborns experience significant morbidity, including mental retardation, sensorineural hearing loss, microcephaly, seizures, and other medical problems.
The risk of congenital CMV infection resulting from primary maternal CMV infection may be higher and of greater severity than that resulting from maternal reactivation of CMV infection. Data Animal Data Doses resulting in two-times the human exposure of ganciclovir (based on the human AUC following a single intravenous infusion of 5 mg per kg of ganciclovir) resulted in maternal and embryo-fetal toxicity in pregnant mice and rabbits as well as teratogenicity in the rabbits. Fetal resorptions were present in at least 85% of rabbits and mice.
Rabbits showed increased embryo-fetal mortality, growth retardation of the fetuses and structural abnormalities of multiple organs of the fetuses including the palate (cleft palate), eyes (anophthalmia/microphthalmia), brain (hydrocephalus), jaw (brachygnathia), kidneys and pancreas (aplastic organs). Increased embryo-fetal mortality was also seen in mice. Daily intravenous doses of approximately 1.7 times the human exposure (based on AUC) administered to female mice prior to mating, during gestation, and during lactation caused hypoplasia of the testes and seminal vesicles in the male offspring, as well as pathologic changes in the nonglandular region of the stomach.
Data from an ex-vivo human placental model showed that ganciclovir crosses the human placenta. The transfer occurred by passive diffusion and was not saturable over a concentration range of 1 to 10 mg/mL.
8.2Lactation Risk Summary No data are available regarding the presence of valganciclovir (prodrug) or ganciclovir (active drug) in human milk, the effects on the breastfed infant, or the effects on milk production. Animal data indicate that ganciclovir is excreted in the milk of lactating rats. The Centers for Disease Control and Prevention recommend that HIV-infected mothers not breastfeed their infants to avoid risking postnatal transmission of HIV.
Advise nursing mothers that breastfeeding is not recommended during treatment with valgancicl… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary After oral administration, valganciclovir (prodrug) is converted to ganciclovir (active drug) and, therefore, valganciclovir is expected to have reproductive toxicity effects similar to ganciclovir. In animal studies, ganciclovir caused maternal and fetal toxicity and embryo-fetal mortality in pregnant mice and rabbits as well as teratogenicity in rabbits at exposures two-times the human exposure. There are no available human data on use of valganciclovir or ganciclovir in pregnant women to establish the presence or absence of drug-associated risk.
The background risk of major birth defects and miscarriage for the indicated populations is unknown. However, the background risk in the U.S. general population of major birth defects is 2 to 4% and the risk of miscarriage is 15 to 20% of clinically recognized pregnancies. Advise pregnant women of the potential risk to the fetus [see Warnings and Precautions ( 5.3 ), Use in Specific Populations ( 8.3 ) ].
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Most maternal CMV infections are asymptomatic or they may be associated with a self-limited mononucleosis-like syndrome. However, in immunocompromised patients (i.e., transplant patients or patients with AIDS) CMV infections may be symptomatic and may result in significant maternal morbidity and mortality. The transmission of CMV to the fetus is a result of maternal viremia and transplacental infection.
Perinatal infection can also occur from exposure of the neonate to CMV shedding in the genital tract. Approximately 10% of children with congenital CMV infection are symptomatic at birth. Mortality in these infants is about 10% and approximately 50 to 90% of symptomatic surviving newborns experience significant morbidity, including mental retardation, sensorineural hearing loss, microcephaly, seizures, and other medical problems.
The risk of congenital CMV infection resulting from primary maternal CMV infection may be higher and of greater severity than that resulting from maternal reactivation of CMV infection. Data Animal Data Doses resulting in two-times the human exposure of ganciclovir (based on the human AUC following a single intravenous infusion of 5 mg per kg of ganciclovir) resulted in maternal and embryo-fetal toxicity in pregnant mice and rabbits as well as teratogenicity in the rabbits. Fetal resorptions were present in at least 85% of rabbits and mice.
Rabbits showed increased embryo-fetal mortality, growth retardation of the fetuses and structural abnormalities of multiple organs of the fetuses including the palate (cleft palate), eyes (anophthalmia/microphthalmia), brain (hydrocephalus), jaw (brachygnathia), kidneys and pancreas (aplastic organs). Increased embryo-fetal mortality was also seen in mice. Daily intravenous doses of approximately 1.7 times the human exposure (based on AUC) administered to female mice prior to mating, during gestation, and during lactation caused hypoplasia of the testes and seminal vesicles in the male offspring, as well as pathologic changes in the nonglandular region of the stomach.
Data from an ex-vivo human placental model showed that ganciclovir crosses the human placenta. The transfer occurred by passive diffusion and was not saturable over a concentration range of 1 to 10 mg/mL.
🧒 Pediatric Use ▾
8.4Pediatric Use Valganciclovir tablets are indicated for the prevention of CMV disease in pediatric kidney transplant patients 4 months to 16 years of age and in pediatric heart transplant patients 1 month to 16 years of age at risk for developing CMV disease [see Indications and Usage ( 1.2 ), Dosage and Administration ( 2.3 )] . The use of valganciclovir for oral solution and tablets for the prevention of CMV disease in pediatric kidney transplant patients 4 months to 16 years of age is based on two single-arm, open-label, non-comparative studies in patients 4 months to 16 years of age.
Study 1 was a safety and pharmacokinetic study in pediatric solid organ transplant patients (kidney, liver, heart, and kidney/pancreas). Valganciclovir was administered once daily within 10 days of transplantation for a maximum of 100 days post-transplantation. Study 2 was a safety and tolerability study where valganciclovir was administered once daily within 10 days of transplantation for a maximum of 200 days post-transplantation in pediatric kidney transplant patients.
The results of these studies were supported by previous demonstration of efficacy in adult patients [see Adverse Reactions (6.1) , Clinical Pharmacology (12.3) , Clinical Studies (14.2) ]. The use of valganciclovir for oral solution and tablets for the prevention of CMV disease in pediatric heart transplant patients 1 month to 16 years of age is based on two studies (Study 1 described above and Study 3) and was supported by previous demonstration of efficacy in adult patients [see Clinical Pharmacology ( 12.3 ), Clinical Studies ( 14.2 ) ].
Study 3 was a pharmacokinetic and safety study of valganciclovir in pediatric heart transplant patients less than 4 months of age who received a single dose of valganciclovir oral solution on each of two consecutive days. A physiologically based pharmacokinetic (PBPK) model was developed based on the available pharmacokinetic data from pediatric and adult patients to support dosing in heart transplant patients less than 1 month of age. However, due to uncertainty in model predictions for neonates, valganciclovir is not indicated for prophylaxis in this age group.
The safety and efficacy of valganciclovir oral solution and tablets have not been established in children for prevention of CMV disease in pediatric liver transplant patients, in kidney transplant patients less than 4 months of age, in heart transplant patients less than 1 month of age, in pediatric AIDS patients with CMV retinitis, and in infants with congenital CMV infection. A pharmacokinetic and pharmacodynamic evaluation of valganciclovir for oral solution was performed in 24 neonates with congenital CMV infection involving the central nervous system.
All patients were treated for 6 weeks with a combination of intravenous ganciclovir 6 mg per kg twice daily or valganciclovir for oral solution at doses ranging from 14 mg per kg to 20 mg per kg twice daily. The pharmacokinetic results showed that in infants greater than 7 days to 3 months of age, a dose of 16 mg per kg twice daily of valganciclovir for oral solution provided ganciclovir systemic exposures (median AUC 0-12h = 23.6 [range 16.8 to 35.5] mcg ∙ h/mL; n = 6) comparable to those obtained in infants up to 3 months of age from a 6 mg per kg dose of intravenous ganciclovir twice daily (AUC 0-12h = 25.3 [range 2.4 to 89.7] mcg ∙ h/mL; n = 18) or to the ganciclovir systemic exposures obtained in adults from a 900 mg dose of valganciclovir tablets twice daily.
However, the efficacy and safety of intravenous ganciclovir and of valganciclovir have not been established for the treatment of congenital CMV infection in infants and no similar disease occurs in adults; therefore, efficacy cannot be extrapolated from intravenous ganciclovir use in adults.
🧓 Geriatric Use ▾
8.5Geriatric Use Studies of valganciclovir tablets have not been conducted in adults older than 65 years of age. Clinical studies of valganciclovir did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
Valganciclovir is known to be substantially excreted by the kidneys, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because renal clearance decreases with age, valganciclovir should be administered with consideration of their renal status. Renal function should be monitored and dosage adjustments should be made accordingly [see Dosage and Administration ( 2.5 ), Warnings and Precautions ( 5.2 ), Use in Specific Populations ( 8.6 ), Clinical Pharmacology ( 12.3 ) ].
🆘 Overdosage ▾
10 OVERDOSAGE Experience with Valganciclovir Tablets : An overdose of valganciclovir could possibly result in increased renal toxicity [see Dosage and Administration (2.5) , Use in Specific Populations (8.6) ]. Because ganciclovir is dialyzable, dialysis may be useful in reducing serum concentrations in patients who have received an overdose of valganciclovir [see Clinical Pharmacology ( 12.3 ) ]. Adequate hydration should be maintained.
The use of hematopoietic growth factors should be considered [see Warnings and Precautions ( 5.1 ) and Clinical Pharmacology ( 12.3 ) ]. Reports of adverse reactions after overdoses with valganciclovir, some with fatal outcomes, have been received from clinical trials and during postmarketing experience. The majority of patients experienced one or more of the following adverse events: Hematological toxicity : myelosuppression including pancytopenia, bone marrow failure, leukopenia, neutropenia, granulocytopenia Hepatotoxicity: hepatitis, liver function disorder Renal toxicity : worsening of hematuria in a patient with pre-existing renal impairment, acute kidney injury, elevated creatinine Gastrointestinal toxicity : abdominal pain, diarrhea, vomiting Neurotoxicity : generalized tremor, seizure
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Valganciclovir is an antiviral drug with activity against CMV [see Microbiology (12.4) ].
12.3Pharmacokinetics Valganciclovir is a prodrug of ganciclovir. Valganciclovir C max and AUC are approximately 1% and 3% of those of ganciclovir, respectively. Pharmacokinetics in Adults : The pharmacokinetics of ganciclovir after administration of valganciclovir tablets have been evaluated in HIV- and CMV-seropositive patients, patients with AIDS and CMV retinitis, and in solid organ transplant patients (Table 10).
Table 10 Ganciclovir Pharmacokinetics* in Healthy Volunteers and HIV-positive/CMV-positive Adults Administered Valganciclovir Tablets 900 mg Once Daily with Food PK parameter N Value (Mean ± SD ) AUC 0-24h (mcg ∙ h/mL) 57 29.1 ±
9.7C max (mcg/mL) 58 5.61 ±
1.52Absolute oral bioavailability (%) 32 59.4 ±
6.1Elimination half-life (hr) 73 4.08 ±
0.76Renal clearance (mL/min/kg) 20 3.21 ± 0.75 (1 study, n=20) *Data were obtained from single and multiple dose studies in healthy volunteers, HIV-positive patients, and HIV-positive/CMV-positive patients with and without retinitis. Patients with CMV retinitis tended to have higher ganciclovir plasma concentrations than patients without CMV retinitis. The systemic ganciclovir exposures attained following administration of 900 mg valganciclovir tablets once daily were comparable across kidney, heart and liver transplant recipients (Table 11).
Table 11 Ganciclovir Pharmacokinetics in Solid Organ Transplant Recipients Administered Valganciclovir Tablets 900 mg Once Daily with Food Parameter Value ( Mean ± SD) Heart Transplant Recipients (N=17) Liver Transplant Recipients (N=75) Kidney Transplant Recipients* (N=68) AUC 0-24h (mcg ∙ h/mL) 40.2 ± 11.8 46.0 ± 16.1 48.2 ±
14.6C max (mcg/mL) 4.9 ± 1.1 5.4 ± 1.5 5.3 ±
1.5Elimination half-life (hr) 6.58 ± 1.50 6.18 ± 1.42 6.77 ± 1.25 * Includes kidney-pancreas The pharmacokinetic parameters of ganciclovir following 200 days of valganciclovir administration in high-risk kidney transplant patients were similar to those in solid organ transplant patients who received valganciclovir for 100 days. Absorption, Distribution, Metabolism, and Excretion The pharmacokinetic (PK) properties of valganciclovir are provided in Table 12. Table 12 Pharmacokinetic Properties of Ganciclovir and Valganciclovir Associated with Valganciclovir Tablets Valganciclovir Ganciclovir Absorption T max (h) median (min-max) (fed conditions) 2.18 1.7h to 3.0h Food effect (high fat meal/fasting): PK parameter ratio and 90% confidence interval a C max : 1.14 (0.95, 1.36) AUC: 1.30 (1.07, 1.51) a T max : ↔: 1.30 (1.07, 1.51) a Distribution % Bound to human plasma proteins ( ex vivo ) Unknown 1 to 2% over 0.5 to 51 mcg/mL Cerebrospinal fluid penetration Unknown Yes Metabolism Hydrolyzed by intestinal and liver esterases No significant metabolism Elimination Dose proportionality AUC was dose proportional under fed conditions across a valganciclovir dose range of 450 to 2625 mg Major route of elimination Metabolism to ganciclovir Glomerular filtration and active tubular secretion t 1/2 (h) See Tables 10 and 11 % Of dose excreted in urine Unknown % Of dose excreted in feces Unknown a Steady state ganciclovir PK was assessed after administration of valganciclovir tablets (875 mg once daily) with a high fat meal containing approximately 600 total calories (31.1 g fat, 51.6 g carbohydrates and 22.2 g protein) to 16 HIV-positive subjects.
Specific Populations : Renal Impairment : The pharmacokinetics of ganciclovir from a single oral dose of 900 mg valganciclovir tablets were evaluated in 24 otherwise healthy individuals with renal impairment. Decreased renal function results in decreased clearance of ganciclovir and increased terminal half-life ( Table 13 ) . Table 13 Pharmacokinetics of Ganciclovir from a Single Oral Dose of 900 mg Valganciclovir Tablets Estimated Creatinine Clearance* (mL/min) N Apparent Clearance (mL/min) Mean ± S… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Valganciclovir is an antiviral drug with activity against CMV [see Microbiology (12.4) ].
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Valganciclovir Tablets USP, 450 mg are pink colored, modified capsule shaped, film coated tablets debossed with ‘RDY’ on one side and ‘762’ on other side and are supplied in bottles of 30’s and 60’s. Bottles of 30’s NDC 43598-356-30 Bottles of 60’s NDC 43598-356-60 Store at 20°C to 25°C (68°F to 77°F) [See USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Valganciclovir tablets USP contains valganciclovir hydrochloride USP, a hydrochloride salt of the L-valyl ester of ganciclovir that exists as a mixture of two diastereomers. Ganciclovir is a synthetic guanine derivative active against CMV. Valganciclovir hydrochloride USP is available as a 450 mg tablet for oral administration.
Each tablet contains 496.3 mg of valganciclovir hydrochloride USP (corresponding to 450 mg of valganciclovir), and the inactive ingredients colloidal silicon dioxide, crospovidone, magnesium stearate, microcrystalline cellulose and povidone. The film-coat applied to the tablets contains hypromellose, iron oxide red, polyethylene glycol, polysorbate and titanium dioxide. Valganciclovir hydrochloride USP is a white to off-white powder, slightly hygroscopic with a molecular formula of C 14 H 22 N 6 O 5 .
HCl and a molecular weight of 390.82. The chemical name for valganciclovir hydrochloride USP is L-Valine,2-[(2-amino-1,6-dihydro-6-oxo-9H-purin-9-yl)methoxy]-3-hydroxypropyl ester, monohydrochloride. Valganciclovir hydrochloride USP with solubility of 97 mg/mL in water at 25°C at a pH of 7.0 and an n-octanol/water partition coefficient of 0.0086 at pH 7.0.
The pKa for valganciclovir hydrochloride USP is 7.5. The chemical structure of valganciclovir hydrochloride USP is: All doses in this insert are specified in terms of valganciclovir.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Serious Adverse Reactions Inform patients that valganciclovir may cause granulocytopenia (neutropenia), anemia, thrombocytopenia and elevated creatinine levels and that dose modification or discontinuation of dosing may be required. Complete blood counts, platelet counts, and creatinine levels should be monitored frequently during treatment [see Warnings and Precautions ( 5.1) ] .
Pregnancy and Contraception Inform females of reproductive potential that valganciclovir causes birth defects in animals. Advise them to use effective contraception during and for at least 30 days following treatment with valganciclovir. Similarly, advise males to use condoms during and for at least 90 days following treatment with valganciclovir [see Use in Specific Populations ( 8.1 , 8.3 ) ].
Carcinogenicity Advise patients that valganciclovir is considered a potential carcinogen [see Nonclinical Toxicity ( 13.1 )] . Lactation Advise mothers not to breast-feed if they are receiving valganciclovir because of the potential for hematologic toxicity and cancer in nursing infants, and because HIV can be passed to the baby in breast milk [see Use in Specific Populations ( 8.2 )] . Infertility Advise patients that valganciclovir may cause temporary or permanent female and male infertility [see Warnings and Precautions ( 5.3 ), Use in Specific Populations ( 8.3 )].
Impairment of Cognitive Ability Inform patients that tasks requiring alertness may be affected including the patient’s ability to drive and operate machinery as seizures, dizziness, and/or confusion have been reported with the use of valganciclovir [see Adverse Reactions ( 6.1 )]. Use in Patients with CMV Retinitis Inform patients that valganciclovir is not a cure for CMV retinitis, and they may continue to experience progression of retinitis during or following treatment. Advise patients to have ophthalmologic follow-up examinations at a minimum of every 4 to 6 weeks while being treated with valganciclovir.
Some patients will require more frequent follow-up. Administration Inform adult patients that they should use valganciclovir tablets, not valganciclovir for oral solution [see Dosage and Administration ( 2.1 ) ]. Inform patients to take valganciclovir tablets with food to maximize bioavailability.
For more information, call 1-888-375-3784. Rx Only Manufactured by: Dr. Reddy’s Laboratories Limited Srikakulam - 532 409 INDIA Distributor: Dr.
Reddy’s Laboratories Inc., Princeton, NJ 08540 USA Revised: 0122
🍼 Nursing Mothers ▾
8.3Females and Males of Reproductive Potential Pregnancy Testing Females of reproductive potential should undergo pregnancy testing before initiation of valganciclovir [see Use in Specific Populations ( 8.1 ) ]. Contraception Females Because of the mutagenic and teratogenic potential of valganciclovir, females of reproductive potential should be advised to use effective contraception during treatment and for at least 30 days following treatment with valganciclovir [see Dosage and Administration ( 2.6 ), Warnings and Precautions ( 5.4 , 5.5 ), Nonclinical Toxicology ( 13.1 ) ].
Males Because of its mutagenic potential, males should be advised to use condoms during and for at least 90 days following, treatment with valganciclovir [see Dosage and Administration ( 2.6 ), Warnings and Precautions ( 5.3 , 5.5 ), Nonclinical Toxicology ( 13.1 ) ]. Infertility Valganciclovir at the recommended doses may cause temporary or permanent female and male infertility [see Warnings and Precautions ( 5.3 ), Nonclinical Toxicology ( 13.1 )] . Data Human Data In a small, open-label, non-randomized clinical study, adult male renal transplant patients receiving valganciclovir for CMV prophylaxis for up to 200 days post-transplantation were compared to an untreated control group.
Patients were followed-up for six months after valganciclovir discontinuation. Among 24 evaluable patients in the valganciclovir group, the mean sperm density at the end of treatment visit decreased by 11 million/mL from baseline; whereas, among 14 evaluable patients in the control group the mean sperm density increased by 33 million/mL. However, at the follow-up visit among 20 evaluable patients in the valganciclovir group the mean sperm density was comparable to that observed among 10 evaluable patients in the untreated control group (the mean sperm density at the end of follow-up visit increased by 41 million/mL from baseline in the valganciclovir group and by 43 million/mL in the untreated group).
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Adult Patients Induction Therapy of CMV Retinitis : In one randomized open-label controlled study, 160 patients with AIDS and newly diagnosed CMV retinitis were randomized to receive treatment with either valganciclovir tablets (900 mg twice daily for 21 days, then 900 mg once daily for 7 days) or with intravenous ganciclovir solution (5 mg per kg twice daily for 21 days, then 5 mg per kg once daily for 7 days). Study participants were: male (91%), White (53%), Hispanic (31%), and Black (11%). The median age was 39 years, the median baseline HIV-1 RNA was 4.9 log 10 , and the median CD4 cell count was 23 cells/mm 3 .
A determination of CMV retinitis progression by the masked review of retinal photographs taken at baseline and Week 4 was the primary outcome measurement of the 3-week induction therapy. Table 19 provides the outcomes at 4 weeks. Table 19 Week 4 Masked Review of Retinal Photographs in CMV Retinitis Study Intravenous Ganciclovir Valganciclovir Tablets Determination of CMV retinitis progression at Week 4 N=80 N=80 Progressor Non-progressor 7 63 7 64 Death Discontinuations due to Adverse Events Failed to return 2 1 1 1 2 1 CMV not confirmed at baseline or no interpretable baseline photos 6 5 Maintenance Therapy of CMV Retinitis: No comparative clinical data are available on the efficacy of valganciclovir tablets for the maintenance therapy of CMV retinitis because all patients in the CMV retinitis study received open-label valganciclovir tablets after Week 4.
However, the AUC for ganciclovir is similar following administration of 900 mg valganciclovir tablets once daily and 5 mg per kg intravenous ganciclovir once daily. Although the ganciclovir C max is lower following valganciclovir tablets administration compared to intravenous ganciclovir, it is higher than the C max obtained following oral ganciclovir administration. Therefore, use of valganciclovir tablets as maintenance therapy is supported by a plasma concentration-time profile similar to that of two approved products for maintenance therapy of CMV retinitis.
Prevention of CMV Disease in Heart, Kidney, Kidney-Pancreas, or Liver Transplantation : A double blind, double-dummy active comparator study was conducted in 372 heart, liver, kidney, or kidney-pancreas transplant patients at high risk for CMV disease (D+/R-). Patients were randomized (2 valganciclovir: 1 oral ganciclovir) to receive either valganciclovir tablets (900 mg once daily) or oral ganciclovir (1,000 mg three times a day) starting within 10 days of transplantation until Day 100 post-transplant. The proportion of patients who developed CMV disease, including CMV syndrome and/or tissue-invasive disease during the first 6 months post-transplant was similar between the valganciclovir tablets arm (12.1%, N=239) and the oral ganciclovir arm (15.2%, N=125).
However, in liver transplant patients, the incidence of tissue-invasive CMV disease was significantly higher in the valganciclovir group compared with the ganciclovir group. These results are summarized in Table 20. Mortality at six months was 3.7% (9/244) in the valganciclovir group and 1.6% (2/126) in the oral ganciclovir group.
Table 20 Percentage of Patients with CMV Disease, Tissue-Invasive CMV Disease or CMV Syndrome by Organ Type: Endpoint Committee, 6 Month ITT Population CMV Disease 1 Tissue-Invasive CMV Disease CMV Syndrome 2 Organ VGCV (N=239) GCV (N=125) VGCV (N=239) GCV (N=125) VGCV (N=239) GCV (N=125) Liver 19% 12% 14% 3% 5% 8% (n=177) (22 / 118) (7 / 59) (16 / 118) (2 / 59) (6 / 118) (5 / 59) Kidney 6% 23% 1% 5% 5% 18% (n=120) (5 / 81) (9 / 39) (1 / 81) (2 / 39) (4 / 81) (7 / 39) Heart 6% 10% 0% 5% 6% 5% (n=56) (2 / 35) (2 / 21) (0 / 35) (1 / 21) (2 / 35) (1 / 21) Kidney/ Pancreas 0% 17% 0% 17% 0% 0% (n=11) (0 / 5) (1 / 6) (0 / 5) (1 / 6) (0 / 5) (0 / 6) GCV = oral ganciclovir; VGCV = valganciclovir 1 Number of patients with CMV disease = Number of patients with tissue-invasive CMV disease or CMV syndrome 2 CM… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term carcinogenicity studies have not been conducted with valganciclovir. However, upon oral administration, valganciclovir is rapidly and extensively converted to ganciclovir. Therefore, like ganciclovir, valganciclovir is a potential carcinogen.
Ganciclovir was carcinogenic in the mouse at oral doses that produced exposures approximately 0.1x and 1.4x, respectively, the mean drug exposure in humans following the recommended intravenous dose of 5 mg/kg, based on area under the plasma concentration curve (AUC) comparisons. At the higher dose, there was a significant increase in the incidence of tumors of the preputial gland in males, forestomach (nonglandular mucosa) in males and females, and reproductive tissues (ovaries, uterus, mammary gland, clitoral gland and vagina) and liver in females.
At the lower dose, a slightly increased incidence of tumors was noted in the preputial and harderian glands in males, forestomach in males and females, and liver in females. Ganciclovir should be considered a potential carcinogen in humans. Valganciclovir increases mutations in mouse lymphoma cells.
In the mouse micronucleus assay, valganciclovir was clastogenic. Valganciclovir was not mutagenic in the Ames Salmonella assay. Ganciclovir increased mutations in mouse lymphoma cells and DNA damage in human lymphocytes in vitro .
In the mouse micronucleus assay, ganciclovir was clastogenic. Ganciclovir was not mutagenic in the Ames Salmonella assay. Valganciclovir is converted to ganciclovir and therefore is expected to have similar reproductive toxicity effects as ganciclovir [see Warnings and Precautions ( 5.3 ) ].
Ganciclovir caused decreased mating behavior, decreased fertility, and an increased incidence of embryolethality in female mice following intravenous doses that produced an exposure approximately 1.7x the mean drug exposure in humans following the dose of 5 mg per kg, based on AUC comparisons. Ganciclovir caused decreased fertility in male mice and hypospermatogenesis in mice and dogs following daily oral or intravenous administration. Systemic drug exposure (AUC) at the lowest dose showing toxicity in each species ranged from 0.03 to 0.1x the AUC of the recommended human intravenous dose.
Valganciclovir caused similar effects on spermatogenesis in mice, rats, and dogs. These effects were reversible at lower doses but irreversible at higher doses. It is considered likely that ganciclovir (and valganciclovir) could cause temporary or permanent inhibition of human spermatogenesis.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term carcinogenicity studies have not been conducted with valganciclovir. However, upon oral administration, valganciclovir is rapidly and extensively converted to ganciclovir. Therefore, like ganciclovir, valganciclovir is a potential carcinogen.
Ganciclovir was carcinogenic in the mouse at oral doses that produced exposures approximately 0.1x and 1.4x, respectively, the mean drug exposure in humans following the recommended intravenous dose of 5 mg/kg, based on area under the plasma concentration curve (AUC) comparisons. At the higher dose, there was a significant increase in the incidence of tumors of the preputial gland in males, forestomach (nonglandular mucosa) in males and females, and reproductive tissues (ovaries, uterus, mammary gland, clitoral gland and vagina) and liver in females.
At the lower dose, a slightly increased incidence of tumors was noted in the preputial and harderian glands in males, forestomach in males and females, and liver in females. Ganciclovir should be considered a potential carcinogen in humans. Valganciclovir increases mutations in mouse lymphoma cells.
In the mouse micronucleus assay, valganciclovir was clastogenic. Valganciclovir was not mutagenic in the Ames Salmonella assay. Ganciclovir increased mutations in mouse lymphoma cells and DNA damage in human lymphocytes in vitro .
In the mouse micronucleus assay, ganciclovir was clastogenic. Ganciclovir was not mutagenic in the Ames Salmonella assay. Valganciclovir is converted to ganciclovir and therefore is expected to have similar reproductive toxicity effects as ganciclovir [see Warnings and Precautions ( 5.3 ) ].
Ganciclovir caused decreased mating behavior, decreased fertility, and an increased incidence of embryolethality in female mice following intravenous doses that produced an exposure approximately 1.7x the mean drug exposure in humans following the dose of 5 mg per kg, based on AUC comparisons. Ganciclovir caused decreased fertility in male mice and hypospermatogenesis in mice and dogs following daily oral or intravenous administration. Systemic drug exposure (AUC) at the lowest dose showing toxicity in each species ranged from 0.03 to 0.1x the AUC of the recommended human intravenous dose.
Valganciclovir caused similar effects on spermatogenesis in mice, rats, and dogs. These effects were reversible at lower doses but irreversible at higher doses. It is considered likely that ganciclovir (and valganciclovir) could cause temporary or permanent inhibition of human spermatogenesis.
📚 References ▾
15 REFERENCES 1. Brion, LP, Fleischman, AR, McCarton, C, Schwartz, GJ. A simple estimate of glomerular filtration rate in low birth weight infants during the first year of life: noninvasive assessment of body composition and growth.
J of Ped 1986: 109(4): 698-707. 2. NIOSH [2014].
NIOSH list of antineoplastic and other hazardous drugs in healthcare settings. By Connor TH, MacKenzie BA, DeBord DG, Trout DB, O’Callaghan JP, Cincinnati, OH: U.S. Department of Health and Human Services, Centers for Disease Control and Prevention, National Institute for Occupational Safety and Health, DHHS (NIOSH) Publication No.
2014-138 (Supersedes 2012-150).
📄 Patient Package Insert ▾
PATIENT INFORMATION Valganciclovir Tablets USP (val gan SYE kloe veer) W hat is the most important information I should know about valganciclovir tablets? Valganciclovir tablets can cause serious side effects, including: • Blood and bone marrow problems. Valganciclovir can affect the bone marrow lowering the amount of your white blood cells, red blood cells, and platelets and may cause serious and life-threatening problems . • Kidney failure.
Kidney failure may happen in people who are elderly, people who take valganciclovir tablets with certain other medicines, or people who are not adequately hydrated. • Fertility problems. Valganciclovir may lower sperm count in males and cause fertility problems. Valganciclovir may also cause fertility problems in women.
Talk to your healthcare provider if this is a concern for you. • Birth defects. Valganciclovir causes birth defects in animals. It is not known if valganciclovir causes birth defects in people.
If you are a female who can become pregnant, you should use effective birth control during treatment with valganciclovir and for at least 30 days after treatment. If you are pregnant, talk to your healthcare provider before starting treatment with valganciclovir. If you are a female who can become pregnant, you should have a pregnancy test done before starting valganciclovir.
Tell your healthcare provider right away if you become pregnant during treatment with valganciclovir . Males should use condoms during treatment with valganciclovir, and for at least 90 days after treatment, if their female sexual partner can become pregnant. Talk to your healthcare provider if you have questions about birth control . • Cancer.
Valganciclovir causes cancer in animals and may potentially cause cancer in people. Your healthcare provider will do regular blood tests during treatment with valganciclovir to check you for side effects. Your healthcare provider may change your dose or stop treatment with valganciclovir if you have serious side effects.
What is valganciclovir? Valganciclovir is a prescription antiviral medicine. In adults, valganciclovir tablets are used: • to treat cytomegalovirus (CMV) retinitis in people who have acquired immunodeficiency syndrome (AIDS).
When CMV virus infects the eyes, it is called CMV retinitis. If CMV retinitis is not treated, it can cause blindness. • to prevent CMV disease in people who have received a kidney, heart, or kidney-pancreas transplant and who have a high risk for getting CMV disease. Valganciclovir does not cure CMV retinitis .
Yo u may still get retinitis or worsening of retinitis during or after treatment with valganciclovir. It is important to stay under a healthcare provider’s care and have your eyes checked at least every 4 to 6 weeks during treatment with valganciclovir. In children, valganciclovir tablets or oral solution are used: · to prevent CMV disease in children 4 months to 16 years of age who have received a kidney transplant and have a high risk for getting CMV disease. · to prevent CMV disease in children 1 month to 16 years of age who have received a heart transplant and have a high risk for getting CMV disease.
It is not known if valganciclovir tablets are safe and effective in children for prevention of CMV disease in liver transplant, in kidney transplant in infants less than 4 months of age, in heart transplant in infants less than 1 month of age, in children with AIDS who have CMV retinitis, and in infants with congenital CMV infection. Do not take valganciclovir tablets if you have had a serious allergic reaction to valganciclovir, ganciclovir or any of the ingredients of valganciclovir tablets. See the end of this leaflet for a list of the ingredients in valganciclovir tablets.
Before you take valganciclovir tablets, tell your healthcare provider about all of your medical conditions, including if you: have low blood cell counts have kidney problems are receiving hemodialysis are receiving radiation treatment are pregnant or p… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
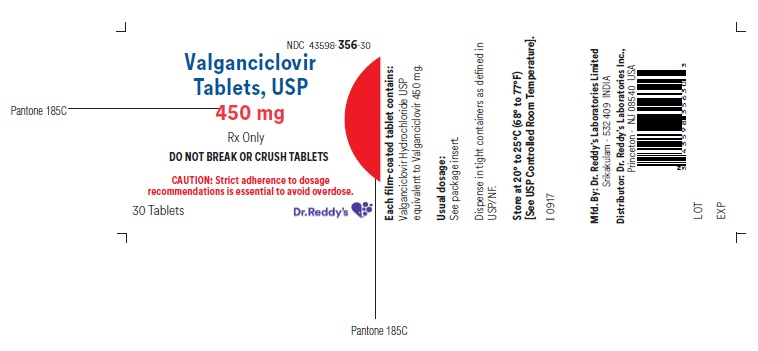
PACKAGE LABEL PRINCIPAL DISPLAY PANEL SECTION Valganciclovir Tablets USP, 450 mg - Container Label
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |