
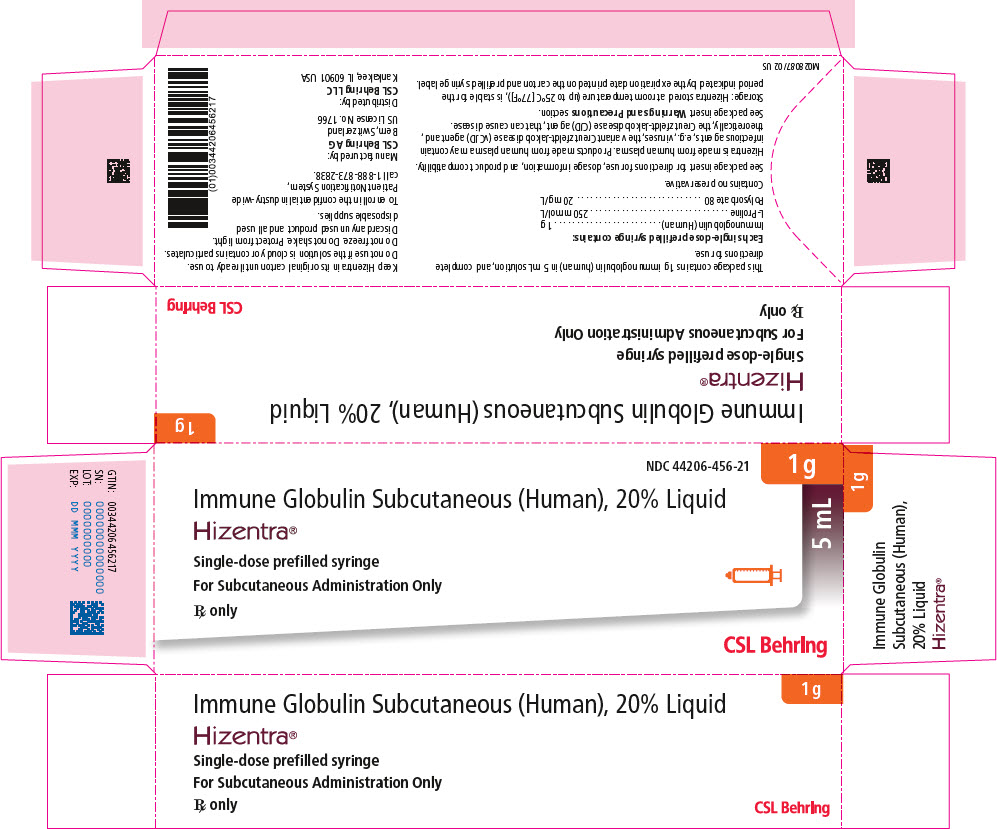
Hizentra HUMAN IMMUNOGLOBULIN G .2 g/mL Liquid — NDC 44206-456-21 (Billing 44206-0456-21)
This is a package of Hizentra HUMAN IMMUNOGLOBULIN G .2 g/mL Liquid from CSL Behring AG, marketed since Jan 2020 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 44206-456-21 alone.
- Record
- FDA NDC Directory package listing · Plasma derivative
- Code segments
- 44206 labeler · 456 product · 21 package
- Package marketed since
- Jan 1, 2020
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 4420645621 7
- Medicaid fills, this package
- 8,396 prescriptions in the last four reported quarters
- FDA record last changed
- Oct 8, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 078373
- GCN: 44679
- GPI-14 (Medi-Span): 1910002020E520
- HICL (First Databank): 041798
- AHFS class code: 80:04.00.00
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
Clinical
- Think of it as a collection of protective proteins — called antibodies — that healthy donors have built up against many different germs. If your immune system can't make enough of...
- What exactly is human immunoglobulin G and why do I need it?
- It depends on the specific product your doctor prescribed. The IV versions — like Privigen, Asceniv, Qivigy, and Gammaplex — are infused into a vein, usually every 3 to 4 weeks. Hi...
- How is it given, and how often will I need infusions?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $192.07 | $960.34 / 5 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J1559 | $14.883 / J1559 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Oct 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 44206-0456-21 You're viewing this Main listing | 1 SYRINGE in 1 CARTON / 5 mL in 1 SYRINGE | 2020-01-01 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Hizentra .2 g/mL 44206-0451-01 | CSL | 1 vial | — | — | FDA listed | — |
| Hizentra .2 g/mL 44206-0452-02 | CSL | 1 vial | — | — | FDA listed | — |
| Hizentra .2 g/mL 44206-0454-04 | CSL | 1 vial | — | — | FDA listed | — |
| Hizentra .2 g/mL 44206-0455-10 | CSL | 1 vial | — | — | FDA listed | — |
| Hizentra .2 g/mLthis 44206-0456-21 | CSL | 1 syringe | — | — | FDA listed | — |
| Hizentra .2 g/mL 44206-0457-22 | CSL | 1 syringe | — | — | FDA listed | — |
| Hizentra .2 g/mL 44206-0458-24 | CSL | 1 syringe | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Purple Book · refreshed Oct 5, 2026
- CMS NADAC weekly file
Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Where does this data come from?
- FDA Purple Book · refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Human Immunoglobulin G inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 741C1PWQ88
Human immunoglobulin A is an antibody protein naturally found in the human body. In medicines, it's used as an active therapeutic component to help the immune system fight infections and disease, rather than as a typical inactive filler or binder.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII 9DLQ4CIU6V
Proline is an amino acid used in pharmaceutical formulations as a bulking agent and stabilizer. It helps maintain product stability and can improve the texture or consistency of medicines, particularly in powders and freeze-dried products.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from CSL Behring AG labeler code 44206
- Privigen Human Immunoglobulin G 20 g/200mL Liquid NDC 44206-438-20
- Privigen Human Immunoglobulin G 40 g/400mL Liquid NDC 44206-439-40
- Hizentra HUMAN IMMUNOGLOBULIN G .2 g/mL Liquid NDC 44206-451-01
- Hizentra HUMAN IMMUNOGLOBULIN G .2 g/mL Liquid NDC 44206-452-02
- Hizentra HUMAN IMMUNOGLOBULIN G .2 g/mL Liquid NDC 44206-454-04
- Hizentra HUMAN IMMUNOGLOBULIN G .2 g/mL Liquid NDC 44206-455-10
- Hizentra HUMAN IMMUNOGLOBULIN G .2 g/mL Liquid NDC 44206-457-22
- Hizentra HUMAN IMMUNOGLOBULIN G .2 g/mL Liquid NDC 44206-458-24
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full FDA label FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Hizentra is an Immune Globulin Subcutaneous (Human) (IGSC), 20% Liquid indicated as replacement therapy for primary humoral immunodeficiency (PI). This includes, but is not limited to, the humoral immune defect in congenital agammaglobulinemia, common variable immunodeficiency, X-linked agammaglobulinemia, Wiskott-Aldrich syndrome, and severe combined immunodeficiencies. Hizentra is an Immune Globulin Subcutaneous (Human) (IGSC), 20% Liquid indicated for the treatment of primary immunodeficiency (PI) ( 1 ).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION For subcutaneous infusion only. Do not inject into a blood vessel. For subcutaneous infusion only.
Do not inject into a blood vessel. Start treatment with Hizentra 1week after the patient's last Immune Globulin Intravenous (Human) (IGIV) infusion, when the patient has received IGIV infusions at regular intervals for at least 3 months. Dosage ( 2.2 ) Calculate the initial weekly dose of Hizentra needed to achieve a systemic serum IgG exposure (area under the concentration-time curve [AUC]) not inferior to that of the previous IGIV treatment.
Initial dose = Previous IGIV dose (in grams) ×
1.53No. of weeks between IGIV doses To convert the dose in grams to milliliters (mL), multiply the calculated dose (in grams) by 5. Adjust the dose of Hizentra over time based on clinical response and serum IgG trough levels. Measure the serum IgG trough level during IGIV therapy prior to switching to Hizentra and again after 2 to 3 months of treatment with Hizentra.
Adjust the dose to achieve a serum IgG trough level that is approximately 290 mg/dL higher than the last trough level during prior IGIV therapy. Administration ( 2.3 ) Infusion sites – Abdomen, thigh, upper arm, and/or lateral hip. Use up to 4 injection sites simultaneously, with at least 2 inches between sites.
Infusion volume – For the first infusion, up to 15 mL per injection site. This may be increased to 20 mL per site after the fourth infusion and to a maximum of 25 mL per site as tolerated. Infusion rate – For the first infusion, up to 15 mL/hr per site.
This may be increased, to a maximum of 25 mL/hr per site as tolerated. However, the maximum flow rate is not to exceed a total of 50 mL/hr for all sites combined.
2.1Preparation and Handling Hizentra is a clear and pale yellow to light brown solution. Do not use if the solution is cloudy or contains particulates. Prior to administration, visually inspect each vial of Hizentra for particulate matter or discoloration, whenever the solution and container permit.
Do not freeze. Do not use any solution that has been frozen. Check the product expiration date on the vial label.
Do not use beyond the expiration date. Do not mix Hizentra with other products. Do not shake the Hizentra vial.
Use aseptic technique when preparing and administering Hizentra. The Hizentra vial is for single-use only. Discard all used administration supplies and any unused product immediately after each infusion in accordance with local requirements.
2.2Dosage The dose should be individualized based on the patient's clinical response to Hizentra therapy and serum immunoglobulin G (IgG) trough levels. Start treatment with Hizentra 1 week after the patient's last Immune Globulin Intravenous (Human) (IGIV) infusion. Before receiving treatment with Hizentra, patients need to have received IGIV treatment at regular intervals for at least 3 months.
Before switching to Hizentra, obtain the patient's serum IgG trough level to guide subsequent dose adjustments ( see below under Dose Adjustment ). Establish the initial weekly dose of Hizentra by converting the monthly IGIV dose into a weekly equivalent and increasing it using a dose adjustment factor. The goal is to achieve a systemic serum IgG exposure (area under the concentration-time curve [AUC]) not inferior to that of the previous IGIV treatment ( see Pharmacokinetics [12.3] ).
Initial Weekly Dose To calculate the initial weekly dose of Hizentra, divide the previous IGIV dose in grams by the number of weeks between doses during the patient's IGIV treatment (e.g., 3 or 4); then multiply this by the dose adjustment factor of 1.53. Initial Hizentra dose = Previous IGIV dose (in grams) Number of weeks between IGIV doses ×
1.53To convert the Hizentra dose (in grams) to milliliters (mL), multiply the calculated dose (in grams) by 5. Dose Adjustment Over time, the dose may need to be adjusted to achieve the desired clinical response and serum IgG trough level. To determine if a dose adj… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Hizentra is a 0.2 g/mL (20%) protein solution for subcutaneous injection. 0.2 g/mL (20%) protein solution for subcutaneous injection ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Hizentra is contraindicated in patients who have had an anaphylactic or severe systemic reaction to the administration of human immune globulin or to components of Hizentra, such as polysorbate 80. Hizentra is contraindicated in patients with hyperprolinemia because it contains the stabilizer L-proline ( see Description [11] ). Hizentra is contraindicated in IgA-deficient patients with antibodies against IgA and a history of hypersensitivity ( see Description [11] ).
Anaphylactic or severe systemic reactions to human immune globulin or components of Hizentra, such as polysorbate 80 ( 4 ) Hyperprolinemia (Hizentra contains the stabilizer L-proline) ( 4 ) IgA-deficient patients with antibodies against IgA and a history of hypersensitivity ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS IgA-deficient patients with anti-IgA antibodies are at greater risk of severe hypersensitivity and anaphylactic reactions. Discontinue use if hypersensitivity reaction occurs ( 5.1 ). Aseptic meningitis syndrome has been reported to occur with IGIV or IGSC treatment ( 5.2 ).
Monitor patients for reactions reported to occur with IGIV treatment that may occur with Hizentra, including renal dysfunction/failure, thrombotic events, hemolysis, and transfusion-related acute lung injury (TRALI) ( 5.3 ). Products made from human plasma can contain infectious agents, e.g., viruses and, theoretically, the Creutzfeldt-Jakob disease (CJD) agent ( 5.4 ).
5.1Hypersensitivity Severe hypersensitivity reactions may occur to human immune globulin or components of Hizentra, such as polysorbate 80. In case of hypersensitivity, discontinue the Hizentra infusion immediately and institute appropriate treatment. Individuals with IgA deficiency can develop anti-IgA antibodies and anaphylactic reactions (including anaphylaxis and shock) after administration of blood components containing IgA.
Patients with known antibodies to IgA may have a greater risk of developing potentially severe hypersensitivity and anaphylactic reactions with administration of Hizentra. Hizentra contains ≤50 mcg/mL IgA ( see Description [11] ).
5.2Aseptic Meningitis Syndrome (AMS) AMS has been reported with use of IGIV 1 or IGSC. The syndrome usually begins within several hours to 2 days following immune globulin treatment. AMS is characterized by the following signs and symptoms: severe headache, nuchal rigidity, drowsiness, fever, photophobia, painful eye movements, nausea, and vomiting.
Cerebrospinal fluid (CSF) studies frequently show pleocytosis up to several thousand cells per cubic millimeter, predominantly from the granulocytic series, and elevated protein levels up to several hundred mg/dL. AMS may occur more frequently in association with high doses (≥2 g/kg) and/or rapid infusion of immune globulin product. Patients exhibiting such signs and symptoms should receive a thorough neurological examination, including CSF studies, to rule out other causes of meningitis.
Discontinuation of immune globulin treatment has resulted in remission of AMS within several days without sequelae.
5.3Reactions Reported to Occur With IGIV Treatment The following reactions have been reported to occur with IGIV treatment and may occur with IGSC treatment. Renal Dysfunction/Failure Renal dysfunction/failure, osmotic nephropathy, and death may occur with use of human immune globulin products. Ensure that patients are not volume depleted and assess renal function, including measurement of blood urea nitrogen (BUN) and serum creatinine, before the initial infusion of Hizentra and at appropriate intervals thereafter.
Periodic monitoring of renal function and urine output is particularly important in patients judged to have a potential increased risk of developing acute renal failure. 2 If renal function deteriorates, consider discontinuing Hizentra. For patients judged to be at risk of developing renal dysfunction because of pre-existing renal insufficiency or predisposition to acute renal failure (such as those with diabetes mellitus or hypovolemia, those who are overweight or use concomitant nephrotoxic medicinal products, or those who are over 65 years of age), administer Hizentra at the minimum rate practicable.
Thrombotic Events Thrombotic events may occur with use of human immune globulin products 3-5 . Patients at increased risk may include those with a history of atherosclerosis, multiple cardiovascular risk factors, advanced age, impaired cardiac output, hypercoagulable disorders, prolonged periods of immobilization, and/or known or suspected hyperviscosity. Because of the potentially increased risk of thrombosis, consider baseline assessment of blood viscosity in patients at risk for hyperviscosity, including those with cryoglobulins, fasting chylomicronemi… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most common adverse reactions (ARs), observed in ≥5% of study subjects receiving Hizentra, were local reactions (i.e., swelling, redness, heat, pain, and itching at the injection site), headache, vomiting, pain, and fatigue. The most common adverse reactions, observed in ≥5% of study subjects, were local reactions (i.e., swelling, redness, heat, pain, and itching at the injection site), headache, vomiting, pain, and fatigue ( 6 ). To report SUSPECTED ADVERSE REACTIONS, contact CSL Behring Pharmacovigilance at 1-866-915-6958 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, AR rates observed in clinical studies of a product cannot be directly compared to rates in the clinical studies of another product and may not reflect the rates observed in clinical practice. The safety of Hizentra was evaluated in a clinical study for 15 months in subjects with PI who had been treated previously with IGIV every 3 or 4 weeks. The safety analyses included 49 subjects in the intention-to-treat (ITT) population.
The ITT population consisted of all subjects who received at least one dose of Hizentra ( see Clinical Studies [14] ). Subjects were treated with Hizentra at weekly doses ranging from 66 to 331 mg/kg body weight during the wash-in/wash-out period and from 72 to 379 mg/kg during the efficacy period. The 49 subjects received a total of 2264 weekly infusions of Hizentra.
No deaths or serious ARs occurred during the study. Two subjects withdrew from the study due to ARs. One subject experienced a severe injection-site reaction one day after the third weekly infusion, and the other subject experienced moderate myositis.
Both reactions were judged to be "at least possibly related" to the administration of Hizentra. Table 2 summarizes the most frequent adverse events (AEs) (experienced by at least 4 subjects), irrespective of causality . Included are all AEs and those considered temporally associated with the Hizentra infusion, i.e., occurring during or within 72 hours after the end of an infusion.
Local reactions were the most frequent AEs observed, with injection-site reactions (i.e., swelling, redness, heat, pain, and itching at the site of injection) comprising 98% of local reactions. Table 2: Incidence of Subjects With Adverse Events (AEs) Excluding infections. (Experienced by 4 or More Subjects) and Rate per Infusion, Irrespective of Causality (ITT Population) All AEs AEs Occurring During or Within 72 Hours of Infusion AE (≥4 Subjects) Number (%) of Subjects (n=49) Number (Rate Rate of AEs per infusion. ) of AEs (n=2264 Infusions) Number (%) of Subjects (n=49) Number (Rate ) of AEs (n=2264 Infusions) Local reactions Includes injection-site reactions as well as bruising, scabbing, pain, irritation, cysts, eczema, and nodules at the injection site.
49 (100) 1340 (0.592) 49 (100) 1322 (0.584) Other AEs: Headache 13 (26.5) 40 (0.018) 12 (24.5) 32 (0.014) Cough 8 (16.3) 9 (0.004) 5 (10.2) 6 (0.003) Diarrhea 7 (14.3) 8 (0.004) 5 (10.2) 6 (0.003) Fatigue 6 (12.2) 6 (0.003) 4 (8.2) 4 (0.002) Back pain 5 (10.2) 11 (0.005) 4 (8.2) 5 (0.002) Nausea 5 (10.2) 5 (0.002) 4 (8.2) 4 (0.002) Abdominal pain, upper 5 (10.2) 5 (0.002) 3 (6.1) 3 (0.001) Rash 5 (10.2) 7 (0.003) 2 (4.1) 3 (0.001) Pain in extremity 4 (8.2) 7 (0.003) 4 (8.2) 6 (0.003) Migraine 4 (8.2) 5 (0.002) 3 (6.1) 4 (0.002) Pain 4 (8.2) 5 (0.002) 3 (6.1) 4 (0.002) Epistaxis 4 (8.2) 6 (0.003) 2 (4.1) 3 (0.001) Pharyngolaryngeal pain 4 (8.2) 6 (0.003) 2 (4.1) 2 (<0.001) Arthralgia 4 (8.2) 5 (0.002) 2 (4.1) 3 (0.001) The ratio of infusions with temporally associated AEs , including local reactions, to all infusions was 1338 to 2264 (59.1%; upper 95% confidence limit of 62.4%).
Excluding local reactions, the corresponding ratio was 173 to 2264 (7.6%; upper 95% confidence limit of 8.9%). Table 3 summarizes the most frequent ARs (i.e., those AEs considered by the investiga… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS The passive transfer of antibodies may: Lead to misinterpretation of the results of serological testing ( 5.5 , 7.2 ). Interfere with the response to live virus vaccines ( 7.1 ).
7.1Live Virus Vaccines The passive transfer of antibodies with immunoglobulin administration may interfere with the response to live virus vaccines such as measles, mumps, rubella, and varicella ( see Patient Counseling Information [17] ).
7.2Serological Testing Various passively transferred antibodies in immunoglobulin preparations may lead to misinterpretation of the results of serological testing.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: No human or animal data. Use only if clearly needed ( 8.1 ). Pediatric: No pediatric-specific dose requirements are necessary to achieve the desired serum IgG levels ( 8.4 ).
8.1Pregnancy Pregnancy Category C. Animal reproduction studies have not been conducted with Hizentra. It is not known whether Hizentra can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity. Hizentra should be given to pregnant women only if clearly needed.
8.3Nursing Mothers Hizentra has not been evaluated in nursing mothers.
8.4Pediatric Use The safety and effectiveness of Hizentra have been established in the pediatric age groups 2 to 16, as supported by evidence from adequate and well-controlled studies. Hizentra was evaluated in 10 pediatric subjects with PI (3 children and 7 adolescents) in a study conducted in the US ( see Clinical Studies [14] ) and in 23 pediatric subjects with PI (18 children and 5 adolescents) in Europe. There were no differences in the safety and efficacy profiles as compared with adult subjects.
No pediatric-specific dose requirements were necessary to achieve the desired serum IgG levels. Safety and effectiveness of Hizentra in pediatric patients below the age of 2 have not been established.
8.5Geriatric Use Of the 49 subjects evaluated in the clinical study of Hizentra, 6 subjects were 65 years of age or older. No overall differences in safety or efficacy were observed between these subjects and younger subjects.
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Category C. Animal reproduction studies have not been conducted with Hizentra. It is not known whether Hizentra can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity. Hizentra should be given to pregnant women only if clearly needed.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of Hizentra have been established in the pediatric age groups 2 to 16, as supported by evidence from adequate and well-controlled studies. Hizentra was evaluated in 10 pediatric subjects with PI (3 children and 7 adolescents) in a study conducted in the US ( see Clinical Studies [14] ) and in 23 pediatric subjects with PI (18 children and 5 adolescents) in Europe. There were no differences in the safety and efficacy profiles as compared with adult subjects.
No pediatric-specific dose requirements were necessary to achieve the desired serum IgG levels. Safety and effectiveness of Hizentra in pediatric patients below the age of 2 have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 49 subjects evaluated in the clinical study of Hizentra, 6 subjects were 65 years of age or older. No overall differences in safety or efficacy were observed between these subjects and younger subjects.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Hizentra supplies a broad spectrum of opsonizing and neutralizing IgG antibodies against a wide variety of bacterial and viral agents. The mechanism of action in PI has not been fully elucidated.
12.3Pharmacokinetics The pharmacokinetics (PK) of Hizentra was evaluated in a PK substudy of subjects with PI participating in the 15-month efficacy and safety study ( see Clinical Studies [14] ). All PK subjects were treated previously with Privigen ® , Immune Globulin Intravenous (Human), 10% Liquid and were switched to weekly subcutaneous treatment with Hizentra. After a 3-month wash-in/wash-out period, doses were adjusted individually with the goal of providing a systemic serum IgG exposure (area under the IgG serum concentration vs time curve; AUC) not inferior to that of the previous weekly-equivalent IGIV dose.
Table 6 summarizes PK parameters for subjects in the substudy following treatment with Hizentra and IGIV. Table 6: Pharmacokinetics Parameters of Hizentra and IGIV Hizentra IGIV For IGIV: weekly-equivalent dose. (Privigen ® ) bw, body weight.
Number of subjects 18 18 Dose Mean 228 mg/kg bw 152 mg/kg bw Range 141-381 mg/kg bw 86-254 mg/kg bw IgG peak levels Mean 1616 mg/dL 2564 mg/dL Range 1090-2825 mg/dL 2046-3456 mg/dL IgG trough levels Mean 1448 mg/dL 1127 mg/dL Range 952-2623 mg/dL 702-1810 mg/dL AUC Standardized to a 7-day period. Mean 10560 day x mg/dL 10320 day x mg/dL Range 7210-18670 day x mg/dL 8051-15530 day x mg/dL For the 19 subjects completing the wash-in/wash-out period, the average dose adjustment for Hizentra was 153% (range: 126% to 187%) of the previous weekly-equivalent IGIV dose.
After 12 weeks of treatment with Hizentra at this individually adjusted dose, the final steady-state AUC determinations were made in 18 of the 19 subjects. The geometric mean ratio of the steady-state AUCs, standardized to a weekly treatment period, for Hizentra vs IGIV treatment was 1.002 (range: 0.77 to 1.20) with a 90% confidence limit of 0.951 to 1.055 for the 18 subjects. With Hizentra, peak serum levels are lower (1616 vs 2564 mg/dL) than those achieved with IGIV while trough levels are generally higher (1448 vs 1127 mg/dL).
In contrast to IGIV administered every 3 to 4 weeks, weekly subcutaneous administration results in relatively stable steady-state serum IgG levels. 13,14 After the subjects had reached steady-state with weekly administration of Hizentra, peak serum IgG levels were observed after a mean of 2.9 days (range: 0 to 7 days) in 18 subjects.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Hizentra supplies a broad spectrum of opsonizing and neutralizing IgG antibodies against a wide variety of bacterial and viral agents. The mechanism of action in PI has not been fully elucidated.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Hizentra is supplied in a single-use, tamper-evident vial containing 0.2 grams of protein per mL of preservative-free liquid. Each vial label contains a peel-off strip with the vial size and product lot number for use in recording doses in a patient treatment record. The components used in the packaging for Hizentra contain no latex.
The following dosage presentations are available: NDC Number Fill Size (mL) Grams Protein 44206-451-01 5 mL 1 44206-452-02 10 mL 2 44206-454-04 20 mL 4
16.2Storage and Handling When stored at room temperature (up to 25°C [77°F]), Hizentra is stable for up to 30 months, as indicated by the expiration date printed on the outer carton and vial label. DO NOT FREEZE. Do not use product that has been frozen. Do not shake. Keep Hizentra in its original carton to protect it from light.
📦 Storage and Handling ▾
16.2Storage and Handling When stored at room temperature (up to 25°C [77°F]), Hizentra is stable for up to 30 months, as indicated by the expiration date printed on the outer carton and vial label. DO NOT FREEZE. Do not use product that has been frozen. Do not shake. Keep Hizentra in its original carton to protect it from light.
📋 Description ▾
11 DESCRIPTION Hizentra, Immune Globulin Subcutaneous (Human), 20% Liquid, is a ready-to-use, sterile 20% (0.2 g/mL) protein liquid preparation of polyvalent human immunoglobulin G (IgG) for subcutaneous administration. Hizentra is manufactured from large pools of human plasma by a combination of cold alcohol fractionation, octanoic acid fractionation, and anion exchange chromatography. The IgG proteins are not subjected to heating or to chemical or enzymatic modification.
The Fc and Fab functions of the IgG molecule are retained. Fab functions tested include antigen binding capacities, and Fc functions tested include complement activation and Fc-receptor-mediated leukocyte activation (determined with complexed IgG). Hizentra has a purity of ≥98% IgG and a pH of 4.6 to 5.2.
Hizentra contains approximately 250 (range: 210 to 290 mmol/L) L-proline (a nonessential amino acid) as a stabilizer, 10 to 30 mg/L polysorbate 80, and trace amounts of sodium. Hizentra contains ≤50 mcg/mL IgA. Hizentra contains no carbohydrate stabilizers (e.g., sucrose, maltose) and no preservative.
Plasma units used in the manufacture of Hizentra are tested using FDA-licensed serological assays for hepatitis B surface antigen and antibodies to human immunodeficiency virus (HIV)-1/2 and hepatitis C virus (HCV) as well as FDA-licensed Nucleic Acid Testing (NAT) for HIV-1 and HCV. All plasma units have been found to be nonreactive (negative) in these tests. For hepatitis B virus (HBV), an investigational NAT procedure is used and the plasma units found to be negative; however, the significance of a negative result has not been established.
In addition, the plasma has been tested for B19 virus (B19V) DNA by NAT. Only plasma that passes virus screening is used for production, and the limit for B19V in the fractionation pool is set not to exceed 10 4 IU of B19V DNA per mL. The manufacturing process for Hizentra includes three steps to reduce the risk of virus transmission.
Two of these are dedicated virus clearance steps: pH 4 incubation to inactivate enveloped viruses; and virus filtration to remove, by size exclusion, both enveloped and non-enveloped viruses as small as approximately 20 nanometers. In addition, a depth filtration step contributes to the virus reduction capacity. 12 These steps have been independently validated in a series of in vitro experiments for their capacity to inactivate and/or remove both enveloped and non-enveloped viruses.
Table 5 shows the virus clearance during the manufacturing process for Hizentra, expressed as the mean log 10 reduction factor (LRF). Table 5: Virus Inactivation/Removal in Hizentra The virus clearance of human parvovirus B19 was investigated experimentally at the pH 4 incubation step. The estimated LRF obtained was ≥5.3.
HIV-1 PRV BVDV WNV EMCV MVM HIV-1, human immunodeficiency virus type 1, a model for HIV-1 and HIV-2; PRV, pseudorabies virus, a nonspecific model for large enveloped DNA viruses (e.g., herpes virus); BVDV, bovine viral diarrhea virus, a model for hepatitis C virus; WNV, West Nile virus; EMCV, encephalomyocarditis virus, a model for hepatitis A virus; MVM, minute virus of mice, a model for a small highly resistant non-enveloped DNA virus (e.g., parvovirus); LRF, log 10 reduction factor; nt, not tested; na, not applicable.
Virus Property Genome RNA DNA RNA RNA RNA DNA Envelope Yes Yes Yes Yes No No Size (nm) 80-100 120-200 50-70 50-70 25-30 18-24 Manufacturing Step Mean LRF pH 4 incubation ≥5.4 ≥5.9 4.6 ≥7.8 nt nt Depth filtration ≥5.3 ≥6.3 2.1 3.0 4.2
2.3Virus filtration ≥5.3 ≥5.5 ≥5.1 ≥5.9 ≥5.4 ≥5.5 Overall Reduction (Log 10 Units) ≥16.0 ≥17.7 ≥11.8 ≥16.7 ≥9.6 ≥7.8 The manufacturing process was also investigated for its capacity to decrease the infectivity of an experimental agent of transmissible spongiform encephalopathy (TSE), considered a model for CJD and its variant (vCJD). 12 Several of the production steps have been shown to decrease infectivity of an experimental TSE model agent. TSE r… [Excerpted — this section continues on DailyMed.]
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Self-administration – If self-administration is appropriate, ensure that the patient receives instructions and training on subcutaneous administration in the home or other appropriate setting and has demonstrated the ability to perform subcutaneous infusions. Ensure patients understand the importance of adhering to the weekly administration schedule to maintain the steady levels of IgG in their blood. Instruct patients to keep their treatment diary/log book current by recording, after each infusion, the time, date, dose, and any reactions, and by removing the peel-off portion of the label (containing the lot number) from the product vial and placing it in the treatment diary/log book.
Tell patients that mild to moderate local (injection-site) reactions (e.g., swelling and redness) are a common side effect of subcutaneous therapy, but to contact their healthcare professional if a local reaction persists for more than a few days. Inform patients of the importance of having an infusion needle long enough to reach the subcutaneous tissue and of changing the actual site of injection with each infusion. Inform patients to consider adjusting the injection-site location, volume per site, and rate of infusion based on how infusions are tolerated.
Dose adjustments – Inform patients that they should be tested regularly to make sure they have the correct levels of Hizentra (IgG) in their blood. These tests may result in adjustments to the Hizentra dose. Hypersensitivity – Inform patients of the early signs of hypersensitivity reactions to Hizentra (including hives, generalized urticaria, tightness of the chest, wheezing, hypotension, and anaphylaxis), and advise them to notify their physician if they experience any of these symptoms.
AMS – Inform patients of the signs of AMS, including severe headache, neck stiffness, drowsiness, fever, sensitivity to light, painful eye movements, nausea, and vomiting, and advise them to notify their physician if they experience any of these symptoms. Interference with vaccines – Inform patients that administration of IgG may interfere with the response to live virus vaccines (e.g., measles, mumps, rubella, and varicella) and to notify their immunizing physician of recent therapy with Hizentra. Reactions reported to occur with IGIV treatment – Advise patients to be aware of and immediately report to their physician symptoms of the following potential reactions: Decreased urine output, sudden weight gain, fluid retention/edema, and/or shortness of breath, which may suggest kidney problems Shortness of breath, changes in mental status, chest pain, and other manifestations of thrombotic and embolic events Fatigue, increased heart rate, yellowing of the skin or eyes, and dark-colored urine, which may suggest hemolysis Severe breathing problems, lightheadedness, drops in blood pressure, and fever, which may suggest TRALI (a condition typically occurring within 1 to 6 hours following transfusion) Transmissible infectious agents – Inform patients that Hizentra is made from human plasma (part of the blood) and may contain infectious agents that can cause disease (e.g., viruses and, theoretically, the CJD agent).
Explain that the risk that Hizentra may transmit an infectious agent has been reduced by screening the plasma donors, by testing the donated plasma for certain virus infections, and by inactivating and/or removing certain viruses during manufacturing. The attached Hizentra "Information for Patients" contains more detailed instructions for patients who will be self-administering Hizentra.
🍼 Nursing Mothers ▾
8.3Nursing Mothers Hizentra has not been evaluated in nursing mothers.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetics (PK) of Hizentra was evaluated in a PK substudy of subjects with PI participating in the 15-month efficacy and safety study ( see Clinical Studies [14] ). All PK subjects were treated previously with Privigen ® , Immune Globulin Intravenous (Human), 10% Liquid and were switched to weekly subcutaneous treatment with Hizentra. After a 3-month wash-in/wash-out period, doses were adjusted individually with the goal of providing a systemic serum IgG exposure (area under the IgG serum concentration vs time curve; AUC) not inferior to that of the previous weekly-equivalent IGIV dose.
Table 6 summarizes PK parameters for subjects in the substudy following treatment with Hizentra and IGIV. Table 6: Pharmacokinetics Parameters of Hizentra and IGIV Hizentra IGIV For IGIV: weekly-equivalent dose. (Privigen ® ) bw, body weight.
Number of subjects 18 18 Dose Mean 228 mg/kg bw 152 mg/kg bw Range 141-381 mg/kg bw 86-254 mg/kg bw IgG peak levels Mean 1616 mg/dL 2564 mg/dL Range 1090-2825 mg/dL 2046-3456 mg/dL IgG trough levels Mean 1448 mg/dL 1127 mg/dL Range 952-2623 mg/dL 702-1810 mg/dL AUC Standardized to a 7-day period. Mean 10560 day x mg/dL 10320 day x mg/dL Range 7210-18670 day x mg/dL 8051-15530 day x mg/dL For the 19 subjects completing the wash-in/wash-out period, the average dose adjustment for Hizentra was 153% (range: 126% to 187%) of the previous weekly-equivalent IGIV dose.
After 12 weeks of treatment with Hizentra at this individually adjusted dose, the final steady-state AUC determinations were made in 18 of the 19 subjects. The geometric mean ratio of the steady-state AUCs, standardized to a weekly treatment period, for Hizentra vs IGIV treatment was 1.002 (range: 0.77 to 1.20) with a 90% confidence limit of 0.951 to 1.055 for the 18 subjects. With Hizentra, peak serum levels are lower (1616 vs 2564 mg/dL) than those achieved with IGIV while trough levels are generally higher (1448 vs 1127 mg/dL).
In contrast to IGIV administered every 3 to 4 weeks, weekly subcutaneous administration results in relatively stable steady-state serum IgG levels. 13,14 After the subjects had reached steady-state with weekly administration of Hizentra, peak serum IgG levels were observed after a mean of 2.9 days (range: 0 to 7 days) in 18 subjects.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES A prospective, open-label, multicenter, single-arm, clinical study conducted in the US evaluated the efficacy, tolerability, and safety of Hizentra in adult and pediatric subjects with PI. Subjects previously receiving monthly treatment with IGIV were switched to weekly subcutaneous administration of Hizentra for 15 months (a 3-month wash-in/wash-out period followed by a 12-month efficacy period). The efficacy analyses included 38 subjects in the modified intention-to-treat (MITT) population.
The MITT population consisted of subjects who completed the wash-in/wash-out period and received at least one infusion of Hizentra during the efficacy period. Although 5% of the administered doses could not be verified, the weekly doses of Hizentra ranged from 72 to 379 mg per kg body weight, which was 149% (range: 114% to 180%) of the previous IGIV dose. Subjects received a total of 2264 infusions of Hizentra.
In the study, the number of injection sites per infusion ranged from 1 to 12. In 73% of infusions; the number of injection sites was 4 or fewer. Up to 4 simultaneous injection sites were permitted using 2 pumps; however, more than 4 sites could be used consecutively during one infusion.
The infusion flow rate did not exceed 50 mL per hour for all injection sites combined. During the efficacy period, the median duration of a weekly infusion ranged from 1.6 to 2.0 hours. The study evaluated the annual rate of serious bacterial infections (SBIs), defined as bacterial pneumonia, bacteremia/septicemia, osteomyelitis/septic arthritis, bacterial meningitis, and visceral abscess.
The study also evaluated the annual rate of any infections, the use of antibiotics for infection (prophylaxis or treatment), the days out of work/school/kindergarten/day care or unable to perform normal activities due to infections, and hospitalizations due to infections. Table 7 summarizes the efficacy results for subjects in the efficacy phase (MITT population) of the study. No subjects experienced an SBI in this study.
Table 7: Summary of Efficacy Results (MITT Population) Number of subjects (efficacy phase) 38 Total number of subject days 12,697 Infections Annual rate of SBIs Defined as bacterial pneumonia, bacteremia/septicemia, osteomyelitis/septic arthritis, bacterial meningitis, and visceral abscess. 0 SBIs per subject year Upper 99% confidence limit: 0.132. Annual rate of any infections 2.76 infections/subject year 95% confidence limits: 2.235; 3.370.
Antibiotic use for infection (prophylaxis or treatment) Number of subjects (%) 27 (71.1) Annual rate 48.5 days/subject year Total number of subject days 12,605 Days out of work/school/kindergarten/day care or unable to perform normal activities due to infections Number of days (%) 71 (0.56) Annual rate 2.06 days/subject year Hospitalizations due to infections Number of days (%) 7 (0.06) Based on 1 subject. Annual rate 0.2 days/subject year
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.2Animal Toxicology and/or Pharmacology Long- and short-term memory loss was seen in juvenile rats in a study modeling hyperprolinemia. In this study, rats received daily subcutaneous injections with L-proline from day 6 to day 28 of life. 15 The daily amounts of L-proline used in this study were more than 60 times higher than the L-proline dose that would result from the administration of 400 mg/kg body weight of Hizentra once weekly.
In unpublished studies using the same animal model (i.e., rats) dosed with the same amount of L-proline with a dosing interval relevant to IGSC treatment (i.e., on 5 consecutive days on days 9 to 13, or once weekly on days 9, 16, and 23), no effects on learning and memory were observed. The clinical relevance of these studies is not known.
📚 References ▾
15 REFERENCES Gabor EP, Meningitis and skin reaction after intravenous immune globulin therapy. Ann Intern Med 1997:127:1130. Cayco AV, Perazella MA, Hayslett JP.
Renal insufficiency after intravenous immune globulin therapy: a report of two cases and an analysis of the literature. J Am Soc Nephrol 1997;8:1788-1793. Dalakas MC.
High-dose intravenous immunoglobulin and serum viscosity: risk of precipitating thromboembolic events. Neurology 1994;44:223-226. Woodruff RK, Grigg AP, Firkin FC, Smith IL.
Fatal thrombotic events during treatment of autoimmune thrombocytopenia with intravenous immunoglobulin in elderly patients. Lancet 1986;2:217-218. Wolberg AS, Kon RH, Monroe DM, Hoffman M.
Coagulation factor XI is a contaminant in intravenous immunoglobulin preparations. Am J Hematol 2000;65:30-34. Copelan EA, Strohm PL, Kennedy MS, Tutschka PJ.
Hemolysis following intravenous immune globulin therapy. Transfusion 1986;26:410-412. Thomas MJ, Misbah SA, Chapel HM, Jones M, Elrington G, Newsom-Davis J.
Hemolysis after high-dose intravenous Ig. Blood 1993;15:3789. Wilson JR, Bhoopalam N, Fisher M.
Hemolytic anemia associated with intravenous immunoglobulin. Muscle Nerve 1997;20:1142-1145. Kessary-Shoham H, Levy Y, Shoenfeld Y, Lorber M, Gershon H.
In vivo administration of intravenous immunoglobulin (IVIg) can lead to enhanced erythrocyte sequestration. J Autoimmun 1999;13:129-135. Rizk A, Gorson KC, Kenney L, Weinstein R.
Transfusion-related acute lung injury after the infusion of IVIG. Transfusion 2001;41:264-268. Pierce LR, Jain N.
Risks associated with the use of intravenous immunoglobulin. Trans Med Rev 2003;17:241-251. Stucki M, Boschetti N, Schäfer W, et al.
Investigations of prion and virus safety of a new liquid IVIG product. Biologicals 2008;36:239-247. Smith GN, Griffiths B, Mollison D, Mollison PL.
Uptake of IgG after intramuscular and subcutaneous injection. Lancet 1972;1:1208-1212. Waniewski I, Gardulf A, Hammarström L.
Bioavailability of γ-globulin after subcutaneous infusions in patients with common variable immunodeficiency. J Clin Immunol 1994;14:90-97. Bavaresco CS, Streck EL, Netto CA, et al.
Chronic hyperprolinemia provokes a memory deficit in the Morris Water Maze Task. Metabolic Brain Disease 2005;20:73-80.
📄 Patient Package Insert ▾
Hizentra Immune Globulin Subcutaneous (Human), 20% Liquid Information for Patients This patient package insert summarizes important information about Hizentra. Please read it carefully before using this medicine. This information does not take the place of talking with your healthcare professional, and it does not include all of the important information about Hizentra.
If you have any questions after reading this, ask your healthcare professional. What is the most important information I should know about Hizentra? Hizentra is supposed to be infused under your skin only.
DO NOT inject Hizentra into a blood vessel (vein or artery). What is Hizentra? Hizentra (Hi – ZEN – tra) is a prescription medicine used to treat primary immune deficiency (PI).
Hizentra is made from human plasma. It contains antibodies, called immunoglobulin G (IgG), that healthy people have to fight germs (bacteria and viruses). People with PI get a lot of infections.
Hizentra helps lower the number of infections you will get. Who should NOT take Hizentra? Do not take Hizentra if you have too much proline in your blood (called "hyperprolinemia") or if you have had reactions to polysorbate 80.
Tell your doctor if you have had a serious reaction to other immune globulin medicines or if you have been told that you also have a deficiency of the immunoglobulin called IgA. How should I take Hizentra? You will take Hizentra through an infusion under your skin.
You will put up to 4 needles into different places of your body at one time. The needles are attached to a pump with an infusion tube. It usually takes about 60 minutes to do one infusion.
You will need to have infusions once a week. Instructions for using Hizentra are at the end of this patient package insert (see " How do I use Hizentra? "). Do not use Hizentra by yourself until you have been taught how by your doctor or healthcare professional.
What should I avoid while taking Hizentra? Vaccines may not work well for you while you are taking Hizentra. Tell your doctor or healthcare professional that you are taking Hizentra before you get a vaccine.
Tell your doctor or healthcare professional if you are pregnant or plan to become pregnant, or if you are nursing. What are possible side effects of Hizentra? The most common side effects with Hizentra are: Redness, swelling, and itching at the injection site Headache/migraine Vomiting Pain (including pain in the back, joints, arms, legs) Fatigue Bruising Diarrhea Stomach ache Nausea Rash Tell your doctor right away or go to the emergency room if you have hives, trouble breathing, wheezing, dizziness, or fainting.
These could be signs of a bad allergic reaction. Tell your doctor right away if you have any of the following symptoms. They could be signs of a serious problem.
Reduced urination, sudden weight gain, or swelling in your legs. These could be signs of a kidney problem. Pain, swelling, warmth, redness, or a lump in your legs or arms.
These could be signs of a blood clot. Bad headache with nausea, vomiting, stiff neck, fever, and sensitivity to light. These could be signs of a brain swelling called meningitis.
Brown or red urine, fast heart rate, yellow skin or eyes. These could be signs of a blood problem. Chest pains or trouble breathing.
Fever over 100ºF. This could be a sign of an infection. Tell your doctor about any side effects that concern you.
You can ask your doctor to give you more information that is available to healthcare professionals. How do I use Hizentra? Infuse Hizentra only after you have been trained by your doctor or healthcare professional.
Below are step-by-step instructions to help you remember how to use Hizentra. Ask your doctor or healthcare professional about any instructions you do not understand. Instructions for use Hizentra comes in single-use vials.
Keep Hizentra in the storage box at room temperature. Step 1: Assemble supplies Gather the Hizentra vial(s), the following disposable supplies (not provided with Hizentra), a… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Dosage and Administration ( 2.2 , 2.3 ) 02/2011 Warnings and Precautions ( 5.2 , 5.3 ) 02/2011
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 5 mL Vial Label NDC 44206-451-01 A5614/876 Immune Globulin Subcutaneous (Human), 20% Liquid Hizentra™ Subcutaneous use only Rx only Each Hizentra single-use vial contains 1 g IgG. Store Hizentra up to 25°C (77°F). Do not freeze. Principal Display Panel
PRINCIPAL DISPLAY PANEL - 5 mL Vial Carton NDC 44206-451-01 1 g 5 mL Immune Globulin Subcutaneous (Human), 20% Liquid Hizentra™ Single-use vial For Subcutaneous Administration Only Rx only CSL Behring PRINCIPAL DISPLAY PANEL - 5 mL Vial Carton
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |