
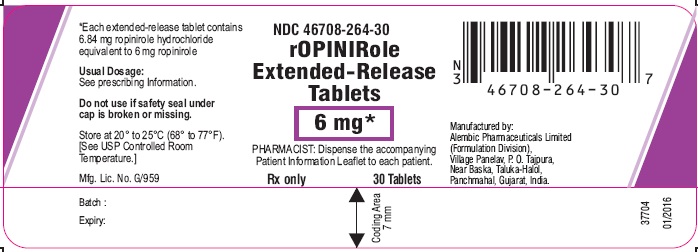
Ropinirole 6 mg Tablet, Film Coated, Extended Release, 90-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Nonergot Dopamine Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Ropinirole is used to treat the symptoms of Parkinson's disease (PD; a disorder of the nervous system that causes difficulties with movement, muscle control, and balance), including shaking of parts of the body, stiffness, slowed movements, and problems with balance. Ropinirole is also used to treat restless legs syndrome (RLS; a condition that causes discomfort in the legs and a strong urge to move the legs, especially at night and when sitting or lying down). Ropinirole is in a class of medications called dopamine agonists. It works by acting in place of dopamine, a natural substance in the...
Read the full MedlinePlus article ↗- Ropinirole treats two different conditions. The regular tablets are approved for Parkinson's disease and for moderate-to-severe Restless Legs Syndrome — that uncomfortable, irresis...
- Yes, and it's one of the most important things to know. Some people taking ropinirole have fallen asleep suddenly during everyday activities — including while driving — sometimes w...
- I heard this medication can make you fall asleep out of nowhere. Is that true?
- It can, and this is something to watch for carefully. Some people develop strong, hard-to-control urges — like gambling, overeating, compulsive shopping, or increased sexual intere...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Ropinirole — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII K679OBS311
Carboxymethylcellulose sodium is a plant-derived thickening agent made from cellulose. In medicines, it acts as a binder to hold ingredients together, a disintegrant to help the tablet break apart, or a thickener in liquids.
-
UNII H3UP11403C
Ethylcellulose is a plant-derived polymer that thickens and forms protective coatings on tablets and capsules. It slows medicine release into the body and protects the contents from moisture and air.
-
UNII ZF94AP8MEY
Hydrogenated castor oil is a processed plant oil made by adding hydrogen to castor oil. It's used as a binder to help hold tablet ingredients together and as a lubricant to prevent sticking during manufacturing.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII Q662QK8M3B
Polyethylene glycol 8000 is a synthetic polymer made from ethylene oxide. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and add bulk to the medicine.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.9817 | $88.35 / 90 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ropinirole 6 mg 00228-3640-03 | Actavis | 30 tablets | $1.405 | AB | Availability likely | — |
| Ropinirole 6 mg 43547-0556-03 | Solco | 30 tablets | $1.405 | AB | Availability likely | — |
| Ropinirole 6 mg 64850-0252-30 | Elite | 30 tablets | $1.405 | AB | Availability likely | — |
| Ropinirole Hydrochloride 6 mg 42291-0715-30 | AvKARE | 30 tablets | — | AB | FDA listed | — |
| Ropinirole 6 mgthis 46708-0264-90 | Alembic | 90 tablets | — | AB | FDA listed | — |
| Ropinirole 6 mg 55111-0727-05 | Dr. | 500 tablets | — | AB | FDA listed | — |
| Ropinirole 6 mg 62332-0109-10 | Alembic | 100 tablets | — | AB | FDA listed | — |
| Ropinirole 6 mg 72162-2604-03 | Bryant | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 46708-0264-10 | 100 TABLET, FILM COATED, EXTENDED RELEASE in 1 CARTON (46708-264-10) | 2013-03-14 | Active |
| 46708-0264-30 | 30 TABLET, FILM COATED, EXTENDED RELEASE in 1 BOTTLE (46708-264-30) | 2013-03-14 | Active |
| 46708-0264-31 | 100 TABLET, FILM COATED, EXTENDED RELEASE in 1 BOTTLE (46708-264-31) | 2013-03-14 | Active |
| 46708-0264-71 | 500 TABLET, FILM COATED, EXTENDED RELEASE in 1 BOTTLE (46708-264-71) | 2013-03-14 | Active |
| 46708-0264-90 You're viewing this | 90 TABLET, FILM COATED, EXTENDED RELEASE in 1 BOTTLE (46708-264-90) | 2013-03-14 | Active |
| 46708-0264-91 | 1000 TABLET, FILM COATED, EXTENDED RELEASE in 1 BOTTLE (46708-264-91) | 2013-03-14 | Active |
Pack size FAQ
What quantity is in NDC 46708-0264-90?
What is the difference between NDC 46708-0264-90 and NDC 46708-0264-30?
What NDC number is used to bill for this package of Ropinirole 6 mg Tablet, Film Coated, Extended Release?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Ropinirole extended-release tablets are non-ergoline dopamine agonist indicated for the treatment of Parkinson’s disease (1.1)
1.1Parkinson's Disease Ropinirole extended-release tablets are indicated for the treatment of Parkinson’s disease.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION •Ropinirole extended-release tablets are taken once daily, with or without food; tablets must be swallowed whole and must not be chewed, crushed, or divided (2.1) •The recommended starting dose is 2 mg taken once daily for 1 to 2 weeks; the dose should be increased by 2 mg/day at 1 week or longer intervals; the maximum dose is 24 mg/day (2.2, 14.2) •Renal Impairment: In patients with end-stage renal disease on hemodialysis, the maximum recommended dose is 18 mg/day (2.2) •If ropinirole extended-release tablets must be discontinued, it should be tapered gradually over a 7-day period; retitration of ropinirole extended-release tablets may be warranted if therapy is interrupted (2.1, 2.2) •Patients may be switched directly from immediate-release ropinirole to ropinirole extended-release tablets; the initial switching dose of ropinirole extended-release tablets should most closely match the total daily dose of immediate-release ropinirole.
(2.3)
2.1General Dosing Recommendations · Ropinirole extended-release tablets are taken once daily, with or without food [see Clinical Pharmacology (12.3)] . · Tablets must be swallowed whole and must not be chewed, crushed, or divided. · If a significant interruption in therapy with ropinirole extended-release tablets has occurred, retitration of therapy may be warranted.
2.2Dosing for Parkinson's Disease The starting dose is 2 mg taken once daily for 1 to 2 weeks, followed by increases of 2 mg/day at 1-week or longer intervals as appropriate, based on therapeutic response and tolerability. The maximum recommended dose of ropinirole extended-release tablets is 24 mg/day. In clinical trials, dosage was initiated at 2 mg/day and gradually titrated based on individual patient therapeutic response and tolerability.
Doses greater than 24 mg/day have not been studied in clinical trials. Patients should be assessed for therapeutic response and tolerability at a minimal interval of 1 week or longer after each dose increment. Monitor patients during dose titration because too rapid a rate of titration may lead to dose selection that may not provide additional benefit, but that may increase the risk of adverse reactions [see Clinical Studies (14.2)] .
Due to the flexible dosing design used in clinical trials, specific dose-response information could not be determined. Ropinirole extended-release tablets should be discontinued gradually over a 7-day period. Renal Impairment No dose adjustment is necessary in patients with moderate renal impairment (creatinine clearance of 30 to 50 mL/min).
The recommended initial dose of ropinirole extended-release tablets for patients with end-stage renal disease on hemodialysis is 2 mg once daily. Further dose escalations should be based on tolerability and need for efficacy. The recommended maximum total daily dose is 18 mg/day in patients receiving regular dialysis.
Supplemental doses after dialysis are not required. The use of ropinirole extended-release tablets in patients with severe renal impairment without regular dialysis has not been studied.
2.3Switching from Immediate-Release Ropinirole Tablets to Extended-Release Ropinirole Tablets Patients may be switched directly from immediate-release ropinirole to extended-release ropinirole tablets. The initial dose of ropinirole extended-release tablets should most closely match the total daily dose of the immediate-release formulation of ropinirole tablets, as shown in Table 1. Table 1.
Conversion from Immediate-Release Ropinirole Tablets to Extended-Release Ropinirole Tablets Immediate-Release Ropinirole Tablets Total Daily Dose (mg) Extended-Release Ropinirole Tablets Total Daily Dose (mg) 0.75 to 2.25 2 3 to 4.5 4 6 6 7.5 to 9 8 12 12 15 16 18 18 21 20 24 24 Following conversion to ropinirole extended-release tablets, the dose may be adjusted depending on therapeutic response and tolerability [see Dosage and Administration (2.2)].
2.4 Effect of Gastrointestinal Transit Time on Medicat…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 2 mg, pink, capsule shaped, film coated tablet, debossed with ‘L191’ on one side and plain on other side. 4 mg, light brown, capsule shaped, film coated tablet, debossed with ‘L193’ on one side and plain on other side. 6 mg, white to off white, capsule shaped, film coated tablet, debossed with ‘L321’ on one side and plain on other side.
8 mg, dark brown to red, capsule shaped, film coated tablet, debossed with ‘L194’ on one side and plain on other side. 12 mg, light green, capsule shaped, film coated tablet, debossed with ‘L195’ on one side and plain on other side. Tablets: 2 mg, 4 mg, 6 mg, 8 mg, and 12 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Ropinirole extended-release tablets are contraindicated in patients known to have a hypersensitivity/allergic reaction including urticaria, angioedema, rash, pruritus) to ropinirole or any of the excipients. History of hypersensitivity/ allergic reaction (including urticaria, angioedema, rash, pruritus) to ropinirole or to any of the excipients (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS •Sudden onset of sleep and somnolence may occur (5.1) •Syncope may occur (5.2) •Hypotension, including orthostatic hypotension may occur (5.3) •Elevation of blood pressure and changes in heart rate may occur (5.4) •May cause hallucinations and psychotic-like behaviors (5.5) •May cause or exacerbate dyskinesia (5.6) •May cause problems with impulse control or compulsive behaviors (5.7)
5.1Falling Asleep during Activities of Daily Living and Somnolence Patients treated with ropinirole have reported falling asleep while engaged in activities of daily living, including driving or operating machinary, which sometimes resulted in accidents. Although many of these patients reported somnolence while on ropinirole, some perceived that they had no warning signs such as excessive drowsiness, and believed that they were alert immediately prior to the event. Some have reported these events more than 1 year after initiation of treatment.
Among the 613 patients who received ropinirole extended-release tablets in clinical trials, there were 5 cases of sudden onset of sleep and 2 cases of motor vehicle accident in which it is not known if falling asleep was a contributing factor. During the 6-month trial in advanced Parkinson’s disease, somnolence was reported in 7% of patients receiving ropinirole extended-release tablets compared with 4% of patients receiving placebo. During the 36-week trial in early Parkinson’s disease, somnolence was reported in 11% of patients receiving ropinirole extended-release tablets compared with 15% of patients receiving the immediate-release formulation of ropinirole tablets [see Adverse Reactions (6.1)].
However, because dose-response was not systematically studied with ropinirole extended-release tablets, the occurrence of somnolence at the highest recommended doses may be higher than these reported frequencies [see Adverse Reactions (6.1)] . It has been reported that falling asleep while engaged in activities of daily living usually occurs in a setting of preexisting somnolence, although patients may not give such a history. For this reason, prescribers should reassess patients for drowsiness or sleepiness, especially since some of the events occur well after the start of treatment.
Prescribers should also be aware that patients may not acknowledge drowsiness or sleepiness until directly questioned about drowsiness or sleepiness during specific activities. Before initiating treatment with ropinirole extended-release tablets, patients should be advised of the potential to develop drowsiness and specifically asked about factors that may increase the risk with ropinirole extended-release tablets such as concomitant sedating medications, the presence of sleep disorders, and concomitant medications that increase ropinirole plasma levels (e.g., ciprofloxacin) [see Drug Interactions (7.1)] .
If a patient develops significant daytime sleepiness or episodes of falling asleep during activities that require active participation (e.g., driving a motor vehicle, conversations, eating), ropinirole extended-release tablets should ordinarily be discontinued [see Dosage and Administration (2.2)] . If a decision is made to continue ropinirole extended-release tablets, patients should be advised to not drive and to avoid other potentially dangerous activities. There is insufficient information to establish that dose reduction will eliminate episodes of falling asleep while engaged in activities of daily living.
5.2Syncope Syncope, sometimes associated with bradycardia, was observed in association with ropinirole extended-release tablets in Parkinson’s disease patients. In a placebo-controlled trial involving patients with advanced Parkinson’s disease, syncope occurred in 2 of the 202 patients (1%) who received ropinirole extended-release tablets, and in none of the 191 patients who received placebo [see Adverse Reactions (6.1)] . Because the trial of ropinirole extended-release tablets excluded patien…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are described in more detail in other sections of the label: · Hypersensitivity [see Contraindications (4)] · Falling Asleep during Activities of Daily Living and Somnolence [see Warnings and Precautions (5.1)] · Syncope [see Warnings and Precautions (5.2)] · Hypotension/Orthostatic Hypotension [see Warnings and Precautions (5.3)] · Elevation of Blood Pressure and Changes in Heart Rate [see Warnings and Precautions (5.4)] · Hallucinations/Psychotic-like Behavior [see Warnings and Precautions (5.5)] · Dyskinesia [see Warnings and Precautions (5.6)] · Impulse Control/Compulsive Behaviors [see Warnings and Precautions (5.7)] · Withdrawal-emergent Hyperpyrexia and Confusion [see Warnings and Precautions (5.8)] · Melanoma [see Warnings and Precautions (5.9)] · Fibrotic Complications [see Warnings and Precautions (5.10)] · Most common adverse reactions (incidence for ropinirole extended-release tablets at least 5% greater than placebo) in advanced Parkinson’s disease with concomitant L-dopa were dyskinesia, nausea, dizziness, hallucination.
(6.1) · Most common adverse reactions (incidence incidence for ropinirole extended-release tablets at least 5%) in early Parkinson’s disease without L-dopa were nausea, somnolence, abdominal pain/discomfort, dizziness, headache, and constipation (6.1) To report SUSPECTED ADVERSE REACTIONS, contact FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug (or of another development program of a different formulation of the same drug) and may not reflect the rates observed in practice. During the premarketing development of ropinirole extended-release tablets, patients with advanced Parkinson’s disease received ropinirole extended-release tablets or placebo as adjunctive therapy in 1 clinical trial.
In a second trial, patients with early Parkinson’s disease were treated with ropinirole extended-release tablets or the immediate-release formulation of ropinirole tablets without L-dopa. Advanced Parkinson’s Disease (with L-dopa) In the 24-week, double-blind, placebo-controlled trial for the treatment of advanced Parkinson’s disease, the most commonly observed adverse reactions in patients treated with ropinirole extended-release tablets (incidence at least 5% greater than placebo) were dyskinesia, nausea, dizziness and hallucination.
Approximately 6% of patients treated with ropinirole extended-release tablets discontinued treatment due to adverse reactions compared with 5% of patients who received placebo. The most common adverse reaction in patients treated with ropinirole extended-release tablets causing discontinuation of treatment with ropinirole extended-release tablets was hallucination (2%) Table 2 lists treatment-emergent adverse reactions that occurred in at least 2% (and were numerically greater than placebo) of patients with advanced Parkinson’s disease treated with ropinirole extended-release tablets who participated in the 26-week, double-blind, placebo-controlled trial.
In this trial, either ropinirole extended-release tablets or placebo was used as an adjunct to L-dopa. Table 2. Treatment-Emergent Adverse Reaction Incidence in a Double-Blind, Placebo-Controlled Trial in Advanced Stage Parkinson’s Disease (With L-dopa) (Events ≥ 2% of Patients Treated with Ropinirole Extended-Release Tabletsand >% with Placebo) a Body System/Adverse Reaction Ropinirole Extended-Release Tablets (n = 202) % Placebo (n = 191) % Ear and labyrinth disorders Vertigo 4 2 Gastrointestinal disorders Nausea 11 4 Constipation 4 2 Abdominal pain/discomfort 6 3 Diarrhea 3 2 Dry mouth 2 <1 General disorders Edema peripheral 4 1 Injury, poisoning, and procedural complication Fall* 2 1 Musculoskeletal and connective tissue disorders Back p…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS •Inhibitors or inducers of CYP1A2: May alter the clearance of ropinirole;dose adjustment may be required (7.1, 12.3) •Hormone replacement therapy (HRT): Starting or stopping HRT treatment may require dose adjustment of ropinirole extended-release tablets (7.2, 12.3) •Dopamine antagonists (e.g., neuroleptics metoclopramide): May reduce efficacy of ropinirole extended-release tablets (7.3)
7.1CYP1A2 Inhibitors and Inducers In vitro metabolism studies showed that CYP1A2 is the major enzyme responsible for the metabolism of ropinirole. There is thus the potential for inducers or inhibitors of this enzyme to alter the clearance of ropinirole. Therefore, if therapy with a drug known to be a potent inducer or inhibitor of CYP1A2 is stopped or started during treatment with ropinirole extended-release tablets, adjustment of the dose of ropinirole extended-release tablets may be required.
Coadministration of ciprofloxacin, an inhibitor of CYP1A2, with immediate-release ropinirole increases the AUC and C max of ropinirole [see Clinical Pharmacology (12.3)] . Cigarette smoking is expected to increase the clearance of ropinirole since CYP1A2 is known to be induced by smoking [see Clinical Pharmacology (12.3)] .
7.2Estrogens Population pharmacokinetic analysis revealed that higher doses of estrogens (usually associated with hormone replacement therapy [HRT]) reduced the clearance of ropinirole. Starting or stopping HRT may require adjustment of dosage of ropinirole extended-release tablets [see Clinical Pharmacology (12.3)] .
7.3Dopamine Antagonists Because ropinirole is a dopamine agonist, it is possible that dopamine antagonists such as neuroleptics (e.g., phenothiazines, butyrophenones, thioxanthenes) or metoclopramide may reduce the efficacy of ropinirole extended-release tablets.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data, may cause fetal harm (8.1)
8.1Pregnancy Pregnancy Category C. There are no adequate and well-controlled studies in pregnant women. In animal reproduction studies, ropinirole has been shown to have adverse effects on embryo-fetal development, including teratogenic effects.
Ropinirole extended-release tablets should be used during pregnancy only if the potential benefit outweighs the potential risk to the fetus. Oral treatment of pregnant rats with ropinirole during organogenesis resulted in decreased fetal body weight, increased fetal death, and digital malformations at 24, 36, and 60 times, respectively, the maximum recommended human dose (MRHD) for Parkinson’s disease (24 mg/day) on a mg/m 2 basis. The combined oral administration of ropinirole at 8 times the MRHD and a clinically relevant dose of L-dopa to pregnant rabbits during organogenesis produced a greater incidence and severity of fetal malformations (primarily digit defects) than were seen in the offspring of rabbits treated with L-dopa alone.
No effect on fetal development was observed in rabbits when ropinirole was administered alone at an oral dose 16 times the MRHD on a mg/m 2 basis. In a perinatal-postnatal study in rats, impaired growth and development of nursing offspring and altered neurological development of female offspring were observed when dams were treated with 4 times the MRHD on a mg/m 2 basis.
8.3Nursing Mothers Ropinirole inhibits prolactin secretion in humans and could potentially inhibit lactation. Ropinirole has been detected in rat milk. It is not known whether this drug is excreted in human milk. Because many drugs are excreted in human milk, caution should be exercised when ropinirole is administered to a nursing woman.
8.4Pediatric Use Safety and effectiveness in the pediatric population have not been established.
8.5Geriatric Use Dose adjustment is not necessary in elderly (65 years and older) patients, as the dose of ropinirole extended-release tablets is individually titrated to clinical therapeutic response and tolerability. Pharmacokinetic trials conducted in patients demonstrated that oral clearance of ropinirole is reduced by 15% in patients above 65 years compared with younger patients [see Clinical Pharmacology (12.3)] . In clinical trials of ropinirole extended-release tablets for Parkinson’s disease, 387 patients were 65 years and older and 107 were 75 and older.
Among patients receiving ropinirole extended-release tablets, hallucination was more common in elderly patients (10%) compared with non-elderly patients (2%). The incidence of overall adverse reactions increased with increasing age for both patients receiving ropinirole extended-release tablets and placebo.
8.6Renal Impairment No dose adjustment is necessary in patients with moderate renal impairment (creatinine clearance of 30 to 50 mL/min). For patients with end-stage renal disease on hemodialysis, a reduced maximum dose is recommended [see Dosage and Administration (2.2), Clinical Pharmacology (12.3)]. The use of ropinirole extended-release tablets in patients with severe renal impairment (creatinine clearance less than 30 mL/min) without regular dialysis has not been studied.
8.7Hepatic Impairment The pharmacokinetics of ropinirole have not been studied in patients with hepatic impairment.
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Category C. There are no adequate and well-controlled studies in pregnant women. In animal reproduction studies, ropinirole has been shown to have adverse effects on embryo-fetal development, including teratogenic effects.
Ropinirole extended-release tablets should be used during pregnancy only if the potential benefit outweighs the potential risk to the fetus. Oral treatment of pregnant rats with ropinirole during organogenesis resulted in decreased fetal body weight, increased fetal death, and digital malformations at 24, 36, and 60 times, respectively, the maximum recommended human dose (MRHD) for Parkinson’s disease (24 mg/day) on a mg/m 2 basis. The combined oral administration of ropinirole at 8 times the MRHD and a clinically relevant dose of L-dopa to pregnant rabbits during organogenesis produced a greater incidence and severity of fetal malformations (primarily digit defects) than were seen in the offspring of rabbits treated with L-dopa alone.
No effect on fetal development was observed in rabbits when ropinirole was administered alone at an oral dose 16 times the MRHD on a mg/m 2 basis. In a perinatal-postnatal study in rats, impaired growth and development of nursing offspring and altered neurological development of female offspring were observed when dams were treated with 4 times the MRHD on a mg/m 2 basis.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in the pediatric population have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Dose adjustment is not necessary in elderly (65 years and older) patients, as the dose of ropinirole extended-release tablets is individually titrated to clinical therapeutic response and tolerability. Pharmacokinetic trials conducted in patients demonstrated that oral clearance of ropinirole is reduced by 15% in patients above 65 years compared with younger patients [see Clinical Pharmacology (12.3)] . In clinical trials of ropinirole extended-release tablets for Parkinson’s disease, 387 patients were 65 years and older and 107 were 75 and older.
Among patients receiving ropinirole extended-release tablets, hallucination was more common in elderly patients (10%) compared with non-elderly patients (2%). The incidence of overall adverse reactions increased with increasing age for both patients receiving ropinirole extended-release tablets and placebo.
🆘 Overdosage ▾
10 OVERDOSAGE The symptoms of overdose with ropinirole are generally related to its dopaminergic activity. General supportive measures are recommended. Vital signs should be maintained, if necessary.
In the Parkinson’s disease program, there have been patients who accidentally or intentionally took more than their prescribed dose of ropinirole. The largest overdose reported with immediate-release ropinirole in clinical trials was 435 mg taken over a 7-day period (62.1 mg/day). Of patients who received a dose greater than 24 mg/day, reported symptoms included adverse events commonly reported during dopaminergic therapy (nausea, dizziness), as well as visual hallucinations, hyperhidrosis, claustrophobia, chorea, palpitations, asthenia, and nightmares.
Additional symptoms reported for doses of 24 mg or less or for overdoses of unknown amount included vomiting, increased coughing, fatigue, syncope, vasovagal syncope, dyskinesia, agitation, chest pain, orthostatic hypotension, somnolence, and confusional state.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Ropinirole is a non-ergoline dopamine agonist. The precise mechanism of action of ropinirole as a treatment for Parkinson’s disease is unknown, although it is thought to be related to its ability to stimulate dopamine D 2 -type receptors within the caudate-putamen in the brain.
12.2Pharmacodynamics Clinical experience with dopamine agonists, including ropinirole, suggests an association with impaired ability to regulate blood pressure with resulting orthostatic hypotension, especially during dose escalation. In some subjects in clinical trials, blood pressure changes were associated with the emergence of orthostatic symptoms, bradycardia, and, in one case in a healthy volunteer, transient sinus arrest with syncope [see Warnings and Precautions (5.2, 5.3)]. The mechanism of orthostatic hypotension induced by ropinirole is presumed to be due to a D 2 -mediated blunting of the noradrenergic response to standing and subsequent decrease in peripheral vascular resistance.
Nausea is a common concomitant symptom of orthostatic signs and symptoms. At oral doses as low as 0.2 mg, ropinirole suppressed serum prolactin concentrations in healthy male volunteers. Immediate-release ropinirole had no dose-related effect on ECG wave form and rhythm in young, healthy, male volunteers in the range of 0.01 to 2.5 mg.
Immediate-release ropinirole had no dose- or exposure-related effect on mean QTc intervals in healthy male and female volunteers titrated to doses up to 4 mg/day. The effect of ropinirole on QTc intervals at higher exposures achieved either due to drug interactions, hepatic impairment, or at higher doses has not been systematically evaluated.
12.3Pharmacokinetics Increase in systemic exposure of ropinirole following oral administration of 2 to 12 mg of ropinirole extended-release tablets was approximately dose-proportional. For ropinirole extended-release tablets, steady-state concentrations of ropinirole are expected to be achieved within 4 days of dosing. Absorption In clinical trials with immediate-release ropinirole, over 88% of a radiolabeled dose was recovered in urine, and the absolute bioavailability was 45% to 55%, indicating approximately 50% first-pass effect.
Relative bioavailability of ropinirole extended-release tablets compared with immediate-release tablets was approximately 100%. In a repeat-dose trial in subjects with Parkinson’s disease using ropinirole extended-release tablets 8 mg, the dose-normalized AUC (0-24) and C min for ropinirole extended-release tablets and immediate-release ropinirole were similar. Dose-normalized C max was, on average, 12% lower for ropinirole extended-release tablets than for the immediate-release formulation and the median time-to-peak concentration was 6 to 10 hours.
In a single-dose trial, administration of ropinirole extended-release tablets to healthy volunteers with food (i.e., high-fat meal) increased AUC by approximately 30% and C max by approximately 44%, compared with dosing under fasted conditions. In a repeat-dose trial in patients with Parkinson’s disease, food (i.e., high-fat meal) increased AUC by approximately 20% and C max by approximately 44%; T max was prolonged by 3 hours (median prolongation) compared with dosing under fasted conditions [see Dosage and Administration (2)] .
Distribution Ropinirole is widely distributed throughout the body, with an apparent volume of distribution of
7.5L/kg. It is up to 40% bound to plasma proteins and has a blood-to-plasma ratio of 1:1. Metabolism Ropinirole is extensively metabolized by the liver.
The major metabolic pathways are N-despropylation and hydroxylation to form the inactive N-despropyl metabolite and hydroxy metabolites. The N-despropyl metabolite is converted to carbamyl glucuronide, carboxylic acid, and N-despropyl hydroxy metabolites. The hydroxy metabolite of ropinirole is rapidly glucuronidated.
In vitro studies indicate that the major cytochrome P450 enzyme invo…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Ropinirole is a non-ergoline dopamine agonist. The precise mechanism of action of ropinirole as a treatment for Parkinson’s disease is unknown, although it is thought to be related to its ability to stimulate dopamine D 2 -type receptors within the caudate-putamen in the brain.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Each capsule shaped, film coated tablet contains ropinirole hydrochloride equivalent to the labeled amount of ropinirole as follows: 2 mg: pink tablets debossed with 'L191' NDC 46708-262-30 bottle of 30 tablets NDC 46708-262-90 bottle of 90 tablets NDC 46708-262-31 bottle of 100 tablets NDC 46708-262-71 bottle of 500 tablets NDC 46708-262-91 bottle of 1000 tablets NDC 46708-262-10 carton of 100 (10X10) unit dose tablets 4 mg: light brown tablets debossed with 'L193' NDC 46708-263-30 bottle of 30 tablets NDC 46708-263-90 bottle of 90 tablets NDC 46708-263-31 bottle of 100 tablets NDC 46708-263-71 bottle of 500 tablets NDC 46708-263-91 bottle of 1000 tablets NDC 46708-263-10 carton of 100 (10X10) unit dose tablets 6 mg: white to off white tablets debossed with 'L321' NDC 46708-264-30 bottle of 30 tablets NDC 46708-264-90 bottle of 90 tablets NDC 46708-264-31 bottle of 100 tablets NDC 46708-264-71 bottle of 500 tablets NDC 46708-264-91 bottle of 1000 tablets NDC 46708-264-10 carton of 100 (10X10) unit dose tablets 8 mg: dark brown to red tablets debossed with 'L194' NDC 46708-265-30 bottle of 30 tablets NDC 46708-265-90 bottle of 90 tablets NDC 46708-265-31 bottle of 100 tablets NDC 46708-265-71 bottle of 500 tablets NDC 46708-265-91 bottle of 1000 tablets NDC 46708-265-10 carton of 100 (10X10) unit dose tablets 12 mg: light green tablets debossed with 'L195' NDC 46708-266-30 bottle of 30 tablets NDC 46708-266-90 bottle of 90 tablets NDC 46708-266-31 bottle of 100 tablets NDC 46708-266-71 bottle of 500 tablets NDC 46708-266-91 bottle of 1000 tablets NDC 46708-266-10 carton of 100 (10X10) unit dose tablets Storage Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Dispense in a tight, light-resistant container as defined in the USP.
📋 Description ▾
11 DESCRIPTION Ropinirole extended-release tablets contains ropinirole, a non-ergoline dopamine agonist as the hydrochloride salt. The chemical name of ropinirole hydrochloride is 4-[2-(dipropylamino)ethyl]-1,3-dihydro-2H-indol-2-one and the empirical formula is C 16 H 24 N 2 O•HCl. The molecular weight is 296.84 (260.38 as the free base).
The structural formula is: Ropinirole hydrochloride is a white to yellow solid with a melting range of 243° to 250°C and a solubility of 133 mg/mL in water. Each capsule shaped, film coated tablet contains 2.28 mg, 4.56 mg, 6.84 mg, 9.12 mg, or 13.68 mg ropinirole hydrochloride equivalent to ropinirole 2 mg, 4 mg, 6 mg, 8 mg, or 12 mg, respectively. Inactive ingredients consist of carboxymethylcellulose sodium, colloidal silicon dioxide, hydrogenated castor oil, hypromellose, magnesium stearate, povidone, pregelatinized starch, ethylcellulose and one or more of the following: FD&C Blue No.
2 aluminum lake, ferric oxides (black, red, yellow), polyethylene glycol 6000, polyethylene glycol 8000, titanium dioxide, talc. Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advice the patient to read the FDA-approved patient labeling (Patient Information). Dosing Instructions Instruct patients to take ropinirole extended-release tablets only as prescribed. If a dose is missed, advise patients not to double their next dose.
Ropinirole extended-release tablets can be taken with or without food. Inform patients to swallow ropinirole extended-release tablets whole and not to chew, crush, or divide the tablets [see Dosage and Administration (2.1)] . Ropinirole is the active ingredient in both ropinirole extended-release tablets and ropinirole tablets (the immediate-release formulation).
Ask your patients if they are taking another medication containing ropinirole. Hypersensitivity/Allergic Reactions Advise patients about the potential for developing a hypersensitivity/allergic reaction including manifestations such as urticaria, angioedema, rash, and pruritus when taking any ropinirole product. Inform patients who experience these or similar reactions after starting ropinirole tablets or ropinirole extended-release tablets, to immediately contact their healthcare professional [see Contraindications (4)] .
Falling Asleep during Activities of Daily Living and Somnolence Alert patients to the potential sedating effects caused by ropinirole extended-release tablets, including somnolence and the possibility of falling asleep while engaged in activities of daily living. Because somnolence is a frequent adverse reaction with potentially serious consequences, patients should not drive a car, operate machinery, or engage in other potentially dangerous activities until they have gained sufficient experience with ropinirole extended-release tablets to gauge whether or not it affects their mental and/or motor performance adversely.
Advise patients that if increased somnolence or episodes of falling asleep during activities of daily living (e.g., conversations, eating, driving a motor vehicle, etc.) are experienced at any time during treatment, they should not drive or participate in potentially dangerous activities until they have contacted their physician. Advise patients of possible additive effects when patients are taking other sedating medications, alcohol, or other central nervous system depressants (e.g., benzodiazepines, antipsychotics, antidepressants, etc.) in combination with ropinirole extended-release tablets or when taking a concomitant medication (e.g., ciprofloxacin) that increases plasma levels of ropinirole [see Warnings and Precautions (5.1)] .
Syncope and Hypotension/Orthostatic Hypotension Advise patients that they may experience syncope and may develop hypotension with or without symptoms such as dizziness, nausea, syncope, and sometimes sweating while taking ropinirole extended-release tablets, especially if they are elderly. Hypotension and/or orthostatic symptoms may occur more frequently during initial therapy or with an increase in dose at any time (cases have been seen after weeks of treatment). Postural/orthostatic symptoms may be related to sitting up or standing.
Accordingly, caution patients against standing rapidly after sitting or lying down, especially if they have been doing so for prolonged periods and especially at the initiation of treatment with ropinirole extended-release tablets [see Warnings and Precautions (5.2, 5.3)] . Elevation of Blood Pressure and Changes in Heart Rate Alert patients to the possibility of increases in blood pressure during treatment with ropinirole extended-release tablets. Exacerbation of hypertension may occur.
Medication dose adjustment may be necessary if elevation of blood pressure is sustained over multiple evaluations. Alert patients with cardiovascular disease, who may not tolerate marked changes in heart rate, to the possibility that they may experience significant increases or decreases in heart rate during treatment with ropinirole extended-release tablets [see Warnings and Precautions (5.4)] . Hallucinat…