
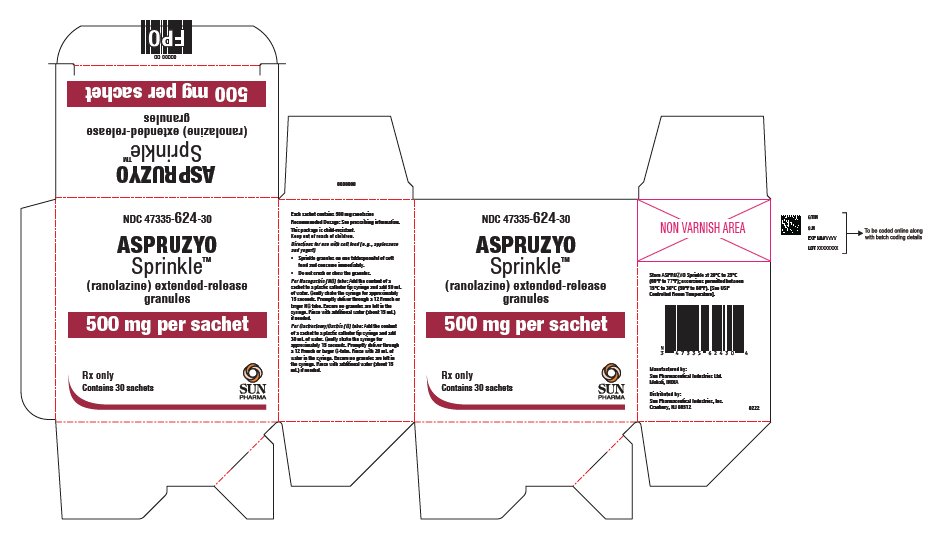
ASPRUZYO SPRINKLE Ranolazine 1000 mg Granule, 30-count
Other active recalls for Ranolazine (different manufacturers) — 2 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Anti-anginal class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Ranolazine is specifically for chronic angina — the recurring chest pain or tightness you get when your heart isn't getting enough blood flow. It's not a heart attack treatment or...
- What exactly is ranolazine supposed to do for me?
- If you're taking the extended-release tablet (Ranexa or generic ranolazine), you can take it with or without food — your choice. The important thing is to swallow it whole. Never c...
- Do I have to take this with food? And can I split the tablet?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Ranolazine — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 4W5IH7FLNY
A clear, oily liquid derived from sebacic acid and butanol. It works as a plasticizer and solvent in pharmaceutical coatings and films, helping them stay flexible and smooth.
-
UNII 905HNO1SIH
A synthetic polymer made from methacrylate compounds that forms a film coating on tablets or capsules. It helps control how quickly the medicine dissolves and releases its active ingredient in the digestive system.
-
UNII 7Z8S9VYZ4B
Ethylcellulose is a plant-derived thickener and film-former made by chemically modifying cellulose. It's used as a binder to hold tablet ingredients together, a coating to control how quickly medicine is released, or a thickener in liquid formulations.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII NX76LV5T8J
A synthetic plastic polymer made from methacrylic acid and ethyl acrylate. It's used as a coating or binder to control how and where the medicine dissolves in your digestive system.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per g | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Aspruzyo Sprinkle 1000 mgthis 47335-0625-30 | SUN | 30 granules | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 11510878 ↗ | Drug product | — | Jan 24, 2038 |
| US 12161761 ↗ | Drug product | — | Jan 24, 2038 |
| US 10898444 ↗ | Drug product | — | Jan 24, 2038 |
| US 11510878 ↗ | Drug product | — | Jan 24, 2038 |
Is there a generic version of ASPRUZYO SPRINKLE ER 1000MG PK?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 47335-0625-11 | 1 GRANULE in 1 PACKET (47335-625-11) | 2022-02-28 | Active |
| 47335-0625-30 You're viewing this | 30 GRANULE in 1 CARTON (47335-625-30) | 2022-02-28 | Active |
| 47335-0625-60 | 60 GRANULE in 1 CARTON (47335-625-60) | 2022-02-28 | Active |
You're viewing one of 3 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 47335-0625-30?
What is the difference between NDC 47335-0625-30 and NDC 47335-0625-11?
What NDC number is used to bill for this package of ASPRUZYO SPRINKLE Ranolazine 1000 mg Granule?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ASPRUZYO Sprinkle is indicated for the treatment of chronic angina. ASPRUZYO Sprinkle may be used with beta-blockers, nitrates, calcium channel blockers, anti‑platelet therapy, lipid-lowering therapy, ACE inhibitors, and angiotensin receptor blockers. ASPRUZYO Sprinkle is an antianginal indicated for the treatment of chronic angina. (1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION 500 mg orally twice daily and increase to 1000 mg orally twice daily, based on clinical symptoms (2.1)
2.1Dosing Information Initiate ASPRUZYO Sprinkle dosing at 500 mg orally twice daily and increase to 1000 mg orally twice daily, as needed, based on clinical symptoms. The maximum recommended daily dose of ASPRUZYO Sprinkle is 1000 mg twice daily. If a dose of ASPRUZYO Sprinkle is missed, take the prescribed dose at the next scheduled time; do not double the next dose.
Directions for use with soft food (e.g., applesauce and yogurt) Sprinkle granules on one tablespoonful of soft food and consume immediately. Do not crush or chew the granules. Direction for nasogastric and gastric tube administration Nasogastric (NG) tube: Add the content of a sachet to a plastic catheter tip syringe and add 50 mL of water.
Gently shake the syringe for approximately 15 seconds. Promptly deliver through a 12 French or larger NG tube. Ensure no granules are left in the syringe.
Rinse with additional water (about 15 mL) if needed. Gastrostomy/Gastric (G) tube : Add the content of a sachet to a plastic catheter tip syringe and add 30 mL of water. Gently shake the syringe for approximately 15 seconds.
Promptly deliver through a 12 French or larger G-tube. Rinse with 20 mL of water in the syringe. Ensure no granules are left in the syringe.
Rinse with additional water (about 15 mL) if needed.
2.2Dose Modification Dose adjustments may be needed when ASPRUZYO Sprinkle is taken in combination with other drugs [see Drug Interactions (7.1)]. Limit the maximum dose of ASPRUZYO Sprinkle to 500 mg twice daily in patients on moderate CYP3A inhibitors such as diltiazem, verapamil, and erythromycin. Use of ASPRUZYO Sprinkle with strong CYP3A inhibitors and CYP3A inducers is contraindicated [see Contraindications (4), Drug Interactions (7.1)].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS ASPRUZYO Sprinkle (ranolazine) is supplied as unit-dose sachets containing 500 or 1000 mg of white to off-white, coated, extended-release granules. Extended-release granules: 500 and 1000 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS ASPRUZYO Sprinkle is contraindicated in patients: Taking strong inhibitors of CYP3A [see Drug Interactions (7.1)] Taking inducers of CYP3A [see Drug Interactions (7.1)] With liver cirrhosis [see Use in Specific Populations (8.6)] Strong CYP3A inhibitors (e.g., ketoconazole, clarithromycin, nelfinavir) (4, 7.1) CYP3A inducers (e.g., rifampin, phenobarbital, St. John's wort) (4, 7.1) Liver cirrhosis (4, 8.6)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS QT interval prolongation: Can occur with ranolazine. Little information available on high doses, long exposure, use with QT interval‑ prolonging drugs, potassium channel variants causing prolonged QT interval, in patients with a family history of (or congenital) long QT syndrome, or in patients with known acquired QT interval prolongation. (5.1) Renal failure: Monitor renal function after initiation and periodically in patients with moderate to severe renal impairment (CrCL <60 mL/min).
If acute renal failure develops, discontinue ASPRUZYO Sprinkle. (5.2)
5.1QT Interval Prolongation Ranolazine blocks I Kr and prolongs the QT c interval in a dose-related manner. Clinical experience in an acute coronary syndrome population did not show an increased risk of proarrhythmia or sudden death [see Clinical Studies (14.2)]. However, there is little experience with high doses (> 1000 mg twice daily) or exposure, other QT‑prolonging drugs, potassium channel variants resulting in a long QT interval, in patients with a family history of (or congenital) long QT syndrome, or in patients with known acquired QT interval prolongation.
5.2Renal Failure Acute renal failure has been observed in patients with severe renal impairment (creatinine clearance [CrCL] < 30 mL/min) while taking ranolazine. If acute renal failure develops (e.g., marked increase in serum creatinine associated with an increase in blood urea nitrogen [BUN]), discontinue ASPRUZYO Sprinkle and treat appropriately [see Use in Specific Populations (8.7)]. Monitor renal function after initiation and periodically in patients with moderate to severe renal impairment (CrCL < 60 mL/min) for increases in serum creatinine accompanied by an increase in BUN.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (> 4% and more common than with placebo) are dizziness, headache, constipation, nausea. (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Sun Pharmaceutical Industries, Inc. at 1-800-818-4555 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. A total of 2018 patients with chronic angina were treated with ranolazine in controlled clinical trials. Of the patients treated with ranolazine, 1026 were enrolled in three double‑blind, placebo-controlled, randomized studies (CARISA, ERICA, MARISA) of up to 12 weeks' duration.
In addition, upon study completion, 1251 patients received treatment with ranolazine in open-label, long-term studies; 1227 patients were exposed to ranolazine for more than 1 year, 613 patients for more than 2 years, 531 patients for more than 3 years, and 326 patients for more than 4 years. At recommended doses, about 6% of patients discontinued treatment with ranolazine because of an adverse event in controlled studies in angina patients compared to about 3% on placebo. The most common adverse events that led to discontinuation more frequently on ranolazine than placebo were dizziness (1.3% versus 0.1%), nausea (1% versus 0%), asthenia, constipation, and headache (each about 0.5% versus 0%).
Doses above 1000 mg twice daily are poorly tolerated. In controlled clinical trials of angina patients, the most frequently reported treatment‑emergent adverse reactions (> 4% and more common on ranolazine than on placebo) were dizziness (6.2%), headache (5.5%), constipation (4.5%), and nausea (4.4%). Dizziness may be dose-related.
In open-label, long-term treatment studies, a similar adverse reaction profile was observed. The following additional adverse reactions occurred at an incidence of 0.5 to 4.0% in patients treated with ranolazine and were more frequent than the incidence observed in placebo-treated patients: Cardiac Disorders- bradycardia, palpitations Ear and Labyrinth Disorders- tinnitus, vertigo Eye Disorders- blurred vision Gastrointestinal Disorders- abdominal pain, dry mouth, vomiting, dyspepsia General Disorders and Administrative Site Adverse Events- asthenia, peripheral edema Metabolism and Nutrition Disorders- anorexia Nervous System Disorders- syncope (vasovagal) Psychiatric Disorders- confusional state Renal and Urinary Disorders- hematuria Respiratory, Thoracic, and Mediastinal Disorders- dyspnea Skin and Subcutaneous Tissue Disorders- hyperhidrosis Vascular Disorders- hypotension, orthostatic hypotension Other (< 0.5%) but potentially medically important adverse reactions observed more frequently with ranolazine than placebo treatment in all controlled studies included: angioedema, renal failure, eosinophilia, chromaturia, blood urea increased, hypoesthesia, paresthesia, tremor, pulmonary fibrosis, thrombocytopenia, leukopenia, and pancytopenia.
A large clinical trial in acute coronary syndrome patients was unsuccessful in demonstrating a benefit for ranolazine, but there was no apparent proarrhythmic effect in these high-risk patients [see Clinical Studies (14.2)]. Laboratory Abnormalities : Ranolazine produces elevations of serum creatinine by 0.1 mg/dL, regardless of previous renal function, likely because of inhibition of creatinine's tubular secretion. In general, the elevation has a rapid onset, shows no signs of progression during long-term therapy, is reversible after discontinuation of ranolazine, and is not accompanied by changes in BUN.
In healthy volunteers, ranolazine 1000 mg twice daily had no effect upon the glomerular filtration rate. More marked and progressive increases in serum creatinine, associated with increases in BUN or potassium, indica…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Moderate CYP3A inhibitors (e.g., diltiazem, verapamil, erythromycin): Limit ASPRUZYO Sprinkle to 500 mg twice daily. (7.1) P-gp inhibitors (e.g., cyclosporine): Ranolazine exposure increased. Titrate ASPRUZYO Sprinkle based on clinical response.
(7.1) CYP3A substrates: Limit simvastatin to 20 mg when used with ASPRUZYO Sprinkle. Doses of other sensitive CYP3A substrates (e.g., lovastatin) and CYP3A substrates with narrow therapeutic range (e.g., cyclosporine, tacrolimus, sirolimus) may need to be reduced with ASPRUZYO Sprinkle. (7.2) OCT2 substrates: Limit the dose of metformin to 1700 mg daily when used with ASPRUZYO Sprinkle 1000 mg twice daily.
Doses of other OCT2 substrates may require adjusted doses. (7.2) Drugs transported by P-gp (e.g., digoxin), or drugs metabolized by CYP2D6 (e.g., tricyclic antidepressants) may need reduced doses when used with ASPRUZYO Sprinkle. (7.2)
7.1Effects of Other Drugs on Ranolazine Strong CYP3A Inhibitors Concomitant use of ASPRUZYO Sprinkle with strong CYP3A inhibitors, including ketoconazole, itraconazole, clarithromycin, nefazodone, nelfinavir, ritonavir, indinavir, and saquinavir is contraindicated [see Contraindications (4), Clinical Pharmacology (12.3)]. Moderate CYP3A Inhibitors Limit the dose of ASPRUZYO Sprinkle to 500 mg twice daily in patients on moderate CYP3A inhibitors, including diltiazem, verapamil, erythromycin, fluconazole, and grapefruit juice or grapefruit-containing products [see Dosage and Administration (2.2), Clinical Pharmacology (12.3)].
P-gp Inhibitors Concomitant use of ASPRUZYO Sprinkle and P-gp inhibitors, such as cyclosporine, may result in increases in ranolazine concentrations. Titrate ASPRUZYO Sprinkle based on clinical response in patients concomitantly treated with predominant P-gp inhibitors such as cyclosporine [see Dosage and Administration (2.2)]. CYP3A Inducers Concomitant use of ASPRUZYO Sprinkle with CYP3A inducers such as rifampin, rifabutin, rifapentine, phenobarbital, phenytoin, carbamazepine, and St.
John's wort is contraindicated [see Contraindications (4), Clinical Pharmacology (12.3)]. Alcohol An in-vitro dissolution study was conducted to evaluate the impact of alcohol on extended-release characteristics of ASPRUZYO Sprinkle. The in-vitro study showed that alcohol causes a rapid release of ranolazine from ASPRUZYO Sprinkle that may increase the risk of adverse events associated with ASPRUZYO Sprinkle.
Patients should not consume alcohol when taking ASPRUZYO Sprinkle [see Clinical Pharmacology (12.3)] .
7.2Effects of Ranolazine on Other Drugs Drugs Metabolized by CYP3A Limit the dose of simvastatin in patients on any dose of ASPRUZYO Sprinkle to 20 mg once daily, when ASPRUZYO Sprinkle is co-administered. Dose adjustment of other sensitive CYP3A substrates (e.g., lovastatin) and CYP3A substrates with a narrow therapeutic range (e.g., cyclosporine, tacrolimus, sirolimus) may be required as ASPRUZYO Sprinkle may increase plasma concentrations of these drugs [see Clinical Pharmacology (12.3)]. Drugs Transported by P-gp Concomitant use of ASPRUZYO Sprinkle and digoxin results in increased exposure to digoxin.
The dose of digoxin may have to be adjusted [see Clinical Pharmacology (12.3)]. Drugs Metabolized by CYP2D6 The exposure to CYP2D6 substrates, such as tricyclic antidepressants and antipsychotics, may be increased during co-administration with ASPRUZYO Sprinkle, and lower doses of these drugs may be required. Drugs Transported by OCT2 In subjects with type 2 diabetes mellitus, concomitant use of ASPRUZYO Sprinkle 1000 mg twice daily and metformin results in increased plasma levels of metformin.
When ASPRUZYO Sprinkle 1000 mg twice daily is co-administered with metformin, metformin dose should not exceed 1700 mg/day. Monitor blood glucose levels and risks associated with high exposures of metformin. Metformin exposure was not significantly increased when given with ranolazine 500 mg twice daily [see Clinical Pharmacolog…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no available data on ranolazine use in pregnant women to inform any drug‑associated risks. Studies in rats and rabbits showed no evidence of fetal harm at exposures 4 times the maximum recommended human dose (MRHD) (see Data). In the U.S. general population, the estimated background risk of major birth defects and of miscarriage of clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data Embryofetal toxicity studies were conducted in rats and rabbits orally administered ranolazine during organogenesis. In rats, decreased fetal weight and reduced ossification were observed at doses (corresponding to 4-fold the AUC for the MRHD) that caused maternal weight loss. No adverse fetal effects were observed in either species exposed (AUC) to ranolazine at exposures (AUC) equal to the MRHD.
8.2Lactation Risk Summary There are no data on the presence of ranolazine in human milk, the effects on the breastfed infant, or the effects on milk production. However, ranolazine is present in rat milk [see Use in Specific Populations (8.1)]. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for ranolazine and any potential adverse effects on the breastfed infant from ranolazine or from the underlying maternal condition.
Adult female rats were administered ranolazine orally from gestation day 6 through postnatal day 20. No adverse effects on pup development, behavior, or reproduction parameters were observed at a maternal dosage level of 60 mg/kg/day (equal to the MHRD based on AUC). At maternally toxic doses, male and female pups exhibited increased mortality and decreased body weight, and female pups showed increased motor activity.
The pups were potentially exposed to low amounts of ranolazine via the maternal milk.
8.4Pediatric Use Safety and effectiveness have not been established in pediatric patients.
8.5Geriatric Use Of the chronic angina patients treated with ranolazine in controlled studies, 496 (48%) were ≥ 65 years of age, and 114 (11%) were ≥ 75 years of age. No overall differences in efficacy were observed between older and younger patients. There were no differences in safety for patients ≥ 65 years compared to younger patients, but patients ≥ 75 years of age on ranolazine, compared to placebo, had a higher incidence of adverse events, serious adverse events, and drug discontinuations due to adverse events.
In general, dose selection for an elderly patient should usually start at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease, or other drug therapy.
8.6Use in Patients with Hepatic Impairment ASPRUZYO Sprinkle is contraindicated in patients with liver cirrhosis. In a study of cirrhotic patients, the C max of ranolazine was increased 30% in cirrhotic patients with mild (Child‑ Pugh Class A) hepatic impairment but increased 80% in cirrhotic patients with moderate (Child-Pugh Class B) hepatic impairment compared to patients without hepatic impairment. This increase was not enough to account for the 200% increase in QT prolongation seen in cirrhotic patients with mild to moderate hepatic impairment [see Clinical Pharmacology (12.2)].
8.7Use in Patients with Renal Impairment A pharmacokinetic study of ranolazine in subjects with severe renal impairment (CrCL< 30 mL/min) was stopped when 2 of 4 subjects developed acute renal failure after receiving ranolazine 500 mg twice daily for 5 days (lead-in phase) followed by 1000 mg twice a day (1 dose in one subject and 11 doses in the other). Increases in creatinine, BUN, and potassium were observed in 3 subjects during the 500 mg lead-in phase. One subject required hemodialysis, while the other 2 subjects improved upon drug discontinuation [s ee Warnings and Precautions (5.2)].
Monitor renal function periodically in patients with moder…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no available data on ranolazine use in pregnant women to inform any drug‑associated risks. Studies in rats and rabbits showed no evidence of fetal harm at exposures 4 times the maximum recommended human dose (MRHD) (see Data). In the U.S. general population, the estimated background risk of major birth defects and of miscarriage of clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data Embryofetal toxicity studies were conducted in rats and rabbits orally administered ranolazine during organogenesis. In rats, decreased fetal weight and reduced ossification were observed at doses (corresponding to 4-fold the AUC for the MRHD) that caused maternal weight loss. No adverse fetal effects were observed in either species exposed (AUC) to ranolazine at exposures (AUC) equal to the MRHD.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness have not been established in pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the chronic angina patients treated with ranolazine in controlled studies, 496 (48%) were ≥ 65 years of age, and 114 (11%) were ≥ 75 years of age. No overall differences in efficacy were observed between older and younger patients. There were no differences in safety for patients ≥ 65 years compared to younger patients, but patients ≥ 75 years of age on ranolazine, compared to placebo, had a higher incidence of adverse events, serious adverse events, and drug discontinuations due to adverse events.
In general, dose selection for an elderly patient should usually start at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease, or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Hypotension, QT prolongation, bradycardia, myoclonic activity, severe tremor, unsteady gait/incoordination, dizziness, nausea, vomiting, dysphasia, and hallucinations have been seen in cases of oral overdose of ranolazine. In cases of extreme overdose of ranolazine fatal outcomes have been reported. In clinical studies, high intravenous exposure resulted in diplopia, paresthesia, confusion, and syncope.
In addition to general supportive measures, continuous ECG monitoring may be warranted in the event of overdose. Since ranolazine is about 62% bound to plasma proteins, hemodialysis is unlikely to be effective in clearing ranolazine.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism of action of ranolazine's antianginal effects has not been determined. Ranolazine has anti-ischemic and antianginal effects that do not depend upon reductions in heart rate or blood pressure. It does not affect the rate-pressure product, a measure of myocardial work, at maximal exercise.
Ranolazine at therapeutic levels can inhibit the cardiac late sodium current (I Na ). However, the relationship of this inhibition to angina symptoms is uncertain. The QT prolongation effect of ranolazine on the surface electrocardiogram is the result of inhibition of I Kr which prolongs the ventricular action potential.
12.2Pharmacodynamics Hemodynamic Effects Patients with chronic angina treated with ranolazine in controlled clinical studies had minimal changes in mean heart rate (< 2 bpm) and systolic blood pressure (< 3 mm Hg). Similar results were observed in subgroups of patients with CHF NYHA Class I or II, diabetes, or reactive airway disease, and in elderly patients. Electrocardiographic Effects Dose and plasma concentration-related increases in the QT c interval [see Warnings and Precautions (5.1)], reductions in T wave amplitude, and, in some cases, notched T waves, have been observed in patients treated with ranolazine.
These effects are believed to be caused by ranolazine and not by its metabolites. The relationship between the change in QT c and ranolazine plasma concentrations is linear, with a slope of about 2.6 msec/1000 ng/mL, through exposures corresponding to doses several-fold higher than the maximum recommended dose of 1000 mg twice daily. The variable blood levels attained after a given dose of ranolazine give a wide range of effects on QT c .
At T max following repeat dosing at 1000 mg twice daily, the mean change in QT c is about 6 msec, but in the 5% of the population with the highest plasma concentrations, the prolongation of QT c is at least 15 msec. In cirrhotic subjects with mild or moderate hepatic impairment, the relationship between plasma level of ranolazine and QT c is much steeper [see Contraindications (4)]. Age, weight, gender, race, heart rate, congestive heart failure, diabetes, and renal impairment did not alter the slope of the QT c -concentration relationship of ranolazine.
No proarrhythmic effects were observed on 7-day Holter recordings in 3,162 acute coronary syndrome patients treated with ranolazine. There was a significantly lower incidence of arrhythmias (ventricular tachycardia, bradycardia, supraventricular tachycardia, and new atrial fibrillation) in patients treated with ranolazine (80%) versus placebo (87%), including ventricular tachycardia ≥ 3 beats (52% versus 61%). However, this difference in arrhythmias did not lead to a reduction in mortality, a reduction in arrhythmia hospitalization, or a reduction in arrhythmia symptoms.
12.3Pharmacokinetics The pharmacokinetic parameter of ranolazine after single dose administration of 1000 mg ASPRUZYO Sprinkle under fasting conditions are summarized in table 1. Table 1: Pharmacokinetic parameters of ranolazine after single dose administration of 1000 mg ASPRUZYO Sprinkle under fasting conditions. Parameter ASPRUZYO Sprinkle Mean CV (%) C max (mcg/mL) 1.95 30 T max (hr) * 10 (2 to 16) AUC 0-t (mcg.hr/mL) 31.4 36 AUC 0-∞ (mcg.hr/mL) 31.7 36 T 1/2 (hr) 5.3 27 Kel (hr -1 ) 0.15 29 *Median range (min-max) is provided Ranolazine is extensively metabolized in the gut and liver and its absorption is highly variable.
The pharmacokinetics of the (+) R-and (-) S-enantiomers of ranolazine are similar in healthy volunteers. Steady state is generally achieved within 3 days of twice-daily dosing with ranolazine. At steady state over the dose range of 500 to 1000 mg twice daily, C max and AUC 0-T increase slightly more than proportionally to dose, 120% and 140%, respectively.
With twice-daily dosing, the trough:peak ratio of the ranolazine plasma concentration is 0.3 to 0.6. The pharmacokinetics o…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of action of ranolazine's antianginal effects has not been determined. Ranolazine has anti-ischemic and antianginal effects that do not depend upon reductions in heart rate or blood pressure. It does not affect the rate-pressure product, a measure of myocardial work, at maximal exercise.
Ranolazine at therapeutic levels can inhibit the cardiac late sodium current (I Na ). However, the relationship of this inhibition to angina symptoms is uncertain. The QT prolongation effect of ranolazine on the surface electrocardiogram is the result of inhibition of I Kr which prolongs the ventricular action potential.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING ASPRUZYO Sprinkle is supplied as white to off-white coated, extended-release granules in sachets of 500 or 1000 mg. Packages are Strength NDC Unit-dose Sachet (Child-resistant) 500 mg NDC 47335-624-11 Unit-dose Sachet (Child-resistant) 1000 mg NDC 47335-625-11 30 Unit-dose Sachets (Child-resistant) 500 mg NDC 47335-624-30 30 Unit-dose Sachets (Child-resistant) 1000 mg NDC 47335-625-30 60 Unit-dose Sachets (Child-resistant) 500 mg NDC 47335-624-60 60 Unit-dose Sachets (Child-resistant) 1000 mg NDC 47335-625-60 Store ASPRUZYO Sprinkle at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C to 30°C (59°F to 86°F). [See USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION ASPRUZYO Sprinkle contains ranolazine, an antianginal available as white to off-white coated extended-release granules filled in a sachet for oral administration. Ranolazine is a racemic mixture, chemically described as 1-piperazineacetamide, N ‑(2,6-dimethylphenyl)-4-[2-hydroxy-3-(2-methoxyphenoxy)propyl]-(±)-. It has a molecular formula of C 24 H 33 N 3 O 4 , a molecular weight of 427.54 g/mole, and the following structural formula: Ranolazine is off-white to white powder.
Ranolazine is soluble in dichloromethane and methanol. ASPRUZYO Sprinkle contains 500 mg or 1000 mg of ranolazine and the following inactive ingredients: amino methacrylate copolymer, dibutyl sebacate, ethyl cellulose, hypromellose, magnesium stearate, methacrylic acid and ethyl acrylate copolymer, microcrystalline cellulose, and talc. structural-formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Inform patients that ASPRUZYO Sprinkle will not abate an acute angina episode. Drug Interactions Advise patients to discuss with their healthcare provider any prescription or over-the-counter medications and supplements prior to concomitant use [see Drug Interactions (7)].
Advise patients to limit grapefruit juice or grapefruit products when taking ASPRUZYO Sprinkle [see Drug Interactions (7)] . QT Interval Prolongation Advise patients to inform their physician of any personal or family history of QT c prolongation, congenital long QT syndrome, or if they are receiving drugs that prolong the QT c interval such as [see Warnings and Precautions (5.1)]. Dizziness, Fainting Inform patients that ASPRUZYO Sprinkle may cause dizziness and lightheadedness.
Patients should know how they react to ASPRUZYO Sprinkle before they operate an automobile or machinery, or engage in activities requiring mental alertness or coordination [see Adverse Reactions (6.1)]. Advise patients to contact their physician if they experience fainting spells while taking ASPRUZYO Sprinkle. Administration Instruct patients to take ASPRUZYO Sprinkle as directed.
Advise patients not to crush or chew the granules. All trademarks are the property of their respective owners. Manufactured by: Sun Pharmaceutical Industries Ltd.
Mohali, INDIA Distributed by: Sun Pharmaceutical Industries, Inc. Cranbury, NJ 08512 FDA-04
💬 Patient Medication Information ▾
Patient Medication Information Patient Information ASPRUZYO Sprinkle (as-PROO-zee-oh spring-KUHL) (ranolazine) extended-release granules What is ASPRUZYO Sprinkle? ASPRUZYO Sprinkle is a prescription medicine used to treat angina that keeps coming back (chronic angina). ASPRUZYO Sprinkle may be used with other medicines that are used for heart problems and blood pressure control.
It is not known if ASPRUZYO Sprinkle is safe and effective in children. Do not take ASPRUZYO Sprinkle if: you take any of the following medicines: for fungus infection: ketoconazole, itraconazole for infection: clarithromycin for depression: nefazodone for HIV: nelfinavir, ritonavir, indinavir saquinavir for tuberculosis (TB): rifampin, rifabutin, rifapentine for seizures: phenobarbital, phenytoin, and carbamazepine St. John's wort you have scarring of your liver (liver cirrhosis) Before taking ASPRUZYO Sprinkle, tell your healthcare provider about all of your medical conditions, including if you: have or have a family history of a heart problem, called 'QT prolongation' or 'long QT syndrome' have liver problems have kidney problems are pregnant or plan to become pregnant.
It is not known if ASPRUZYO Sprinkle will harm your unborn baby. are breastfeeding or plan to breastfeed. It is not known if ranolazine passes into your breast milk. Talk to your healthcare provider about the best way to feed your baby.
Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements. ASPRUZYO Sprinkle may affect the way other medicines work and other medicines may affect how ASPRUZYO Sprinkle works. Know the medicines you take.
Keep a list of them to show your healthcare provider or pharmacist when you get a new medicine. How should I take ASPRUZYO Sprinkle? Take ASPRUZYO Sprinkle exactly as your healthcare provider tells you.
Your healthcare provider will tell you how much ASPRUZYO Sprinkle to take and when to take it. Do not change your dose unless your healthcare provider tells you to. Tell your healthcare provider if you still have symptoms of angina after starting ASPRUZYO Sprinkle.
Take ASPRUZYO Sprinkle 2 times a day. ASPRUZYO Sprinkle may be taken or given as follows: To open the sachet fold back on dotted line and tear at notch or use scissors. Directions for use with soft food (e.g., applesauce and yogurt): Sprinkle granules on one tablespoonful of soft food and consume immediately.
Do not crush or chew the granules. Giving ASPRUZYO Sprinkle with water through a 12 French or larger nasogastric (NG) tube : Add the granules from the sachet to a plastic catheter tip syringe and add 50 mL of water. Gently shake the syringe for about 15 seconds.
Connect the catheter tip syringe to the NG tube and give the mixture right away. Make sure that no granules are left in the syringe. Rinse the syringe with about 15 mL of additional water if needed and give through NG tube.
Giving ASPRUZYO Sprinkle with water through a 12 French or larger gastric (G) tube: Add the granules from the sachet to a plastic catheter tip syringe and add 30 mL of water. Gently shake the syringe for about 15 seconds. Connect the catheter tip syringe to the G-tube and give the mixture right away.
Rinse the syringe with 20 mL of additional water and give through G-tube. Make sure that no granules are left in the syringe. Rinse the syringe with about 15 mL of additional water if needed and give through G-tube.
If you miss a dose of ASPRUZYO Sprinkle, take the next dose of ASPRUZYO Sprinkle at your regular time. Do not make up for the missed dose. Do not take 2 doses at the same time.
If you take too much ASPRUZYO Sprinkle, call your healthcare provider, or go to the nearest emergency room right away. What should I avoid while taking ASPRUZYO Sprinkle? You should limit grapefruit, grapefruit juice, and products that contain grapefruit during treatment with ASPRUZYO Sprinkle.
Grapefruit products can increase the a…