
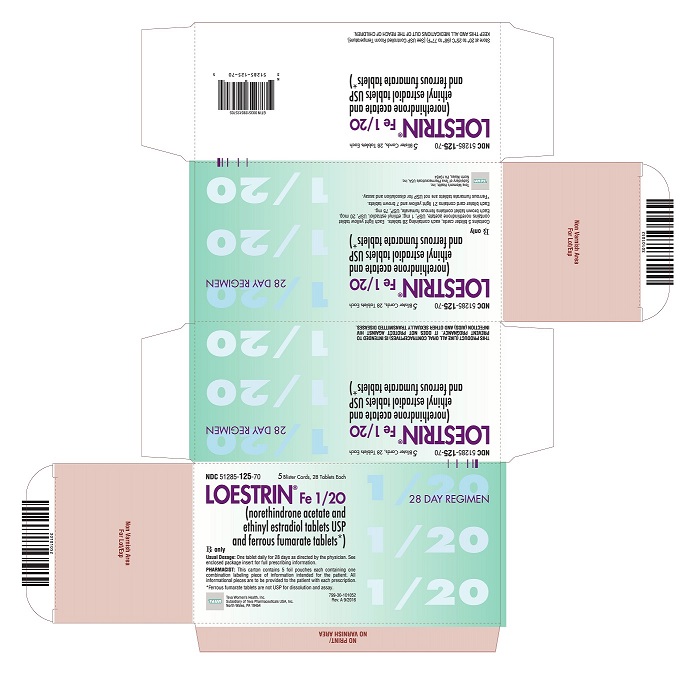
Loestrin Fe 28 Day Norethindrone Acetate and Ethinyl Estradiol and Ferrous Fumarate Kit, 5 pouches — NDC 51285-125-70 (Billing 51285-0125-70)
This is a package of 5 pouches of Loestrin Fe 28 Day Norethindrone Acetate and Ethinyl Estradiol and Ferrous Fumarate Kit from Teva Women's Health LLC, marketed since Feb 2015 and currently FDA-listed; retail pharmacies pay about $8.23 per pouche (NADAC). It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 003301
- GCN: 68102
- GPI-14 (Medi-Span): 25990003610310
- HICL (First Databank): 001454
- AHFS class code: 68:12.00.00
- RxCUI (RxNorm): 259176
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Iron bivalent, oral preparations class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Oral contraceptives (birth-control pills) containing ethinyl estradiol (an estrogen) and norethindrone (a progestin) are used to prevent pregnancy. Estrogen and progestin are two female sex hormones. Combinations of estrogen and progestin work mainly by preventing ovulation (the release of eggs from the ovaries). Oral contraceptives are an effective method of birth control, but they do not prevent the spread of human immunodeficiency virus (HIV, the virus that causes acquired immunodeficiency syndrome [AIDS]) and other sexually transmitted diseases.
Read the full MedlinePlus article ↗- Its main job is preventing pregnancy. Some versions, like Xarah Fe and certain generic kits, are also approved for moderate acne in females 15 and older who want birth control and...
- Take one pill by mouth every day at the same time, in the order on your pack. Most 28-day packs have 21 active pills and 7 reminder pills, and you start the next pack the day after...
- If you miss one active pill, take it as soon as you remember and take the next one at your usual time. If you miss two or more active pills, you may need to use back-up birth contr...
- Spotting, light bleeding and nausea are common in the first 1 to 3 packs, and they usually go away. Don't stop the pill because of them. Call your doctor if they continue, or right...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $8.232 | $41.16 / 5 kit |
| Medicaid paysCMS SDUD · 12 mo | $1.87 | $9.33 / 5 kit |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 51285-0125-70 You're viewing this Main listing | 5 POUCH in 1 CARTON / 1 BLISTER PACK in 1 POUCH / 1 KIT in 1 BLISTER PACK | 2015-02-26 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Tarina Fe 1/20 EQ 50102-0228-23 | Afaxys | 3 pouches | $0.129 | AB | Availability likely | save 98% |
| HAILEY Fe 1/20 68462-0419-29 | Glenmark | 1 kit | $0.129 | AB | Availability likely | save 98% |
| Junel Fe 28 Day 00555-9026-58 | Teva | 6 pouches | $0.129 | AB | Availability likely | save 98% |
| Hailey Fe 1.5/30 68462-0503-29 | Glenmark | 3 pouches | $0.142 | AB | Availability likely | save 98% |
| Junel Fe 28 Day 00555-9028-58 | Teva | 6 pouches | $0.142 | AB | Availability likely | save 98% |
| Junel Fe 24 00093-5328-62 | Teva | 3 pouches | $0.175 | AB | Availability likely | save 98% |
| Tarina 24 Fe 50102-0224-23 | Afaxys | 3 pouches | $0.175 | AB | Availability likely | save 98% |
| Finzala 00093-8210-62 | Teva | 12 tablets | $0.304 | AB | Availability likely | save 96% |
| Charlotte 24Fe 68462-0852-29 | Glenmark | 1 kit | $0.304 | AB | Availability likely | save 96% |
| norethindrone acetate and ethinyl estradiol and ferrous fumarate 68462-0376-29 | Glenmark | 1 kit | $0.422 | AB | FDA listed | save 95% |
| Melodetta 24 Fe 69238-1031-07 | Amneal | 1 kit | $0.422 | — | FDA listed | save 95% |
| Norethindrone Acetate And Ethinyl Estradiol And Ferrous Fumarate 00378-7303-53 | Mylan | 21 tablets | $0.788 | AB | Availability likely | save 90% |
| Norethindrone Acetate and Ethinyl Estradiol and Ferrous Fumarate 68462-0849-29 | Glenmark | 24 capsules | $0.962 | AB | Availability likely | save 88% |
| Loestrin Fe 28 Daythis 51285-0125-70 | Teva | 5 pouches | $8.232 | AB | Availability likely | — |
| Junel Fe 28 Day 50090-3237-00 | A-S | 1 kit | — | AB | FDA listed | — |
| Norethindrone Acetate and Ethinyl Estradiol and Ferrous Fumarate 60219-1031-07 | Amneal | 1 kit | — | — | FDA listed | — |
| Aurovela 24 Fe 65862-0934-58 | Aurobindo | 5 pouches | — | AB | FDA listed | — |
| Aurovela Fe 1/20 65862-0940-58 | Aurobindo | 5 pouches | — | AB | FDA listed | — |
| AUROVELA Fe 65862-0941-58 | Aurobindo | 5 pouches | — | AB | FDA listed | — |
| Junel Fe 28 Day 50090-3122-00 | A-S | 6 pouches | — | AB | FDA listed | — |
| Junel Fe 28 Day 63629-5628-01 | Bryant | 6 pouches | — | AB | FDA listed | — |
| Oshih 59651-0504-88 | Aurobindo | 3 pouches | — | — | FDA listed | — |
| Loestrin Fe 28 Day 51285-0128-70 | Teva | 5 pouches | — | AB | FDA listed | — |
| Junel Fe 28 Day 72789-0450-79 | PD-Rx | 1 pouch | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: CIGARETTE SMOKING AND SERIOUS CARDIOVASCULAR EVENTS Cigarette smoking increases the risk of serious cardiovascular events from combination oral contraceptive (COC) use. This risk increases with age, particularly in women over 35 years of age, and with the number of cigarettes smoked. For this reason, COCs, including Loestrin, are contraindicated in women who are over 35 years of age and smoke (see CONTRAINDICATIONS and WARNINGS ).
Cigarette smoking increases the risk of serious cardiovascular side effects from oral contraceptive use. This risk increases with age and with heavy smoking (15 or more cigarettes per day) and is quite marked in women over 35 years of age. Women who use oral contraceptives are strongly advised not to smoke.
Cigarette smoking increases the risk of serious cardiovascular side effects from oral contraceptive use. This risk increases with age and with heavy smoking (15 or more cigarettes per day) and is quite marked in women over 35 years of age. Women who use oral contraceptives are strongly advised not to smoke.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Loestrin 21 and Loestrin Fe 28 are indicated for the prevention of pregnancy in women who elect to use oral contraceptives as a method of contraception. Oral contraceptives are highly effective. Table I lists the typical accidental pregnancy rates for users of combination oral contraceptives and other methods of contraception.
The efficacy of these contraceptive methods, except sterilization, depends upon the reliability with which they are used. Correct and consistent use of methods can result in lower failure rates. TABLE I: LOWEST EXPECTED AND TYPICAL FAILURE RATES DURING THE FIRST YEAR OF CONTINUOUS USE OF A METHOD % Of Women Experiencing an Unintended Pregnancy in the First Year of Continuous Use Method Lowest Expected * Typical ** (No contraception) (85) (85) Oral contraceptives combined progestin only 0.1 0.5 3 N/A *** N/A *** Diaphragm with spermicidal cream or jelly 6 20 Spermicides alone (foam, creams, gels, vaginal suppositories, and vaginal film) 6 26 Vaginal Sponge nulliparous parous 9 20 20 40 Implant 0.05
0.05Injection: depot medroxyprogesterone acetate 0.3
0.3IUD progesterone T copper T 380A LNg 20 1.5 0.6 0.1 2 0.8
0.1Condom without spermicides female male 5 3 21 14 Cervical Cap with spermicidal cream or jelly nulliparous parous 9 26 20 40 Periodic abstinence (all methods) 1 to 9 25 Withdrawal 4 19 Female sterilization 0.5
0.5Male sterilization 0.10
0.15Adapted from RA Hatcher et al, Reference 7. * The authors' best guess of the percentage of women expected to experience an accidental pregnancy among couples who initiate a method (not necessarily for the first time) and who use it consistently and correctly during the first year if they do not stop for any other reason. ** This term represents “typical” couples who initiate use of a method (not necessarily for the first time), who experience an accidental pregnancy during the first year if they do not stop use for any other reason. *** N/A-Data not available.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The tablet dispenser has been designed to make oral contraceptive dosing as easy and as convenient as possible. The tablets are arranged in either three or four rows of seven tablets each, with the days of the week appearing on the tablet dispenser above the first row of tablets. Note: Each tablet dispenser has been preprinted with the days of the week, starting with Sunday, to facilitate a Sunday-Start regimen.
Six different day label strips have been provided with the Detailed Patient & Brief Summary Patient Package Insert in order to accommodate a Day-1 Start regimen. If the patient is using the Day-1 Start regimen, she should place the self-adhesive day label strip that corresponds to her starting day over the preprinted days. Important: The patient should be instructed to use an additional method of protection until after the first week of administration in the initial cycle when utilizing the Sunday-Start regimen.
The possibility of ovulation and conception prior to initiation of use should be considered. Dosage and Administration for 21-Day Dosage Regimen To achieve maximum contraceptive effectiveness, Loestrin 21 must be taken exactly as directed and at intervals not exceeding 24 hours. Loestrin 21 provides the patient with a convenient tablet schedule of “3 weeks on - 1 week off”.
Two dosage regimens are described, one of which may be more convenient or suitable than the other for an individual patient. For the initial cycle of therapy, the patient begins her tablets according to the Day-1 Start or Sunday-Start regimen. With either regimen, the patient takes one tablet daily for 21 consecutive days followed by one week of no tablets.
A. Sunday-Start Regimen: The patient begins taking tablets from the top row on the first Sunday after menstrual flow begins. When menstrual flow begins on Sunday, the first tablet is taken on the same day.
The last tablet in the dispenser will then be taken on a Saturday, followed by no tablets for a week (7 days). For all subsequent cycles, the patient then begins a new 21-tablet regimen on the eighth day, Sunday, after taking her last tablet. Following this regimen, of 21 days on - 7 days off, the patient will start all subsequent cycles on a Sunday.
B. Day-1 Regimen: The first day of menstrual flow is Day 1. The patient places the self-adhesive day label strip that corresponds to her starting day over the preprinted days on the tablet dispenser.
She starts taking one tablet daily, beginning with the first tablet in the top row. The patient completes her 21-tablet regimen when she has taken the last tablet in the tablet dispenser. She will then take no tablets for a week (7 days).
For all subsequent cycles, the patient begins a new 21-tablet regimen on the eighth day after taking her last tablet, again starting with the first tablet in the top row after placing the appropriate day label strip over the preprinted days on the tablet dispenser. Following this regimen of 21 days on - 7 days off, the patient will start all subsequent cycles on the same day of the week as the first course. Likewise, the interval of no tablets will always start on the same day of the week.
Tablets should be taken regularly with a meal or at bedtime. It should be stressed that efficacy of medication depends on strict adherence to the dosage schedule. Special Notes on Administration Menstruation usually begins two or three days, but may begin as late as the fourth or fifth day, after discontinuing medication.
If spotting occurs while on the usual regimen of one tablet daily, the patient should continue medication without interruption. If the patient forgets to take one or more tablets, the following is suggested: One tablet is missed take tablet as soon as remembered take next tablet at the regular time Two consecutive tablets are missed (week 1 or week 2) take two tablets as soon as remembered take two tablets the next day use another birth control method for seven days following the m… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Oral contraceptives are contraindicated in women who currently have the following conditions: Thrombophlebitis or thromboembolic disorders A past history of deep vein thrombophlebitis or thromboembolic disorders Cerebral vascular or coronary artery disease Current diagnosis of, or history of, breast cancer, which may be hormone sensitive Carcinoma of the endometrium or other known or suspected estrogen-dependent neoplasia Undiagnosed abnormal genital bleeding Cholestatic jaundice of pregnancy or jaundice with prior pill use Hepatic adenomas or carcinomas Are receiving Hepatitis C drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir, due to the potential for ALT elevations (see Warnings, RISK OF LIVER ENZYME ELEVATIONS WITH CONCOMITANT HEPATITIS C TREATMENT ).
⚠️ Warnings ▾
WARNINGS The use of oral contraceptives is associated with increased risks of several serious conditions including myocardial infarction, thromboembolism, stroke, hepatic neoplasia, and gallbladder disease, although the risk of serious morbidity or mortality is very small in healthy women without underlying risk factors. The risk of morbidity and mortality increases significantly in the presence of other underlying risk factors such as hypertension, hyperlipidemias, obesity, and diabetes. Practitioners prescribing oral contraceptives should be familiar with the following information relating to these risks.
The information contained in this package insert is principally based on studies carried out in patients who used oral contraceptives with higher formulations of estrogens and progestogens than those in common use today. The effect of long-term use of the oral contraceptives with lower formulations of both estrogens and progestogens remains to be determined. Throughout this labeling, epidemiological studies reported are of two types: retrospective or case control studies and prospective or cohort studies.
Case control studies provide a measure of the relative risk of a disease, namely, a ratio of the incidence of a disease among oral contraceptive users to that among nonusers. The relative risk does not provide information on the actual clinical occurrence of a disease. Cohort studies provide a measure of attributable risk, which is the difference in the incidence of disease between oral contraceptive users and nonusers.
The attributable risk does provide information about the actual occurrence of a disease in the population (adapted from References 8 and 9 with the author's permission). For further information, the reader is referred to a text on epidemiological methods. 1.
Thromboembolic Disorders and Other Vascular Problems a. Myocardial infarction An increased risk of myocardial infarction has been attributed to oral contraceptive use. This risk is primarily in smokers or women with other underlying risk factors for coronary artery disease such as hypertension, hypercholesterolemia, morbid obesity, and diabetes.
The relative risk of heart attack for current oral contraceptive users has been estimated to be two to six (10-16). The risk is very low under the age of 30. Smoking in combination with oral contraceptive use has been shown to contribute substantially to the incidence of myocardial infarctions in women in their mid-thirties or older with smoking accounting for the majority of excess cases (17).
Mortality rates associated with circulatory disease have been shown to increase substantially in smokers over the age of 35 and non-smokers over the age of 40 (Table II) among women who use oral contraceptives. Adapted from P.M. Layde and V.
Beral, Reference 18. Oral contraceptives may compound the effects of well-known risk factors, such as hypertension, diabetes, hyperlipidemias, age and obesity (19). In particular, some progestogens are known to decrease HDL cholesterol and cause glucose intolerance, while estrogens may create a state of hyperinsulinism (20-24).
Oral contraceptives have been shown to increase blood pressure among users (see section 9 in WARNINGS ). Similar effects on risk factors have been associated with an increased risk of heart disease. Oral contraceptives must be used with caution in women with cardiovascular disease risk factors.
Table II b. Thromboembolism An increased risk of thromboembolic and thrombotic disease associated with the use of oral contraceptives is well established. Case control studies have found the relative risk of users compared to non-users to be 3 for the first episode of superficial venous thrombosis, 4 to 11 for deep vein thrombosis or pulmonary embolism, and 1.5 to 6 for women with predisposing conditions for venous thromboembolic disease (9, 10, 25-30).
Cohort studies have shown the relative risk to be somewhat lower, about 3 for new cases and about 4.5 for new cases req… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS An increased risk of the following serious adverse reactions has been associated with the use of oral contraceptives (see WARNINGS section): Thrombophlebitis Arterial thromboembolism Pulmonary embolism Myocardial infarction Cerebral hemorrhage Cerebral thrombosis Hypertension Gallbladder disease Hepatic adenomas or benign liver tumors Post Marketing Experience Five studies that compared breast cancer risk between ever-users (current or past use) of COCs and never-users of COCs reported no association between ever use of COCs and breast cancer risk, with effect estimates ranging from 0.90 - 1.12 (Figure 1) (70-74).
Three studies compared breast cancer risk between current or recent COC users (<6 months since last use) and never users of COCs (Figure 1) (70, 73, 75). One of these studies reported no association between breast cancer risk and COC use. The other two studies found an increased relative risk of 1.19 - 1.33 with current or recent use.
Both of these studies found an increased risk of breast cancer with current use of longer duration, with relative risks ranging from 1.03 with less than one year of COC use to approximately 1.4 with more than 8-10 years of COC use. FIGURE 1: RELEVANT STUDIES OF RISK OF BREAST CANCER WITH COMBINED ORAL CONTRACEPTIVES RR = relative risk; OR = odds ratio; HR = hazard ratio. “ever COC” are females with current or past COC use; “never COC use” are females that never used COCs. There is evidence of an association between the following conditions and the use of oral contraceptives, although additional confirmatory studies are needed: Mesenteric thrombosis Retinal thrombosis The following adverse reactions have been reported in patients receiving oral contraceptives and are believed to be drug-related: Nausea Vomiting Gastrointestinal symptoms (such as abdominal cramps and bloating) Breakthrough bleeding Spotting Change in menstrual flow Amenorrhea Temporary infertility after discontinuation of treatment Edema Melasma which may persist Breast changes: tenderness, enlargement, secretion Change in weight (increase or decrease) Change in cervical erosion and secretion Diminution in lactation when given immediately postpartum Cholestatic jaundice Migraine Rash (allergic) Depression Reduced tolerance to carbohydrates Vaginal candidiasis Change in corneal curvature (steepening) Intolerance to contact lenses The following adverse reactions have been reported in users of oral contraceptives and the association has been neither confirmed nor refuted: Pre-menstrual syndrome Cataracts Changes in appetite Cystitis-like syndrome Headache Nervousness Dizziness Hirsutism Loss of scalp hair Erythema multiforme Erythema nodosum Hemorrhagic eruption Vaginitis Porphyria Impaired renal function Hemolytic uremic syndrome Budd-Chiari syndrome Acne Changes in libido Colitis figure 1
🆘 Overdosage ▾
OVERDOSAGE Serious ill effects have not been reported following acute ingestion of large doses of oral contraceptives by young children. Overdosage may cause nausea, and withdrawal bleeding may occur in females.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Combination oral contraceptives act by suppression of gonadotropins. Although the primary mechanism of this action is inhibition of ovulation, other alterations include changes in the cervical mucus (which increase the difficulty of sperm entry into the uterus) and the endometrium (which reduce the likelihood of implantation). Pharmacokinetics The pharmacokinetics of Loestrin have not been characterized; however, the following pharmacokinetic information regarding norethindrone acetate and ethinyl estradiol is taken from the literature.
Absorption Norethindrone acetate appears to be completely and rapidly deacetylated to norethindrone after oral administration, since the disposition of norethindrone acetate is indistinguishable from that of orally administered norethindrone (1). Norethindrone acetate and ethinyl estradiol are subject to first-pass metabolism after oral dosing, resulting in an absolute bioavailability of approximately 64% for norethindrone and 43% for ethinyl estradiol (1-3). Distribution Volume of distribution of norethindrone and ethinyl estradiol ranges from 2 to 4 L/kg (1 to 3).
Plasma protein binding of both steroids is extensive (greater than 95%); norethindrone binds to both albumin and sex hormone binding globulin, whereas ethinyl estradiol binds only to albumin (4). Metabolism Norethindrone undergoes extensive biotransformation, primarily via reduction, followed by sulfate and glucuronide conjugation. The majority of metabolites in the circulation are sulfates, with glucuronides accounting for most of the urinary metabolites (5).
A small amount of norethindrone acetate is metabolically converted to ethinyl estradiol. Ethinyl estradiol is also extensively metabolized, both by oxidation and by conjugation with sulfate and glucuronide. Sulfates are the major circulating conjugates of ethinyl estradiol and glucuronides predominate in urine.
The primary oxidative metabolite is 2-hydroxy ethinyl estradiol, formed by the CYP3A4 isoform of cytochrome P450. Part of the first-pass metabolism of ethinyl estradiol is believed to occur in gastrointestinal mucosa. Ethinyl estradiol may undergo enterohepatic circulation (6).
Excretion Norethindrone and ethinyl estradiol are excreted in both urine and feces, primarily as metabolites (5, 6). Plasma clearance values for norethindrone and ethinyl estradiol are similar (approximately
0.4L/hr/kg) (1-3). Special Population Race: The effect of race on the disposition of Loestrin has not been evaluated. Renal Insufficiency The effect of renal disease on the disposition of Loestrin has not been evaluated.
In premenopausal women with chronic renal failure undergoing peritoneal dialysis who received multiple doses of an oral contraceptive containing ethinyl estradiol and norethindrone, plasma ethinyl estradiol concentrations were higher and norethindrone concentrations were unchanged compared to concentrations in premenopausal women with normal renal function. Hepatic Insufficiency The effect of hepatic disease on the disposition of Loestrin has not been evaluated. However, ethinyl estradiol and norethindrone may be poorly metabolized in patients with impaired liver function.
Drug-Drug Interactions Numerous drug-drug interactions have been reported for oral contraceptives. A summary of these is found under PRECAUTIONS, Drug Interactions .
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Loestrin 1/20 (21 Tablets) (norethindrone acetate 1 mg and ethinyl estradiol 20 mcg tablets, USP) are packaged in cartons of five blister cards. Each card contains 21 light yellow, round, flat-faced, beveled-edge, unscored tablets debossed with stylized b on one side and 977 on the other side. (NDC 51285-131-97).
Loestrin Fe 1/20 (28 Tablets) (norethindrone acetate 1 mg and ethinyl estradiol 20 mcg tablets, USP, and ferrous fumarate tablets) are packaged in cartons of five blister cards. Each card contains 21 light yellow, round, flat-faced, beveled-edge, unscored tablets debossed with stylized b on one side and 977 on the other side and 7 brown, round, flat-faced, beveled-edge, unscored tablets debossed with stylized b on one side and 247 on the other side. Each brown tablet contains 75 mg ferrous fumarate.
The ferrous fumarate tablets are present to facilitate ease of drug administration via a 28-day regimen, are non-hormonal, and do not serve any therapeutic purpose. (NDC 51285-125-70). Loestrin 1.5/30 (21 Tablets) (norethindrone acetate 1.5 mg and ethinyl estradiol 30 mcg tablets, USP) are packaged in cartons of five blister cards.
Each card contains 21 pink, round, flat-faced, beveled-edge, unscored tablets debossed with stylized b on one side and 978 on the other side. (NDC 51285-127-97). Loestrin Fe 1.5/30 (28 Tablets) (norethindrone acetate 1.5 mg and ethinyl estradiol 30 mcg tablets, USP, and ferrous fumarate tablets) are packaged in cartons of five blister cards.
Each card contains 21 pink, round, flat-faced, beveled-edge, unscored tablets debossed with stylized b on one side and 978 on the other side and 7 brown, round, flat-faced, beveled-edge, unscored tablets debossed with stylized b on one side and 247 on the other side. Each brown tablet contains 75 mg ferrous fumarate. The ferrous fumarate tablets are present to facilitate ease of drug administration via a 28-day regimen, are non-hormonal, and do not serve any therapeutic purpose.
(NDC 51285-128-70). Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
📋 Description ▾
DESCRIPTION Loestrin ® 21 and Loestrin ® Fe 28 are progestogen-estrogen combinations. Loestrin ® Fe 1/20 and 1.5/30: Each provides a continuous dosage regimen consisting of 21 oral contraceptive tablets and seven ferrous fumarate tablets. The ferrous fumarate tablets are present to facilitate ease of drug administration via a 28-day regimen, are non-hormonal, and do not serve any therapeutic purpose.
Each light yellow tablet contains norethindrone acetate, USP (17α-ethinyl-19-nortestosterone acetate), 1 mg; ethinyl estradiol, USP (17α-ethinyl-1,3,5(10)-estratriene-3, 17β-diol), 20 mcg. Each light yellow tablet contains the following inactive ingredients: acacia, compressible sugar, D&C yellow no. 10 aluminum lake, lactose monohydrate, magnesium stearate and pregelatinized corn starch.
Each pink tablet contains norethindrone acetate, USP (17α-ethinyl-19-nortestosterone acetate), 1.5 mg; ethinyl estradiol, USP (17α-ethinyl-1,3,5(10)-estratriene-3, 17β-diol), 30 mcg. Each pink tablet contains the following inactive ingredients: acacia, compressible sugar, FD&C red no. 40 aluminum lake HT, lactose monohydrate, magnesium stearate and pregelatinized corn starch.
Each brown tablet contains the following ingredients: crospovidone, ferrous fumarate, hydrogenated vegetable oil, NF Type I and microcrystalline cellulose. Norethindrone Acetate, USP C 22 H 28 O 3 M.W. 340.46 Ethinyl Estradiol, USP C 20 H 24 O 2 M.W.
296.40 Norethindrone Acetate, USP Structural Formula Ethinyl Estradiol, USP Structural Formula
⚠️ Precautions ▾
PRECAUTIONS 1. Patients should be counseled that this product does not protect against HIV infection (AIDS) and other sexually transmitted infections. 2.
Physical Examination and Follow-Up It is good medical practice for all women to have annual history and physical examinations, including women using oral contraceptives. The physical examination, however, may be deferred until after initiation of oral contraceptives if requested by the woman and judged appropriate by the clinician. The physical examination should include special reference to blood pressure, breasts, abdomen and pelvic organs, including cervical cytology, and relevant laboratory tests.
In case of undiagnosed, persistent or recurrent abnormal vaginal bleeding, appropriate measures should be conducted to rule out malignancy. Women with a strong family history of breast cancer or who have breast nodules should be monitored with particular care. 3.
Lipid Disorders Women who are being treated for hyperlipidemia should be followed closely if they elect to use oral contraceptives. Some progestogens may elevate LDL levels and may render the control of hyperlipidemias more difficult. 4.
Liver Function If jaundice develops in any woman receiving such drugs, the medication should be discontinued. Steroid hormones may be poorly metabolized in patients with impaired liver function. 5.
Fluid Retention Oral contraceptives may cause some degree of fluid retention. They should be prescribed with caution, and only with careful monitoring, in patients with conditions which might be aggravated by fluid retention. 6.
Contact Lenses Contact lens wearers who develop visual changes or changes in lens tolerance should be assessed by an ophthalmologist. 7. Drug Interactions Effects of Other Drugs on Oral Contraceptives (69) Rifampin: Metabolism of both norethindrone and ethinyl estradiol is increased by rifampin.
A reduction in contraceptive effectiveness and increased incidence of breakthrough bleeding and menstrual irregularities have been associated with concomitant use of rifampin. Anticonvulsants: Anticonvulsants such as phenobarbital, phenytoin, and carbamazepine, have been shown to increase the metabolism of ethinyl estradiol and/or norethindrone, which could result in a reduction in contraceptive effectiveness. Troglitazone: Administration of troglitazone with an oral contraceptive containing ethinyl estradiol and norethindrone reduced the plasma concentrations of both by approximately 30%, which could result in a reduction in contraceptive effectiveness.
Antibiotics: Pregnancy while taking oral contraceptives has been reported when the oral contraceptives were administered with antimicrobials such as ampicillin, tetracycline, and griseofulvin. However, clinical pharmacokinetic studies have not demonstrated any consistent effect of antibiotics (other than rifampin) on plasma concentrations of synthetic steroids. Atorvastatin: Coadministration of atorvastatin and an oral contraceptive increased AUC values for norethindrone and ethinyl estradiol by approximately 30% and 20%, respectively.
Concomitant Use with HCV Combination Therapy – Liver Enzyme Elevation Coadministration of Loestrin with HCV drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir is contraindicated due to potential for ALT elevations (see Warnings, RISK OF LIVER ENZYME ELEVATIONS WITH CONCOMITANT HEPATITIS C TREATMENT ). Coadministration of Loestrin and glecaprevir/pibrentasvir is not recommended due to potential for ALT elevations. Other: Ascorbic acid and acetaminophen may increase plasma ethinyl estradiol concentrations, possibly by inhibition of conjugation.
A reduction in contraceptive effectiveness and increased incidence of breakthrough bleeding has been suggested with phenylbutazone. Effects of Oral Contraceptives on Other Drugs Oral contraceptive combinations containing ethinyl estradiol may inhibit the metabolism of other compounds. Increased plasma concentrations of… [Excerpted — this section continues on DailyMed.]
📚 References ▾
REFERENCES Back DJ, Breckenridge AM, Crawford FE, McIver M, Orme ML’E, Rowe PH and Smith E: Kinetics of norethindrone in women II. Single-dose kinetics. Clin Pharmacol Ther 1978; 24:448-453.
Hümpel M, Nieuwober B, Wendt H and Speck U: Investigations of pharmacokinetics of ethinyl estradiol to specific consideration of a possible first-pass effect in women. Contraception 1979;19:421- 432. Back DJ, Breckenridge AM, Crawford FE, MacIver M, Orme ML’E, Rowe PH and Watts MJ.
An investigation of the pharmacokinetics of ethinyl estradiol in women using radioimmunoassay. Contraception 1979; 20:263-273. Hammond GL, Lähteenmäki PLA, Lähteenmäki P and Luukkainen T.
Distribution and percentages of non-protein bound contraceptive steroids in human serum. J Steroid Biochem 1982;17:375-380. Fotherby K.
Pharmacokinetics and metabolism of progestins in humans, in Pharmacology of the contraceptive steroids, Goldzieher JW, Fotherby K (eds), Raven Press, Ltd., New York, 1994; 99-126. Goldzieher JW. Pharmacokinetics and metabolism of ethinyl estrogens, in Pharmacology of the contraceptive steroids, Goldzieher JW, Fotherby K (eds), Raven Press Ltd., New York, 1994; 127-151.
Hatcher RA, et al. 1998. Contraceptive Technology, Seventeenth Edition.
New York: Irvington Publishers. Stadel, B.V.: Oral contraceptives and cardiovascular disease. (Pt.
1). New England Journal of Medicine , 305:612-618, 1981. Stadel, B.V.: Oral contraceptives and cardiovascular disease.
(Pt. 2). New England Journal of Medicine , 305:672-677, 1981.
Adam, S.A., and M. Thorogood: Oral contraception and myocardial infarction revisited: The effects of new preparations and prescribing patterns. Brit.
J. Obstet. and Gynec , 88:838-845, 1981. Mann, J.I., and W.H.
Inman: Oral contraceptives and death from myocardial infarction. Brit. Med.
J. , 2(5965): 245-248, 1975. Mann, J.I., M.P. Vessey, M.
Thorogood, and R. Doll: Myocardial infarction in young women with special reference to oral contraceptive practice. Brit.
Med. J. , 2(5956):241-245, 1975. Royal College of General Practitioners' Oral Contraception Study: Further analyses of mortality in oral contraceptive users.
Lancet , 1:541-546, 1981. Slone, D., S. Shapiro, D.W.
Kaufman, L. Rosenberg, O.S. Miettinen, and P.D.
Stolley: Risk of myocardial infarction in relation to current and discontinued use of oral contraceptives. N.E.J.M. , 305:420-424, 1981. Vessey, M.P.: Female hormones and vascular disease: An epidemiological overview.
Brit. J. Fam.
Plann. , 6:1-12, 1980. Russell-Briefel, R.G., T.M. Ezzati, R.
Fulwood, J.A. Perlman, and R.S. Murphy: Cardiovascular risk status and oral contraceptive use, United States, 1976-80.
Preventive Medicine , 15:352-362, 1986. Goldbaum, G.M., J.S. Kendrick, G.C.
Hogelin, and E.M. Gentry: The relative impact of smoking and oral contraceptive use on women in the United States. J.A.M.A. , 258:1339-1342, 1987.
Layde, P.M., and V. Beral: Further analyses of mortality in oral contraceptive users: Royal College General Practitioners' Oral Contraception Study. (Table 5) Lancet , 1:541-546, 1981.
Knopp, R.H.: Arteriosclerosis risk: The roles of oral contraceptives and postmenopausal estrogens. J. of Reprod. Med. , 31(9)(Supplement): 913-921, 1986.
Krauss, R.M., S. Roy, D.R. Mishell, J.
Casagrande, and M.C. Pike: Effects of two low-dose oral contraceptives on serum lipids and lipoproteins: Differential changes in high-density lipoproteins subclasses. Am.
J. Obstet. Gyn. , 145:446-452, 1983.
Wahl, P., C. Walden, R. Knopp, J.
Hoover, R. Wallace, G. Heiss, and B.
Rifkind: Effect of estrogen/progestin potency on lipid/lipoprotein cholesterol. N.E.J.M. , 308:862-867, 1983. Wynn, V., and R.
Niththyananthan: The effect of progestin in combined oral contraceptives on serum lipids with special reference to high-density lipoproteins. Am. J.
Obstet. and Gyn. , 142:766-771, 1982. Wynn, V., and I. Godsland: Effects of oral contraceptives on carbohydrate metabolism.
J. Reprod. Medicine , 31 (9)(Supplement): 892-897, 1986.
L… [Excerpted — this section continues on DailyMed.]
📄 Patient Package Insert ▾
DETAILED PATIENT PACKAGE INSERT Cigarette smoking increases the risk of serious cardiovascular side effects from oral contraceptive use. This risk increases with age and with heavy smoking (15 or more cigarettes per day) and is quite marked in women over 35 years of age. Women who use oral contraceptives are strongly advised not to smoke.
This product (like all oral contraceptives) is intended to prevent pregnancy. It does not protect against HIV infection (AIDS) and other sexually transmitted infections. What You Should Know About Oral Contraceptives Any woman who considers using oral contraceptives (the “birth control pill” or “the pill”) should understand the benefits and risks of using this form of birth control.
This leaflet will give you much of the information you will need to make this decision and will also help you determine if you are at risk of developing any of the serious side effects of the pill. It will tell you how to use the pill properly so that it will be as effective as possible. However, this leaflet is not a replacement for a careful discussion between you and your healthcare provider.
You should discuss the information provided in this leaflet with him or her, both when you first start taking the pill and during your revisits. You should also follow your healthcare provider's advice with regard to regular check-ups while you are on the pill. EFFECTIVENESS OF ORAL CONTRACEPTIVES Oral contraceptives or “birth control pills” or “the pill” are used to prevent pregnancy and are more effective than other non-surgical methods of birth control.
When they are taken correctly, the chance of becoming pregnant is less than 1% (1 pregnancy per 100 women per year of use) when used perfectly, without missing any pills. Typical failure rates are actually 3% per year. The chance of becoming pregnant increases with each missed pill during a menstrual cycle.
In comparison, typical failure rates for other methods of birth control during the first year of use are as follows: Implant: <1% Injection: <1% IUD: <1 to 2% Diaphragm with spermicides: 20% Spermicides alone: 26% Vaginal Sponge: 20 to 40% Female sterilization: <1% Male sterilization: <1% Cervical Cap: 20 to 40% Condom alone (male): 14% Condom alone (female): 21% Periodic abstinence: 25% Withdrawal: 19% No method: 85% WHO SHOULD NOT TAKE ORAL CONTRACEPTIVES Cigarette smoking increases the risk of serious cardiovascular side effects from oral contraceptive use.
This risk increases with age and with heavy smoking (15 or more cigarettes per day) and is quite marked in women over 35 years of age. Women who use oral contraceptives are strongly advised not to smoke. Some women should not use the pill.
For example, you should not take the pill if you are pregnant or think you may be pregnant. You should also not use the pill if you have any of the following conditions: A history of heart attack or stroke Blood clots in the legs (thrombophlebitis), lungs (pulmonary embolism), or eyes A history of blood clots in the deep veins of your legs Chest pain (angina pectoris) Known or suspected breast cancer Unexplained vaginal bleeding (until a diagnosis is reached by your doctor) Yellowing of the whites of the eyes or of the skin (jaundice) during pregnancy or during previous use of the pill Liver tumor (benign or cancerous) Take any Hepatitis C drug combination containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir.
This may increase levels of the liver enzyme “alanine aminotransferase” (ALT) in the blood. Tell your healthcare provider if you have ever had any of these conditions. Your healthcare provider can recommend a safer method of birth control.
OTHER CONSIDERATIONS BEFORE TAKING ORAL CONTRACEPTIVES Tell your healthcare provider if you have: Breast nodules, fibrocystic disease of the breast, an abnormal breast x-ray or mammogram Diabetes Elevated cholesterol or triglycerides High blood pressure Migraine or other headaches or epilepsy Depression Gallbladder, h… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL NDC 51285-131-97 21 DAY REGIMEN Loestrin ® 21 1/20 (norethindrone acetate and ethinyl estradiol tablets, USP) PHARMACIST: This carton contains 5 foil pouches each containing one combination labeling piece of information intended for the patient. All informational pieces are to be provided to the patient with each prescription. This product (like all oral contraceptives) is intended to prevent pregnancy.
It does not protect against HIV infection (AIDS) and other sexually transmitted infections. Rx only 5 Blister Cards, 21 Tablets Each 1
PRINCIPAL DISPLAY PANEL NDC 51285-125-70 28 DAY REGIMEN Loestrin ® Fe 1/20 (norethindrone acetate and ethinyl estradiol tablets, USP and ferrous fumarate tablets*) PHARMACIST: This carton contains 5 foil pouches each containing one combination labeling piece of information intended for the patient. All informational pieces are to be provided to the patient with each prescription. *Ferrous fumarate tablets are not USP for dissolution and assay. This product (like all oral contraceptives) is intended to prevent pregnancy.
It does not protect against HIV infection (AIDS) and other sexually transmitted infections. Rx only 5 Blister Cards, 28 Tablets Each 1
PRINCIPAL DISPLAY PANEL NDC 51285-127-97 21 DAY REGIMEN Loestrin ® 21 1.5/30 (norethindrone acetate and ethinyl estradiol tablets, USP) PHARMACIST: This carton contains 5 foil pouches each containing one combination labeling piece of information intended for the patient. All informational pieces are to be provided to the patient with each prescription. This product (like all oral contraceptives) is intended to prevent pregnancy.
It does not protect against HIV infection (AIDS) and other sexually transmitted infections. Rx only 5 Blister Cards, 21 Tablets Each 1
PRINCIPAL DISPLAY PANEL NDC 51285-128-70 28 DAY REGIMEN Loestrin ® Fe 1.5/30 (norethindrone acetate and ethinyl estradiol tablets, USP and ferrous fumarate tablets*) PHARMACIST: This carton contains 5 foil pouches each containing one combination labeling piece of information intended for the patient. All informational pieces are to be provided to the patient with each prescription. *Ferrous fumarate tablets are not USP for dissolution and assay. This product (like all oral contraceptives) is intended to prevent pregnancy.
It does not protect against HIV infection (AIDS) and other sexually transmitted infections. Rx only 5 Blister Cards, 28 Tablets Each 1
Medicaid utilization & spend
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |