
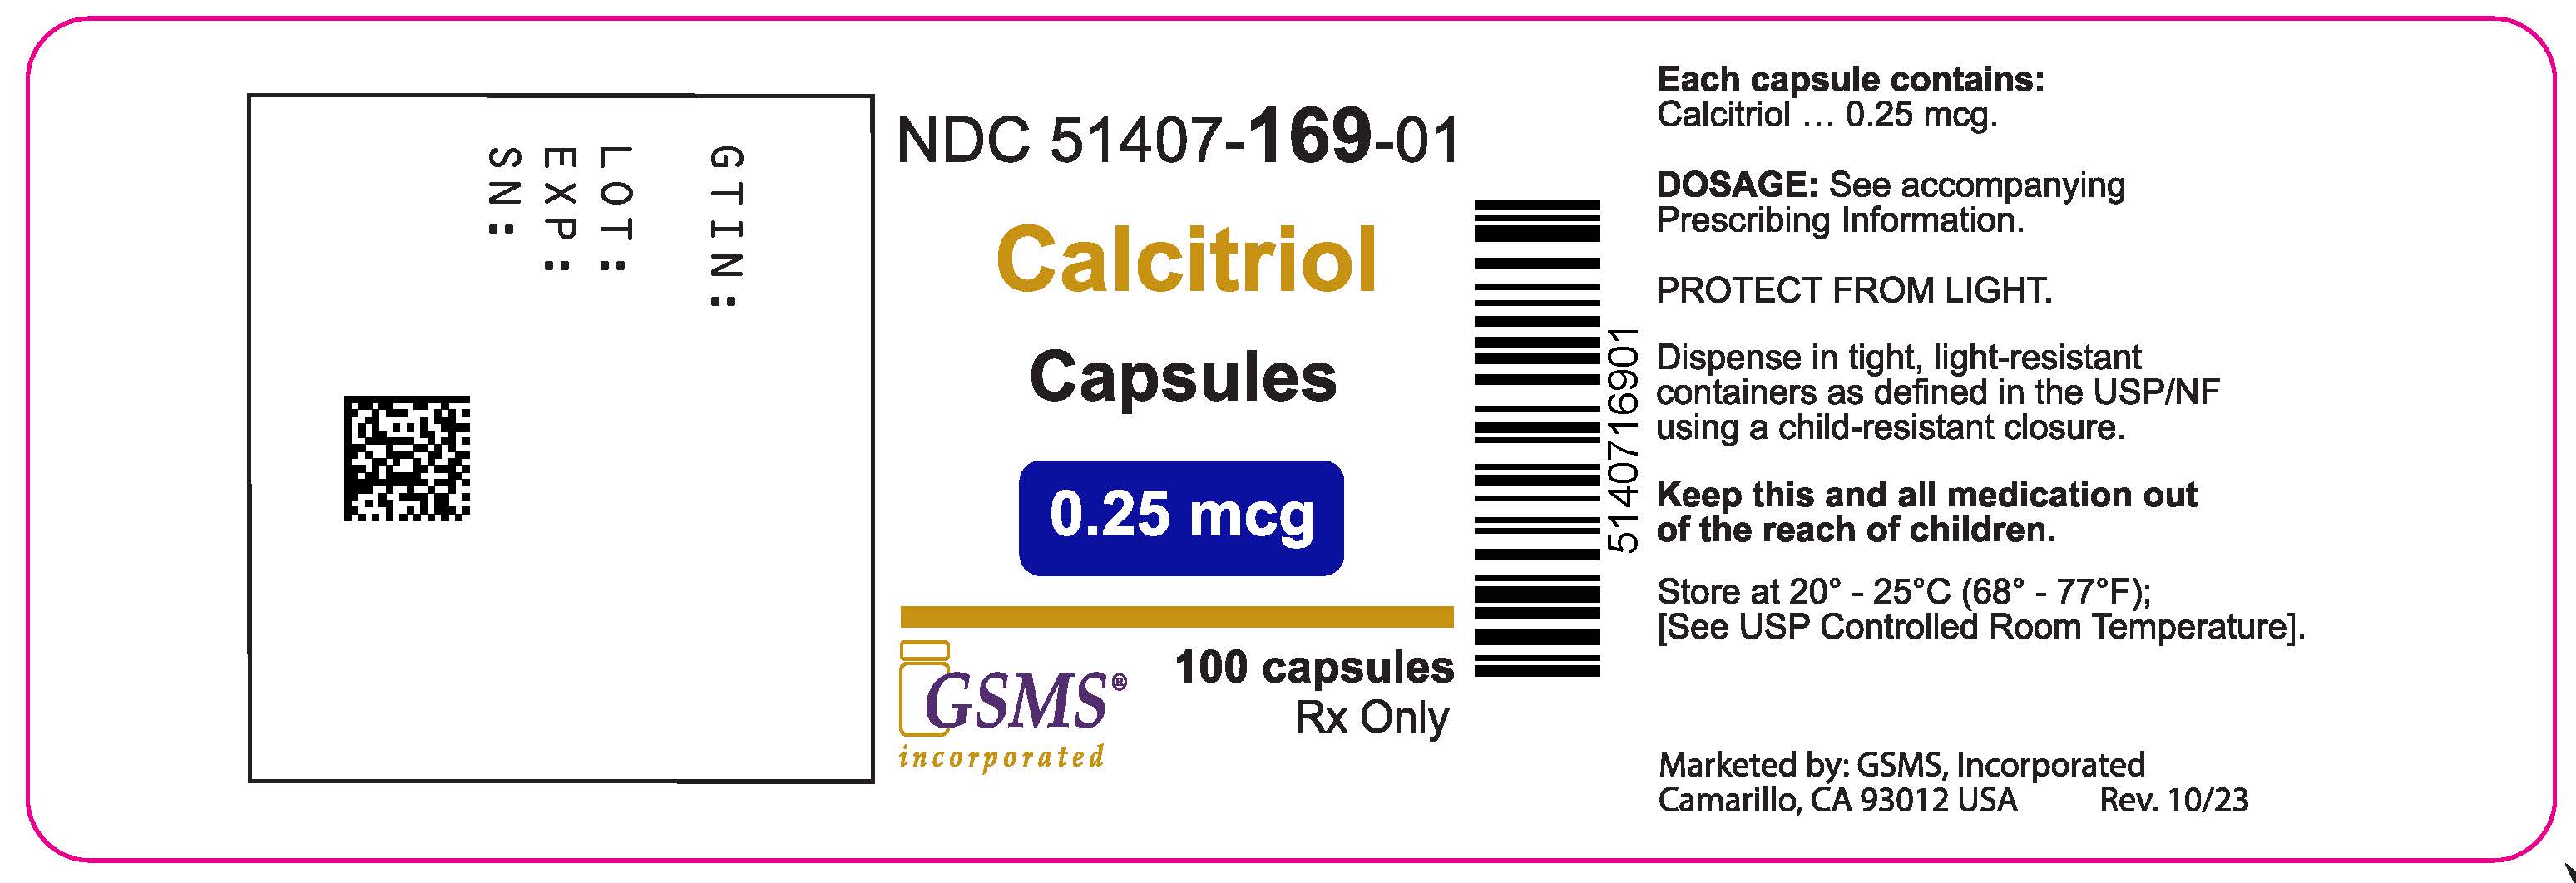
Calcitriol .25 ug Capsule, Liquid Filled, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Vitamin D3 Analog class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Calcitriol is used to treat and prevent low levels of calcium and bone disease in patients whose kidneys or parathyroid glands (glands in the neck that release natural substances to control the amount of calcium in the blood) are not working normally. It is also used to treat secondary hyperparathyroidism (a condition in which the body produces too much parathyroid hormone [PTH; a natural substance needed to control the amount of calcium in the blood]) and metabolic bone disease in people with kidney disease. Calcitriol is in a class of medications called vitamin D analogs. It works by helping...
Read the full MedlinePlus article ↗- Calcitriol is actually the active form that vitamin D becomes after your liver and kidneys process it. If your kidneys aren't working well, they can't make enough calcitriol on the...
- What exactly is calcitriol, and why did my doctor prescribe it instead of regular vitamin D?
- The biggest thing to watch for is high calcium — the early signs are things like unusual weakness, headache, nausea, dry mouth, a metallic taste, or constipation. If those get wors...
- What side effects should I actually watch out for while taking this?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII REK4960K2U
Butylated hydroxyanisole is a synthetic preservative that prevents oils and fats in medicines from spoiling or becoming rancid. It keeps the medicine stable and extends its shelf life.
-
UNII 1P9D0Z171K
BHT is a synthetic antioxidant that prevents fats and oils in medicines from breaking down and becoming rancid. It helps keep the product stable and effective during storage.
-
UNII WZB9127XOA
A synthetic red dye used to color medications and make them easier to identify. It serves as a colorant in tablets, capsules, and liquid formulations.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII C9H2L21V7U
A fat derived from coconut or palm oil containing shorter fatty acid chains. It serves as a solvent and carrier to help dissolve or suspend active ingredients, improving absorption and stability in liquid formulations.
-
UNII 6O92ICV9RU
A waxy substance derived from sorbitol that helps mix oil and water together in medicines. It's used as an emulsifier to keep ingredients evenly blended and stable.
-
UNII 506T60A25R
Sorbitol is a natural sugar alcohol derived from glucose. It serves as a sweetener, humectant, and bulking agent in medications to improve taste and help maintain moisture in the product.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
13 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Calcitriol .25 ug 00093-7352-01 | Teva | 100 capsules | $0.158 | AB | Availability likely | — |
| Calcitriol .25 ug 23155-0662-01 | Heritage | 100 capsules | $0.158 | AB | Availability likely | — |
| Calcitriol .25 ug 60687-0345-01 | American | 100 capsules | $0.158 | AB | Availability likely | — |
| Calcitriol .25 ug 62135-0610-90 | Chartwell | 90 capsules | $0.158 | AB | Availability likely | — |
| Calcitriol .25 ug 64380-0723-04 | Strides | 30 capsules | $0.158 | AB | Availability likely | — |
| Calcitriol .25 ug 69452-0207-13 | BIONPHARMA | 30 capsules | $0.158 | AB | Availability likely | — |
| Calcitriol .25 ug 00054-0007-13 | Hikma | 30 capsules | $0.161 | AB | Availability likely | — |
| Calcitriol .25 ug 42806-0732-01 | EPIC | 100 capsules | — | AB | FDA listed | — |
| Calcitriol .25 ug 50090-6711-00 | A-S | 30 capsules | — | AB | FDA listed | — |
| Calcitriol .25 ug 50090-7470-00 | A-S | 30 capsules | — | AB | FDA listed | — |
| Calcitriol .25 ugthis 51407-0169-30 | Golden | 30 capsules | — | AB | Discontinued | — |
| Calcitriol .25 ug 55154-8186-00 | Cardinal | 10 capsules | — | AB | FDA listed | — |
| Calcitriol .25 ug 62756-0967-18 | Sun | 1000 capsules | — | — | FDA listed | — |
| Calcitriol .25 ug 63304-0239-01 | Sun | 100 capsules | — | AB | Discontinued | — |
| Calcitriol .25 ug 63629-7323-01 | Bryant | 30 capsules | — | AB | FDA listed | — |
| Calcitriol .25 ug 63629-8741-01 | Bryant | 100 capsules | — | AB | FDA listed | — |
| Calcitriol .25 ug 65162-0519-03 | Amneal | 30 capsules | — | AB | FDA listed | — |
| Calcitriol .25 ug 71610-0468-09 | Aphena | 9000 capsules | — | AB | FDA listed | — |
| Calcitriol .25 ug 71610-0521-09 | Aphena | 9000 capsules | — | AB | FDA listed | — |
| Calcitriol .25 ug 71610-0870-30 | Aphena | 30 capsules | — | AB | FDA listed | — |
| Calcitriol .25 ug 72162-1031-01 | Bryant | 100 capsules | — | AB | FDA listed | — |
| Calcitriol .25 ug 72789-0058-01 | PD-Rx | 100 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 51407-0169-01 | 100 CAPSULE, LIQUID FILLED in 1 BOTTLE, PLASTIC (51407-169-01) | 2019-01-03 | Active |
| 51407-0169-30 You're viewing this | 30 CAPSULE, LIQUID FILLED in 1 BOTTLE, PLASTIC (51407-169-30) | 2019-01-03 | Discontinued by firm |
You're viewing the smallest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 51407-0169-30?
What is the difference between NDC 51407-0169-30 and NDC 51407-0169-01?
What NDC number is used to bill for this package of Calcitriol .25 ug Capsule, Liquid Filled?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
What does the discontinued status mean for this NDC?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Predialysis Patients Calcitriol capsules are indicated in the management of secondary hyperparathyroidism and resultant metabolic bone disease in patients with moderate to severe chronic renal failure (Ccr 15 to 55 mL/min) not yet on dialysis. In children, the creatinine clearance value must be corrected for a surface area of 1.73 square meters. A serum iPTH level of ≥ 100 pg/mL is strongly suggestive of secondary hyperparathyroidism.
Dialysis Patients Calcitriol capsules are indicated in the management of hypocalcemia and the resultant metabolic bone disease in patients undergoing chronic renal dialysis. In these patients, calcitriol capsules administration enhances calcium absorption, reduces serum alkaline phosphatase levels, and may reduce elevated parathyroid hormone levels and the histological manifestations of osteitis fibrosa cystica and defective mineralization. Hypoparathyroidism Patients Calcitriol capsules are also indicated in the management of hypocalcemia and its clinical manifestations in patients with postsurgical hypoparathyroidism, idiopathic hypoparathyroidism, and pseudohypoparathyroidism.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The optimal daily dose of calcitriol must be carefully determined for each patient. Calcitriol can be administered orally as a capsule (0.25 mcg or 0.50 mcg). Calcitriol Capsule therapy should always be started at the lowest possible dose and should not be increased without careful monitoring of serum calcium.
The effectiveness of calcitriol therapy is predicated on the assumption that each patient is receiving an adequate but not excessive daily intake of calcium. Patients are advised to have a dietary intake of calcium at a minimum of 600 mg daily. The U.S.
RDA for calcium in adults is 800 mg to 1200 mg. To ensure that each patient receives an adequate daily intake of calcium, the physician should either prescribe a calcium supplement or instruct the patient in proper dietary measures. Because of improved calcium absorption from the gastrointestinal tract, some patients on calcitriol may be maintained on a lower calcium intake.
Patients who tend to develop hypercalcemia may require only low doses of calcium or no supplementation at all. During the titration period of treatment with calcitriol, serum calcium levels should be checked at least twice weekly. When the optimal dosage of calcitriol has been determined, serum calcium levels should be checked every month (or as given below for individual indications).
Samples for serum calcium estimation should be taken without a tourniquet. Dialysis Patients The recommended initial dose of calcitriol is 0.25 mcg/day. If a satisfactory response in the biochemical parameters and clinical manifestations of the disease state is not observed, dosage may be increased by 0.25 mcg/day at 4 to 8 week intervals.
During this titration period, serum calcium levels should be obtained at least twice weekly, and if hypercalcemia is noted, the drug should be immediately discontinued until normocalcemia ensues (see PRECAUTIONS: General ). Phosphorus, magnesium, and alkaline phosphatase should be determined periodically. Patients with normal or only slightly reduced serum calcium levels may respond to Calcitriol doses of 0.25 mcg every other day.
Most patients undergoing hemodialysis respond to doses between 0.5 and 1 mcg/day. Oral calcitriol may normalize plasma ionized calcium in some uremic patients, yet fail to suppress parathyroid hyperfunction. In these individuals with autonomous parathyroid hyperfunction, oral calcitriol may be useful to maintain normocalcemia, but has not been shown to be adequate treatment for hyperparathyroidism.
Hypoparathyroidism The recommended initial dosage of calcitriol is 0.25 mcg/day given in the morning. If a satisfactory response in the biochemical parameters and clinical manifestations of the disease is not observed, the dose may be increased at 2- to 4-week intervals. During the dosage titration period, serum calcium levels should be obtained at least twice weekly and, if hypercalcemia is noted, calcitriol should be immediately discontinued until normocalcemia ensues (see PRECAUTIONS: General ).
Careful consideration should also be given to lowering the dietary calcium intake. Serum calcium, phosphorus, and 24-hour urinary calcium should be determined periodically. Most adult patients and pediatric patients age 6 years and older have responded to dosages in the range of 0.5 mcg to 2 mcg daily.
Pediatric patients in the 1 to 5 year age group with hypoparathyroidism have usually been given 0.25 mcg to 0.75 mcg daily. The number of treated patients with pseudohypoparathyroidism less than 6 years of age is too small to make dosage recommendations. Malabsorption is occasionally noted in patients with hypoparathyroidism; hence, larger doses of calcitriol may be needed.
Predialysis Patients The recommended initial dosage of calcitriol is 0.25 mcg/day in adults and pediatric patients 3 years of age and older. This dosage may be increased if necessary to 0.5 mcg/day. For pediatric patients less than 3 years of age, the recommended initial dosag…
⛔ Contraindications ▾
CONTRAINDICATIONS Calcitriol should not be given to patients with hypercalcemia or evidence of vitamin D toxicity. Use of calcitriol in patients with known hypersensitivity to calcitriol (or drugs of the same class) or any of the inactive ingredients is contraindicated.
⚠️ Warnings ▾
WARNINGS Overdosage of any form of vitamin D is dangerous (see OVERDOSAGE ). Progressive hypercalcemia due to overdosage of vitamin D and its metabolites may be so severe as to require emergency attention. Chronic hypercalcemia can lead to generalized vascular calcification, nephrocalcinosis and other soft-tissue calcification.
The serum calcium times phosphate (Ca × P) product should not be allowed to exceed 70 mg 2 /dL 2 . Radiographic evaluation of suspect anatomical regions may be useful in the early detection of this condition. Calcitriol is the most potent metabolite of vitamin D available.
The administration of calcitriol to patients in excess of their daily requirements can cause hypercalcemia, hypercalciuria, and hyperphosphatemia. Therefore, pharmacologic doses of vitamin D and its derivatives should be withheld during calcitriol treatment to avoid possible additive effects and hypercalcemia. If treatment is switched from ergocalciferol (vitamin D 2 ) to calcitriol, it may take several months for the ergocalciferol level in the blood to return to the baseline value (see OVERDOSAGE ).
Calcitriol increases inorganic phosphate levels in serum. While this is desirable in patients with hypophosphatemia, caution is called for in patients with renal failure because of the danger of ectopic calcification. A non-aluminum phosphate-binding compound and a low-phosphate diet should be used to control serum phosphorus levels in patients undergoing dialysis.
Magnesium-containing preparations (eg, antacids) and calcitriol should not be used concomitantly in patients on chronic renal dialysis because such use may lead to the development of hypermagnesemia. Studies in dogs and rats given calcitriol for up to 26 weeks have shown that small increases of calcitriol above endogenous levels can lead to abnormalities of calcium metabolism with the potential for calcification of many tissues in the body.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Since calcitriol is believed to be the active hormone which exerts vitamin D activity in the body, adverse effects are, in general, similar to those encountered with excessive vitamin D intake, ie, hypercalcemia syndrome or calcium intoxication (depending on the severity and duration of hypercalcemia) (see WARNINGS ). Because of the short biological half-life of calcitriol, pharmacokinetic investigations have shown normalization of elevated serum calcium within a few days of treatment withdrawal, ie, much faster than in treatment with vitamin D 3 preparations.
The early and late signs and symptoms of vitamin D intoxication associated with hypercalcemia include: Early: weakness, headache, somnolence, nausea, vomiting, dry mouth, constipation, muscle pain, bone pain, metallic taste, and anorexia, abdominal pain or stomach ache. Late: polyuria, polydipsia, anorexia, weight loss, nocturia, conjunctivitis (calcific), pancreatitis, photophobia, rhinorrhea, pruritus, hyperthermia, decreased libido, elevated BUN, albuminuria, hypercholesterolemia, elevated SGOT (AST) and SGPT (ALT), ectopic calcification, nephrocalcinosis, hypertension, cardiac arrhythmias, dystrophy, sensory disturbances, dehydration, apathy, arrested growth, urinary tract infections, and, rarely, overt psychosis.
In clinical studies on hypoparathyroidism and pseudohypoparathyroidism, hypercalcemia was noted on at least one occasion in about 1 in 3 patients and hypercalciuria in about 1 in 7 patients. Elevated serum creatinine levels were observed in about 1 in 6 patients (approximately one half of whom had normal levels at baseline). In concurrent hypercalcemia and hyperphosphatemia, soft-tissue calcification may occur; this can be seen radiographically (see WARNINGS ).
In patients with normal renal function, chronic hypercalcemia may be associated with an increase in serum creatinine (see PRECAUTIONS: General ). Hypersensitivity reactions (pruritus, rash, urticaria, and very rarely severe erythematous skin disorders) may occur in susceptible individuals. One case of erythema multiforme and one case of allergic reaction (swelling of lips and hives all over the body) were confirmed by rechallenge.
To report SUSPECTED ADVERSE REACTIONS, contact Bionpharma Inc. at 1-888-235BION or 1-888-235-2466 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
Drug Interactions Cholestyramine Cholestyramine has been reported to reduce intestinal absorption of fat-soluble vitamins; as such it may impair intestinal absorption of calcitriol (see WARNINGS and PRECAUTIONS: General ). Phenytoin/Phenobarbital The coadministration of phenytoin or phenobarbital will not affect plasma concentrations of calcitriol, but may reduce endogenous plasma levels of 25(OH)D 3 by accelerating metabolism. Since blood level of calcitriol will be reduced, higher doses of calcitriol may be necessary if these drugs are administered simultaneously.
Thiazides Thiazides are known to induce hypercalcemia by the reduction of calcium excretion in urine. Some reports have shown that the concomitant administration of thiazides with Calcitriol causes hypercalcemia. Therefore, precaution should be taken when coadministration is necessary.
Digitalis Calcitriol dosage must be determined with care in patients undergoing treatment with digitalis, as hypercalcemia in such patients may precipitate cardiac arrhythmias (see PRECAUTIONS: General ). Ketoconazole Ketoconazole may inhibit both synthetic and catabolic enzymes of calcitriol. Reductions in serum endogenous calcitriol concentrations have been observed following the administration of 300 mg/day to 1200 mg/day ketoconazole for a week to healthy men.
However, in vivo drug interaction studies of ketoconazole with calcitriol have not been investigated. Corticosteroids A relationship of functional antagonism exists between vitamin D analogues, which promote calcium absorption, and corticosteroids, which inhibit calcium absorption. Phosphate-Binding Agents Since calcitriol also has an effect on phosphate transport in the intestine, kidneys and bones, the dosage of phosphate-binding agents must be adjusted in accordance with the serum phosphate concentration.
Vitamin D Since calcitriol is the most potent active metabolite of vitamin D 3 , pharmacological doses of vitamin D and its derivatives should be withheld during treatment with calcitriol to avoid possible additive effects and hypercalcemia (see WARNINGS ). Calcium Supplements Uncontrolled intake of additional calcium-containing preparations should be avoided (see PRECAUTIONS: General ). Magnesium Magnesium-containing preparations (eg, antacids) may cause hypermagnesemia and should therefore not be taken during therapy with calcitriol by patients on chronic renal dialysis.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects Pregnancy Category C. Calcitriol has been found to be teratogenic in rabbits when given at doses of 0.08 and 0.3 mcg/kg (approximately 2 and 6 times the maximum recommended dose based on mg/m 2 ). All 15 fetuses in 3 litters at these doses showed external and skeletal abnormalities.
However, none of the other 23 litters (156 fetuses) showed external and skeletal abnormalities compared with controls. Teratogenicity studies in rats at doses up to 0.45 mcg/kg (approximately 5 times maximum recommended dose based on mg/m 2 ) showed no evidence of teratogenic potential. There are no adequate and well-controlled studies in pregnant women.
Calcitriol should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Nonteratogenic Effects In the rabbit, dosages of 0.3 mcg/kg/day (approximately 6 times maximum recommended dose based on surface area) administered on days 7 to 18 of gestation resulted in 19% maternal mortality, a decrease in mean fetal body weight and a reduced number of newborn surviving to 24 hours. A study of perinatal and postnatal development in rats resulted in hypercalcemia in the offspring of dams given calcitriol at doses of 0.08 or 0.3 mcg/kg/day (approximately 1 and 3 times the maximum recommended dose based on mg/m 2 ), hypercalcemia and hypophosphatemia in dams given calcitriol at a dose of 0.08 or 0.3 mcg/kg/day, and increased serum urea nitrogen in dams given calcitriol at a dose of 0.3 mcg/kg/day.
In another study in rats, maternal weight gain was slightly reduced at a dose of 0.3 mcg/kg/day (approximately 3 times the maximum recommended dose based on mg/m 2 ) administered on days 7 to 15 of gestation. The offspring of a woman administered 17 mcg/day to 36 mcg/day of calcitriol (approximately 17 to 36 times the maximum recommended dose), during pregnancy manifested mild hypercalcemia in the first 2 days of life which returned to normal at day 3.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness of calcitriol in pediatric patients undergoing dialysis have not been established. The safety and effectiveness of calcitriol in pediatric predialysis patients is based on evidence from adequate and well-controlled studies of calcitriol in adults with predialysis chronic renal failure and additional supportive data from non-placebo controlled studies in pediatric patients. Dosing guidelines have not been established for pediatric patients under 1 year of age with hypoparathyroidism or for pediatric patients less than 6 years of age with pseudohypoparathyroidism (see DOSAGE AND ADMINISTRATION: Hypoparathyroidism ).
Oral doses of calcitriol ranging from 10 to 55 ng/kg/day have been shown to improve calcium homeostasis and bone disease in pediatric patients with chronic renal failure for whom hemodialysis is not yet required (predialysis). Long-term calcitriol therapy is well tolerated by pediatric patients. The most common safety issues are mild, transient episodes of hypercalcemia, hyperphosphatemia, and increases in the serum calcium times phosphate (Ca × P) product which are managed effectively by dosage adjustment or temporary discontinuation of the vitamin D derivative.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of calcitriol did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
OVERDOSAGE Administration of calcitriol to patients in excess of their daily requirements can cause hypercalcemia, hypercalciuria, and hyperphosphatemia. Since calcitriol is a derivative of vitamin D, the signs and symptoms of overdose are the same as for an overdose of vitamin D (see ADVERSE REACTIONS ). High intake of calcium and phosphate concomitant with Calcitriol capsules may lead to similar abnormalities.
The serum calcium times phosphate (Ca × P) product should not be allowed to exceed 70 mg 2 /dL 2 . High levels of calcium in the dialysate bath may contribute to the hypercalcemia (see WARNINGS ). Treatment of Hypercalcemia and Overdosage in Dialysis Patients and Hypoparathyroidism Patients General treatment of hypercalcemia (greater than 1 mg/dL above the upper limit of the normal range) consists of immediate discontinuation of calcitriol therapy, institution of a low-calcium diet and withdrawal of calcium supplements.
Serum calcium levels should be determined daily until normocalcemia ensues. Hypercalcemia frequently resolves in 2 to 7 days. When serum calcium levels have returned to within normal limits, calcitriol therapy may be reinstituted at a dose of 0.25 mcg/day less than prior therapy.
Serum calcium levels should be obtained at least twice weekly after all dosage changes and subsequent dosage titration. In dialysis patients, persistent or markedly elevated serum calcium levels may be corrected by dialysis against a calcium-free dialysate. Treatment of Hypercalcemia and Overdosage in Predialysis Patients If hypercalcemia ensues (greater than 1 mg/dL above the upper limit of the normal range), adjust dosage to achieve normocalcemia by reducing calcitriol therapy from 0.5 mcg to 0.25 mcg daily.
If the patient is receiving a therapy of 0.25 mcg daily, discontinue calcitriol until patient becomes normocalcemic. Calcium supplements should also be reduced or discontinued. Serum calcium levels should be determined 1 week after withdrawal of calcium supplements.
If serum calcium levels have returned to normal, calcitriol therapy may be reinstituted at a dosage of 0.25 mcg/day if previous therapy was at a dosage of 0.5 mcg/day. If calcitriol therapy was previously administered at a dosage of 0.25 mcg/day, calcitriol therapy may be reinstituted at a dosage of 0.25 mcg every other day. If hypercalcemia is persistent at the reduced dosage, serum PTH should be measured.
If serum PTH is normal, discontinue calcitriol therapy and monitor patient in 3 months' time. Treatment of Hyperphosphatemia in Predialysis Patients If serum phosphorus levels exceed 5.0 mg/dL to 5.5 mg/dL, a calcium-containing phosphate-binding agent (ie, calcium carbonate or calcium acetate) should be taken with meals. Serum phosphorus levels should be determined as described earlier (see PRECAUTIONS: Laboratory Tests ).
Aluminum-containing gels should be used with caution as phosphate-binding agents because of the risk of slow aluminum accumulation. Treatment of Accidental Overdosage of Calcitriol The treatment of acute accidental overdosage of calcitriol should consist of general supportive measures. If drug ingestion is discovered within a relatively short time, induction of emesis or gastric lavage may be of benefit in preventing further absorption.
If the drug has passed through the stomach, the administration of mineral oil may promote its fecal elimination. Serial serum electrolyte determinations (especially calcium), rate of urinary calcium excretion, and assessment of electrocardiographic abnormalities due to hypercalcemia should be obtained. Such monitoring is critical in patients receiving digitalis.
Discontinuation of supplemental calcium and a low-calcium diet are also indicated in accidental overdosage. Due to the relatively short duration of the pharmacological action of calcitriol, further measures are probably unnecessary. Should, however, persistent and markedly elevated serum calcium levels occur, there are a variety of therapeutic alte…
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Man's natural supply of vitamin D depends mainly on exposure to the ultraviolet rays of the sun for conversion of 7-dehydrocholesterol in the skin to vitamin D 3 (cholecalciferol). Vitamin D 3 must be metabolically activated in the liver and the kidney before it is fully active as a regulator of calcium and phosphorus metabolism at target tissues. The initial transformation of vitamin D 3 is catalyzed by a vitamin D 3 -25-hydroxylase enzyme (25-OHase) present in the liver, and the product of this reaction is 25 hydroxyvitamin D 3 [25-(OH)D 3 ].
Hydroxylation of 25-(OH)D 3 occurs in the mitochondria of kidney tissue, activated by the renal 25-hydroxyvitamin D 3 -1 alpha-hydroxylase (alpha-OHase), to produce 1,25-(OH) 2 D 3 (calcitriol), the active form of vitamin D 3 . Endogenous synthesis and catabolism of calcitriol, as well as physiological control mechanisms affecting these processes, play a critical role regulating the serum level of calcitriol. Physiological daily production is normally 0.5 to 1.0 mcg and is somewhat higher during periods of increased bone synthesis (eg, growth or pregnancy).
Pharmacodynamics The two known sites of action of calcitriol are intestine and bone. A calcitriol receptor-binding protein appears to exist in the mucosa of human intestine. Additional evidence suggests that calcitriol may also act on the kidney and the parathyroid glands.
Calcitriol is the most active known form of vitamin D 3 in stimulating intestinal calcium transport. In acutely uremic rats calcitriol has been shown to stimulate intestinal calcium absorption. The kidneys of uremic patients cannot adequately synthesize calcitriol, the active hormone formed from precursor vitamin D.
Resultant hypocalcemia and secondary hyperparathyroidism are a major cause of the metabolic bone disease of renal failure. However, other bone-toxic substances which accumulate in uremia (eg, aluminum) may also contribute. The beneficial effect of calcitriol in renal osteodystrophy appears to result from correction of hypocalcemia and secondary hyperparathyroidism.
It is uncertain whether calcitriol produces other independent beneficial effects. Calcitriol treatment is not associated with an accelerated rate of renal function deterioration. No radiographic evidence of extraskeletal calcification has been found in predialysis patients following treatment.
The duration of pharmacologic activity of a single dose of calcitriol is about 3 to 5 days. Pharmacokinetics Absorption Calcitriol is rapidly absorbed from the intestine. Peak serum concentrations (above basal values) were reached within 3 to 6 hours following oral administration of single doses of 0.25 to 1.0 mcg of Calcitriol.
Following a single oral dose of 0.5 mcg, mean serum concentrations of calcitriol rose from a baseline value of 40.0±4.4 (SD) pg/mL to 60.0±4.4 pg/mL at 2 hours, and declined to 53.0±6.9 at 4 hours, 50±7.0 at 8 hours, 44±4.6 at 12 hours, and 41.5±5.1 at 24 hours. Following multiple-dose administration, serum calcitriol levels reached steady-state within 7 days. Distribution Calcitriol is approximately 99.9% bound in blood.
Calcitriol and other vitamin D metabolites are transported in blood, by an alpha-globulin vitamin D binding protein. There is evidence that maternal calcitriol may enter the fetal circulation. Calcitriol is transferred into human breast milk at low levels (ie, 2.2±0.1 pg/mL).
Metabolism In vivo and in vitro studies indicate the presence of two pathways of metabolism for calcitriol. The first pathway involves the 24-hydroxylase as the first step in catabolism of calcitriol. There is definite evidence of 24-hydroxylase activity in the kidney; this enzyme is also present in many target tissues which possess the vitamin D receptor such as the intestine.
The end product of this pathway is a side chain shortened metabolite, calcitroic acid. The second pathway involves the conversion of calcitriol via the stepwise hydroxylation of carbon-26 and c…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Capsules: 0.25 mcg calcitriol in soft gelatin, light orange, oval capsules, imprinted with CAL1 in black ink; bottles of 30 (NDC 51407-169-30), and bottles of 100 (NDC 51407-169-01). Capsules: 0.5 mcg calcitriol in soft gelatin, dark orange-red, oval capsules, imprinted with CAL2 in black ink; bottles of 100 (NDC 51407-170-01). Calcitriol Capsules should be protected from light.
Store at 20° to 25°C (68°-77°F) [see USP Controlled Room Temperature]. REFERENCE Jones CL, et al. Comparisons between oral and intraperitoneal 1,25-dihydroxyvitamin D 3 therapy in children treated with peritoneal dialysis.
Clin Nephrol. 1994; 42:44-49. Manufactured for: Bionpharma Inc.
Princeton, NJ 08540, USA Rev. 02/23 Marketed by: GSMS, Inc. Camarillo, CA 93012 USA
📋 Description ▾
DESCRIPTION Calcitriol is a synthetic vitamin D analog which is active in the regulation of the absorption of calcium from the gastrointestinal tract and its utilization in the body. Calcitriol Capsules contain 0.25 mcg or 0.5 mcg calcitriol, fractionated triglyceride of coconut oil, butylated hydroxyanisole (BHA) and butylated hydroxytoluene (BHT) as antioxidants. Gelatin capsule shells contain glycerin, water, sorbitol, sorbitan, mannitol, water, FD&C Yellow No.
6, FD&C Red #40, titanium dioxide and iron oxide black. Calcitriol is a white, crystalline compound which occurs naturally in humans. It has a calculated molecular weight of 416.65 and is soluble in organic solvents but relatively insoluble in water.
Chemically, calcitriol is 9,10- seco(5Z,7E)-5,7,10(19)-cholestatriene-1α, 3β, 25-triol and has the following structural formula: The other names frequently used for calcitriol are 1α,25-dihydroxycholecalciferol, 1,25-dihydroxyvitamin D 3 , 1,25-DHCC, 1,25(OH) 2 D 3 and 1,25-diOHC. image description
💬 Information for Patients ▾
Information For Patients The patient and his or her caregivers should be informed about compliance with dosage instructions, adherence to instructions about diet and calcium supplementation, and avoidance of the use of unapproved nonprescription drugs. Patients and their caregivers should also be carefully informed about the symptoms of hypercalcemia (see ADVERSE REACTIONS ). The effectiveness of calcitriol therapy is predicated on the assumption that each patient is receiving an adequate daily intake of calcium.
Patients are advised to have a dietary intake of calcium at a minimum of 600 mg daily. The U.S. RDA for calcium in adults is 800 mg to 1200 mg.