
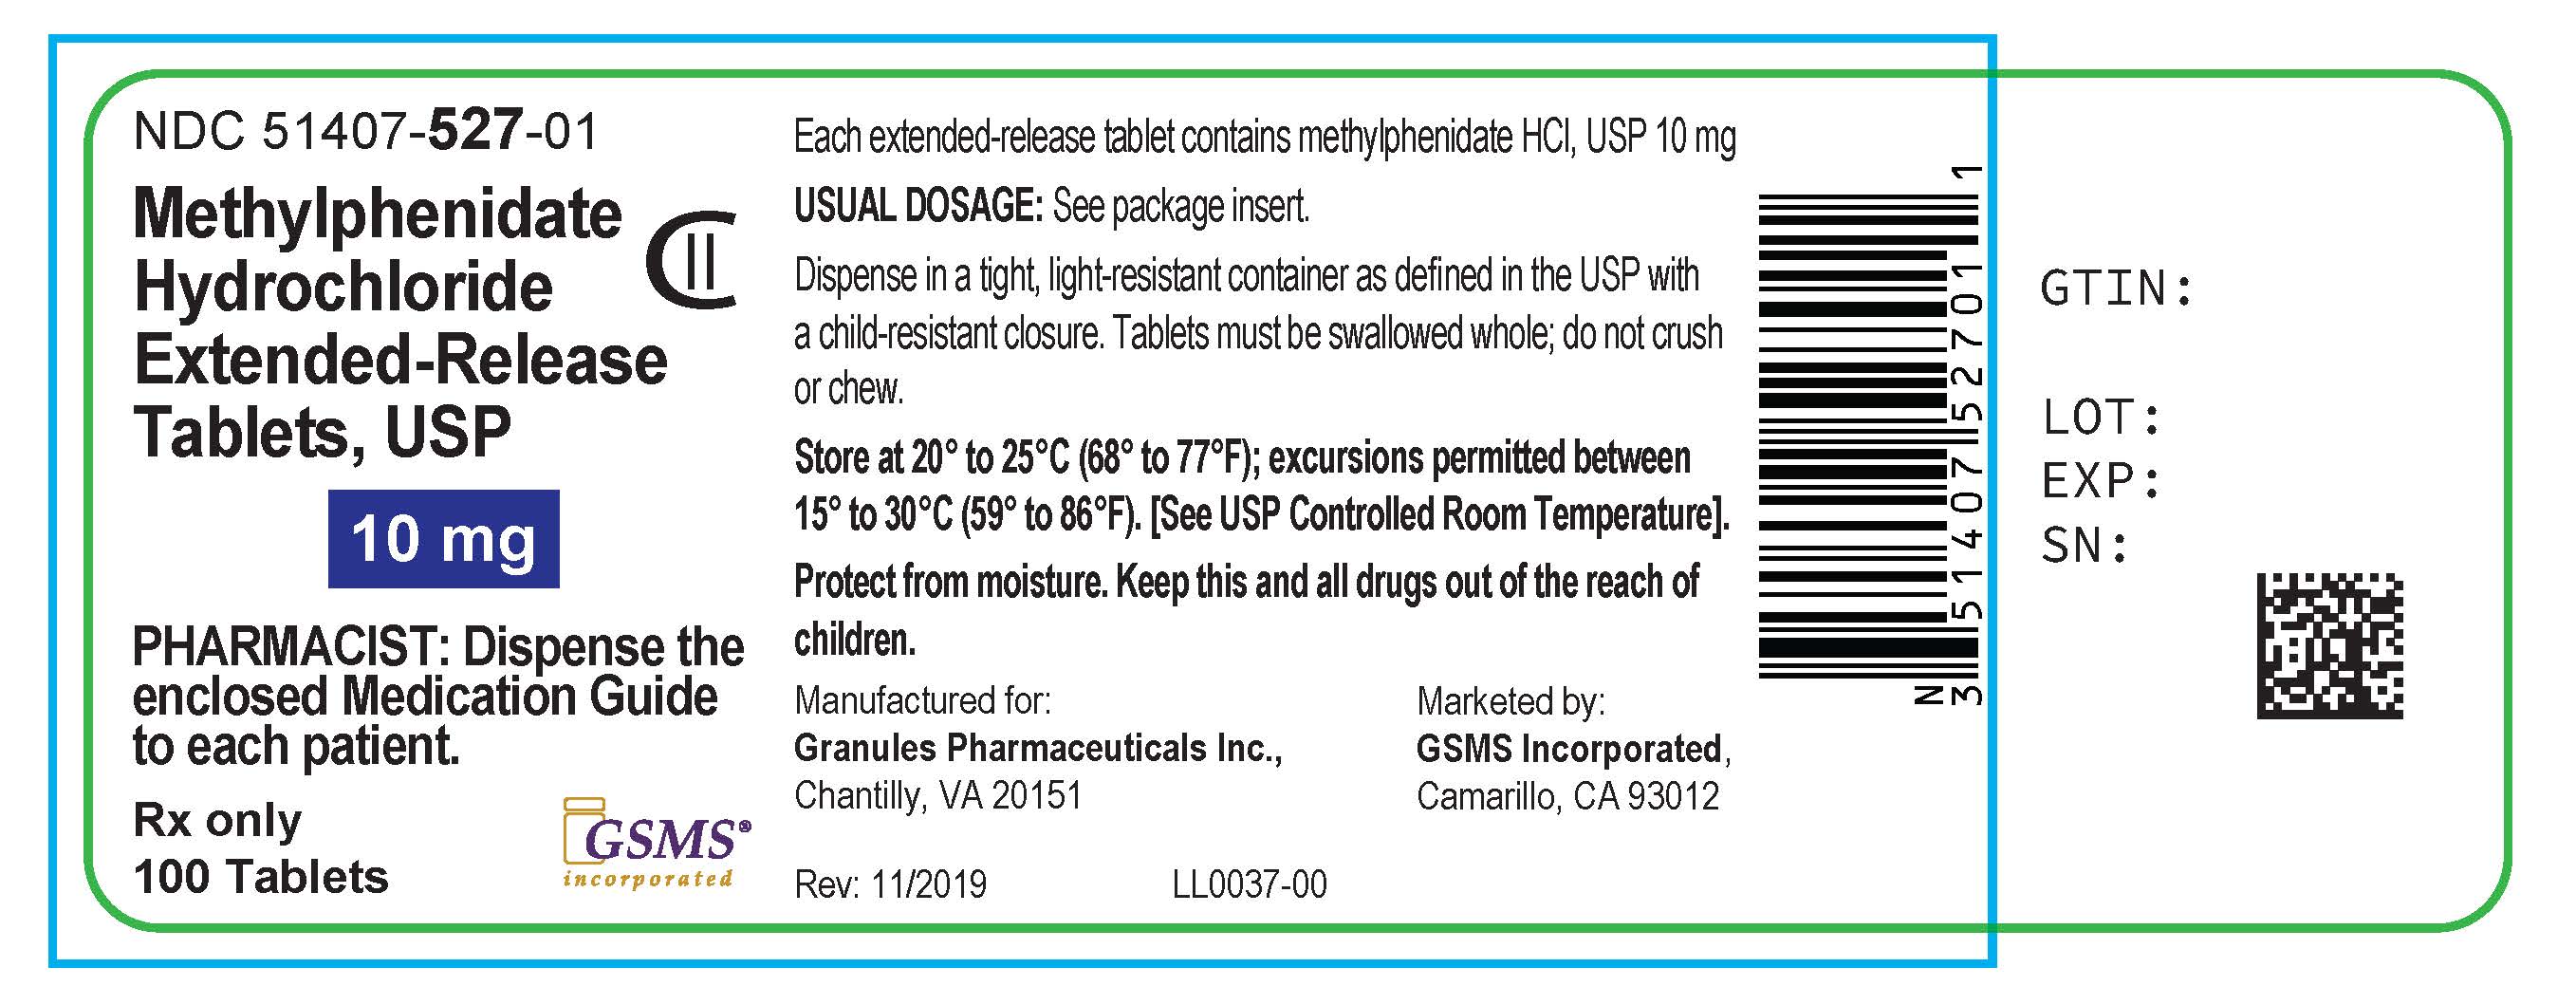
Methylphenidate Hydrochloride 10 mg Tablet, Extended Release, 100-count — NDC 51407-527-01 (Billing 51407-0527-01)
This is a package of 100 tablets of Methylphenidate Hydrochloride 10 mg Tablet, Extended Release from Golden State Medical Supply, Inc., marketed since Nov 2018 and currently FDA-listed. It is this product's only package size.
Other active recalls for Methylphenidate Hydrochloride (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 044072
- GCN: 93075
- HICL (First Databank): 001682
- AHFS class code: 28:20.32.00
- RxCUI (RxNorm): 1091145
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Central Nervous System Stimulant class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It mainly treats ADHD, and some products are also used for narcolepsy. The exact approval depends on the product and the age group. Your prescriber chooses the right one for you.
- It depends on your product. Many extended-release forms are taken once daily in the morning, while Jornay PM is taken in the evening. Swallow extended-release tablets whole, and fo...
- The most common ones are decreased appetite, headache, dry mouth, nausea, trouble sleeping, anxiety and dizziness. Children and teens may get upper stomach pain. Call your doctor i...
- Call for chest pain, fainting, a racing heartbeat, hallucinations, seizures, painful erections that won’t go away, or color changes in your fingers or toes. Also call if you notice...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Methylphenidate Hydrochloride — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $1.04 | $104.08 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 2, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 51407-0527-01 You're viewing this Main listing | 100 TABLET, EXTENDED RELEASE in 1 BOTTLE, PLASTIC | 2019-11-14 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Methylphenidate Hydrochloride 10 mg 00406-1445-01 | SpecGx | 100 tablets | $0.458 | AB | Discontinued | — |
| Methylphenidate Hydrochloride Extended Release 10 mg 10702-0075-01 | KVK-Tech, | 100 tablets | $0.458 | AB | Availability likely | — |
| Methylphenidate Hydrochloride 10 mg 70010-0042-01 | Granules | 100 tablets | $0.458 | AB | Availability likely | — |
| Methylphenidate Hydrochloride 10 mgthis 51407-0527-01 | Golden | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII Z78RG6M2N2
Hypromellose 2208 is a plant-derived thickening agent used as a binder and film-coating material in tablets and capsules. It helps hold ingredients together and creates a protective coating that controls how quickly the medicine dissolves.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: ABUSE AND DEPENDENCE CNS stimulants, including Methylphenidate hydrochloride extended-release tablets, other methylphenidate-containing products, and amphetamines, have a high potential for abuse and dependence. Assess the risk of abuse prior to prescribing, and monitor for signs of abuse and dependence while on therapy [see Warnings and Precautions (5.1) , Drug Abuse and Dependence (9.2 , 9.3 )] . WARNING: ABUSE AND DEPENDANCE See full prescribing information for complete boxed warning.
CNS stimulants, including Methylphenidate hydrochloride extended-release tablets, other methylphenidate-containing products, and amphetamine, have a high potential for abuse and dependence ( 5.1 , 9.2 , 9.3 ). Assess the risk of abuse prior to prescribing, and monitor for signs of abuse and dependence while on therapy ( 5.1 , 9.2 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Methylphenidate hydrochloride extended-release tablets are indicated for the treatment of: Attention Deficit Hyperactivity Disorders (ADHD) in pediatric patients 6 years and older and adults Narcolepsy Limitations of Use The use of methylphenidate hydrochloride extended-release tablets are not recommended in pediatric patients younger than 6 years of age because they had higher plasma exposure and a higher incidence of adverse reactions (e.g., weight loss) than patients 6 years and older at the same dosage [see Warnings and Precautions (5.7) , Use in Specific Populations (8.4) ] .
Methylphenidate hydrochloride extended-release tablet is a central nervous system (CNS) stimulant indicated for the treatment of Attention Deficit Hyperactivity Disorders (ADHD) and Narcolepsy ( 1 ). Limitations of Use The use of methylphenidate hydrochloride extended-release tablets are not recommended in pediatric patients younger than 6 years of age because they had higher plasma exposure and a higher incidence of adverse reactions (e.g., weight loss) than patients 6 years and older at the same dosage ( 5.7 , 8.4 ).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION N/A Methylphenidate hydrochloride extended-release tablets (2.2) : May switch to Methylphenidate hydrochloride extended-release tablets when the 8-hour dosage of Methylphenidate hydrochloride extended-release tablets corresponds to the titrated 8-hour dosage of methylphenidate hydrochloride tablets. Must be swallowed whole and never crushed or chewed.
2.1Pretreatment Screening Prior to treating pediatric patients and adults with central nervous system (CNS) stimulants, including Methylphenidate hydrochloride extended-release tablets, assess for the presence of cardiac disease (i.e., perform a careful history including family history of sudden death or ventricular arrhythmia, and physical examination) [see Warnings and Precautions (5.2) ] . Assess the risk of abuse prior to prescribing, and monitor for signs of abuse and dependence while on therapy. Maintain careful prescription records, educate patients about abuse, monitor for signs of abuse and overdose, and periodically reevaluate the need for Methylphenidate hydrochloride extended-release tablets use [see Boxed Warning , Warnings and Precautions (5.1) , Drug Abuse and Dependence (9) ].
2.2General Dosing Information Methylphenidate hydrochloride extended-release tablets have a duration of action of approximately 8 hours. Therefore, Methylphenidate hydrochloride extended-release tablets may be used in place of methylphenidate hydrochloride tablets when the 8-hour dosage of Methylphenidate hydrochloride extended-release tablets corresponds to the titrated 8-hour dosage of methylphenidate hydrochloride tablets. Methylphenidate hydrochloride extended-release tablets must be swallowed whole and never crushed or chewed.
Pharmacological treatment of ADHD may be needed for extended periods. Periodically reevaluate the long-term use of Methylphenidate hydrochloride extended-release tablets, and adjust dosage as needed.
2.3Dose Reduction and Discontinuation If paradoxical worsening of symptoms or other adverse reactions occur, reduce the dosage, or, if necessary, discontinue Methylphenidate hydrochloride extended-release tablets. If improvement is not observed after appropriate dosage adjustment over a one-month period, the drug should be discontinued.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 10 mg extended-release tablets, white to off white, round shaped, uncoated, tablets debossed with “FM4” on one side and plain on other side. 20 mg extended-release tablets, white to off white, round shaped, uncoated, tablets debossed with “FM5” on one side and plain on other side. Extended-release Tablets: 10 mg and 20 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Hypersensitivity to methylphenidate or other components of Methylphenidate hydrochloride extended-release tablets. Hypersensitivity reactions such as angioedema and anaphylactic reactions have been reported in patients treated with methylphenidate [ see Adverse Reactions (6) ]. Concomitant treatment with monoamine oxidase inhibitors (MAOIs), or within 14 days following discontinuation of treatment with an MAOI, because of the risk of hypertensive crises [ see Drug Interactions (7.1) ]. Patients with pheochromocytoma or a history of pheochromocytoma.
Serious reactions, including elevated blood pressure and tachyarrhythmia, have been reported in patients with pheochromocytoma or a history of pheochromocytoma who received an amphetamine product. Methylphenidate hydrochloride extended-release tablets are contraindicated in: Known hypersensitivity to methylphenidate or other product components of Methylphenidate hydrochloride extended-release tablets. (4) Concurrent treatment with a monoamine oxidase inhibitor (MAOI), or use of an MAOI within the preceding 14 days (4) .
Patients with pheochromocytoma or a history of pheochromocytoma ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS N/A Serious Cardiovascular Events: Sudden death has been reported in association with CNS-stimulant treatment at usual doses in pediatric patients with structural cardiac abnormalities or other serious heart problems. In adults, sudden death, stroke, and myocardial infarction have been reported. Avoid use in patients with known structural cardiac abnormalities, cardiomyopathy, serious heart rhythm arrhythmias, or coronary artery disease (5.2) .
Blood Pressure and Heart Rate Increases: Monitor blood pressure and pulse. Consider the benefits and risk in patients for whom an increase in blood pressure or heart rate would be problematic (5.3) . Psychiatric Adverse Reactions: Use of stimulants may cause psychotic or manic symptoms in patients with no prior history or exacerbation of symptoms in patients with pre-existing psychiatric illness.
Evaluate for pre-existing psychotic or bipolar disorder prior to Methylphenidate hydrochloride extended-release tablets use (5.4) . Priapism: Cases of painful and prolonged penile erections, and priapism have been reported with methylphenidate products. Immediate medical attention should be sought if signs or symptoms of prolonged penile erections or priapism are observed (5.5) .
Peripheral Vasculopathy, including Raynaud’s Phenomenon: Stimulants used to treat ADHD are associated with peripheral vasculopathy, including Raynaud’s phenomenon. Careful observation for digital changes is necessary during treatment with ADHD stimulants (5.6) . Long-Term Suppression of Growth in Pediatric Patients: Monitor height and weight at appropriate intervals in pediatric patients (5.7) .
5.1Potential for Abuse and Dependence CNS stimulants, including Methylphenidate hydrochloride extended-release tablets other methylphenidate-containing products, and amphetamines, have a high potential for abuse and dependence. Assess the risk of abuse prior to prescribing, and monitor for signs of abuse and dependence while on therapy [see Boxed Warning , Drug Abuse and Dependence (9.2 , 9.3 )].
5.2Serious Cardiovascular Reactions Sudden death, stroke and myocardial infarction have been reported in adults with CNS stimulant treatment at recommended doses. Sudden death has been reported in pediatric patients with structural cardiac abnormalities and other serious heart problems taking CNS stimulants at recommended doses for ADHD. Avoid use in patients with known serious structural cardiac abnormalities, cardiomyopathy, serious heart rhythm abnormalities, coronary artery disease, and other serious heart problems.
Further evaluate patients who develop exertional chest pain, unexplained syncope, or arrhythmias during Methylphenidate hydrochloride extended-release tablets treatment.
5.3Blood Pressure and Heart Rate Increases CNS stimulants cause an increase in blood pressure (mean increase approximately 2 to 4 mmHg) and heart rate (mean increase approximately 3 to 6 bpm). Individuals may have larger increases. Monitor all patients for hypertension and tachycardia.
5.4Psychiatric Adverse Reactions Exacerbation of Preexisting Psychosis CNS stimulants may exacerbate symptoms of behavior disturbance and thought disorder in patients with a preexisting psychotic disorder. Induction of a Manic Episode in Patients with Bipolar Disorder CNS stimulants may induce a manic or mixed mood episode in patients. Prior to initiating treatment, screen patients for risk factors for developing a manic episode (e.g., comorbid or history of depressive symptoms or a family history of suicide, bipolar disorder, or depression).
New Psychotic or Manic Symptoms CNS stimulants, at recommended doses, may cause psychotic or manic symptoms (e.g., hallucinations, delusional thinking, or mania) in patients without a prior history of psychotic illness or mania. If such symptoms occur, consider discontinuing Methylphenidate hydrochloride extended-release tablets. In a pooled analysis of multiple short-term, placebo-controlled studies of… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following are discussed in more detail in other sections of the labeling: Abuse and Dependence [see Boxed Warning , Warnings and Precautions (5.1) , Drug Abuse and Dependence (9.2 , 9.3 ) ] Known hypersensitivity to methylphenidate or other ingredients of Methylphenidate hydrochloride extended-release tablets [ see Contraindications (4) ] Hypertensive crisis with Concomitant Use of Monoamine Oxidase Inhibitors [see Contraindications (4) , Drug Interactions (7.1) ] Serious Cardiovascular Reactions [see Warnings and Precautions (5.2) ] Blood Pressure and Heart Rate Increases [see Warnings and Precautions (5.3) ] Psychiatric Adverse Reactions [see Warnings and Precautions (5.4) ] Priapism [see Warnings and Precautions (5.5) ] Peripheral Vasculopathy, including Raynaud’s Phenomenon [see Warnings and Precautions (5.6) ] Long-term Suppression of Growth in Pediatric Patients [see Warnings and Precautions (5.7) ] The following adverse reactions associated with the use of all Methylphenidate hydrochloride extended-release tablets and other methylphenidate products were identified in clinical trials, spontaneous reports, and literature.
Because these reactions were reported voluntarily from a population of uncertain size, it is not always possible to estimate their frequency reliably or to establish a causal relationship to drug exposure. Adverse Reactions Reported with Methylphenidate hydrochloride extended-release tablets Infections and Infestations: nasopharyngitis Blood and the Lymphatic System Disorders : leukopenia, thrombocytopenia, anemia Immune System Disorders: hypersensitivity reactions, including angioedema and anaphylaxis Metabolism and Nutrition Disorders: decreased appetite, reduced weight gain, and suppression of growth during prolonged use in pediatric patients Psychiatric Disorders: insomnia, anxiety, restlessness, agitation, psychosis (sometimes with visual and tactile hallucinations), depressed mood Nervous System Disorders: headache, dizziness, tremor, dyskinesia including choreoathetoid movements, drowsiness, convulsions, cerebrovascular disorders (including vasculitis, cerebral hemorrhages and cerebrovascular accidents), serotonin syndrome in combination with serotonergic drugs Eye Disorders: blurred vision, difficulties in visual accommodation Cardiac Disorders: tachycardia, palpitations, increased blood pressure, arrhythmias, angina pectoris Respiratory, Thoracic and Mediastinal Disorders: cough Gastrointestinal Disorders: dry mouth, nausea, vomiting, abdominal pain, dyspepsia Hepatobiliary Disorders: abnormal liver function, ranging from transaminase elevation to severe hepatic injury Skin and Subcutaneous Tissue Disorders: hyperhidrosis, pruritus, urticaria, exfoliative dermatitis, scalp hair loss, erythema multiforme rash, thrombocytopenic purpura Musculoskeletal and Connective Tissue Disorders: arthralgia, muscle cramps, rhabdomyolysis Investigations: weight loss (adult ADHD patients) Additional Adverse Reactions Reported with Other Methylphenidate-Containing Products The list below shows adverse reactions not listed for Methylphenidate hydrochloride extended-release tablets that have been reported with other methylphenidate-containing products.
Blood and Lymphatic Disorders: pancytopenia Immune System Disorders: hypersensitivity reactions such as auricular swelling, bullous conditions, eruptions, exanthemas Psychiatric Disorders: affect lability, mania, disorientation and libido changes Nervous System Disorders: migraine Eye Disorders: diplopia, mydriasis Cardiac Disorders: sudden cardiac death, myocardial infarction, bradycardia, extrasystole Vascular Disorders: peripheral coldness, Raynaud's phenomenon Respiratory, Thoracic and Mediastinal Disorders: pharyngolaryngeal pain, dyspnea Gastrointestinal Disorders: diarrhea, constipation Skin and Subcutaneous Tissue Disorders: angioneurotic edema, erythema, fixed drug eruption Musculoskeletal, Connective Tissue and bone Disorders: myalgi… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS N/A Antihypertensive drugs: Monitor blood pressure. Adjust dosage of antihypertensive drug as needed (7) Halogenated anesthetics: Avoid use of Methylphenidate hydrochloride extended-release tablets on the day of surgery if halogenated anesthetics will be used (7) Risperidone: The combined use of methylphenidate with risperidone when there is a change in dose of either or both medications may increase the risk of extrapyramidal symptoms (EPS). Monitor for signs of EPS (7) .
7.1Clinically Important Interactions with Methylphenidate hydrochloride extended-release tablets Table 1 presents clinically important drug interactions with Methylphenidate hydrochloride extended-release tablets. Table 1: Clinically Important Drug Interactions with Methylphenidate Hydrochloride Extended-Release Tablets Monoamine Oxidase Inhibitors (MAOI) Clinical Impact Concomitant use of MAOIs and CNS stimulants, including Methylphenidate hydrochloride extended-release tablets can cause hypertensive crisis. Potential outcomes include death, stroke, myocardial infarction, aortic dissection, ophthalmological complications, eclampsia, pulmonary edema, and renal failure [ see Contraindications (4) ] .
Intervention Concomitant use of Methylphenidate hydrochloride extended-release tablets with MAOIs or within 14 days after discontinuing MAOI treatment is contraindicated. Examples selegiline, tranylcypromine, isocarboxazid, phenelzine, linezolid, methylene blue Antihypertensive Drugs Clinical Impact Methylphenidate hydrochloride extended-release tablets may decrease the effectiveness of drugs used to treat hypertension [ see Warnings and Precautions (5.3) ] . Intervention Monitor blood pressure and adjust the dosage of the antihypertensive drug as needed.
Examples Potassium-sparing and thiazide diuretics, calcium channel blockers, angiotensin-converting-enzyme (ACE) inhibitors, angiotensin II receptor blockers (ARBs), beta blockers, centrally acting alpha-2 receptor agonists Halogenated Anesthetics Clinical Impact Concomitant use of halogenated anesthetics and Methylphenidate hydrochloride extended-release tablets may increase the risk of sudden blood pressure and heart rate increase during surgery. Intervention Avoid use of Methylphenidate hydrochloride extended-release tablets in patients being treated with anesthetics on the day of surgery.
Examples halothane, isoflurane, enflurane, desflurane, sevoflurane Risperidone The combined use of methylphenidate with risperidone when there is a change in dose of either or both medications may increase the risk of extrapyramidal symptoms (EPS). Monitor for signs of EPS.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS N/A
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to ADHD medications, including Methylphenidate hydrochloride extended-release tablets, during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for ADHD Medications at 1-866-961-2388 or visit https://womensmentalhealth.org/adhd-medications/ Risk Summary Published studies and postmarketing reports on methylphenidate use during pregnancy have not identified a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes.
There may be risks to the fetus associated with the use of CNS stimulants use during pregnancy [see Clinical Considerations] . No effects on morphological development were observed in embryo-fetal development studies with oral administration of methylphenidate to pregnant rats and rabbits during organogenesis at doses up to 10 and 15 times, respectively, the maximum recommended human dose (MRHD) of 60 mg/day given to adolescents on a mg/m 2 basis. However, spina bifida was observed in rabbits at a dose 52 times the MRHD given to adolescents.
A decrease in pup body weight was observed in a pre- and post-natal development study with oral administration of methylphenidate to rats throughout pregnancy and lactation at doses 6 times the MRHD given to adolescents (see Data) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions CNS stimulants, such as Methylphenidate hydrochloride extended-release tablets, can cause vasoconstriction and thereby decrease placental perfusion. No fetal and/or neonatal adverse reactions have been reported with the use of therapeutic doses of methylphenidate during pregnancy; however, premature delivery and low birth weight infants have been reported in amphetamine-dependent mothers.
Data Animal Data In embryo-fetal development studies conducted in rats and rabbits, methylphenidate was administered orally at doses of up to 75 and 200 mg/kg/day, respectively, during the period of organogenesis. Malformations (increased incidence of fetal spina bifida) were observed in rabbits at the highest dose, which is approximately 52 times the MRHD of 60 mg/day given to adolescents on a mg/m 2 basis. The no effect level for embryo-fetal development in rabbits was 60 mg/kg/day (15times the MRHD given to adolescents on a mg/m 2 basis).
There was no evidence of morphological development effects in rats, although increased incidences of fetal skeletal variations were seen at the highest dose level (10 times the MRHD of 60 mg/day given to adolescents on a mg/m 2 basis), which was also maternally toxic. The no effect level for embryo-fetal development in rats was 25 mg/kg/day (3 times the MRHD on a mg/m 2 basis). When methylphenidate was administered to rats throughout pregnancy and lactation at doses of up to 45 mg/kg/day, offspring body weight gain was decreased at the highest dose (6 times the MRHD of 60 mg/day given to adolescents on a mg/m 2 basis), but no other effects on postnatal development were observed.
The no effect level for pre- and postnatal development in rats was 15 mg/kg/day (~2 times the MRHD given to adolescents on a mg/m 2 basis).
8.2Lactation Risk Summary Limited published literature, based on milk sampling from seven mothers reports that methylphenidate is present in human milk, which resulted in infant doses of 0.16% to 0.7% of the maternal weight-adjusted dosage and a milk/plasma ratio ranging between 1.1 and 2.7. There are no reports of adverse effects… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to ADHD medications, including Methylphenidate hydrochloride extended-release tablets, during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for ADHD Medications at 1-866-961-2388 or visit https://womensmentalhealth.org/adhd-medications/ Risk Summary Published studies and postmarketing reports on methylphenidate use during pregnancy have not identified a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes.
There may be risks to the fetus associated with the use of CNS stimulants use during pregnancy [see Clinical Considerations] . No effects on morphological development were observed in embryo-fetal development studies with oral administration of methylphenidate to pregnant rats and rabbits during organogenesis at doses up to 10 and 15 times, respectively, the maximum recommended human dose (MRHD) of 60 mg/day given to adolescents on a mg/m 2 basis. However, spina bifida was observed in rabbits at a dose 52 times the MRHD given to adolescents.
A decrease in pup body weight was observed in a pre- and post-natal development study with oral administration of methylphenidate to rats throughout pregnancy and lactation at doses 6 times the MRHD given to adolescents (see Data) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions CNS stimulants, such as Methylphenidate hydrochloride extended-release tablets, can cause vasoconstriction and thereby decrease placental perfusion. No fetal and/or neonatal adverse reactions have been reported with the use of therapeutic doses of methylphenidate during pregnancy; however, premature delivery and low birth weight infants have been reported in amphetamine-dependent mothers.
Data Animal Data In embryo-fetal development studies conducted in rats and rabbits, methylphenidate was administered orally at doses of up to 75 and 200 mg/kg/day, respectively, during the period of organogenesis. Malformations (increased incidence of fetal spina bifida) were observed in rabbits at the highest dose, which is approximately 52 times the MRHD of 60 mg/day given to adolescents on a mg/m 2 basis. The no effect level for embryo-fetal development in rabbits was 60 mg/kg/day (15times the MRHD given to adolescents on a mg/m 2 basis).
There was no evidence of morphological development effects in rats, although increased incidences of fetal skeletal variations were seen at the highest dose level (10 times the MRHD of 60 mg/day given to adolescents on a mg/m 2 basis), which was also maternally toxic. The no effect level for embryo-fetal development in rats was 25 mg/kg/day (3 times the MRHD on a mg/m 2 basis). When methylphenidate was administered to rats throughout pregnancy and lactation at doses of up to 45 mg/kg/day, offspring body weight gain was decreased at the highest dose (6 times the MRHD of 60 mg/day given to adolescents on a mg/m 2 basis), but no other effects on postnatal development were observed.
The no effect level for pre- and postnatal development in rats was 15 mg/kg/day (~2 times the MRHD given to adolescents on a mg/m 2 basis).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of methylphenidate hydrochloride extended-release tablets have not been established in pediatric patients below the age of 6 years. In studies evaluating extended-release methylphenidate products, patients 4 to <6 years of age had higher systemic methylphenidate exposures than those observed in older pediatric patients at the same dosage. Pediatric patients 4 to <6 years of age also had a higher incidence of adverse reactions, including weight loss.
The safety and effectiveness of Methylphenidate hydrochloride extended-release tablets for the treatment of ADHD have been established in pediatric patients 6 to 17 years. Long-Term Suppression of Growth Growth should be monitored during treatment with stimulants, including Methylphenidate hydrochloride extended-release tablets. Pediatric patients who are not growing or gaining weight as expected may need to have their treatment interrupted [ see Warnings and Precautions (5.7) ] .
Juvenile Animal Toxicity Data Rats treated with methylphenidate early in the postnatal period through sexual maturation demonstrated a decrease in spontaneous locomotor activity in adulthood. A deficit in acquisition of a specific learning task was observed in females only. The doses at which these findings were observed are at least 4 times the MRHD of 60 mg/day given to children on a mg/m 2 basis.
In a study conducted in young rats, methylphenidate was administered orally at doses of up to 100 mg/kg/day for 9 weeks, starting early in the postnatal period (postnatal Day 7) and continuing through sexual maturity (postnatal Week 10). When these animals were tested as adults (postnatal Weeks 13 to 14), decreased spontaneous locomotor activity was observed in males and females previously treated with 50 mg/kg/day (approximately 4 times the MRHD of 60 mg/day given to children on a mg/m 2 basis) or greater, and a deficit in the acquisition of a specific learning task was seen in females exposed to the highest dose (8 times the MRHD given to children on a mg/m 2 basis).
The no effect level for juvenile neurobehavioral development in rats was 5 mg/kg/day (approximately 0.5 times the MRHD given to children on a mg/m 2 basis). The clinical significance of the long-term behavioral effects observed in rats is unknown.
🧓 Geriatric Use ▾
8.5Geriatric Use Methylphenidate hydrochloride tablet has not been studied in the geriatric population.
🆘 Overdosage ▾
10 OVERDOSAGE Human Experience Signs and symptoms of acute overdosage, resulting principally from overstimulation of the central nervous system and from excessive sympathomimetic effects, may include the following: nausea, vomiting, diarrhea, restlessness, anxiety, agitation, tremors, hyperreflexia, muscle twitching, convulsions (which may be followed by coma), euphoria, confusion, hallucinations, delirium, sweating, flushing, headache, hyperpyrexia, tachycardia, palpitations, cardiac arrhythmias, hypertension, hypotension, tachypnea, mydriasis, dryness of mucous membranes, and rhabdomyolysis.
Posterior reversible encephalopathy syndrome (PRES) symptoms including headache, altered mental status, hypertension, seizures, and visual disturbances including blindness have occurred in the setting of an amphetamine product overdose. Symptoms of PRES are usually reversible but may evolve into ischemic stroke or cerebral hemorrhage. Diagnosis of PRES should be confirmed by radiological procedure (e.g., MRI).
Overdose Management Consult with a Certified Poison Control Center (1-800-222-1222) for the latest recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY N/A
12.1Mechanism of Action Methylphenidate hydrochloride is a central nervous system (CNS) stimulant. The mode of therapeutic action in ADHD and narcolepsy is not known.
12.2Pharmacodynamics Methylphenidate is a racemic mixture comprised of the d- and l-threo enantiomers. The d-threo enantiomer is more pharmacologically active than the l-threo enantiomer. Methylphenidate blocks the reuptake of norepinephrine and dopamine into the presynaptic neuron and increase the release of these monoamines into the extraneuronal space.
Cardiac Electrophysiology A formal QT study has not been conducted in patients taking Methylphenidate hydrochloride extended-release tablets. The effect of dexmethylphenidate, the pharmacologically active d-enantiomer of Methylphenidate hydrochloride tablets on the QT interval was evaluated in a double-blind, placebo- and open-label active (moxifloxacin)-controlled study following single doses of dexmethylphenidate XR 40 mg (maximum recommended adult total daily dosage) in 75 healthy volunteers. Electrocardiograms (ECGs) were collected up to 12 hours postdose.
Frederica’s method for heart rate correction was employed to derive the corrected QT interval (QTcF). The maximum mean prolongation of QTcF intervals was less than 5 ms, and the upper limit of the 90% confidence interval (CI) was below 10 ms for all time-matched comparisons versus placebo. This was below the threshold of clinical concern and there was no evident exposure response relationship.
12.3Pharmacokinetics Absorption Methylphenidate hydrochloride in the extended-release tablets is more slowly but as extensively absorbed as in the regular tablets. Relative bioavailability of the extended-release tablet compared to the Methylphenidate hydrochloride tablet measured by the urinary excretion of Methylphenidate hydrochloride major metabolite (α-phenyl-2-piperidine acetic acid) was 105% (49% to 168%) in children and 101% (85% to 152%) in adults. The time to peak rate in children was 1.9 hours (0.3 to 4.4 hours) for the Methylphenidate hydrochloride tablets and 4.7 hours (1.3 to 8.2 hours) for the Methylphenidate hydrochloride extended-release tablets.
An average of 67% of extended-release tablet dose was excreted in children as compared to 86% in adults. Effect of Food After a high-fat meal, both area under the curve (AUC) (by 25%) and C max (by 27%) are higher. Time to C max (T max ) is faster after a high-fat meal (median T max : 2.5 hours) as compared to without food (median T max : 3 hours).
Distribution Binding to plasma proteins is low (10% to 33%). The volume of distribution was 2.65 ±
1.11L/kg for d-methylphenidate and 1.80 ±
0.91L/kg for l-methylphenidate. Elimination The systemic clearance is 0.40 ±
0.12L/h/kg for d-methylphenidate and 0.73 ±
0.28L/h/kg for l-methylphenidate. Metabolism Methylphenidate is metabolized primarily by de-esterification to alpha-phenyl-piperidine acetic acid (ritalinic acid), which has little or no pharmacologic activity. Excretion After oral administration, 78% to 97% of the dose is excreted in the urine and 1% to 3% in feces in the form of metabolites within 48 to 96 hours.
Most of the dose is excreted in the urine as alpha-phenyl-2-piperidine acetic acid (60% to 86%). The cumulative urinary excretion of alpha-phenyl-2-piperidine acetic acid are not significantly different for Methylphenidate hydrochloride extended-release tablets. Studies in Specific Populations Male and Female Patients In a clinical study involving adult subjects who received Methylphenidate hydrochloride extended-release tablets plasma concentrations of Methylphenidate hydrochloride's major metabolite appeared to be greater in females than in males.
No gender differences were observed for Methylphenidate hydrochloride plasma concentration in the same subjects. Racial or Ethnic Groups There is insufficient experience with the use of Methylphenidate hydrochloride extended-release to detect ethnic variations in ph… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Methylphenidate hydrochloride is a central nervous system (CNS) stimulant. The mode of therapeutic action in ADHD and narcolepsy is not known.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Methylphenidate hydrochloride extended-release tablets, USP are available as follows: 10 mg: White to off white, round shaped, uncoated, tablets debossed with “FM4” on one side and plain on other side. Bottles of 100 tablets NDC 51407-527-01 20 mg: White to off white, round shaped, uncoated, tablets debossed with “FM5” on one side and plain on other side. Bottles of 100 tablets NDC 51407-528-01 NOTE : Methylphenidate hydrochloride extended-release tablets, USP are color-additive free.
Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C to 30°C (59°F to 86°F) [See USP Controlled Room Temperature]. Protect from moisture. Dispense in a tight, light-resistant container as defined in the USP, with a child-resistant closure.
Disposal Comply with local laws and regulations on drug disposal of CNS stimulants. Dispose of remaining, unused, or expired Methylphenidate hydrochloride extended-release tablets, USP by a medicine takeback program or by an authorized collector registered with the Drug Enforcement Administration. If no take-back program or authorized collector is available, mix Methylphenidate hydrochloride extended-release tablets, USP with an undesirable, nontoxic substance to make it less appealing to children and pets.
Place the mixture in a container such as a sealed plastic bag and discard Methylphenidate hydrochloride extended-release tablets, USP in the household trash.
📋 Description ▾
11 DESCRIPTION Methylphenidate hydrochloride extended-release tablets, USP contains methylphenidate hydrochloride a CNS stimulant. It is available as extended-release tablets of 10 mg and 20 mg strength for oral administration. Methylphenidate hydrochloride is methyl α-phenyl-2-piperidineacetate hydrochloride, and its structural formula is: Methylphenidate hydrochloride USP is a white, odorless, fine crystalline powder.
Its solutions are acid to litmus. It is freely soluble in water and in methanol, soluble in alcohol, and slightly soluble in chloroform and in acetone. Its molecular weight is 269.77 g/mol.
Methylphenidate hydrochloride extended-release tablets, USP contains the following inactive ingredients: hypromellose, microcrystalline cellulose, lactose monohydrate, colloidal silicon dioxide and magnesium stearate. FDA approved dissolution test differs from the USP dissolution test. methyl-ER-tabs-str
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Controlled Substance Status/High Potential for Abuse and Dependence Advise patients that Methylphenidate hydrochloride extended-release tablets are controlled substances, and they can be abused and lead to dependence. Instruct patients that they should not give Methylphenidate hydrochloride extended-release tablets to anyone else.
Advise patients to store Methylphenidate hydrochloride extended-release tablets in a safe place, preferably locked, to prevent abuse. Advise patients to comply with laws and regulations on drug disposal. Advise patients to dispose of remaining, unused, or expired Methylphenidate hydrochloride extended-release tablets by a medicine take-back program if available [see Boxed Warning , Warnings and Precautions (5.1) , Drug Abuse and Dependence (9.1, 9.2, 9.3) , How Supplied/Storage and Handling (16) ] .
Serious Cardiovascular Risks Advise patients that there is a potential serious cardiovascular risk including sudden death, myocardial infarction, stroke, and hypertension with Methylphenidate hydrochloride extended-release tablets use. Instruct patients to contact a healthcare provider immediately if they develop symptoms such as exertional chest pain, unexplained syncope, or other symptoms suggestive of cardiac disease [ see Warnings and Precautions (5.2) ]. Blood Pressure and Heart Rate Increases Instruct patients that Methylphenidate hydrochloride extended-release tablets can cause elevations of their blood pressure and pulse rate [ see Warnings and Precautions (5.3) ] .
Psychiatric Risks Advise patients that Methylphenidate hydrochloride extended-release tablets at recommended doses, can cause psychotic or manic symptoms, even in patients without prior history of psychotic symptoms or mania [ see Warnings and Precautions (5.4) ]. Priapism Advise patients of the possibility of painful or prolonged penile erections (priapism). Instruct them to seek immediate medical attention in the event of priapism [ see Warnings and Precautions (5.5) ] .
Circulation Problems in Fingers and Toes [Peripheral vasculopathy, including Raynaud’s Phenomenon] Instruct patients about the risk of peripheral vasculopathy, including Raynaud’s phenomenon, and associated signs and symptoms: fingers or toes may feel numb, cool, painful, and/or may change color from pale, to blue, to red. Instruct patients to report to their physician any new numbness, pain, skin color change, or sensitivity to temperature in fingers or toes. Instruct patients to call their physician immediately with any signs of unexplained wounds appearing on fingers or toes while taking Methylphenidate hydrochloride extended-release tablets.
Further clinical evaluation (e.g., rheumatology referral) may be appropriate for certain patients [ see Warnings and Precautions (5.6) ] . Suppression of Growth Advise patients that Methylphenidate hydrochloride extended-release tablets may cause slowing of growth and weight loss [ see Warnings and Precautions (5.7) ]. Pregnancy Registry Advise patients that there is a pregnancy exposure registry that monitors pregnancy outcomes in patients exposed to ADHD medications, including Methylphenidate hydrochloride extended-release tablets, during pregnancy [see Use in Specific Populations (8.1) ] .
The Medication Guide may also be obtained by calling 877-770-3183. Manufactured by: Granules Pharmaceuticals Inc. Chantilly, VA 20151 Marketed by: GSMS, Inc.
Camarillo, CA 93012 USA Rev. 07/2026
💬 Medication Guide ▾
MEDICATION GUIDE MEDICATION GUIDE Methylphenidate Hydrochloride Extended-Release Tablets (meth" il fen' i date hye" droe klor' ide) What is the most important information I should know about Methylphenidate hydrochloride extended-release tablets? Methylphenidate hydrochloride extended-release tablets is a federal controlled substance (CII) because it can be abused or lead to dependence. Keep Methylphenidate hydrochloride extended-release tablets in a safe place to prevent misuse and abuse.
Selling or giving away Methylphenidate hydrochloride extended-release tablets may harm others and is against the law. Tell your doctor if you or your child have ever abused or been dependent on alcohol, prescription medicines or street drugs. The following have been reported with use of methylphenidate hydrochloride and other stimulant medicines: 1.
Heart-related problems: sudden death in patients who have heart problems or heart defects stroke and heart attack in adults increased blood pressure and heart rate Tell your doctor if you or your child have any heart problems, heart defects, high blood pressure, or a family history of these problems. Your doctor should check you or your child carefully for heart problems before starting Methylphenidate hydrochloride extended-release tablets. Your doctor should check you or your child’s blood pressure and heart rate regularly during treatment with Methylphenidate hydrochloride extended-release tablets.
Call your doctor right away if you or your child has any signs of heart problems such as chest pain, shortness of breath, or fainting while taking Methylphenidate hydrochloride extended-release tablets. 2. Mental (Psychiatric) problems: All Patients new or worse behavior and thought problems new or worse bipolar illness new or worse aggressive behavior or hostility new psychotic symptoms (such as hearing voices, believing things that are not true, are suspicious) or new manic symptoms Tell your doctor about any mental problems you or your child have, or about a family history of suicide, bipolar illness, or depression.
Call your doctor right away if you or your child have any new or worsening mental symptoms or problems while taking Methylphenidate hydrochloride extended-release tablets, especially seeing or hearing things that are not real, believing things that are not real, or are suspicious. What is Methylphenidate hydrochloride extended-release tablets? Methylphenidate hydrochloride extended-release tablet is a central nervous system (CNS) stimulant prescription medicine used for the treatment of Attention Deficit Hyperactivity Disorder (ADHD) in people 6 years of age and older.
Methylphenidate hydrochloride extended-release tablets may help increase attention and decrease impulsiveness and hyperactivity in patients with ADHD. Methylphenidate hydrochloride extended-release tablets are not recommended for use in children under 6 years of age with ADHD. Methylphenidate hydrochloride extended-release tablets should be used as a part of a total treatment program for ADHD that may include counseling or other therapies.
Methylphenidate hydrochloride extended-release tablets are also used in the treatment of a sleep disorder called narcolepsy. Who should not take Methylphenidate hydrochloride extended-release tablets? Methylphenidate hydrochloride extended-release tablets should not be taken if you or your child: are allergic to methylphenidate hydrochloride, or any of the ingredients in Methylphenidate hydrochloride extended-release tablets.
See the end of this Medication Guide for a complete list of ingredients in Methylphenidate hydrochloride extended-release tablets. are taking or have taken within the past 14 days an anti-depression medicine called a monoamine oxidase inhibitor or MAOI. have a condition called pheochromocytoma (a rare tumor that usually grows in the adrenal glands which are above your kidneys). Methylphenidate hydrochloride extended-release tablets may not be right for you or you… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption Methylphenidate hydrochloride in the extended-release tablets is more slowly but as extensively absorbed as in the regular tablets. Relative bioavailability of the extended-release tablet compared to the Methylphenidate hydrochloride tablet measured by the urinary excretion of Methylphenidate hydrochloride major metabolite (α-phenyl-2-piperidine acetic acid) was 105% (49% to 168%) in children and 101% (85% to 152%) in adults. The time to peak rate in children was 1.9 hours (0.3 to 4.4 hours) for the Methylphenidate hydrochloride tablets and 4.7 hours (1.3 to 8.2 hours) for the Methylphenidate hydrochloride extended-release tablets.
An average of 67% of extended-release tablet dose was excreted in children as compared to 86% in adults. Effect of Food After a high-fat meal, both area under the curve (AUC) (by 25%) and C max (by 27%) are higher. Time to C max (T max ) is faster after a high-fat meal (median T max : 2.5 hours) as compared to without food (median T max : 3 hours).
Distribution Binding to plasma proteins is low (10% to 33%). The volume of distribution was 2.65 ±
1.11L/kg for d-methylphenidate and 1.80 ±
0.91L/kg for l-methylphenidate. Elimination The systemic clearance is 0.40 ±
0.12L/h/kg for d-methylphenidate and 0.73 ±
0.28L/h/kg for l-methylphenidate. Metabolism Methylphenidate is metabolized primarily by de-esterification to alpha-phenyl-piperidine acetic acid (ritalinic acid), which has little or no pharmacologic activity. Excretion After oral administration, 78% to 97% of the dose is excreted in the urine and 1% to 3% in feces in the form of metabolites within 48 to 96 hours.
Most of the dose is excreted in the urine as alpha-phenyl-2-piperidine acetic acid (60% to 86%). The cumulative urinary excretion of alpha-phenyl-2-piperidine acetic acid are not significantly different for Methylphenidate hydrochloride extended-release tablets. Studies in Specific Populations Male and Female Patients In a clinical study involving adult subjects who received Methylphenidate hydrochloride extended-release tablets plasma concentrations of Methylphenidate hydrochloride's major metabolite appeared to be greater in females than in males.
No gender differences were observed for Methylphenidate hydrochloride plasma concentration in the same subjects. Racial or Ethnic Groups There is insufficient experience with the use of Methylphenidate hydrochloride extended-release to detect ethnic variations in pharmacokinetics. Patients with Renal Impairment Methylphenidate hydrochloride has not been studied in renally-impaired patients.
Renal impairment is expected to have minimal effect on the pharmacokinetics of methylphenidate since less than 1% of a radiolabeled dose is excreted in the urine as unchanged compound, and the major metabolite (ritalinic acid), has little or no pharmacologic activity. Patients with Hepatic Impairment Methylphenidate hydrochloride has not been studied in patients with hepatic impairment. Hepatic impairment is expected to have minimal effect on the pharmacokinetics of methylphenidate since it is metabolized primarily to ritalinic acid by nonmicrosomal hydrolytic esterases that are widely distributed throughout the body.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Methylphenidate is a racemic mixture comprised of the d- and l-threo enantiomers. The d-threo enantiomer is more pharmacologically active than the l-threo enantiomer. Methylphenidate blocks the reuptake of norepinephrine and dopamine into the presynaptic neuron and increase the release of these monoamines into the extraneuronal space.
Cardiac Electrophysiology A formal QT study has not been conducted in patients taking Methylphenidate hydrochloride extended-release tablets. The effect of dexmethylphenidate, the pharmacologically active d-enantiomer of Methylphenidate hydrochloride tablets on the QT interval was evaluated in a double-blind, placebo- and open-label active (moxifloxacin)-controlled study following single doses of dexmethylphenidate XR 40 mg (maximum recommended adult total daily dosage) in 75 healthy volunteers. Electrocardiograms (ECGs) were collected up to 12 hours postdose.
Frederica’s method for heart rate correction was employed to derive the corrected QT interval (QTcF). The maximum mean prolongation of QTcF intervals was less than 5 ms, and the upper limit of the 90% confidence interval (CI) was below 10 ms for all time-matched comparisons versus placebo. This was below the threshold of clinical concern and there was no evident exposure response relationship.
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE N/A
9.1Controlled Substance Methylphenidate hydrochloride extended-release tablets contain methylphenidate hydrochloride, a Schedule II controlled substance.
9.2Abuse CNS stimulants, including Methylphenidate hydrochloride extended-release tablets have a high potential for abuse. Abuse is characterized by impaired control over drug use despite harm, and craving. Signs and symptoms of CNS stimulant abuse include increased heart rate, respiratory rate, blood pressure, and/or sweating, dilated pupils, hyperactivity, restlessness, insomnia, decreased appetite, loss of coordination, tremors, flushed skin, vomiting, and/or abdominal pain.
Anxiety, psychosis, hostility, aggression, and suicidal or homicidal ideation have also been observed. Abusers of CNS stimulants may chew, snort, inject, or use other unapproved routes of administration which may result in overdose and death [ see Overdosage (10) ] . To reduce the abuse of CNS stimulants including Methylphenidate hydrochloride extended-release tablets assess the risk of abuse prior to prescribing.
After prescribing, keep careful prescription records, educate patients and their families about abuse and on proper storage and disposal of CNS stimulants [ see How Supplied/Storage and Handling (16) ] , monitor for signs of abuse while on therapy, and reevaluate the need for Methylphenidate hydrochloride extended-release tablets use.
9.3Dependence Tolerance Tolerance (a state of adaptation in which exposure to a drug results in a reduction of the drug’s desired and/or undesired effects over time) can occur during chronic therapy with CNS stimulants, including Methylphenidate hydrochloride extended-release tablets. Dependence Physical dependence (which is manifested by a withdrawal syndrome produced by abrupt cessation, rapid dose reduction, or administration of an antagonist) may occur in patients treated with CNS stimulants including Methylphenidate hydrochloride extended-release tablets.
Withdrawal symptoms after abrupt cessation following prolonged high-dosage administration of CNS stimulants include dysphoric mood; fatigue; vivid, unpleasant dreams; insomnia or hypersomnia; increased appetite; and psychomotor retardation or agitation.
🔒 Controlled Substance ▾
9.1Controlled Substance Methylphenidate hydrochloride extended-release tablets contain methylphenidate hydrochloride, a Schedule II controlled substance.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY N/A
13.1Carcinogenesis, Mutagenesis, and Impairment of Fertility Carcinogenesis In a lifetime carcinogenicity study carried out in B6C3F1 mice, methylphenidate caused an increase in hepatocellular adenomas, and in males only, an increase in hepatoblastomas at a daily dose of approximately 60 mg/kg/day. This dose is approximately 2 times the MRHD of 60 mg/day given to children on mg/m 2 basis. Hepatoblastoma is a relatively rare rodent malignant tumor type.
There was no increase in total malignant hepatic tumors. The mouse strain used is sensitive to the development of hepatic tumors and the significance of these results to humans is unknown. Methylphenidate did not cause any increase in tumors in a lifetime carcinogenicity study carried out in F344 rats; the highest dose used was approximately 45 mg/kg/day, which is approximately 4 times the MRHD (children) on a mg/m 2 basis.
In a 24-week carcinogenicity study in the transgenic mouse strain p53+/-, which is sensitive to genotoxic carcinogens, there was no evidence of carcinogenicity. Male and female mice were fed diets containing the same concentration of methylphenidate as in the lifetime carcinogenicity study; the high-dose groups were exposed to 60 to 74 mg/kg/day of methylphenidate. Mutagenesis Methylphenidate was not mutagenic in the in vitro Ames reverse mutation assay, in the in vitro mouse lymphoma cell forward mutation assay, or in the in vitro chromosomal aberration assay using human lymphocytes.
Sister chromatid exchanges and chromosome aberrations were increased, indicative of a weak clastogenic response, in an in vitro assay in cultured Chinese Hamster Ovary (CHO) cells. Methylphenidate was negative in vivo in males and females in the mouse bone marrow micronucleus assay. Impairment of Fertility No human data on the effect of methylphenidate on fertility are available.
Methylphenidate did not impair fertility in male or female mice that were fed diets containing the drug in an 18-week continuous breeding study. The study was conducted at doses up to 160 mg/kg/day, approximately 10 times the MRHD of 60 mg/day given to adolescents on a mg/m 2 basis.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, and Impairment of Fertility Carcinogenesis In a lifetime carcinogenicity study carried out in B6C3F1 mice, methylphenidate caused an increase in hepatocellular adenomas, and in males only, an increase in hepatoblastomas at a daily dose of approximately 60 mg/kg/day. This dose is approximately 2 times the MRHD of 60 mg/day given to children on mg/m 2 basis. Hepatoblastoma is a relatively rare rodent malignant tumor type.
There was no increase in total malignant hepatic tumors. The mouse strain used is sensitive to the development of hepatic tumors and the significance of these results to humans is unknown. Methylphenidate did not cause any increase in tumors in a lifetime carcinogenicity study carried out in F344 rats; the highest dose used was approximately 45 mg/kg/day, which is approximately 4 times the MRHD (children) on a mg/m 2 basis.
In a 24-week carcinogenicity study in the transgenic mouse strain p53+/-, which is sensitive to genotoxic carcinogens, there was no evidence of carcinogenicity. Male and female mice were fed diets containing the same concentration of methylphenidate as in the lifetime carcinogenicity study; the high-dose groups were exposed to 60 to 74 mg/kg/day of methylphenidate. Mutagenesis Methylphenidate was not mutagenic in the in vitro Ames reverse mutation assay, in the in vitro mouse lymphoma cell forward mutation assay, or in the in vitro chromosomal aberration assay using human lymphocytes.
Sister chromatid exchanges and chromosome aberrations were increased, indicative of a weak clastogenic response, in an in vitro assay in cultured Chinese Hamster Ovary (CHO) cells. Methylphenidate was negative in vivo in males and females in the mouse bone marrow micronucleus assay. Impairment of Fertility No human data on the effect of methylphenidate on fertility are available.
Methylphenidate did not impair fertility in male or female mice that were fed diets containing the drug in an 18-week continuous breeding study. The study was conducted at doses up to 160 mg/kg/day, approximately 10 times the MRHD of 60 mg/day given to adolescents on a mg/m 2 basis.
📄 Recent Major Changes ▾
Contraindications ( 4 ) 07/2026
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 10 mg Tablet Bottle Label Package Label – 10 mg NDC 51407-527-01 Methylphenidate Hydrochloride Extended-Release Tablets, USP CII 10 mg PHARMACIST: Dispense the enclosed Medication Guide to each patient Rx Only 100 Tablets 51407-527-01.jpg
PRINCIPAL DISPLAY PANEL - 20 mg Tablet Bottle Label NDC 51407-528-01 Methylphenidate Hydrochloride Extended-Release Tablets, USP CII 20 mg PHARMACIST: Dispense the enclosed Medication Guide to each patient Rx Only 100 Tablets 51407-528-01.jpg
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |