
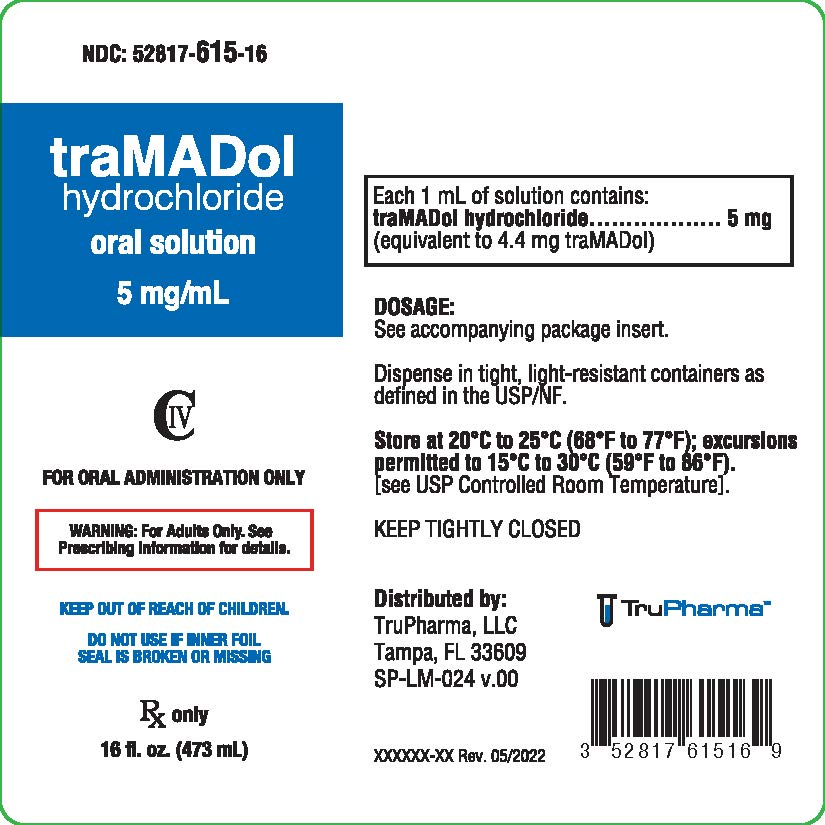
Tramadol Hydrochloride 5 mg/mL Solution, 473 mL — NDC 52817-615-16 (Billing 52817-0615-16)
This is a package of 473 mL of Tramadol Hydrochloride 5 mg/mL Solution from TruPharma, LLC, marketed since Sep 2020 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 52817-615-16 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 52817 labeler · 615 product · 16 package
- Package marketed since
- Jan 25, 2023
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 473 mL per package
- Barcode (UPC-A, from the NDC)
- 3 5281761516 9
- FDA record last changed
- Jul 24, 2026
Other active recalls for Tramadol Hydrochloride (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 081474
- GCN: 48598
- GPI-14 (Medi-Span): 65100095102005
- HICL (First Databank): 008317
- AHFS class code: 28:08.08.00
- RxCUI (RxNorm): 2395808
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Opioid Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Tramadol is used to relieve certain types of pain. Tramadol is in a class of medications called opiate (narcotic) analgesics. It works by changing the way the brain and nervous system respond to pain.
Read the full MedlinePlus article ↗- It treats pain that is severe enough to need an opioid when other options haven’t worked or can’t be tolerated. Extended-release forms are for ongoing, around-the-clock pain, not a...
- Take it by mouth exactly as prescribed. If you have extended-release tablets, swallow them whole, never crush, chew or cut them. Don’t take it with other tramadol products.
- Dizziness, nausea, constipation, headache, sleepiness, itching and dry mouth are common. Call your doctor for seizures, severe dizziness, or agitation, fever and shaking. Slow brea...
- Avoid alcohol. Mixing tramadol with alcohol, sleep aids, benzodiazepines or other opioids can cause dangerous sedation and slowed breathing. Tell me about any antidepressants, MAOI...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 52817-0615-16 You're viewing this Main listing | 473 mL in 1 BOTTLE | 2023-01-25 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Tramadol Hydrochloride 5 mg/mLthis 52817-0615-16 | TruPharma, | 473 ml | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 11103452 ↗ | Method of use | U-3197 | Sep 1, 2040 |
| US 11752103 ↗ | Method of use | U-3197 | Sep 1, 2040 |
Is there a generic version of TRAMADOL HCL 5 MG/ML SOLUTION?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 2968PHW8QP
A weak organic acid derived from citrus fruits or made through fermentation. It works as a buffer to control pH, a preservative to extend shelf life, and a flavoring agent in medications.
-
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII OJ245FE5EU
Sodium benzoate is a salt derived from benzoic acid, a preservative. It's added to medicines to prevent growth of bacteria, fungi, and other microorganisms that could spoil the product.
-
UNII 96K6UQ3ZD4
Sucralose is a synthetic sweetener made from sugar. It's added to medicines to improve taste without adding calories, helping make bitter or unpleasant-tasting drugs easier to take.
-
UNII B22547B95K
A salt derived from citric acid that helps maintain the proper acid-base balance in the medicine. It's used as a buffer to keep the product stable and at the right pH level.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from TruPharma, LLC labeler code 52817
- Clonidine Transdermal System USP, 0.2 mg/day .2 mg/d Patch NDC 52817-506-04
- Clonidine Transdermal System USP, 0.3 mg/day .3 mg/d Patch NDC 52817-507-04
- VERSACLOZ Clozapine 50 mg/mL Suspension NDC 52817-601-38
- Clonidine Transdermal System USP, 0.1 mg/day .1 mg/d Patch NDC 52817-610-04
- Clonidine Transdermal System USP, 0.2 mg/day .2 mg/d Patch NDC 52817-611-04
- Clonidine Transdermal System USP, 0.3 mg/day .3 mg/d Patch NDC 52817-612-04
- Baclofen 10 mg/5mL Solution NDC 52817-620-08
- apomorphine hydrocloride APOMORPHINE HYDROCHLORIDE 30 mg/3mL Injection NDC 52817-720-05
- Clotrimazole Topical Solution USP, 1% 10 mg/mL Solution NDC 52817-800-30
- Triamcinolone Acetonide 1 mg/g Cream NDC 52817-811-15
- Aminocaproic acid .25 g/mL Solution NDC 52817-815-08
- Acetic Acid 20.65 mg/mL Solution NDC 52817-816-15
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: RISK OF MEDICATION ERRORS; ADDICTION, ABUSE, and MISUSE; RISK EVALUATION and MITIGATION STRATEGY (REMS); LIFE-THREATENING RESPIRATORY DEPRESSION; ACCIDENTAL INGESTION; ULTRA-RAPID METABOLISM OF TRAMADOL and OTHER RISK FACTORS FOR LIFE-THREATENING RESPIRATORY DEPRESSION IN CHILDREN; NEONATAL OPIOID WITHDRAWAL SYNDROME; INTERACTIONS WITH DRUGS AFFECTING CYTOCHROME P450 ISOENZYMES; and RISKS FROM CONCOMITANT USE WITH BENZODIAZEPINES OR OTHER CNS DEPRESSANTS WARNING: RISK OF MEDICATION ERRORS; ADDICTION, ABUSE, and MISUSE; RISK EVALUATION and MITIGATION STRATEGY (REMS); LIFE-THREATENING RESPIRATORY DEPRESSION; ACCIDENTAL INGESTION; ULTRA-RAPID METABOLISM OF TRAMADOL and OTHER RISK FACTORS FOR LIFE-THREATENING RESPIRATORY DEPRESSION IN CHILDREN; NEONATAL OPIOID WITHDRAWAL SYNDROME; INTERACTIONS WITH DRUGS AFFECTING CYTOCHROME P450 ISOENZYMES; and RISKS FROM CONCOMITANT USE WITH BENZODIAZEPINES OR OTHER CNS DEPRESSANTS See full prescribing information for complete boxed warning.
Ensure accuracy when prescribing, dispensing, and administering tramadol hydrochloride oral solution. Dosing errors due to confusion between mg and mL can result in accidental overdose and death. ( 2.1 , 5.1 ) Tramadol hydrochloride oral solution exposes users to the risks of addiction, abuse and misuse, which can lead to overdose and death.
Assess each patient's risk prior to prescribing tramadol hydrochloride oral solution, and monitor regularly for these behaviors or conditions. ( 5.2 ) To ensure that the benefits of opioid analgesics outweigh the risks of addiction, abuse, and misuse, the Food and Drug Administration (FDA) has required a Risk Evaluation and Mitigation Strategy (REMS) for these products. ( 5.3 ) Serious, life-threatening, or fatal respiratory depression may occur.
Monitor closely, especially during initiation or following a dose increase. ( 5.4 ) Accidental ingestion of tramadol hydrochloride oral solution, especially by children, can result in a fatal overdose of tramadol. ( 5.4 ) Life-threatening respiratory depression and death have occurred in children who received tramadol.
Some of the reported cases followed tonsillectomy and/or adenoidectomy; in at least one case, the child had evidence of being an ultra-rapid metabolizer of tramadol due to a CYP2D6 polymorphism ( 5.5 ). Tramadol hydrochloride oral solution is contraindicated in children younger than 12 years of age and in children younger than 18 years of age following tonsillectomy and/or adenoidectomy ( 4 ). Avoid the use of tramadol hydrochloride oral solution in adolescents 12 to 18 years of age who have other risk factors that may increase their sensitivity to the respiratory depressant effects of tramadol.
( 5.5 ) Prolonged use of tramadol hydrochloride oral solution, during pregnancy can result in neonatal opioid withdrawal syndrome, which may be life threatening if not recognized and treated. If prolonged opioid use is required in a pregnant woman, advise the patient of the risk of neonatal opioid withdrawal syndrome and ensure that appropriate treatment will be available. ( 5.6 ) The effects of concomitant use or discontinuation of cytochrome P450 3A4 inducers, 3A4 inhibitors, or 2D6 inhibitors with tramadol are complex.
Use of cytochrome P450 3A4 inducers, 3A4 inhibitors, or 2D6 inhibitors with tramadol hydrochloride oral solution requires careful consideration of the effects on the parent drug, tramadol, and the active metabolite, M1. ( 5.7 , 7 ) Concomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing for use in patients for whom alternative treatment options are inadequate; limit dosages and durations to the minimum required; and follow patients for signs and symptoms of respiratory depression and sedation.
( 5.8 , 7 ) RISK OF MEDICATION ERRORS Ensure accuracy when prescribing, dispensing, and a… [Excerpted — this section continues on DailyMed.]
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Tramadol hydrochloride oral solution is indicated in adults for the management of pain severe enough to require an opioid analgesic and for which alternative treatments are inadequate. Tramadol hydrochloride oral solution is an opioid agonist indicated in adults for the management of pain severe enough to require an opioid analgesic and for which alternative treatments are inadequate ( 1 ). Limitations of Use ( 1 ) Because of the risks of addiction, abuse, and misuse with opioids, even at recommended doses ( 5.2 ), reserve tramadol hydrochloride oral solution for use in patients for whom alternative treatment options [e.g., non-opioid analgesics]: Have not been tolerated or are not expected to be tolerated ( 1 ).
Have not provided adequate analgesia, or are not expected to provide adequate analgesia ( 1 ). Limitations of Use Because of the risks of addiction, abuse, and misuse with opioids, even at recommended doses [see Warnings and Precautions ( 5.2 )] , reserve tramadol hydrochloride oral solution for use in patients for whom alternative treatment options [e.g., non-opioid analgesics]: Have not been tolerated or are not expected to be tolerated. Have not provided adequate analgesia or are not expected to provide adequate analgesia.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Use the lowest effective dosage for the shortest duration consistent with individual patient treatment goals ( 2.1 ). Initiate the dosing regimen for each patient individually, taking into account the patient's severity of pain, patient response, prior analgesic treatment experience, and risk factors for addiction, abuse, and misuse ( 2.1 ). Monitor patients closely for respiratory depression, especially within the first 24–72 hours of initiating therapy and following dosage increases with tramadol hydrochloride oral solution and adjust the dosage accordingly ( 2.1 ).
Discuss availability of naloxone with the patient and caregiver and assess each patient’s need for access to naloxone, both when initiating and renewing treatment with tramadol hydrochloride oral solution. Consider prescribing naloxone based on the patient’s risk factors for overdose [ 2.2 , 5.2 , 5.4 , 5.8 ]. Start at 25 mg /day and titrate in 25 mg increments as separate doses every 3 days to reach 100 mg /day (25 mg four times a day).
Thereafter the total daily dose may be increased by 50 mg as tolerated every 3 days to reach 200 mg /day (50 mg four times a day). After titration, tramadol hydrochloride oral solution 50 mg to 100 mg can be administered as needed for pain relief every 4 to 6 hours not to exceed 400 mg /day ( 2.3 , 2.4 ). Severe hepatic impairment : Recommended dose is 50 mg every 12 hours ( 2.3 ).
Do not abruptly discontinue tramadol hydrochloride oral solution in a physically-dependent patient because rapid discontinuation of opioid analgesics has resulted in serious withdrawal symptoms, uncontrolled pain, and suicide ( 2.5 ).
2.1Important Dosage and Administration Instructions Ensure accuracy when prescribing, dispensing, and administering tramadol hydrochloride oral solution to avoid dosing errors due to confusion between mg and mL which could result in accidental overdose and death. Ensure the proper dose is communicated and dispensed. When writing prescriptions, include both the total dose in mg and the total dose in volume.
Instruct patients on how to measure and take the correct dose of tramadol hydrochloride oral solution and to use extreme caution when measuring the dose. Strongly advise patients to always use a calibrated oral syringe or other oral dosing device, with metric units of measurements (i.e., mL), to correctly measure the prescribed amount of medication. Inform patients that oral dosing devices may be obtained from their pharmacy and to never use household teaspoons or tablespoons to measure tramadol hydrochloride oral solution [see Patient Counseling Information ( 17 )] .
Do not use tramadol hydrochloride oral solution concomitantly with other tramadol-containing products. Do not administer tramadol hydrochloride oral solution at a dose exceeding 400 mg (80 mL) per day. Use the lowest effective dosage for the shortest duration consistent with individual patient treatment goals [see Warnings and Precautions ( 5.2 )] .
Initiate the dosing regimen for each patient individually, taking into account the patient's severity of pain, patient response, prior analgesic treatment experience, and risk factors for addiction, abuse, and misuse [see Warnings and Precautions ( 5.2 )] . Monitor patients closely for respiratory depression, especially within the first 24–72 hours of initiating therapy and following dosage increases with tramadol hydrochloride oral solution and adjust the dosage accordingly [see Warnings and Precautions ( 5.4 )] .
2.2Patient Access to Naloxone for the Emergency Treatment of Opioid Overdose Discuss the availability of naloxone for the emergency treatment of opioid overdose with the patient and caregiver and assess the potential need for access to naloxone, both when initiating and renewing treatment with tramadol hydrochloride oral solution [see Warnings and Precautions ( 5.4 ), Patient Counseling Information ( 17 )] . Inform patients and caregivers about the various ways to obtain… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tramadol hydrochloride oral solution is supplied as a clear liquid in 16 oz white, opaque plastic bottles, containing tramadol hydrochloride, 5 mg/mL (equivalent to tramadol 4.4 mg per 1 mL). Oral Solution: tramadol hydrochloride 5 mg/mL ( 3 ).
⛔ Contraindications ▾
4 CONTRAINDICATIONS Tramadol hydrochloride oral solution is contraindicated for: all children younger than 12 years of age [see Warnings and Precautions ( 5.5 )] . postoperative management in children younger than 18 years of age following tonsillectomy and/or adenoidectomy [see Warnings and Precautions ( 5.5 )] . Tramadol hydrochloride oral solution is also contraindicated in patients with: Significant respiratory depression [see Warnings and Precautions ( 5.4 )] . Acute or severe bronchial asthma in an unmonitored setting or in the absence of resuscitative equipment [see Warnings and Precautions ( 5.13 )] .
Known or suspected gastrointestinal obstruction, including paralytic ileus [see Warnings and Precautions ( 5.16 )] . Hypersensitivity to tramadol, any other component of this product or opioids [see Warnings and Precautions ( 5.17 )] . Concurrent use of monoamine oxidase inhibitors (MAOIs) or use within the last 14 days [see Drug Interactions ( 7 )] .
Children younger than 12 years of age ( 4 ). Postoperative management in children younger than 18 years of age following tonsillectomy and/or adenoidectomy ( 4 ). Significant respiratory depression ( 4 ).
Acute or severe bronchial asthma in an unmonitored setting or in the absence of resuscitative equipment ( 4 ). Known or suspected gastrointestinal obstruction, including paralytic ileus ( 4 ). Hypersensitivity to tramadol, any other component of this product or opioids ( 4 ).
Concurrent use of monoamine oxidase inhibitors (MAOIs) or use of MAOIs within the last 14 days ( 4 ).
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Serotonin Syndrome : May be life-threatening. Can occur with use of tramadol alone, with concomitant use of serotonergic drugs, with drugs that impair metabolism of serotonin or tramadol ( 5.9 ). Risk of Seizure : Can occur at the recommended dose of tramadol.
Concomitant use with other drugs may increase seizure risk. Risk may increase in patients with epilepsy, a history of seizures, and in patients with a recognized risk for seizures ( 5.10 ). Risk of Suicide : Do not prescribe for suicidal or addiction-prone patients ( 5.11 ).
Adrenal Insufficiency : If diagnosed, treat with physiologic replacement of corticosteroids, and wean patient off the opioid ( 5.12 ). Life-Threatening Respiratory Depression in Patients with Chronic Pulmonary Disease or in Elderly, Cachectic, or Debilitated Patients : Monitor closely, particularly during initiation and titration ( 5.13 ). Severe Hypotension : Monitor during dosage initiation and titration.
Avoid use of tramadol hydrochloride oral solution in patients with circulatory shock ( 5.14 ). Risks of Use in Patients with Increased Intracranial Pressure, Brain Tumors, Head Injury, or Impaired Consciousness : Monitor for sedation and respiratory depression. Avoid use of tramadol hydrochloride oral solution in patients with impaired consciousness or coma ( 5.15 ).
5.1Risk of Accidental Overdose and Death due to Medication Errors Dosing errors can result in accidental overdose and death. Avoid dosing errors that may result from confusion between mg and mL when prescribing, dispensing, and administering tramadol hydrochloride oral solution. Ensure that the dose is communicated clearly and dispensed accurately.
Instruct patients on how to measure and take the correct dose of tramadol hydrochloride oral solution and to use extreme caution when measuring the dose. Strongly advise patients to always use a calibrated oral dosing device that can measure and deliver the prescribed dose accurately and to never use household teaspoons or tablespoons to measure a dose because household teaspoons and tablespoons are not adequate measuring devices [see Patient Counseling Information ( 17 )] .
5.2Addiction, Abuse and Misuse Tramadol hydrochloride oral solution contains tramadol, a Schedule IV controlled substance. As an opioid, tramadol hydrochloride oral solution exposes users to the risks of addiction, abuse, and misuse [see Drug Abuse and Dependence ( 9 )]. Although the risk of addiction in any individual is unknown, it can occur in patients appropriately prescribed tramadol hydrochloride oral solution.
Addiction can occur at recommended dosages and if the drug is misused or abused. Assess each patient's risk for opioid addiction, abuse, or misuse prior to prescribing tramadol hydrochloride oral solution, and monitor all patients receiving tramadol hydrochloride oral solution for the development of these behaviors and conditions. Risks are increased in patients with a personal or family history of substance abuse (including drug or alcohol abuse or addiction) or mental illness (e.g., major depression).
The potential for these risks should not, however, prevent the proper management of pain in any given patient. Patients at increased risk may be prescribed opioids such as tramadol hydrochloride oral solution, but use in such patients necessitates intensive counseling about the risks and proper use of tramadol hydrochloride oral solution along with intensive monitoring for signs of addiction, abuse, and misuse. Consider prescribing naloxone for the emergency treatment of opioid overdose [see Dosage and Administration ( 2.2 ), Warnings and Precautions ( 5.4 )] .
Opioids are sought by drug abusers and people with addiction disorders and are subject to criminal diversion. Consider these risks when prescribing or dispensing tramadol hydrochloride oral solution. Strategies to reduce these risks include prescribing the drug in the smallest appropriate quantity and advising the patient… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described, or described in greater detail, in other sections: Addiction, Abuse, and Misuse [see Warnings and Precautions ( 5.2 )] Life-Threatening Respiratory Depression [see Warnings and Precautions ( 5.4 )] Ultra-Rapid Metabolism of Tramadol and Other Risk Factors for Life-threatening Respiratory Depression in Children [see Warnings and Precautions ( 5.5 )] Neonatal Opioid Withdrawal Syndrome [see Warnings and Precautions ( 5.6 )] Interactions with Benzodiazepines or Other CNS Depressants [see Warnings and Precautions ( 5.8 )] Serotonin Syndrome [see Warnings and Precautions ( 5.9 )] Seizures [see Warnings and Precautions ( 5.10 )] Suicide [see Warnings and Precautions ( 5.11 )] Adrenal Insufficiency [see Warnings and Precautions ( 5.12 )] Severe Hypotension [see Warnings and Precautions ( 5.14 )] Gastrointestinal Adverse Reactions [see Warnings and Precautions ( 5.16 )] Hypersensitivity Reactions [see Warnings and Precautions ( 5.17 )] Withdrawal [see Warnings and Precautions ( 5.18 )] The most common incidence of treatment-emergent adverse events (≥15.0%) in patients from clinical trials were dizziness/vertigo, nausea, constipation, headache, somnolence, vomiting and pruritus ( 6 ).
To report SUSPECTED ADVERSE REACTIONS, contact TruPharma, LLC at 1-877-541-5504 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Tramadol hydrochloride was administered to 550 patients during the double-blind or open-label extension periods in U.S. studies of chronic nonmalignant pain. Of these patients, 375 were 65 years old or older.
Table 1 reports the cumulative incidence rate of adverse reactions by 7, 30 and 90 days for the most frequent reactions (5% or more by 7 days). The most frequently reported events were in the central nervous system and gastrointestinal system. Although the reactions listed in the table are felt to be probably related to tramadol hydrochloride administration, the reported rates also include some events that may have been due to underlying disease or concomitant medication.
The overall incidence rates of adverse experiences in these trials were similar for tramadol hydrochloride and the active control groups, TYLENOL with Codeine #3 (acetaminophen 300 mg with codeine phosphate 30 mg), and aspirin 325 mg with codeine phosphate 30 mg, however, the rates of withdrawals due to adverse events appeared to be higher in the tramadol hydrochloride groups. Table 1: Cumulative Incidence of Adverse Reactions for Tramadol HCl Tablets in Chronic Trials of Nonmalignant Pain (N=427) Up to 7 Days Up to 30 Days Up to 90 Days Dizziness/Vertigo 26% 31% 33% Nausea 24% 34% 40% Constipation 24% 38% 46% Headache 18% 26% 32% Somnolence 16% 23% 25% Vomiting 9% 13% 17% Pruritus 8% 10% 11% CNS Stimulation CNS Stimulation is a composite of nervousness, anxiety, agitation, tremor, spasticity, euphoria, emotional lability and hallucinations 7% 11% 14% Asthenia 6% 11% 12% Sweating 6% 7% 9% Dyspepsia 5% 9% 13% Dry Mouth 5% 9% 10% Diarrhea 5% 6% 10% Incidence 1% to Less than 5% Possibly Causally Related The following lists adverse reactions that occurred with an incidence of 1% to less than 5% in clinical trials, and for which the possibility of a causal relationship with tramadol hydrochloride exists.
Body as a Whole : Malaise. Cardiovascular : Vasodilation. Central Nervous System : Anxiety, Confusion, Coordination disturbance, Euphoria, Miosis, Nervousness, Sleep disorder.
Gastrointestinal : Abdominal pain, Anorexia, Flatulence. Musculoskeletal : Hypertonia. Skin : Rash.
Special Senses : Visual disturbance. Urogenital : Menopausal symptoms, Urinary frequency, Urinary retention. Incidence Less… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 2: Clinically Significant Drug Interactions with tramadol hydrochloride oral solution Inhibitors of CYP2D6 Clinical Impact: The concomitant use of tramadol hydrochloride oral solution and CYP2D6 inhibitors may result in an increase in the plasma concentration of tramadol and a decrease in the plasma concentration of M1, particularly when an inhibitor is added after a stable dose of tramadol hydrochloride oral solution is achieved. Since M1 is a more potent µ-opioid agonist, decreased M1 exposure could result in decreased therapeutic effects, and may result in signs and symptoms of opioid withdrawal in patients who had developed physical dependence to tramadol.
Increased tramadol exposure can result in increased or prolonged therapeutic effects and increased risk for serious adverse events including seizures and serotonin syndrome. After stopping a CYP2D6 inhibitor, as the effects of the inhibitor decline, the tramadol plasma concentration will decrease and the M1 plasma concentration will increase. This could increase or prolong therapeutic effects but also increase adverse reactions related to opioid toxicity, such as potentially fatal respiratory depression [see Clinical Pharmacology ( 12.3 )] .
Intervention: If concomitant use of a CYP2D6 inhibitor is necessary, follow patients closely for adverse reactions including opioid withdrawal, seizures and serotonin syndrome. If a CYP2D6 inhibitor is discontinued, consider lowering tramadol hydrochloride oral solution dosage until stable drug effects are achieved. Follow patients closely for adverse events including respiratory depression and sedation.
Examples: Quinidine, fluoxetine, paroxetine and bupropion Inhibitors of CYP3A4 Clinical Impact: The concomitant use of tramadol hydrochloride oral solution and CYP3A4 inhibitors can increase the plasma concentration of tramadol and may result in a greater amount of metabolism via CYP2D6 and greater levels of M1. Follow patients closely for increased risk of serious adverse events including seizures and serotonin syndrome, and adverse reactions related to opioid toxicity including potentially fatal respiratory depression, particularly when an inhibitor is added after a stable dose of tramadol hydrochloride oral solution is achieved.
After stopping a CYP3A4 inhibitor, as the effects of the inhibitor decline, the tramadol plasma concentration will decrease [see Clinical Pharmacology ( 12.3 )] , resulting in decreased opioid efficacy or a withdrawal syndrome in patients who had developed physical dependence to tramadol. Intervention: If concomitant use is necessary, consider dosage reduction of tramadol hydrochloride oral solution until stable drug effects are achieved. Follow patients closely for seizures and serotonin syndrome, and signs of respiratory depression and sedation at frequent intervals.
If a CYP3A4 inhibitor is discontinued, consider increasing the tramadol hydrochloride oral solution dosage until stable drug effects are achieved and follow patients for signs and symptoms of opioid withdrawal. Examples: >Macrolide antibiotics (e.g., erythromycin), azole-antifungal agents (e.g. ketoconazole), protease inhibitors (e.g., ritonavir) CYP3A4 Inducers Clinical Impact: The concomitant use of tramadol hydrochloride oral solution and CYP3A4 inducers can decrease the plasma concentration of tramadol [see Clinical Pharmacology ( 12.3 )] , resulting in decreased efficacy or onset of a withdrawal syndrome in patients who have developed physical dependence to tramadol.
After stopping a CYP3A4 inducer, as the effects of the inducer decline, the tramadol plasma concentration will increase [see Clinical Pharmacology ( 12.3 )] , which could increase or prolong both the therapeutic effects and adverse reactions, and may cause seizures, serotonin syndrome, and/or potentially fatal respiratory depression. Intervention: If concomitant use is necessary, consider increasing the tramadol hydrochloride oral solution dosage u… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: May cause fetal harm ( 8.1 ). Lactation: Breastfeeding not recommended ( 8.2 ).
8.1Pregnancy Risk Summary Prolonged use of opioid analgesics during pregnancy may cause neonatal opioid withdrawal syndrome. Available data with tramadol hydrochloride in pregnant women are insufficient to inform a drug-associated risk for major birth defects and miscarriage or adverse maternal outcomes. There are adverse outcomes reported with fetal exposure to opioid analgesics ( see Clinical Considerations) .
In animal reproduction studies, tramadol administration during organogenesis decreased fetal weights and reduced ossification in mice, rats, and rabbits at 1.4, 0.6, and 3.6 times the maximum recommended human daily dosage (MRHD). In a pre- and post-natal development study, tramadol decreased pup body weight and increased pup mortality at 1.2 and 1.9 times the MRHD. In a published study, tramadol caused structural abnormalities in the brains of fetuses when administered to female Sprague Dawley rats from Gestation Days 10-21 at a dose comparable to the MRHD [see Data ] .
Based on animal data, advise pregnant women of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions Prolonged use of opioid analgesics during pregnancy for medical or nonmedical purposes can result in respiratory depression and physical dependence in the neonate and neonatal opioid withdrawal syndrome shortly after birth. Neonatal opioid withdrawal syndrome can present as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea and failure to gain weight.
The onset, duration, and severity of neonatal opioid withdrawal syndrome vary based on the specific opioid used, duration of use, timing and amount of last maternal use, and rate of elimination of the drug by the newborn. Observe newborns for symptoms and signs of neonatal opioid withdrawal syndrome and manage accordingly [see Warnings and Precautions ( 5.6 )] . Neonatal seizures, neonatal withdrawal syndrome, fetal death and still birth have been reported during postmarketing.
Labor or Delivery Opioids cross the placenta and may produce respiratory depression and psycho-physiologic effects in neonates. An opioid antagonist, such as naloxone, must be available for reversal of opioid-induced respiratory depression in the neonate. Tramadol hydrochloride oral solution is not recommended for use in pregnant women during or immediately prior to labor, when other analgesic techniques are more appropriate.
Opioid analgesics, including tramadol hydrochloride oral solution, can prolong labor through actions which temporarily reduce the strength, duration, and frequency of uterine contractions. However, this effect is not consistent and may be offset by an increased rate of cervical dilation, which tends to shorten labor. Monitor neonates exposed to opioid analgesics during labor for signs of excess sedation and respiratory depression.
Tramadol has been shown to cross the placenta. The mean ratio of serum tramadol in the umbilical veins compared to maternal veins was 0.83 for 40 women given tramadol during labor. The effect of tramadol hydrochloride, if any, on the later growth, development, and functional maturation of the child is unknown.
Data Animal Data Tramadol has been shown to be embryotoxic and fetotoxic in mice, (120 mg/kg), rats (25 mg/kg) and rabbits (75 mg/kg) at maternally toxic dosages, but did not cause malformations at these dose levels. These doses on a mg/m 2 basis are 1.4, 0.6, and 3.6 times the maximum recommended human daily dos… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Prolonged use of opioid analgesics during pregnancy may cause neonatal opioid withdrawal syndrome. Available data with tramadol hydrochloride in pregnant women are insufficient to inform a drug-associated risk for major birth defects and miscarriage or adverse maternal outcomes. There are adverse outcomes reported with fetal exposure to opioid analgesics ( see Clinical Considerations) .
In animal reproduction studies, tramadol administration during organogenesis decreased fetal weights and reduced ossification in mice, rats, and rabbits at 1.4, 0.6, and 3.6 times the maximum recommended human daily dosage (MRHD). In a pre- and post-natal development study, tramadol decreased pup body weight and increased pup mortality at 1.2 and 1.9 times the MRHD. In a published study, tramadol caused structural abnormalities in the brains of fetuses when administered to female Sprague Dawley rats from Gestation Days 10-21 at a dose comparable to the MRHD [see Data ] .
Based on animal data, advise pregnant women of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions Prolonged use of opioid analgesics during pregnancy for medical or nonmedical purposes can result in respiratory depression and physical dependence in the neonate and neonatal opioid withdrawal syndrome shortly after birth. Neonatal opioid withdrawal syndrome can present as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea and failure to gain weight.
The onset, duration, and severity of neonatal opioid withdrawal syndrome vary based on the specific opioid used, duration of use, timing and amount of last maternal use, and rate of elimination of the drug by the newborn. Observe newborns for symptoms and signs of neonatal opioid withdrawal syndrome and manage accordingly [see Warnings and Precautions ( 5.6 )] . Neonatal seizures, neonatal withdrawal syndrome, fetal death and still birth have been reported during postmarketing.
Labor or Delivery Opioids cross the placenta and may produce respiratory depression and psycho-physiologic effects in neonates. An opioid antagonist, such as naloxone, must be available for reversal of opioid-induced respiratory depression in the neonate. Tramadol hydrochloride oral solution is not recommended for use in pregnant women during or immediately prior to labor, when other analgesic techniques are more appropriate.
Opioid analgesics, including tramadol hydrochloride oral solution, can prolong labor through actions which temporarily reduce the strength, duration, and frequency of uterine contractions. However, this effect is not consistent and may be offset by an increased rate of cervical dilation, which tends to shorten labor. Monitor neonates exposed to opioid analgesics during labor for signs of excess sedation and respiratory depression.
Tramadol has been shown to cross the placenta. The mean ratio of serum tramadol in the umbilical veins compared to maternal veins was 0.83 for 40 women given tramadol during labor. The effect of tramadol hydrochloride, if any, on the later growth, development, and functional maturation of the child is unknown.
Data Animal Data Tramadol has been shown to be embryotoxic and fetotoxic in mice, (120 mg/kg), rats (25 mg/kg) and rabbits (75 mg/kg) at maternally toxic dosages, but did not cause malformations at these dose levels. These doses on a mg/m 2 basis are 1.4, 0.6, and 3.6 times the maximum recommended human daily dosage (MRHD) for mouse, rat and rabbit, respectively. No drug-related malformations were observed in progeny of mice (up to… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of tramadol in pediatric patients have not been established. Life-threatening respiratory depression and death have occurred in children who received tramadol [see Warnings and Precautions ( 5.5 )] . In some of the reported cases, these events followed tonsillectomy and/or adenoidectomy, and one of the children had evidence of being an ultra-rapid metabolizer of tramadol (i.e., multiple copies of the gene for cytochrome P450 isoenzyme 2D6).
Children with sleep apnea may be particularly sensitive to the respiratory depressant effects of tramadol. Because of the risk of life-threatening respiratory depression and death: Tramadol hydrochloride oral solution is contraindicated for all children younger than 12 years of age [see Contraindications ( 4 )] . Tramadol hydrochloride oral solution is contraindicated for postoperative management in pediatric patients younger than 18 years of age following tonsillectomy and/or adenoidectomy [see Contraindications ( 4 )] .
Avoid the use of tramadol hydrochloride oral solution in adolescents 12 to 18 years of age who have other risk factors that may increase their sensitivity to the respiratory depressant effects of tramadol unless the benefits outweigh the risks. Risk factors include conditions associated with hypoventilation such as postoperative status, obstructive sleep apnea, obesity, severe pulmonary disease, neuromuscular disease, and concomitant use of other medications that cause respiratory depression.
🧓 Geriatric Use ▾
8.5Geriatric Use A total of 455 elderly (65 years of age or older) subjects were exposed to tramadol hydrochloride in controlled clinical trials. Of those, 145 subjects were 75 years of age and older. In studies including geriatric patients, treatment-limiting adverse events were higher in subjects over 75 years of age compared to those under 65 years of age.
Specifically, 30% of those over 75 years of age had gastrointestinal treatment-limiting adverse events compared to 17% of those under 65 years of age. Constipation resulted in discontinuation of treatment in 10% of those over 75. Respiratory depression is the chief risk for elderly patients treated with opioids, and has occurred after large initial doses were administered to patients who were not opioid-tolerant or when opioids were co-administered with other agents that depress respiration.
Titrate the dosage of tramadol hydrochloride oral solution slowly in geriatric patients starting at the low end of the dosing range and monitor closely for signs of central nervous system and respiratory depression [see Warnings and Precautions ( 5.13 )] . Tramadol is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
🆘 Overdosage ▾
10 OVERDOSAGE Clinical Presentation Acute overdosage with tramadol hydrochloride oral solution can be manifested by respiratory depression, somnolence progressing to stupor or coma, skeletal muscle flaccidity, cold and clammy skin, constricted pupils, and, in some cases, pulmonary edema, bradycardia, QT prolongation, hypotension, partial or complete airway obstruction, atypical snoring, seizures, and death. Marked mydriasis rather than miosis may be seen with hypoxia in overdose situations. Deaths due to overdose have been reported with abuse and misuse of tramadol [see Warnings and Precautions ( 5.2 ), Drug Abuse and Dependence ( 9.2 )] .
Review of case reports has indicated that the risk of fatal overdose is further increased when tramadol is abused concurrently with alcohol or other CNS depressants, including other opioids. Treatment of Overdose In case of overdose, priorities are the re-establishment of a patent and protected airway and institution of assisted or controlled ventilation, if needed. Employ other supportive measures (including oxygen and vasopressors) in the management of circulatory shock and pulmonary edema as indicated.
Cardiac arrest or serious arrhythmias will require advanced life-supporting measures. Opioid antagonists, such as naloxone, are specific antidotes to respiratory depression resulting from opioid overdose. For clinically significant respiratory or circulatory depression secondary to tramadol overdose, administer an opioid antagonist.
While naloxone will reverse some, but not all, symptoms caused by overdosage with tramadol, the risk of seizures is also increased with naloxone administration. In animals, convulsions following the administration of toxic doses of tramadol hydrochloride could be suppressed with barbiturates or benzodiazepines but were increased with naloxone. Naloxone administration did not change the lethality of an overdose in mice.
Hemodialysis is not expected to be helpful in an overdose because it removes less than 7% of the administered dose in a 4-hour dialysis period. Because the duration of opioid reversal is expected to be less than the duration of action of tramadol in tramadol hydrochloride oral solution, carefully monitor the patient until spontaneous respiration is reliably re-established. If the response to an opioid antagonist is suboptimal or only brief in nature, administer additional antagonist as directed by the product's prescribing information.
In an individual physically dependent on opioids, administration of the recommended usual dosage of the antagonist will precipitate an acute withdrawal syndrome. The severity of the withdrawal symptoms experienced will depend on the degree of physical dependence and the dose of the antagonist administered. If a decision is made to treat serious respiratory depression in the physically dependent patient, administration of the antagonist should be begun with care and by titration with smaller than usual doses of the antagonist.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Tramadol hydrochloride oral solution contains tramadol, an opioid agonist and inhibitor of norepinephrine and serotonin re-uptake. Although the mode of action is not completely understood, the analgesic effect of tramadol is believed to be due to both binding to µ-opioid receptors and weak inhibition of re-uptake of norepinephrine and serotonin. Opioid activity is due to both low affinity binding of the parent compound and higher affinity binding of the O -demethylated metabolite M1 to µ-opioid receptors.
In animal models, M1 is up to 6 times more potent than tramadol in producing analgesia and 200 times more potent in µ-opioid binding. Tramadol-induced analgesia is only partially antagonized by the opioid antagonist naloxone in several animal tests. The relative contribution of both tramadol and M1 to human analgesia is dependent upon the plasma concentrations of each compound [see Clinical Pharmacology ( 12.2 )] .
Analgesia in humans begins approximately within one hour after administration and reaches a peak in approximately two to three hours.
12.2Pharmacodynamics Effects on the Central Nervous System Tramadol produces respiratory depression by direct action on brain stem respiratory centers. The respiratory depression involves a reduction in the responsiveness of the brain stem respiratory centers to both increases in carbon dioxide tension and electrical stimulation. Tramadol administration may produce a constellation of symptoms including nausea and vomiting, dizziness, and somnolence.
Tramadol causes miosis, even in total darkness. Pinpoint pupils are a sign of opioid overdose but are not pathognomonic (e.g., pontine lesions of hemorrhagic or ischemic origins may produce similar findings). Marked mydriasis rather than miosis may be seen due to hypoxia in overdose situations.
Effects on the Gastrointestinal Tract and Other Smooth Muscle Tramadol causes a reduction in motility associated with an increase in smooth muscle tone in the antrum of the stomach and duodenum. Digestion of food in the small intestine is delayed and propulsive contractions are decreased. Propulsive peristaltic waves in the colon are decreased, while tone may be increased to the point of spasm resulting in constipation.
Other opioid-induced effects may include a reduction in biliary and pancreatic secretions, spasm of sphincter of Oddi, and transient elevations in serum amylase. Effects on the Cardiovascular System Tramadol produces peripheral vasodilation, which may result in orthostatic hypotension or syncope. Manifestations of peripheral vasodilation may include pruritus, flushing, red eyes, sweating and/or orthostatic hypotension.
The effect of oral tramadol on the QTcF interval was evaluated in a double-blind, randomized, four-way crossover, placebo- and positive- (moxifloxacin) controlled study in 68 adult male and female healthy subjects. At a 600 mg/day dose (1.5-fold the maximum immediate-release daily dose), the study demonstrated no significant effect on the QTcF interval. Effects on the Endocrine System Opioids inhibit the secretion of adrenocorticotropic hormone (ACTH), cortisol, and luteinizing hormone (LH) in humans.
They also stimulate prolactin, growth hormone (GH) secretion, and pancreatic secretion of insulin and glucagon [see Warnings and Precautions ( 5.12 ); Adverse Reactions ( 6 )] . Chronic use of opioids may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility. The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that may influence gonadal hormone levels have not been adequately controlled for in studies conducted to date [see Adverse Reactions ( 6 )] .
Effects on the Immune System Opioids have been shown to have a variety of effects on components of t… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Tramadol hydrochloride oral solution contains tramadol, an opioid agonist and inhibitor of norepinephrine and serotonin re-uptake. Although the mode of action is not completely understood, the analgesic effect of tramadol is believed to be due to both binding to µ-opioid receptors and weak inhibition of re-uptake of norepinephrine and serotonin. Opioid activity is due to both low affinity binding of the parent compound and higher affinity binding of the O -demethylated metabolite M1 to µ-opioid receptors.
In animal models, M1 is up to 6 times more potent than tramadol in producing analgesia and 200 times more potent in µ-opioid binding. Tramadol-induced analgesia is only partially antagonized by the opioid antagonist naloxone in several animal tests. The relative contribution of both tramadol and M1 to human analgesia is dependent upon the plasma concentrations of each compound [see Clinical Pharmacology ( 12.2 )] .
Analgesia in humans begins approximately within one hour after administration and reaches a peak in approximately two to three hours.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Tramadol hydrochloride oral solution is supplied as a clear, grape flavored liquid containing tramadol HCl, 5 mg/mL. Supplied in 16 oz (473 mL) white, opaque plastic bottles with a child-resistant cap, NDC 52817-615-16 Dispense in a tight container. Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to30°C (59°F to 86°F). [see USP Controlled Room Temperature].
Store tramadol hydrochloride oral solution securely and dispose of properly [see Patient Counseling Information ( 17 )].
📦 Storage and Handling ▾
Dispense in a tight container. Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to30°C (59°F to 86°F). [see USP Controlled Room Temperature]. Store tramadol hydrochloride oral solution securely and dispose of properly [see Patient Counseling Information ( 17 )].
📋 Description ▾
11 DESCRIPTION Tramadol hydrochloride oral solution is an opioid agonist. The chemical name for tramadol hydrochloride is (±) cis -2-[(dimethylamino)methyl]-1-(3-methoxyphenyl) cyclohexanol hydrochloride. The structural formula is: The molecular formula of tramadol hydrochloride is C 16 H 25 NO 2 · HCl, and the molecular weight is 299.8.
Tramadol hydrochloride is a white, bitter, crystalline and odorless powder. It is readily soluble in water and ethanol and has a pKa of 9.41. The n-octanol/water log partition coefficient (logP) is 1.35 at pH 7.
Tramadol hydrochloride oral solution is a clear, grape flavored liquid containing 5 mg of tramadol hydrochloride per 1 mL (equivalent to tramadol 4.4 mg per 1 mL) Inactive ingredients include: citric acid, glycerin, grape flavor, propylene glycol, purified water, sodium benzoate, sodium citrate dihydrate, and sucralose. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Storage and Disposal Because of the risks associated with accidental ingestion, misuse, and abuse, advise patients to store tramadol hydrochloride oral solution securely, out of sight and reach of children, and in a location not accessible by others, including visitors to the home [see Warnings and Precautions ( 5.2 , 5.3 ), Drug Abuse and Dependence ( 9.2 )] . Inform patients that leaving tramadol hydrochloride oral solution unsecured can pose a deadly risk to others in the home.
Advise patients and caregivers that when medicines are no longer needed, they should be disposed of promptly. Inform patients that medicine take-back options are the preferred way to safely dispose of most types of unneeded medicines. If no take back programs or Drug Enforcement Administration (DEA)-registered collectors are available, instruct patients to dispose of tramadol hydrochloride oral solution by following these four steps: Mix tramadol hydrochloride oral solution with an unpalatable substance such as dirt, cat litter, or used coffee grounds; Place the mixture in a container such as a sealed plastic bag; Throw the container in the household trash; Delete all personal information on the prescription label of the empty bottle.
Inform patients that they can visit www.fda.gov/drugdisposal for additional information on disposal of unused medicines. Medication Errors Instruct patients on how to measure and take the correct dose of tramadol hydrochloride oral solution and to always use a calibrated oral syringe or other oral dosing device to correctly measure the prescribed amount of medication [see Dosage and Administration ( 2.1 ), Warnings and Precautions ( 5.1 )] . Addiction, Abuse, and Misuse Inform patients that the use of tramadol hydrochloride oral solution, even when taken as recommended, can result in addiction, abuse, and misuse, which can lead to overdose and death [see Warnings and Precautions ( 5.2 )] .
Instruct patients not to share tramadol hydrochloride oral solution with others and to take steps to protect tramadol hydrochloride oral solution from theft or misuse. Life-Threatening Respiratory Depression Inform patients of the risk of life-threatening respiratory depression, including information that the risk is greatest when starting tramadol hydrochloride oral solution or when the dosage is increased, and that it can occur even at recommended dosages. Educate patients and caregivers on how to recognize respiratory depression and emphasize the importance of calling 911 or getting emergency medical help right away in the event of a known or suspected overdose [see Warnings and Precautions ( 5.4 )] .
Patient Access to Naloxone for the Emergency Treatment of Opioid Overdose Discuss with the patient and caregiver the availability of naloxone for the emergency treatment of opioid overdose, both when initiating and renewing treatment with tramadol hydrochloride oral solution. Inform patients and caregivers about the various ways to obtain naloxone as permitted by individual state naloxone dispensing and prescribing requirements or guidelines (e.g., by prescription, directly from a pharmacist, or as part of a community-based program) [see Dosage and Administration ( 2.2 ), Warnings and Precautions ( 5.4 ) ] .
Educate patients and caregivers on how to recognize the signs and symptoms of an overdose. Explain to patients and caregivers that naloxone’s effects are temporary, and that they must call 911 or get emergency medical help right away in all cases of known or suspected opioid overdose, even if naloxone is administered [see Overdosage ( 10 )] . If naloxone is prescribed, also advise patients and caregivers: How to treat with naloxone in the event of an opioid overdose To tell family and friends about their naloxone and to keep it in a place where family and friends can access it in an emergency To read the Patient Infor… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
Manufactured for: TruPharma, LLC, Tampa, FL 33609. This Medication Guide has been approved by the U.S. Food and Drug Administration.
Issued/Revised: 11/2022 MEDICATION GUIDE Tramadol hydrochloride oral solution, CIV Tramadol hydrochloride oral solution is: A strong prescription pain medicine that contains an opioid (narcotic) that is used for the management of pain in adults, when other pain treatments such as non-opioid pain medicines do not treat your pain well enough or you cannot tolerate them. An opioid pain medicine that can put you at risk for overdose and death. Even if you take your dose correctly as prescribed you are at risk for opioid addiction, abuse, and misuse that can lead to death.
Important information about tramadol hydrochloride oral solution: Get emergency help right away if you take too much tramadol hydrochloride oral solution (overdose). When you first start taking tramadol hydrochloride oral solution, when your dose is changed, or if you take too much (overdose), serious or life-threatening breathing problems that can lead to death may occur. Takingtramadol hydrochloride oral solution with other opioid medicines, benzodiazepines, alcohol, or other central nervous system depressants (including street drugs) can cause severe drowsiness, decreased awareness, breathing problems, coma, and death.
Never give anyone else your tramadol hydrochloride oral solution. They could die from taking it. Selling or giving away tramadol hydrochloride oral solution is against the law.
Store tramadol hydrochloride oral solution securely, out of sight and reach of children, and in a location not accessible by others, including visitors to the home. Important Information Guiding Use in Pediatric Patients: Do not give tramadol hydrochloride oral solution to a child younger than 12 years of age. Do not give tramadol hydrochloride oral solution to anyone younger than 18 years of age after surgery to remove the tonsils, adenoids, or both.
Avoid giving tramadol hydrochloride oral solution to children between 12 to 18 years of age who have risk factors for breathing problems such as obstructive sleep apnea, obesity, or underlying lung problems. Do not take tramadol hydrochloride oral solution if you have: Severe asthma, trouble breathing, or other lung problems. A bowel blockage or have narrowing of the stomach or intestines.
An allergy to tramadol. Taken a Monoamine Oxidase Inhibitor, MAOI, (medicine used for depression) within the last 14 days. Before taking tramadol hydrochloride oral solution, tell your healthcare provider if you have a history of: head injury, seizures problems urinating abuse of street or prescription drugs, alcohol addiction, or mental health problems. liver, kidney, thyroid problems pancreas or gallbladder problems Tell your healthcare provider if you are: pregnant or planning to become pregnant.
Prolonged use of tramadol hydrochloride oral solution during pregnancy can cause withdrawal symptoms in your newborn baby that could be life-threatening if not recognized and treated. breastfeeding. Not recommended; it may harm your baby. taking prescription or over-the-counter medicines, vitamins, or herbal supplements. Taking tramadol hydrochloride oral solution with certain other medicines can cause serious side effects that could lead to death.
When taking tramadol hydrochloride oral solution: Do not change your dose. Take tramadol hydrochloride oral solution exactly as prescribed by your healthcare provider. Use the lowest dose possible for the shortest time needed.
Always use a calibrated oral syringe or other oral dosing device obtained from your doctor or pharmacist tocorrectly measure your dose. Never use a household teaspoon or tablespoon to measure tramadol hydrochloride oral solution. Take your prescribed dose as indicated by your healthcare provider.
The maximum dosage is 10 mL to 20 mL every 4 to 6 hours, as needed for pain relief. Do not take more than your prescribed dose and do not take more than… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The analgesic activity of tramadol hydrochloride oral solution is due to both parent drug and the M1 metabolite [see Clinical Pharmacology ( 12.1 , 12.2 )] . Tramadol is administered as a racemate and both the [-] and [+] forms of both tramadol and M1 are detected in the circulation. Linear pharmacokinetics have been observed following multiple doses of 50 and 100 mg to steady-state.
Absorption Table 3 shows the mean plasma concentrations of tramadol and M1 pharmacokinetic parameters following a single-dose administration of 50 mg tramadol hydrochloride oral solution and 50 mg immediate-release tramadol tablet under fasted conditions in healthy adult subjects. Table 3: Summary of Tramadol and M1 Pharmacokinetic Parameters Following Single Dose Administration Under Fasted Condition in Healthy Adult Subjects Parameters Tramadol hydrochloride oral solution 50 mg Fasted Immediate-release tramadol tablet 50 mg Fasted Tramadol hydrochloride oral solution 50 mg Fasted Immediate-release tramadol tablet 50 mg Fasted Tramadol M1 Mean ± SD Mean ± SD Mean ± SD Mean ± SD T max median (min – max) (hr) 1.5 (0.50 2.50) 1.5 (0.75 3.0) 2.0 (0.50 5.00) 2.25 (1.25 10.00) C max (ng/mL) 180.20 ± 33.81 173.51 ± 29.59 47.77 ± 19.06 46.14 ±
18.28AUC 0-t (hr*ng/mL) 1623.93 ± 502.43 1681.64 ± 578.06 624.12 ± 205.58 624.10 ± 199.82 AUC 0-inf (hr*ng/mL) 1658.31 ± 525.97 1721.47 ± 624.72 638.95 ± 207.13 639.26 ± 198.04 t 1/2 (hr) 7.65 ± 1.63 7.61 ± 1.82 7.94 ± 1.65 8.06 ±
2.11The mean absolute bioavailability of a 100 mg oral dose is approximately 75%. The mean peak plasma concentration of racemic tramadol and M1 occurs at two and three hours, respectively, after administration in healthy adults. In general, both enantiomers of tramadol and M1 follow a parallel time course in the body following single and multiple doses although small differences (~ 10%) exist in the absolute amount of each enantiomer present.
Steady-state plasma concentrations of both tramadol and M1 are achieved within two days with four-times-per-day dosing. There is no evidence of self-induction (see Figure 1 and Table 4 below). Figure 1: Mean Tramadol and M1 Plasma Concentration Profiles after a Single 100 mg Oral Dose and after Twenty-Nine 100 mg Oral Doses of Tramadol HCl given four times per day.
Table 4: Mean (%CV) Pharmacokinetic Parameters for Racemic Tramadol and M1 Metabolite Population/Dosage Regimen SD = Single dose, MD = Multiple dose, p.o.= Oral administration, i.v.= Intravenous administration, q.i.d. = Four times daily Parent Drug/ Metabolite Peak Conc.(ng/mL) Time to Peak (hrs) Clearance/F b F represents the oral bioavailability of tramadol (mL/min/Kg) t 1/2 (hrs) Healthy Adults, 100 mg qid, MD p.o. Tramadol M1 592 (30) 110 (29) 2.3 (61) 2.4 (46) 5.90 (25) Not applicable 6.7 (15) 7.0 (14) Healthy Adults, 100 mg SD p.o.
Tramadol M1 308 (25) 55.0 (36) 1.6 (63) 3.0 (51) 8.50 (31) 5.6 (20) 6.7 (16) Geriatric, (>75 yrs) 50 mg SD p.o. Tramadol M1 208 (31) Not measured 2.1 (19) 6.89 (25) 7.0 (23) Hepatic Impaired, 50 mg SD p.o. Tramadol M1 217 (11) 19.4 (12) 1.9 (16) 9.8 (20) 4.23 (56) 13.3 (11) 18.5 (15) Renal Impaired, CLcr1030 mL/min 100 mg SD i.v.
Tramadol M1 4.23 (54) 10.6 (31) 11.5 (40) Renal Impaired, CLcr<5 mL/min 100 mg SD i.v. Tramadol M1 3.73 (17) 11.0 (29) 16.9 (18) Figure 1 Food Effects Oral administration of tramadol hydrochloride oral solution with food does not significantly affect its rate or extent of absorption, therefore, tramadol hydrochloride oral solution can be administered without regard to food. Distribution The volume of distribution of tramadol was 2.6 and 2.9 liters/kg in male and female subjects, respectively, following a 100 mg intravenous dose.
The binding of tramadol to human plasma proteins is approximately 20% and binding also appears to be independent of concentration up to 10 mcg/mL. Saturation of plasma protein binding occurs only at concentrations outside the clinically relevant range. Elimination Tramadol is elimin… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Effects on the Central Nervous System Tramadol produces respiratory depression by direct action on brain stem respiratory centers. The respiratory depression involves a reduction in the responsiveness of the brain stem respiratory centers to both increases in carbon dioxide tension and electrical stimulation. Tramadol administration may produce a constellation of symptoms including nausea and vomiting, dizziness, and somnolence.
Tramadol causes miosis, even in total darkness. Pinpoint pupils are a sign of opioid overdose but are not pathognomonic (e.g., pontine lesions of hemorrhagic or ischemic origins may produce similar findings). Marked mydriasis rather than miosis may be seen due to hypoxia in overdose situations.
Effects on the Gastrointestinal Tract and Other Smooth Muscle Tramadol causes a reduction in motility associated with an increase in smooth muscle tone in the antrum of the stomach and duodenum. Digestion of food in the small intestine is delayed and propulsive contractions are decreased. Propulsive peristaltic waves in the colon are decreased, while tone may be increased to the point of spasm resulting in constipation.
Other opioid-induced effects may include a reduction in biliary and pancreatic secretions, spasm of sphincter of Oddi, and transient elevations in serum amylase. Effects on the Cardiovascular System Tramadol produces peripheral vasodilation, which may result in orthostatic hypotension or syncope. Manifestations of peripheral vasodilation may include pruritus, flushing, red eyes, sweating and/or orthostatic hypotension.
The effect of oral tramadol on the QTcF interval was evaluated in a double-blind, randomized, four-way crossover, placebo- and positive- (moxifloxacin) controlled study in 68 adult male and female healthy subjects. At a 600 mg/day dose (1.5-fold the maximum immediate-release daily dose), the study demonstrated no significant effect on the QTcF interval. Effects on the Endocrine System Opioids inhibit the secretion of adrenocorticotropic hormone (ACTH), cortisol, and luteinizing hormone (LH) in humans.
They also stimulate prolactin, growth hormone (GH) secretion, and pancreatic secretion of insulin and glucagon [see Warnings and Precautions ( 5.12 ); Adverse Reactions ( 6 )] . Chronic use of opioids may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility. The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that may influence gonadal hormone levels have not been adequately controlled for in studies conducted to date [see Adverse Reactions ( 6 )] .
Effects on the Immune System Opioids have been shown to have a variety of effects on components of the immune system in in vitro and animal models. The clinical significance of these findings is unknown. Overall, the effects of opioids appear to be modestly immunosuppressive.
Concentration–Efficacy Relationships The minimum effective analgesic concentration will vary widely among patients, especially among patients who have been previously treated with potent opioid agonists. The minimum effective analgesic concentration of tramadol for any individual patient may increase over time due to an increase in pain, the development of a new pain syndrome and/or the development of analgesic tolerance [see Dosage and Administration ( 2 )] . Concentration–Adverse Reaction Relationships There is a relationship between increasing tramadol plasma concentration and increasing frequency of dose-related opioid adverse reactions such as nausea, vomiting, CNS effects, and respiratory depression.
In opioid-tolerant patients, the situation may be altered by the development of tolerance to opioid-related adverse reactions [see Dosage and Administration ( 2 )] .
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Tramadol hydrochloride has been given in single oral doses of 50, 75 and 100 mg to patients with pain following surgical procedures and pain following oral surgery (extraction of impacted molars). In single-dose models of pain following oral surgery, pain relief was demonstrated in some patients at doses of 50 mg and 75 mg. A dose of 100 mg tramadol hydrochloride tended to provide analgesia superior to codeine sulfate 60 mg, but it was not as effective as the combination of aspirin 650 mg with codeine phosphate 60 mg.
Tramadol hydrochloride has been studied in three long-term controlled trials involving a total of 820 patients, with 530 patients receiving tramadol hydrochloride. Patients with a variety of chronic painful conditions were studied in double-blind trials of one to three months duration. Average daily doses of approximately 250 mg of tramadol hydrochloride in divided doses were generally comparable to five doses of acetaminophen 300 mg with codeine phosphate 30 mg (TYLENOL with Codeine #3) daily, five doses of aspirin 325 mg with codeine phosphate 30 mg daily, or two to three doses of acetaminophen 500 mg with oxycodone hydrochloride 5 mg (TYLOX) daily.
Titration Trials In a randomized, blinded clinical study with 129 to 132 patients per group, a 10-day titration to a daily tramadol hydrochloride dose of 200 mg (50 mg four times per day), attained in 50 mg increments every 3 days, was found to result in fewer discontinuations due to dizziness or vertigo than titration over only 4 days or no titration. In a second study with 54 to 59 patients per group, patients who had nausea or vomiting when titrated over 4 days were randomized to re-initiate tramadol hydrochloride therapy using slower titration rates.
A 16-day titration schedule, starting with 25 mg every morning and using additional doses in 25 mg increments every third day to 100 mg/day (25 mg four times per day), followed by 50 mg increments in the total daily dose every third day to 200 mg/day (50 mg four times per day), resulted in fewer discontinuations due to nausea or vomiting and fewer discontinuations due to any cause than did a 10-day titration schedule (See Figure 2) . Figure 2: Figure 2
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.1Controlled Substance Tramadol hydrochloride oral solution contains tramadol, a Schedule IV controlled substance.
9.2Abuse Tramadol hydrochloride oral solution contains tramadol, a substance having potential for abuse. Tramadol hydrochloride oral solution can be abused and is subject to misuse, addiction, and criminal diversion [see Warnings and Precautions ( 5.2 )] . All patients treated with opioids require careful monitoring for signs of abuse and addiction, because use of opioid analgesic products carries the risk of addiction even under appropriate medical use.
Prescription drug abuse is the intentional non-therapeutic use of a prescription drug, even once, for its rewarding psychological or physiological effects. Drug addiction is a cluster of behavioral, cognitive, and physiological phenomena that develop after repeated substance use and includes: a strong desire to take the drug, difficulties in controlling its use, persisting in its use despite harmful, or potentially harmful, consequences, a higher priority given to drug use than to other activities and obligations, increased tolerance, and sometimes a physical withdrawal. "Drug-seeking" behavior is very common in persons with substance use disorders.
Drug-seeking tactics include emergency calls or visits near the end of office hours, refusal to undergo appropriate examination, testing or referral, repeated "loss" of prescriptions, tampering with prescriptions and reluctance to provide prior medical records or contact information for other treating physician(s). "Doctor shopping" (visiting multiple prescribers to obtain additional prescriptions) is common among drug abusers and people suffering from untreated addiction. Preoccupation with achieving adequate pain relief can be appropriate behavior in a patient with poor pain control.
Abuse and addiction are separate and distinct from physical dependence and tolerance. Healthcare providers should be aware that addiction may not be accompanied by concurrent tolerance and symptoms of physical dependence in all addicts. In addition, abuse of opioids can occur in the absence of true addiction.
Tramadol hydrochloride oral solution, like other opioids, can be diverted for non-medical use into illicit channels of distribution. Careful record-keeping of prescribing information, including quantity, frequency, and renewal requests, as required by state and federal law, is strongly advised. Proper assessment of the patient, proper prescribing practices, periodic re-evaluation of therapy, and proper dispensing and storage are appropriate measures that help to limit abuse of opioid drugs.
Risks Specific to Abuse of tramadol hydrochloride oral solution Tramadol hydrochloride oral solution is intended for oral use only. Abuse of tramadol hydrochloride oral solution poses a risk of overdose and death. The risk is increased with concurrent abuse of tramadol hydrochloride oral solution with alcohol and other central nervous system depressants.
Parenteral drug abuse is commonly associated with transmission of infectious diseases such as hepatitis and HIV.
9.3Dependence Both tolerance and physical dependence can develop during chronic opioid therapy. Tolerance is the need for increasing doses of drugs to maintain a defined effect such as analgesia (in the absence of disease progression or other external factors). Tolerance may occur to both the desired and undesired effects of drugs, and may develop at different rates for different effects.
Physical dependence is a physiological state in which the body adapts to the drug after a period of regular exposure, resulting in withdrawal symptoms after abrupt discontinuation or a significant dosage reduction of a drug. Withdrawal also may be precipitated through the administration of drugs with opioid antagonist activity (e.g., naloxone, nalmefene), mixed agonist/antagonist analgesics (pentazocine, butorphanol, nalbuphine), or partial agonists (buprenorphine). Phy… [Excerpted — this section continues on DailyMed.]
🔒 Controlled Substance ▾
9.1Controlled Substance Tramadol hydrochloride oral solution contains tramadol, a Schedule IV controlled substance.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis A slight, but statistically significant, increase in two common murine tumors, pulmonary and hepatic, was observed in an NMRI mouse carcinogenicity study, particularly in aged mice. Mice were dosed orally up to 30 mg/kg in the drinking water (0.36 times the MRHD) for approximately two years, although the study was not done with the Maximum Tolerated Dose. This finding is not believed to suggest risk in humans.
No evidence of carcinogenicity was noted in a rat 2-year carcinogenicity study testing oral doses of up to 30 mg/kg in the drinking water, 0.73 times the MRHD. Mutagenesis Tramadol was mutagenic in the presence of metabolic activation in the mouse lymphoma assay. Tramadol was not mutagenic in the in vitro bacterial reverse mutation assay using Salmonella and E. coli (Ames), the mouse lymphoma assay in the absence of metabolic activation, the in vitro chromosomal aberration assay, or the in vivo micronucleus assay in bone marrow.
Impairment of Fertility No effects on fertility were observed for tramadol at oral dose levels up to 50 mg/kg in male rats and 75 mg/kg in female rats. These dosages are 1.2 and 1.8 times the maximum recommended human daily dose based on body surface area, respectively. However, published studies report that treatment of adult male rats with tramadol (40 mg/kg, IP and SC for 30 and 60 days, respectively, 1.2x the MRHD based on BSA; or 4.5 to 135 mg/kg, SC for 18 weeks, 0.01x to 3.2x the MRHD based on BSA) produced adverse effects on male reproductive hormones and male reproductive tissues.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis A slight, but statistically significant, increase in two common murine tumors, pulmonary and hepatic, was observed in an NMRI mouse carcinogenicity study, particularly in aged mice. Mice were dosed orally up to 30 mg/kg in the drinking water (0.36 times the MRHD) for approximately two years, although the study was not done with the Maximum Tolerated Dose. This finding is not believed to suggest risk in humans.
No evidence of carcinogenicity was noted in a rat 2-year carcinogenicity study testing oral doses of up to 30 mg/kg in the drinking water, 0.73 times the MRHD. Mutagenesis Tramadol was mutagenic in the presence of metabolic activation in the mouse lymphoma assay. Tramadol was not mutagenic in the in vitro bacterial reverse mutation assay using Salmonella and E. coli (Ames), the mouse lymphoma assay in the absence of metabolic activation, the in vitro chromosomal aberration assay, or the in vivo micronucleus assay in bone marrow.
Impairment of Fertility No effects on fertility were observed for tramadol at oral dose levels up to 50 mg/kg in male rats and 75 mg/kg in female rats. These dosages are 1.2 and 1.8 times the maximum recommended human daily dose based on body surface area, respectively. However, published studies report that treatment of adult male rats with tramadol (40 mg/kg, IP and SC for 30 and 60 days, respectively, 1.2x the MRHD based on BSA; or 4.5 to 135 mg/kg, SC for 18 weeks, 0.01x to 3.2x the MRHD based on BSA) produced adverse effects on male reproductive hormones and male reproductive tissues.
📄 Recent Major Changes ▾
RECENT MAJOR CHANGES Warnings and Precautions
5.20Hyponutremia ( 5.20 )
5.21Hypoglycemia ( 5.21 ) 09/2021 09/2021
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - tramadol hydrochloride oral solution 5 mg/mL, 16 oz Bottle Label NDC 52817-615-16 Tramadol hydrochloride oral solution 5 mg/mL (equivalent to tramadol 4.4 mg per 1 mL) CIV Keep out of reach of children. Rx only 16 oz. (473 mL) 16oz bottle
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |