
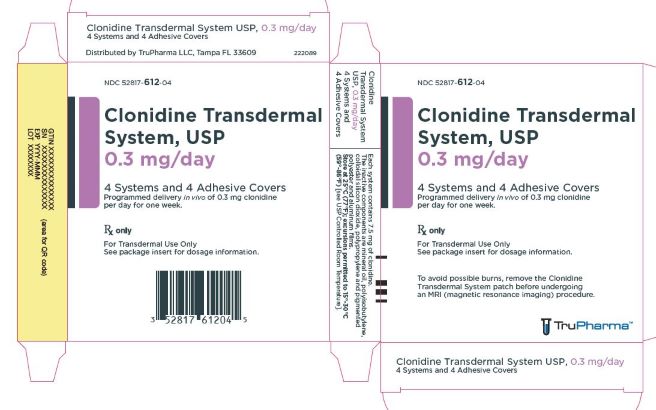
Clonidine Transdermal System USP, 0.3 mg/day .3 mg/d Patch, 4 patches — NDC 52817-612-04 (Billing 52817-0612-04)
This is a package of 4 patches of Clonidine Transdermal System USP, 0.3 mg/day .3 mg/d Patch from TruPharma, LLC, marketed since Jun 2023 and currently FDA-listed, this package's marketing is listed to end Oct 2026; retail pharmacies pay about $12.29 per patche (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 52817-612-04 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 52817 labeler · 612 product · 04 package
- Package marketed since
- Jun 30, 2023
- Package marketing ended
- Oct 30, 2026
- Sample package
- No — commercial package
- Billing quantity
- 4 EA per package
- Barcode (UPC-A, from the NDC)
- 3 5281761204 5
- Medicaid fills, this package
- 3,645 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 000345
- GCN: 23872
- GPI-14 (Medi-Span): 36201010008830
- HICL (First Databank): 036550
- AHFS class code: 24:24.00.00
- RxCUI (RxNorm): 998671
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Central alpha-2 Adrenergic Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Transdermal clonidine is used alone or in combination with other medications to treat high blood pressure. Clonidine is in a class of medications called centrally acting alpha-agonist hypotensive agents. It works by decreasing your heart rate and relaxing the blood vessels so that blood can flow more easily through the body.
Read the full MedlinePlus article ↗- It depends on the product. Tablets, oral solutions, Nexiclon XR and patches lower high blood pressure. Certain extended-release products treat ADHD. The epidural injection is used...
- No. Stopping suddenly can cause rebound high blood pressure, with headache, a racing heart, nervousness and anxiety. Your doctor will lower the dose gradually.
- Sleepiness is common. Don't drive or use heavy equipment until you know how it affects you. Avoid alcohol, and ask me before combining it with other sedating medicines.
- No. Extended-release clonidine tablets should be swallowed whole, not crushed, chewed or broken. They can be taken with or without food.
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $12.291 | $49.16 / 4 patch |
| Medicaid paysCMS SDUD · 12 mo | $16.74 | $66.98 / 4 patch |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 52817-0612-04 You're viewing this Main listing | 4 POUCH in 1 CARTON / 1 PATCH in 1 POUCH / 1 d in 1 PATCH | 2023-06-30 | Oct 30, 2026 | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Clonidine .3 mg/d 00378-0873-99 | Mylan | 4 patches | $12.291 | AB | Availability likely | — |
| Clonidine transdermal system .3 mg/d 00591-3510-04 | Actavis | 4 patches | $12.291 | AB | Availability likely | — |
| Clonidine Transdermal System USP, 0.3 mg/day 52817-0507-04 | TruPharma, | 4 patches | $12.291 | AB | Availability likely | — |
| Clonidine Transdermal System USP, 0.3 mg/daythis 52817-0612-04 | TruPharma, | 4 patches | $12.291 | AB | Availability likely | — |
| Clonidine .3 mg/24h 75907-0025-48 | Dr. | 4 patches | $12.291 | AB | Availability likely | — |
| Catapres-TTS-3 .3 mg/d 82089-0103-34 | Technomed | 4 patches | — | AB | FDA listed | — |
| Catapres-TTS-3 .3 mg/d 82089-0203-34 | Technomed | 4 patches | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII T5L8T28FGP
Mineral oil is a clear, odorless liquid derived from crude oil. It acts as a lubricant and emollient in medications, helping pills slide smoothly during manufacturing and aiding moisture retention in topical products.
-
UNII FLT10CH37X
Polyisobutylene is a synthetic rubber-like polymer used as a glidant and lubricant. It helps the medicine flow smoothly during manufacturing and prevents ingredients from sticking together or to equipment.
-
UNII 98553S1MHQ
A synthetic rubber-like polymer used as a binder and thickening agent. It helps hold tablet ingredients together and can modify the texture or viscosity of liquid and semi-solid formulations.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from TruPharma, LLC labeler code 52817
- Clonidine Transdermal System USP, 0.1 mg/day .1 mg/d Patch NDC 52817-505-04
- Clonidine Transdermal System USP, 0.2 mg/day .2 mg/d Patch NDC 52817-506-04
- Clonidine Transdermal System USP, 0.3 mg/day .3 mg/d Patch NDC 52817-507-04
- VERSACLOZ Clozapine 50 mg/mL Suspension NDC 52817-601-38
- Clonidine Transdermal System USP, 0.1 mg/day .1 mg/d Patch NDC 52817-610-04
- Clonidine Transdermal System USP, 0.2 mg/day .2 mg/d Patch NDC 52817-611-04
- Tramadol Hydrochloride 5 mg/mL Solution NDC 52817-615-16
- Baclofen 10 mg/5mL Solution NDC 52817-620-08
- apomorphine hydrocloride APOMORPHINE HYDROCHLORIDE 30 mg/3mL Injection NDC 52817-720-05
- Clotrimazole Topical Solution USP, 1% 10 mg/mL Solution NDC 52817-800-30
- Triamcinolone Acetonide 1 mg/g Cream NDC 52817-811-15
- Aminocaproic acid .25 g/mL Solution NDC 52817-815-08
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Clonidine transdermal system is indicated in the treatment of hypertension. It may be employed alone or concomitantly with other antihypertensive agents.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Apply Clonidine Transdermal System, USP once every 7 days to a hairless area of intact skin on the upper outer arm or chest. Each new application of Clonidine Transdermal System, USP should be on a different skin site from the previous location. If the system loosens during 7‑day wearing, the adhesive cover should be applied directly over the system to ensure good adhesion.
There have been rare reports of the need for patch changes prior to 7 days to maintain blood pressure control. To initiate therapy, Clonidine Transdermal System, USP dosage should be titrated according to individual therapeutic requirements, starting with Clonidine Transdermal System USP, 0.1 mg/day. If after one or two weeks the desired reduction in blood pressure is not achieved, increase the dosage by adding another Clonidine Transdermal System USP, 0.1 mg/day or changing to a larger system.
An increase in dosage above two Clonidine Transdermal Systems USP, 0.3 mg/day is usually not associated with additional efficacy. When substituting Clonidine Transdermal System, USP for oral clonidine or for other antihypertensive drugs, physicians should be aware that the antihypertensive effect of Clonidine Transdermal System, USP may not commence until 2‑3 days after initial application. Therefore, gradual reduction of prior drug dosage is advised.
Some or all previous antihypertensive treatment may have to be continued, particularly in patients with more severe forms of hypertension. Renal Impairment Patients with renal impairment may benefit from a lower initial dose. Patients should be carefully monitored.
Since only a minimal amount of clonidine is removed during routine hemodialysis, there is no need to give supplemental clonidine following dialysis.
⛔ Contraindications ▾
CONTRAINDICATIONS Clonidine transdermal system should not be used in patients with known hypersensitivity to clonidine or to any other component of the transdermal system.
⚠️ Warnings ▾
WARNINGS Withdrawal Patients should be instructed not to discontinue therapy without consulting their physician. Sudden cessation of clonidine treatment has, in some cases, resulted in symptoms such as nervousness, agitation, headache, tremor, and confusion accompanied or followed by a rapid rise in blood pressure and elevated catecholamine concentrations in the plasma. The likelihood of such reactions to discontinuation of clonidine therapy appears to be greater after administration of higher doses or continuation of concomitant beta‑blocker treatment and special caution is therefore advised in these situations.
Rare instances of hypertensive encephalopathy, cerebrovascular accidents and death have been reported after clonidine withdrawal. When discontinuing therapy with clonidine transdermal system, the physician should reduce the dose gradually over 2 to 4 days to avoid withdrawal symptomatology. An excessive rise in blood pressure following discontinuation of clonidine transdermal system therapy can be reversed by administration of oral clonidine hydrochloride or by intravenous phentolamine.
If therapy is to be discontinued in patients receiving a beta‑blocker and clonidine concurrently, the beta‑blocker should be withdrawn several days before the gradual discontinuation of clonidine transdermal system.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Clinical trial experience with clonidine transdermal system Most systemic adverse effects during clonidine transdermal system therapy have been mild and have tended to diminish with continued therapy. In a 3‑month multi-clinic trial of clonidine transdermal system in 101 hypertensive patients, the systemic adverse reactions were, dry mouth (25 patients) and drowsiness (12), fatigue (6), headache (5), lethargy and sedation (3 each), insomnia, dizziness, impotence/sexual dysfunction, dry throat (2 each) and constipation, nausea, change in taste and nervousness (1 each).
In the above mentioned 3‑month controlled clinical trial, as well as other uncontrolled clinical trials, the most frequent adverse reactions were dermatological and are described below. In the 3‑month trial, 51 of the 101 patients had localized skin reactions such as erythema (26 patients) and/or pruritus, particularly after using an adhesive cover throughout the 7‑day dosage interval. Allergic contact sensitization to clonidine transdermal system was observed in 5 patients.
Other skin reactions were localized vesiculation (7 patients), hyperpigmentation (5), edema (3), excoriation (3), burning (3), papules (1), throbbing (1), blanching (1), and a generalized macular rash (1). In additional clinical experience, contact dermatitis resulting in treatment discontinuation was observed in 128 of 673 patients (about 19 in 100) after a mean duration of treatment of 37 weeks. The incidence of contact dermatitis was about 34 in 100 among white women, about 18 in 100 in white men, about 14 in 100 in black women, and approximately 8 in 100 in black men.
Analysis of skin reaction data showed that the risk of having to discontinue clonidine transdermal system treatment because of contact dermatitis was greatest between treatment weeks 6 and 26, although sensitivity may develop either earlier or later in treatment. In a large‑scale clinical acceptability and safety study by 451 physicians in a total of 3539 patients, other allergic reactions were recorded for which a causal relationship to clonidine transdermal system was not established: maculopapular rash (10 cases); urticaria (2 cases); and angioedema of the face (2 cases), which also affected the tongue in one of the patients.
Marketing Experience with clonidine transdermal system The following adverse reactions have been identified during post-approval use of clonidine transdermal system. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to estimate reliably their frequency or establish a causal relationship to drug exposure. Decisions to include these reactions in labeling are typically based on one or more of the following factors: (1) seriousness of the reaction, (2) frequency of reporting, or (3) strength of causal connection to clonidine transdermal system.
Body as a Whole: Fever; malaise; weakness; pallor; and withdrawal syndrome. Cardiovascular: Congestive heart failure; cerebrovascular accident; electrocardiographic abnormalities (i.e., bradycardia, sick sinus syndrome disturbances and arrhythmias); chest pain; orthostatic symptoms; syncope; increases in blood pressure; sinus bradycardia and AV block with and without the use of concomitant digitalis; Raynaud’s phenomenon; tachycardia; bradycardia; and palpitations. Central and Peripheral Nervous System/Psychiatric: Delirium; mental depression; hallucinations (including visual and auditory); localized numbness; vivid dreams or nightmares; restlessness; anxiety; agitation; irritability; other behavioral changes; and drowsiness.
Dermatological: Angioneurotic edema; localized or generalized rash; hives; urticaria; contact dermatitis; pruritus; alopecia; and localized hypo or hyper pigmentation. Gastrointestinal: Anorexia and vomiting. Genitourinary: Difficult micturition; loss of libido; and decreased sexual activity.
Metabolic: Gynecomastia or breast enlargement and weight gain. Musculosk… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
Drug Interactions Clonidine may potentiate the CNS-depressive effects of alcohol, barbiturates or other sedating drugs. If a patient receiving clonidine is also taking tricyclic antidepressants, the hypotensive effect of clonidine may be reduced, necessitating an increase in the clonidine dose. If a patient receiving clonidine is also taking neuroleptics, orthostatic regulation disturbances (e.g., orthostatic hypotension, dizziness, fatigue) may be induced or exacerbated.
Monitor heart rate in patients receiving clonidine concomitantly with agents known to affect sinus node function or AV nodal conduction e.g., digitalis, calcium channel blockers, and beta‑blockers. Sinus bradycardia resulting in hospitalization and pacemaker insertion has been reported in association with the use of clonidine concomitantly with diltiazem or verapamil. Amitriptyline in combination with clonidine enhances the manifestation of corneal lesions in rats (see Toxicology ).
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects Reproduction studies performed in rabbits at doses up to approximately 3 times the oral maximum recommended daily human dose (MRDHD) of clonidine hydrochloride produced no evidence of a teratogenic or embryotoxic potential in rabbits. In rats, however, doses as low as 1/3 the oral MRDHD (1/15 the MRDHD on a mg/m 2 basis) of clonidine were associated with increased resorptions in a study in which dams were treated continuously from 2 months prior to mating. Increased resorptions were not associated with treatment at the same or at higher dose levels (up to 3 times the oral MRDHD) when the dams were treated on gestation days 6 to 15.
Increases in resorption were observed at much higher dose levels (40 times the oral MRDHD on a mg/kg basis; 4 to 8 times the MRDHD on a mg/m 2 basis) in mice and rats treated on gestation days 1 to 14 (lowest dose employed in the study was 500 µg/kg). No adequate well‑controlled studies have been conducted in pregnant women. Clonidine crosses the placental barrier (see CLINICAL PHARMACOLOGY, Pharmacokinetics ).
Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in pediatric patients have not been established in adequate and well-controlled trials.
🆘 Overdosage ▾
OVERDOSAGE Hypertension may develop early and may be followed by hypotension, bradycardia, respiratory depression, hypothermia, drowsiness, decreased or absent reflexes, weakness, irritability and miosis. The frequency of CNS depression may be higher in children than adults. Large overdoses may result in reversible cardiac conduction defects or dysrhythmias, apnea, coma and seizures.
Signs and symptoms of overdose generally occur within 30 minutes to two hours after exposure. As little as 0.1 mg of clonidine has produced signs of toxicity in children. If symptoms of poisoning occur following dermal exposure, remove all clonidine transdermal systems.
After their removal, the plasma clonidine levels will persist for about 8 hours, then decline slowly over a period of several days. Rare cases of clonidine transdermal system poisoning due to accidental or deliberate mouthing or ingestion of the patch have been reported, many of them involving children. There is no specific antidote for clonidine overdosage.
Ipecac syrup‑induced vomiting and gastric lavage would not be expected to remove significant amounts of clonidine following dermal exposure. If the patch is ingested, whole bowel irrigation may be considered and the administration of activated charcoal and/or cathartic may be beneficial. Supportive care may include atropine sulfate for bradycardia, intravenous fluids and/or vasopressor agents for hypotension and vasodilators for hypertension.
Naloxone may be a useful adjunct for the management of clonidine‑induced respiratory depression, hypotension and/or coma; blood pressure should be monitored since the administration of naloxone has occasionally resulted in paradoxical hypertension. Dialysis is not likely to significantly enhance the elimination of clonidine. The largest overdose reported to date, involved a 28‑year old male who ingested 100 mg of clonidine hydrochloride powder.
This patient developed hypertension followed by hypotension, bradycardia, apnea, hallucinations, semicoma, and premature ventricular contractions. The patient fully recovered after intensive treatment. Plasma clonidine levels were 60 ng/mL after 1 hour, 190 ng/mL after 1.5 hours, 370 ng/mL after 2 hours, and 120 ng/mL after 5.5 and 6.5 hours.
In mice and rats, the oral LD 50 of clonidine is 206 and 465 mg/kg, respectively.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Clonidine stimulates alpha‑adrenoreceptors in the brain stem. This action results in reduced sympathetic outflow from the central nervous system and in decreases in peripheral resistance, renal vascular resistance, heart rate, and blood pressure. Renal blood flow and glomerular filtration rate remain essentially unchanged.
Normal postural reflexes are intact; therefore, orthostatic symptoms are mild and infrequent. Acute studies with clonidine hydrochloride in humans have demonstrated a moderate reduction (15% to 20%) of cardiac output in the supine position with no change in the peripheral resistance; at a 45° tilt there is a smaller reduction in cardiac output and a decrease of peripheral resistance. During long‑term therapy, cardiac output tends to return to control values, while peripheral resistance remains decreased.
Slowing of the pulse rate has been observed in most patients given clonidine, but the drug does not alter normal hemodynamic responses to exercise. Tolerance to the antihypertensive effect may develop in some patients, necessitating a reevaluation of therapy. Other studies in patients have provided evidence of a reduction in plasma renin activity and in the excretion of aldosterone and catecholamines.
The exact relationship of these pharmacologic actions to the antihypertensive effect of clonidine has not been fully elucidated. Clonidine acutely stimulates the release of growth hormone in children as well as adults but does not produce a chronic elevation of growth hormone with long‑term use. Pharmacokinetics Clonidine transdermal system delivers clonidine at an approximately constant rate for 7 days.
The absolute bioavailability of clonidine from the clonidine transdermal system dosage form is approximately 60%. Steady-state clonidine plasma levels are obtained within 3 days after transdermal application to the upper outer arm and increase linearly with increasing size of the transdermal patch. Mean steady-state plasma concentrations with the 3.5 cm 2 , 7.0 cm 2 and 10.5 cm 2 systems are approximately 0.4 ng/mL, 0.8 ng/mL, and 1.1 ng/mL, respectively.
Similar clonidine steady-state concentrations are reached after application to the chest. Steady-state clonidine plasma levels remain constant after removal of one system and application of a new system of the same size. Following intravenous administration clonidine displays biphasic disposition with a distribution half-life of about 20 minutes and an elimination half-life ranging from 12 to 16 hours.
The half-life increases up to 41 hours in patients with severe impairment of renal function. Clonidine has a total clearance of 177 mL/min and a renal clearance of 102 mL/min. The apparent volume of distribution (V z ) of clonidine is 197 L (2.9 L/kg).
Clonidine crosses the placental barrier. It has been shown to cross the blood brain barrier in rats. Following oral administration, about 40% to 60% of the absorbed dose is recovered in the urine as unchanged drug within 24 hours.
About 50% of the absorbed dose is metabolized in the liver. After removal of the clonidine transdermal system, clonidine plasma concentrations decline slowly with a half-life of approximately 20 hours.
🧬 Mechanism of Action ▾
System Structure and Components Clonidine Transdermal System, USP is a multi-layered film, 0.2 mm thick, containing clonidine as the active agent. The system areas are 3.5 cm 2 (Clonidine Transdermal System USP, 0.1 mg/day), 7.0 cm 2 (Clonidine Transdermal System USP, 0.2 mg/day) and 10.5 cm 2 (Clonidine Transdermal System USP, 0.3 mg/day) and the amount of drug released is directly proportional to the area (see Release Rate Concept ). The composition per unit area is the same for all three doses.
Proceeding from the visible surface towards the surface attached to the skin, there are four consecutive layers: 1) a backing layer of pigmented polyester and aluminum film; 2) a drug reservoir of clonidine, mineral oil, polyisobutylene, and colloidal silicon dioxide; 3) a microporous polypropylene membrane that controls the rate of delivery of clonidine from the system to the skin surface; 4) an adhesive formulation of clonidine, mineral oil, polyisobutylene, and colloidal silicon dioxide. Prior to use, a protective slit release liner of polyester that covers the adhesive layer is removed.
Cross Section of the System: cross-section-table
Release Rate Concept Clonidine Transdermal System, USP, is programmed to release clonidine at an approximately constant rate for 7 days. The energy for drug release is derived from the concentration gradient existing between a saturated solution of drug in the system and the much lower concentration prevailing in the skin. Clonidine flows in the direction of the lower concentration at a constant rate, limited by the rate‑controlling membrane, so long as a saturated solution is maintained in the drug reservoir.
Following system application to intact skin, clonidine in the adhesive layer saturates the skin site below the system. Clonidine from the drug reservoir then begins to flow through the rate‑controlling membrane and the adhesive layer of the system into the systemic circulation via the capillaries beneath the skin. Therapeutic plasma clonidine levels are achieved 2 to 3 days after initial application of Clonidine Transdermal System, USP, 0.1 mg/day.
The 3.5, 7.0, and 10.5 cm 2 systems deliver 0.1, 0.2, and 0.3 mg of clonidine per day, respectively. To ensure constant release of drug for 7 days, the total drug content of the system is higher than the total amount of drug delivered. Application of a new system to a fresh skin site at weekly intervals continuously maintains therapeutic plasma concentrations of clonidine.
If the Clonidine Transdermal System, USP is removed and not replaced with a new system, therapeutic plasma clonidine levels will persist for about 8 hours and then decline slowly over several days. Over this time period, blood pressure returns gradually to pretreatment levels.
Pharmacokinetics Clonidine transdermal system delivers clonidine at an approximately constant rate for 7 days. The absolute bioavailability of clonidine from the clonidine transdermal system dosage form is approximately 60%. Steady-state clonidine plasma levels are obtained within 3 days after transdermal application to the upper outer arm and increase linearly with increasing size of the transdermal patch.
Mean steady-state plasma concentrations with the 3.5 cm 2 , 7.0 cm 2 and 10.5 cm 2 systems are approximately 0.4 ng/mL, 0.8 ng/mL, and 1.1 ng/mL, respectively. Similar clonidine steady-state concentrations are reached after application to the chest. Steady-state clonidine plasma levels remain constant after removal of one system and application of a new system of the same size.
Following intravenous administration clonidine displays biphasic disposition with a distribution half-life of about 20 minutes and an elimination half-life ranging from 12 to 16 hours. The half-life increases up to 41 hours in patients with severe impairment of renal function. Clonidine has a total clearance of 177 mL/min and a renal clearance of 102 mL/min.
The apparent volume of distribution (V z ) of clonidine is 197 L (2.9 L/… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Clonidine Transdermal System USP, 0.1 mg/day, Clonidine Transdermal System USP, 0.2 mg/day, and Clonidine Transdermal System USP, 0.3 mg/day are supplied as 4 pouched systems and 4 adhesive covers per carton. See chart below. Programmed Delivery Clonidine in vivo Per Day Over 1 Week Clonidine Content Size Code Clonidine Transdermal System USP, 0.1 mg/day NDC 52817-610-04 0.1 mg 2.5 mg 3.5 cm 2 BI-31 Clonidine Transdermal System USP, 0.2 mg/day NDC 52817-611-04 0.2 mg 5.0 mg 7.0 cm 2 BI-32 Clonidine Transdermal System USP, 0.3 mg/day NDC 52817-612-04 0.3 mg 7.5 mg 10.5 cm 2 BI-33
📦 Storage and Handling ▾
STORAGE AND HANDLING Store at 25°C (77°F); excursions permitted to 15°- 30°C (59°- 86°F) [see USP Controlled Room Temperature]. Distributed by: TruPharma LLC, Tampa FL 33609, USA Address medical inquiries to: (877) 541-5504 Revised: March 2023 222078
📋 Description ▾
DESCRIPTION Clonidine Transdermal System, USP provides continuous systemic delivery of clonidine for 7 days at an approximately constant rate. Clonidine is a centrally acting alpha‑agonist hypotensive agent. It is an imidazoline derivative with the chemical name 2,6‑dichloro‑N‑2‑imidazolidinylidenebenzenamine and has the following chemical structure: System Structure and Components Clonidine Transdermal System, USP is a multi-layered film, 0.2 mm thick, containing clonidine as the active agent.
The system areas are 3.5 cm 2 (Clonidine Transdermal System USP, 0.1 mg/day), 7.0 cm 2 (Clonidine Transdermal System USP, 0.2 mg/day) and 10.5 cm 2 (Clonidine Transdermal System USP, 0.3 mg/day) and the amount of drug released is directly proportional to the area (see Release Rate Concept ). The composition per unit area is the same for all three doses. Proceeding from the visible surface towards the surface attached to the skin, there are four consecutive layers: 1) a backing layer of pigmented polyester and aluminum film; 2) a drug reservoir of clonidine, mineral oil, polyisobutylene, and colloidal silicon dioxide; 3) a microporous polypropylene membrane that controls the rate of delivery of clonidine from the system to the skin surface; 4) an adhesive formulation of clonidine, mineral oil, polyisobutylene, and colloidal silicon dioxide.
Prior to use, a protective slit release liner of polyester that covers the adhesive layer is removed. Cross Section of the System: cross-section-table Release Rate Concept Clonidine Transdermal System, USP, is programmed to release clonidine at an approximately constant rate for 7 days. The energy for drug release is derived from the concentration gradient existing between a saturated solution of drug in the system and the much lower concentration prevailing in the skin.
Clonidine flows in the direction of the lower concentration at a constant rate, limited by the rate‑controlling membrane, so long as a saturated solution is maintained in the drug reservoir. Following system application to intact skin, clonidine in the adhesive layer saturates the skin site below the system. Clonidine from the drug reservoir then begins to flow through the rate‑controlling membrane and the adhesive layer of the system into the systemic circulation via the capillaries beneath the skin.
Therapeutic plasma clonidine levels are achieved 2 to 3 days after initial application of Clonidine Transdermal System, USP, 0.1 mg/day. The 3.5, 7.0, and 10.5 cm 2 systems deliver 0.1, 0.2, and 0.3 mg of clonidine per day, respectively. To ensure constant release of drug for 7 days, the total drug content of the system is higher than the total amount of drug delivered.
Application of a new system to a fresh skin site at weekly intervals continuously maintains therapeutic plasma concentrations of clonidine. If the Clonidine Transdermal System, USP is removed and not replaced with a new system, therapeutic plasma clonidine levels will persist for about 8 hours and then decline slowly over several days. Over this time period, blood pressure returns gradually to pretreatment levels. clonidine structure
💬 Information for Patients ▾
Information for Patients Patients should be cautioned against interruption of clonidine transdermal system therapy without their physician’s advice. Since patients may experience a possible sedative effect, dizziness, or accommodation disorder with use of clonidine, caution patients about engaging in activities such as driving a vehicle or operating appliances or machinery. Also, inform patients that this sedative effect may be increased by concomitant use of alcohol, barbiturates, or other sedating drugs.
Patients who wear contact lenses should be cautioned that treatment with clonidine transdermal system may cause dryness of eyes. Patients should be instructed to consult their physicians promptly about the possible need to remove the patch if they observe moderate to severe localized erythema and/or vesicle formation at the site of application or generalized skin rash. If a patient experiences isolated, mild localized skin irritation before completing 7 days of use, the system may be removed and replaced with a new system applied to a fresh skin site.
If the system should begin to loosen from the skin after application, the patient should be instructed to place the adhesive cover directly over the system to ensure adhesion during its 7‑day use. Used clonidine transdermal system PATCHES contain a substantial amount of their initial drug content which may be harmful to infants and children if accidentally applied or ingested. THEREFORE, PATIENTS SHOULD BE CAUTIONED TO KEEP BOTH USED AND UNUSED clonidine transdermal system PATCHES OUT OF THE REACH OF CHILDREN.
After use, clonidine transdermal system PATCHES should be folded in half with the adhesive sides together and discarded away from children’s reach. Instructions for use, storage and disposal of the system are provided at the end of this monograph. These instructions are also included in each box of clonidine transdermal system.
PATIENT INSTRUCTIONS Clonidine Transdermal System, USP (Read the following instructions carefully before using this medication. If you have any questions, please consult with your doctor.) General Information Clonidine transdermal system is a square, tan adhesive PATCH containing an active blood‑pressure‑lowering medication. It is designed to deliver the drug into the body through the skin smoothly and consistently for one full week.
Normal exposure to water, as in showering, bathing, and swimming, should not affect the PATCH. The optional white, round ADHESIVE COVER should be applied directly over the PATCH, should the PATCH begin to separate from the skin. The ADHESIVE COVER ensures that the PATCH sticks to the skin.
The clonidine transdermal system PATCH must be replaced with a new one on a fresh skin site if the one in use significantly loosens or falls off. Skin burns have been reported at the patch site in several patients wearing an aluminized transdermal system during a magnetic resonance imaging scan (MRI). Because the clonidine transdermal system PATCH contains aluminum, it is recommended to remove the system before undergoing an MRI.
How to Apply the Clonidine Transdermal System PATCH Each box of clonidine transdermal system contains two types of pouches: 1. Apply the square, tan clonidine transdermal system PATCH once a week, preferably at a convenient time on the same day of the week (i.e., prior to bedtime on Tuesday of week one; prior to bedtime on Tuesday of week two, etc.). 2.
Select a hairless area such as on the upper, outer arm or upper chest. The area chosen should be free of cuts, abrasions, irritation, scars or calluses and should not be shaved before applying the clonidine transdermal system PATCH. Do not place the clonidine transdermal system PATCH on skin folds or under tight undergarments, since premature loosening may occur.
3. Wash hands with soap and water and thoroughly dry them. 4.
Clean the area chosen with soap and water. Rinse and wipe dry with a clean, dry tissue. 5.
Select the pouch labeled Clonidine Transderma… [Excerpted — this section continues on DailyMed.]
⚠️ Precautions ▾
PRECAUTIONS General In patients who have developed localized contact sensitization to clonidine transdermal system, continuation of clonidine transdermal system or substitution of oral clonidine hydrochloride therapy may be associated with development of a generalized skin rash. In patients who develop an allergic reaction to clonidine transdermal system, substitution of oral clonidine hydrochloride may also elicit an allergic reaction (including generalized rash, urticaria, or angioedema). The sympatholytic action of clonidine may worsen sinus node dysfunction and atrioventricular (AV) block, especially in patients taking other sympatholytic drugs.
There are post-marketing reports of patients with conduction abnormalities and/or taking other sympatholytic drugs who developed severe bradycardia requiring IV atropine, IV isoproterenol and temporary cardiac pacing while taking clonidine. In hypertension caused by pheochromocytoma, no therapeutic effect of clonidine transdermal system can be expected. In rare instances, loss of blood pressure control has been reported in patients using clonidine transdermal system according to the instructions for use.
Perioperative Use Clonidine transdermal system therapy should not be interrupted during the surgical period. Blood pressure should be carefully monitored during surgery and additional measures to control blood pressure should be available if required. Physicians considering starting clonidine transdermal system therapy during the perioperative period must be aware that therapeutic plasma clonidine levels are not achieved until 2 to 3 days after initial application of clonidine transdermal system (see DOSAGE AND ADMINISTRATION ).
Defibrillation or Cardioversion The clonidine transdermal systems should be removed before attempting defibrillation or cardioversion because of the potential for altered electrical conductivity which may increase the risk of arcing, a phenomenon associated with the use of defibrillators. MRI Skin burns have been reported at the patch site in several patients wearing an aluminized transdermal system during a magnetic resonance imaging scan (MRI). Because the clonidine transdermal system contains aluminum, it is recommended to remove the system before undergoing an MRI.
Information for Patients Patients should be cautioned against interruption of clonidine transdermal system therapy without their physician’s advice. Since patients may experience a possible sedative effect, dizziness, or accommodation disorder with use of clonidine, caution patients about engaging in activities such as driving a vehicle or operating appliances or machinery. Also, inform patients that this sedative effect may be increased by concomitant use of alcohol, barbiturates, or other sedating drugs.
Patients who wear contact lenses should be cautioned that treatment with clonidine transdermal system may cause dryness of eyes. Patients should be instructed to consult their physicians promptly about the possible need to remove the patch if they observe moderate to severe localized erythema and/or vesicle formation at the site of application or generalized skin rash. If a patient experiences isolated, mild localized skin irritation before completing 7 days of use, the system may be removed and replaced with a new system applied to a fresh skin site.
If the system should begin to loosen from the skin after application, the patient should be instructed to place the adhesive cover directly over the system to ensure adhesion during its 7‑day use. Used clonidine transdermal system PATCHES contain a substantial amount of their initial drug content which may be harmful to infants and children if accidentally applied or ingested. THEREFORE, PATIENTS SHOULD BE CAUTIONED TO KEEP BOTH USED AND UNUSED clonidine transdermal system PATCHES OUT OF THE REACH OF CHILDREN.
After use, clonidine transdermal system PATCHES should be folded in half with the adhesive sides together and discarded away from child… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers As clonidine is excreted in human milk, caution should be exercised when clonidine transdermal system is administered to a nursing woman.
🔒 Drug Abuse and Dependence ▾
Clinical trial experience with clonidine transdermal system Most systemic adverse effects during clonidine transdermal system therapy have been mild and have tended to diminish with continued therapy. In a 3‑month multi-clinic trial of clonidine transdermal system in 101 hypertensive patients, the systemic adverse reactions were, dry mouth (25 patients) and drowsiness (12), fatigue (6), headache (5), lethargy and sedation (3 each), insomnia, dizziness, impotence/sexual dysfunction, dry throat (2 each) and constipation, nausea, change in taste and nervousness (1 each).
In the above mentioned 3‑month controlled clinical trial, as well as other uncontrolled clinical trials, the most frequent adverse reactions were dermatological and are described below. In the 3‑month trial, 51 of the 101 patients had localized skin reactions such as erythema (26 patients) and/or pruritus, particularly after using an adhesive cover throughout the 7‑day dosage interval. Allergic contact sensitization to clonidine transdermal system was observed in 5 patients.
Other skin reactions were localized vesiculation (7 patients), hyperpigmentation (5), edema (3), excoriation (3), burning (3), papules (1), throbbing (1), blanching (1), and a generalized macular rash (1). In additional clinical experience, contact dermatitis resulting in treatment discontinuation was observed in 128 of 673 patients (about 19 in 100) after a mean duration of treatment of 37 weeks. The incidence of contact dermatitis was about 34 in 100 among white women, about 18 in 100 in white men, about 14 in 100 in black women, and approximately 8 in 100 in black men.
Analysis of skin reaction data showed that the risk of having to discontinue clonidine transdermal system treatment because of contact dermatitis was greatest between treatment weeks 6 and 26, although sensitivity may develop either earlier or later in treatment. In a large‑scale clinical acceptability and safety study by 451 physicians in a total of 3539 patients, other allergic reactions were recorded for which a causal relationship to clonidine transdermal system was not established: maculopapular rash (10 cases); urticaria (2 cases); and angioedema of the face (2 cases), which also affected the tongue in one of the patients.
Marketing Experience with clonidine transdermal system The following adverse reactions have been identified during post-approval use of clonidine transdermal system. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to estimate reliably their frequency or establish a causal relationship to drug exposure. Decisions to include these reactions in labeling are typically based on one or more of the following factors: (1) seriousness of the reaction, (2) frequency of reporting, or (3) strength of causal connection to clonidine transdermal system.
Body as a Whole: Fever; malaise; weakness; pallor; and withdrawal syndrome. Cardiovascular: Congestive heart failure; cerebrovascular accident; electrocardiographic abnormalities (i.e., bradycardia, sick sinus syndrome disturbances and arrhythmias); chest pain; orthostatic symptoms; syncope; increases in blood pressure; sinus bradycardia and AV block with and without the use of concomitant digitalis; Raynaud’s phenomenon; tachycardia; bradycardia; and palpitations. Central and Peripheral Nervous System/Psychiatric: Delirium; mental depression; hallucinations (including visual and auditory); localized numbness; vivid dreams or nightmares; restlessness; anxiety; agitation; irritability; other behavioral changes; and drowsiness.
Dermatological: Angioneurotic edema; localized or generalized rash; hives; urticaria; contact dermatitis; pruritus; alopecia; and localized hypo or hyper pigmentation. Gastrointestinal: Anorexia and vomiting. Genitourinary: Difficult micturition; loss of libido; and decreased sexual activity.
Metabolic: Gynecomastia or breast enlargement and weight gain. Musculoskeletal: Muscle or… [Excerpted — this section continues on DailyMed.]
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility Chronic dietary administration of clonidine was not carcinogenic to rats (132 weeks) or mice (78 weeks) dosed, respectively, at up to 46 to 70 times the maximum recommended daily human dose as mg/kg (9 or 6 times the MRDHD on a mg/m 2 basis). There was no evidence of genotoxicity in the Ames test for mutagenicity or mouse micronucleus test for clastogenicity. Fertility of male and female rats was unaffected by clonidine doses as high as 150 µg/kg (approximately 3 times the MRDHD).
In a separate experiment, fertility of female rats appeared to be affected at dose levels of 500 to 2000 µg/kg (10 to 40 times the oral MRDHD on a mg/kg basis; 2 to 8 times the MRDHD on a mg/m 2 basis).
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 0.1 mg Carton NDC 52817- 610 -04 Clonidine Transdermal System, USP 0.1 mg/day 4 Systems and 4 Adhesive Covers Programmed delivery in vivo of 0.1 mg clonidine per day for one week. Rx only For Transdermal Use Only - See package insert for dosage information carton - 0.1 mg
PRINCIPAL DISPLAY PANEL - 0.1 mg Adhesive Cover Contents: 1 ADHESIVE COVER WARNING THIS DOES NOT CONTAIN ACTIVE MEDICATION. APPLY OVER THE PATCH, IF NECESSARY. 1 adhesive-cover - 0.1 mg
PRINCIPAL DISPLAY PANEL - 0.1 mg Pouch Clonidine Transdermal System USP 01. mg/day Programmed delivery in vivo of 0.1 mg clonidine per day for one week. To avoid possible burns, remove the clinidine transdermal system patch before undergoing an MRI (magnetic resonance imaging) procedure. Rx only 222070 pouch (front) - 0.1 mg pouch (back) - 0.1 mg
PRINCIPAL DISPLAY PANEL - 0.2 mg Carton NDC 52817- 611 -04 Clonidine Transdermal System, USP 0.2 mg/day 4 Systems and 4 Adhesive Covers Programmed delivery in vivo of 0.2 mg clonidine per day for one week. Rx only For Transdermal Use Only - See package insert for dosage information carton - 0.2 mg
PRINCIPAL DISPLAY PANEL - 0.2 mg Adhesive Cover Contents: 1 ADHESIVE COVER WARNING THIS DOES NOT CONTAIN ACTIVE MEDICATION. APPLY OVER THE PATCH, IF NECESSARY. 2 adhesive cover - 0.2 mg
PRINCIPAL DISPLAY PANEL - 0.2 mg Pouch Clonidine Transdermal System USP 0.2 mg/day Programmed delivery in vivo of 0.2 mg clonidine per day for one week. To avoid possible burns, remove the clonidine transdermal system patch before undergoing an MRI (magnetic resonance imaging) procedure. Rx only 222073 pouch (front) - 0.2 mg pouch (back) - 0.2 mg
PRINCIPAL DISPLAY PANEL carton - 0.3 mg NDC 52817- 612 -04 Clonidine Transdermal System, USP 0.3 mg/day 4 Systems and 4 Adhesive Covers Programmed delivery in vivo of 0.3 mg clonidine per day for one week. Rx only For Transdermal Use Only - See package insert for dosage information carton - 0.3 mg
PRINCIPAL DISPLAY PANEL - 0.3 mg Adhesive Cover Contents: 1 ADHESIVE COVER WARNING THIS DOES NOT CONTAIN ACTIVE MEDICATION. APPLY OVER THE PATCH, IF NECESSARY. 3 adhesive cover - 0.3 mg
PRINCIPAL DISPLAY PANEL - 0.3 mg Pouch Clonidine Transdermal System USP 0.3 mg/day Programmed delivery in vivo of 0.3 mg clonidine per day for one week. To avoid possible burns, remove the clonidine transdermal system patch before undergoing an MRI (magnetic resonance imaging) procedure. Rx only 222076 pouch (front) - 0.3 mg pouch (back) - 0.3 mg