
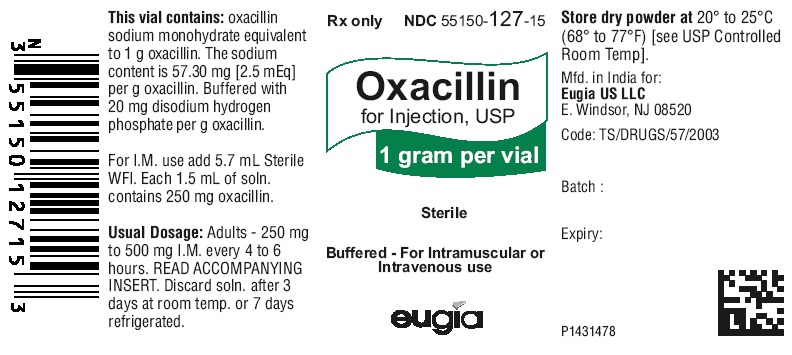
Oxacillin 1 g Injection, Powder, For Solution, 10 vials
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Penicillin-class Antibacterial class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Oxacillin injection is used to treat infections caused by certain bacteria. Oxacillin injection is in a class of medications called penicillins. It works by killing bacteria. Antibiotics such as oxacillin injection will not work for colds, flu, or other viral infections. Taking antibiotics when they are not needed increases your risk of getting an infection later that resists antibiotic treatment.
Read the full MedlinePlus article ↗- Oxacillin is specifically designed to fight staph bacteria that have learned to break down standard penicillin. The staph strain causing your infection produces an enzyme called pe...
- Why am I getting oxacillin instead of a regular penicillin?
- That depends on how serious your infection is and how well your body responds. Mild to moderate infections are often treated for at least two weeks, while serious infections like e...
- How long will I need to be on this antibiotic?
Patient education
Supplement & herbal interactions
Oxacillin may be associated with lower levels of 7 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII GR686LBA74
Sodium phosphate, dibasic is a salt derived from phosphoric acid. It acts as a buffer to help maintain the medicine's pH balance and may serve as a binder or filler in tablets and capsules.
1 inactive ingredient listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $1.12 | — |
| Medicare drug plans payPart D · Q2 2026 | $8.84 | — |
| Medicare Part B allowsASP · J2700 | $0.763 / J2700 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Oxacillin 1 gthis 55150-0127-15 | Eugia | 10 vials | — | AP | FDA listed | — |
| Oxacillin 1 g/20mL 63323-0813-20 | Fresenius | 10 vials | — | AP | FDA listed | — |
| Oxacillin 1 g/20mL 64679-0698-01 | Wockhardt | 10 vials | — | AP | FDA listed | — |
| oxacillin 1 g 83270-0306-10 | Onesource | 10 vials | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2025 (Q1-Q4)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 55150-0127-15 You're viewing this | 10 VIAL in 1 BOX (55150-127-15) / 1 INJECTION, POWDER, FOR SOLUTION in 1 VIAL | 2013-01-18 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Oxacillin is indicated in the treatment of infections caused by penicillinase producing staphylococci which have demonstrated susceptibility to the drug. Cultures and susceptibility tests should be performed initially to determine the causative organism and its susceptibility to the drug (See CLINICAL PHARMACOLOGY - Susceptibility Test Methods ). Oxacillin may be used to initiate therapy in suspected cases of resistant staphylococcal infections prior to the availability of susceptibility test results.
Oxacillin should not be used in infections caused by organisms susceptible to penicillin G. If the susceptibility tests indicate that the infection is due to an organism other than a resistant Staphylococcus , therapy should not be continued with oxacillin. To reduce the development of drug-resistant bacteria and maintain the effectiveness of Oxacillin for Injection, USP and other antibacterial drugs, Oxacillin for Injection, USP should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria.
When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Bacteriologic studies to determine the causative organisms and their susceptibility to oxacillin should always be performed. Duration of therapy varies with the type of severity of infection as well as the overall condition of the patient; therefore, it should be determined by the clinical and bacteriological response of the patient. In severe staphylococcal infections, therapy with oxacillin should be continued for at least 14 days.
Therapy should be continued for at least 48 hours after the patient has become afebrile, asymptomatic, and cultures are negative. Treatment of endocarditis and osteomyelitis may require a longer duration of therapy. With intravenous administration, particularly in elderly patients, care should be taken because of the possibility of thrombophlebitis.
RECOMMENDED DOSAGES FOR OXACILLIN FOR INJECTION, USP Drug Adults Infants and Children <40 kg (88 lbs) Other Recommendations Oxacillin 250 to 500 mg IM or IV every 4 to 6 hours (mild to moderate infections) 50 mg/kg/day IM or IV in equally divided doses every 6 hours (mild to moderate infections) 1 gram IM or IV every 4 to 6 hours (severe infections) 100 mg/kg/day IM or IV in equally divided doses every 4 to 6 hours (severe infections) Premature and Neonates 25 mg/kg/day IM or IV Directions for Use For Intramuscular Use Use Sterile Water for Injection, USP.
Add 5.7 mL to the 1 gram vial and 11.5 mL to the 2 gram vial. Shake well until a clear solution is obtained. After reconstitution, vials will contain 250 mg of active drug per 1.5 mL of solution.
The reconstituted solution is stable for 3 days at 70°F or for one week under refrigeration (40°F). For Direct Intravenous Use Use Sterile Water for Injection, USP or Sodium Chloride Injection, USP. Add 10 mL to the 1 gram vial and 20 mL to the 2 gram vial.
Withdraw the entire contents and administer slowly over a period of approximately 10 minutes. For Administration by Intravenous Drip Reconstitute as directed above ( For Direct Intravenous Use ) prior to diluting with Intravenous Solution. STABILITY PERIODS FOR OXACILLIN FOR INJECTION, USP Concentration mg/mL Sterile Water for Injection USP 0.9% Sodium chloride Injection, USP M/6 Molar Sodium Lactate Solution 5% Dextrose in water 5% Dextrose in 0.45% sodium chloride 10% Invert Sugar Injection, USP Lactated Ringers Solution ROOM TEMPERATURE (25°C) 10-100 4 Days 4 Days 10-30 24 Hrs 24 Hrs 0.5-2 6 Hrs 6 Hrs 6 Hrs REFRIGERATION (4°C) 10-100 7 Days 7 Days 10-30 4 Days 4 Days 4 Days 4 Days 4 Days FROZEN (-15°C) 50-100 30 Days 250/1.5 mL 30 Days 100 30 Days 10-100 30 Days 30 Days 30 Days 30 Days 30 Days Stability studies on oxacillin sodium at concentrations of 0.5 mg/mL and 2 mg/mL in various intravenous solutions listed below indicate the drug will lose less than 10% activity at room temperature (70°F) during a 6-hour period.
IV Solution 5% Dextrose in Normal Saline 10% D-Fructose in Water 10% D-Fructose in Normal Saline Lactated Potassic Saline Injection 10% Invert Sugar in Normal Saline 10% Invert Sugar Plus 0.3% Potassium Chloride in Water Travert 10% Electrolyte #1 Travert 10% Electrolyte #2 Travert 10% Electrolyte #3 Only those solutions listed above should be used for the intravenous infusion of oxacillin sodium. The concentration of the antibiotic should fall within the range specified. The drug concentration and the rate and volume of the infusion should be adjusted so that the total dose of oxacillin is administered before the drug loses its stability in the solution in use.
If another agent is used in conjunction with oxacillin therapy, it should not be physically mixed with oxacillin but should be administered separately. Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit. Do not add supplementary medication to Oxacillin for Injection, USP.
⛔ Contraindications ▾
CONTRAINDICATIONS A history of a hypersensitivity (anaphylactic) reaction to any penicillin is a contraindication.
⚠️ Warnings ▾
WARNINGS Serious and occasionally fatal hypersensitivity (anaphylactic shock with collapse) reactions have occurred in patients receiving penicillin. The incidence of anaphylactic shock in all penicillin-treated patients is between 0.015 and 0.04 percent. Anaphylactic shock resulting in death has occurred in approximately 0.002 percent of the patients treated.
When oxacillin therapy is indicated, it should be initiated only after a comprehensive patient drug and allergy history has been obtained. If an allergic reaction occurs, oxacillin should be discontinued and appropriate therapy instituted. Clostridium difficile associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including Oxacillin for Injection, USP, and may range in severity from mild diarrhea to fatal colitis.
Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C. difficile . C. difficile produces toxins A and B which contribute to the development of CDAD. Hypertoxin producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy.
CDAD must be considered in all patients who present with diarrhea following antibiotic use. Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents. If CDAD is suspected or confirmed, ongoing antibiotic use not directed against C. difficile may need to be discontinued.
Appropriate fluid and electrolyte management, protein supplementation, antibiotic treatment of C. difficile , and surgical evaluation should be instituted as clinically indicated.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Body as a Whole The reported incidence of allergic reactions to penicillin ranges from 0.7 to 10 percent (see WARNINGS ). Sensitization is usually the result of treatment but some individuals have had immediate reactions when first treated. In such cases, it is thought that the patients may have had prior exposure to the drug via trace amounts present in milk and vaccines.
Two types of allergic reactions to penicillins are noted clinically, immediate and delayed. Immediate reactions usually occur within 20 minutes of administration and range in severity from urticaria and pruritus to angioneurotic edema, laryngospasm, bronchospasm, hypotension, vascular collapse and death. Such immediate anaphylactic reactions are very rare (see WARNINGS ) and usually occur after parenteral therapy but have occurred in patients receiving oral therapy.
Another type of immediate reaction, an accelerated reaction, may occur between 20 minutes and 48 hours after administration and may include urticaria, pruritus, and fever. Although laryngeal edema, laryngospasm, and hypotension occasionally occur, fatality is uncommon. Delayed allergic reactions to penicillin therapy usually occur after 48 hours and sometimes as late as 2 to 4 weeks after initiation of therapy.
Manifestations of this type of reaction include serum sickness-like symptoms (i.e., fever, malaise, urticaria, myalgia, arthralgia, abdominal pain) and various skin rashes. Nausea, vomiting, diarrhea, stomatitis, black or hairy tongue, and other symptoms of gastrointestinal irritation may occur, especially during oral penicillin therapy. Nervous System Reactions Neurotoxic reactions similar to those observed with penicillin G may occur with large intravenous doses of oxacillin, especially with patients with renal insufficiency.
Urogenital Reactions Renal tubular damage and interstitial nephritis have been associated with the administration of oxacillin. Manifestations of this reaction may include rash, fever, eosinophilia, hematuria, proteinuria, and renal insufficiency. Nephropathy induced by penicillins does not appear to be dose-related and is generally reversible upon prompt discontinuation of therapy.
Gastrointestinal Reactions Pseudomembranous colitis has been reported with the use of oxacillin. The onset of pseudomembranous colitis symptoms may occur during or after antibiotic treatment (see WARNINGS ). Metabolic Reactions Agranulocytosis, neutropenia, and bone marrow depression have been associated with the use of oxacillin.
Hepatotoxicity, characterized by fever, nausea, and vomiting associated with abnormal liver function tests, mainly elevated SGOT levels, has been associated with the use of oxacillin. To report SUSPECTED ADVERSE REACTIONS, contact FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
Drug Interactions Tetracycline, a bacteriostatic antibiotic, may antagonize the bactericidal effect of penicillin and concurrent use of these drugs should be avoided. Oxacillin blood levels may be increased and prolonged by concurrent administration of probenecid which blocks the renal tubular secretion of penicillins. Probenecid decreases the apparent volume of distribution and slows the rate of excretion by competitively inhibiting renal tubular secretion of penicillins.
Oxacillin-probenecid therapy should be limited to those infections where very high serum levels of oxacillin are necessary.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects Reproduction studies performed in the mouse, rat, and rabbit have revealed no evidence of impaired fertility or harm to the fetus due to the penicillinase-resistant penicillins. Human experience with the penicillins during pregnancy has not shown any positive evidence of adverse effects on the fetus. There are, however, no adequate or well-controlled studies in pregnant women showing conclusively that harmful effects of these drugs on the fetus can be excluded.
Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed.
🧒 Pediatric Use ▾
Pediatric Use Because of incompletely developed renal function in pediatric patients, oxacillin may not be completely excreted, with abnormally high blood levels resulting. Frequent blood levels are advisable in this group with dosage adjustments when necessary. All pediatric patients treated with penicillins should be monitored closely for clinical and laboratory evidence of toxic or adverse effects.
Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of Oxacillin for Injection did not include sufficient number of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
This drug is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function. Oxacillin for Injection contains 57.30 mg (2.5 mEq) of sodium per gram.
At the usual recommended doses, patients would receive between 57.30 and 343.8 mg/day (2.5 and 15 mEq) of sodium. The geriatric population may respond with a blunted natriuresis to salt loading. This may be clinically important with regard to such diseases as congestive heart failure.
🆘 Overdosage ▾
OVERDOSAGE The signs and symptoms of oxacillin overdosage are those described in the ADVERSE REACTIONS section. If signs or symptoms occur, discontinue use of the medication, treat symptomatically, and institute appropriate supportive measures.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Intravenous administration provides peak serum levels approximately 5 minutes after the injection is completed. Slow I.V. administration of 500 mg gives a peak serum level of 43 mcg/mL after 5 minutes with a half-life of 20 to 30 minutes. Oxacillin sodium, with normal doses, has insignificant concentrations in the cerebrospinal and ascitic fluids.
It is found in therapeutic concentrations in the pleural, bile, and amniotic fluids. Oxacillin Sodium is rapidly excreted as unchanged drug in the urine by glomerular filtration and active tubular secretion. The elimination half-life for oxacillin is about 0.5 hours.
Nonrenal elimination includes hepatic inactivation and excretion in bile. Oxacillin sodium binds to serum protein, mainly albumin. The degree of protein binding reported varies with the method of study and the investigator, but generally has been found to be 94.2 ± 2.1%.
Probenecid blocks the renal tubular secretion of penicillins. Therefore, the concurrent administration of probenecid prolongs the elimination of oxacillin and, consequently, increases the serum concentration. Intramuscular injections give peak serum levels 30 minutes after injection.
A 250 mg dose gives a level of 5.3 mcg/mL while a 500 mg dose peaks at 10.9 mcg/mL. Intravenous injection gives a peak about 5 minutes after the injection is completed. Slow I.V. dosing with 500 mg gives a 5 minute peak of 43 mcg/mL with a half-life of 20 to 30 minutes.
Microbiology Mode of Action Penicillinase-resistant penicillins exert a bactericidal action against penicillin susceptible microorganisms during the state of active multiplication. All penicillins inhibit the biosynthesis of the bacterial cell wall. Mechanism of Resistance Resistance to penicillins may be mediated by destruction of the beta-lactam ring by a beta-lactamase, altered affinity of penicillin for target, or decreased penetration of the antibiotic to reach the target site.
Cross Resistance Resistance to oxacillin (or cefoxitin) implies resistance to all other beta-lactam agents, except newer agents with activity against methicillin-resistant Staphylococcus aureus . Susceptibility Testing For specific information regarding susceptibility test interpretive criteria and associated test methods and quality control standards recognized by FDA for this drug, please see: https://www.fda.gov/STIC .
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Each vial of Oxacillin for Injection, USP contains oxacillin sodium monohydrate equivalent to 1 gram or 2 grams of oxacillin. Oxacillin for Injection USP, 1 g vials in a Box of 10 NDC 55150-127-15 Oxacillin for Injection USP, 2 g vials in a Box of 10 NDC 55150-128-24 Oxacillin for Injection, USP is a sterile, white to off-white powder and after reconstitution it becomes colorless to light yellow colored clear liquid. Store dry powder at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
The vial stopper is not made with natural rubber latex. Distributed by: Eugia US LLC 279 Princeton-Hightstown Rd. E.
Windsor, NJ 08520 Manufactured by: Eugia Pharma Specialities Limited Hyderabad - 500032 India Revised: November 2022
📋 Description ▾
DESCRIPTION Oxacillin for Injection, USP is a semisynthetic penicillin antibiotic derived from 6-amino-penicillanic acid. It is the sodium salt in a parenteral dosage form. Each vial of Oxacillin for Injection, USP contains oxacillin sodium monohydrate equivalent to 1 gram or 2 grams of oxacillin.
The sodium content is 57.30 mg [2.5 mEq] per gram oxacillin. The product is buffered with 20 mg sterile disodium hydrogen phosphate per gram oxacillin. Oxacillin for Injection, USP is a sterile, white to off-white powder supplied in vials.
Oxacillin sodium, C 19 H 18 N 3 NaO 5 S • H 2 O molecular weight 441.43, is designated as 4-Thia-1-azabicyclo [3.2.0]heptane-2-carboxylic acid, 3,3-dimethyl-6-[[(5-methyl-3-phenyl-4-isoxazolyl) carbonyl] amino]-7-oxo-, monosodium salt, monohydrate, [2 S (2α,5α,6β)] and has the following structural formula: Chemical Structure
💬 Information for Patients ▾
Information for Patients Patients should be counseled that antibacterial drugs including Oxacillin for Injection, USP should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold). When Oxacillin for Injection, USP is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed.
Skipping doses or not completing the full course of therapy may: (1) decrease the effectiveness of the immediate treatment, and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by Oxacillin for Injection, USP or other antibacterial drugs in the future. Diarrhea is a common problem caused by antibiotics which usually ends when the antibiotic is discontinued. Sometimes after starting treatment with antibiotics, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibiotic.
If this occurs, patients should contact their physician as soon as possible.