
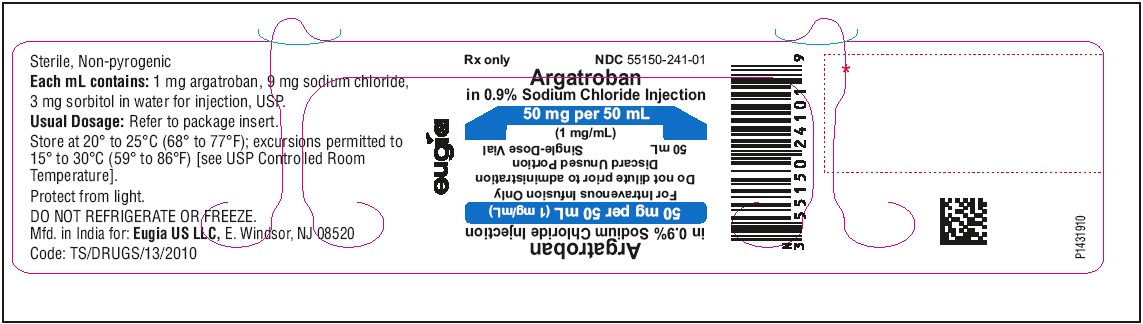
Argatroban 50 mg/50mL Injection, Solution — NDC 55150-241-01 (Billing 55150-0241-01)
This is a package of Argatroban 50 mg/50mL Injection, Solution from Eugia US LLC, marketed since Nov 2018 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 076985
- GCN: 42847
- GPI-14 (Medi-Span): 83337015202010
- HICL (First Databank): 037600
- AHFS class code: 20:12.04.12
- RxCUI (RxNorm): 1804735
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Direct Thrombin Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It's a blood thinner given through a vein. It prevents or treats blood clots in adults with heparin-induced thrombocytopenia (HIT), and it's used during PCI, a heart artery procedu...
- A healthcare professional gives it as an IV infusion, usually in a hospital. Your team will check blood clotting tests to guide the dose, so you don't need to worry about timing or...
- Some people have low blood pressure, shortness of breath, fever, diarrhea, nausea, or vomiting. During PCI, chest pain, back pain, and headache can also happen. Minor bleeding is p...
- Tell them right away about unusual bleeding, blood in your urine or stool, vomiting or coughing up blood, dizziness, trouble breathing, rash, or swelling. Bleeding can happen anywh...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Argatroban — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $0.8000 | $40.00 / 50 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J0898 | $1.214 / J0898 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 55150-0241-01 You're viewing this Main listing | 1 VIAL, SINGLE-DOSE in 1 CARTON / 50 mL in 1 VIAL, SINGLE-DOSE | 2018-11-27 | — | Active |
| 55150-0241-10 55150-241-10 | 10 VIAL, SINGLE-DOSE in 1 CARTON / 50 mL in 1 VIAL, SINGLE-DOSE | 2018-11-27 | — | Active |
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Argatroban 50 mg/50mL Injection, Solution?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Argatroban 50 mg/50mL 00143-9377-01 | Hikma | 1 vial | — | AP | FDA listed | — |
| Argatroban 50 mg/50mL 00143-9559-01 | Hikma | 1 vial | — | AP | FDA listed | — |
| Argatroban 1 mg/mL 16729-0430-11 | Accord | 1 vial | — | — | FDA listed | — |
| Argatroban 1 mg/mL 25021-0414-50 | Sagent | 1 vial | — | AP | FDA listed | — |
| Argatroban 50 mg/50mLthis 55150-0241-01 | Eugia | 1 vial | — | — | FDA listed | — |
| Argatroban 50 mg/50mL 65145-0126-01 | Caplin | 1 vial | — | AP | FDA listed | — |
| Argatroban 50 mg/50mL 65219-0429-50 | Fresenius | 1 vial | — | AP | FDA listed | — |
| Argatroban 50 mg/50mL 68083-0568-01 | Gland | 1 vial | — | AP | FDA listed | — |
| Argatroban 50 mg/50mL 83301-0062-01 | Mullan | 1 vial | — | AP | FDA listed | — |
| Argatroban 50 mg/50mL 83301-0500-01 | Mullan | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 506T60A25R
Sorbitol is a natural sugar alcohol derived from glucose. It serves as a sweetener, humectant, and bulking agent in medications to improve taste and help maintain moisture in the product.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Argatroban in sodium chloride injection is a direct thrombin inhibitor indicated: For prophylaxis or treatment of thrombosis in adult patients with heparin-induced thrombocytopenia (HIT) (1.1) As an anticoagulant in adult patients with or at risk for HIT undergoing percutaneous coronary intervention (PCI) (1.2)
1.1Heparin-Induced Thrombocytopenia Argatroban in sodium chloride injection is indicated for prophylaxis or treatment of thrombosis in adult patients with heparin-induced thrombocytopenia (HIT).
1.2Percutaneous Coronary Intervention Argatroban in sodium chloride injection is indicated as an anticoagulant in adult patients with or at risk for HIT undergoing percutaneous coronary intervention (PCI).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Argatroban 50 mg in 50 mL aqueous sodium chloride solution (1 mg/mL) is intended for administration to adult patients (2.1) Heparin-Induced Thrombocytopenia (2.2) The dose for heparin-induced thrombocytopenia without hepatic impairment is 2 mcg/kg/min administered as a continuous infusion (2.2) Percutaneous Coronary Intervention (2.3) The dose for patients with or at risk for heparin-induced thrombocytopenia undergoing percutaneous coronary intervention is started at 25 mcg/kg/min and a bolus of 350 mcg/kg administered via a large bore intravenous line over 3 to 5 minutes (2.3)
2.1Preparation for Intravenous Administration Each 50 mL glass vial contains 50 mg of argatroban (1 mg/mL); and, as supplied, is ready for intravenous infusion. Dilution is not required. Argatroban in sodium chloride injection is a clear, colorless to pale yellow solution.
Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration whenever solution and container permit. Do not use if the solution is cloudy, contains precipitates, or if the cap/over seal is not intact. Vial may be inverted for use with a medical infusion set.
2.2Dosing in Patients with Heparin-Induced Thrombocytopenia Initial Dosage: Before administering Argatroban in sodium chloride injection, discontinue heparin therapy and obtain a baseline aPTT. The recommended initial dose of Argatroban in sodium chloride injection for adult patients without hepatic impairment is 2 mcg/kg/min, administered as a continuous infusion (see Table 1). Table 1.
1. with or without thrombosis Recommended Doses and Infusion Rates for 2 mcg/kg/min Dose of Argatroban in Sodium Chloride Injection for Patients With HIT 1 and Without Hepatic Impairment (1 mg/mL Concentration) Body Weight (kg) Dose (mcg/min) Infusion Rate (mL/hr) 50 100 6 60 120 7 70 140 8 80 160 10 90 180 11 100 200 12 110 220 13 120 240 14 130 260 16 140 280 17 Monitoring Therapy: For use in HIT, therapy with Argatroban in sodium chloride injection is monitored using the aPTT with a target range of 1.5 to 3 times the initial baseline value (not to exceed 100 seconds).
Tests of anticoagulant effects (including the aPTT) typically attain steady-state levels within 1 to 3 hours following initiation of Argatroban in sodium chloride injection. Check the aPTT 2 hours after initiation of therapy and after any dose change to confirm that the patient has attained the desired therapeutic range. Dosage Adjustment: After the initiation of Argatroban in sodium chloride injection, adjust the dose (not to exceed 10 mcg/kg/min) as necessary to obtain a steady-state aPTT in the target range [ see Clinical Studies (14.1) ] .
2.3Dosing in Patients Undergoing Percutaneous Coronary Interventions Initial Dosage: Initiate an infusion of Argatroban in sodium chloride injection at 25 mcg/kg/min and administer a bolus of 350 mcg/kg via a large bore intravenous line over 3 to 5 minutes (see Table 2). Check an activated clotting time (ACT) 5 to 10 minutes after the bolus dose is completed. The PCI procedure may proceed if the ACT is greater than 300 seconds.
Dosage Adjustment: If the ACT is less than 300 seconds, an additional intravenous bolus dose of 150 mcg/kg should be administered, the infusion dose increased to 30 mcg/kg/min, and the ACT checked 5 to 10 minutes later (see Table 2). If the ACT is greater than 450 seconds, decrease the infusion rate to 15 mcg/kg/min, and check the ACT 5 to 10 minutes later (Table 3). Continue titrating the dose until a therapeutic ACT (between 300 and 450 seconds) has been achieved; continue the same infusion rate for the duration of the PCI procedure.
In case of dissection, impending abrupt closure, thrombus formation during the procedure, or inability to achieve or maintain an ACT over 300 seconds, additional bolus doses of 150 mcg/kg may be administered and the infusion dose increased to 40 mcg/kg/min. Check the ACT after each additional bolus… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: 50 mg/50 mL (1 mg/mL) clear solution in a single-dose vial. The solution is ready for intravenous infusion. Injection: 50 mg/50 mL (1 mg/mL) clear solution in single-dose vial (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Argatroban in sodium chloride injection is contraindicated in: Patients with major bleeding, [ see Warnings and Precautions (5.1) ] Patients with a history of hypersensitivity to argatroban products. Airway, skin, and generalized hypersensitivity reactions have been reported [ see Adverse Reactions (6.1) ] . Major bleeding (4) History of hypersensitivity to this product (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Risk of hemorrhage: Hemorrhage at any site can occur (unexplained fall in hematocrit of blood pressure or other unexplained symptom may indicate hemorrhage). Use with caution in patients at risk, including those receiving antiplatelet agents, thrombolytics, or other anticoagulants. ( 5.1 ) Use in hepatic impairment: Adjust starting dose and titrate carefully in patients with HIT who have moderate or severe hepatic impairment.
Avoid use in PCI in patients with clinically significant hepatic impairment ( 5.2 )
5.1Risk of Hemorrhage Hemorrhage can occur at any site in the body in patients receiving Argatroban in sodium chloride injection. An unexplained fall in hematocrit or hemoglobin or a fall in blood pressure may indicate hemorrhage. Intracranial and retroperitoneal hemorrhage [ see Adverse Reactions (6.1) ] have been reported.
The risk of hemorrhage with Argatroban in sodium chloride injection may be increased in severe hypertension; immediately following lumbar puncture; spinal anesthesia; major surgery (especially involving the brain, spinal cord, or eye); hematologic conditions associated with increased bleeding tendencies such as congenital or acquired bleeding disorders and gastrointestinal lesions such as ulcerations. Concomitant use of Argatroban in sodium chloride injection with antiplatelet agents, thrombolytics, and other anticoagulants may increase the risk of bleeding.
5.2Use in Hepatic Impairment When administering Argatroban in sodium chloride injection to patients with hepatic impairment, start with a lower dose and carefully titrate until the desired level of anticoagulation is achieved. Achievement of steady state aPTT levels may take longer and require more Argatroban in sodium chloride injection dose adjustments in patients with hepatic impairment compared to patients with normal hepatic function [ see Use in Specific Populations (8.6) ]. Also, upon cessation of Argatroban in sodium chloride injection in the hepatically impaired patient, full reversal of anticoagulant effects may require longer than 4 hours due to decreased clearance and increased elimination half-life of argatroban [ see Dosage and Administration (2.4) and Clinical Pharmacology (12.3) ] .
Avoid the use of high doses of Argatroban in sodium chloride injection in patients undergoing PCI who have clinically significant hepatic disease or AST/ALT levels ≥3 times the upper limit of normal.
5.3Laboratory Tests Anticoagulation effects associated with Argatroban in sodium chloride injection at doses up to 40 mcg/kg/min correlate with increases of the activated partial thromboplastin time (aPTT). Although other global clot-based tests including prothrombin time (PT), the International Normalized Ratio (INR), and thrombin time (TT) are affected by Argatroban in sodium chloride injection, the therapeutic ranges for these tests have not been identified for Argatroban in sodium chloride injection therapy. In clinical trials in PCI, the activated clotting time (ACT) was used for monitoring argatroban anticoagulant activity during the procedure.
The concomitant use of Argatroban in sodium chloride injection and warfarin results in prolongation of the PT and INR beyond that produced by warfarin alone [ see Dosage and Administration (2.5) and Clinical Pharmacology (12.2) ] .
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described elsewhere in the labeling: Risk of Hemorrhage [see Warnings and Precautions (5.1) ] HIT patients: The most common (> 5%) adverse reactions were dyspnea, hypotension, fever, diarrhea, sepsis, and cardiac arrest (6.1) PCI patients: The most common (> 5%) adverse reactions were chest pain, hypotension, back pain, nausea, vomiting and headache (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Eugia US LLC at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Adverse Reactions in Patients with HIT (With or Without Thrombosis) Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The following safety information is based on all 568 patients treated with argatroban in Study 1 and Study 2. The safety profile of the patients from these studies is compared with that of 193 historical controls in which the adverse reactions were collected retrospectively.
Adverse reactions are separated into hemorrhagic and non-hemorrhagic reactions. Major bleeding was defined as bleeding that was overt and associated with a hemoglobin decrease ≥2 g/dL, that led to a transfusion of ≥2 units, or that was intracranial, retroperitoneal, or into a major prosthetic joint. Minor bleeding was overt bleeding that did not meet the criteria for major bleeding.
Table 4 gives an overview of the most frequently observed hemorrhagic adverse reactions, presented separately by major and minor bleeding, sorted by decreasing occurrence among argatroban-treated patients with HIT (with or without thrombosis). Table 4. DIC = disseminated intravascular coagulation.
BKA = below-the-knee amputation. 1. with or without thrombosis 2. Patients may have experienced more than 1 adverse reaction.
3. One patient experienced intracranial hemorrhage 4 days after discontinuation of argatroban and following therapy with urokinase and oral anticoagulation. 4.
The historical control group consisted of patients with a clinical diagnosis of HIT (with or without thrombosis) that were considered eligible by an independent medical panel. Major and Minor Hemorrhagic Adverse Reactions in Patients With HIT 1 Major Hemorrhagic Reactions 2 Argatroban-Treated Patients (Study 1 and Study 2) (n = 568) % Historical Control 4 (n = 193) % Overall bleeding 5.3
6.7Gastrointestinal 2.3
1.6Genitourinary and hematuria 0.9
0.5Decrease in hemoglobin and hematocrit 0.7 0 Multisystem hemorrhage and DIC 0.5 1 Limb and BKA stump 0.5 0 Intracranial hemorrhage 0 3
0.5Minor Hemorrhagic Reactions 2 Argatroban-Treated Patients (Study 1 and Study 2) (n = 568) % Historical Control 4 (n = 193) % Gastrointestinal 14.4
18.1Genitourinary and hematuria 11.6
0.8Decrease in hemoglobin and hematocrit 10.4 0 Groin 5.4
3.1Hemoptysis 2.9
0.8Brachial 2.4
0.8Table 5 gives an overview of the most frequently observed non-hemorrhagic reactions sorted by decreasing frequency of occurrence (≥2%) among argatroban-treated HIT/HITTS patients. Table 5. 1.
Patients may have experienced more than 1 adverse reaction. 2. With or without thrombosis 3.
The historical control group consisted of patients with a clinical diagnosis of HIT (with or without thrombosis) that were considered eligible by an independent medical panel Non-hemorrhagic Adverse Reactions in Patients 1 With HIT 2 Argatroban-Treated Patients (Study 1 and Study 2) (n = 568) % Historical Control 3 (n = 193) % Dyspnea 8.1
8.8Hypotension 7.2
2.6Fever 6.9
2.1Diarrhea 6.2
1.6Sepsis 6.0
12.4Cardiac arrest 5.8
3.1Nausea 4.8
0.5Ventricular tachycardia 4.8
3.1Pain 4.6
3.1Urinary tract infection 4.6
5.2Vomiting 4.2 0 Infection 3.7
3.6Pneumonia 3.3
9.3Atrial fibrillation 3.0
11.4Coughing 2.8
1.6Abnormal renal function 2.8
4.7Abdominal pain 2.6 1.… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS
7.1Heparin If Argatroban in sodium chloride injection is to be initiated after cessation of heparin therapy, allow sufficient time for heparin’s effect on the aPTT to decrease prior to initiation of Argatroban in sodium chloride injection therapy.
7.2Oral Anticoagulant Agents Pharmacokinetic drug-drug interactions between Argatroban in sodium chloride injection and warfarin (7.5 mg single oral dose) have not been demonstrated. However, the concomitant use of Argatroban in sodium chloride injection and warfarin (5 to 7.5 mg initial oral dose, followed by 2.5 to 6 mg/day orally for 6 to 10 days) results in prolongation of the prothrombin time (PT) and International Normalized Ratio (INR) [ see Dosage and Administration (2.5) , Clinical Pharmacology (12.2) ] .
7.3Aspirin/Acetaminophen No drug-drug interactions have been demonstrated between Argatroban in sodium chloride injection and concomitantly administered aspirin or acetaminophen [ see Clinical Pharmacology (12.3) ] .
7.4Thrombolytic Agents The safety and effectiveness of Argatroban in sodium chloride injection with thrombolytic agents have not been established [ see Adverse Reactions (6.1) ].
7.5Glycoprotein IIb/IIIa Antagonists The safety and effectiveness of Argatroban in sodium chloride injection with glycoprotein IIb/IIIa antagonists have not been established.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Discontinue nursing or drug, taking into account the importance of the drug to the mother. ( 8.2 ) Pediatric Use: Safety and effectiveness have not been established ( 8.4 )
8.1Pregnancy Risk Summary Limited data from published literature and postmarketing reports do not suggest an association between Argatroban in sodium chloride injection and adverse fetal developmental outcomes. There are risks to the mother associated with untreated thrombosis in pregnancy and a risk of hemorrhage in the mother and fetus associated with use of anticoagulants (see Clinical Considerations ) . In animal reproduction studies, there was no evidence of adverse developmental outcomes with intravenous administration of argatroban during organogenesis in rats and rabbits at doses up to 0.3- and 0.2 times, respectively, the maximum recommended human dose (MHRD) (see Data ) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of birth defects and miscarriage in clinically recognized pregnancies is 2%-4% and 15%-20%, respectively.
Clinical Considerations Disease-Associated Maternal and/or Embryo-Fetal Risk Pregnancy confers an increased risk for thromboembolism that is higher for women with underlying thromboembolic disease and certain high risk pregnancy conditions. Published data describe that women with a previous history of venous thrombosis are at high risk for recurrence during pregnancy. Fetal/Neonatal Adverse Reactions Use of anticoagulants, including Argatroban in sodium chloride injection, may increase the risk of bleeding in the fetus and neonate.
Monitor neonates for bleeding [see Warnings and Precautions (5.1 , 5.3) ] . Labor or Delivery All patients receiving anticoagulants, including pregnant women, are at risk for bleeding. Pregnant women receiving Argatroban in sodium chloride injection should be carefully monitored for evidence of excessive bleeding or unexpected changes in coagulation parameters [see Warnings and Precautions (5.1 , 5.3) ] .
Data Animal Data Developmental studies performed in rats with argatroban at intravenous doses up to 27 mg/kg/day (0.3 times the maximum recommended human dose, based on body surface area) and in rabbits at intravenous doses up to 10.8 mg/kg/day (0.2 times the maximum recommended dose for humans, based on body surface area) have revealed no evidence of harm to the fetus.
8.2Lactation Risk Summary There are no data on the presence of argatroban in human milk, or its effects on milk production. Argatroban is present in rat milk. The developmental and health benefits of breastfeeding should be considered along with the mother’s need for Argatroban in sodium chloride injection and any potential adverse effects on the breastfed child from Argatroban in sodium chloride injection or from the underlying maternal condition.
Data Animal Data Argatroban is detected in rat milk.
8.4Pediatric Use Safety and effectiveness have not been established in pediatric patients. Argatroban was studied among 18 seriously ill pediatric patients who required an alternative to heparin anticoagulation. Most patients were diagnosed with HIT or suspected HIT.
Age ranges of patients were <6 months, n = 8; six months to <8 years, n = 6; 8 to 16 years, n = 4. All patients had serious underlying conditions and were receiving multiple concomitant medications. Thirteen patients received argatroban solely as a continuous infusion (no bolus dose).
Dosing was initiated in the majority of these 13 patients at 1 mcg/kg/min and subsequently titrated as needed to achieve and maintain an aPTT of 1.5 to 3 times the baseline value. Most patients required multiple dose adjustments to maintain anticoagulation parameters within the desired range. During the 30-day study period, thrombotic events o… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Limited data from published literature and postmarketing reports do not suggest an association between Argatroban in sodium chloride injection and adverse fetal developmental outcomes. There are risks to the mother associated with untreated thrombosis in pregnancy and a risk of hemorrhage in the mother and fetus associated with use of anticoagulants (see Clinical Considerations ) . In animal reproduction studies, there was no evidence of adverse developmental outcomes with intravenous administration of argatroban during organogenesis in rats and rabbits at doses up to 0.3- and 0.2 times, respectively, the maximum recommended human dose (MHRD) (see Data ) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of birth defects and miscarriage in clinically recognized pregnancies is 2%-4% and 15%-20%, respectively.
Clinical Considerations Disease-Associated Maternal and/or Embryo-Fetal Risk Pregnancy confers an increased risk for thromboembolism that is higher for women with underlying thromboembolic disease and certain high risk pregnancy conditions. Published data describe that women with a previous history of venous thrombosis are at high risk for recurrence during pregnancy. Fetal/Neonatal Adverse Reactions Use of anticoagulants, including Argatroban in sodium chloride injection, may increase the risk of bleeding in the fetus and neonate.
Monitor neonates for bleeding [see Warnings and Precautions (5.1 , 5.3) ] . Labor or Delivery All patients receiving anticoagulants, including pregnant women, are at risk for bleeding. Pregnant women receiving Argatroban in sodium chloride injection should be carefully monitored for evidence of excessive bleeding or unexpected changes in coagulation parameters [see Warnings and Precautions (5.1 , 5.3) ] .
Data Animal Data Developmental studies performed in rats with argatroban at intravenous doses up to 27 mg/kg/day (0.3 times the maximum recommended human dose, based on body surface area) and in rabbits at intravenous doses up to 10.8 mg/kg/day (0.2 times the maximum recommended dose for humans, based on body surface area) have revealed no evidence of harm to the fetus.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness have not been established in pediatric patients. Argatroban was studied among 18 seriously ill pediatric patients who required an alternative to heparin anticoagulation. Most patients were diagnosed with HIT or suspected HIT.
Age ranges of patients were <6 months, n = 8; six months to <8 years, n = 6; 8 to 16 years, n = 4. All patients had serious underlying conditions and were receiving multiple concomitant medications. Thirteen patients received argatroban solely as a continuous infusion (no bolus dose).
Dosing was initiated in the majority of these 13 patients at 1 mcg/kg/min and subsequently titrated as needed to achieve and maintain an aPTT of 1.5 to 3 times the baseline value. Most patients required multiple dose adjustments to maintain anticoagulation parameters within the desired range. During the 30-day study period, thrombotic events occurred during argatroban administration to two patients and following argatroban discontinuation in three other patients.
Major bleeding occurred among two patients; one patient experienced an intracranial hemorrhage after 4 days of argatroban therapy in the setting of sepsis and thrombocytopenia and another patient experienced an intracranial hemorrhage after receiving argatroban for greater than 14 days. The study findings did not establish the safe and effective use of argatroban in pediatric patients and the dosing of 1 mcg/kg/min was not supported by the pharmacokinetic data described below. Pediatric Pharmacokinetics (PK) and Pharmacodynamics (PD) PK parameters of argatroban were characterized in population PK/PD analysis model with sparse data from 15 seriously ill pediatric patients.
Argatroban clearance in these seriously ill pediatric patients (0.16 L/hr/kg) was 50% lower compared to argatroban clearance in healthy adults (0.31 L/hr/kg). Four pediatric patients with elevated bilirubin (secondary to cardiac complications or hepatic impairment) had, on average, 80% lower clearance (0.03 L/hr/kg) when compared to pediatric patients with normal bilirubin levels. These PK/PD analysis models based on a goal of aPTT prolongation of 1.5 to 3 times the baseline value and avoidance of an aPTT >100 seconds for seriously ill pediatric patients with HIT/HITTS who require an alternative to heparin suggested the following: For patients with normal hepatic function , a starting infusion rate of 0.75 mcg/kg/min may have comparable aPTT responses as a starting dose of 2 mcg/kg/min in healthy adults.
Additionally, based on an evaluation of aPTT every two hours, increasing the dosage by 0.1 to 0.25 mcg/kg/min could achieve additional aPTT responses. For patients with hepatic impairment a starting infusion rate of 0.2 mcg/kg/min with increasing dosing by increments of 0.05 mcg/kg/min may have comparable argatroban exposure as expected with adult doses. The safety and effectiveness of Argatroban in sodium chloride injection with the above dosing have not been adequately assessed in pediatric patients and the safety and effectiveness of Argatroban in sodium chloride injection is not established in pediatric patients.
In addition, the described dosage did not take into account multiple factors that could affect the dosage such as current aPTT, target aPTT, and the clinical status of the patient.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of subjects (1340) in clinical studies of argatroban, 35% were 65 and over. In the clinical studies of adult patients with HIT (with or without thrombosis), the effectiveness of argatroban was not affected by age. No trends were observed across age groups for both aPTT and the ACT.
The safety analysis did suggest that older patients tended to have an increased incidence of adverse reactions compared to younger patients; however, older patients had increased underlying conditions, which may predispose them to adverse reactions. The studies were not sized appropriately to detect differences in safety between age groups.
🆘 Overdosage ▾
10 OVERDOSAGE Excessive anticoagulation, with or without bleeding, may be controlled by discontinuing Argatroban in sodium chloride injection or by decreasing the Argatroban in sodium chloride injection dose. In clinical studies, anticoagulation parameters generally returned from therapeutic levels to baseline within 2 to 4 hours after discontinuation of the drug. Reversal of anticoagulant effect may take longer in patients with hepatic impairment.
No specific antidote to Argatroban in sodium chloride injection is available; if life-threatening bleeding occurs and excessive plasma levels of argatroban are suspected, discontinue Argatroban in sodium chloride injection immediately and measure aPTT and other coagulation parameters. When argatroban was administered as a continuous infusion (2 mcg/kg/min) prior to and during a 4-hour hemodialysis session, approximately 20% of argatroban was cleared through dialysis. Single intravenous doses of argatroban at 200, 124, 150, and 200 mg/kg were lethal to mice, rats, rabbits, and dogs, respectively.
The symptoms of acute toxicity were loss of righting reflex, tremors, clonic convulsions, paralysis of hind limbs, and coma.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Argatroban in sodium chloride injection is a direct thrombin inhibitor that reversibly binds to the thrombin active site. Argatroban does not require the co-factor antithrombin III for antithrombotic activity. Argatroban exerts its anticoagulant effects by inhibiting thrombin-catalyzed or -induced reactions, including fibrin formation; activation of coagulation factors V, VIII, and XIII; activation of protein C; and platelet aggregation.
Argatroban inhibits thrombin with an inhibition constant (Ki) of 0.04 μM. At therapeutic concentrations, argatroban has little or no effect on related serine proteases (trypsin, factor Xa, plasmin, and kallikrein). Argatroban is capable of inhibiting the action of both free and clot-associated thrombin.
12.2Pharmacodynamics When argatroban is administered by continuous infusion, anticoagulant effects and plasma concentrations of argatroban follow similar, predictable temporal response profiles, with low intersubject variability. Immediately upon initiation of argatroban infusion, anticoagulant effects are produced as plasma argatroban concentrations begin to rise. Steady-state levels of both drug and anticoagulant effect are typically attained within 1 to 3 hours and are maintained until the infusion is discontinued or the dosage adjusted.
Steady-state plasma argatroban concentrations increase proportionally with dose (for infusion doses up to 40 mcg/kg/min in healthy subjects) and are well correlated with steady-state anticoagulant effects. For infusion doses up to 40 mcg/kg/min, argatroban increases in a dose-dependent fashion, the activated partial thromboplastin time (aPTT), the activated clotting time (ACT), the prothrombin time (PT), the International Normalized Ratio (INR), and the thrombin time (TT) in healthy volunteers and cardiac patients. Representative steady-state plasma argatroban concentrations and anticoagulant effects are shown below for argatroban infusion doses up to 10 mcg/kg/min (see Figure 1).
Effect on International Normalized Ratio (INR): Because argatroban is a direct thrombin inhibitor, co-administration of argatroban and warfarin produces a combined effect on the laboratory measurement of the INR. However, concurrent therapy, compared to warfarin monotherapy, exerts no additional effect on vitamin K–dependent factor Xa activity. The relationship between INR on co-therapy and warfarin alone is dependent on both the dose of argatroban and the thromboplastin reagent used.
This relationship is influenced by the International Sensitivity Index (ISI) of the thromboplastin. Data for 2 commonly utilized thromboplastins with ISI values of 0.88 (Innovin, Dade) and 1.78 (Thromboplastin C Plus, Dade) are presented in Figure 2 for an argatroban dose of 2 mcg/kg/min. Thromboplastins with higher ISI values than shown result in higher INRs on combined therapy of warfarin and argatroban.
These data are based on results obtained in normal individuals [ see Dosage and Administration (2.5) , Warnings and Precautions (5.3) ]. Figure 2 demonstrates the relationship between INR for warfarin alone and INR for warfarin co-administered with argatroban at a dose of 2 mcg/kg/min. To calculate INR for warfarin alone (INR W ), based on INR for co-therapy of warfarin and argatroban (INR WA ), when the argatroban dose is 2 mcg/kg/min, use the equation next to the appropriate curve.
Example: At a dose of 2 mcg/kg/min and an INR performed with Thromboplastin A, the equation 0.19 + 0.57 (INR WA ) = INR W would allow a prediction of the INR on warfarin alone (INR W ). Thus, using an INR WA value of 4.0 obtained on combined therapy: INR W = 0.19 + 0.57 (4) = 2.47 as the value for INR on warfarin alone. The error (confidence interval) associated with a prediction is ± 0.4 units.
Similar linear relationships and prediction errors exist for argatroban at a dose of 1 mcg/kg/min. Thus, for argatroban doses of 1 or 2 mcg/kg/min, INR W can be predicted from I… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Argatroban in sodium chloride injection is a direct thrombin inhibitor that reversibly binds to the thrombin active site. Argatroban does not require the co-factor antithrombin III for antithrombotic activity. Argatroban exerts its anticoagulant effects by inhibiting thrombin-catalyzed or -induced reactions, including fibrin formation; activation of coagulation factors V, VIII, and XIII; activation of protein C; and platelet aggregation.
Argatroban inhibits thrombin with an inhibition constant (Ki) of 0.04 μM. At therapeutic concentrations, argatroban has little or no effect on related serine proteases (trypsin, factor Xa, plasmin, and kallikrein). Argatroban is capable of inhibiting the action of both free and clot-associated thrombin.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Argatroban in sodium chloride injection is supplied as a single-dose vial containing 50 mg argatroban in 50 mL of aqueous solution (1 mg/mL). 50 mL single-dose vials packaged in carton of 10 vials NDC 55150-241-10 50 mL single-dose vial packaged individually NDC 55150-241-01 Storage and Handling: Store the vials in original cartons at 20º to 25ºC (68º to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Do not refrigerate or freeze.
Retain in the original carton to protect from light. If the solution is cloudy, or if an insoluble precipitate is noted, the vial should be discarded. The vial stopper is not made with natural rubber latex.
📋 Description ▾
11 DESCRIPTION Argatroban in sodium chloride injection is a synthetic direct thrombin inhibitor. The chemical name for argatroban monohydrate is 1-[5-[(aminoiminomethyl)amino]-1-oxo-2-[[(1,2,3,4-tetrahydro-3-methyl-8-quinolinyl)sulfonyl]amino]pentyl]-4-methyl-2-piperidinecarboxylic acid, monohydrate. Argatroban has 4 asymmetric carbons.
One of the asymmetric carbons has an R configuration (stereoisomer Type I) and an S configuration (stereoisomer Type II). Argatroban consists of a mixture of R and S stereoisomers at a ratio of approximately 65:35. The molecular formula of argatroban is C 23 H 36 N 6 O 5 S•H 2 O.
Its molecular weight is 526.66 g/mol. The structural formula is: Argatroban in sodium chloride injection is a sterile, non-pyrogenic, clear, colorless to pale yellow solution. It is supplied in a clear glass single-dose vial containing 50 mg of argatroban in 50 mL sodium chloride solution.
Each mL contains 1 mg argatroban, 9 mg sodium chloride, USP, 3 mg sorbitol, NF in water for injection, USP. The pH of the solution is between 4.0 to 7.5. Argatroban Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Inform patients of the risks associated with Argatroban in sodium chloride injection as well as the plan for regular monitoring during administration of the drug. Specifically, inform patients to report: the use of any other products known to affect bleeding [ see Warnings and Precautions (5.1) ] . any medical history that may increase the risk for bleeding, including a history of severe hypertension; recent lumbar puncture or spinal anesthesia; major surgery, especially involving the brain, spinal cord, or eye; hematologic conditions associated with increased bleeding tendencies such as congenital or acquired bleeding disorders and gastrointestinal lesions such as ulcerations. any bleeding signs or symptoms. the occurrence of any signs or symptoms of allergic reactions (e.g., airway reactions, skin reactions and vasodilation reactions) [ see Adverse Reactions (6.1) ] .
Distributed by: Eugia US LLC 279 Princeton-Hightstown Rd. E. Windsor, NJ 08520 Manufactured by: Eugia Pharma Specialities Limited Hyderabad - 500032 India
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Distribution: Argatroban distributes mainly in the extra cellular fluid as evidenced by an apparent steady-state volume of distribution of 174 mL/kg (12.18 L in a 70 kg adult). Argatroban is 54% bound to human serum proteins, with binding to albumin and α 1 -acid glycoprotein being 20% and 34%, respectively. Metabolism: The main route of argatroban metabolism is hydroxylation and aromatization of the 3-methyltetrahydroquinoline ring in the liver.
The formation of each of the 4 known metabolites is catalyzed in vitro by the human liver microsomal cytochrome P450 enzymes CYP3A4/5. The primary metabolite (M1) exerts 3- to 5-fold weaker anticoagulant effects than argatroban. Unchanged argatroban is the major component in plasma.
The plasma concentrations of M1 range between 0% and 20% of that of the parent drug. The other metabolites (M2 to M4) are found only in very low quantities in the urine and have not been detected in plasma or feces. These data, together with the lack of effect of erythromycin (a potent CYP3A4/5 inhibitor) on argatroban pharmacokinetics, suggest that CYP3A4/5-mediated metabolism is not an important elimination pathway in vivo .
Total body clearance is approximately 5.1 mL/kg/min (0.31 L/kg/hr) for infusion doses up to 40 mcg/kg/min. The terminal elimination half-life of argatroban ranges between 39 and 51 minutes. There is no interconversion of the 21–(R):21–(S) diastereoisomers.
The plasma ratio of these diastereoisomers is unchanged by metabolism or hepatic impairment, remaining constant at 65:35 (± 2%). Excretion: Argatroban is excreted primarily in the feces, presumably through biliary secretion. In a study in which 14 C-argatroban (5 mcg/kg/min) was infused for 4 hours into healthy subjects, approximately 65% of the radioactivity was recovered in the feces within 6 days of the start of infusion with little or no radioactivity subsequently detected.
Approximately 22% of the radioactivity appeared in the urine within 12 hours of the start of infusion. Little or no additional urinary radioactivity was subsequently detected. Average percent recovery of unchanged drug, relative to total dose, was 16% in urine and at least 14% in feces.
Special Populations: Hepatic Impairment : The dosage of Argatroban in sodium chloride injection should be decreased in patients with hepatic impairment [ see Dosage and Administration (2.4) and Warnings and Precautions (5.2) ] . Patients with hepatic impairment were not studied in percutaneous coronary intervention (PCI) trials. At a dose of 2.5 mcg/kg/min, hepatic impairment is associated with decreased clearance and increased elimination half-life of argatroban (to 1.9 mL/kg/min and 181 minutes, respectively, for patients with a Child-Pugh score >6).
Renal Impairment : No dosage adjustment is necessary in patients with renal dysfunction. The effect of renal disease on the pharmacokinetics of argatroban was studied in 6 subjects with normal renal function (mean Clcr = 95 ± 16 mL/min) and in 18 subjects with mild (mean Clcr = 64 ± 10 mL/min), moderate (mean Clcr = 41 ± 5.8 mL/min), and severe (mean Clcr = 5 ± 7 mL/min) renal impairment. The pharmacokinetics and pharmacodynamics of argatroban at dosages up to 5 mcg/kg/min were not significantly affected by renal dysfunction.
Use of argatroban was evaluated in a study of 12 patients with stable end-stage renal disease undergoing chronic intermittent hemodialysis. Argatroban was administered at a rate of 2 to 3 mcg/kg/min (begun at least 4 hours prior to dialysis) or as a bolus dose of 250 mcg/kg at the start of dialysis followed by a continuous infusion of 2 mcg/kg/min. Although these regimens did not achieve the goal of maintaining ACT values at 1.8 times the baseline value throughout most of the hemodialysis period, the hemodialysis sessions were successfully completed with both of these regimens.
The mean ACTs produced in this study ranged from 1.39 to 1.82 times baseline, and the mean aPTTs ranged from… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics When argatroban is administered by continuous infusion, anticoagulant effects and plasma concentrations of argatroban follow similar, predictable temporal response profiles, with low intersubject variability. Immediately upon initiation of argatroban infusion, anticoagulant effects are produced as plasma argatroban concentrations begin to rise. Steady-state levels of both drug and anticoagulant effect are typically attained within 1 to 3 hours and are maintained until the infusion is discontinued or the dosage adjusted.
Steady-state plasma argatroban concentrations increase proportionally with dose (for infusion doses up to 40 mcg/kg/min in healthy subjects) and are well correlated with steady-state anticoagulant effects. For infusion doses up to 40 mcg/kg/min, argatroban increases in a dose-dependent fashion, the activated partial thromboplastin time (aPTT), the activated clotting time (ACT), the prothrombin time (PT), the International Normalized Ratio (INR), and the thrombin time (TT) in healthy volunteers and cardiac patients. Representative steady-state plasma argatroban concentrations and anticoagulant effects are shown below for argatroban infusion doses up to 10 mcg/kg/min (see Figure 1).
Effect on International Normalized Ratio (INR): Because argatroban is a direct thrombin inhibitor, co-administration of argatroban and warfarin produces a combined effect on the laboratory measurement of the INR. However, concurrent therapy, compared to warfarin monotherapy, exerts no additional effect on vitamin K–dependent factor Xa activity. The relationship between INR on co-therapy and warfarin alone is dependent on both the dose of argatroban and the thromboplastin reagent used.
This relationship is influenced by the International Sensitivity Index (ISI) of the thromboplastin. Data for 2 commonly utilized thromboplastins with ISI values of 0.88 (Innovin, Dade) and 1.78 (Thromboplastin C Plus, Dade) are presented in Figure 2 for an argatroban dose of 2 mcg/kg/min. Thromboplastins with higher ISI values than shown result in higher INRs on combined therapy of warfarin and argatroban.
These data are based on results obtained in normal individuals [ see Dosage and Administration (2.5) , Warnings and Precautions (5.3) ]. Figure 2 demonstrates the relationship between INR for warfarin alone and INR for warfarin co-administered with argatroban at a dose of 2 mcg/kg/min. To calculate INR for warfarin alone (INR W ), based on INR for co-therapy of warfarin and argatroban (INR WA ), when the argatroban dose is 2 mcg/kg/min, use the equation next to the appropriate curve.
Example: At a dose of 2 mcg/kg/min and an INR performed with Thromboplastin A, the equation 0.19 + 0.57 (INR WA ) = INR W would allow a prediction of the INR on warfarin alone (INR W ). Thus, using an INR WA value of 4.0 obtained on combined therapy: INR W = 0.19 + 0.57 (4) = 2.47 as the value for INR on warfarin alone. The error (confidence interval) associated with a prediction is ± 0.4 units.
Similar linear relationships and prediction errors exist for argatroban at a dose of 1 mcg/kg/min. Thus, for argatroban doses of 1 or 2 mcg/kg/min, INR W can be predicted from INR WA . For argatroban doses greater than 2 mcg/kg/min, the error associated with predicting INR W from INR WA is ± 1.
Thus, INR W cannot be reliably predicted from INR WA at doses greater than 2 mcg/kg/min. Figure 1. Relationship at Steady State Between Argatroban Dose, Plasma Argatroban Concentration and Anticoagulant Effect Figure 2.
INR Relationship of Argatroban Plus Warfarin Versus Warfarin Alone
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Heparin-Induced Thrombocytopenia The safety and efficacy of argatroban were evaluated in an historically controlled efficacy and safety study (Study 1) and a follow-on efficacy and safety study (Study 2). These studies were comparable with regard to study design, study objectives, dosing regimens as well as study outline, conduct, and monitoring. In these studies, 568 adult patients were treated with argatroban and 193 adult patients made up the historical control group.
Patients had a clinical diagnosis of heparin-induced thrombocytopenia, either without thrombosis (HIT) or with thrombosis (HITTS [heparin-induced thrombocytopenia and thrombosis syndrome]) and were males or non-pregnant females between the age of 18 and 80 years old. HIT/HITTS was defined by a fall in platelet count to less than 100,000/μL or a 50% decrease in platelets after the initiation of heparin therapy with no apparent explanation other than HIT. Patients with HITTS also had an arterial or venous thrombosis documented by appropriate imaging techniques or supported by clinical evidence such as acute myocardial infarction, stroke, pulmonary embolism, or other clinical indications of vascular occlusion.
Patients who had documented histories of positive heparin-dependent antibody tests without current thrombocytopenia or heparin challenge (e.g., patients with latent disease) were also included if they required anticoagulation. These studies did not include patients with documented unexplained aPTT >200% of control at baseline, documented coagulation disorder or bleeding diathesis unrelated to HIT, a lumbar puncture within the past 7 days or a history of previous aneurysm, hemorrhagic stroke, or a thrombotic stroke within the past 6 months unrelated to HIT.
The initial dose of argatroban was 2 mcg/kg/min. Two hours after the start of the argatroban infusion, an aPTT level was obtained and dose adjustments were made (up to a maximum of 10 mcg/kg/min) to achieve a steady-state aPTT value that was 1.5 to 3.0 times the baseline value, not to exceed 100 seconds. Overall the mean aPTT level for HIT and HITTS patients during the Argatroban infusion increased from baseline values of 34 and 38 seconds, respectively, to 62.5 and 64.5 seconds, respectively.
The primary efficacy analysis was based on a comparison of event rates for a composite endpoint that included death (all causes), amputation (all causes) or new thrombosis during the treatment and follow-up period (study days 0 to 37). Secondary analyses included evaluation of the event rates for the components of the composite endpoint as well as time-to-event analyses. In Study 1, a total of 304 patients were enrolled as follows: active HIT (n = 129), active HITTS (n = 144), or latent disease (n = 31).
Among the 193 historical controls, 139 (72%) had active HIT, 46 (24%) had active HITTS, and 8 (4%) had latent disease. Within each group, those with active HIT and those with latent disease were analyzed together. Positive laboratory confirmation of HIT/HITTS by the heparin-induced platelet aggregation test or serotonin release assay was demonstrated in 174 of 304 (57%) argatroban-treated patients (i.e., in 80 with HIT or latent disease and 94 with HITTS) and in 149 of 193 (77%) historical controls (i.e., in 119 with HIT or latent disease and 30 with HITTS).
The test results for the remainder of the patients and controls were either negative or not determined. There was a significant improvement in the composite outcome in patients with HIT and HITTS treated with argatroban versus those in the historical control group (see Table 9). The components of the composite endpoint are shown in Table 9.
Table 9. 1. Death (all cause), amputation (all cause), or new thrombosis within 37-day study period 2.
Reported as the most severe outcome among the components of composite endpoint (severity ranking: death > amputation > new thrombosis); patients may have had multiple outcomes. Efficacy Results of St… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies with argatroban have not been performed. Argatroban was not genotoxic in the Ames test, the Chinese hamster ovary cell (CHO/HGPRT) forward mutation test, the Chinese hamster lung fibroblast chromosome aberration test, the rat hepatocyte, and WI-38 human fetal lung cell unscheduled DNA synthesis (UDS) tests, or the mouse micronucleus test. Argatroban at intravenous doses up to 27 mg/kg/day (0.3 times the recommended maximum human dose based on body surface area) had no effect on fertility and reproductive function of male and female rats.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies with argatroban have not been performed. Argatroban was not genotoxic in the Ames test, the Chinese hamster ovary cell (CHO/HGPRT) forward mutation test, the Chinese hamster lung fibroblast chromosome aberration test, the rat hepatocyte, and WI-38 human fetal lung cell unscheduled DNA synthesis (UDS) tests, or the mouse micronucleus test. Argatroban at intravenous doses up to 27 mg/kg/day (0.3 times the recommended maximum human dose based on body surface area) had no effect on fertility and reproductive function of male and female rats.
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 50 mg per 50 mL (1 mg / mL) - Container Label Rx only NDC 55150-241-01 Argatroban in 0.9% Sodium Chloride Injection 50 mg per 50 mL (1 mg / mL) For Intravenous Infusion Only Do not dilute prior to administration Discard Unused Portion 50 mL Single Dose Vial PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 50 mg per 50 mL (1 mg / mL) - Container Label
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 50 mg per 50 mL (1 mg / mL) - Container-Carton Rx only NDC 55150-241-01 Argatroban in 0.9% Sodium Chloride Injection 50 mg per 50 mL (1 mg/mL) For Intravenous Infusion Only Do not dilute prior to administration Discard Unused Portion Sterile Non-pyrogenic 50 mL Single-Dose Vial eugia PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 50 mg per 50 mL (1 mg / mL) - Container-Carton
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 50 mg per 50 mL (1 mg / mL) – Container-Carton (10 Vials) Rx only NDC 55150-241-10 Argatroban in 0.9% Sodium Chloride Injection 50 mg per 50 mL (1 mg / mL) For Intravenous Infusion Only Do not dilute prior to administration Discard Unused Portion Sterile 10 x 50 mL Non-pyrogenic Single Dose Vials eugia PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 50 mg per 50 mL (1 mg / mL) – Container-Carton (10 Vials)
Medicaid utilization & spend
Medicaid utilization by pack size
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |