
Signifor LAR pasireotide Kit — NDC 55292-143-01 (Billing 55292-0143-01)
This is a package of Signifor LAR pasireotide Kit from Recordati Rare Diseases, Inc., marketed since Dec 2014 and currently FDA-listed. It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 073224
- GCN: 37599
- GPI-14 (Medi-Span): 3017007540G240
- HICL (First Databank): 041635
- AHFS class code: 68:29.04.00
- RxCUI (RxNorm): 1597596
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Somatostatin Analog class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Signifor LAR treats acromegaly and Cushing's disease. It is for people whose surgery did not work well enough or is not possible. It lowers the excess hormones behind these conditi...
- A trained health care professional mixes it and injects it into your buttock muscle, usually every 4 weeks. You don't give it yourself, and food doesn't matter.
- Diarrhea, nausea, belly pain, headache, tiredness, and hair loss are common. High blood sugar and gallstones are also common, so you'll be monitored.
- Call about extreme thirst or urination, fainting, a very slow or irregular heartbeat, severe belly pain or fever, yellowing skin, severe weakness, or greasy loose stools.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Pasireotide Diaspartate — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J2502 | $616.708 / J2502 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 2, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 55292-0143-01 You're viewing this Main listing | 1 KIT in 1 KIT * 6 mL in 1 VIAL, SINGLE-USE * 2 mL in 1 SYRINGE | 2014-12-15 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Signifor LARthis 55292-0143-01 | Recordati | 1 kit | — | — | FDA listed | — |
| Signifor LAR 55292-0142-01 | Recordati | 1 kit | — | — | FDA listed | — |
| Signifor LAR 55292-0139-01 | Recordati | 1 kit | — | — | FDA listed | — |
| Signifor LAR 55292-0140-01 | Recordati | 1 kit | — | — | FDA listed | — |
| Signifor LAR 55292-0141-01 | Recordati | 1 kit | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 7473761 ↗ | Drug substance | — | Dec 14, 2026 |
| US 7759308 ↗ | Drug product | — | Oct 25, 2026 |
| US 7473761 ↗ | Drug substance | — | Dec 14, 2026 |
| US 9351923 ↗ | Drug product | — | May 23, 2028 |
| US 9351923 ↗ | Drug product | — | May 23, 2028 |
| US 7759308 ↗ | Drug product | — | Oct 25, 2026 |
| US 7759308 ↗ | Drug product | — | Oct 25, 2026 |
| US 7759308 ↗ | Drug product | — | Oct 25, 2026 |
| US 7473761 ↗ | Drug substance | — | Dec 14, 2026 |
| US 9351923 ↗ | Drug product | — | May 23, 2028 |
| US 9351923 ↗ | Drug product | — | May 23, 2028 |
| US 7473761 ↗ | Drug substance | — | Dec 14, 2026 |
| US 9351923 ↗ | Drug product | — | May 23, 2028 |
| US 7759308 ↗ | Drug product | — | Oct 25, 2026 |
| US 7473761 ↗ | Drug substance | — | Dec 14, 2026 |
Is there a generic version of SIGNIFOR LAR 60 MG KIT?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE SIGNIFOR LAR is a somatostatin analog indicated for the treatment of: Patients with acromegaly who have had an inadequate response to surgery and/or for whom surgery is not an option. ( 1.1 ) Patients with Cushing's disease for whom pituitary surgery is not an option or has not been curative. ( 1.2 )
1.1Acromegaly SIGNIFOR LAR is indicated for the treatment of patients with acromegaly who have had an inadequate response to surgery and/or for whom surgery is not an option.
1.2Cushing's Disease SIGNIFOR LAR is indicated for the treatment of patients with Cushing's disease for whom pituitary surgery is not an option or has not been curative.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Evaluate fasting plasma glucose (FPG), hemoglobin A1c (HbA1c), liver enzyme tests, electrocardiogram (ECG), serum magnesium, and serum potassium prior to starting. ( 2.1 ) Optimize glucose control in patients with poorly controlled diabetes mellitus prior to starting. ( 2.1 ) Must be administered by a health care professional only by intramuscular injection in the right or left gluteus immediately after reconstitution.
( 2.2 ) Initial Dose: Acromegaly: The initial dose is 40 mg by intramuscular injection once every 4 weeks (every 28 days). ( 2.3 ) Cushing's Disease: The initial dose is 10 mg by intramuscular injection once every 4 weeks (every 28 days). ( 2.3 ) Adjust dose based on response and tolerability.
( 2.4 ) Patients with Hepatic Impairment: Child-Pugh B : Acromegaly: Recommended initial dose is 20 mg once every 4 weeks and maximum dose is 40 mg once every 4 weeks ( 2.5 , 8.6 ) Cushing's Disease: Recommended initial dose is 10 mg once every 4 weeks and maximum dose is 20 mg once every 4 weeks ( 2.5 , 8.6 ) Child-Pugh C : Avoid use in these patients ( 2.5 , 8.6 ) Follow reconstitution and administration instructions. ( 2.6 )
2.1Recommended Baseline Evaluations Prior to Initiation of SIGNIFOR LAR Prior to the initiation of SIGNIFOR LAR, it is recommended that patients have the following baseline evaluations: Fasting plasma glucose (FPG) and hemoglobin A1c (HbA1c) [see Warnings and Precautions (5.1)] Liver tests [see Warnings and Precautions (5.3)] Electrocardiogram (ECG), serum potassium and serum magnesium levels [see Warnings and Precautions (5.2)] Patients with poorly controlled diabetes mellitus, who have inadequate glucose control, should have anti-diabetic therapy optimized prior to starting SIGNIFOR LAR [see Warnings and Precautions (5.1)] .
2.2Important Administration Instructions SIGNIFOR LAR must be reconstituted by a trained healthcare professional immediately before use. Illustrations on reconstitution are found in Instructions for Use [see Dosage and Administration (2.6)] . SIGNIFOR LAR must be inspected visually before use.
The suspension should appear free of foreign particulates and should be homogeneous after mixing. SIGNIFOR LAR must be administered by a trained healthcare professional only by intramuscular injection in the right or left gluteus immediately after reconstitution. SIGNIFOR LAR must never be administered intravenously.
2.3Recommended Initial Dose Acromegaly The recommended initial dose of SIGNIFOR LAR for the treatment of acromegaly is 40 mg administered by intramuscular injection once every 4 weeks (every 28 days) [see Dosage and Administration (2.6) ]. Cushing's Disease The recommended initial dose of SIGNIFOR LAR for the treatment of Cushing's disease is 10 mg administered by intramuscular injection once every 4 weeks (every 28 days) [see Dosage and Administration (2.6) ].
2.4Dose Adjustment and Monitoring Acromegaly The dose may be increased to a maximum of 60 mg for patients who have not normalized growth hormone (GH) and/or age and sex adjusted insulin-like growth factor-1 (IGF-1) levels after 3 months of treatment with SIGNIFOR LAR at 40 mg and who tolerate this dose. Management of SIGNIFOR LAR-related adverse reactions or over-response to treatment (age and sex adjusted IGF-1 less than the lower limit of normal) may require dose reduction. The dose may be decreased, either temporarily or permanently, by 20 mg decrements [see Warnings and Precautions (5)] .
Cushing's Disease Following 4 months of treatment with the initial dose of 10 mg once every 28 days, the dose may be increased for patients who have not normalized 24-hour urinary free cortisol (UFC) and who tolerate this dose, up to a maximum dose of 40 mg once every 28 days. Management of suspected adverse reactions or over-response to treatment (e.g., cortisol levels less than the lower limit of the normal range or in the low part of the normal range in patients with symptoms suggestive of adren… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS SIGNIFOR LAR for injectable suspension: 10 mg, 20 mg, 30 mg, 40 mg, or 60 mg of slightly yellow to yellow powder in a vial and 2 mL diluent. SIGNIFOR LAR for injectable suspension: 10 mg, 20 mg, 30 mg, 40 mg, and 60 mg, powder in a vial to be reconstituted with the provided 2 mL diluent. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hyperglycemia, Diabetes, and Ketoacidosis: Sometimes severe. Monitor glucose levels as clinically appropriate during therapy. Monitor glucose levels more frequently in the months that follow initiation or discontinuation of SIGNIFOR LAR therapy and following SIGNIFOR LAR dose adjustment.
Use anti-diabetic treatment if indicated.If ketoacidosis is suspected, discontinue SIGNIFOR LAR and promptly evaluate and treat the patient. ( 2.1 , 5.1 ) Bradycardia and QT Prolongation: Use with caution in at-risk patients; evaluate ECG and electrolytes prior to dosing and periodically while on treatment. ( 2.1 , 5.2 , 7.1 ) Liver Test Elevations: Evaluate liver enzyme tests prior to and during treatment.
( 2.1 , 5.3 ) Cholelithiasis and Complications of Cholelithiasis: Monitor periodically. Discontinue if complications of cholelithiasis are suspected. ( 5.4 ) Pituitary Hormone Deficiency(ies): Monitor for occurrence periodically and treat if clinically indicated.
( 5.5 ) Steatorrhea and Malabsorption of Dietary Fats : New onset steatorrhea, stool discoloration, loose stools, abdominal bloating, and weight loss may occur. If new occurrence or worsening of these symptoms are reported, evaluate for potential pancreatic exocrine insufficiency ( 5.6 )
5.1Hyperglycemia, Diabetes, and Ketoacidosis SIGNIFOR LAR can cause increases in blood glucose levels which are sometimes severe. There have been postmarketing cases of ketoacidosis with SIGNIFOR LAR in patients with history of diabetes and in patients without history of diabetes. In the acromegalic patient study, 5 patients naïve to drug therapy treated with SIGNIFOR LAR (2 of whom were normoglycemic at baseline) and none in the active comparator group were hospitalized for hyperglycemia (blood glucose range 359-506 mg/dL).
Two additional patients who had received active comparator in the main trial and were switched to SIGNIFOR LAR in the extension trial, were hospitalized for elevated glucose levels while on SIGNIFOR LAR; one of those patients developed diabetic ketoacidosis. In the Cushing's disease study, 2 patients were hospitalized for elevated blood glucose. In clinical studies for acromegaly and Cushing's disease, SIGNIFOR LAR caused an increase in the incidence of diabetes and prediabetes.
A majority of patients, including those with normal glucose tolerance, prediabetes and diabetes, experienced increased glucose levels within the first 3 months of treatment [see Adverse Reactions (6.1) ]. In the drug-naïve acromegaly study, the prevalence of diabetes increased from 30% at baseline to 60% at Month 12. In the study evaluating acromegaly patients previously treated with somatostatin analogs, the prevalence of diabetes increased from 71% at baseline to 87% at Month 6 in patients treated with SIGNIFOR LAR 40 mg, and from 60% to 84% in patients treated with SIGNIFOR LAR 60 mg.
In the Cushing's disease study, the prevalence of diabetes increased from 40% at baseline to 56% at Month 12. Patients with poor baseline glycemic control are at higher risk of developing severe hyperglycemia. Assess FPG and HbA1c prior to starting treatment with SIGNIFOR LAR [see Dosage and Administration (2.1)] .
In patients with poorly controlled diabetes mellitus, optimize anti-diabetic treatment before SIGNIFOR LAR initiation. Monitor blood glucose weekly for the first 3 months after initiating SIGNIFOR LAR and the first 4- to 6 weeks after dose increases. Continue monitoring thereafter, as clinically appropriate.
Patients who develop significant hyperglycemia on SIGNIFOR LAR may require initiation of anti-diabetic treatment or adjustment in their current anti-diabetic treatment. The optimal treatment for the management of SIGNIFOR LAR-induced hyperglycemia is not known. If hyperglycemia cannot be controlled despite medical management, reduce the dose of SIGNIFOR LAR or discontinue SIGNIFOR LAR.
Assess FPG and HbA1c after SIGNIFOR LAR discontinuation, if indicated. Patients receiving ant… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Clinically significant adverse reactions that appear in other sections of the labeling include: Hyperglycemia, Diabetes, and Ketoacidosis [see Warnings and Precautions (5.1)] Bradycardia and QT Prolongation [see Warnings and Precautions (5.2)] Liver Test Elevations [see Warnings and Precautions (5.3)] Cholelithiasis and Complications of Cholelithiasis [see Warnings and Precautions (5.4)] Pituitary Hormone Deficiency(ies) [see Warnings and Precautions (5.5)] Steatorrhea and Malabsorption of Dietary Fats [see Warnings and Precautions (5.6) ] Adverse drug reactions associated with SIGNIFOR LAR and occurring in ≥ 20% of patients were diarrhea, cholelithiasis, hyperglycemia, and diabetes mellitus.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Recordati Rare Diseases Inc. at 1-888-575-8344 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in clinical trials of a drug cannot be directly compared to rates in clinical trials of another drug and may not reflect the rates observed in practice. Drug-Naïve Patients With Acromegaly The data described in Table 1 are derived from an active-controlled trial in patients with acromegaly naïve to previous drug therapy [see Clinical Studies (14.1)] . The data reflect exposure of 178 patients with acromegaly to SIGNIFOR LAR for a mean duration of 43 weeks.
In the overall study population, 52% were female and the average age of patients was 45 years. Table 1 presents common adverse reactions associated with SIGNIFOR LAR in this study. These adverse reactions were not present at baseline or, if present, worsened from baseline and occurred in at least 5% of patients treated with SIGNIFOR LAR.
Table 1 – Adverse Reactions Occurring in Greater Than or Equal to 5% of Patients Exposed to SIGNIFOR LAR in Patients With Acromegaly Naïve to Drug Therapy a Diabetes mellitus includes the following PTs: diabetes mellitus and type 2 diabetes mellitus. b Sinus bradycardia includes the following PTs: bradycardia and sinus bradycardia. c Injection-site reaction related AEs includes the following PTs: injection-site pain, injection-site reaction, injection-site haematoma, injection-site pruritus, injection-site swelling, injection-site erythema.
Adverse Reaction Type SIGNIFOR LAR (40-60 mg) % N = 178 Active Comparator % N = 180 Hyperglycemia Related Adverse Reactions Hyperglycemia 29 8 Diabetes mellitus a 26 4 Blood glucose increased 8 2 Glycosylated hemoglobin increased 6 2 Hypoglycemia 5 7 Gastrointestinal Related Adverse Reactions Diarrhea 39 45 Abdominal pain 18 22 Nausea 14 22 Abdominal distension 12 12 Vomiting 8 7 Abdominal pain upper 6 8 Hepatobiliary Related Adverse Reactions Cholelithiasis 26 36 Cardiac Related Adverse Reactions Sinus bradycardia b 10 7 Hypertension 8 7 Nervous System Related Adverse Reactions Headache 19 26 Dizziness 10 11 Skin Related Adverse Reactions Alopecia 18 19 Infections Related Adverse Reactions Nasopharyngitis 16 16 Influenza 8 4 Upper respiratory tract infection 7 3 Cough 5 8 Laboratory Related Adverse Reactions Blood creatine phosphokinase increased 13 12 Alanine aminotransferase increased 8 4 Aspartate aminotransferase increased 6 4 Lipase increased 6 7 Weight decreased 5 4 General and Injection-Site Related Adverse Reactions Fatigue 10 10 Injection-site reaction c 7 7 Musculoskeletal and Connective Tissue Related Adverse Reactions Arthralgia 10 12 Back pain 8 11 Pain in extremity 7 4 Blood Related Adverse Reactions Anemia 6 6 Other notable adverse reactions which occurred with a frequency of 5% or less for SIGNIFOR LAR were: adrenal insufficiency (3%); glucose tolerance impaired (1%); QT-prolongation (4%); blood amylase increased (2%).
Patients With Acromegaly Inadequately Controlled on Other Somatostatin Analogs at Baseline The data described in Table 2 are derived from an active-controlled study in patients with acro… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Drugs that Prolong QT: Use with caution in patients who are at significant risk of developing QTc prolongation. ( 5.2 , 7.1 ) Cyclosporine: Consider additional monitoring. ( 7.2 ) Bromocriptine: Consider bromocriptine dose reduction. ( 7.2 )
7.1Effect of Other Drugs on SIGNIFOR LAR Drugs That Prolong QT Co-administration of drugs that prolong the QT interval with SIGNIFOR LAR may have additive effects on the prolongation of the QT interval. Monitoring effects on the QT interval at 21 days is recommended [see Warnings and Precautions (5.2)] .
7.2Effect of SIGNIFOR LAR on Other Drugs Cyclosporine Concomitant administration of cyclosporine with SIGNIFOR LAR may decrease the relative bioavailability of cyclosporine and, therefore, dose adjustment of cyclosporine to maintain therapeutic levels may be necessary. Bromocriptine Co-administration of SIGNIFOR LAR with bromocriptine may increase the blood levels of bromocriptine. Dose reduction of bromocriptine may be necessary.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Females and Males of Reproductive Potential : Advise premenopausal females of the potential for an unintended pregnancy ( 8.3 )
8.1Pregnancy Risk Summary The limited data with SIGNIFOR LAR in pregnant women are insufficient to inform a drug-associated risk for major birth defects and miscarriage. In embryo-fetal development studies in rabbits, findings indicating a developmental delay were observed with subcutaneous administration of pasireotide during organogenesis at doses less than the exposure in humans at the highest recommended dose; maternal toxicity was not observed at this dose (see Data ) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2%-4% and 15%-20%, respectively. Data Animal Data In embryo-fetal development studies in rats given 1 mg/kg/day, 5 mg/kg/day, and 10 mg/kg/day subcutaneously throughout organogenesis, maternal toxicity was observed at all doses, including the lowest dose tested which had exposures 12 times higher than that at the maximum therapeutic dose based on area under the curve (AUC) comparisons across species.
An increased incidence of early/total resorptions and malrotated limbs was observed in rats at 10 mg/kg/day. At 10 mg/kg/day in rats, the maternal systemic exposure (AUC) was 42179 ng*hr/mL, approximately 106 times the exposure in humans at the highest recommended dose of 60 mg SIGNIFOR LAR administered as an intramuscular injection once every 4 weeks. In embryo-fetal development studies in rabbits given 0.05 mg/kg/day, 1 mg/kg/day, and 5 mg/kg/day subcutaneously through organogenesis, maternal toxicity was observed at 1 mg/kg/day, at a maternal systemic exposure (AUC) of 1906 ng*hr/mL, approximately 5 times higher than the maximum human therapeutic exposure.
An increased incidence of unossified forepaw phalanx, indicative of a developmental retardation, was observed in rabbits at 0.05 mg/kg/day, with maternal systemic exposures less than the systemic exposure in humans at the highest recommended dose. In pre- and post-natal developmental studies in rats given subcutaneous doses of 2 mg/kg/day, 5 mg/kg/day, and 10 mg/kg/day during gestation through lactation and weaning, maternal toxicity was observed at all doses including the lowest dose (9 times higher than the maximum therapeutic dose based on surface area comparisons across species).
Retardation of physiological growth, attributed to GH inhibition was observed at 2 mg/kg/day during a pre- and post-natal study in rats. After weaning, body weight gains in the rat pups (F1 generation) exposed to pasireotide were comparable to controls, showing reversibility of this developmental delay.
8.2Lactation Risk Summary There is no information available on the presence of SIGNIFOR LAR in human milk, the effects of the drug on the breastfed infant, or the effects of the drug on milk production. Studies show that pasireotide administered subcutaneously passes into the milk of lactating rats; however, due to species-specific differences in lactation physiology, animal data may not reliably predict drug levels in human milk (see Data). The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for SIGNIFOR LAR, and any potential adverse effects on the breastfed child from SIGNIFOR LAR or from the underlying maternal condition.
Data Available data in animals have shown excretion of pasireotide in milk. After a single 1 mg/kg [ 14 C]-pasireotide subcutaneous dose to lactating rats, the transfer of radioactivity into milk was observed. The overall milk:plasma (M/P) exposure ratio of total radioactivity was 0.28, based on AUC 0-∞ values.
8.3Females and Males of Reproductive Potential Discuss the potential for unintended pregnancy with premenopausal women as the thera… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary The limited data with SIGNIFOR LAR in pregnant women are insufficient to inform a drug-associated risk for major birth defects and miscarriage. In embryo-fetal development studies in rabbits, findings indicating a developmental delay were observed with subcutaneous administration of pasireotide during organogenesis at doses less than the exposure in humans at the highest recommended dose; maternal toxicity was not observed at this dose (see Data ) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2%-4% and 15%-20%, respectively. Data Animal Data In embryo-fetal development studies in rats given 1 mg/kg/day, 5 mg/kg/day, and 10 mg/kg/day subcutaneously throughout organogenesis, maternal toxicity was observed at all doses, including the lowest dose tested which had exposures 12 times higher than that at the maximum therapeutic dose based on area under the curve (AUC) comparisons across species.
An increased incidence of early/total resorptions and malrotated limbs was observed in rats at 10 mg/kg/day. At 10 mg/kg/day in rats, the maternal systemic exposure (AUC) was 42179 ng*hr/mL, approximately 106 times the exposure in humans at the highest recommended dose of 60 mg SIGNIFOR LAR administered as an intramuscular injection once every 4 weeks. In embryo-fetal development studies in rabbits given 0.05 mg/kg/day, 1 mg/kg/day, and 5 mg/kg/day subcutaneously through organogenesis, maternal toxicity was observed at 1 mg/kg/day, at a maternal systemic exposure (AUC) of 1906 ng*hr/mL, approximately 5 times higher than the maximum human therapeutic exposure.
An increased incidence of unossified forepaw phalanx, indicative of a developmental retardation, was observed in rabbits at 0.05 mg/kg/day, with maternal systemic exposures less than the systemic exposure in humans at the highest recommended dose. In pre- and post-natal developmental studies in rats given subcutaneous doses of 2 mg/kg/day, 5 mg/kg/day, and 10 mg/kg/day during gestation through lactation and weaning, maternal toxicity was observed at all doses including the lowest dose (9 times higher than the maximum therapeutic dose based on surface area comparisons across species).
Retardation of physiological growth, attributed to GH inhibition was observed at 2 mg/kg/day during a pre- and post-natal study in rats. After weaning, body weight gains in the rat pups (F1 generation) exposed to pasireotide were comparable to controls, showing reversibility of this developmental delay.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of SIGNIFOR LAR have not been established in pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of SIGNIFOR LAR did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE In the event of overdosage, it is recommended that appropriate supportive treatment be initiated, as dictated by the patient's clinical status, until resolution of the symptoms. Up-to-date information about the treatment of overdose can be obtained from a certified Regional Poison Center. In the event of an overdose, contact the National Capital Poison Center at 1-800-222-1222 or www.poison.org.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action SIGNIFOR LAR is an injectable cyclohexapeptide, somatostatin analog. Pasireotide exerts its pharmacological activity via binding to somatostatin receptors (SSTR). There are 5 known human somatostatin receptor subtypes: SSTR 1, 2, 3, 4, and 5.
These receptor subtypes are expressed in different tissues under normal physiological conditions. Somatostatin analogs bind to SSTRs with different potencies. Pasireotide binds with high affinity to 4 of the 5 SSTRs (see Table 4).
Table 4 – Binding Affinities of Somatostatin (SRIF-14) and Pasireotide to the Five Human SSTR Subtypes (SSTR 1-5) Results are the mean + SEM of IC 50 values expressed as nmol/l (nM). Compound SSTR1 SSTR2 SSTR3 SSTR4 SSTR5 Somatostatin (SRIF-14) 0.93 ± 0.12 0.15 ± 0.02 0.56 ± 0.17 1.5 ± 0.4 0.29 ±
0.04Pasireotide 9.3 ± 0.1 1.0 ± 0.1 1.5 ± 0.3 > 100 0.16 ± 0.01
12.2Pharmacodynamics Somatostatin receptors are expressed in many tissues including neuroendocrine tumors (e.g., growth hormone or adrenocorticotropic hormone secreting pituitary adenomas). Acromegaly Pasireotide binds to SSTR2 and SSTR5 subtype receptors which may be relevant for inhibition of GH secretion. In vivo studies show that SIGNIFOR LAR lowers GH and IGF-1 levels in patients with acromegaly.
Cushing's Disease Corticotroph tumor cells from Cushing's disease patients frequently over-express SSTR5 whereas the other receptor subtypes are often not expressed or are expressed at lower levels. Pasireotide binds and activates the SSTRs resulting in inhibition of ACTH secretion, which leads to decreased cortisol secretion. Cardiac Electrophysiology Individually corrected QT (QTcI) interval was evaluated in a randomized, blinded, crossover study in healthy subjects investigating pasireotide subcutaneous doses of 0.6 mg and 1.95 mg twice daily, respectively.
The maximum mean (95% upper confidence bound) placebo-subtracted QTcI change from baseline was 12.7 (14.7) ms and 16.6 (18.6) ms, respectively. Both pasireotide doses decreased heart rate, with a maximum mean (95% lower confidence bound) placebo-subtracted change from baseline of -10.9 (-11.9) beats per minute (bpm) observed at 1.5 hours for pasireotide 0.6 mg twice daily, and -15.2 (-16.5) bpm at 0.5 hours for pasireotide 1.95 mg twice daily. The predicted pasireotide peak concentration (25.8 ng/mL) following SIGNIFOR LAR 60-mg dose in acromegaly patients is similar to the observed peak concentration (24.3 mg/mL) of the subcutaneous SIGNIFOR 0.6 mg twice daily dose and below the observed peak concentration (80.6 ng/mL) of the subcutaneous SIGNIFOR 1.95 mg twice daily dose.
The predicted pasireotide peak concentration for the SIGNIFOR LAR dose of 40 mg in Cushing's disease patients is 14 ng/mL.
12.3Pharmacokinetics Pasireotide for intramuscular use is formulated as microspheres for long-acting release. After a single injection, the plasma pasireotide concentration shows an initial burst release on the injection day, followed by a dip from Day 2 to Day 7, then a slow increase to the maximum concentration around Day 21, and a slow declining phase over the next weeks, concomitant with the terminal degradation phase of the polymer matrix of the dosage form. Absorption and Distribution No studies have been conducted to evaluate the absolute bioavailability of pasireotide in humans.
Food effect is unlikely to occur since SIGNIFOR LAR is administered via a parenteral route. In healthy volunteers, pasireotide administered as SIGNIFOR LAR is widely distributed with large apparent volume of distribution (V z /F > 100 L). Distribution between blood and plasma is concentration-independent and shows that pasireotide is primarily located in the plasma (91%).
Plasma protein binding is moderate (88%) and independent of concentration. Pasireotide has low passive permeability and is likely to be a substrate of P-glycoprotein (P-gp), but the impact of P-gp on the ADME (absorption, distribution, metabolism, excretion) of… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action SIGNIFOR LAR is an injectable cyclohexapeptide, somatostatin analog. Pasireotide exerts its pharmacological activity via binding to somatostatin receptors (SSTR). There are 5 known human somatostatin receptor subtypes: SSTR 1, 2, 3, 4, and 5.
These receptor subtypes are expressed in different tissues under normal physiological conditions. Somatostatin analogs bind to SSTRs with different potencies. Pasireotide binds with high affinity to 4 of the 5 SSTRs (see Table 4).
Table 4 – Binding Affinities of Somatostatin (SRIF-14) and Pasireotide to the Five Human SSTR Subtypes (SSTR 1-5) Results are the mean + SEM of IC 50 values expressed as nmol/l (nM). Compound SSTR1 SSTR2 SSTR3 SSTR4 SSTR5 Somatostatin (SRIF-14) 0.93 ± 0.12 0.15 ± 0.02 0.56 ± 0.17 1.5 ± 0.4 0.29 ±
0.04Pasireotide 9.3 ± 0.1 1.0 ± 0.1 1.5 ± 0.3 > 100 0.16 ± 0.01
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied SIGNIFOR LAR for injectable suspension is supplied in a single-use kit containing the following: One 6-mL brownish glass vial with a grey rubber stopper of SIGNIFOR LAR containing slightly yellow to yellow powder with a flip-off cap One 3-mL glass barrel/grey rubber stopper prefilled syringe containing 2 mL of clear, colorless to slightly yellow/brown diluent solution for reconstitution One sterile 20G x 1.5" stainless steel, polypropylene safety injection needle One vial adapter made of polycarbonate for drug product reconstitution SIGNIFOR LAR kits are available in the following strengths: SIGNIFOR LAR Kit Final Concentration When Reconstituted (total product strength per total volume) Final Concentration When Reconstituted (per mL) Flip-off Cap Color NDC 10 mg 10 mg/2 mL 5 mg/mL Brown 55292-139-01 20 mg 20 mg/2 mL 10 mg/mL Gray 55292-140-01 30 mg 30 mg/2 mL 15 mg/mL Lilac 55292-141-01 40 mg 40 mg/2 mL 20 mg/mL Red 55292-142-01 60 mg 60 mg/2 mL 30 mg/mL Orange 55292-143-01
16.2Storage and Handling Store at 2°C to 8°C (36°F-46°F). Do not freeze. SIGNIFOR LAR should be stored at refrigerated temperatures between 2°C to 8°C (36°F-46°F) until the time of use. SIGNIFOR LAR drug product kit should remain at room temperature for a minimum of 30 minutes before reconstitution, but should not exceed 24 hours at room temperature. However, after preparation of the drug suspension, it must be administered immediately.
📋 Description ▾
11 DESCRIPTION SIGNIFOR LAR (pasireotide) for injectable suspension is a long-acting release form of pasireotide pamoate, as powder to be suspended in the provided diluent immediately prior to intramuscular injection. SIGNIFOR LAR contains pasireotide, a somatostatin analog in the form of pasireotide pamoate (pamoic acid salt). Pasireotide is a cyclohexapeptide with pharmacologic properties mimicking those of the natural hormone somatostatin.
Pasireotide pamoate has a chemical name of (2-Aminoethyl) carbamic acid (2R,5S,8S,11S,14R,17S,19aS)-11-(4-aminobutyl)-5-benzyl-8-(4-benzyloxybenzyl)-14-(1H-indol-3-ylmethyl)-4,7,10,13,16,19-hexaoxo-17-phenyloctadecahydro-3a,6,9,12,15,18-hexaazacyclopentacyclooctadecen-2-yl ester pamoic acid salt. The molecular formula of pasireotide pamoate is C 58 H 66 N 10 O 9 • C 23 H 16 O 6 and the molecular weight is 1435.58 g/mol. The structural formula is: The drug product consists of pasireotide pamoate uniformly distributed within microspheres which are made of biodegradable copolymers of poly (D,L-lactide-co-glycolide) acids (PLGA).
SIGNIFOR LAR is available in a vial containing the sterile pasireotide pamoate, PLGA microspheres powder, 10 mg, 20 mg, 30 mg, 40 mg, and 60 mg to be reconstituted with the provided 2 mL sterile diluent. Each vial contains: *corresponds to 10 mg, 20 mg, 30 mg, 40 mg, and 60 mg of pasireotide base, respectively. 10 mg 20 mg 30 mg 40 mg 60 mg Pasireotide pamoate 13.71 mg* 27.42 mg* 41.13 mg* 54.84 mg* 82.26 mg* Poly(D,L-lactide-co-glycolide) [50-60:40-50] 13.15 mg 26.29 mg 39.44 mg 52.58 mg 78.87 mg Poly(D,L-lactide-co-glycolide) [50:50] 13.15 mg 26.29 mg 39.44 mg 52.58 mg 78.87 mg Each diluent prefilled syringe contains: Mannitol 90 mg Carboxymethylcellulose sodium 14 mg Poloxamer 188 4 mg Water for injections add to 2 mL structural formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Instruct patients on the importance of adhering to their return visit schedule. Advise patients that SIGNIFOR LAR should only be administered by a trained healthcare professional.
Hyperglycemia, Diabetes, and Ketoacidosis Advise patients to assess FPG and HbA1c prior to starting treatment with SIGNIFOR LAR and advise patients to consistently monitor blood glucose levels, particularly after the start of treatment or after dose changes, so that appropriate action can be taken. Advise patients to contact their healthcare provider if they experience signs or symptoms of diabetes or ketoacidosis [see Warnings and Precautions (5.1) ]. Bradycardia and QT Prolongation Advise patients that an ECG will be taken before treatment and periodically thereafter.
Advise patients with cardiac disease and with risk factors for QT prolongation and bradycardia that adjustments in cardiac medications may be made and electrolyte disturbances may require correction [see Warnings and Precautions (5.2)] . Liver Test Elevations Advise patients that liver function will be assessed prior to starting treatment with SIGNIFOR LAR and will be closely monitored for the first three months of treatment and thereafter as clinically indicated [see Warnings and Precautions (5.3) ]. Cholelithiasis and Complications of Cholelithiasis Inform patients that cholelithiasis and complications of cholelithiasis have been reported with the use of SIGNIFOR LAR [ see Warnings and Precautions (5.4) ].
Advise patients to contact their healthcare provider if they experience signs or symptoms of gallstones (cholelithiasis) or complications of cholelithiasis (e.g., cholecystitis or cholangitis) [ see Warnings and Precautions (5.4) ]. Advise patients that the gallbladder will be monitored by ultrasound periodically [see Warnings and Precautions (5.4)] . Pituitary Hormone Deficiency(ies) Advise patients that monitoring of anterior pituitary function will be performed periodically [see Warnings and Precautions (5.5)] .
Steatorrhea and Malabsorption of Dietary Fats Advise patients to contact their healthcare provider if they experience new or worsening symptoms of steatorrhea, stool discoloration, loose stools, abdominal bloating, and weight loss [see Warnings and Precautions (5.6) ]. Manufactured for: Recordati Rare Diseases Inc., Bridgewater, NJ 08807 U.S.A
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Pasireotide for intramuscular use is formulated as microspheres for long-acting release. After a single injection, the plasma pasireotide concentration shows an initial burst release on the injection day, followed by a dip from Day 2 to Day 7, then a slow increase to the maximum concentration around Day 21, and a slow declining phase over the next weeks, concomitant with the terminal degradation phase of the polymer matrix of the dosage form. Absorption and Distribution No studies have been conducted to evaluate the absolute bioavailability of pasireotide in humans.
Food effect is unlikely to occur since SIGNIFOR LAR is administered via a parenteral route. In healthy volunteers, pasireotide administered as SIGNIFOR LAR is widely distributed with large apparent volume of distribution (V z /F > 100 L). Distribution between blood and plasma is concentration-independent and shows that pasireotide is primarily located in the plasma (91%).
Plasma protein binding is moderate (88%) and independent of concentration. Pasireotide has low passive permeability and is likely to be a substrate of P-glycoprotein (P-gp), but the impact of P-gp on the ADME (absorption, distribution, metabolism, excretion) of pasireotide is expected to be low. In clinical testing in healthy volunteers, P-gp inhibition did not affect the rate or extent of pasireotide availability [see Drug Interactions (7.1)] .
At therapeutic dose levels, pasireotide is not expected to be a substrate of BCRP (breast cancer resistance protein), OCT1 (organic cation transporter 1), or OATP (organic anion-transporting polypeptides) 1B1, 1B3, or 2B1. Elimination Metabolism and Excretion Pasireotide was shown to be highly metabolically stable in human liver and kidney microsomes. In healthy volunteers, pasireotide in its unchanged form is the predominant form found in plasma, urine and feces.
Somatropin may increase CYP450 enzymes and, therefore, suppression of GH secretion by somatostatin analogs including pasireotide may decrease the metabolic clearance of compounds metabolized by CYP450 enzymes. Pasireotide is eliminated mainly via hepatic clearance (biliary excretion) with a small contribution of the renal route. In a human ADME study with subcutaneous SIGNIFOR with a single dose 0.6 mg, 55.9 ± 6.63% of the radioactivity dose was recovered over the first 10 days post dosing, including 48.3 ± 8.16% of the radioactivity in feces and 7.63 ± 2.03% in urine.
The apparent clearance (CL/F) of SIGNIFOR LAR in healthy volunteers is on average 4.5-8.5 L/hour. Steady-State Pharmacokinetics PK steady-state for SIGNIFOR LAR is achieved after 3 monthly doses. Following multiple intramuscular doses every 4 weeks (every 28 days), SIGNIFOR LAR demonstrates approximately dose-proportional PK exposures (steady-state trough; Ctrough, ss) in the dose range of 10 mg to 60 mg every 4 weeks.
Special Populations Population PK analyses of SIGNIFOR LAR suggest that race, gender, and body weight do not have clinically relevant influence on circulating levels of pasireotide. No dose adjustment is required for demographics. Pediatric Patients No studies have been performed in pediatric patients [see Use in Specific Populations (8.4)] .
Geriatric Patients Age is not a significant covariate in the population PK analysis. Therefore age is not expected to significantly impact circulating levels of pasireotide. Efficacy and safety data on patients older than 65 years are limited [see Use in Specific Populations (8.5)] .
Hepatic Impairment In a clinical study with a single subcutaneous dose of 600 µg pasireotide in subjects with impaired hepatic function (Child-Pugh A, B, and C), subjects with moderate and severe hepatic impairment (Child-Pugh B and C) showed significantly higher exposures than subjects with normal hepatic function. Upon comparing with the control group, AUC inf was increased by 12%, 56%, and 42%; and C max was increased by 3%, 46%, and 33% respectively, in the mild, moderate,… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Somatostatin receptors are expressed in many tissues including neuroendocrine tumors (e.g., growth hormone or adrenocorticotropic hormone secreting pituitary adenomas). Acromegaly Pasireotide binds to SSTR2 and SSTR5 subtype receptors which may be relevant for inhibition of GH secretion. In vivo studies show that SIGNIFOR LAR lowers GH and IGF-1 levels in patients with acromegaly.
Cushing's Disease Corticotroph tumor cells from Cushing's disease patients frequently over-express SSTR5 whereas the other receptor subtypes are often not expressed or are expressed at lower levels. Pasireotide binds and activates the SSTRs resulting in inhibition of ACTH secretion, which leads to decreased cortisol secretion. Cardiac Electrophysiology Individually corrected QT (QTcI) interval was evaluated in a randomized, blinded, crossover study in healthy subjects investigating pasireotide subcutaneous doses of 0.6 mg and 1.95 mg twice daily, respectively.
The maximum mean (95% upper confidence bound) placebo-subtracted QTcI change from baseline was 12.7 (14.7) ms and 16.6 (18.6) ms, respectively. Both pasireotide doses decreased heart rate, with a maximum mean (95% lower confidence bound) placebo-subtracted change from baseline of -10.9 (-11.9) beats per minute (bpm) observed at 1.5 hours for pasireotide 0.6 mg twice daily, and -15.2 (-16.5) bpm at 0.5 hours for pasireotide 1.95 mg twice daily. The predicted pasireotide peak concentration (25.8 ng/mL) following SIGNIFOR LAR 60-mg dose in acromegaly patients is similar to the observed peak concentration (24.3 mg/mL) of the subcutaneous SIGNIFOR 0.6 mg twice daily dose and below the observed peak concentration (80.6 ng/mL) of the subcutaneous SIGNIFOR 1.95 mg twice daily dose.
The predicted pasireotide peak concentration for the SIGNIFOR LAR dose of 40 mg in Cushing's disease patients is 14 ng/mL.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Drug-Naïve Patients with Acromegaly A multicenter, randomized, double-blind study was conducted to assess the safety and efficacy of SIGNIFOR LAR in patients with active acromegaly. A total of 358 patients naïve to drugs used to treat acromegaly were randomized in a 1:1 ratio to SIGNIFOR LAR or another somatostatin analog active comparator. Randomization was stratified based on previous pituitary surgical status (e.g., at least 1 prior pituitary surgery versus no prior pituitary surgery).
In the overall study population, 52% were female and the average age of patients was 45 years. Sixty percent of patients were Caucasian, 23% Asian, 12% Other, 3% American Indian, and 2% were Black. Forty-two percent of patients had previous pituitary surgery, and 1 patient had a history of pituitary radiation therapy.
Median time between diagnosis and trial participation was 6 months. Median GH was 8.8 mcg/L (range: 0.8-200 mcg/L) and 10.1 mcg/L (range: 0.6-169.6 mcg/L) for SIGNIFOR LAR and active comparator, respectively at baseline. Median standardized IGF-1, defined as IGF-1 value divided by the ULN (i.e., fold above the ULN), was 2.9 (range: 0.9-6.9) and 2.9 (range: 0.8-7.3), for SIGNIFOR LAR and active comparator, respectively, at baseline.
The starting dose of SIGNIFOR LAR was 40 mg. Dose increase was allowed in both arms, at the discretion of investigators, after 3 and 6 months of treatment if mean GH was greater than or equal to 2.5 mcg/L and/or IGF-1 was greater than the ULN for age and sex. The maximum allowed dose for SIGNIFOR LAR was 60 mg.
The maximum dose of the active comparator was not used in this trial because the trial was multi-national and the maximum dose approved in the US was not approved in all participating countries. The efficacy endpoint was the proportion of patients with a mean GH level less than 2.5 mcg/L and a normal IGF-1 levels at month 12 (age- and sex-adjusted) (see Table 5, Figure 3, and Figure 4). The proportion of patients achieving this level of control was 31.3% and 19.2% for SIGNIFOR LAR and active comparator, respectively.
The changes in mean GH and IGF-1 levels by study visits in subjects with a measurement at these visits (observed cases) are shown in Figures 3 and 4. Table 5 – Results at Month 12 in Drug-Naïve Patients Study SIGNIFOR LAR (40-60 mg) % N = 176 Active Comparator c % N = 182 GH < 2.5 mcg/L and normalized IGF-1 a 31.3% b 19.2% GH < 2.5 mcg/L and IGF-1 ≤ ULN 35.8% 20.9% Normalized IGF-1 38.6% b 23.6% GH < 2.5 mcg/L 48.3% 51.6% a Primary endpoint [patients with IGF-1< lower limit of normal (LLN) were not considered as "responders"].
ULN = Upper limit of normal. b p-value < 0.01 for treatment difference. c The maximum dose approved for use in the United States was not used in this trial but the majority of patients were receiving the dose most commonly used in the United States to treat acromegaly. Figure 3. Mean GH (mcg/L) Levels By Visit in Drug Naïve Patient Study Numbers of patients with a GH value at the given timepoint for SIGNIFOR LAR/Active comparator arm are displayed as xxx/xxx on the x-axis.
Figure 4. Mean Standardized IGF-1 Levels Fold above the upper limit of normal for the assay By Visit in Drug Naïve Patient Study Numbers of patients with an IGF-1 value at the given timepoint for SIGNIFOR LAR/Active comparator arm are displayed as xxx/xxx on the x axis. Biochemical control was achieved by Month 3 in 30.1% of patients in the SIGNIFOR LAR arm.
Ninety-eight percent of patients treated with SIGNIFOR LAR had either a reduction or no change in tumor volume from baseline assessed by MRI at Month 12. The median (range) change in tumor volume was a reduction of 39.8% (-97.6% to 16.9%). Additionally, ring size and acromegaly symptoms score (i.e., headache, fatigue, perspiration, paresthesia, and osteoarthralgia) were followed.
At Month 12, reductions in ring size and in symptom severity scores in both treatment groups compared to baseline were noted. Figure 3… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis A lifetime carcinogenicity study was conducted in rats and transgenic mice. Rats were given daily subcutaneous doses of pasireotide at 0.01 mg/kg/day, 0.05 mg/kg/day, and 0.3 mg/kg/day for 104 weeks. There were no drug-related tumors in rats at exposures up to 5-times higher than the maximum recommended clinical exposure of the pasireotide LAR 60 mg dose.
Mice were given subcutaneous doses of pasireotide at 0.5 mg/kg/day, 1 mg/kg/day, and 2.5 mg/kg/day for 26 weeks and did not identify any carcinogenic potential. Mutagenesis Pasireotide was not genotoxic in a battery of in vitro assays (Ames mutation test in Salmonella and Escherichia coli and mutation test in human peripheral lymphocytes). Pasireotide was not genotoxic in an in vivo rat bone marrow nucleus test.
Impairment of Fertility Subcutaneous dosing at 0.1 mg/kg/day before mating and continuing into gestation in rats at exposures less than the human clinical exposure based on body surface area comparisons across species resulted in statistically significant increased implantation loss and decreased viable fetuses, corpora lutea, and implantation sites. Abnormal cycles or acyclicity were observed at 1 mg/kg/day (4-fold higher than the maximum therapeutic exposure of pasireotide LAR based on surface area, comparisons across species).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis A lifetime carcinogenicity study was conducted in rats and transgenic mice. Rats were given daily subcutaneous doses of pasireotide at 0.01 mg/kg/day, 0.05 mg/kg/day, and 0.3 mg/kg/day for 104 weeks. There were no drug-related tumors in rats at exposures up to 5-times higher than the maximum recommended clinical exposure of the pasireotide LAR 60 mg dose.
Mice were given subcutaneous doses of pasireotide at 0.5 mg/kg/day, 1 mg/kg/day, and 2.5 mg/kg/day for 26 weeks and did not identify any carcinogenic potential. Mutagenesis Pasireotide was not genotoxic in a battery of in vitro assays (Ames mutation test in Salmonella and Escherichia coli and mutation test in human peripheral lymphocytes). Pasireotide was not genotoxic in an in vivo rat bone marrow nucleus test.
Impairment of Fertility Subcutaneous dosing at 0.1 mg/kg/day before mating and continuing into gestation in rats at exposures less than the human clinical exposure based on body surface area comparisons across species resulted in statistically significant increased implantation loss and decreased viable fetuses, corpora lutea, and implantation sites. Abnormal cycles or acyclicity were observed at 1 mg/kg/day (4-fold higher than the maximum therapeutic exposure of pasireotide LAR based on surface area, comparisons across species).
📄 Patient Package Insert ▾
This Patient Information has been approved by the U.S. Food and Drug Administration. Revised: 7/2024 Patient Information SIGNIFOR ® LAR (sig-na-for L.A.R.) (pasireotide) for injectable suspension, for intramuscular use Read this Patient Information before you start receiving SIGNIFOR LAR, and each time you receive it.
There may be new information. This leaflet does not take the place of talking to your healthcare provider about your medical condition or your treatment. What is SIGNIFOR LAR?
SIGNIFOR LAR is a prescription medicine used to treat people with: acromegaly for whom surgery has not worked well enough or who cannot have surgery. Cushing's disease for whom surgery has not worked well enough or who cannot have surgery. It is not known if SIGNIFOR LAR is safe and effective for use in children.
What should I tell my healthcare provider before receiving SIGNIFOR LAR? Before you receive SIGNIFOR LAR, tell your healthcare provider about all of your medical conditions, including if you: have high blood sugar (hyperglycemia). have diabetes. have or have had heart problems, including an abnormal heart rate or rhythm or problems with the electrical system of your heart (QT prolongation). have a low level of potassium or magnesium in your blood. have liver problems. have gallstones (cholelithiasis). are pregnant or plan to become pregnant.
It is not known if SIGNIFOR LAR will harm your unborn baby. are breastfeeding or plan to breastfeed. It is not known if SIGINFOR LAR passes into your breast milk. Talk to your healthcare provider about the best way to feed your baby if you take SIGNIFOR LAR.
Treatment with SIGNIFOR LAR may result in improved fertility and the possibility of unplanned pregnancy in females who have acromegaly or Cushing's disease and have not gone through menopause. Talk to your healthcare provider about birth control methods that may be right for you during treatment with SIGNIFOR LAR. Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements.
SIGNIFOR LAR and other medicines may affect each other, causing side effects. SIGNIFOR LAR may affect the way other medicines work, and other medicines may affect how SIGNIFOR LAR works. Your healthcare provider may need to change your dose of SIGNIFOR LAR or your other medicines.
Especially tell your healthcare provider if you take: medicines to control your heart beat (antiarrhythmics) medicines to control your blood pressure (such as beta-blockers or calcium channel blockers) medicines to control the potassium and magnesium (electrolytes) levels in your body medicines that may affect the way the electrical system of your heart works (QT prolongation) cyclosporine bromocriptine Ask your healthcare provider for a list of these medicines if you are not sure. Know the medicines you take. Keep a list of them to show to your healthcare provider and pharmacist when you get a new medicine.
How will I receive SIGNIFOR LAR? SIGNIFOR LAR must be given by a trained healthcare provider as an injection into the muscle of your buttocks (intramuscularly). Your healthcare provider will tell you how much SIGNIFOR LAR you will receive and when you will receive it.
Your healthcare provider may change your dose of SIGNIFOR LAR or the length of time between your injections. Your healthcare provider will tell you how long you need to receive SIGNIFOR LAR. Before you receive SIGNIFOR LAR for the first time, your healthcare provider should do a blood test to check your fasting blood sugar level, hemoglobin A1c level, electrolyte levels, and your liver function.
You will need to check your blood sugar levels during treatment with SIGNIFOR LAR, especially after you start treatment with SIGNIFOR LAR and after your dose is increased. Your healthcare provider will tell you how often you should check your blood sugar levels. Before you receive SIGNIFOR LAR for the first time and during your treatment, your h… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Warnings and Precautions, Steatorrhea and Malabsorption of Dietary Fats ( 5.6 ) 7/2024
📄 Package Label / Principal Display Panel ▾
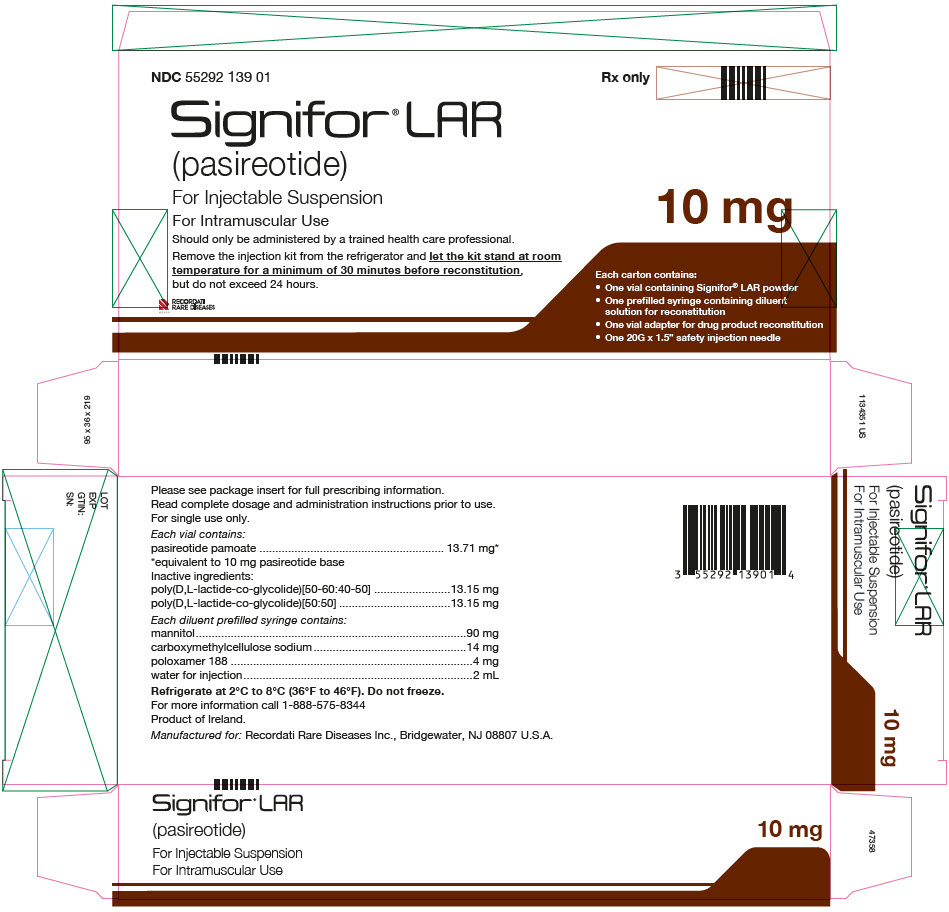
PRINCIPAL DISPLAY PANEL - Kit Carton - NDC 55292 139 01 NDC 55292 139 01 Signifor ® LAR (pasireotide) For Injectable Suspension For Intramuscular Use Should only be administered by a trained health care professional. Remove the injection kit from the refrigerator and let the kit stand at room temperature for a minimum of 30 minutes before reconstitution, but do not exceed 24 hours. RECORDATI RARE DISEASES GROUP Rx only 10 mg Each carton contains: One vial containing Signifor ® LAR powder One prefilled syringe containing diluent solution for reconstitution One vial adapter for drug product reconstitution One 20G x 1.5" safety injection needle PRINCIPAL DISPLAY PANEL - Kit Carton - NDC 55292 139 01
PRINCIPAL DISPLAY PANEL - Kit Carton - NDC 55292 140 01 NDC 55292 140 01 Signifor ® LAR (pasireotide) For Injectable Suspension For Intramuscular Use Should only be administered by a trained health care professional. Remove the injection kit from the refrigerator and let the kit stand at room temperature for a minimum of 30 minutes before reconstitution, but do not exceed 24 hours. RECORDATI RARE DISEASES GROUP Rx only 20 mg Each carton contains: One vial containing Signifor ® LAR powder One prefilled syringe containing diluent solution for reconstitution One vial adapter for drug product reconstitution One 20G x 1.5" safety injection needle PRINCIPAL DISPLAY PANEL - Kit Carton - NDC 55292 140 01
PRINCIPAL DISPLAY PANEL - Kit Carton - NDC 55292 141 01 NDC 55292 141 01 Signifor ® LAR (pasireotide) For Injectable Suspension For Intramuscular Use Should only be administered by a trained health care professional. Remove the injection kit from the refrigerator and let the kit stand at room temperature for a minimum of 30 minutes before reconstitution, but do not exceed 24 hours. RECORDATI RARE DISEASES GROUP Rx only 30 mg Each carton contains: One vial containing Signifor ® LAR powder One prefilled syringe containing diluent solution for reconstitution One vial adapter for drug product reconstitution One 20G x 1.5" safety injection needle PRINCIPAL DISPLAY PANEL - Kit Carton - NDC 55292 141 01
PRINCIPAL DISPLAY PANEL - Kit Carton - NDC 55292 142 01 NDC 55292 142 01 Signifor ® LAR (pasireotide) For Injectable Suspension For Intramuscular Use Should only be administered by a trained health care professional. Remove the injection kit from the refrigerator and let the kit stand at room temperature for a minimum of 30 minutes before reconstitution, but do not exceed 24 hours. RECORDATI RARE DISEASES GROUP Rx only 40 mg Each carton contains: One vial containing Signifor ® LAR powder One prefilled syringe containing diluent solution for reconstitution One vial adapter for drug product reconstitution One 20G x 1.5" safety injection needle PRINCIPAL DISPLAY PANEL - Kit Carton - NDC 55292 142 01
PRINCIPAL DISPLAY PANEL - Kit Carton - NDC 55292 143 01 NDC 55292 143 01 Signifor ® LAR (pasireotide) For Injectable Suspension For Intramuscular Use Should only be administered by a trained health care professional. Remove the injection kit from the refrigerator and let the kit stand at room temperature for a minimum of 30 minutes before reconstitution, but do not exceed 24 hours. RECORDATI RARE DISEASES GROUP Rx only 60 mg Each carton contains: One vial containing Signifor ® LAR powder One prefilled syringe containing diluent solution for reconstitution One vial adapter for drug product reconstitution One 20G x 1.5" safety injection needle PRINCIPAL DISPLAY PANEL - Kit Carton - NDC 55292 143 01
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |