
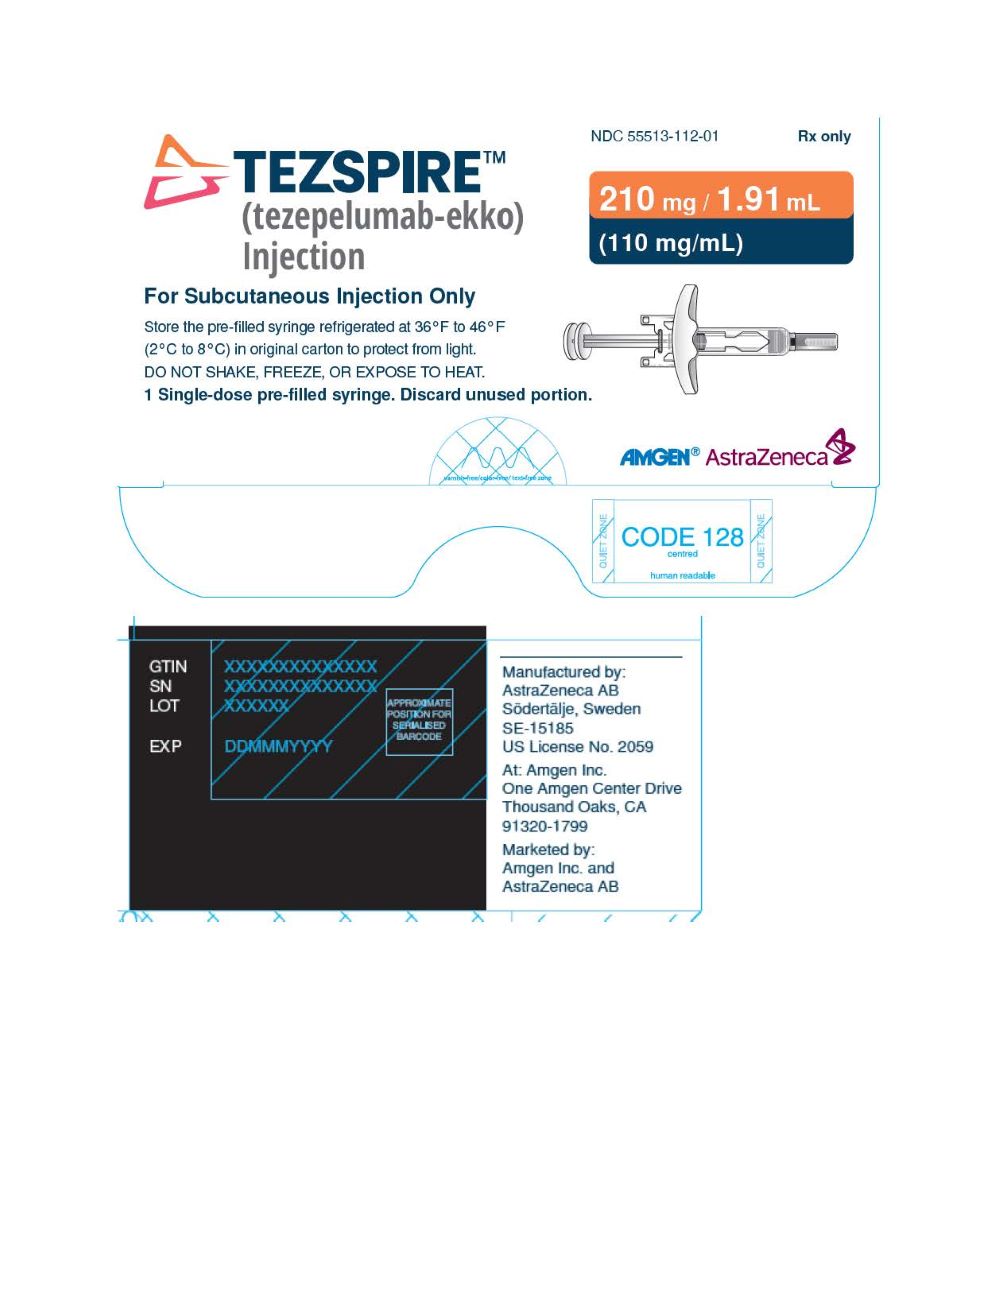
TEZSPIRE tezepelumab-ekko 210 mg/1.9mL Injection, Solution, 1 syringe
🆔 Identity & classification
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Tezepelumab injection is used to prevent wheezing, difficulty breathing, chest tightness, and coughing caused by asthma. It is also used to treat chronic rhinosinusitis with nasal polyps (an ongoing sinus condition). Tezepelumab injection is in a class of medications called monoclonal antibodies. It works by reducing a certain type of white blood cell to help decrease swelling and irritation of the airways to allow for easier breathing.
Read the full MedlinePlus article ↗- No — tezepelumab is not a rescue medication. It works in the background to prevent flares over time, not to open your airways in a crisis. If you're having an acute asthma attack,...
- Can I use tezepelumab when I'm having an asthma attack?
- Measurable reductions in inflammation markers start appearing within about 2 weeks of your first injection. That said, the full benefit — like fewer asthma attacks or improved nasa...
- Not on your own — especially if you're on any steroid medications. Stopping steroids suddenly can cause serious withdrawal effects or allow other health issues to surface. If your...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Tezepelumab-ekko — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII Q40Q9N063P
Acetic acid is a weak organic acid commonly used in medicines as a buffer and pH adjuster. It helps maintain the proper acidity level to ensure the drug remains stable and effective in its formulation.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII 9DLQ4CIU6V
Proline is an amino acid used in pharmaceutical formulations as a bulking agent and stabilizer. It helps maintain product stability and can improve the texture or consistency of medicines, particularly in powders and freeze-dried products.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $1,975.05 | $3,772.35 / 1.91 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J2356 | $17.920 / J2356 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Tezspire 210 mg/1.9mLthis 55513-0112-01 | Amgen | 1 syringe | — | — | FDA listed | — |
| Tezspire 210 mg/1.9mL 55513-0123-01 | Amgen | 1 cartridge | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Why the date isn’t exact: Biosimilar timing can change because patents may be challenged, settled, licensed, added or removed, and litigation can move the real date earlier or later.
🛈 What do these terms mean?
- Biologic patent
- A patent the reference product’s maker has publicly listed. A biosimilar generally can’t launch until these expire — unless they’re invalidated or resolved in a settlement.
- Reference-product exclusivity
- A flat 12 years of FDA market protection from the biologic’s first licensure (the BPCIA). No biosimilar can be licensed before it ends, regardless of patents.
- Interchangeable exclusivity
- The first interchangeable biosimilar can earn a period as the only interchangeable version (pharmacists can substitute it without the prescriber).
- Earliest biosimilar (LOE)
- The latest of all the dates above — the soonest a biosimilar can realistically reach the market. Litigation and settlements can move it earlier.
Biologics have no small-molecule “generics” — competition comes from FDA-licensed biosimilars, tracked in the FDA Purple Book.
| Code | What it grants | Expires |
|---|---|---|
| RefProduct | Reference-product exclusivity (12-year, BPCIA) — no biosimilar can be licensed before this date | Dec 17, 2033 |
Is there a biosimilar for TEZSPIRE 210 MG/1.91 ML SYRING?
Why do different websites show different biosimilar dates?
Can a biosimilar launch before the last patent expires?
What does “current Purple Book estimate” mean?
What does “FDA listed” mean?
What does a patent or protection date mean here?
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 55513-0112-01 You're viewing this | 1 SYRINGE in 1 CARTON (55513-112-01) / 1.91 mL in 1 SYRINGE | 2021-12-17 | Active |
| 55513-0112-96 | 1 SYRINGE in 1 CARTON (55513-112-96) / 1.91 mL in 1 SYRINGE | 2021-12-17 | Active |
| 55513-0112-99 | 1.91 mL in 1 SYRINGE (55513-112-99) | 2021-12-17 | Discontinued by firm |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 55513-0112-01?
What is the difference between NDC 55513-0112-01 and NDC 55513-0112-96?
What NDC number is used to bill for this package of TEZSPIRE tezepelumab-ekko 210 mg/1.9mL Injection, Solution?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE TEZSPIRE is a thymic stromal lymphopoietin (TSLP) blocker, human monoclonal antibody (IgG2λ), indicated: • for the add-on maintenance treatment of adult and pediatric patients aged 12 years and older with severe asthma. ( 1.1 ) Limitations of Use: Not for relief of acute bronchospasm or status asthmaticus. ( 1.1 ) • for the add-on maintenance treatment of adult and pediatric patients aged 12 years and older with inadequately controlled chronic rhinosinusitis with nasal polyps (CRSwNP).
( 1.2 )
1.1Asthma TEZSPIRE is indicated for the add-on maintenance treatment of adult and pediatric patients aged 12 years and older with severe asthma. Limitations of Use: TEZSPIRE is not indicated for the relief of acute bronchospasm or status asthmaticus.
1.2Chronic Rhinosinusitis with Nasal Polyps TEZSPIRE is indicated for the add-on maintenance treatment of adult and pediatric patients aged 12 years and older with inadequately controlled chronic rhinosinusitis with nasal polyps (CRSwNP).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Recommended dosage is 210 mg administered once every 4 weeks. ( 2.1 ) • Administer by subcutaneous injection. ( 2.1 ) • See full prescribing information for preparation and administration instructions. ( 2.2 )
2.1Recommended Dosage The recommended dosage of TEZSPIRE is 210 mg administered subcutaneously once every 4 weeks. Missed Dose Information If a dose is missed, administer the dose as soon as possible. Thereafter, the patient can continue (resume) dosing on the usual day of administration. If the next dose is already due, then administer as planned.
2.2Preparation and Administration Instructions TEZSPIRE vial and pre‑filled syringe are intended for administration by a healthcare provider. TEZSPIRE pre-filled pen can be administered by patients/caregivers or healthcare providers. Patients/caregivers may administer TEZSPIRE pre-filled pen after proper training in subcutaneous injection technique and after the healthcare provider determines it is appropriate.
Each vial, pre-filled syringe and pre‑filled pen contain a single dose of TEZSPIRE. • Prior to administration, remove TEZSPIRE from the refrigerator and allow it to reach room temperature. This generally takes 60 minutes. Do not expose to heat and do not shake.
Do not use if the security seal on the carton has been broken. Do not put back in the refrigerator once TEZSPIRE has reached room temperature. • Visually inspect TEZSPIRE for particulate matter and discoloration prior to administration. TEZSPIRE is a clear to opalescent, colorless to light yellow solution.
Do not use TEZSPIRE if liquid is cloudy, discolored, or if it contains large particles or foreign particulate matter. Do not use if the vial, pre-filled syringe or pre‑filled pen has been dropped or damaged or if the expiration date has passed. • Inject TEZSPIRE 210 mg (contents of one vial, one pre-filled syringe or one pre-filled pen as described below) subcutaneously into the thigh or abdomen, except for the 2 inches (5 cm) around the navel. If a healthcare provider or caregiver administers the injection, the upper arm can also be used.
A patient should not self-inject in the upper arm. TEZSPIRE should not be injected into areas where the skin is tender, bruised, erythematous, or hardened. It is recommended to rotate the injection site with each injection.
Administration Instructions for Single-Dose Pre-filled Syringe Refer to Figure 1 to identify the pre-filled syringe components for use in the administration steps. Do not remove the needle cover until Step 2 of these instructions when you are ready to inject TEZSPIRE. Do not touch the needle guard activation clips to prevent premature activation of the needle safety guard.
Figure 1 TEZSPIRE Pre-filled Syringe Components 1. Grasp the syringe body to remove the pre-filled syringe from its carton. Do not grab the pre-filled syringe by the plunger.
The pre-filled syringe may contain small air bubbles; this is normal. Do not expel the air bubbles prior to administration. 2.
Do not remove the needle cover until ready to inject. Hold the syringe body and remove the needle cover by pulling straight off. Do not hold the plunger or plunger head while removing the needle cover.
You may see a drop of liquid at the end of the needle. This is normal. 3.
Gently pinch the skin and administer subcutaneously at approximately 45° angle into the recommended injection site (i.e., upper arm, thigh, or abdomen). 4. Inject all of the medication by pushing in the plunger all the way until the plunger head is completely between the needle guard activation clips.
This is necessary to activate the needle guard. 5. After injection, maintain pressure on the plunger head and remove the needle from the skin.
Release pressure on the plunger head to allow the needle guard to cover the needle. Do not re-cap the pre-filled syringe. 6.
Discard the used syringe into a sharps container. Administration Instructions for Single-Dose Pre-filled Pen These administration…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: a clear to opalescent, colorless to light yellow solution available as: • 210 mg/1.91 mL (110 mg/mL) solution in a single-dose glass vial. • 210 mg/1.91 mL (110 mg/mL) solution in a single-dose pre-filled syringe. • 210 mg/1.91 mL (110 mg/mL) solution in a single‑dose pre‑filled pen. Injection: • 210 mg/1.91 mL (110 mg/mL) solution in a single-dose glass vial. ( 3 ) • 210 mg/1.91 mL (110 mg/mL) solution in a single-dose pre-filled syringe.
( 3 ) • 210 mg/1.91 mL (110 mg/mL) solution in a single‑dose pre‑filled pen. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS TEZSPIRE is contraindicated in patients who have known hypersensitivity to tezepelumab-ekko or any of its excipients [see Warnings and Precautions (5.1) ] . Known hypersensitivity to tezepelumab-ekko or excipients. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Hypersensitivity Reactions: Hypersensitivity reactions have been observed in the clinical trials (e.g., rash, allergic conjunctivitis) following the administration of TEZSPIRE. Postmarketing cases of anaphylaxis have been reported. Initiate appropriate treatment as clinically indicated in the event of a hypersensitivity reaction.
( 5.1 ) • Risk Associated with Abrupt Reduction in Corticosteroid Dosage: Do not discontinue systemic or inhaled corticosteroids abruptly upon initiation of therapy with TEZSPIRE. Decrease corticosteroids gradually, if appropriate. ( 5.3 ) • Parasitic (Helminth) Infection: Treat patients with pre-existing helminth infections before therapy with TEZSPIRE.
If patients become infected while receiving TEZSPIRE and do not respond to anti-helminth treatment, discontinue TEZSPIRE until the parasitic infection resolves. ( 5.4 ) • Vaccination: Avoid use of live attenuated vaccines. ( 5.5 )
5.1Hypersensitivity Reactions Hypersensitivity reactions were observed in the clinical trials (e.g., rash and allergic conjunctivitis) following the administration of TEZSPIRE. Postmarketing cases of anaphylaxis have also been reported [see Contraindications (4) and Adverse Reactions (6.2) ] . These reactions can occur within hours of administration, but in some instances have a delayed onset (i.e., days).
In the event of a hypersensitivity reaction, consider the benefits and risks for the individual patient to determine whether to continue or discontinue treatment with TEZSPIRE.
5.2Acute Asthma Symptoms or Deteriorating Disease TEZSPIRE should not be used to treat acute asthma symptoms or acute exacerbations. Do not use TEZSPIRE to treat acute bronchospasm or status asthmaticus. Patients should seek medical advice if their asthma remains uncontrolled or worsens after initiation of treatment with TEZSPIRE.
5.3Risk Associated with Abrupt Reduction of Corticosteroid Dosage Do not discontinue systemic or inhaled corticosteroids abruptly upon initiation of therapy with TEZSPIRE. Reductions in corticosteroid dose, if appropriate, should be gradual and performed under the direct supervision of a physician. Reduction in corticosteroid dose may be associated with systemic withdrawal symptoms and/or unmask conditions previously suppressed by systemic corticosteroid therapy.
5.4Parasitic (Helminth) Infection Thymic stromal lymphopoietin (TSLP) may be involved in the immunological response to some helminth infections. Patients with known helminth infections were excluded from participation in clinical trials. It is unknown if TEZSPIRE will influence a patient’s response against helminth infections.
Treat patients with pre-existing helminth infections before initiating therapy with TEZSPIRE. If patients become infected while receiving treatment with TEZSPIRE and do not respond to anti-helminth treatment, discontinue treatment with TEZSPIRE until infection resolves.
5.5Live Attenuated Vaccines The concomitant use of TEZSPIRE and live attenuated vaccines has not been evaluated. The use of live attenuated vaccines should be avoided in patients receiving TEZSPIRE.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: • Hypersensitivity Reactions [see Warnings and Precautions (5.1) ] Most common adverse reactions (incidence ≥ 3%) are: • Asthma: pharyngitis, arthralgia, and back pain. ( 6.1 ) • Chronic rhinosinusitis with nasal polyps: nasopharyngitis, upper respiratory tract infection, epistaxis, pharyngitis, back pain, influenza, injection site reaction and arthralgia. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact AstraZeneca at 1-800-236-9933 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse Reactions in Adult and Pediatric Patients 12 Years of Age and Older with Asthma The safety of TEZSPIRE in asthma was based on the pooled safety population from PATHWAY and NAVIGATOR, which consists of 665 adult and pediatric patients 12 years of age and older with severe asthma who received at least one dose of TEZSPIRE 210 mg subcutaneously once every 4 weeks.
The two placebo-controlled clinical trials were of 52 weeks duration. In addition, a similar safety profile was seen in a trial that enrolled 150 adult patients with severe asthma who required treatment with daily oral corticosteroids [see Clinical Studies (14.1) ] . Adverse reactions that occurred at an incidence greater than or equal to 3% and more common than in the placebo group from the pooled safety population (PATHWAY and NAVIGATOR) are shown in Table 1.
Table 1 Adverse Reactions with TEZSPIRE with Incidence Greater than or Equal to 3% and More Common than Placebo in Patients with Severe Asthma in the Pooled Safety Population (PATHWAY and NAVIGATOR) Adverse Reaction TEZSPIRE N=665 % Placebo N=669 % Pharyngitis Pharyngitis (including Pharyngitis, Pharyngitis bacterial, Pharyngitis streptococcal and Viral pharyngitis) 4 3 Arthralgia 4 3 Back pain 4 3 Specific Adverse Reactions Cardiovascular Events In a randomized, double-blind, long term extension trial, patients 12 years and older with severe asthma from trials NAVIGATOR and the additional trial [see Clinical Studies (14.1) ] received TEZSPIRE 210 mg subcutaneously every 4 weeks or placebo for up to 104 weeks.
In the trial, the incidence rates (IR) per 100 patient-years (PY) for serious cardiac adverse events in patients treated with TEZSPIRE or placebo were 1.08 and 0.21, respectively, with an incidence rate difference (IRD) of 0.88 (95% CI: 0.24, 1.53). The types of serious cardiac adverse events were heterogeneous. In the trial, the IR per 100 PY for adjudicated major adverse cardiovascular events (MACE, defined as cardiovascular deaths, non-fatal myocardial infarctions, and non-fatal strokes) in patients treated with TEZSPIRE or placebo were 0.60 and 0.42, respectively, with an IRD of 0.18 (95% CI: -0.51, 0.75).
Injection Site Reactions In the pooled safety population (PATHWAY and NAVIGATOR), in which TEZSPIRE or placebo was administered using the vial by a healthcare provider, injection site reactions (e.g., injection site erythema, injection site swelling, injection site pain) occurred at a rate of 3.3% in patients treated with TEZSPIRE compared with 2.7% in patients treated with placebo. In an open-label trial of 216 patients with asthma in which TEZSPIRE was administered by healthcare providers and patients or caregivers using either the pre-filled pen or pre-filled syringe, injection site reactions (e.g., injection site erythema, injection site swelling, injection site pain) were observed in 5.7% patients using the pre-filled pen and 0% using the pre-filled syringe.
However, the trial was not designed to compare injection site reactions between patients who received TEZSPIRE by the pre-filled pen versus pre-f…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS No formal drug interaction studies have been performed with TEZSPIRE.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no available data on TEZSPIRE use in pregnant women to evaluate for any drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes. Placental transfer of monoclonal antibodies such as tezepelumab-ekko is greater during the third trimester of pregnancy; therefore, potential effects on a fetus are likely to be greater during the third trimester of pregnancy. In an enhanced pre- and post-natal development (ePPND) study conducted in cynomolgus monkeys, placental transport of tezepelumab-ekko was observed but there was no evidence of fetal harm following intravenous administration of tezepelumab-ekko throughout pregnancy at doses that produced maternal exposures up to 168 times the exposure at the maximum recommended human dose (MRHD) of 210 mg administered subcutaneously (see Data) .
The estimated background risk of major birth defects and miscarriages for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk: In women with poorly or moderately controlled asthma, evidence demonstrates that there is an increased risk of preeclampsia in the mother and prematurity, low birth weight, and small for gestational age in the neonate. The level of asthma control should be closely monitored in pregnant women and treatment adjusted as necessary to maintain optimal control. Data Animal Data In the ePPND study, pregnant cynomolgus monkeys received tezepelumab-ekko from GD20 to GD22 (dependent on pregnancy determination), at the beginning of organogenesis, and once every 7 days until the end of gestation at doses that produced exposures up to 168 times that achieved with the MRHD (on an AUC basis with maternal intravenous doses up to 300 mg/kg/week).
There were no tezepelumab-ekko related adverse effects on maternal health, pregnancy outcome, embryo-fetal development, or neonatal growth and development up to 6.5 months of age. Tezepelumab-ekko crossed the placenta in cynomolgus monkeys and tezepelumab-ekko serum concentrations were 0.5- to 6.7-fold higher in infants relative to maternal animals.
8.2Lactation Risk Summary There is no information regarding the presence of tezepelumab-ekko in human milk, its effects on the breastfed infant, or its effects on milk production. However, tezepelumab-ekko is a human monoclonal antibody immunoglobulin G2λ (IgG2λ), and immunoglobulin G (IgG) is present in human milk in small amounts. Tezepelumab‑ekko was present in the milk of cynomolgus monkeys postpartum following dosing during pregnancy (see Data) .
The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for TEZSPIRE and any potential adverse effects on the breastfed infant from TEZSPIRE or from the underlying maternal condition. Data Animal Data In a prenatal and postnatal development study in cynomolgus monkeys, tezepelumab-ekko concentrations in milk were up to 0.5% of the maternal serum concentrations after intravenous administration of tezepelumab-ekko up to 300 mg/kg/week (168 times the exposures based on AUC achieved at MRHD).
The concentration of tezepelumab-ekko in animal milk does not necessarily predict the concentration of drug in human milk.
8.4Pediatric Use Asthma The safety and effectiveness of TEZSPIRE for the add-on maintenance treatment of severe asthma have been established in pediatric patients aged 12 years and older [see Adverse Reactions (6.1) and Clinical Studies (14.1)] . Use of TEZSPIRE for this indication is supported by evidence from a total of 82 pediatric patients aged 12 to 17 years enrolled in NAVIGATOR and received treatment with…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no available data on TEZSPIRE use in pregnant women to evaluate for any drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes. Placental transfer of monoclonal antibodies such as tezepelumab-ekko is greater during the third trimester of pregnancy; therefore, potential effects on a fetus are likely to be greater during the third trimester of pregnancy. In an enhanced pre- and post-natal development (ePPND) study conducted in cynomolgus monkeys, placental transport of tezepelumab-ekko was observed but there was no evidence of fetal harm following intravenous administration of tezepelumab-ekko throughout pregnancy at doses that produced maternal exposures up to 168 times the exposure at the maximum recommended human dose (MRHD) of 210 mg administered subcutaneously (see Data) .
The estimated background risk of major birth defects and miscarriages for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk: In women with poorly or moderately controlled asthma, evidence demonstrates that there is an increased risk of preeclampsia in the mother and prematurity, low birth weight, and small for gestational age in the neonate. The level of asthma control should be closely monitored in pregnant women and treatment adjusted as necessary to maintain optimal control. Data Animal Data In the ePPND study, pregnant cynomolgus monkeys received tezepelumab-ekko from GD20 to GD22 (dependent on pregnancy determination), at the beginning of organogenesis, and once every 7 days until the end of gestation at doses that produced exposures up to 168 times that achieved with the MRHD (on an AUC basis with maternal intravenous doses up to 300 mg/kg/week).
There were no tezepelumab-ekko related adverse effects on maternal health, pregnancy outcome, embryo-fetal development, or neonatal growth and development up to 6.5 months of age. Tezepelumab-ekko crossed the placenta in cynomolgus monkeys and tezepelumab-ekko serum concentrations were 0.5- to 6.7-fold higher in infants relative to maternal animals.
🧒 Pediatric Use ▾
8.4Pediatric Use Asthma The safety and effectiveness of TEZSPIRE for the add-on maintenance treatment of severe asthma have been established in pediatric patients aged 12 years and older [see Adverse Reactions (6.1) and Clinical Studies (14.1)] . Use of TEZSPIRE for this indication is supported by evidence from a total of 82 pediatric patients aged 12 to 17 years enrolled in NAVIGATOR and received treatment with TEZSPIRE 210 mg subcutaneously every 4 weeks (n=41) or placebo (n=41). Compared with placebo, improvements in annualized asthma exacerbation (rate ratio 0.70; 95% CI 0.34, 1.46) and FEV1 (LS mean change versus placebo
0.17L; 95% CI -0.01, 0.35) were observed in pediatric patients treated with TEZSPIRE. The safety profile and pharmacodynamic responses in pediatric patients were generally similar to the overall study population. The safety and effectiveness of TEZSPIRE have not been established in patients younger than 12 years of age with asthma.
CRSwNP The safety and effectiveness of TEZSPIRE for the add-on maintenance treatment of inadequately controlled CRSwNP have been established in pediatric patients aged 12 years and older. Use of TEZSPIRE for this indication is supported by evidence from the adequate and well-controlled study of TEZSPIRE in adults (WAYPOINT) [see Clinical Studies (14.2) ] with the following additional data: • Pharmacokinetic (PK) data from adult and pediatric patients aged 12 years and older with severe asthma and adult patients with CRSwNP [see Clinical Pharmacology (12.3) ] . • Safety data in pediatric patients aged 12 years and older with severe asthma [see Adverse Reactions (6.1) ] .
The safety and effectiveness of TEZSPIRE have not been established in patients younger than 12 years of age with CRSwNP.
🧓 Geriatric Use ▾
8.5Geriatric Use Asthma Of the 665 patients with asthma treated with TEZSPIRE in clinical trials (PATHWAY and NAVIGATOR) for severe asthma, 119 patients (18%) were 65 years or older. No overall differences in safety or effectiveness of TEZSPIRE have been observed between patients 65 years of age and older and younger patients [see Adverse Reactions (6.1) and Clinical Studies (14.1) ] . CRSwNP Of the 203 patients with CRSwNP treated with TEZSPIRE in a clinical trial (WAYPOINT) for CRSwNP, 29 patients (14%) were 65 years or older.
No overall differences in safety or effectiveness of TEZSPIRE have been observed between patients 65 years of age and older and younger adult patients [see Adverse Reactions (6.1) and Clinical Studies (14.2) ] .
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Tezepelumab-ekko is a thymic stromal lymphopoietin (TSLP) blocker, human monoclonal antibody IgG2λ that binds to human TSLP with a dissociation constant of 15.8 pM and blocks its interaction with the heterodimeric TSLP receptor. TSLP is a cytokine mainly derived from epithelial cells and occupies an upstream position in inflammatory cascades. Airway and mucosal inflammation are important components of the pathogenesis of asthma and CRSwNP.
Multiple cell types (e.g., mast cells, eosinophils, neutrophils, macrophages, lymphocytes, ILC2 cells) and mediators (e.g., histamine, eicosanoids, leukotrienes, cytokines) are involved in airway and mucosal inflammation. Increased levels of TSLP mRNA and protein are found in the airways of patients with asthma as well as in nasal polyp tissue. Blocking TSLP with tezepelumab-ekko reduces biomarkers and cytokines associated with inflammation including blood eosinophils, airway submucosal eosinophils, IgE, FeNO, IL-5, and IL-13; however, the mechanism of tezepelumab-ekko action in asthma and CRSwNP has not been definitively established.
12.2Pharmacodynamics In NAVIGATOR, administration of TEZSPIRE 210 mg subcutaneously every 4 weeks (n=528) reduced blood eosinophils counts, FeNO, IL-5 concentration and IL-13 concentration from baseline compared with placebo (n=531) with an onset of effect 2 weeks after initiation of treatment and sustained reduction on treatment to 52 weeks. TEZSPIRE caused a slow but progressive reduction in serum total IgE concentration throughout 52 weeks of treatment. Similar effects were seen in PATHWAY.
In WAYPOINT, administration of TEZSPIRE 210 mg subcutaneously every 4 weeks (n=203) resulted in reductions from baseline of blood eosinophils, FeNO (in participants with co-morbid asthma [about 60% of patients]) and serum IgE as compared to placebo (n=205). Blood eosinophils were reduced beginning at Week 4, the first observed timepoint, with reductions maintained through Week 52. Reductions in FeNO and serum IgE were observed during the treatment period at Weeks 24 and 52.
12.3Pharmacokinetics The pharmacokinetics of tezepelumab-ekko is similar in patients with asthma and CRSwNP. The pharmacokinetics of tezepelumab-ekko were dose-proportional following administration of a single subcutaneous dose over a dose range from 0.01 to 2 times the recommended dose. With an every 4 weeks dosing regimen, tezepelumab-ekko achieves steady-state after 12 weeks and the accumulation ratio for C trough is 1.86-fold.
Absorption Following subcutaneous administration, the maximum serum concentration was reached in approximately 3 to 10 days. Based on population pharmacokinetic analysis, the estimated absolute bioavailability was approximately 77%. There was no clinically relevant difference in bioavailability when administered to different injection sites (abdomen, thigh, or upper arm).
Distribution Based on population pharmacokinetic analysis, central and peripheral volume of distribution of tezepelumab-ekko were
3.9 L and
2.2L, respectively, for a 70 kg individual. Elimination As a human monoclonal antibody, tezepelumab-ekko is eliminated by intracellular catabolism and there is no evidence of target-mediated clearance within the studied dose range. Based on population pharmacokinetic analysis, the estimated clearance for tezepelumab-ekko was
0.17L/d for a 70 kg individual. The elimination half-life was approximately 26 days. Metabolism Tezepelumab-ekko is a human monoclonal antibody (IgG2λ) that is degraded by proteolytic enzymes widely distributed in the body and not metabolized by hepatic enzymes.
Specific Populations Age, Sex, Race Based on population pharmacokinetic analysis, age (12 to 80 years), sex and race (White, Black, Asian, Other) had no clinically meaningful effects on the pharmacokinetics of tezepelumab-ekko. Body Weight Based on population pharmacokinetic analysis, higher body weight was associated with lower exposure.…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Tezepelumab-ekko is a thymic stromal lymphopoietin (TSLP) blocker, human monoclonal antibody IgG2λ that binds to human TSLP with a dissociation constant of 15.8 pM and blocks its interaction with the heterodimeric TSLP receptor. TSLP is a cytokine mainly derived from epithelial cells and occupies an upstream position in inflammatory cascades. Airway and mucosal inflammation are important components of the pathogenesis of asthma and CRSwNP.
Multiple cell types (e.g., mast cells, eosinophils, neutrophils, macrophages, lymphocytes, ILC2 cells) and mediators (e.g., histamine, eicosanoids, leukotrienes, cytokines) are involved in airway and mucosal inflammation. Increased levels of TSLP mRNA and protein are found in the airways of patients with asthma as well as in nasal polyp tissue. Blocking TSLP with tezepelumab-ekko reduces biomarkers and cytokines associated with inflammation including blood eosinophils, airway submucosal eosinophils, IgE, FeNO, IL-5, and IL-13; however, the mechanism of tezepelumab-ekko action in asthma and CRSwNP has not been definitively established.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied TEZSPIRE (tezepelumab-ekko) injection is a sterile, preservative-free, clear to opalescent, colorless to light yellow solution supplied as a single-dose vial, single-dose pre-filled syringe with a fixed 27-gauge ½ inch needle with a needle cover or single-dose pre-filled pen with a fixed 27-gauge ½ inch needle with a needle cover. The vial, pre-filled syringe and pre-filled pen, including the needle cover and stopper, are not made with natural rubber latex. TEZSPIRE is available as: • Single-Dose Vial: Carton contains one 210 mg/1.91 mL (110 mg/mL) glass vial (NDC 55513‑100‑01) • Single-Dose Pre-filled Syringe: Carton contains one 210 mg/1.91 mL (110 mg/mL) pre-filled syringe (NDC 55513‑112‑01) • Single-Dose Pre-filled Pen: Carton contains one 210 mg/1.91 mL (110 mg/mL) pre-filled pen (NDC 55513-123‑01) Storage and Handling Store refrigerated between 36°F to 46°F (2°C to 8°C).
If necessary, TEZSPIRE may be kept at room temperature between 68°F to 77˚F (20°C to 25°C) for a maximum of 30 days. Do not put back in the refrigerator once TEZSPIRE has reached room temperature. After removal from the refrigerator, TEZSPIRE must be used within 30 days or discarded.
Store TEZSPIRE in original carton to protect from light until time of use. Do not freeze. Do not shake.
Do not expose to heat.
📋 Description ▾
11 DESCRIPTION Tezepelumab-ekko, a thymic stromal lymphopoietin (TSLP) blocker, is a human monoclonal antibody immunoglobulin G2λ (IgG2λ) produced in Chinese hamster ovary (CHO) cells by recombinant DNA technology. Tezepelumab-ekko has a molecular weight of approximately 147 kDa. TEZSPIRE (tezepelumab-ekko) injection is a sterile, preservative-free, clear to opalescent, colorless to light yellow solution for subcutaneous injection supplied in a single-dose vial, single-dose pre-filled syringe or single‑dose pre‑filled pen.
Each single-dose vial, pre-filled syringe or pre‑filled pen delivers 1.91 mL containing 210 mg tezepelumab-ekko, glacial acetic acid (2.8 mg), L-proline (48 mg), polysorbate 80 (0.19 mg), sodium hydroxide, and water for injection. The pH is 5.2.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient and/or caregiver to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Hypersensitivity Reactions Inform patients that hypersensitivity reactions (e.g., anaphylaxis, rash and allergic conjunctivitis) can occur following administration of TEZSPIRE [ see Contraindications (4) and Adverse Reactions (6) ] . These reactions can occur within hours of administration, but in some instances have a delayed onset (i.e., days).
Instruct patients to contact their healthcare provider if they experience symptoms of an allergic reaction [see Warnings and Precautions (5.1) ] . Not for Acute Symptoms or Deteriorating Disease Inform patients that TEZSPIRE does not treat acute asthma symptoms or acute exacerbations. Inform patients to seek medical advice if their asthma remains uncontrolled or worsens after initiation of treatment with TEZSPIRE [see Warnings and Precautions (5.2) ] .
Risk Associated with Abrupt Reduction of Corticosteroid Dosage Inform patients to not discontinue systemic or inhaled corticosteroids except under the direct supervision of a healthcare provider. Inform patients that reduction in corticosteroid dose may be associated with systemic withdrawal symptoms and/or unmask conditions previously suppressed by systemic corticosteroid therapy [see Warnings and Precautions (5.3) ] . Administration of Vaccines Instruct patients to inform the healthcare provider that they are taking TEZSPIRE prior to a potential vaccination [see Warnings and Precautions (5.5) ] .
Proper Storage and Disposal Advise patients to refrigerate TEZSPIRE at 36°F to 46°F (2°C to 8°C). TEZSPIRE may be kept at room temperature between 68°F to 77˚F (20°C to 25°C) for a maximum of 30 days [see How Supplied/Storage and Handling (16) ] . Inform patients and caregivers of the need for proper disposal of the pre-filled pen after use, including the use of a sharps disposal container.
Manufactured by: AstraZeneca AB, Södertälje, Sweden SE-15185 US License No. 2059 At: Amgen Inc., One Amgen Center Drive, Thousand Oaks, CA 91320-1799 Marketed by: Amgen Inc. and AstraZeneca AB ©AstraZeneca and Amgen 2025 TEZSPIRE is a trademark of Amgen Inc. and AstraZeneca.