
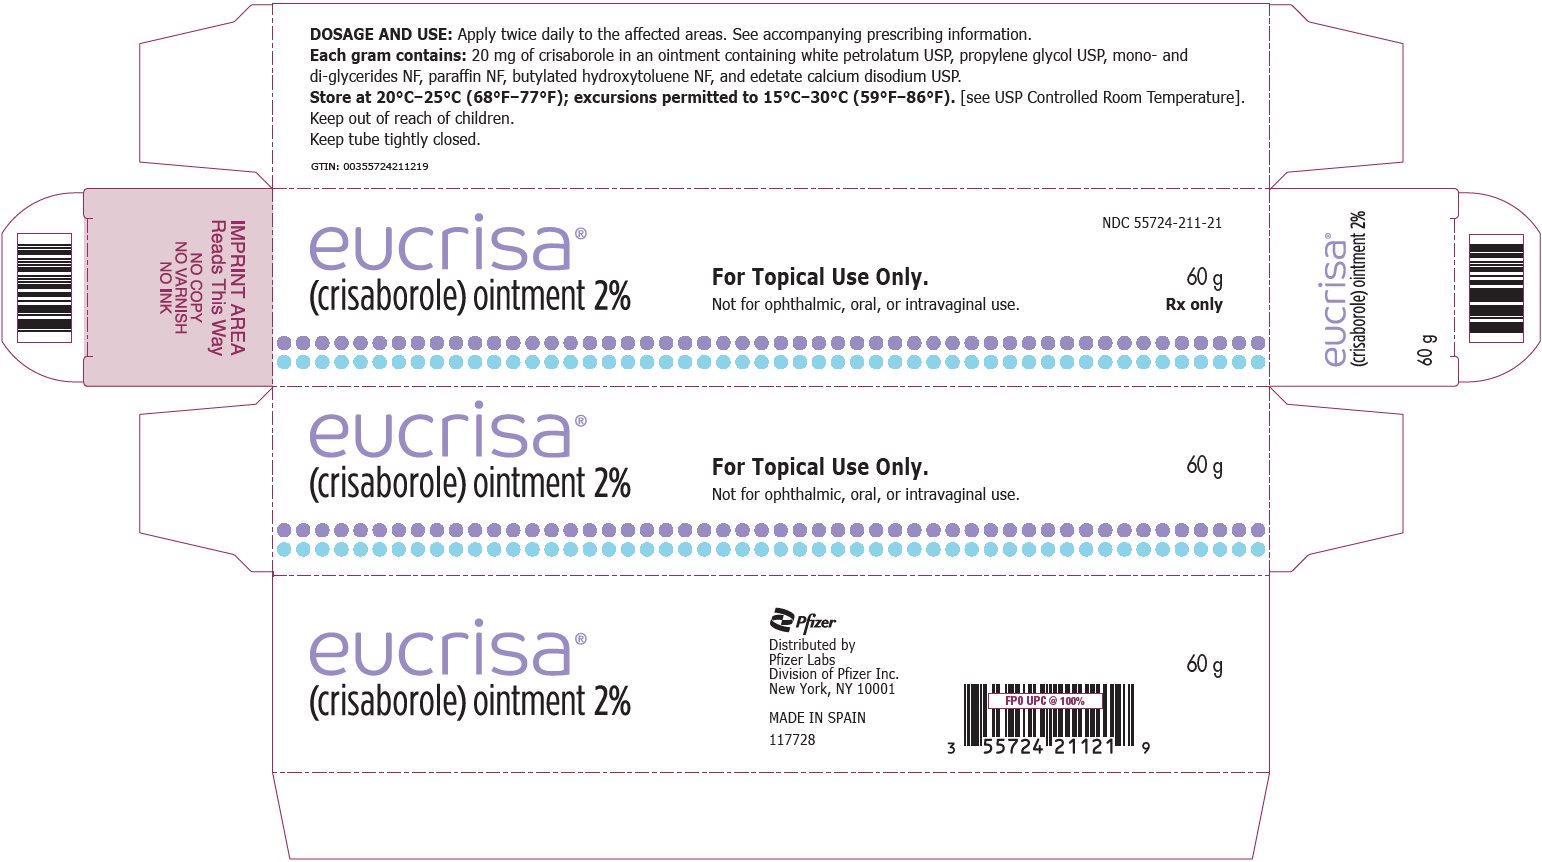
Eucrisa crisaborole 20 mg/g Ointment, 6 tubes
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Phosphodiesterase 4 Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Crisaborole is used to treat eczema (atopic dermatitis; a skin condition which causes the skin to be dry and itchy and to sometimes develop red, scaly rashes) in adults and children 3 years of age and older. Crisaborole is in a class of medications called phosphodiesterase inhibitors. It works by blocking the action of certain natural substances in the body that cause inflammation.
Read the full MedlinePlus article ↗- No, it's a prescription medicine, not a moisturizer. Eucrisa contains crisaborole, which works by blocking an inflammatory enzyme in the skin. It's specifically approved to treat m...
- What is Eucrisa actually for — is it just a fancy moisturizer?
- A burning or stinging sensation right after applying is actually the most commonly reported side effect — about 4% of people in clinical trials experienced it. For most people it's...
- It burns when I apply it — is that normal? Should I stop using it?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Crisaborole — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 1P9D0Z171K
BHT is a synthetic antioxidant that prevents fats and oils in medicines from breaking down and becoming rancid. It helps keep the product stable and effective during storage.
-
UNII 25IH6R4SGF
Edetate calcium disodium is a chelating agent, a chemical that binds to metal ions. It's used in some medications to prevent unwanted metals from interfering with the drug's stability and effectiveness.
-
UNII 230OU9XXE4
A waxy substance made from glycerin and stearic acid that acts as an emulsifier to blend oily and watery ingredients together. It also helps thicken and stabilize the medicine's texture.
-
UNII I9O0E3H2ZE
Paraffin is a waxy, petroleum-derived substance used as a coating, lubricant, and hardening agent in tablets and capsules. It helps protect the medicine from moisture and gives pills a smooth finish.
-
UNII 4T6H12BN9U
Petrolatum is a purified mineral oil-based jelly derived from petroleum. In medicines, it acts as an emollient, lubricant, and moisture barrier to soften skin, reduce friction, and help prevent water loss from formulations.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per g | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $12.60 | $189.03 / 15 g |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Eucrisa 20 mg/gthis 55724-0211-42 | Pfizer | 6 tubes | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8501712 ↗ | Method of use | U-1932 | Feb 16, 2027 |
| US 9682092 ↗ | Method of use | U-1932 | Feb 16, 2027 |
| US 8168614 ↗ | Method of use | U-1932 | Jan 20, 2030 |
| US 8039451 ↗ | Drug substance | — | Jun 29, 2029 |
| US 8039451*PED ↗ | Drug product | — | Dec 29, 2029 |
| US 8168614*PED ↗ | Drug product | — | Jul 20, 2030 |
| US 8501712*PED ↗ | Drug product | — | Aug 16, 2027 |
| US 9682092*PED ↗ | Drug product | — | Aug 16, 2027 |
| Code | What it grants | Expires |
|---|---|---|
| D-191 | Other change requiring clinical data (3-year) | Apr 3, 2026 |
Is there a generic version of EUCRISA 2% OINTMENT?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 55724-0211-11 | 1 TUBE in 1 CARTON (55724-211-11) / 100 g in 1 TUBE | $10.69 / g | $1,069.06 | 2017-01-30 | Active |
| 55724-0211-21 | 1 TUBE in 1 CARTON (55724-211-21) / 60 g in 1 TUBE | $12.65 / g | $758.77 | 2017-01-30 | Active |
| 55724-0211-23 | 1 TUBE in 1 CARTON (55724-211-23) / 60 g in 1 TUBE | — | — | 2017-01-30 | Active |
| 55724-0211-42 You're viewing this | 6 TUBE in 1 CARTON (55724-211-42) / 2.5 g in 1 TUBE | — | — | 2017-01-30 | Active |
This pack shows little to no recent Medicaid volume — a different pack size carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 55724-0211-42?
What NDC number is used to bill for this package of Eucrisa crisaborole 20 mg/g Ointment?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE EUCRISA is indicated for topical treatment of mild to moderate atopic dermatitis in adult and pediatric patients 3 months of age and older. EUCRISA is a phosphodiesterase 4 inhibitor indicated for topical treatment of mild to moderate atopic dermatitis in adult and pediatric patients 3 months of age and older. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Apply a thin layer of EUCRISA twice daily to affected areas. Once clinical effect is achieved, consider reducing application to once daily [see Clinical Studies (14) ] . EUCRISA is for topical use only and not for ophthalmic, oral, or intravaginal use. • Apply a thin layer twice daily to affected areas.
( 2 ) • Once clinical effect is achieved, consider reducing application to once daily. ( 2 ) • For topical use only. ( 2 ) • Not for ophthalmic, oral, or intravaginal use.
( 2 )
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Ointment: 20 mg of crisaborole per gram (2%) of white to off-white ointment. Ointment, 2%. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS EUCRISA is contraindicated in patients with known hypersensitivity to crisaborole or any component of the formulation. [see Warnings and Precautions (5.1) ] Known hypersensitivity to crisaborole or any component of the formulation. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypersensitivity reactions : If signs and symptoms of hypersensitivity occur, discontinue EUCRISA immediately and initiate appropriate therapy. ( 5.1 )
5.1Hypersensitivity Reactions Hypersensitivity reactions, including contact urticaria, have occurred in patients treated with EUCRISA. Hypersensitivity should be suspected in the event of severe pruritus, swelling and erythema at the application site or at a distant site. If signs and symptoms of hypersensitivity occur, discontinue EUCRISA immediately and initiate appropriate therapy.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most common adverse reaction occurring in ≥1% in subjects is application site pain. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Pfizer Inc. at 1-800-438-1985 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In two double-blind, vehicle-controlled clinical trials (Trial 1 and Trial 2), 1012 subjects 2 to 79 years of age with mild to moderate atopic dermatitis were treated with EUCRISA twice daily for 4 weeks. The adverse reaction reported by ≥1% of EUCRISA-treated subjects is listed in Table 1.
Table 1: Adverse Reaction Occurring in ≥1% of Subjects in Atopic Dermatitis Trials through Week 4 Adverse Reaction EUCRISA Twice Daily N=1012 n (%) Vehicle Twice Daily N=499 n (%) Application site pain Refers to skin sensations such as burning or stinging. 45 (4) 6 (1) Less common (<1%) adverse reactions in subjects treated with EUCRISA included contact urticaria [see Warnings and Precautions (5.1) ]. In one double-blind, vehicle-controlled trial including an initial open-label period (Trial 3), 497 subjects 3 months of age and older with mild to moderate atopic dermatitis received EUCRISA twice daily for up to 8 weeks.
This was followed by a double-blind period, during which 135 subjects out of 270 randomized subjects received EUCRISA and 135 subjects received vehicle once daily for 52 weeks or until they developed a flare. The adverse reactions observed in the open-label period were similar to the known safety profile of twice daily treatment with EUCRISA. The adverse reactions observed with once daily treatment were similar to vehicle [see Clinical Studies (14) ] .
6.2Postmarketing Experience The following adverse reactions have been identified during postapproval use of EUCRISA. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure: Skin and Subcutaneous: allergic contact dermatitis
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Available data from case reports with EUCRISA use in pregnant women are insufficient to inform a drug-associated risk for major birth defects, miscarriage, or other adverse maternal or fetal outcomes. In animal reproduction studies, there were no adverse developmental effects observed with oral administration of crisaborole in pregnant rats and rabbits during organogenesis at doses up to 3 and 2 times, respectively, the maximum recommended human dose (MRHD) ( see Data ). The background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies carry some risk of birth defect, loss, or other adverse outcomes. The background risk of major birth defects in the U.S. general population is 2% to 4% and of miscarriage is 15% to 20% of clinically recognized pregnancies. Data Animal Data Rat and rabbit embryo-fetal development was assessed after oral administration of crisaborole.
Crisaborole did not cause adverse effects to the fetus at oral doses up to 300 mg/kg/day in pregnant rats during the period of organogenesis (3 times the MRHD on an area under the curve (AUC) comparison basis). No crisaborole-related fetal malformations were noted after oral treatment with crisaborole in pregnant rats at doses up to 600 mg/kg/day (13 times the MRHD on an AUC comparison basis) during the period of organogenesis. Maternal toxicity was produced at this high dose of 600 mg/kg/day in pregnant rats and was associated with decreased fetal body weight and delayed skeletal ossification.
Crisaborole did not cause adverse effects to the fetus at oral doses up to the highest dose tested of 100 mg/kg/day in pregnant rabbits during the period of organogenesis (2 times the MRHD on an AUC comparison basis). In a prenatal/postnatal development study, pregnant rats were treated with crisaborole at doses of 150, 300, or 600 mg/kg/day by oral gavage during gestation and lactation (from gestation day 7 through day 20 of lactation). Crisaborole did not have any adverse effects on fetal development at doses up to 300 mg/kg/day (3 times the MRHD on an AUC comparison basis).
Maternal toxicity was produced at the high dose of 600 mg/kg/day in pregnant rats and was associated with stillbirths, pup mortality, and reduced pup weights.
8.2Lactation Risk Summary There is no information available on the presence of EUCRISA in human milk, the effects of the drug on the breastfed infant or the effects of the drug on milk production after topical application of EUCRISA to women who are breastfeeding. EUCRISA is systemically absorbed. The lack of clinical data during lactation precludes a clear determination of the risk of EUCRISA to a breastfed infant.
Therefore, the developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for EUCRISA and any potential adverse effects on the breastfed infant from EUCRISA or from the underlying maternal condition.
8.4Pediatric Use The safety and effectiveness of EUCRISA have been established in pediatric patients ages 3 months and older for topical treatment of mild to moderate atopic dermatitis. Use of EUCRISA administered twice daily in this age group is supported by data from two 28-day adequate, vehicle-controlled safety and efficacy trials (1,313 pediatric subjects ages 2 years to 17 years of whom 874 received EUCRISA), a 28-day open-label, safety and pharmacokinetics (PK) trial (137 subjects ages 3 months to less than 2 years who received EUCRISA), and another trial with an open-label period of up to 8 weeks (327 pediatric subjects ages 5 months to less than 18 years who received EUCRISA) [see Clinical Pharmacology (12.3) and Clinical Studies (14) ] .
The safety and effectiveness of EUCRISA in pediatric patients below the age of 3 months have not been established.
8.5Geriatric Use Clinical studies of EUCRISA did not include sufficient numbers of subjects age 65 and over to determine whe…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from case reports with EUCRISA use in pregnant women are insufficient to inform a drug-associated risk for major birth defects, miscarriage, or other adverse maternal or fetal outcomes. In animal reproduction studies, there were no adverse developmental effects observed with oral administration of crisaborole in pregnant rats and rabbits during organogenesis at doses up to 3 and 2 times, respectively, the maximum recommended human dose (MRHD) ( see Data ). The background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies carry some risk of birth defect, loss, or other adverse outcomes. The background risk of major birth defects in the U.S. general population is 2% to 4% and of miscarriage is 15% to 20% of clinically recognized pregnancies. Data Animal Data Rat and rabbit embryo-fetal development was assessed after oral administration of crisaborole.
Crisaborole did not cause adverse effects to the fetus at oral doses up to 300 mg/kg/day in pregnant rats during the period of organogenesis (3 times the MRHD on an area under the curve (AUC) comparison basis). No crisaborole-related fetal malformations were noted after oral treatment with crisaborole in pregnant rats at doses up to 600 mg/kg/day (13 times the MRHD on an AUC comparison basis) during the period of organogenesis. Maternal toxicity was produced at this high dose of 600 mg/kg/day in pregnant rats and was associated with decreased fetal body weight and delayed skeletal ossification.
Crisaborole did not cause adverse effects to the fetus at oral doses up to the highest dose tested of 100 mg/kg/day in pregnant rabbits during the period of organogenesis (2 times the MRHD on an AUC comparison basis). In a prenatal/postnatal development study, pregnant rats were treated with crisaborole at doses of 150, 300, or 600 mg/kg/day by oral gavage during gestation and lactation (from gestation day 7 through day 20 of lactation). Crisaborole did not have any adverse effects on fetal development at doses up to 300 mg/kg/day (3 times the MRHD on an AUC comparison basis).
Maternal toxicity was produced at the high dose of 600 mg/kg/day in pregnant rats and was associated with stillbirths, pup mortality, and reduced pup weights.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of EUCRISA have been established in pediatric patients ages 3 months and older for topical treatment of mild to moderate atopic dermatitis. Use of EUCRISA administered twice daily in this age group is supported by data from two 28-day adequate, vehicle-controlled safety and efficacy trials (1,313 pediatric subjects ages 2 years to 17 years of whom 874 received EUCRISA), a 28-day open-label, safety and pharmacokinetics (PK) trial (137 subjects ages 3 months to less than 2 years who received EUCRISA), and another trial with an open-label period of up to 8 weeks (327 pediatric subjects ages 5 months to less than 18 years who received EUCRISA) [see Clinical Pharmacology (12.3) and Clinical Studies (14) ] .
The safety and effectiveness of EUCRISA in pediatric patients below the age of 3 months have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of EUCRISA did not include sufficient numbers of subjects age 65 and over to determine whether they respond differently from younger subjects.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Crisaborole is a phosphodiesterase 4 (PDE-4) inhibitor. PDE-4 inhibition results in increased intracellular cyclic adenosine monophosphate (cAMP) levels. The specific mechanism(s) by which crisaborole exerts its therapeutic action for the treatment of atopic dermatitis is not well defined.
12.2Pharmacodynamics Cardiac Electrophysiology At therapeutic doses, EUCRISA ointment is not expected to prolong QTc to any clinically relevant extent.
12.3Pharmacokinetics Absorption The PK of EUCRISA were investigated in 33 pediatric subjects 2 to 17 years of age with mild to moderate atopic dermatitis and a mean ± SD body surface area (BSA) involvement of 49 ± 20% (range 27% to 92%). In this study, subjects applied approximately 3 mg/cm 2 of EUCRISA ointment (dose range was approximately 6 g to 30 g per application) twice daily for 8 days. Plasma concentrations were quantifiable in all the subjects.
The mean ± SD maximum plasma concentration (C max ) and area under the concentration time curve from 0 to 12 hours post dose (AUC 0–12 ) for crisaborole on Day 8 were 127 ± 196 ng/mL and 949 ± 1240 ng h/mL, respectively. Systemic concentrations of crisaborole were at steady state by Day 8. Based on the ratios of AUC 0–12 between Day 8 and Day 1, the mean accumulation factor for crisaborole was 1.9.
The PK of EUCRISA were investigated in 13 subjects 4 months to less than 24 months of age. The mean ± SD C max and AUC 0–12 for crisaborole were 188 ± 100 ng/mL and 1164 ± 550 ng∙h/mL, respectively. Distribution Based on an in vitro study, crisaborole is 97% bound to human plasma proteins.
Elimination Metabolism Crisaborole is substantially metabolized into inactive metabolites. The major metabolite 5-(4-cyanophenoxy)-2-hydroxyl benzylalcohol (metabolite 1), is formed via hydrolysis; this metabolite is further metabolized into downstream metabolites, among which 5-(4-cyanophenoxy)-2-hydroxyl benzoic acid (metabolite 2), formed via oxidation, is also a major metabolite. PK of metabolites 1 and 2 were assessed in the PK study described above and the systemic concentrations were at or near steady state by Day 8.
Based on the ratios of AUC 0–12 between Day 8 and Day 1, the mean accumulation factors for metabolites 1 and 2 were 1.7 and 6.3, respectively. Excretion Renal excretion of metabolites is the major route of elimination. Drug Interaction Studies In vitro studies using human liver microsomes indicated that under the conditions of clinical use, crisaborole and metabolite 1 are not expected to inhibit cytochrome P450 (CYP) 1A2, 2B6, 2C8, 2C9, 2C19, 2D6, and 3A4.
In vitro human liver microsomes studies for metabolite 2 showed that it did not inhibit activities of CYP2C19, 2D6, and 3A4; was a weak inhibitor of CYP1A2 and 2B6; and a moderate inhibitor of CYP2C8 and 2C9. The most sensitive enzyme, CYP2C9, was further investigated in a clinical trial using warfarin as a CYP2C9 substrate. The results of this study showed no drug interaction potential.
In vitro studies in human hepatocytes showed that under the conditions of clinical use, crisaborole and metabolites 1 and 2 are not expected to induce CYP enzymes. In vitro studies showed that crisaborole and metabolite 1 did not inhibit the activities of uridine diphosphate (UDP)-glucuronosyltransferase (UGT) 1A1, 1A4, 1A6, 1A9, 2B7, and 2B15. Metabolite 2 did not inhibit UGT1A4, 1A6, 2B7, and 2B15.
Metabolite 2 showed weak inhibition of UGT1A1, however, no clinically significant drug interactions are expected between crisaborole (and its metabolites) and UGT1A1 substrates at therapeutic concentrations. Metabolite 2 showed moderate inhibition of UGT1A9 and may result in a moderate increase of the concentrations of sensitive UGT1A9 substrates. In vitro studies indicate that under the condition of clinical use, crisaborole and metabolites 1 and 2 are not expected to cause clinically significant interactions with substrates of P-glycoprotein and organic anion…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Crisaborole is a phosphodiesterase 4 (PDE-4) inhibitor. PDE-4 inhibition results in increased intracellular cyclic adenosine monophosphate (cAMP) levels. The specific mechanism(s) by which crisaborole exerts its therapeutic action for the treatment of atopic dermatitis is not well defined.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied EUCRISA is a white to off-white ointment containing 2% crisaborole and is supplied in 60 g and 100 g laminate tubes. 60 g tube: NDC 55724-211-21 100 g tube: NDC 55724-211-11
16.2Storage and Handling Store at 20°C–25°C (68°F–77°F); excursions permitted to 15°C–30°C (59°F–86°F). [see USP Controlled Room Temperature]. Keep tube tightly closed.
📦 Storage and Handling ▾
16.2Storage and Handling Store at 20°C–25°C (68°F–77°F); excursions permitted to 15°C–30°C (59°F–86°F). [see USP Controlled Room Temperature]. Keep tube tightly closed.
📋 Description ▾
11 DESCRIPTION EUCRISA contains 2% crisaborole (w/w) in a petrolatum-based, white to off-white ointment and is for topical use. The active ingredient, crisaborole, is a phosphodiesterase-4 (PDE-4) inhibitor. Crisaborole is described chemically as 5-(4-cyanophenoxy)-1,3-dihydro-1-hydroxy-[2,1]-benzoxaborole.
The empirical formula is C 14 H 10 BNO 3 and the molecular weight is 251.1 g/mol. The structural formula is represented below: Crisaborole drug substance is freely soluble in common organic solvents such as isopropyl alcohol and propylene glycol, and insoluble in water. Each gram of EUCRISA contains 20 mg of crisaborole in an ointment containing white petrolatum, propylene glycol, mono- and di-glycerides, paraffin, butylated hydroxytoluene, and edetate calcium disodium.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient or caregivers to read the FDA-approved patient labeling (Patient Information). Hypersensitivity Reactions Advise patients to discontinue EUCRISA and seek medical attention immediately if signs or symptoms of hypersensitivity occur [see Warnings and Precautions (5.1) ] . Administration Instructions Advise patients or caregivers that EUCRISA is for topical use only and is not for ophthalmic, oral, or intravaginal use.