
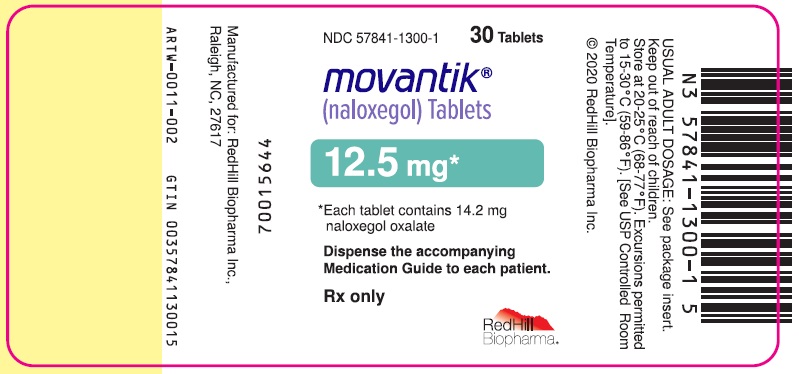
MOVANTIK naloxegol oxalate 12.5 mg Tablet, Film Coated, 90-count
🆔 Identity & classification
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Naloxegol is used to treat constipation caused by opiate (narcotic) pain medications in adults with chronic (ongoing) pain that is not caused by cancer. Naloxegol is in a class of medications called peripherally acting mu-opioid receptor antagonists. It works by protecting the bowel from the effects of opiate (narcotic) medications.
Read the full MedlinePlus article ↗- Opioid pain medications like oxycodone or hydrocodone attach to receptors throughout your body — including your gut — and slow down how quickly things move through your intestines....
- Why am I constipated from my pain medication, and how does Movantik help?
- Yes — you should stop regular laxatives before you begin Movantik. If after three days you still aren't getting enough relief, laxatives can be added back on an as-needed basis. Yo...
- Do I need to stop my laxatives before starting Movantik?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII B697894SGQ
Polyethylene glycol 400 is a clear, thick liquid made from petroleum-derived polymers. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII 8D4SNN7V92
Propyl gallate is a synthetic antioxidant derived from gallic acid. It prevents oils and fats in the medicine from oxidizing and spoiling, helping the product stay stable and effective during storage.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Movantik 12.5 mg 82625-8801-01 | Averitas | 30 tablets | $14.602 | — | Availability likely | — |
| Movantik 12.5 mgthis 57841-1300-02 | RedHill | 90 tablets | — | — | Discontinued | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 7786133 ↗ | Drug substance | — | Sep 16, 2028 |
| US 9012469 ↗ | Drug substance | — | Apr 2, 2032 |
| US 9012469 ↗ | Drug substance | — | Apr 2, 2032 |
| US 7786133 ↗ | Drug substance | — | Sep 16, 2028 |
Is there a generic version of this drug?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 57841-1300-01 | 30 TABLET, FILM COATED in 1 BOTTLE (57841-1300-1) | $14.60 / ea | $438.05 | 2020-10-01 | Discontinued by firm |
| 57841-1300-02 You're viewing this | 90 TABLET, FILM COATED in 1 BOTTLE (57841-1300-2) | — | — | 2020-10-01 | Discontinued by firm |
| 57841-1300-03 | 10 BLISTER PACK in 1 CARTON (57841-1300-3) / 10 TABLET, FILM COATED in 1 BLISTER PACK | — | — | 2020-10-01 | Discontinued by firm |
| 57841-1300-04 | 1 BLISTER PACK in 1 CARTON (57841-1300-4) / 3 TABLET, FILM COATED in 1 BLISTER PACK | — | — | 2020-10-01 | Discontinued by firm |
Pack size FAQ
What quantity is in NDC 57841-1300-02?
What is the difference between NDC 57841-1300-02 and NDC 57841-1300-04?
What NDC number is used to bill for this package of MOVANTIK naloxegol oxalate 12.5 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
What does the discontinued status mean for this NDC?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE MOVANTIK ® is indicated for the treatment of opioid-induced constipation (OIC) in adult patients with chronic non-cancer pain, including patients with chronic pain related to prior cancer or its treatment who do not require frequent (e.g., weekly) opioid dosage escalation. MOVANTIK is an opioid antagonist indicated for the treatment of opioid-induced constipation (OIC) in adult patients with chronic non-cancer pain, including patients with chronic pain related to prior cancer or its treatment who do not require frequent (e.g., weekly) opioid dosage escalation.
(1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Administration : Discontinue maintenance laxative therapy before starting MOVANTIK; may resume laxatives if patients have OIC symptoms after taking MOVANTIK for 3 days. (2.1) Alteration in analgesic dosing regimen prior to starting MOVANTIK is not required. (2.1) Patients receiving opioids for less than 4 weeks may be less responsive to MOVANTIK.
(2.1) Take on an empty stomach at least 1 hour prior to the first meal of the day or 2 hours after the meal. (2.1) For patients who are unable to swallow the MOVANTIK tablet whole, the tablet can be crushed and given orally or administered via nasogastric tube, see full prescribing information. (2.1) Avoid consumption of grapefruit or grapefruit juice.
(2.1 , 7.1) Discontinue if treatment with the opioid pain medication is also discontinued. (2.1) Recommended dosage : 25 mg once daily; if not tolerated, reduce to 12.5 mg once daily. (2.2) Renal Impairment (CLcr < 60 mL/min): 12.5 mg once daily; increase to 25 mg once daily if tolerated and monitor for adverse reactions.
(2.3 , 8.6)
2.1Administration Instructions Discontinue all maintenance laxative therapy prior to initiation of MOVANTIK. Laxative(s) can be used as needed if there is a suboptimal response to MOVANTIK after three days. Alteration in analgesic dosing regimen prior to initiating MOVANTIK is not required.
Patients receiving opioids for less than 4 weeks may be less responsive to MOVANTIK [see Clinical Studies (14) ] . Take MOVANTIK on an empty stomach at least 1 hour prior to the first meal of the day or 2 hours after the meal. For patients who are unable to swallow the MOVANTIK tablet whole, the tablet can be crushed to a powder, mixed with 4 ounces (120 mL) of water, and drunk immediately.
The glass should be refilled with 4 ounces (120 mL) of water, stirred and the contents drunk. MOVANTIK can also be administered via a nasogastric (NG) tube, as follows: Flush the NG tube with 1 ounce (30 mL) of water using a 60 mL syringe. Crush the tablet to a powder in a container and mix with approximately 2 ounces (60 mL) of water.
Draw up the mixture using the 60 mL syringe and administer the syringe contents through the NG tube. Add approximately 2 ounces (60 mL) of water to the same container used to prepare the dose of MOVANTIK. Draw up the water using the same 60 mL syringe and use all the water to flush the NG tube and any remaining medicine from the NG tube into the stomach.
Avoid consumption of grapefruit or grapefruit juice during treatment with MOVANTIK. Discontinue MOVANTIK if treatment with the opioid pain medication is also discontinued.
2.2Adult Dosage The recommended MOVANTIK dosage is 25 mg once daily in the morning. If patients are not able to tolerate MOVANTIK, reduce the dosage to 12.5 mg once daily [see Clinical Pharmacology (12.2) ] .
2.3Dosage in Adult Patients with Renal Impairment The starting dosage for patients with creatinine clearance (CLcr) <60 mL/min (i.e., patients with moderate, severe, or end-stage renal impairment) is 12.5 mg once daily. If this dosage is well tolerated but OIC symptoms continue, the dosage may be increased to 25 mg once daily taking into consideration the potential for markedly increased exposures in some patients with renal impairment and the increased risk of adverse reactions with higher exposures [see Use in Specific Populations (8.6) and Clinical Pharmacology (12.3) ] .
2.4Dosage Recommendations due to Drug Interactions Avoid concomitant use of MOVANTIK with moderate CYP3A4 inhibitor drugs (e.g., diltiazem, erythromycin, verapamil). If concurrent use is unavoidable, reduce the MOVANTIK dosage to 12.5 mg once daily and monitor for adverse reactions [see Drug Interactions (7.1) and Clinical Pharmacology (12.3) ] .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS MOVANTIK (naloxegol) is available in two strengths: Tablets: 12.5 mg supplied as mauve, oval, biconvex, film-coated, intagliated with “nGL” on one side and “12.5” on the other side. Tablets: 25 mg supplied as mauve, oval, biconvex, film-coated, intagliated with “nGL” on one side and “25” on the other side. Tablets: 12.5 mg and 25 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS MOVANTIK is contraindicated in: Patients with known or suspected gastrointestinal obstruction and patients at risk of recurrent obstruction, due to the potential for gastrointestinal perforation [see Warnings and Precautions (5.3) ] . Patients concomitantly using strong CYP3A4 inhibitors (e.g., clarithromycin, ketoconazole) because these medications can significantly increase exposure to naloxegol which may precipitate opioid withdrawal symptoms such as hyperhidrosis, chills, diarrhea, abdominal pain, anxiety, irritability, and yawning [see Drug Interactions (7.1) and Clinical Pharmacology (12.3) ] .
Patients who have had a known serious or severe hypersensitivity reaction to MOVANTIK or any of its excipients [see Adverse Reactions (6.2) ] . Patients with known or suspected gastrointestinal obstruction and at risk of recurrent obstruction. (4 , 5.3 ) Concomitant use with strong CYP3A4 inhibitors (e.g., clarithromycin, ketoconazole).
(4 , 7.1) Known serious or severe hypersensitivity reaction to MOVANTIK or any of its excipients. (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Opioid withdrawal : Consider the overall risk benefit in patients with disruptions to the blood-brain barrier. Monitor for symptoms of opioid withdrawal. (5.1) Severe abdominal pain and/or diarrhea : Monitor for the development of symptoms after initiating treatment with MOVANTIK and discontinue if severe symptoms develop.
Consider restarting MOVANTIK at 12.5 mg once daily if appropriate. (5.2) Gastrointestinal perforation : Consider the overall risk benefit in patients with known or suspected lesions of the GI tract. Monitor for severe, persistent or worsening abdominal pain; discontinue if development of symptoms.
(5.3)
5.1Opioid Withdrawal Clusters of symptoms consistent with opioid withdrawal, including hyperhidrosis, chills, diarrhea, abdominal pain, anxiety, irritability, and yawning have occurred in patients treated with MOVANTIK [see Adverse Reactions (6.1 )] . In addition, patients receiving methadone as therapy for their pain condition were observed in clinical trials to have a higher frequency of gastrointestinal adverse reactions that may have been related to opioid withdrawal than patients receiving other opioids [see Adverse Reactions (6.1) ] .
Patients having disruptions to the blood-brain barrier may be at increased risk for opioid withdrawal or reduced analgesia. Take into account the overall risk-benefit profile when using MOVANTIK in such patients. Monitor for symptoms of opioid withdrawal in such patients.
5.2Severe Abdominal Pain and/or Diarrhea Reports of severe abdominal pain and/or diarrhea have been reported, some of which resulted in hospitalization. Most of the cases of severe abdominal pain were reported in patients taking the 25 mg dosage. Symptoms generally occurred within a few days of initiation of MOVANTIK.
Monitor patients for the development of abdominal pain and/or diarrhea with MOVANTIK and discontinue therapy if severe symptoms occur. Consider restarting MOVANTIK at 12.5 mg once daily, if appropriate.
5.3Gastrointestinal Perforation Cases of gastrointestinal (GI) perforation have been reported with use of peripherally acting opioid antagonists, including MOVANTIK. Postmarketing cases of GI perforation, including fatal cases, were reported when MOVANTIK was used in patients at risk of GI perforation (e.g., infiltrative gastrointestinal tract malignancy, recent gastrointestinal tract surgery, diverticular disease including diverticulitis, ischemic colitis, or concomitantly treated with bevacizumab). MOVANTIK is contraindicated in patients with known or suspected gastrointestinal obstruction or in patients at risk of recurrent obstruction [see Contraindications (4) ] .
Take into account the overall risk-benefit profile when using MOVANTIK in patients with these conditions or other conditions which might result in impaired integrity of the gastrointestinal tract wall (e.g., Crohn’s disease). Monitor for the development of severe, persistent or worsening abdominal pain; discontinue MOVANTIK in patients who develop this symptom.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Serious and important adverse reactions described elsewhere in labeling include: Opioid withdrawal [see Warnings and Precautions (5.1) ] Severe abdominal pain and/or diarrhea [see Warnings and Precautions (5.2) ] Gastrointestinal perforation [see Warnings and Precautions (5.3) ] The most common adverse reactions in clinical trials (≥3%) are: abdominal pain, diarrhea, nausea, flatulence, vomiting, and headache. (6.1) To report SUSPECTED ADVERSE REACTIONS, contact RedHill at 1-833-237-4455 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The data described below reflect exposure to MOVANTIK in 1497 patients in clinical trials, including 537 patients exposed for greater than six months, and 320 patients exposed for 12 months. The safety data described in Table 1 are derived from two double-blind, placebo-controlled trials (Studies 1 and 2) in patients with OIC and non-cancer related pain [see Clinical Studies (14) ] .
Study 3 (n=302) was a safety extension study that allowed patients from Study 1 to continue the same blinded treatment for an additional 12 weeks. Safety data for patients in Study 3 are similar to those listed in Table 1. Study 4 (n=844) was a Phase 3, 52-week, multi-center, open-label, randomized, parallel group, safety and tolerability study of naloxegol versus usual care treatment for OIC (as determined by the investigator and excluding peripheral opioid antagonists) in patients with non-cancer related pain.
The population enrolled in Study 4 was similar to that of the other studies. Eligible patients were randomized in a 2:1 ratio to receive either naloxegol 25 mg once daily or usual care treatment for OIC. The most commonly used laxatives in the usual care group were rectal stimulants (e.g., bisacodyl), oral stimulants (e.g., senna), and oral osmotics (e.g., macrogol, magnesium).
Safety data for patients in Study 4 are similar to those listed in Table 1. Table 1 lists adverse reactions in pooled Studies 1 and 2 occurring in ≥3% of patients receiving MOVANTIK 12.5 mg or 25 mg and at an incidence greater than placebo. Table 1.
Adverse Reactions Adverse reactions occurring in ≥3% of patients receiving MOVANTIK 12.5 mg or 25 mg and at an incidence greater than placebo. in Patients with OIC and Non-Cancer Pain (Studies 1 and 2) Adverse Reaction MOVANTIK 25 mg (n=446) MOVANTIK 12.5 mg (n=441) Placebo (n=444) Abdominal Pain Includes: abdominal pain, abdominal pain upper, abdominal pain lower, and gastrointestinal pain. 21% 12% 7% Diarrhea 9% 6% 5% Nausea 8% 7% 5% Flatulence 6% 3% 3% Vomiting 5% 3% 4% Headache 4% 4% 3% Hyperhidrosis 3% <1% <1% Opioid Withdrawal Possible opioid withdrawal, defined as at least three adverse reactions potentially related to opioid withdrawal that occurred on the same day and were not all related to the gastrointestinal system, occurred in less than 1% (1/444) of placebo subjects, 1% (5/441) receiving MOVANTIK 12.5 mg, and 3% (14/446) receiving MOVANTIK 25 mg in Studies 1 and 2 regardless of maintenance opioid treatment.
Symptoms included but were not limited to hyperhidrosis, chills, diarrhea, abdominal pain, anxiety, irritability, and yawning. Patients receiving methadone as therapy for their pain condition were observed in Studies 1 and 2 to have a higher frequency of gastrointestinal adverse reactions than patients receiving other opioids [39% (7/18) vs. 26% (110/423) in the 12.5 mg group; 75% (24/32) vs.
34% (142/414) in the 25 mg group].
6.2Postmarketing Experience The following adverse reactions have been identified during post-approval use of MOVANTIK. Because reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably e…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Moderate CYP3A4 inhibitors (e.g., diltiazem, erythromycin, verapamil) : Increased naloxegol concentrations; avoid concomitant use; if unavoidable, reduce dosage to 12.5 mg once daily and monitor for adverse reactions. (2.4 , 7.1) Strong CYP3A4 inducers (e.g., rifampin) : Decreased concentrations of naloxegol; concomitant use is not recommended. (7.1) Other opioid antagonists : Potential for additive effect and increased risk of opioid withdrawal; avoid concomitant use.
(7.1)
7.1Effects of Other Drugs on MOVANTIK Table 2 displays the effects of other drugs on MOVANTIK. Table 2. Effects of Other Drugs on MOVANTIK Concomitant Agent Mechanism of Action Clinical Recommendation CYP3A4 Inhibitors Strong CYP3A4 inhibitors (e.g., ketoconazole, itraconazole, clarithromycin) Increase plasma naloxegol concentrations and may increase the risk of adverse reactions [see Clinical Pharmacology (12.3) ].
Use with strong CYP3A4 inhibitors is contraindicated [see Contraindications (4) ] . Moderate CYP3A4 inhibitors (e.g., diltiazem, erythromycin, verapamil) Avoid use with moderate CYP3A4 inhibitors; if unavoidable, decrease the dosage of MOVANTIK to 12.5 mg once daily and monitor for adverse reactions [see Dosage and Administration (2.4) ] . Weak CYP3A4 inhibitors (e.g., quinidine, cimetidine) Clinically significant increases in naloxegol concentrations are not expected.
No dosage adjustments are necessary. Grapefruit or grapefruit juice The effect of grapefruit juice varies widely among brands and is concentration-, dose-, and preparation-dependent. Studies have shown that it can be classified as a “strong CYP3A inhibitor” when a certain preparation was used (e.g., high dose, double strength) or as a “moderate CYP3A inhibitor” when another preparation was used (e.g., low dose, single strength).
Can increase plasma naloxegol concentrations. Avoid consumption of grapefruit or grapefruit juice during treatment with MOVANTIK [see Dosage and Administration (2.1) ] . CYP3A4 Inducers Strong CYP3A4 inducers (e.g., rifampin, carbamazepine, St.
John’s Wort) Significantly decrease plasma naloxegol concentrations and may decrease the efficacy of MOVANTIK [see Clinical Pharmacology (12.3) ] . Use with strong CYP3A4 inducers is not recommended . Other Drug Interactions Other opioid antagonists Potential for additive effect of opioid receptor antagonism and increased risk of opioid withdrawal.
Avoid use of MOVANTIK with another opioid antagonist.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy : May precipitate opioid withdrawal in pregnant women and the fetus. (8.1) Lactation : Breastfeeding not recommended. (8.2) Hepatic Impairment : Avoid in severe impairment. (8.7)
8.1Pregnancy Risk Summary Limited available data with MOVANTIK use in pregnant women are insufficient to inform a drug associated risk of adverse developmental outcomes. MOVANTIK may precipitate opioid withdrawal in the pregnant women and the fetus (see Clinical Considerations ) . In animal development studies, no effects on embryo-fetal development were observed following administration of naloxegol in pregnant rats during the period of organogenesis at doses up to 1452 times the human AUC (area under the plasma concentration-time curve) at the maximum recommended human dose.
No effects on embryo-fetal development were observed following administration of naloxegol in pregnant rabbits during the period of organogenesis at doses up to 409 times the human AUC at the maximum recommended human dose. The estimated background risk of major birth defects and miscarriage for the indicated populations are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically-recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Maternal and Fetal/Neonatal adverse reactions The use of MOVANTIK may be associated with opioid withdrawal in the pregnant woman and the fetus. Data Animal Data Oral administration of up to 750 mg/kg/day naloxegol in rats (1452 times the human AUC at the maximum recommended human dose) and 450 mg/kg/day naloxegol in rabbits (409 times the human AUC at the maximum recommended human dose) during the period of organogenesis produced no adverse effects on embryo-fetal development.
Oral administration of up to 500 mg/kg/day in rats (195 times the maximum recommended human dose based on body surface area) during the period of organogenesis through lactation produced no adverse effects on parturition or the offspring.
8.2Lactation There are no data on the presence of naloxegol in human milk, the effects in nursing infants, or the effects on milk production. Naloxegol is present in rat milk (see Data ). Because of the potential for adverse reactions, including opioid withdrawal in breastfed infants, advise women that breastfeeding is not recommended during treatment with MOVANTIK.
Data Following oral administration of naloxegol in lactating rats, concentrations of naloxegol in milk were approximately 3- to 4-fold higher than concentrations of naloxegol in maternal plasma. Naloxegol was detected in plasma from pups.
8.4Pediatric Use The safety and effectiveness of MOVANTIK have not been established in pediatric patients.
8.5Geriatric Use Of the total number of subjects in clinical studies of MOVANTIK, 11% were 65 and over, while 2% were 75 and over. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. MOVANTIK exposure was higher in elderly healthy Japanese subjects compared to young subjects [see Clinical Pharmacology (12.3) ] .
No dosage adjustment is needed in elderly patients.
8.6Renal Impairment Some subjects with creatinine clearance (CLcr) values <60 mL/minute (i.e., moderate, severe, or end-stage renal disease) were shown to exhibit markedly higher systemic exposure of naloxegol compared to subjects with normal renal function. The reason for these high exposures is not understood. However, as the risk of adverse reactions increases with systemic exposure, a lower starting dosage of 12.5 mg once daily is recommended.
No dosage adjustment is needed in patients with mild ren…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Limited available data with MOVANTIK use in pregnant women are insufficient to inform a drug associated risk of adverse developmental outcomes. MOVANTIK may precipitate opioid withdrawal in the pregnant women and the fetus (see Clinical Considerations ) . In animal development studies, no effects on embryo-fetal development were observed following administration of naloxegol in pregnant rats during the period of organogenesis at doses up to 1452 times the human AUC (area under the plasma concentration-time curve) at the maximum recommended human dose.
No effects on embryo-fetal development were observed following administration of naloxegol in pregnant rabbits during the period of organogenesis at doses up to 409 times the human AUC at the maximum recommended human dose. The estimated background risk of major birth defects and miscarriage for the indicated populations are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically-recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Maternal and Fetal/Neonatal adverse reactions The use of MOVANTIK may be associated with opioid withdrawal in the pregnant woman and the fetus. Data Animal Data Oral administration of up to 750 mg/kg/day naloxegol in rats (1452 times the human AUC at the maximum recommended human dose) and 450 mg/kg/day naloxegol in rabbits (409 times the human AUC at the maximum recommended human dose) during the period of organogenesis produced no adverse effects on embryo-fetal development.
Oral administration of up to 500 mg/kg/day in rats (195 times the maximum recommended human dose based on body surface area) during the period of organogenesis through lactation produced no adverse effects on parturition or the offspring.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of MOVANTIK have not been established in pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of subjects in clinical studies of MOVANTIK, 11% were 65 and over, while 2% were 75 and over. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. MOVANTIK exposure was higher in elderly healthy Japanese subjects compared to young subjects [see Clinical Pharmacology (12.3) ] .
No dosage adjustment is needed in elderly patients.
🆘 Overdosage ▾
10 OVERDOSAGE In a clinical study of patients with OIC a daily dose of 50 mg (twice the recommended dosage), administered over 4 weeks, was associated with an increased incidence of GI adverse reactions, such as abdominal pain, diarrhea, and nausea. These adverse reactions frequently occurred within 1-2 days after dosing. No antidote is known for naloxegol.
Dialysis was noted to be ineffective as a means of elimination in a clinical study in patients with renal failure. If a patient on opioid therapy receives an overdose of naloxegol, the patient should be monitored closely for potential evidence of opioid withdrawal symptoms such as chills, rhinorrhea, diaphoresis, or reversal of central analgesic effect. Base treatment on the degree of opioid withdrawal symptoms, including changes in blood pressure and heart rate, and on the need for analgesia.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Naloxegol is an antagonist of opioid binding at the mu-opioid receptor. When administered at the recommended dose levels, naloxegol functions as a peripherally-acting mu-opioid receptor antagonist in tissues, such as the gastrointestinal tract, thereby decreasing the constipating effects of opioids. Naloxegol is a PEGylated derivative of naloxone and is a substrate for the P-glycoprotein transporter (P-gp).
Also, the presence of the PEG moiety in naloxegol reduces its passive permeability as compared with naloxone. Due to the reduced permeability and increased efflux of naloxegol across the blood-brain barrier, related to P-gp substrate properties, the CNS penetration of naloxegol is expected to be negligible at the recommended dose levels limiting the potential for interference with centrally mediated opioid analgesia.
12.2Pharmacodynamics Use of opioids induces slowing of gastrointestinal motility and transit. Antagonism of gastrointestinal mu-opioid receptors by naloxegol inhibits opioid-induced delay of gastrointestinal transit time. Effect on Cardiac Repolarization In a randomized, double-blind, 4-way cross-over thorough QTc prolongation study with moxifloxacin as a positive control, a single 25 mg therapeutic dose or a 150 mg dose (6 times the maximum recommended dosage) of naloxegol did not have an effect on the QTc interval compared to placebo.
Changes in heart rate, RR, PR, and QRS ECG intervals were similar between placebo and naloxegol 25 or 150 mg. Exposure Response Analysis The exposure-response analysis for adverse events showed that the probability of experiencing abdominal pain increased with increasing naloxegol exposure over the dose range of 12.5 mg to 25 mg once a day. The exposure-response analysis for efficacy conducted using the definition of response in the clinical trials [see Clinical Studies (14) ] indicated that response was similar over this dose range.
12.3Pharmacokinetics Absorption Following oral administration, MOVANTIK is absorbed with peak concentrations (C max ) achieved at less than 2 hours. In a majority of subjects, a secondary plasma concentration peak of naloxegol was observed approximately 0.4 to 3 hours after the first peak. Across the range of doses evaluated, peak plasma concentration and area under the plasma concentration-time curve (AUC) increased in a dose-proportional or almost dose-proportional manner.
Accumulation was minimal following multiple daily doses of naloxegol. MOVANTIK as a crushed tablet mixed in water, given orally or administered through a nasogastric tube into the stomach, provides systemic naloxegol concentrations that are comparable to the whole tablet, with a median t max of 0.75 and 1.5 hours (range 0.25 to 5 hours) for the crushed tablet given orally and the crushed tablet given via nasogastric (NG) tube, respectively [see Dosage and Administration (2.2) ] . Food Effects A high-fat meal increased the extent and rate of naloxegol absorption.
The C max and AUC were increased by approximately 30% and 45%, respectively. In clinical trials, naloxegol was dosed on an empty stomach approximately 1 hour prior to the first meal in the morning. Distribution The mean apparent volume of distribution during the terminal phase (Vz/F) in healthy volunteers ranged from 968 L to 2140 L across dosing groups and studies.
Plasma protein binding of naloxegol in humans was low (~4.2%). Metabolism Naloxegol is metabolized primarily by the CYP3A enzyme system. In a mass balance study in humans, a total of 6 metabolites were identified in plasma, urine, and feces.
These metabolites were formed via N-dealkylation, O-demethylation, oxidation, and partial loss of the PEG chain. Human metabolism data suggests absence of major metabolites. The activity of the metabolites at the opioid receptor has not been determined.
Excretion Following oral administration of radio-labeled naloxegol, 68% and 16% of total administered dose were recover…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Naloxegol is an antagonist of opioid binding at the mu-opioid receptor. When administered at the recommended dose levels, naloxegol functions as a peripherally-acting mu-opioid receptor antagonist in tissues, such as the gastrointestinal tract, thereby decreasing the constipating effects of opioids. Naloxegol is a PEGylated derivative of naloxone and is a substrate for the P-glycoprotein transporter (P-gp).
Also, the presence of the PEG moiety in naloxegol reduces its passive permeability as compared with naloxone. Due to the reduced permeability and increased efflux of naloxegol across the blood-brain barrier, related to P-gp substrate properties, the CNS penetration of naloxegol is expected to be negligible at the recommended dose levels limiting the potential for interference with centrally mediated opioid analgesia.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING MOVANTIK (naloxegol) tablets are supplied as: NDC 57841-1300-1: 12.5 mg, bottle of 30 tablets NDC 57841-1300-2: 12.5 mg, bottle of 90 tablets NDC 57841-1300-3: 12.5 mg, unit dose blister carton of 100 tablets (for HUD only) NDC 57841-1301-1: 25 mg, bottle of 30 tablets NDC 57841-1301-2: 25 mg, bottle of 90 tablets NDC 57841-1301-3: 25 mg, unit dose blister carton of 100 tablets (for HUD only) Storage Store MOVANTIK at 20-25°C (68-77°F). Excursions permitted to 15-30°C (59-86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION MOVANTIK (naloxegol), an opioid antagonist, contains naloxegol oxalate as the active ingredient. (Naloxegol is a PEGylated derivative of naloxone.) The chemical name for naloxegol oxalate is: (5α,6α)-17-allyl-6-(2,5,8,11,14,17,20-heptaoxadocosan-22-yloxy)-4,5-epoxymorphinan-3,14-diol oxalate. The structural formula is: The empirical formula for naloxegol oxalate is C 34 H 53 NO 11 .C 2 H 2 O 4 and the molecular weight is 742.
Naloxegol oxalate is a white to off-white powder, with high aqueous solubility across the physiologic pH range. MOVANTIK (naloxegol) tablets for oral use contain 14.2 mg and 28.5 mg of naloxegol oxalate, respectively, equivalent to 12.5 mg and 25 mg of naloxegol. Excipients in tablet core are: mannitol, cellulose microcrystalline, croscarmellose sodium, magnesium stearate, and propyl gallate.
Excipients in tablet coat are: hypromellose, titanium dioxide, polyethylene glycol, iron oxide red, and iron oxide black. Chemical structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Administration Advise patients to: Discontinue all maintenance laxative therapy prior to initiation of MOVANTIK. Laxative(s) can be used as needed if there is a suboptimal response to MOVANTIK after three days.
Take MOVANTIK on an empty stomach at least 1 hour prior to the first meal of the day or 2 hours after the meal. Discontinue MOVANTIK if treatment with the opioid pain medication is also discontinued. Avoid consumption of grapefruit or grapefruit juice during treatment with MOVANTIK.
Inform their healthcare provider if their opioid pain medication is discontinued. Inform their healthcare provider if they are unable to tolerate MOVANTIK, so a dosage adjustment can be considered. If patients are unable to swallow the MOVANTIK tablet whole , the tablet can be crushed to a powder, mixed with water and administered orally or via a nasogastric (NG) tube, as described in the Medication Guide.
Drug Interactions Advise patients to tell their healthcare provider when they start or stop taking any concomitant medications. Strong CYP3A4 inhibitors (e.g., clarithromycin, ketoconazole) are contraindicated with MOVANTIK, and other CYP3A4 enzyme modulating drugs can alter MOVANTIK exposure [see Contraindications (4) and Drug Interactions (7.1)] . Opioid Withdrawal Advise patients that clusters of symptoms consistent with opioid withdrawal may occur while taking MOVANTIK, including sweating, chills, diarrhea, abdominal pain, anxiety, irritability, and yawning.
Inform patients taking methadone as therapy for their pain condition that they may be more likely to have gastrointestinal adverse reactions such as abdominal pain and diarrhea that may be related to opioid withdrawal, than patients receiving other opioids [see Warnings and Precautions (5.1) ]. Severe Abdominal Pain and/or Diarrhea Advise patients that symptoms may occur after starting treatment. The patient should discontinue MOVANTIK and contact their healthcare provider if they develop severe abdominal pain and/or diarrhea [see Warnings and Precautions (5.2) ] .
Gastrointestinal Perforation Advise patients to discontinue MOVANTIK and promptly seek medical attention if they develop unusually severe, persistent or worsening abdominal pain [see Warnings and Precautions (5.3) ] . Pregnancy Advise females of reproductive potential, who become pregnant or are planning to become pregnant that the use of MOVANTIK during pregnancy may precipitate opioid withdrawal in the pregnant women and the fetus [see Use in Specific Populations (8.1) ] . Lactation Advise females that breastfeeding is not recommended during treatment with MOVANTIK [see Use in Specific Populations (8.2) ] .
MOVANTIK is a registered trademark of the AstraZeneca Group of companies and used under license by RedHill Biopharma Inc. Distributed by: RedHill Biopharma Inc., Raleigh, NC 27617 © 2020 RedHill Biopharma Inc.
💬 Medication Guide ▾
MEDICATION GUIDE MOVANTIK ® (mo-van-tic) (naloxegol) tablets, for oral use Read this Medication Guide before you start taking MOVANTIK and each time you get a refill. There may be new information. This information does not take the place of talking with your healthcare provider about your medical condition or your treatment.
What is the most important information I should know about MOVANTIK? MOVANTIK may cause serious side effects, including: Opioid withdrawal. You may have symptoms of opioid withdrawal during treatment with MOVANTIK including sweating, chills, diarrhea, stomach pain, anxiety, irritability, and yawning.
If you take methadone to treat your pain, you may be more likely to have stomach pain and diarrhea than people who do not take methadone. Tell your health care provider if you have any of these symptoms. Severe stomach pain or diarrhea, or both severe stomach pain and diarrhea.
Severe stomach pain and diarrhea can happen when you take MOVANTIK. These problems can happen within a few days after you start taking MOVANTIK and can lead to hospitalization. Stop taking MOVANTIK and call your healthcare provider right away if you have severe stomach pain or diarrhea, or both severe stomach pain and diarrhea.
Tear in your stomach or intestinal wall (perforation). Stomach pain that is severe can be a sign of a serious medical condition. If you have stomach pain that gets worse or does not go away, stop taking MOVANTIK and get emergency medical help right away.
What is MOVANTIK? MOVANTIK is a prescription medicine used to treat constipation that is caused by prescription pain medicines called opioids, in adults with long-lasting (chronic) pain that is not caused by active cancer. It is not known if MOVANTIK is safe and effective in children.
Who should not take MOVANTIK? Do not take MOVANTIK if you: have a bowel blockage (intestinal obstruction) or have a history of bowel blockage. are allergic to MOVANTIK or any of the ingredients in MOVANTIK. See the end of this Medication Guide for a complete list of ingredients in MOVANTIK.
MOVANTIK can interact with certain other medicines and cause side effects, including opioid withdrawal symptoms such as sweating, chills, diarrhea, stomach pain, anxiety, irritability, and yawning. Tell your healthcare provider or pharmacist before you start or stop any medicines during treatment with MOVANTIK. What should I tell my healthcare provider before taking MOVANTIK?
Before you take MOVANTIK, tell your healthcare provider about all of your medical conditions, including if you: have any stomach or bowel (intestines) problems, including inflammation in parts of the large intestine (diverticulitis), inflammation and injury of the intestines caused by reduced blood flow (ischemic colitis), or cancer of the stomach or bowel. have had recent surgery on the stomach or intestines. have kidney problems. have liver problems. are pregnant or plan to become pregnant. Taking MOVANTIK during pregnancy may cause opioid withdrawal symptoms in you or your unborn baby.
Tell your healthcare provider right away if you become pregnant during treatment with MOVANTIK. are breastfeeding or plan to breastfeed. It is not known if MOVANTIK passes into your breast milk. taking MOVANTIK while you are breastfeeding may cause opioid withdrawal in your baby. You and your healthcare provider should decide if you will take MOVANTIK or breastfeed.
You should not breastfeed if you take MOVANTIK. Tell your healthcare provider about all of the medicines you take , including prescription and over-the-counter medicines, vitamins, and herbal supplements. Other medicines may affect the way MOVANTIK works.
Especially tell your healthcare provider if you take a medicine called bevacizumab. How should I take MOVANTIK? Take MOVANTIK exactly as your healthcare provider tells you.
Take your prescribed dose of MOVANTIK 1 time each day, on an empty stomach, at least 1 hour before your first meal of the day or 2 hours after the meal. If…