
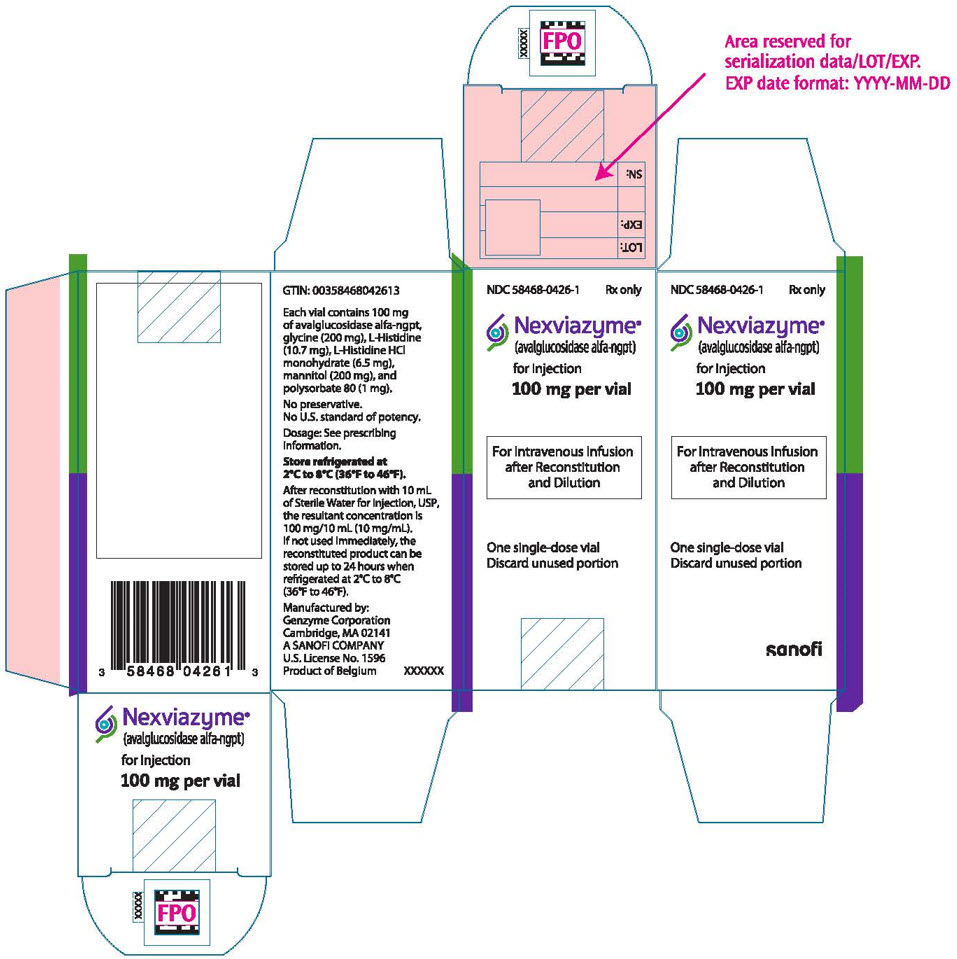
Nexviazyme avalglucosidase alfa-ngpt 100 mg/10mL Injection, Powder, Lyophilized, For Solution — NDC 58468-0426-1 (Billing 58468-0426-01)
This is a package of Nexviazyme avalglucosidase alfa-ngpt 100 mg/10mL Injection, Powder, Lyophilized, For Solution from Genzyme Corporation, marketed since Aug 2021 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 58468-0426-1 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 58468 labeler · 0426 product · 1 package
- Package marketed since
- Aug 6, 2021
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 5846804261 3
- Medicaid fills, this package
- 545 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 082556
- GCN: 50008
- GPI-14 (Medi-Span): 30907722552120
- HICL (First Databank): 047521
- AHFS class code: 44:00.00.00
- RxCUI (RxNorm): 2565818
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Hydrolytic Lysosomal Glycogen-specific Enzyme class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Avalglucosidase alfa-ngpt injection is used to treat the symptoms of Pompe disease (an inherited condition in which the body lacks a certain enzyme to break down glycogen in the body). Avalglucosidase alfa-ngpt injection is in a class of medications called enzymes. It works by providing the enzyme to break down glycogen in the body.
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $2,137.02 | $21,370.16 / 10 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J0219 | $83.945 / J0219 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Oct 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 58468-0426-01 You're viewing this Main listing | 1 VIAL, SINGLE-DOSE in 1 CARTON / 10 mL in 1 VIAL, SINGLE-DOSE | 2021-08-06 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Nexviazyme 100 mg/10mLthis 58468-0426-01 | Genzyme | 1 vial | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Purple Book · refreshed Oct 5, 2026
- CMS NADAC weekly file
Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Why the date isn’t exact: Biosimilar timing can change because patents may be challenged, settled, licensed, added or removed, and litigation can move the real date earlier or later.
🛈 What do these terms mean?
- Biologic patent
- A patent the reference product’s maker has publicly listed. A biosimilar generally can’t launch until these expire — unless they’re invalidated or resolved in a settlement.
- Reference-product exclusivity
- A flat 12 years of FDA market protection from the biologic’s first licensure (the BPCIA). No biosimilar can be licensed before it ends, regardless of patents.
- Interchangeable exclusivity
- The first interchangeable biosimilar can earn a period as the only interchangeable version (pharmacists can substitute it without the prescriber).
- Earliest biosimilar (LOE)
- The latest of all the dates above — the soonest a biosimilar can realistically reach the market. Litigation and settlements can move it earlier.
Biologics have no small-molecule “generics” — competition comes from FDA-licensed biosimilars, tracked in the FDA Purple Book.
| Code | What it grants | Expires |
|---|---|---|
| RefProduct | Reference-product exclusivity (12-year, BPCIA) — no biosimilar can be licensed before this date | Aug 6, 2033 |
Is there a biosimilar for NEXVIAZYME 100 MG VIAL?
Why do different websites show different biosimilar dates?
Can a biosimilar launch before the last patent expires?
What does “current Purple Book estimate” mean?
What does “FDA listed” mean?
What does a patent or protection date mean here?
Where does this data come from?
- FDA Purple Book · refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
200 mg / 10 mL
UNII TE7660XO1C
Glycine is an amino acid used in medicines as a buffer to help stabilize pH and improve taste. It may also serve as a filler or binder to give the product proper form and consistency.
-
10.7 mg / 10 mL
UNII 4QD397987E
An amino acid used as a buffer and stabilizer in medications. It helps maintain the pH balance and protects the active drug from breaking down during storage and use.
-
6.5 mg / 10 mL
UNII X573657P6P
Histidine monohydrochloride monohydrate is an amino acid salt used as a buffer in medicines. It helps maintain the proper acidity level of liquid formulations to keep the drug stable and effective.
-
200 mg / 10 mL
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
1 mg / 10 mL
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Genzyme Corporation labeler code 58468
- Cerdelga eliglustat 84 mg Capsule NDC 58468-0220-1
- Cablivi caplacizumab Kit NDC 58468-0225-1
- Wayrilz rilzabrutinib 400 mg Tablet, Film Coated NDC 58468-0251-5
- Qfitlia fitusiran 20 mg/.2mL Injection, Solution NDC 58468-0347-1
- Qfitlia fitusiran 50 mg/.5mL Injection, Solution NDC 58468-0348-1
- Campath ALEMTUZUMAB 30 mg/mL Injection NDC 58468-0357-1
- Cerezyme IMIGLUCERASE 40 U/mL Injection, Powder, Lyophilized, For Solution NDC 58468-4663-1
- Alglucosidase alfa 5 mg/mL Solution NDC 58468-5005-1
- Avalglucosidase alfa 10 mg/mL Solution NDC 58468-5006-1
- IMIGLUCERASE 40 U/mL Injection, Powder, Lyophilized, For Solution NDC 58468-5010-1
- AVALGLUCOSIDASE ALFA 100 mg/10mL Injection, Powder, Lyophilized, For Solution NDC 58468-5011-1
- THYROTROPIN ALFA .9 mg/mL Injection, Powder, Lyophilized, For Solution NDC 58468-5015-1
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SEVERE HYPERSENSITIVITY REACTIONS, INFUSION-ASSOCIATED REACTIONS, and RISK OF ACUTE CARDIORESPIRATORY FAILURE IN SUSCEPTIBLE PATIENTS WARNING: SEVERE HYPERSENSITIVITY REACTIONS, INFUSION-ASSOCIATED REACTIONS, and RISK OF ACUTE CARDIORESPIRATORY FAILURE IN SUSCEPTIBLE PATIENTS See full prescribing information for complete boxed warning. Hypersensitivity Reactions Including Anaphylaxis Appropriate medical monitoring and support measures, including cardiopulmonary resuscitation equipment, should be readily available.
If a severe hypersensitivity reaction occurs, discontinue NEXVIAZYME immediately and initiate appropriate medical treatment. ( 5.1 ) Infusion-Associated Reactions (IARs) If severe IARs occur, consider immediate discontinuation and initiation of appropriate medical treatment. ( 5.2 ) Risk of Acute Cardiorespiratory Failure in Susceptible Patients Patients susceptible to fluid volume overload, or those with acute underlying respiratory illness or compromised cardiac or respiratory function, may be at risk of serious exacerbation of their cardiac or respiratory status during NEXVIAZYME infusion.
( 5.3 ) Hypersensitivity Reactions Including Anaphylaxis Patients treated with NEXVIAZYME have experienced life-threatening hypersensitivity reactions, including anaphylaxis. Appropriate medical monitoring and support measures, including cardiopulmonary resuscitation equipment, should be readily available during NEXVIAZYME administration. If a severe hypersensitivity reaction (e.g., anaphylaxis) occurs, discontinue NEXVIAZYME immediately and initiate appropriate medical treatment.
In patients with severe hypersensitivity reactions, a desensitization procedure to NEXVIAZYME may be considered [see Warnings and Precautions (5.1) ] . Infusion-Associated Reactions (IARs) Patients treated with NEXVIAZYME have experienced severe IARs. If severe IARs occur, consider immediate discontinuation of NEXVIAZYME, initiation of appropriate medical treatment, and the benefits and risks of readministering NEXVIAZYME following severe IARs.
Patients with an acute underlying illness at the time of NEXVIAZYME infusion may be at greater risk for IARs. Patients with advanced Pompe disease may have compromised cardiac and respiratory function, which may predispose them to a higher risk of severe complications from IARs [see Warnings and Precautions (5.2) ] . Risk of Acute Cardiorespiratory Failure in Susceptible Patients Patients susceptible to fluid volume overload, or those with acute underlying respiratory illness or compromised cardiac or respiratory function for whom fluid restriction is indicated may be at risk of serious exacerbation of their cardiac or respiratory status during NEXVIAZYME infusion.
More frequent monitoring of vitals should be performed during NEXVIAZYME infusion in such patients [see Warnings and Precautions (5.3) ] .
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE NEXVIAZYME is indicated for the treatment of patients 1 year of age and older with late-onset Pompe disease (lysosomal acid alpha-glucosidase [GAA] deficiency). NEXVIAZYME is a hydrolytic lysosomal glycogen-specific enzyme indicated for the treatment of patients 1 year of age and older with late-onset Pompe disease (lysosomal acid alpha-glucosidase [GAA] deficiency). ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Consider administering antihistamines, antipyretics, and/or corticosteroids prior to NEXVIAZYME administration to reduce the risk of IARs. ( 2.1 ) NEXVIAZYME is administered as intravenous infusion. For patients weighing ( 2.2 ): ≥30 kg, the recommended dosage is 20 mg/kg (of actual body weight) every two weeks. <30 kg, the recommended dosage is 40 mg/kg (of actual body weight) every two weeks.
See the full prescribing information for dosage modifications due to hypersensitivity reactions or IARs. ( 2.3 ) Must be reconstituted and diluted prior to use. ( 2.4 ) For instructions on storage and administration, see full prescribing information.
( 2.5 , 2.6 )
2.1Recommendations Prior to NEXVIAZYME Treatment Prior to NEXVIAZYME administration, consider pretreating with antihistamines, antipyretics, and/or corticosteroids [see Warnings and Precautions (5.1 , 5.2) ] . NEXVIAZYME must be reconstituted and diluted prior to use [see Dosage and Administration (2.4) ] . Appropriate medical monitoring and support measures, including cardiopulmonary resuscitation equipment, should be readily available during NEXVIAZYME administration.
2.2Recommended Dosage and Administration NEXVIAZYME is administered as intravenous infusion. For patients weighing: 30 kg or more- the recommended dosage is 20 mg/kg (of actual body weight) every two weeks [see Dosage and Administration (2.6) ] Less than 30 kg- the recommended dosage is 40 mg/kg (of actual body weight) every two weeks [see Dosage and Administration (2.6) ] The initial recommended infusion rate is 1 mg/kg/hour. Gradually increase the infusion rate every 30 minutes if there are no signs of infusion-associated reactions (IARs) [see Dosage and Administration (2.6) ] .
If one or more doses are missed, restart NEXVIAZYME treatment as soon as possible, maintaining the 2 week interval between infusions thereafter.
2.3Administration Modifications Due to Hypersensitivity Reactions and/or Infusion-Associated Reactions In the event of a severe hypersensitivity reaction (e.g., anaphylaxis) or severe infusion-associated reaction (IAR), immediately discontinue NEXVIAZYME administration and initiate appropriate medical treatment. For additional recommendations in the event of a severe hypersensitivity reaction or IAR, [ see Warnings and Precautions (5.1 , 5.2) ] . In the event of a mild to moderate hypersensitivity reaction or a mild to moderate IAR, consider temporarily holding the infusion for 30 minutes or slowing the infusion rate by 50% [see Dosage and Administration (2.6) ] and initiating appropriate medical treatment [see Warnings and Precautions (5.1 , 5.2) ] .
If symptoms persist for longer than 30 minutes despite holding or slowing the infusion, stop the infusion and monitor the patient. Consider re-initiating the infusion on the same day when symptoms subside at 50% of the rate at which the reaction occurred with appropriate pretreatment. If symptoms subside after holding the infusion, resume infusion at 50% of the rate at which the reaction occurred, and subsequently increase the infusion rate every 15 to 30 minutes by 50% as tolerated.
Alternatively, if symptoms subside after slowing the infusion, complete the infusion at the reduced rate as tolerated. Starting with the next infusion, increase the infusion rate until the infusion rate at which the reaction occurred is reached. Consider continuing to increase the infusion rate in a stepwise manner until reaching the recommended infusion rate.
Closely monitor the patient.
2.4Reconstitution and Dilution Instructions Reconstitute and dilute NEXVIAZYME in the following manner. Use aseptic technique during preparation. Reconstitute the Lyophilized Powder Determine the number of NEXVIAZYME vials to be reconstituted based on actual body weight in kg and the recommended dose [see Dosage and Administration (2.2) ] .
Round the number of vials up to the next whole number. Remove the required number of NEXVIAZYME vials from the… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS For injection: 100 mg of avalglucosidase alfa-ngpt as a white to pale-yellow lyophilized powder in a single-dose vial for reconstitution. For injection: 100 mg of avalglucosidase alfa-ngpt as a lyophilized powder in a single-dose vial for reconstitution. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS See boxed warning . ( 5.1 , 5.2 , 5.3)
5.1Hypersensitivity Reactions Including Anaphylaxis Life-threatening hypersensitivity reactions, including anaphylaxis, have been reported in NEXVIAZYME-treated patients. In NEXVIAZYME clinical studies, 67 (48%) NEXVIAZYME-treated patients experienced hypersensitivity reactions, including 6 (4%) patients who reported severe hypersensitivity reactions and 3 (2%) patients who experienced anaphylaxis; 2 (1%) patients who experienced anaphylaxis discontinued from the study. Some of the hypersensitivity reactions were IgE mediated.
Symptoms of severe hypersensitivity reactions (e.g., anaphylaxis) included chest discomfort, erythema, generalized edema, hypotension, hypoxia, rash, respiratory distress, tongue edema, and urticaria. Prior to NEXVIAZYME administration, consider pretreating with antihistamines, antipyretics, and/or corticosteroids. Appropriate medical monitoring and support measures, including cardiopulmonary resuscitation equipment, should be readily available during NEXVIAZYME administration.
If a severe hypersensitivity reaction (e.g., anaphylaxis) occurs, discontinue NEXVIAZYME immediately and initiate appropriate medical treatment. Consider the risks and benefits of re-administering NEXVIAZYME following severe hypersensitivity reactions (including anaphylaxis). Patients may be rechallenged using slower infusion rates at a dosage lower than the recommended dosage.
In patients with severe hypersensitivity reaction, desensitization measures to NEXVIAZYME may be considered. If the decision is made to readminister NEXVIAZYME, ensure the patient tolerates the infusion. Once the patient tolerates the infusion, the dosage (dose and/or the rate) may be increased to reach the recommended dosage.
If a mild or moderate hypersensitivity reaction occurs, consider temporarily holding the infusion or slowing the infusion rate [see Dosage and Administration (2.3) ] .
5.2Infusion-Associated Reactions In clinical studies, IARs were reported to occur at any time during and/or within a few hours after the NEXVIAZYME infusion and were more likely to occur with higher infusion rates. IARs were reported in 48 (34%) NEXVIAZYME-treated patients in all clinical studies. In these studies, 5 (4%) NEXVIAZYME-treated patients reported 10 severe IARs including symptoms of chest discomfort, decreased or increased blood pressure, dysphagia, erythema, generalized edema, hypoxia, nausea, respiratory distress, tongue edema, and urticaria.
The majority of IARs were assessed as mild to moderate. IARs that led to treatment discontinuation were chest discomfort, cough, dizziness, erythema, flushing, nausea, ocular hyperemia, respiratory distress, and urticaria. Increased incidence of IARs was observed in patients with higher ADA titers [see Adverse Reactions (6.1) ] .
Prior to NEXVIAZYME administration, consider pretreating with antihistamines, antipyretics, and/or corticosteroids to reduce the risk of IARs. However, IARs may still occur in patients after receiving pretreatment. If a severe IAR occurs, discontinue NEXVIAZYME immediately and initiate appropriate medical treatment.
Consider the benefits and risks of readministering NEXVIAZYME following a severe IAR. Patients may be rechallenged using slower infusion rates at a dosage lower than the recommended dosage. Once the patient tolerates the infusion, the dosage (dose and/or the rate) may be increased to reach the recommended dosage.
If a mild or moderate IAR occurs, consider temporarily holding the infusion or slowing the infusion rate [see Dosage and Administration (2.3) ]. Patients with an acute underlying illness at the time of NEXVIAZYME infusion appear to be at greater risk for IARs. Patients with advanced Pompe disease may have compromised cardiac and respiratory function, which may predispose them to a higher risk of severe complications from IARs.
5.3Risk of Acute Cardiorespiratory Failure in Susceptible Patients Patients su… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed in greater detail in other sections of the labeling: Hypersensitivity Reactions Including Anaphylaxis [see Warnings and Precautions (5.1) ] Infusion-Associated Reactions (IARs) [see Warnings and Precautions (5.2) ] The most common adverse reactions (>5%) were headache, fatigue, diarrhea, nausea, arthralgia, dizziness, myalgia, pruritus, vomiting, dyspnea, erythema, paresthesia and urticaria. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Genzyme at 1-800-633-1610, option 1 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse Reactions from Clinical Trials in the Pompe Disease Population The pooled safety analysis from 4 clinical trials in the Pompe disease population (including Study 1) with a mean exposure of 26 months and up to 85 months of treatment included a total of 141 NEXVIAZYME-treated patients (118 adult and 23 pediatric patients [see Clinical Studies (14.1) ] .
Adverse reactions were similar across both adult and pediatric populations. Serious adverse reactions reported in 2 or more NEXVIAZYME-treated patients were respiratory distress, chills, and pyrexia. A total of 4 NEXVIAZYME-treated patients in clinical trials permanently discontinued NEXVIAZYME due to adverse reactions, including 3 patients who discontinued the treatment because of a serious adverse reaction.
The most frequently reported adverse reactions (>5%) in the pooled safety population were abdominal pain, arthralgia, chills, diarrhea, dizziness, dyspnea, erythema, fatigue, flushing, headache, hypertension, hypotension, myalgia, nausea, pruritus, pyrexia, rash, vomiting, and urticaria. Hypersensitivity reactions were reported in 67 (48%) NEXVIAZYME-treated patients, including 6 (4%) patients who reported severe hypersensitivity reactions. Symptoms of severe hypersensitivity reactions (e.g., anaphylaxis) included chest discomfort, erythema, generalized edema, hypotension, hypoxia, rash, respiratory distress, tongue edema, and urticaria.
IARs were reported in 48 (34%) NEXVIAZYME-treated patients. Six (4%) NEXVIAZYME-treated patients reported 13 severe IARs including symptoms of chest discomfort, decreased or increased blood pressure, dysphagia, erythema, generalized edema, hypoxia, nausea, respiratory distress, tongue edema, and urticaria. IARs reported in more than 1 patient included chest discomfort, cyanosis, decreased or increased blood pressure, diarrhea, dizziness, erythema, fatigue, feeling hot or cold, generalized edema, headache, hyperhidrosis, hypoxia, influenza-like illness, nausea, pain, pruritus, pyrexia, rash, respiratory distress, tachycardia, throat irritation, tongue edema, tremor, urticaria, and vomiting.
Adverse Reactions from Clinical Trials in Late-Onset Pompe Disease (LOPD) In Study 1, 100 patients aged 16 to 78 years of age with LOPD (naïve to enzyme replacement therapy) were treated with either 20 mg/kg of NEXVIAZYME (n=51) or 20 mg/kg of alglucosidase alfa (n=49) given every other week as an intravenous infusion for 49 weeks followed by an open-label extension period [see Clinical Studies (14.1) ] . During the double-blind active-controlled period of 49 weeks, serious adverse reactions were reported in 1 (2%) patient treated with NEXVIAZYME and in 3 (6%) patients treated with alglucosidase alfa.
The most frequently reported adverse reactions in (>5%) NEXVIAZYME-treated patients were headache, fatigue, diarrhea, nausea, arthralgia, dizziness, myalgia, pruritus, vomiting, dyspnea, erythema, paresthesia, and urticaria. IARs were reported in 13 (25%) of the NEXVIAZYME-treated patients. IARs reported in more than 1 patient on NEXVIAZYME were mild to moderate a… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Available data from case reports of NEXVIAZYME use in pregnant women are insufficient to evaluate for a drug associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. However, available data from postmarketing reports and published case reports on alglucosidase alfa (another hydrolytic lysosomal glycogen-specific enzyme replacement therapy) use in pregnant women have not identified a drug-associated risk of adverse pregnancy outcomes. The continuation of treatment for Pompe disease during pregnancy should be individualized to the pregnant woman.
Untreated Pompe disease may result in worsening disease symptoms in pregnant women (see Clinical Considerations ) . Embryo-fetal toxicity studies performed in pregnant mice resulted in maternal toxicity related to an immunologic response (including an anaphylactoid response) and embryo-fetal loss at 17 times the human steady-state AUC at the recommended biweekly dose of 20 mg/kg for LOPD patients weighing ≥30 kg or 10 times the human steady-state AUC at the recommended biweekly dose of 40 mg/kg for LOPD patients weighing <30 kg.
Avalglucosidase alfa-ngpt did not cross the placenta in mice, therefore, the adverse effects were likely related to the immunologic response in the mothers. Embryo-fetal toxicity studies performed in pregnant rabbits showed no adverse effects on the fetuses at exposure up to 91 times the human steady-state AUC at the recommended biweekly dosage of 20 mg/kg for LOPD patients weighing ≥30 kg or 50 times the human steady-state AUC at the recommended biweekly dose of 40 mg/kg for LOPD patients weighing <30 kg (see Data ) .
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, miscarriage, or other adverse outcomes. In the U.S. general population, the background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Pregnant women exposed to NEXVIAZYME, or their healthcare providers, should report NEXVIAZYME exposure by calling 1-800-633-1610, option 1. Clinical Considerations Disease-associated maternal and/or embryo-fetal risk Untreated Pompe disease has been associated with worsening respiratory and musculoskeletal symptoms in some pregnant women. Data Animal data The majority of reproductive toxicity studies in mice included the pretreatment with diphenhydramine (DPH) to prevent or minimize hypersensitivity reactions.
The effects of NEXVIAZYME were evaluated based on comparison with a control group treated with DPH alone. Rabbits tested in reproductive toxicity studies were not pretreated with DPH because hypersensitivity reactions were not observed. Embryo-fetal toxicity studies performed in pregnant mice at doses of 0, 10, 20, or 50 mg/kg/day administered intravenously once daily on gestational days 6 through 15 resulted in an immunologic response, including an anaphylactoid response, in some dams at the highest dose of 50 mg/kg/day (17 times the human steady-state AUC at the recommended biweekly dose of 20 mg/kg for LOPD patients weighing ≥30 kg or 10 times the human steady-state AUC at the recommended biweekly dose of 40 mg/kg for LOPD patients weighing <30 kg).
Increased post-implantation loss and mean number of late resorptions were observed in this group. Placental transfer studies determined that avalglucosidase alfa-ngpt was not transported from the maternal to the fetal circulation in mice, suggesting that the embryo-fetal effects were due to maternal toxicity relating to the immunologic response. The maternal no observed adverse effect level (NOAEL) was 50 mg/kg/day intravenously (17 times the human AUC) and the developmental NOAEL was 20 mg/kg/day intravenously (4.8 times the human AUC).
Embryo-fetal toxicity studies performed in rabbits at doses of 0, 30, 60, and 100 mg/kg/day administered int… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from case reports of NEXVIAZYME use in pregnant women are insufficient to evaluate for a drug associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. However, available data from postmarketing reports and published case reports on alglucosidase alfa (another hydrolytic lysosomal glycogen-specific enzyme replacement therapy) use in pregnant women have not identified a drug-associated risk of adverse pregnancy outcomes. The continuation of treatment for Pompe disease during pregnancy should be individualized to the pregnant woman.
Untreated Pompe disease may result in worsening disease symptoms in pregnant women (see Clinical Considerations ) . Embryo-fetal toxicity studies performed in pregnant mice resulted in maternal toxicity related to an immunologic response (including an anaphylactoid response) and embryo-fetal loss at 17 times the human steady-state AUC at the recommended biweekly dose of 20 mg/kg for LOPD patients weighing ≥30 kg or 10 times the human steady-state AUC at the recommended biweekly dose of 40 mg/kg for LOPD patients weighing <30 kg.
Avalglucosidase alfa-ngpt did not cross the placenta in mice, therefore, the adverse effects were likely related to the immunologic response in the mothers. Embryo-fetal toxicity studies performed in pregnant rabbits showed no adverse effects on the fetuses at exposure up to 91 times the human steady-state AUC at the recommended biweekly dosage of 20 mg/kg for LOPD patients weighing ≥30 kg or 50 times the human steady-state AUC at the recommended biweekly dose of 40 mg/kg for LOPD patients weighing <30 kg (see Data ) .
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, miscarriage, or other adverse outcomes. In the U.S. general population, the background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Pregnant women exposed to NEXVIAZYME, or their healthcare providers, should report NEXVIAZYME exposure by calling 1-800-633-1610, option 1. Clinical Considerations Disease-associated maternal and/or embryo-fetal risk Untreated Pompe disease has been associated with worsening respiratory and musculoskeletal symptoms in some pregnant women. Data Animal data The majority of reproductive toxicity studies in mice included the pretreatment with diphenhydramine (DPH) to prevent or minimize hypersensitivity reactions.
The effects of NEXVIAZYME were evaluated based on comparison with a control group treated with DPH alone. Rabbits tested in reproductive toxicity studies were not pretreated with DPH because hypersensitivity reactions were not observed. Embryo-fetal toxicity studies performed in pregnant mice at doses of 0, 10, 20, or 50 mg/kg/day administered intravenously once daily on gestational days 6 through 15 resulted in an immunologic response, including an anaphylactoid response, in some dams at the highest dose of 50 mg/kg/day (17 times the human steady-state AUC at the recommended biweekly dose of 20 mg/kg for LOPD patients weighing ≥30 kg or 10 times the human steady-state AUC at the recommended biweekly dose of 40 mg/kg for LOPD patients weighing <30 kg).
Increased post-implantation loss and mean number of late resorptions were observed in this group. Placental transfer studies determined that avalglucosidase alfa-ngpt was not transported from the maternal to the fetal circulation in mice, suggesting that the embryo-fetal effects were due to maternal toxicity relating to the immunologic response. The maternal no observed adverse effect level (NOAEL) was 50 mg/kg/day intravenously (17 times the human AUC) and the developmental NOAEL was 20 mg/kg/day intravenously (4.8 times the human AUC).
Embryo-fetal toxicity studies performed in rabbits at doses of 0, 30, 60, and 100 mg/kg/day administered intravenously once daily on gesta… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of NEXVIAZYME for the treatment of late-onset Pompe disease have been established in pediatric patients aged 1 year and older. Use of NEXVIAZYME for this indication is supported by evidence from two clinical studies which included adults with LOPD, and 1 pediatric patient with LOPD (16 years of age) and from safety experience in 19 pediatric patients with infantile-onset Pompe disease (IOPD) (1 to 12 years of age) treated with NEXVIAZYME [see Clinical Studies (14.1) ] .
NEXVIAZYME is not approved for the treatment of IOPD. The safety profile of NEXVIAZYME in pediatric patients 1 to 12 years old with Pompe disease was similar to the safety profile of NEXVIAZYME in older pediatric and adult patients with LOPD. The safety and effectiveness of NEXVIAZYME have not been established in pediatric patients younger than 1 year of age.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies with NEXVIAZYME included 13 patients 65 to 74 years of age and 4 patients 75 years of age and older. The recommended dosage in geriatric patients is the same as the recommended dosage in younger adult patients [see Adverse Reactions (6.1) ] .
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Pompe disease (also known as glycogen storage disease type II, acid maltase deficiency, and glycogenosis type II) is an inherited disorder of glycogen metabolism caused by a deficiency of the lysosomal enzyme acid α-glucosidase (GAA) that degrades glycogen to glucose in the lysosome. GAA deficiency results in intralysosomal accumulation of glycogen in various tissues. Avalglucosidase alfa-ngpt provides an exogenous source of GAA.
The M6P on avalglucosidase alfa-ngpt mediates binding to M6P receptors on the cell surface with high affinity. After binding, it is internalized and transported into lysosomes where it undergoes proteolytic cleavage that results in increased GAA enzymatic activity. Avalglucosidase alfa-ngpt then exerts enzymatic activity in cleaving glycogen.
12.2Pharmacodynamics In patients with Pompe disease, excess of glycogen is degraded to hexose tetrasaccharide (Hex4) which is then excreted in urine. The urinary Hex4 assay measures the major component, glucose tetrasaccharide (Glc4). Treatment with NEXVIAZYME resulted in reductions of urinary Glc4 concentrations (normalized by urine creatinine and reported as mmol Glc4/mol creatinine) in patients with Pompe disease.
In ERT-naïve LOPD patients in Study 1, the baseline mean (SD) urinary Glc4 concentration was 12.7 mmol/mol (10.10) and 8.7 mmol/mol (5.04) in NEXVIAZYME and alglucosidase alfa treatment groups, respectively [see Clinical Studies (14.1) ] . At Week 145, the mean urinary Glc4 concentration was 4.32 mmol/mol (4.28) in patients who continued with NEXVIAZYME and 5.25 mmol/mol (7.48) in patients who switched from alglucosidase alfa to NEXVIAZYME. For patients who started on NEXVIAZYME, the mean percentage (SD) change in urinary Glc4 concentration from baseline was -54% (24), at Week 49 and -53% (73) at Week 145.
For patients who started on alglucosidase alfa and switched to NEXVIAZYME at Week 49, the mean percentage (SD) change in urinary Glc4 concentration from baseline was -11% (32) at Week 49, and -48% (42) at Week 145.
12.3Pharmacokinetics The avalglucosidase alfa-ngpt exposure increases in an approximately proportional manner with increasing doses over a range from 5 to 20 mg/kg (0.25 to 1 time the approved recommended dosage in LOPD patients weighing greater than or equal to 30 kg or 0.125 to 0.5 times the approved recommended dosage in LOPD patients weighing less than 30 kg). No accumulation was observed following every two weeks dosing. Following intravenous infusion of 20 mg/kg of NEXVIAZYME every two weeks in LOPD patients weighing greater than or equal to 30 kg, the mean ± SD plasma C max of avalglucosidase alfa-ngpt at Week 1 and Week 49 was 259 ± 72 µg/mL and 242 ± 81 µg/mL, respectively; the mean ± SD plasma AUC of avalglucosidase alfa-ngpt at Week 1 and Week 49 was 1,290 ± 420 µg∙h/mL and 1,250 ± 433 µg∙h/mL, respectively.
Patients weighing less than 30 kg are expected to have similar AUC following intravenous infusion of 40 mg/kg of NEXVIAZYME every two weeks. Distribution The volume of distribution of avalglucosidase alfa-ngpt was
3.4L in LOPD patients. Elimination The mean total body clearance of avalglucosidase alfa-ngpt was
0.9L/hour and the mean plasma elimination half-life of avalglucosidase alfa-ngpt was 1.6 hours in LOPD patients. Metabolism The protein portion of avalglucosidase alfa-ngpt is expected to be metabolized into small peptides by catabolic pathways. Specific Populations Population pharmacokinetic analyses indicated that age, which ranged from 1 to 78 years in the clinical trials, and sex did not significantly influence the pharmacokinetics of avalglucosidase alfa-ngpt in patients with Pompe disease.
Pediatric patients In 16 patients aged 1 to 12 years with Pompe disease, following a 4-hour intravenous infusion of NEXVIAZYME 20 mg/kg every two weeks and 7-hour intravenous infusion of NEXVIAZYME 40 mg/kg every two weeks, the mean C max ranged from 175 to 189 µg/mL and 2… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Pompe disease (also known as glycogen storage disease type II, acid maltase deficiency, and glycogenosis type II) is an inherited disorder of glycogen metabolism caused by a deficiency of the lysosomal enzyme acid α-glucosidase (GAA) that degrades glycogen to glucose in the lysosome. GAA deficiency results in intralysosomal accumulation of glycogen in various tissues. Avalglucosidase alfa-ngpt provides an exogenous source of GAA.
The M6P on avalglucosidase alfa-ngpt mediates binding to M6P receptors on the cell surface with high affinity. After binding, it is internalized and transported into lysosomes where it undergoes proteolytic cleavage that results in increased GAA enzymatic activity. Avalglucosidase alfa-ngpt then exerts enzymatic activity in cleaving glycogen.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied NEXVIAZYME (avalglucosidase alfa-ngpt) for injection is supplied as a sterile, white to pale-yellow lyophilized powder in a single-dose vial. Each vial contains 100 mg of avalglucosidase alfa-ngpt. NEXVIAZYME is available as: One single-dose vial in a carton (NDC 58468-0426-1) Storage and Handling Store refrigerated at 2°C to 8°C (36°F to 46°F). Do not use NEXVIAZYME after the expiration date on the vial.
📦 Storage and Handling ▾
Storage and Handling Store refrigerated at 2°C to 8°C (36°F to 46°F). Do not use NEXVIAZYME after the expiration date on the vial.
📋 Description ▾
11 DESCRIPTION Avalglucosidase alfa-ngpt is a hydrolytic lysosomal glycogen-specific recombinant human α-glucosidase enzyme conjugated with multiple synthetic bis-mannose-6-phosphate (bis-M6P)-tetra-mannose glycans resulting in approximately 15 moles of M6P per mole of enzyme (15 M6P) and is produced in Chinese hamster ovary cells (CHO). Avalglucosidase alfa-ngpt has a molecular weight of approximately 124 kDa. NEXVIAZYME (avalglucosidase alfa-ngpt) for injection is a sterile white to pale-yellow lyophilized powder for intravenous use after reconstitution and dilution.
Each single-dose vial contains 100 mg of avalglucosidase alfa-ngpt, glycine (200 mg), L-Histidine (10.7 mg), L-Histidine HCl monohydrate (6.5 mg), mannitol (200 mg), and polysorbate 80 (1 mg). After reconstitution with 10 mL of Sterile Water for Injection, USP, the resultant concentration is 100 mg/10 mL (10 mg/mL) with a pH of approximately 6.2.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Hypersensitivity Reactions Including Anaphylaxis and Infusion-Associated Reactions (IARs) Advise the patient and caregiver that reactions related to the infusion may occur during and after NEXVIAZYME treatment, including life-threatening hypersensitivity reactions, including anaphylaxis, and IARs. Inform the patient and caregiver of the signs and symptoms of hypersensitivity reactions and IARs and to seek medical care should signs and symptoms occur [see Warnings and Precautions (5.1 , 5.2) ] .
Risk of Acute Cardiorespiratory Failure Advise the patient and caregiver that patients with underlying respiratory illness or compromised cardiac or respiratory function may be at risk of acute cardiorespiratory failure from volume overload during NEXVIAZYME infusion and should seek medical care should signs and symptoms occur [see Warnings and Precautions (5.3) ] . NEXVIAZYME Exposure During Pregnancy or Lactation Advise a pregnant or lactating woman exposed to NEXVIAZYME to report NEXVIAZYME exposure to her healthcare provider and by calling 1-800-633-1610, option 1 [see Use in Specific Populations (8.1. , 8.2) ] .
Pompe Registry Inform the patient and/or caregiver that there is a Pompe Registry to better understand the variability and progression of Pompe disease and to monitor and evaluate long-term effects of NEXVIAZYME. Encourage the patient and/or caregiver to enroll in the Pompe Registry and state that participation is voluntary and may involve long-term follow-up. For more information regarding the registry program, direct the patient and caregiver to visit www.registrynxt.com or call 1-800-745-4447, extension 15500.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The avalglucosidase alfa-ngpt exposure increases in an approximately proportional manner with increasing doses over a range from 5 to 20 mg/kg (0.25 to 1 time the approved recommended dosage in LOPD patients weighing greater than or equal to 30 kg or 0.125 to 0.5 times the approved recommended dosage in LOPD patients weighing less than 30 kg). No accumulation was observed following every two weeks dosing. Following intravenous infusion of 20 mg/kg of NEXVIAZYME every two weeks in LOPD patients weighing greater than or equal to 30 kg, the mean ± SD plasma C max of avalglucosidase alfa-ngpt at Week 1 and Week 49 was 259 ± 72 µg/mL and 242 ± 81 µg/mL, respectively; the mean ± SD plasma AUC of avalglucosidase alfa-ngpt at Week 1 and Week 49 was 1,290 ± 420 µg∙h/mL and 1,250 ± 433 µg∙h/mL, respectively.
Patients weighing less than 30 kg are expected to have similar AUC following intravenous infusion of 40 mg/kg of NEXVIAZYME every two weeks. Distribution The volume of distribution of avalglucosidase alfa-ngpt was
3.4L in LOPD patients. Elimination The mean total body clearance of avalglucosidase alfa-ngpt was
0.9L/hour and the mean plasma elimination half-life of avalglucosidase alfa-ngpt was 1.6 hours in LOPD patients. Metabolism The protein portion of avalglucosidase alfa-ngpt is expected to be metabolized into small peptides by catabolic pathways. Specific Populations Population pharmacokinetic analyses indicated that age, which ranged from 1 to 78 years in the clinical trials, and sex did not significantly influence the pharmacokinetics of avalglucosidase alfa-ngpt in patients with Pompe disease.
Pediatric patients In 16 patients aged 1 to 12 years with Pompe disease, following a 4-hour intravenous infusion of NEXVIAZYME 20 mg/kg every two weeks and 7-hour intravenous infusion of NEXVIAZYME 40 mg/kg every two weeks, the mean C max ranged from 175 to 189 µg/mL and 250 to 403 µg/mL, respectively. The mean AUC last ranged from 805 to 923 µg∙hr/mL for 20 mg/kg every two weeks and 1,720 to 2,630 µg∙hr/mL for 40 mg/kg every two weeks.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics In patients with Pompe disease, excess of glycogen is degraded to hexose tetrasaccharide (Hex4) which is then excreted in urine. The urinary Hex4 assay measures the major component, glucose tetrasaccharide (Glc4). Treatment with NEXVIAZYME resulted in reductions of urinary Glc4 concentrations (normalized by urine creatinine and reported as mmol Glc4/mol creatinine) in patients with Pompe disease.
In ERT-naïve LOPD patients in Study 1, the baseline mean (SD) urinary Glc4 concentration was 12.7 mmol/mol (10.10) and 8.7 mmol/mol (5.04) in NEXVIAZYME and alglucosidase alfa treatment groups, respectively [see Clinical Studies (14.1) ] . At Week 145, the mean urinary Glc4 concentration was 4.32 mmol/mol (4.28) in patients who continued with NEXVIAZYME and 5.25 mmol/mol (7.48) in patients who switched from alglucosidase alfa to NEXVIAZYME. For patients who started on NEXVIAZYME, the mean percentage (SD) change in urinary Glc4 concentration from baseline was -54% (24), at Week 49 and -53% (73) at Week 145.
For patients who started on alglucosidase alfa and switched to NEXVIAZYME at Week 49, the mean percentage (SD) change in urinary Glc4 concentration from baseline was -11% (32) at Week 49, and -48% (42) at Week 145.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Clinical Trial in Patients with Late-Onset Pompe Disease Study 1 (NCT02782741) was a randomized, double-blinded, multinational, multicenter trial comparing the efficacy and safety of NEXVIAZYME to alglucosidase alfa in treatment-naïve patients with LOPD. One hundred patients (51 in NEXVIAZYME and 49 in alglucosidase alfa) were randomized in a 1:1 ratio based on baseline forced vital capacity ([FVC] % predicted; <55% or ≥55%), sex, age (<18 years or ≥18 years), and country (Japan or not-Japan) to receive 20 mg/kg of NEXVIAZYME or alglucosidase alfa administered intravenously once every two weeks for 49 weeks.
After 49 weeks, all randomized patients in Study 1 had the option to enter an open-label extension treatment period to receive NEXVIAZYME and continue treatment up to at least Week 145. Demographic and Disease Characteristics Of the 100 randomized patients, 52 were males, the baseline median age was 49 years old (range from 16 to 78), median baseline weight was 76.4 kg (range from 38 to 139 kg), median length of time since diagnosis was 6.9 months (range from 0.3 to 328.4 months), mean age at diagnosis was 46.4 years old (range from 11 to 78), mean FVC (% predicted) at baseline was 62.1% (range from 32 to 85%), and mean 6MWT at baseline was 388.9 meters (range from 118 to 630 meters).
The racial groups for the patients consisted of 94 White (94%), 3 Black or African American (3%), and 3 Asian (3%). Fifteen patients were Hispanic/Latino (15%), 76 non-Hispanic/Latino (76%) and 9 were not reported. Five patients (all in the alglucosidase alfa arm) discontinued the study prior to Week 49: four due to adverse events (acute myocardial infarction, arthritis, dyspnea, and urticaria), and one due to withdrawal of consent.
All 95 patients who did not discontinue the study prior to Week 49 entered the open-label period (51 from the NEXVIAZYME arm and 44 from the alglucosidase alfa arm). Of the 95 patients, 77 patients had follow-up data on FVC (% predicted) at Week 145 (44 from the NEXVIAZYME arm and 33 from the alglucosidase alfa arm) and 80 patients had follow-up data on 6MWT at Week 145 (45 from the NEXVIAZYME arm and 35 from the alglucosidase alfa arm). Fourteen (14%) patients (7 in each group) discontinued during the Extension Treatment period (5 for adverse event, 1 for poor compliance to protocol and 8 for other reason).
Primary Efficacy Results from the 49-Week Active-Controlled Period and Open-Label Period up to Week 145 in Study 1 The primary endpoint of Study 1 was the change in FVC (% predicted) in the upright position from baseline to Week 49. At Week 49, the least squares (LS) mean change in FVC (% predicted) for patients treated with NEXVIAZYME and alglucosidase alfa was 2.9% and 0.5%, respectively. The estimated treatment difference was 2.4% (95% CI: -0.1, 5.0) favoring NEXVIAZYME (see Table 6 ).
Figure 1 presents the LS mean change from baseline in FVC (% predicted) over time by treatment group up to Week 49. Table 6: Summary Results of FVC (% predicted) in Upright Position in ERT-Naïve Patients with LOPD (Study 1) All randomized patients NEXVIAZYME (n=51) Alglucosidase Alfa (n=49) Pretreatment baseline Mean (SD) 62.5 (14.4) 61.6 (12.4) Week 49 Mean (SD) 65.5 (17.4) 61.2 (13.5) Estimated change from baseline to week 49 LS mean (SE)
2.9Estimated using a mixed model for repeated measures (MMRM) including baseline FVC (% predicted, as continuous), sex, baseline age (years), treatment group, visit, and treatment-by-visit interaction term as fixed effects. (0.9) 0.5 (0.9) Estimated difference between groups in change from baseline to week 49 LS mean (95% CI)
2.4Noninferiority margin of 1.1% (p=0.0074). Statistical superiority of NEXVIAZYME over alglucosidase alfa was not achieved (p=0.06). (-0.1, 5.0) Figure 1: Plot of LS Mean (SE) Change from Baseline of FVC (% predicted) in Upright Position over Time in ERT-Naïve Patients with LOPD (Study 1) All randomized patients For patients who continued t… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term studies in animals to evaluate the carcinogenic potential or studies to evaluate mutagenic potential have not been performed with avalglucosidase alfa-ngpt. Intravenous administration of avalglucosidase alfa-ngpt every other day at doses up to 50 mg/kg (exposure not evaluated) had no adverse effects on fertility in male or female mice.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term studies in animals to evaluate the carcinogenic potential or studies to evaluate mutagenic potential have not been performed with avalglucosidase alfa-ngpt. Intravenous administration of avalglucosidase alfa-ngpt every other day at doses up to 50 mg/kg (exposure not evaluated) had no adverse effects on fertility in male or female mice.
📄 Recent Major Changes ▾
Dosage and Administration ( 2.1 , 2.2 ) 9/2023 Warnings and Precautions ( 5.1 , 5.2 ) 9/2023
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 100 mg Vial Carton NDC 58468-0426-1 Rx only Nexviazyme ® (avalglucosidase alfa-ngpt) for Injection 100 mg per vial For Intravenous Infusion after Reconstitution and Dilution One single-dose vial Discard unused portion PRINCIPAL DISPLAY PANEL - 100 mg Vial Carton
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |