
Zumandimine Drospirenone and Ethinyl Estradiol Kit — NDC 59651-030-85 (Billing 59651-0030-85)
This is a package of Zumandimine Drospirenone and Ethinyl Estradiol Kit from Aurobindo Pharma Limited, marketed since Mar 2018 and currently FDA-listed; retail pharmacies pay about $0.1511 per unit (NADAC). It is the main listing for this product, which comes in 4 package sizes.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 047787
- GCN: 13083
- GPI-14 (Medi-Span): 25990002150320
- HICL (First Databank): 022026
- AHFS class code: 68:12.00.00
- RxCUI (RxNorm): 284207
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Progestin class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Oral contraceptives (birth-control pills) containing ethinyl estradiol (an estrogen) and drospirenone (a progestin) are used to prevent pregnancy, treat certain types of acne, and to relieve the symptoms of premenstrual dysphoric disorder (symptoms that occur before the menstrual period each month). Your doctor will select the best medication for your needs. Estrogen and progestin are two female sex hormones. Combinations of estrogen and progestin work by preventing ovulation (the release of eggs from the ovaries). Oral contraceptives treat acne by decreasing the amounts of certain natural sub...
Read the full MedlinePlus article ↗- It's primarily a birth control pill, but it can do more than that. Depending on which brand you have, it may also be approved to treat moderate acne or the emotional and physical s...
- What is this pill actually used for — is it just birth control?
- Take one tablet every day at the same time, following the order printed on your blister pack — the order really matters. If you miss a pill, take it as soon as you remember and kee...
- How do I take this pill and what happens if I miss one?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.151 | $0.45 / 3 kit |
| Medicaid paysCMS SDUD · 12 mo | $0.3712 | $1.11 / 3 kit |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 59651-0030-28 59651-030-28 | 1 BLISTER PACK in 1 CARTON / 1 KIT in 1 BLISTER PACK | $0.1511 / ea | $0.15 | 2018-03-26 | — | Active |
| 59651-0030-85 You're viewing this Main listing | 3 BLISTER PACK in 1 CARTON / 1 KIT in 1 BLISTER PACK | $0.1511 / ea | $0.45 | 2018-03-26 | — | Active |
| 59651-0030-87 59651-030-87 | 1 POUCH in 1 CARTON / 1 BLISTER PACK in 1 POUCH / 1 KIT in 1 BLISTER PACK | — | — | 2018-03-26 | — | Active |
| 59651-0030-88 59651-030-88 | 3 POUCH in 1 CARTON / 1 BLISTER PACK in 1 POUCH / 1 KIT in 1 BLISTER PACK | — | — | 2018-03-26 | — | Active |
This pack effectively ties for the lowest per-ea cost of the 2 priced pack sizes ($0.1511 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Zumandimine Drospirenone and Ethinyl Estradiol Kit?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Drospirenone And Ethinyl Estradiol 00378-7300-53 | Mylan | 3 pouches | $0.149 | AB | Availability likely | save 1% |
| Drospirenone and Ethinyl Estradiol 31722-0945-31 | Camber | 1 kit | $0.151 | AB | Availability likely | — |
| Zumandiminethis 59651-0030-85 | Aurobindo | 1 kit | $0.151 | AB | Availability likely | — |
| Syeda 70700-0115-85 | Xiromed, | 1 kit | $0.151 | AB | Availability likely | — |
| Drospirenone And Ethinyl Estradiol 60505-4897-08 | Apotex | 63 tablets | $0.151 | AB | Availability likely | — |
| Drospirenone And Ethinyl Estradiol 68180-0868-73 | Lupin | 63 tablets | $0.151 | AB | Availability likely | — |
| drospirenone and ethinyl estradiol 68462-0733-29 | Glenmark | 1 kit | $0.151 | AB | Availability likely | — |
| Ocella 00555-9131-67 | TEVA | 1 kit | $0.154 | AB | Discontinued | +2% |
| Drospirenone and ethinyl estradiol 31722-0934-31 | Camber | 1 kit | $0.191 | AB | Availability likely | +26% |
| Nikki 68180-0886-73 | Lupin | 1 kit | $0.191 | AB | Availability likely | +26% |
| Vestura 00480-4000-62 | Teva | 72 tablets | $0.191 | AB | Availability likely | +26% |
| drospirenone and ethinyl estradiol 68462-0720-29 | Glenmark | 1 kit | $0.191 | AB | Availability likely | +26% |
| Jasmiel 50102-0240-23 | Afaxys | 3 pouches | $0.191 | AB | Availability likely | +26% |
| Drospirenone and Ethinyl Estradiol 72603-0875-03 | NorthStar | 3 pouches | $0.191 | AB | Availability likely | +26% |
| Yasmin 50419-0402-03 | Bayer | 1 kit | $4.397 | AB | Availability likely | +2811% |
| Yaz 50419-0405-03 | Bayer | 1 kit | $5.844 | AB | Availability likely | +3769% |
| drospirenone and ethinyl estradiol 71205-0144-28 | Proficient | 1 kit | — | AB | FDA listed | — |
| Lo-Zumandimine 59651-0029-87 | Aurobindo | 1 pouch | — | AB | FDA listed | — |
| Syeda 63629-2335-01 | Bryant | 1 kit | — | AB | FDA listed | — |
| Drospirenone And Ethinyl Estradiol 79929-0019-07 | Naari | 21 tablets | — | AB | FDA listed | — |
| drospirenone and ethinyl estradiol 50090-2494-00 | A-S | 1 kit | — | AB | FDA listed | — |
| drospirenone and ethinyl estradiol 50090-2594-00 | A-S | 1 kit | — | AB | FDA listed | — |
| Drospirenone And Ethinyl Estradiol 67296-2286-03 | Redpharm | 63 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: CIGARETTE SMOKING AND SERIOUS CARDIOVASCULAR EVENTS Cigarette smoking increases the risk of serious cardiovascular events from combination oral contraceptives (COC) use. This risk increases with age, particularly in women over 35 years of age, and with the number of cigarettes smoked. For this reason, COCs should not be used by women who are over 35 years of age and smoke [see Contraindications (4) ] .
WARNING: CIGARETTE SMOKING AND SERIOUS CARDIOVASCULAR EVENTS See full prescribing information for complete boxed warning. Women over 35 years old who smoke should not use Zumandimine. ( 4 ) Cigarette smoking increases the risk of serious cardiovascular events from combination oral contraceptive (COC) use.
(4)
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Zumandimine ® (drospirenone and ethinyl estradiol tablets) are indicated for use by females of reproductive potential to prevent pregnancy. Zumandimine (drospirenone and ethinyl estradiol tablets) is a combination of drospirenone, a progestin, and ethinyl estradiol, an estrogen, indicated for use by females of reproductive potential to prevent pregnancy. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Take one tablet daily by mouth at the same time every day. ( 2.1 ) Tablets must be taken in the order directed on the blister pack. ( 2.1 )
2.1How to Take Zumandimine Take one tablet by mouth at the same time every day. The failure rate may increase when pills are missed or taken incorrectly. To achieve maximum contraceptive effectiveness, Zumandimine must be taken as directed, in the order directed on the blister pack. Single missed pills should be taken as soon as remembered.
2.2How to Start Zumandimine Instruct the patient to begin taking Zumandimine either on the first day of her menstrual period (Day 1 Start) or on the first Sunday after the onset of her menstrual period (Sunday Start). Day 1 Start During the first cycle of Zumandimine use, instruct the patient to take one light pink to pink Zumandimine daily, beginning on Day 1 of her menstrual cycle. (The first day of menstruation is Day 1.) She should take one light pink to pink Zumandimine daily for 21 consecutive days, followed by one green tablet daily on Days 22 through 28.
Zumandimine should be taken in the order directed on the package at the same time each day, preferably after the evening meal or at bedtime with some liquid, as needed. Zumandimine can be taken without regard to meals. If Zumandimine is first taken later than the first day of the menstrual cycle, Zumandimine should not be considered effective as a contraceptive until after the first 7 consecutive days of product administration.
Instruct the patient to use a non-hormonal contraceptive as back-up during the first 7 days. The possibility of ovulation and conception prior to initiation of medication should be considered. Sunday Start During the first cycle of Zumandimine use, instruct the patient to take one light pink to pink Zumandimine daily, beginning on the first Sunday after the onset of her menstrual period.
She should take one light pink to pink Zumandimine daily for 21 consecutive days, followed by one green tablet daily on Days 22 through 28. Zumandimine should be taken in the order directed on the package at the same time each day, preferably after the evening meal or at bedtime with some liquid, as needed. Zumandimine can be taken without regard to meals.
Zumandimine should not be considered effective as a contraceptive until after the first 7 consecutive days of product administration. Instruct the patient to use a non-hormonal contraceptive as back-up during the first 7 days. The possibility of ovulation and conception prior to initiation of medication should be considered.
The patient should begin her next and all subsequent 28-day regimens of Zumandimine on the same day of the week that she began her first regimen, following the same schedule. She should begin taking her light pink to pink tablets on the next day after ingestion of the last green tablet, regardless of whether or not a menstrual period has occurred or is still in progress. Anytime a subsequent cycle of Zumandimine is started later than the day following administration of the last green tablet, the patient should use another method of contraception until she has taken a light pink to pink Zumandimine daily for seven consecutive days.
When switching from a different birth control pill When switching from another birth control pill, Zumandimine should be started on the same day that a new pack of the previous oral contraceptive would have been started. When switching from a method other than a birth control pill When switching from a transdermal patch or vaginal ring, Zumandimine should be started when the next application would have been due. When switching from an injection, Zumandimine should be started when the next dose would have been due.
When switching from an intrauterine contraceptive or an implant, Zumandimine should be started on the day of removal. Withdrawal bleeding usually occurs within 3 days following the last light pink to pink tablet. If spotting or breakthrough bleeding… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Zumandimine (drospirenone and ethinyl estradiol tablets, USP) are available in blister packs. Each blister pack contains 28 tablets in the following order: 21 light pink to pink tablets each containing 3 mg of drospirenone (DRSP) and 0.03 mg of ethinyl estradiol (EE) debossed with “S” on one side and “76” on other side. 7 inert green tablets debossed with “S” on one side and “37” on other side.
Zumandimine (drospirenone and ethinyl estradiol tablet, USP) consists of 28 tablets in the following order ( 3 ): 21 light pink to pink tablets, each containing 3 mg drospirenone (DRSP) and 0.03 mg ethinyl estradiol (EE) 7 inert green tablets
⛔ Contraindications ▾
4 CONTRAINDICATIONS Zumandimine is contraindicated in females who are known to have or develop the following conditions: Renal impairment Adrenal insufficiency A high risk of arterial or venous thrombotic diseases. Examples include women who are known to: Smoke, if over age 35 [see Boxed Warning and Warnings and Precautions (5.1) ] Have deep vein thrombosis or pulmonary embolism, now or in the past [see Warnings and Precautions (5.1) ] Have cerebrovascular disease [see Warnings and Precautions (5.1) ] Have coronary artery disease [see Warnings and Precautions (5.1) ] Have thrombogenic valvular or thrombogenic rhythm diseases of the heart (for example, subacute bacterial endocarditis with valvular disease, or atrial fibrillation) [see Warnings and Precautions (5.1) ] Have inherited or acquired hypercoagulopathies [see Warnings and Precautions (5.1) ] Have uncontrolled hypertension [see Warnings and Precautions (5.6) ] Have diabetes mellitus with vascular disease [see Warnings and Precautions (5.8) ] Have headaches with focal neurological symptoms or have migraine headaches with or without aura if over age 35 [see Warnings and Precautions (5.9) ] Undiagnosed abnormal uterine bleeding [see Warnings and Precautions (5.10) ] Current diagnosis of, or history of, breast cancer, which may be hormone-sensitive [see Warnings and Precautions (5.3) ] Liver tumor (benign or malignant) or liver disease [see Warnings and Precautions (5.4) and Use in Specific Populations (8.7) ] Use of Hepatitis C drug combinations containing ombitasvir, paritaprevir/ritonavir, with or without dasabuvir due to the potential for ALT elevations [see Warnings and Precautions (5.5) and Drug Interactions (7.2) ].
Renal impairment ( 4 ) Adrenal insufficiency ( 4 ) A high risk of arterial or venous thrombotic diseases ( 4) Undiagnosed abnormal uterine bleeding ( 4) Breast cancer ( 4 ) Liver tumors or liver disease ( 4 ) Co-administration with Hepatitis C drug combinations containing ombitasvir, paritaprevir/ritonavir, with or without dasabuvir ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Vascular risks: Stop Zumandimine if a thrombotic event occurs. Stop at least 4 weeks before and through 2 weeks after major surgery. Start no earlier than 4 weeks after delivery, in women who are not breastfeeding ( 5.1 ).
COCs containing DRSP may be associated with a higher risk of venous thromboembolism (VTE) than COCs containing levonorgestrel or some other progestins. Before initiating Zumandimine in a new COC user or a woman who is switching from a contraceptive that does not contain DRSP, consider the risks and benefits of a DRSP-containing COC in light of her risk of a VTE ( 5.1 ). Hyperkalemia : DRSP has anti-mineralocorticoid activity.
Do not use in patients predisposed to hyperkalemia. Check serum potassium concentration during the first treatment cycle in women on long-term treatment with medications that may increase serum potassium concentration. ( 5.2 , 7.1 , 7.2 ) Liver disease : Discontinue Zumandimine if jaundice occurs.
( 5.4 ) High blood pressure : Do not prescribe Zumandimine for women with uncontrolled hypertension or hypertension with vascular disease. ( 5.6 ) Carbohydrate and lipid metabolic effects : Monitor prediabetic and diabetic women taking Zumandimine. Consider an alternate contraceptive method for women with uncontrolled dyslipidemia.
( 5.8 ) Headache : Evaluate significant change in headaches and discontinue Zumandimine if indicated. ( 5.9 ) Uterine bleeding : Evaluate irregular bleeding or amenorrhea. ( 5.10 )
5.1Thromboembolic Disorders and Other Vascular Problems Stop Zumandimine if an arterial or venous thrombotic (VTE) event occurs. Based on presently available information on Zumandimine, DRSP-containing COCs may be associated with a higher risk of venous thromboembolism (VTE) than COCs containing the progestin levonorgestrel or some other progestins. Epidemiologic studies that compared the risk of VTE reported that the risk ranged from no increase to a three-fold increase.
Before initiating use of Zumandimine in a new COC user or a woman who is switching from a contraceptive that does not contain DRSP, consider the risks and benefits of a DRSP-containing COC in light of her risk of a VTE. Known risk factors for VTE include smoking, obesity, and family history of VTE, in addition to other factors that contraindicate use of COCs [see Contraindications (4) ] . A number of studies have compared the risk of VTE for users of Zumandimine to the risk for users of other COCs, including COCs containing levonorgestrel.
Those that were required or sponsored by regulatory agencies are summarized in Table 2. Table 2: Estimates (Hazard Ratios) of Venous Thromboembolism Risk in Current Users of Zumandimine Compared to Users of Oral Contraceptives that Contain Other Progestins a) “New users” - no use of combination hormonal contraception for at least the prior 6 months b) Includes low-dose COCs containing the following progestins: norgestimate, norethindrone, levonorgestrel, desogestrel, norgestrel, medroxyprogesterone, or ethynodiol diacetate c) Includes low-dose COCs containing the following progestins: levonorgestrel, desogestrel, dienogest, chlormadinone acetate, gestodene, cyproterone acetate, norgestimate, or norethindrone d) Includes low-dose COCs containing the following progestins: norgestimate, norethindrone, or levonorgestrel Epidemiologic Study (Author, Year of Publication) Population Studied Comparator Product (all are low-dose COCs; with ≤ 0.04 mg of EE) Hazard Ratio (HR) (95% CI) i3 Ingenix (Seeger 2007) Initiators, including new users a All COCs available in the US during the conduct of the study b HR: 0.9 (0.5 to 1.6) EURAS (Dinger 2007) Initiators, including new users a All COCs available in Europe during the conduct of the study c Levonorgestrel/EE HR: 0.9 (0.6 to 1.4) HR: 1.0 (0.6 to 1.8) “FDA-funded study” (2011) New users a All users (i.e., initiation and continuing use of study combination hormonal contraception) Other COCs available during the course of t… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions with the use of COCs are discussed elsewhere in the labeling: Serious cardiovascular events and stroke [see Boxed Warning and Warnings and Precautions (5.1) ] Vascular events [see Warnings and Precautions (5.1) ] Liver disease [see Warnings and Precautions (5.4) ] The most frequent adverse reactions (≥ 2%) are premenstrual syndrome (13.2%), headache /migraine (10.7%), breast pain/tenderness/discomfort (8.3%), nausea/vomiting (4.5%), abdominal pain/tenderness/discomfort (2.3%), mood changes (2.3%).
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, the adverse reaction rates observed cannot be directly compared to rates in other clinical trials and may not reflect the rates observed in practice. The data provided reflect the experience with the use of Zumandimine (3 mg DRSP/0.03 mg EE) in the adequate and well-controlled studies for contraception (N=2,837). The US pivotal clinical study (N=326) was a multicenter, open-label trial in healthy women aged 18 to 35 who were treated for up to 13 cycles.
The second pivotal study (N=442)was a multicenter, randomized, open-label comparative European study of Zumandimine vs. 0.150 mg desogestrel/0.03 mg EE conducted in healthy women aged 17 to 40 who were treated for up to 26 cycles. The most common adverse reactions (≥ 2% of users) were: premenstrual syndrome (13.2%), headache/migraine (10.7%), breast pain/tenderness/discomfort (8.3%), nausea/vomiting (4.5%) abdominal pain/discomfort/tenderness (2.3%) and mood changes (depression, depressed mood, irritability, mood swings, mood altered and affect lability (2.3%).
Adverse Reactions (≥ 1%) Leading to Study Discontinuation: Of 2,837 women, 6.7% discontinued from the clinical trials due to an adverse reaction; the most frequent adverse reaction leading to discontinuation was headache/migraine (1.5%). Serious Adverse Reactions: Depression, pulmonary embolism, toxic skin eruption, and uterine leiomyoma.
6.2Postmarketing Experience Five studies that compared breast cancer risk between ever-users (current or past use) of COCs and never-users of COCs reported no association between ever use of COCs and breast cancer risk, with effect estimates ranging from 0.90 to 1.12 (Figure 3). Three studies compared breast cancer risk between current or recent COC users (<6 months since last use) and never users of COCs (Figure 3). One of these studies reported no association between breast cancer risk and COC use.
The other two studies found an increased relative risk of 1.19 to 1.33 with current or recent use. Both of these studies found an increased risk of breast cancer with current use of longer duration, with relative risks ranging from 1.03 with less than one year of COC use to approximately 1.4 with more than 8 to 10 years of COC use. Figure 3: Relative Studies of Risk of Breast Cancer with Combined Oral Contraceptives RR = relative risk; OR = odds ratio; HR = hazard ratio. “ever COC” are females with current or past COC use; “never COC use” are females that never used COCs.
The following adverse reactions have been identified during post-approval use of Zumandimine. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Adverse reactions, including fatalities, are grouped into System Organ Classes and ordered by frequency.
Vascular disorders: Venous and arterial thromboembolic events (including pulmonary emboli, deep vein thrombosis, intracardiac thrombosis, intracranial venous sinus thrombosis, sagittal sinus thrombosis, retinal vein occlusion, myocardial infarction and stroke), hypertension Hepatobiliary disorders: Gallbladder disease Immune syste… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Consult the labeling of all concurrently-used drugs to obtain further information about interactions with hormonal contraceptives or the potential for enzyme alterations . Drugs or herbal products that induce certain enzymes (for example, CYP3A4) may decrease the effectiveness of COCs or increase breakthrough bleeding. Counsel patients to use a back-up or alternative method of contraception when enzyme inducers are used with COCs.
( 7.1 )
7.1Effects of Other Drugs on Combined Oral Contraceptives Substances diminishing the efficacy of COCs: Drugs or herbal products that induce certain enzymes, including cytochrome P450 3A4 (CYP3A4), may decrease the effectiveness of COCs or increase breakthrough bleeding. Some drugs or herbal products that may decrease the effectiveness of hormonal contraceptives include phenytoin, barbiturates, carbamazepine, bosentan, felbamate, griseofulvin, oxcarbazepine, rifampin, topiramate and products containing St. John’s wort.
Interactions between oral contraceptives and other drugs may lead to breakthrough bleeding and/or contraceptive failure. Counsel women to use an alternative method of contraception or a back-up method when enzyme inducers are used with COCs, and to continue back-up contraception for 28 days after discontinuing the enzyme inducer to ensure contraceptive reliability. Substances increasing the plasma concentrations of COCs: Co-administration of atorvastatin and certain COCs containing EE increase AUC values for EE by approximately 20%.
Ascorbic acid and acetaminophen may increase plasma EE concentrations, possibly by inhibition of conjugation. Concomitant administration of moderate or strong CYP3A4 inhibitors such as azole antifungals (e.g., ketoconazole, itraconazole, voriconazole, fluconazole), verapamil, macrolides (e.g., clarithromycin, erythromycin), diltiazem, and grapefruit juice can increase the plasma concentrations of the estrogen or the progestin or both. In a clinical drug-drug interaction study conducted in premenopausal women, once daily co-administration of DRSP 3 mg/EE 0.02 mg containing tablets with strong CYP3A4 inhibitor, ketoconazole 200 mg twice daily for 10 days resulted in a moderate increase of DRSP systemic exposure.
The exposure of EE was increased mildly [see Warnings and Precautions (5.2) and Clinical Pharmacology (12.3) ] . Human immunodeficiency virus (HIV)/Hepatitis C virus (HCV) protease inhibitors and non-nucleoside reverse transcriptase inhibitors : Significant changes (increase or decrease) in the plasma concentrations of estrogen and progestin have been noted in some cases of co-administration with HIV/HCV protease inhibitors or with non-nucleoside reverse transcriptase inhibitors. Antibiotics : There have been reports of pregnancy while taking hormonal contraceptives and antibiotics, but clinical pharmacokinetic studies have not shown consistent effects of antibiotics on plasma concentrations of synthetic steroids.
7.2Effects of Combined Oral Contraceptives on Other Drugs COCs containing EE may inhibit the metabolism of other compounds. COCs have been shown to significantly decrease plasma concentrations of lamotrigine, likely due to induction of lamotrigine glucuronidation. This may reduce seizure control; therefore, dosage adjustments of lamotrigine may be necessary.
Consult the labeling of the concurrently-used drug to obtain further information about interactions with COCs or the potential for enzyme alterations. COCs Increasing the Plasma Concentrations of CYP450 Enzymes : In clinical studies, administration of a hormonal contraceptive containing EE did not lead to any increase or only to a weak increase in plasma concentrations of CYP3A4 substrates (e.g., midazolam) while plasma concentrations of CYP2C19 substrates (e.g., omeprazole and voriconazole) and CYP1A2 substrates (e.g., theophylline and tizanidine) can have a weak or moderate increase.
Clinical studies did not indicate an inhibitory potential of DRSP towards… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Can reduce milk production in breast-feeding females ( 8.2 )
8.1Pregnancy Risk Summary There is no use for contraception in pregnancy; therefore, Zumandimine should be discontinued during pregnancy. Epidemiologic studies and meta-analyses have not found an increased risk of genital or non-genital birth defects (including cardiac anomalies and limb-reduction defects) following exposure to CHCs before conception or during early pregnancy. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4 percent and 15 to 20 percent, respectively.
Data Human Data A retrospective database study of women in Norway, that included 44,734 pregnancies of which 368 were women who inadvertently took drospirenone/ethinyl estradiol during the first trimester of a pregnancy, found there were no adverse effects on pre-term birth, small for gestational age, or birth weight Z-scores. Post-marketing adverse event data on the use of Zumandimine in pregnant women suggest that frequencies of miscarriage and congenital anomalies were not higher than the estimated background risk in the general population.
8.2Lactation Risk Summary DRSP is present in human milk. After a single oral administration of 3 mg DRSP/0.03 mg EE tablets, DRSP concentration in breast milk over the 24-h period ranged from 1.4 to 7 ng/mL, with a mean ± standard deviation value of 3.7 ± 1.9 ng/mL. The estimated mean infant dose was 0.003 mg/day, which is about 0.1% of maternal dose (see Data).
There is limited information on the effects of Zumandimine on the breast-fed infant. CHCs can reduce milk production in breast-feeding females. This reduction can occur at any time but is less likely to occur once breast-feeding is well-established.
When possible, advise the nursing female to use other methods of contraception until she discontinues breast-feeding. [See also Dosage and Administration (2.2) ]. The developmental and health benefits of breast-feeding should be considered along with the mother’s clinical need for Zumandimine and any potential adverse effects on the breast-fed child from Zumandimine or from the underlying maternal condition. Data Human Data An open-label study evaluated the degree of DRSP transfer into milk within 72 hours following a single oral administration of 3 mg DRSP/0.03 mg EE tablets to 6 healthy lactating women who were 1 week to 3 months post-partum.
DRSP was present in breast milk with a mean C max of 13.5 ng/mL, while the mean C max in serum of lactating women was 30.8 ng/mL. The DRSP concentration in breast milk over the 24-hour period following dosing ranged from 1.4 to 7 ng/mL, with a mean ± standard deviation value of 3.7 ± 1.9 ng/mL. Based on single dose data, the maximal daily infant dose of DRSP was calculated to be 0.003 mg/day, which represented a mean of 0.1% of the maternal dose.
8.4Pediatric Use Safety and efficacy of Zumandimine has been established in women of reproductive age. Efficacy is expected to be the same for postpubertal adolescents under the age of 18 and for users 18 years and older. Use of this product before menarche is not indicated.
8.5Geriatric Use Zumandimine has not been studied in postmenopausal women and is not indicated in this population.
8.6Patients with Renal Impairment Zumandimine is contraindicated in patients with renal impairment [see Contraindications (4) and Warnings and Precautions (5.2)] . In subjects with creatinine clearance (CLcr) of 50 to 79 mL/min, serum DRSP concentrations were comparable to those in a control group with CLcr ≥ 80 mL/min. In subjects with CLcr of 30 to 49 mL/min, serum DRSP concentrations were on average 37% higher than those in the control group.
In addition, there is a potential to develop hyperkalemia in subjects with renal impairment whose serum potassium is in the upper reference range, and who are concomitantly using potassium sparing drugs [see C… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There is no use for contraception in pregnancy; therefore, Zumandimine should be discontinued during pregnancy. Epidemiologic studies and meta-analyses have not found an increased risk of genital or non-genital birth defects (including cardiac anomalies and limb-reduction defects) following exposure to CHCs before conception or during early pregnancy. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4 percent and 15 to 20 percent, respectively.
Data Human Data A retrospective database study of women in Norway, that included 44,734 pregnancies of which 368 were women who inadvertently took drospirenone/ethinyl estradiol during the first trimester of a pregnancy, found there were no adverse effects on pre-term birth, small for gestational age, or birth weight Z-scores. Post-marketing adverse event data on the use of Zumandimine in pregnant women suggest that frequencies of miscarriage and congenital anomalies were not higher than the estimated background risk in the general population.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and efficacy of Zumandimine has been established in women of reproductive age. Efficacy is expected to be the same for postpubertal adolescents under the age of 18 and for users 18 years and older. Use of this product before menarche is not indicated.
🧓 Geriatric Use ▾
8.5Geriatric Use Zumandimine has not been studied in postmenopausal women and is not indicated in this population.
🆘 Overdosage ▾
10 OVERDOSAGE There have been no reports of serious ill effects from overdose, including ingestion by children. Overdosage may cause withdrawal bleeding in females and nausea. DRSP is a spironolactone analogue which has anti-mineralocorticoid properties. Serum concentration of potassium and sodium, and evidence of metabolic acidosis, should be monitored in cases of overdose.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action COCs lower the risk of becoming pregnant primarily by suppressing ovulation.
12.2Pharmacodynamics Drospirenone is a spironolactone analogue with anti-mineralocorticoid activity. The estrogen in Zumandimine is ethinyl estradiol (EE). No specific pharmacodynamic studies were conducted with Zumandimine.
12.3Pharmacokinetics Absorption The absolute bioavailability of DRSP from a single entity tablet is about 76%. The absolute bioavailability of EE is approximately 40% as a result of presystemic conjugation and first-pass metabolism. The absolute bioavailability of Zumandimine, which is a combination tablet of DRSP and EE, has not been evaluated.
Serum concentrations of DRSP and EE reached peak levels within 1 to 2 hours after administration of Zumandimine. The pharmacokinetics of DRSP are dose proportional following single doses ranging from 1 to 10 mg. Following daily dosing of Zumandimine, steady state DRSP concentrations were observed after 8 days.
There was about 2 to 3 fold accumulation in serum C max and AUC (0-24h) values of DRSP following multiple dose administration of Zumandimine (see Table 3). For EE, steady-state conditions are reported during the second half of a treatment cycle. Following daily administration of Zumandimine serum C max and AUC (0-24h) values of EE accumulate by a factor of about 1.5 to 2 (see Table 3).
Table 3: Mean Pharmacokinetic Parameters of Zumandimine (DRSP 3 mg and EE 0.03 mg) DRSP Mean (%CV) Values Cycle / Day No. of Subjects C max (ng/mL) T max (h) AUC(0-24h) (ng•h/mL) t 1/2 (h) 1/1 12 36.9 (13) 1.7 (47) 288 (25) NA 1/21 12 87.5 (59) 1.7 (20) 827 (23) 30.9 (44) 6/21 12 84.2 (19) 1.8 (19) 930 (19) 32.5 (38) 9/21 12 81.3 (19) 1.6 (38) 957 (23) 31.4 (39) 13/21 12 78.7 (18) 1.6 (26) 968 (24) 31.1 (36) EE Mean (%CV) Values Cycle / Day No. of Subjects C max (pg/mL) T max (h) AUC(0-24h) (pg•h/mL) t 1/2 (h) 1/1 11 53.5 (43) 1.9 (45) 280 (87) NA 1/21 11 92.1 (35) 1.5 (40) 461 (94) NA 6/21 11 99.1 (45) 1.5 (47) 346 (74) NA 9/21 11 87 (43) 1.5 (42) 485 (92) NA 13/21 10 90.5 (45) 1.6 (38) 469 (83) NA NA - Not available Food Effect The rate of absorption of DRSP and EE following single administration of a formulation similar to Zumandimine was slower under fed (high fat meal) conditions with the serum C max being reduced about 40% for both components.
The extent of absorption of DRSP, however, remained unchanged. In contrast, the extent of absorption of EE was reduced by about 20% under fed conditions. Distribution DRSP and EE serum concentrations decline in two phases.
The apparent volume of distribution of DRSP is approximately 4 L/kg and that of EE is reported to be approximately 4 to 5 L/kg. DRSP does not bind to sex hormone binding globulin (SHBG) or corticosteroid binding globulin (CBG) but binds about 97% to other serum proteins. Multiple dosing over 3 cycles resulted in no change in the free fraction (as measured at trough concentrations).
EE is reported to be highly but non-specifically bound to serum albumin (approximately 98.5 %) and induces an increase in the serum concentrations of both SHBG and CBG. EE induced effects on SHBG and CBG were not affected by variation of the DRSP dosage in the range of 2 to 3 mg. Metabolism The two main metabolites of DRSP found in human plasma were identified to be the acid form of DRSP generated by opening of the lactone ring and the 4,5-dihydrodrospirenone-3-sulfate, formed by reduction and subsequent sulfation.
These metabolites were shown not to be pharmacologically active. Drospirenone is also subject to oxidative metabolism catalyzed by CYP3A4. EE has been reported to be subject to significant gut and hepatic first-pass metabolism.
Metabolism of EE and its oxidative metabolites occur primarily by conjugation with glucuronide or sulfate. CYP3A4 in the liver is responsible for the 2-hydroxylation which is the major oxidative reaction. The 2-hydroxy metabolite is further transformed by methylation and gluc… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action COCs lower the risk of becoming pregnant primarily by suppressing ovulation.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Zumandimine (drospirenone and ethinyl estradiol) tablets, USP are light pink to pink, round, flat faced, beveled-edge tablets, debossed with “S” on one side and “76” on other side. Each green, round, mottled, flat faced beveled-edge, uncoated tablets are debossed with “S” on one side and “37” on other side. They are available in blister packs of 28 tablets each.
The blister packs are available in the following packages: The Blister Packs are packed in pouches and the pouches are packaged in cartons Carton of 1 Pouch NDC 59651-030-87 Carton of 3 Pouches NDC 59651-030-88 The Blister Packs are packed in cartons Carton of 1 Blister Pack NDC 59651-030-28 Carton of 3 Blister Packs NDC 59651-030-85
16.2Storage Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Zumandimine (drospirenone and ethinyl estradiol tablets, USP) provide an oral contraceptive regimen consisting of 28 tablets that contain the ingredients specified for each tablet below: 21 light pink to pink tablets contains 3 mg DRSP and 0.03 mg EE 7 inert green tablets The inactive ingredients in the light pink to pink tablets are corn starch, FD&C Red no. 40, lactose monohydrate, magnesium stearate, povidone, talc and vitamin-E. The green inert tablets contain anhydrous lactose, croscarmellose sodium, FD &C Blue No.2 aluminum lake, ferric oxide yellow, magnesium stearate, microcrystalline cellulose and povidone.
Drospirenone (6R,7R,8R,9S,10R,13S,14S,15S,16S,17S)-1,3',4',6,6a,7,8,9,10,11,12,13, 14,15,15a,16-hexadecahydro-10,13-dimethylspiro-[17H-dicyclopropa-[6,7:15,16] cyclopenta[a]phenanthrene-17,2'(5H)-furan]-3,5'(2H)-dione) is a synthetic progestational compound and has a molecular weight of 366.5 and a molecular formula of C 24 H 30 O 3 . Ethinyl estradiol (19-nor-17α-pregna 1,3,5(10)-triene-20-yne-3,17-diol) is a synthetic estrogenic compound and has a molecular weight of 296.4 and a molecular formula of C 20 H 24 O 2 .
The structural formulas are as follows: FDA approved dissolution test specifications differ from USP. Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Counsel patients that cigarette smoking increases the risk of serious cardiovascular events from COC use, and that women who are over 35 years old and smoke should not use COCs. Counsel patients that the increased risk of VTE compared to non-users of COCs is greatest after initially starting a COC or restarting (following a 4-week or greater pill-free interval) the same or a different COC.
Counsel patients about the information regarding the risk of VTE with DRSP-containing COCs compared to COCs that contain levonorgestrel or some other progestins. Counsel patients that Zumandimine does not protect against HIV infection (AIDS) and other sexually transmitted diseases. Counsel patients on Warnings and Precautions associated with COCs.
Counsel patients that Zumandimine contains DRSP. Drospirenone may increase potassium. Patients should be advised to inform their healthcare provider if they have kidney, liver or adrenal disease because the use of Zumandimine in the presence of these conditions could cause serious heart and health problems.
They should also inform their healthcare provider if they are currently on daily, long-term treatment (NSAIDs, potassium-sparing diuretics, potassium supplementation, ACE inhibitors, angiotensin-II receptor antagonists, heparin or aldosterone antagonists) for a chronic condition or taking strong CYP3A4 inhibitors. Inform patients that Zumandimine is not indicated during pregnancy. If pregnancy occurs during treatment with Zumandimine, instruct the patient to stop further intake.
Counsel patients to take one tablet daily by mouth at the same time every day. Instruct patients what to do in the event pills are missed. Counsel patients to use a back-up or alternative method of contraception when enzyme inducers are used with COCs.
Counsel patients who are breastfeeding or who desire to breastfeed that COCs may reduce breast milk production. This is less likely to occur if breastfeeding is well established. Counsel any patient who starts COCs postpartum, and who has not yet had a period, to use an additional method of contraception until she has taken a light pink to pink tablet for 7 consecutive days.
Counsel patients that amenorrhea may occur. Rule out pregnancy in the event of amenorrhea in two or more consecutive cycles. Distributed by: Aurobindo Pharma USA, Inc.
279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 032, India Revised: 10/2023
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption The absolute bioavailability of DRSP from a single entity tablet is about 76%. The absolute bioavailability of EE is approximately 40% as a result of presystemic conjugation and first-pass metabolism. The absolute bioavailability of Zumandimine, which is a combination tablet of DRSP and EE, has not been evaluated.
Serum concentrations of DRSP and EE reached peak levels within 1 to 2 hours after administration of Zumandimine. The pharmacokinetics of DRSP are dose proportional following single doses ranging from 1 to 10 mg. Following daily dosing of Zumandimine, steady state DRSP concentrations were observed after 8 days.
There was about 2 to 3 fold accumulation in serum C max and AUC (0-24h) values of DRSP following multiple dose administration of Zumandimine (see Table 3). For EE, steady-state conditions are reported during the second half of a treatment cycle. Following daily administration of Zumandimine serum C max and AUC (0-24h) values of EE accumulate by a factor of about 1.5 to 2 (see Table 3).
Table 3: Mean Pharmacokinetic Parameters of Zumandimine (DRSP 3 mg and EE 0.03 mg) DRSP Mean (%CV) Values Cycle / Day No. of Subjects C max (ng/mL) T max (h) AUC(0-24h) (ng•h/mL) t 1/2 (h) 1/1 12 36.9 (13) 1.7 (47) 288 (25) NA 1/21 12 87.5 (59) 1.7 (20) 827 (23) 30.9 (44) 6/21 12 84.2 (19) 1.8 (19) 930 (19) 32.5 (38) 9/21 12 81.3 (19) 1.6 (38) 957 (23) 31.4 (39) 13/21 12 78.7 (18) 1.6 (26) 968 (24) 31.1 (36) EE Mean (%CV) Values Cycle / Day No. of Subjects C max (pg/mL) T max (h) AUC(0-24h) (pg•h/mL) t 1/2 (h) 1/1 11 53.5 (43) 1.9 (45) 280 (87) NA 1/21 11 92.1 (35) 1.5 (40) 461 (94) NA 6/21 11 99.1 (45) 1.5 (47) 346 (74) NA 9/21 11 87 (43) 1.5 (42) 485 (92) NA 13/21 10 90.5 (45) 1.6 (38) 469 (83) NA NA - Not available Food Effect The rate of absorption of DRSP and EE following single administration of a formulation similar to Zumandimine was slower under fed (high fat meal) conditions with the serum C max being reduced about 40% for both components.
The extent of absorption of DRSP, however, remained unchanged. In contrast, the extent of absorption of EE was reduced by about 20% under fed conditions. Distribution DRSP and EE serum concentrations decline in two phases.
The apparent volume of distribution of DRSP is approximately 4 L/kg and that of EE is reported to be approximately 4 to 5 L/kg. DRSP does not bind to sex hormone binding globulin (SHBG) or corticosteroid binding globulin (CBG) but binds about 97% to other serum proteins. Multiple dosing over 3 cycles resulted in no change in the free fraction (as measured at trough concentrations).
EE is reported to be highly but non-specifically bound to serum albumin (approximately 98.5 %) and induces an increase in the serum concentrations of both SHBG and CBG. EE induced effects on SHBG and CBG were not affected by variation of the DRSP dosage in the range of 2 to 3 mg. Metabolism The two main metabolites of DRSP found in human plasma were identified to be the acid form of DRSP generated by opening of the lactone ring and the 4,5-dihydrodrospirenone-3-sulfate, formed by reduction and subsequent sulfation.
These metabolites were shown not to be pharmacologically active. Drospirenone is also subject to oxidative metabolism catalyzed by CYP3A4. EE has been reported to be subject to significant gut and hepatic first-pass metabolism.
Metabolism of EE and its oxidative metabolites occur primarily by conjugation with glucuronide or sulfate. CYP3A4 in the liver is responsible for the 2-hydroxylation which is the major oxidative reaction. The 2-hydroxy metabolite is further transformed by methylation and glucuronidation prior to urinary and fecal excretion .
Excretion DRSP serum concentrations are characterized by a terminal disposition phase half-life of approximately 30 hours after both single and multiple dose regimens. Excretion of DRSP was nearly complete after ten days and amounts excreted were slightly higher in feces compared to urine. DRSP was ex… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Drospirenone is a spironolactone analogue with anti-mineralocorticoid activity. The estrogen in Zumandimine is ethinyl estradiol (EE). No specific pharmacodynamic studies were conducted with Zumandimine.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES In the clinical efficacy studies of up to 2 years duration, 2,629 subjects completed 33,160 cycles of use without any other contraception. The mean age of the subjects was 25.5 ± 4.7 years. The age range was 16 to 37 years.
The racial demographic was: 83% Caucasian, 1% Hispanic, 1% Black, <1% Asian, <1% other, <1% missing data, 14% not inquired and <1% unspecified. Pregnancy rates in the clinical trials were less than one per 100 woman-years of use.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In a 24 month oral carcinogenicity study in mice dosed with 10 mg/kg/day DRSP alone or 1 + 0.01, 3 + 0.03 and 10 + 0.1 mg/kg/day of DRSP and EE, 0.1 to 2 times the exposure (AUC of DRSP) of women taking a contraceptive dose, there was an increase in carcinomas of the harderian gland in the group that received the high dose of DRSP alone. In a similar study in rats given 10 mg/kg/day DRSP alone or 0.3 + 0.003, 3 + 0.03 and 10 + 0.1 mg/kg/day DRSP and EE, 0.8 to 10 times the exposure of women taking a contraceptive dose, there was an increased incidence of benign and total (benign and malignant) adrenal gland pheochromocytomas in the group receiving the high dose of DRSP.
Mutagenesis studies for DRSP were conducted in vivo and in vitro and no evidence of mutagenic activity was observed [See Warnings and Precautions (5.3 , 5.4) ] .
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In a 24 month oral carcinogenicity study in mice dosed with 10 mg/kg/day DRSP alone or 1 + 0.01, 3 + 0.03 and 10 + 0.1 mg/kg/day of DRSP and EE, 0.1 to 2 times the exposure (AUC of DRSP) of women taking a contraceptive dose, there was an increase in carcinomas of the harderian gland in the group that received the high dose of DRSP alone. In a similar study in rats given 10 mg/kg/day DRSP alone or 0.3 + 0.003, 3 + 0.03 and 10 + 0.1 mg/kg/day DRSP and EE, 0.8 to 10 times the exposure of women taking a contraceptive dose, there was an increased incidence of benign and total (benign and malignant) adrenal gland pheochromocytomas in the group receiving the high dose of DRSP.
Mutagenesis studies for DRSP were conducted in vivo and in vitro and no evidence of mutagenic activity was observed [See Warnings and Precautions (5.3 , 5.4) ] .
📚 References ▾
15 REFERENCES Seeger, J.D., Loughlin, J., Eng, P.M., Clifford, C.R., Cutone, J., and Walker, A.M. (2007). Risk of thromboembolism in women taking ethinylestradiol/drospirenone and other oral contraceptives.
Obstet Gynecol 110 , 587-593. Dinger, J.C., Heinemann, L.A., and Kuhl-Habich, D. (2007).
The safety of a drospirenone-containing oral contraceptive: final results from the European Active Surveillance Study on oral contraceptives based on 142,475 women-years of observation. Contraception 75 , 344-354. Combined hormonal contraceptives (CHCs) and the risk of cardiovascular endpoints.
Sidney, S. (primary author) http://www.fda.gov/downloads/Drugs/DrugSafety/UCM277384.pdf, accessed Oct 27, 2011. Lidegaard, O., Lokkegaard, E., Svendsen, A.L., and Agger, C.
(2009). Hormonal contraception and risk of venous thromboembolism: national follow-up study. BMJ 339 , b2890.
Lidegaard, O., Nielsen, L.H., Skovlund, C.W., Skjeldestad, F.E., and Lokkegaard, E. (2011). Risk of venous thromboembolism from use of oral contraceptives containing different progestogens and oestrogen doses: Danish cohort study, 2001-9.
BMJ 343 , d6423. van Hylckama Vlieg, A., Helmerhorst, F.M., Vandenbroucke, J.P., Doggen, C.J., and Rosendaal, F.R. (2009). The venous thrombotic risk of oral contraceptives, effects of oestrogen dose and progestogen type: results of the MEGA case-control study.
BMJ 339 , b2921. Dinger, J., Assmann, A., Mohner, S., and Minh, T.D. (2010).
Risk of venous thromboembolism and the use of dienogest- and drospirenone-containing oral contraceptives: results from a German case-control study. J Fam Plann Reprod Health Care 36 , 123-129. Jick, S.S., and Hernandez, R.K.
(2011). Risk of non-fatal venous thromboembolism in women using oral contraceptives containing drospirenone compared with women using oral contraceptives containing levonorgestrel: case-control study using United States claims data. BMJ 342 , d2151.
Parkin, L., Sharples, K., Hernandez, R.K., and Jick, S.S. (2011). Risk of venous thromboembolism in users of oral contraceptives containing drospirenone or levonorgestrel: nested case-control study based on UK General Practice Research Database.
BMJ 342 , d2139.
📄 Patient Package Insert ▾
FDA Approved Patient Labeling Guide for Using Zumandimine ® (drospirenone and ethinyl estradiol tablets, USP) WARNING TO WOMEN WHO SMOKE Do not use Zumandimine if you smoke cigarettes and are over 35 years old. Smoking increases your risk of serious cardiovascular side effects (heart and blood vessel problems) from birth control pills, including death from heart attack, blood clots or stroke. This risk increases with age and the number of cigarettes you smoke.
Birth control pills help to lower the chances of becoming pregnant when taken as directed. They do not protect against HIV infection (AIDS) and other sexually transmitted diseases. What is Zumandimine?
Zumandimine is a birth control pill. It contains two female hormones, a synthetic estrogen called ethinyl estradiol and a progestin called drospirenone. The progestin drospirenone may increase potassium.
Therefore, you should not take Zumandimine if you have kidney, liver or adrenal disease because this could cause serious heart and health problems. Other drugs may also increase potassium. If you are currently on daily, long-term treatment for a chronic condition with any of the medications below, you should consult your healthcare provider about whether Zumandimine is right for you, and during the first month that you take Zumandimine, you should have a blood test to check your potassium level.
NSAIDs (ibuprofen [Motrin, Advil], naproxen [Aleve and others] when taken long-term and daily for treatment of arthritis or other problems) Potassium-sparing diuretics (spironolactone and others) Potassium supplementation ACE inhibitors (Capoten, Vasotec, Zestril and others) Angiotensin-II receptor antagonists (Cozaar, Diovan, Avapro and others) Heparin Aldosterone antagonists How Well Does Zumandimine Work? Your chance of getting pregnant depends on how well you follow the directions for taking your birth control pills.
The better you follow the directions, the less chance you have of getting pregnant. Based on the results of two clinical studies, about 1 woman out of 100 women may get pregnant during the first year they use Zumandimine. The following chart shows the chance of getting pregnant for women who use different methods of birth control.
Each box on the chart contains a list of birth control methods that are similar in effectiveness. The most effective methods are at the top of the chart. The box on the bottom of the chart shows the chance of getting pregnant for women who do not use birth control and are trying to get pregnant.
How Do I Take Zumandimine? 1. Be sure to read these directions before you start taking your pills or anytime you are not sure what to do.
2. The right way to take the pill is to take one pill every day at the same time in the order directed on the package. Preferably, take the pill after the evening meal or at bedtime, with some liquid, as needed.
Zumandimine can be taken without regard to meals. If you miss pills you could get pregnant. This includes starting the pack late.
The more pills you miss, the more likely you are to get pregnant. See "WHAT TO DO IF YOU MISS PILLS” below. 3.
Many women have spotting or light bleeding at unexpected times, or may feel sick to their stomach during the first 1 to 3 packs of pills. If you do have spotting or light bleeding or feel sick to your stomach, do not stop taking the pill. The problem will usually go away.
If it does not go away, check with your healthcare provider. 4. Missing pills can also cause spotting or light bleeding, even when you make up these missed pills.
On the days you take two pills, to make up for missed pills, you could also feel a little sick to your stomach. 5. If you have vomiting (within 3 to 4 hours after you take your pill), you should follow the instructions for "WHAT TO DO IF YOU MISS PILLS." If you have diarrhea or if you take certain medicines, including some antibiotics and some herbal products such as St.
John's Wort, your pills may not work as well. Use a back-up method (su… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Dosage and Administration ( 2.3 ) 5/2023 Contraindications, Pregnancy ( 4 ) Removed 5/2023 Warnings and Precautions, ( 5.11 ) Removed 5/2023
📄 Package Label / Principal Display Panel ▾
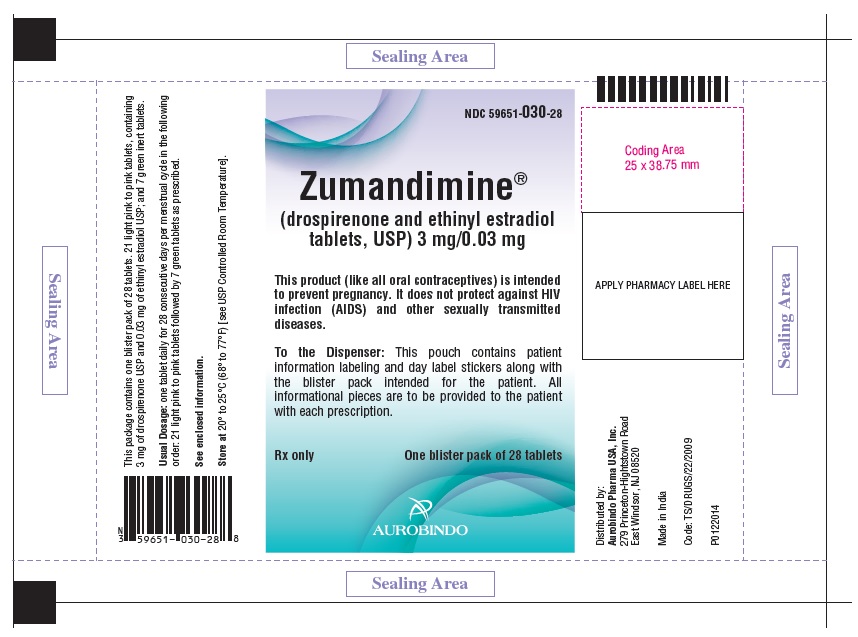
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL - 3 mg/ 0.03 mg Blister Pouch NDC 59651-030-28 Zumandimine ® (drospirenone and e thinyl estradiol tablets, USP) 3 mg/0.03 mg This product (like all oral contraceptives) is intended to prevent pregnancy. It does not protect against HIV infection (AIDS) and other sexually transmitted diseases. To the Dispenser: This pouch contains patient information labeling and day label stickers along with the blister pack intended for the patient.
All informational pieces are to be provided to the patient with each prescription. Rx only One blister pack of 28 tablets AUROBINDO PACKAGE LABEL.PRINCIPAL DISPLAY PANEL - 3 mg/ 0.03 mg Blister Pouch
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL - 3 mg/ 0.03 mg Pouch Carton NDC 59651-030-87 Zumandimine ® (drospirenone and ethinyl estradiol tablets, USP) 3 mg/0.03 mg This product (like all oral contraceptives) is intended to prevent pregnancy. It does not protect against HIV infection (AIDS) and other sexually transmitted diseases. To the Dispenser: This pouch contains patient information labeling and day label stickers along with the blister pack intended for the patient.
All informational pieces are to be provided to the patient with each prescription Rx only One blister pack of 28 tablets. AUROBINDO PACKAGE LABEL.PRINCIPAL DISPLAY PANEL - 3 mg/ 0.03 mg Pouch Carton
Medicaid utilization & spend
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |