
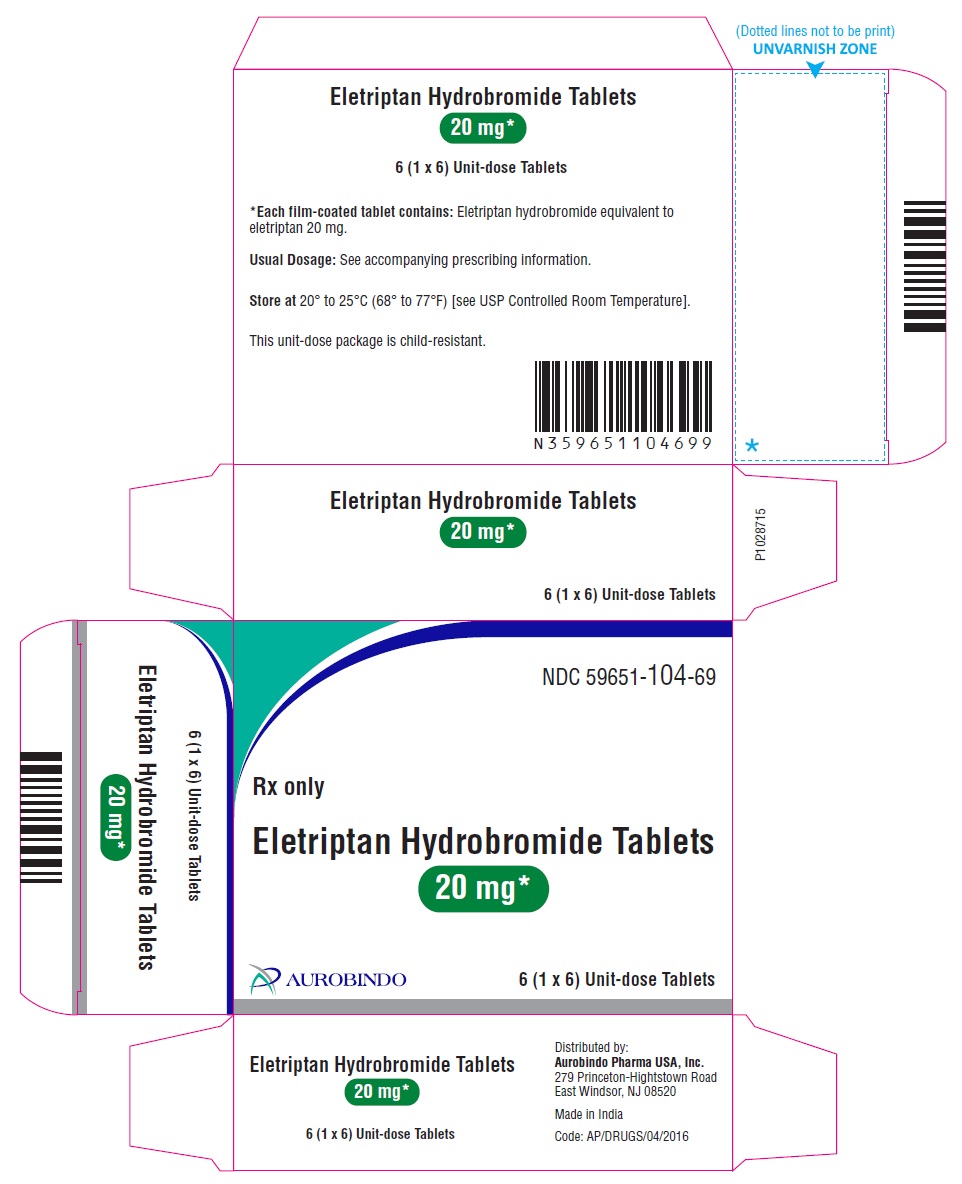
Eletriptan Hydrobromide 20 mg Tablet, Film Coated, 6-count — NDC 59651-104-69 (Billing 59651-0104-69)
This is a package of 6 tablets of Eletriptan Hydrobromide 20 mg Tablet, Film Coated from Aurobindo Pharma Limited, marketed since Jan 2019 and currently FDA-listed; retail pharmacies pay about $1.73 per tablet (NADAC). It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 049605
- GCN: 15173
- GPI-14 (Medi-Span): 67406025100320
- HICL (First Databank): 023093
- AHFS class code: 28:32.28.00
- RxCUI (RxNorm): 359493
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Serotonin-1b and Serotonin-1d Receptor Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It treats migraine attacks in adults once they've started, with or without aura. It won't prevent migraines, and it hasn't been shown to work for cluster headache.
- Take a tablet by mouth when your migraine begins, with or without food. If it isn't gone after 2 hours or it returns, you may take a second dose at least 2 hours after the first. T...
- The most common are tiredness or weakness, nausea, dizziness and sleepiness. Some people feel tingling, warmth, dry mouth, or tightness in the chest, throat or jaw. That tightness...
- Get help right away for chest pain, stroke symptoms, a dangerous heartbeat, severe belly pain with bloody diarrhea, swelling of the face or throat, or signs of serotonin syndrome l...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $1.729 | $10.38 / 6 tablets |
| Medicaid paysCMS SDUD · 12 mo | $4.17 | $25.03 / 6 tablets |
| Medicare drug plans payPart D · Q2 2026 | $4.13 | $24.80 / 6 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 59651-0104-69 You're viewing this Main listing | 1 BLISTER PACK in 1 CARTON / 6 TABLET, FILM COATED in 1 BLISTER PACK | 2019-01-15 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Eletriptan Hydrobromide 20 mg 00093-8310-18 | Teva | 1 tablet | $1.729 | AB | Availability likely | — |
| Eletriptan Hydrobromide 20 mg 00378-4287-85 | Mylan | 6 tablets | $1.729 | AB | Availability likely | — |
| Eletriptan hydrobromide 20 mg 31722-0443-31 | Camber | 6 tablets | $1.729 | AB | Availability likely | — |
| Eletriptan Hydrobromide 20 mgthis 59651-0104-69 | Aurobindo | 6 tablets | $1.729 | AB | Availability likely | — |
| Relpax 20 mg 58151-0367-56 | Viatris | 6 tablets | $77.371 | AB | Availability likely | +4374% |
| Eletriptan Hydrobromide 20 mg 24689-0167-01 | Apnar | 100 tablets | — | AB | FDA listed | — |
| Eletriptan hydrobromide 20 mg 68382-0922-06 | Zydus | 30 tablets | — | AB | FDA listed | — |
| Eletriptan hydrobromide 20 mg 70771-1107-00 | Zydus | 1000 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII X7XJ6RM9Q2
A plant-derived cellulose processed into tiny crystals. It acts as a binder and filler to give the tablet or capsule structure and helps the medicine break apart properly in your stomach.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII XHX3C3X673
Triacetin is a clear, oily liquid made from glycerin and acetic acid. It works as a plasticizer and solvent in medicines, helping soften coatings and improve how liquids mix together in formulations.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Eletriptan hydrobromide tablets are indicated for the acute treatment of migraine with or without aura in adults. Limitations of Use: Use only if a clear diagnosis of migraine has been established. If a patient has no response to the first migraine attack treated with eletriptan hydrobromide tablets, reconsider the diagnosis of migraine before eletriptan hydrobromide tablets are administered to treat any subsequent attacks.
Eletriptan hydrobromide tablets are not intended for the prevention of migraine attacks. Safety and effectiveness of eletriptan hydrobromide tablets have not been established for cluster headache. Eletriptan hydrobromide is a serotonin (5-HT 1B/1D ) receptor agonist (triptan) indicated for the acute treatment of migraine with or without aura in adults (1) Limitations of Use: Use only after a clear diagnosis of migraine has been established (1) Not indicated for the prophylactic therapy of migraine (1) Not indicated for the treatment of cluster headache (1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The maximum recommended single dose is 40 mg. In controlled clinical trials, single doses of 20 mg and 40 mg were effective for the acute treatment of migraine in adults. A greater proportion of patients had a response following a 40 mg dose than following a 20 mg dose [see Clinical Studies (14) ] .
If the migraine has not resolved by 2 hours after taking eletriptan hydrobromide tablets, or returns after transient improvement, a second dose may be administered at least 2 hours after the first dose. The maximum daily dose should not exceed 80 mg. The safety of treating an average of more than 3 migraine attacks in a 30-day period has not been established.
Single dose: 20 mg or 40 mg (2) Maximum single dose: 40 mg (2) May repeat dose after 2 hours if needed; not to exceed 80 mg in any 24-hour period (2)
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 20 mg Tablets : Orange colored, round, biconvex, film-coated tablets debossed with ‘EL’ on one side and ‘20’ on the other side. 40 mg Tablets : Orange colored, round, biconvex, film-coated tablets debossed with ‘EL’ on one side and ‘40’ on the other side. Tablets: 20 mg and 40 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Eletriptan hydrobromide tablets are contraindicated in patients with: Ischemic coronary artery disease (CAD) (angina pectoris, history of myocardial infarction, or documented silent ischemia) or coronary artery vasospasm, including Prinzmetal’s angina [see Warnings and Precautions (5.1) ]. Wolff-Parkinson-White syndrome or arrhythmias associated with other cardiac accessory conduction pathway disorders [see Warnings and Precautions (5.2) ]. History of stroke, transient ischemic attack (TIA), or history or current evidence of hemiplegic or basilar migraine because these patients are at a higher risk of stroke [see Warnings and Precautions (5.4) ].
Peripheral vascular disease [see Warnings and Precautions (5.5) ]. Ischemic bowel disease [see Warnings and Precautions (5.5) ]. Uncontrolled hypertension [see Warnings and Precautions (5.8) ].
Recent use (i.e., within 24 hours) of another 5-hydroxytryptamine 1 (5-HT 1 ) agonist, ergotamine-containing medication, or ergot-type medication such as dihydroergotamine (DHE) or methysergide [see Drug Interactions (7.1) ]. Hypersensitivity to eletriptan hydrobromide tablets (angioedema and anaphylaxis seen) [see Warnings and Precautions (5.9) ]. Recent use (i.e., within at least 72 hours) of the following potent CYP3A4 inhibitors: ketoconazole, itraconazole, nefazodone, troleandomycin, clarithromycin, ritonavir, or nelfinavir [see Drug Interactions (7.2) and Clinical Pharmacology (12.3) ].
History of coronary artery disease (CAD) or coronary artery vasospasm ( 4 ) Wolff-Parkinson-White syndrome or other cardiac accessory conduction pathway disorders ( 4 ) History of stroke, transient ischemic attack, or history or current evidence of hemiplegic or basilar migraine ( 4 ) Peripheral vascular disease ( 4 ) Ischemic bowel disease ( 4 ) Uncontrolled hypertension ( 4 ) Within 24 hours of treatment with another 5-HT 1 agonist, or an ergotamine-containing medication ( 4 ) Hypersensitivity to eletriptan hydrobromide tablets (angioedema and anaphylaxis seen) ( 4 ) Within at least 72 hours of treatment with the following potent CYP3A4 inhibitors: ketoconazole, itraconazole, nefazodone, troleandomycin, clarithromycin, ritonavir, or nelfinavir ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Eletriptan hydrobromide should only be used where a clear diagnosis of migraine has been established. Myocardial ischemia/infarction or Prinzmetal’s angina: Perform cardiac evaluation in patients with multiple cardiovascular risk factors ( 5.1 ) Arrhythmias: Discontinue eletriptan hydrobromide if occurs ( 5.2 ) Chest/throat/neck/jaw pain, tightness, pressure, or heaviness: Generally not myocardial ischemia; evaluate high risk patients for CAD ( 5.3 ) Cerebral hemorrhage, subarachnoid hemorrhage, or stroke: Discontinue eletriptan hydrobromide if occurs ( 5.4 ) Gastrointestinal ischemia or infarction events, or peripheral vasospastic reactions: Discontinue eletriptan hydrobromide if occurs ( 5.5 ) Medication overuse headache: Detoxification may be necessary ( 5.6 ) Serotonin syndrome: Discontinue eletriptan hydrobromide if occurs ( 5.7 , 7.3 )
5.1Myocardial Ischemia, Myocardial Infarction, and Prinzmetal’s Angina Eletriptan hydrobromide is contraindicated in patients with ischemic or vasospastic CAD. There have been rare reports of serious cardiac adverse reactions, including acute myocardial infarction, occurring within a few hours following administration of eletriptan hydrobromide. Some of these reactions occurred in patients without known CAD.
Eletriptan hydrobromide may cause coronary artery vasospasm (Prinzmetal’s angina), even in patients without a history of CAD. Perform a cardiovascular evaluation in triptan-naïve patients who have multiple cardiovascular risk factors (e.g., increased age, diabetes, hypertension, smoking, obesity, strong family history of CAD) prior to receiving eletriptan hydrobromide. Do not use eletriptan hydrobromide if there is evidence of CAD or coronary artery vasospasm [see Contraindications (4) ].
For patients with multiple cardiovascular risk factors who have a negative cardiovascular evaluation, consider administering the first eletriptan hydrobromide dose in a medically-supervised setting and performing an electrocardiogram (ECG) immediately following administration of eletriptan hydrobromide. For such patients, consider periodic cardiovascular evaluation in intermittent long-term users of eletriptan hydrobromide.
5.2Arrhythmias Life-threatening disturbances of cardiac rhythm including ventricular tachycardia and ventricular fibrillation leading to death have been reported within a few hours following the administration of 5-HT 1 agonists. Discontinue eletriptan hydrobromide if these disturbances occur. Eletriptan hydrobromide is contraindicated in patients with Wolff-Parkinson-White syndrome or arrhythmias associated with other cardiac accessory conduction pathway disorders [see Contraindications (4) ].
5.3Chest, Throat, Neck and/or Jaw Pain/Tightness/Pressure Sensations of tightness, pain, and pressure in the chest, throat, neck, and jaw commonly occur after treatment with eletriptan hydrobromide and are usually non-cardiac in origin. However, perform a cardiac evaluation if these patients are at high cardiac risk. Eletriptan hydrobromide is contraindicated in patients with CAD or Prinzmetal’s variant angina [see Contraindications (4) ].
5.4Cerebrovascular Events Cerebral hemorrhage, subarachnoid hemorrhage, and stroke have occurred in patients treated with 5-HT 1 agonists, and some have resulted in fatalities. In a number of cases, it appears possible that the cerebrovascular events were primary, the 5-HT 1 agonist having been administered in the incorrect belief that the symptoms experienced were a consequence of migraine, when they were not. Before treating headaches in patients not previously diagnosed as migraineurs, and in migraineurs who present with symptoms atypical of migraine, other potentially serious neurological conditions need to be excluded.
Eletriptan hydrobromide is contraindicated in patients with a history of stroke or TIA [see Contraindications (4) ].
5.5Other Vasospasm Reactions Eletriptan hydrobromide may cause non-coronary vasospastic… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are described elsewhere in other sections of the prescribing information: Myocardial ischemia and myocardial infarction, and Prinzmetal’s angina [see Warnings and Precautions (5.2) ] Arrhythmias [see Warnings and Precautions (5.3) ] Chest, throat, neck, and/or jaw pain/tightness/pressure [see Warnings and Precautions (5.4) ] Cerebrovascular events [see Warnings and Precautions (5.4) ] Other vasospasm reactions [see Warnings and Precautions (5.5) ] Medication overuse headache [see Warnings and Precautions (5.6) ] Serotonin syndrome [see Warnings and Precautions (5.7) ] Increase in blood pressure [see Warnings and Precautions (5.8) ] Hypersensitivity reactions [see Contraindications (4) and Warnings and Precautions (5.9) ] Most common adverse reactions (≥ 5% and >placebo) were asthenia, nausea, dizziness, and somnolence.
These reactions appear to be dose-related. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. Among 4,597 patients who treated the first migraine headache with eletriptan hydrobromide in short-term placebo-controlled trials, the most common adverse reactions reported with treatment with eletriptan hydrobromide were asthenia, nausea, dizziness, and somnolence.
These reactions appear to be dose-related. In long-term open-label studies where patients were allowed to treat multiple migraine attacks for up to 1 year, 128 (8.3%) out of 1,544 patients discontinued treatment due to adverse reactions. Table 1 lists adverse reactions that occurred in the subset of 5,125 migraineurs who received eletriptan doses of 20 mg, 40 mg and 80 mg or placebo in worldwide placebo-controlled clinical trials.
Only adverse reactions that were more frequent in a eletriptan hydrobromide treatment group compared to the placebo group with an incidence greater than or equal to 2% are included in Table 1. Table 1: Adverse Reactions Incidence in Placebo-Controlled Migraine Clinical Trials: Reactions Reported by ≥ 2% Patients Treated with Eletriptan Hydrobromide and More Than Placebo Adverse Reaction Type Placebo (n=988) Eletriptan Hydrobromide 20 mg (n=431) Eletriptan Hydrobromide 40 mg (n=1774) Eletriptan Hydrobromide 80 mg (n=1932) ATYPICAL SENSATIONS Paresthesia 2% 3% 3% 4% Flushing/feeling of warmth 2% 2% 2% 2% PAIN AND PRESSURE SENSATIONS Chest – tightness/pain/pressure 1% 1% 2% 4% Abdominal – pain/discomfort/stomach pain/ cramps/pressure 1% 1% 2% 2% DIGESTIVE Dry mouth 2% 2% 3% 4% Dyspepsia 1% 1% 2% 2% Dysphagia-throat tightness/difficulty swallowing 0.2% 1% 2% 2% Nausea 5% 4% 5% 8% NEUROLOGICAL Dizziness 3% 3% 6% 7% Somnolence 4% 3% 6% 7% Headache 3% 4% 3% 4% OTHER Asthenia 3% 4% 5% 10% The frequency of adverse reactions in clinical trials did not increase when up to 2 doses of eletriptan hydrobromide were taken within 24 hours.
The incidence of adverse reactions in controlled clinical trials was not affected by gender, age, or race of the patients. Adverse reaction frequencies were also unchanged by concomitant use of drugs commonly taken for migraine prophylaxis (e.g., SSRIs, beta blockers, calcium channel blockers, tricyclic antidepressants), estrogen replacement therapy or oral contraceptives.
6.2Postmarketing Experience The following adverse reaction(s) have been identified during post approval use of eletriptan hydrobromide. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Neurological: seizure Digestive: vomiting
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS
7.1Ergot-Containing Drugs Including Other 5-HT 1B/1D Agonists Ergot-containing drugs have been reported to cause prolonged vasospastic reactions. Because these effects may be additive, use of ergotamine-containing or ergot-type medications (like dihydroergotamine [DHE] or methysergide) and eletriptan hydrobromide within 24 hours of each other is contraindicated . Concomitant use of other 5-HT 1 agonists within 24 hours of eletriptan hydrobromide treatment is contraindicated [see Contraindications (4) ] .
7.2CYP3A4 Inhibitors Potent CYP3A4 inhibitors significantly increase the exposure of eletriptan hydrobromide. Eletriptan hydrobromide should not be used within at least 72 hours of treatment with potent CYP3A4 inhibitors [see Contraindications (4) and Clinical Pharmacology (12.3) ] .
7.3Selective Serotonin Reuptake Inhibitors/Serotonin and Norepinephrine Reuptake Inhibitors and Serotonin Syndrome Cases of serotonin syndrome have been reported during co-administration of triptans and SSRIs, SNRIs, TCAs and MAO inhibitors [see Warnings and Precautions (5.7) ].
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data, may cause fetal harm ( 8.1 )
8.1Pregnancy Risk Summary Available human data on the use of eletriptan hydrobromide in pregnant women are not sufficient to draw conclusions about drug-associated risk for major birth defects and miscarriage. In animal studies, oral administration of eletriptan during pregnancy or throughout pregnancy and lactation was associated with developmental toxicity (decreased fetal and pup weights, increased incidences of fetal structural abnormalities, decreased pup viability) at clinically-relevant doses [see Data] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
The reported rate of major birth defects among deliveries to women with migraine ranged from 2.2% to 2.9% and the reported rate of miscarriage was 17%, which were similar to rates reported in women without migraine. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk: Several studies have suggested that women with migraine may be at increased risk of preeclampsia and gestational hypertension during pregnancy. Data Human Data A study using linked data from the Medical Birth Registry of Norway to the Norwegian Prescription Database compared pregnancy outcomes in women who redeemed prescriptions for triptans during pregnancy, as well as a migraine disease comparison group who redeemed prescriptions for triptans before pregnancy only.
Of the 189 women who redeemed prescriptions for eletriptan during the first trimester, 4 (2.1%) had infants with major congenital malformations, while for the 174 women who redeemed prescriptions for eletriptan before, but not during, pregnancy, 11 (6.3%) had infants with major congenital malformations. Methodological limitations of this study, including small size of the eletriptan population and infrequent events, do not allow for thorough characterization of risk. Animal Data When pregnant rats were administered eletriptan (0, 10, 30, or 100 mg/kg/day) during the period of organogenesis, fetal weights were decreased and the incidences of vertebral and sternebral variations were increased at 100 mg/kg/day (approximately 12 times the maximum recommended human dose [MRHD] of 80 mg/day on a mg/m 2 basis).
The 30 and 100 mg/kg/day doses were also maternally toxic, as evidenced by decreased maternal body weight gain during gestation. The no-effect dose for adverse effects on embryofetal development in rats was 30 mg/kg/day, which is approximately 4 times the MRHD on a mg/m 2 basis. When eletriptan (0, 5, 10, or 50 mg/kg/day) was orally administered to pregnant rabbits throughout organogenesis, fetal weights were decreased at 50 mg/kg/day.
The incidences of fused sternebrae and vena cava deviations were increased at all doses. Maternal toxicity was not evident at any dose. A no-effect dose for adverse effects on embryofetal development in rabbits was not established; the lowest dose tested (5 mg/kg/day) is similar to the MRHD on a mg/m 2 basis.
Oral administration of eletriptan (0, 5, 15, or 50 mg/kg/day) to female rats throughout pregnancy and lactation resulted in a decrease in offspring viability and body weight at the highest dose tested. The no-effect dose for adverse effects on pre- and postnatal development in rats (15 mg/kg/day) is approximately 2 times the MRHD on a mg/m 2 basis.
8.2Lactation Risk Summary Eletriptan is excreted in human milk. There are no data on the effects of eletriptan on the breastfed infant or the effects of eletriptan on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for eletriptan hydrobromide and any potential adverse effects on the breastfed child from eletriptan hydrobromide or from the underlying maternal condition.
Infant exposure can be minimized by avoiding breastfeeding for 24 hou… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available human data on the use of eletriptan hydrobromide in pregnant women are not sufficient to draw conclusions about drug-associated risk for major birth defects and miscarriage. In animal studies, oral administration of eletriptan during pregnancy or throughout pregnancy and lactation was associated with developmental toxicity (decreased fetal and pup weights, increased incidences of fetal structural abnormalities, decreased pup viability) at clinically-relevant doses [see Data] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
The reported rate of major birth defects among deliveries to women with migraine ranged from 2.2% to 2.9% and the reported rate of miscarriage was 17%, which were similar to rates reported in women without migraine. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk: Several studies have suggested that women with migraine may be at increased risk of preeclampsia and gestational hypertension during pregnancy. Data Human Data A study using linked data from the Medical Birth Registry of Norway to the Norwegian Prescription Database compared pregnancy outcomes in women who redeemed prescriptions for triptans during pregnancy, as well as a migraine disease comparison group who redeemed prescriptions for triptans before pregnancy only.
Of the 189 women who redeemed prescriptions for eletriptan during the first trimester, 4 (2.1%) had infants with major congenital malformations, while for the 174 women who redeemed prescriptions for eletriptan before, but not during, pregnancy, 11 (6.3%) had infants with major congenital malformations. Methodological limitations of this study, including small size of the eletriptan population and infrequent events, do not allow for thorough characterization of risk. Animal Data When pregnant rats were administered eletriptan (0, 10, 30, or 100 mg/kg/day) during the period of organogenesis, fetal weights were decreased and the incidences of vertebral and sternebral variations were increased at 100 mg/kg/day (approximately 12 times the maximum recommended human dose [MRHD] of 80 mg/day on a mg/m 2 basis).
The 30 and 100 mg/kg/day doses were also maternally toxic, as evidenced by decreased maternal body weight gain during gestation. The no-effect dose for adverse effects on embryofetal development in rats was 30 mg/kg/day, which is approximately 4 times the MRHD on a mg/m 2 basis. When eletriptan (0, 5, 10, or 50 mg/kg/day) was orally administered to pregnant rabbits throughout organogenesis, fetal weights were decreased at 50 mg/kg/day.
The incidences of fused sternebrae and vena cava deviations were increased at all doses. Maternal toxicity was not evident at any dose. A no-effect dose for adverse effects on embryofetal development in rabbits was not established; the lowest dose tested (5 mg/kg/day) is similar to the MRHD on a mg/m 2 basis.
Oral administration of eletriptan (0, 5, 15, or 50 mg/kg/day) to female rats throughout pregnancy and lactation resulted in a decrease in offspring viability and body weight at the highest dose tested. The no-effect dose for adverse effects on pre- and postnatal development in rats (15 mg/kg/day) is approximately 2 times the MRHD on a mg/m 2 basis.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. The efficacy of eletriptan hydrobromide tablets (40 mg) in patients 11 to 17 was not established in a randomized, placebo-controlled trial of 274 adolescent migraineurs [see Clinical Studies (14) ] . Adverse reactions observed were similar in nature to those reported in clinical trials in adults.
Postmarketing experience with other triptans includes a limited number of reports that describe pediatric patients who have experienced clinically serious adverse reactions that are similar in nature to those reported rarely in adults. Long-term safety of eletriptan was studied in 76 adolescent patients who received treatment for up to one year. A similar profile of adverse reactions to that of adults was observed.
The long-term safety of eletriptan in pediatric patients has not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Blood pressure was increased to a greater extent in elderly subjects than in young subjects. The pharmacokinetic disposition of eletriptan in the elderly is similar to that seen in younger adults [see Clinical Pharmacology (12.3) ] . In clinical trials, there were no apparent differences in efficacy or the incidence of adverse reactions between patients under 65 years of age and those 65 and above.
🆘 Overdosage ▾
10 OVERDOSAGE The elimination half-life of eletriptan is about 4 hours [see Clinical Pharmacology (12.3) ] , therefore monitoring of patients after overdose with eletriptan should continue for at least 20 hours or longer while symptoms or signs persist. There is no specific antidote to eletriptan. It is unknown what effect hemodialysis or peritoneal dialysis has on the serum concentration of eletriptan.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Eletriptan binds with high affinity to 5-HT 1B , 5-HT 1D and 5-HT 1F receptors, has modest affinity for 5-HT 1A , 5-HT 1E , 5-HT 2B and 5-HT 7 receptors. Migraines are likely due to local cranial vasodilatation and/or to the release of sensory neuropeptides (vasoactive intestinal peptide, substance P and calcitonin gene-related peptide) through nerve endings in the trigeminal system. The therapeutic activity of eletriptan hydrobromide for the treatment of migraine headache is thought to be due to the agonist effects at the 5-HT 1B/1D receptors on intracranial blood vessels (including the arterio-venous anastomoses) and sensory nerves of the trigeminal system which result in cranial vessel constriction and inhibition of pro-inflammatory neuropeptide release.
12.3Pharmacokinetics Absorption: Eletriptan is well absorbed after oral administration with peak plasma levels occurring approximately 1.5 hours after dosing to healthy subjects. In patients with moderate to severe migraine the median T max is 2.0 hours. The mean absolute bioavailability of eletriptan is approximately 50%.
The oral pharmacokinetics are slightly more than dose-proportional over the clinical dose range. The AUC and C max of eletriptan are increased by approximately 20 to 30% following oral administration with a high fat meal. Eletriptan hydrobromide can be taken with or without food.
Distribution: The volume of distribution of eletriptan following IV administration is 138L. Plasma protein binding is moderate and approximately 85%. Metabolism: The N-demethylated metabolite of eletriptan is the only known active metabolite.
This metabolite causes vasoconstriction similar to eletriptan in animal models. Though the half-life of the metabolite is estimated to be about 13 hours, the plasma concentration of the N-demethylated metabolite is 10 to 20% of parent drug and is unlikely to contribute significantly to the overall effect of the parent compound. In vitro studies indicate that eletriptan is primarily metabolized by cytochrome P-450 enzyme CYP3A4 [see Contraindications (4) and Drug Interactions (7.2) ] .
Elimination: The terminal elimination half-life of eletriptan is approximately 4 hours. Mean renal clearance (CL R ) following oral administration is approximately
3.9L/h. Non-renal clearance accounts for about 90% of the total clearance. Specific Populations Age: The pharmacokinetics of eletriptan are generally unaffected by age.
Blood pressure was increased to a greater extent in elderly subjects than in young subjects [see Use in Specific Populations (8.5) ] . The pharmacokinetic disposition of eletriptan in the elderly is similar to that seen in younger adults. There is a statistically significant increased half-life (from about 4.4 hours to 5.7 hours) between elderly (65 to 93 years of age) and younger adult subjects (18 to 45 years of age) [see Use in Specific Populations (8.5) ] .
Gender: The pharmacokinetics of eletriptan are unaffected by gender. Race: A comparison of pharmacokinetic studies run in western countries with those run in Japan has indicated an approximate 35% reduction in the exposure of eletriptan in Japanese male volunteers compared to western males. Population pharmacokinetic analysis of two clinical studies indicates no evidence of pharmacokinetic differences between Caucasians and non-Caucasian patients.
Menstrual Cycle: In a study of 16 healthy females, the pharmacokinetics of eletriptan remained consistent throughout the phases of the menstrual cycle. Renal Impairment: There was no significant change in clearance observed in subjects with mild, moderate or severe renal impairment, though blood pressure elevations were observed in this population [see Warnings and Precautions (5.8) ] . Hepatic Impairment : Subjects with mild or moderate hepatic impairment demonstrated an increase in both AUC (34%) and half-life.
The C max was increased by 18%. No dose adjustment is necessary in subj… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Eletriptan binds with high affinity to 5-HT 1B , 5-HT 1D and 5-HT 1F receptors, has modest affinity for 5-HT 1A , 5-HT 1E , 5-HT 2B and 5-HT 7 receptors. Migraines are likely due to local cranial vasodilatation and/or to the release of sensory neuropeptides (vasoactive intestinal peptide, substance P and calcitonin gene-related peptide) through nerve endings in the trigeminal system. The therapeutic activity of eletriptan hydrobromide for the treatment of migraine headache is thought to be due to the agonist effects at the 5-HT 1B/1D receptors on intracranial blood vessels (including the arterio-venous anastomoses) and sensory nerves of the trigeminal system which result in cranial vessel constriction and inhibition of pro-inflammatory neuropeptide release.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Eletriptan hydrobromide tablets containing 20 mg or 40 mg eletriptan (base) as the hydrobromide salt. Eletriptan Hydrobromide Tablets 20 mg are orange colored, round, biconvex, film-coated tablets debossed with ‘EL’ on one side and ‘20’ on the other side. They are supplied as follows: Carton of 6 (1 X 6) Unit-dose Tablets NDC 59651-104-69 Eletriptan Hydrobromide Tablets 40 mg are orange colored, round, biconvex, film-coated tablets debossed with ‘EL’ on one side and ‘40’ on the other side.
They are supplied as follows: Carton of 6 (1 X 6) Unit-dose Tablets NDC 59651-105-69 Carton of 12 (2 X 6) Unit-dose Tablets NDC 59651-105-93 Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Eletriptan hydrobromide tablets contain eletriptan hydrobromide, which is a selective 5-hydroxytryptamine 1B/1D (5-HT1B/1D) receptor agonist. Eletriptan hydrobromide is chemically designated as (R)-3-[(1-Methyl-2-pyrrolidinyl)methyl]-5-[2-(phenylsulfonyl)ethyl]-1H-indole monohydrobromide, and it has the following chemical structure: The molecular formula is C 22 H 26 N 2 O 2 S . HBr, representing a molecular weight of 463.43.
Eletriptan hydrobromide is an off-white to brown color powder that is freely soluble in methanol and very slightly soluble in water. Each eletriptan hydrobromide tablet for oral administration contains 24.23 or 48.46 mg of eletriptan hydrobromide equivalent to 20 mg or 40 mg of eletriptan, respectively. Each tablet also contains the inactive ingredients croscarmellose sodium, FD&C yellow 6 aluminum lake, hypromellose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, titanium dioxide and triacetin.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA Approved Patient Labeling (Patient Information) Myocardial Ischemia and/or Infarction, Prinzmetal ’ s Angina, Other Vasospastic Reactions, and Cerebrovascular Events Inform patients that eletriptan hydrobromide may cause serious cardiovascular adverse reactions such as myocardial infarction or stroke, which may result in hospitalization and even death. Although serious cardiovascular reactions can occur without warning symptoms, instruct patients to be alert for the signs and symptoms of chest pain, shortness of breath, weakness, slurring of speech, and instruct them to ask for medical advice when observing any indicative sign or symptoms.
Instruct patients to seek medical advice if they have symptoms of other vasospastic reactions [see Warnings and Precautions (5.1 , 5.2 , 5.4 , 5.5 , and 5.8 )]. Anaphylactic/Anaphylactoid Reactions Inform patients that anaphylactic/anaphylactoid reactions have occurred in patients receiving eletriptan hydrobromide. Such reactions can be life threatening or fatal.
In general, anaphylactic reactions to drugs are more likely to occur in individuals with a history of sensitivity to multiple allergens [see Contraindications (4) ]. Medication Overuse Headache Inform patients that use of drugs to treat acute migraines for 10 or more days per month may lead to an exacerbation of headache, and encourage patients to record headache frequency and drug use (e.g., by keeping a headache diary) [see Warnings and Precautions (5.6) ]. Serotonin Syndrome Inform patients about the risk of serotonin syndrome with the use of eletriptan hydrobromide or other triptans, particularly during combined use with selective serotonin reuptake inhibitors (SSRIs) or serotonin and norepinephrine reuptake inhibitors (SNRIs) [see Warnings and Precautions (5.7) and Drug Interactions (7.3) ] .
Pregnancy Advise patients to notify their healthcare provider if they become pregnant or intend to become pregnant during therapy [see Use in Specific Populations (8.1) ]. Lactation Inform patients to notify their healthcare provider if they are breastfeeding or plan to breastfeed [see Use in Specific Populations (8.2) ]. Patient Information Eletriptan Hydrobromide Tablets (EL-e-TRIP-tan HYE-droe-BROE-mide) Please read this information before you start taking eletriptan hydrobromide tablets and each time you get a refill.
There may be new information. This information does not take the place of talking with your doctor about your medical condition or your treatment. What is the most important information I should know about eletriptan hydrobromide tablets?
Eletriptan hydrobromide tablets can cause serious side effects, including: Heart attack and other heart problems. Heart problems may lead to death. Stop taking eletriptan hydrobromide tablets and get emergency medical help right away if you have any of the following symptoms of a heart attack: discomfort in the center of your chest that lasts for more than a few minutes, or that goes away and comes back chest pain or chest discomfort that feels like an uncomfortable heavy pressure, squeezing, fullness, or pain pain or discomfort in your arms, back, neck, jaw, or stomach shortness of breath with or without chest discomfort breaking out in a cold sweat nausea or vomiting feeling lightheaded Eletriptan hydrobromide tablets are not for people with risk factors for heart disease unless a heart exam is done and shows no problem.
You have a higher risk for heart disease if you: have high blood pressure have high cholesterol levels smoke are overweight have diabetes have a family history of heart disease are a female who has gone through menopause are a male over age 40 Serotonin syndrome . Serotonin syndrome is a serious and life-threatening problem that can happen in people taking eletriptan hydrobromide tablets, especially if eletriptan hydrobromide tablets are taken with anti-depressant medicines called selective serotonin reuptake inhibitors (SSRIs)… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption: Eletriptan is well absorbed after oral administration with peak plasma levels occurring approximately 1.5 hours after dosing to healthy subjects. In patients with moderate to severe migraine the median T max is 2.0 hours. The mean absolute bioavailability of eletriptan is approximately 50%.
The oral pharmacokinetics are slightly more than dose-proportional over the clinical dose range. The AUC and C max of eletriptan are increased by approximately 20 to 30% following oral administration with a high fat meal. Eletriptan hydrobromide can be taken with or without food.
Distribution: The volume of distribution of eletriptan following IV administration is 138L. Plasma protein binding is moderate and approximately 85%. Metabolism: The N-demethylated metabolite of eletriptan is the only known active metabolite.
This metabolite causes vasoconstriction similar to eletriptan in animal models. Though the half-life of the metabolite is estimated to be about 13 hours, the plasma concentration of the N-demethylated metabolite is 10 to 20% of parent drug and is unlikely to contribute significantly to the overall effect of the parent compound. In vitro studies indicate that eletriptan is primarily metabolized by cytochrome P-450 enzyme CYP3A4 [see Contraindications (4) and Drug Interactions (7.2) ] .
Elimination: The terminal elimination half-life of eletriptan is approximately 4 hours. Mean renal clearance (CL R ) following oral administration is approximately
3.9L/h. Non-renal clearance accounts for about 90% of the total clearance. Specific Populations Age: The pharmacokinetics of eletriptan are generally unaffected by age.
Blood pressure was increased to a greater extent in elderly subjects than in young subjects [see Use in Specific Populations (8.5) ] . The pharmacokinetic disposition of eletriptan in the elderly is similar to that seen in younger adults. There is a statistically significant increased half-life (from about 4.4 hours to 5.7 hours) between elderly (65 to 93 years of age) and younger adult subjects (18 to 45 years of age) [see Use in Specific Populations (8.5) ] .
Gender: The pharmacokinetics of eletriptan are unaffected by gender. Race: A comparison of pharmacokinetic studies run in western countries with those run in Japan has indicated an approximate 35% reduction in the exposure of eletriptan in Japanese male volunteers compared to western males. Population pharmacokinetic analysis of two clinical studies indicates no evidence of pharmacokinetic differences between Caucasians and non-Caucasian patients.
Menstrual Cycle: In a study of 16 healthy females, the pharmacokinetics of eletriptan remained consistent throughout the phases of the menstrual cycle. Renal Impairment: There was no significant change in clearance observed in subjects with mild, moderate or severe renal impairment, though blood pressure elevations were observed in this population [see Warnings and Precautions (5.8) ] . Hepatic Impairment : Subjects with mild or moderate hepatic impairment demonstrated an increase in both AUC (34%) and half-life.
The C max was increased by 18%. No dose adjustment is necessary in subjects with mild or moderate hepatic impairment. The effects of severe hepatic impairment on eletriptan metabolism have not been evaluated [see Use in Specific Populations (8.6) ] .
Drug Interaction Studies CYP3A4 inhibitors: In vitro studies have shown that eletriptan is metabolized by the CYP3A4 enzyme. A clinical study demonstrated about a 3-fold increase in C max and about a 6-fold increase in the AUC of eletriptan when combined with ketoconazole. The half-life increased from 5 hours to 8 hours and the T max increased from 2.8 hours to 5.4 hours.
Another clinical study demonstrated about a 2-fold increase in C max and about a 4-fold increase in AUC when erythromycin was co-administered with eletriptan. It has also been shown that co-administration of verapamil and eletriptan yields about a 2-fold increase… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The efficacy of eletriptan hydrobromide in the acute treatment of migraines was evaluated in eight randomized, double-blind placebo-controlled studies. All eight studies used 40 mg. Seven studies evaluated an 80 mg dose and two studies included a 20 mg dose.
In all eight studies, randomized patients treated their headaches as outpatients. Seven studies enrolled adults and one study enrolled adolescents (age 11 to 17). Patients treated in the seven adult studies were predominantly female (85%) and Caucasian (94%) with a mean age of 40 years (range 18 to 78).
In all studies, patients were instructed to treat a moderate to severe headache. Headache response, defined as a reduction in headache severity from moderate or severe pain to mild or no pain, was assessed up to 2 hours after dosing. Associated symptoms such as nausea, vomiting, photophobia and phonophobia were also assessed.
Maintenance of response was assessed for up to 24 hours post dose. In the adult studies, a second dose of eletriptan hydrobromide or other medication was allowed 2 to 24 hours after the initial treatment for both persistent and recurrent headaches. The incidence and time to use of these additional treatments were also recorded.
In the seven adult studies, the percentage of patients achieving headache response 2 hours after treatment was significantly greater among patients receiving eletriptan hydrobromide at all doses compared to those who received placebo. The two-hour response rates from these controlled clinical studies are summarized in Table 2. Table 2: Percentage of Patients with Headache Response (Mild or No Headache) 2 Hours Following Treatment Placebo Eletriptan Hydrobromide 20 mg Eletriptan Hydrobromide 40 mg Eletriptan Hydrobromide 80 mg Study 1 23.8% 54.3%* 65.0%* 77.1%* (n=126) (n=129) (n=117) (n=118) Study 2 19.0% NA 61.6%* 64.6%* (n=232) (n=430) (n=446) Study 3 21.7% 47.3%* 61.9%* 58.6%* (n=276) (n=273) (n=281) (n=290) Study 4 39.5% NA 62.3%* 70.0%* (n=86) (n=175) (n=170) Study 5 20.6% NA 53.9%* 67.9%* (n=102) (n=206) (n=209) Study 6 31.3% NA 63.9%* 66.9%* (n=80) (n=169) (n=160) Study 7 29.5% NA 57.5%* NA (n=122) (n=492) * p value < 0.05 vs placebo NA - Not Applicable Comparisons of the performance of different drugs based upon results obtained in different clinical trials are never reliable.
Because studies are generally conducted at different times, with different samples of patients, by different investigators, employing different criteria and/or different interpretations of the same criteria, under different conditions (dose, dosing regimen, etc.), quantitative estimates of treatment response and the timing of response may be expected to vary considerably from study to study. The estimated probability of achieving an initial headache response within 2 hours following treatment is depicted in Figure 1.
Figure 1: Estimated Probability of Initial Headache Response Within 2 Hours* *Figure 1 shows the Kaplan-Meier plot of probability over time of obtaining headache response (no or mild pain) following treatment with eletriptan. The plot is based on 7 placebo-controlled, outpatient trials in adults providing evidence of efficacy (Studies 1 through 7). Patients not achieving headache response or taking additional treatment prior to 2 hours were censored at 2 hours.
For patients with migraine-associated photophobia, phonophobia, and nausea at baseline, there was a decreased incidence of these symptoms following administration of eletriptan hydrobromide as compared to placebo. Two to 24 hours following the initial dose of study treatment, patients were allowed to use additional treatment for pain relief in the form of a second dose of study treatment or other medication. The estimated probability of taking a second dose or other medications for migraine over the 24 hours following the initial dose of study treatment is summarized in Figure 2.
Figure 2: Estimated Probability of Taking a Second Dose/Other Medication Over th… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Eletriptan was administered to rats and mice in the diet for 104 weeks. In rats, the incidence of testicular interstitial cell adenomas was increased at the high dose of 75 mg/kg/day, but not at 15 mg/kg/day, a dose associated with plasma exposures (AUC) approximately 2 times that in humans at the MRHD of 80 mg/day. In mice, the incidence of hepatocellular adenomas was increased at the high dose of 400 mg/kg/day, but not a dose of 90 mg/kg/day, associated with plasma AUC approximately 7 times that in humans at the MRHD.
Mutagenesis Eletriptan was negative in in vitro (bacteria reverse mutation (Ames), mammalian cell gene mutation (CHO/ HGPRT), chromosomal aberration assay in human lymphocytes) and in vivo (mouse micronucleus) assays. Impairment of Fertility In a fertility and early embryonic development study, eletriptan (50, 100, or 200 mg/kg/day) was orally administered to male and female rats prior to and throughout mating and continuing in females to implantation. Plasma exposures (AUC) were 4, 8 and 16 times in males and 7, 14 and 28 times in females, respectively, that in humans at the MRHD.
Prolongation of the estrous cycle and decreases in the number of corpora lutea, implants, and viable fetuses per dam were observed at 200 mg/kg/day. Male fertility parameters were not affected.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Eletriptan was administered to rats and mice in the diet for 104 weeks. In rats, the incidence of testicular interstitial cell adenomas was increased at the high dose of 75 mg/kg/day, but not at 15 mg/kg/day, a dose associated with plasma exposures (AUC) approximately 2 times that in humans at the MRHD of 80 mg/day. In mice, the incidence of hepatocellular adenomas was increased at the high dose of 400 mg/kg/day, but not a dose of 90 mg/kg/day, associated with plasma AUC approximately 7 times that in humans at the MRHD.
Mutagenesis Eletriptan was negative in in vitro (bacteria reverse mutation (Ames), mammalian cell gene mutation (CHO/ HGPRT), chromosomal aberration assay in human lymphocytes) and in vivo (mouse micronucleus) assays. Impairment of Fertility In a fertility and early embryonic development study, eletriptan (50, 100, or 200 mg/kg/day) was orally administered to male and female rats prior to and throughout mating and continuing in females to implantation. Plasma exposures (AUC) were 4, 8 and 16 times in males and 7, 14 and 28 times in females, respectively, that in humans at the MRHD.
Prolongation of the estrous cycle and decreases in the number of corpora lutea, implants, and viable fetuses per dam were observed at 200 mg/kg/day. Male fertility parameters were not affected.
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL-20 mg (1x6) Carton NDC 59651-104-69 Rx only Eletriptan Hydrobromide Tablets 20 mg * AUROBINDO 6 (1 x 6) Unit-dose Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL-20 mg (1x6) Carton
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 40 mg (1x6) Carton NDC 59651-105-69 Rx only Eletriptan Hydrobromide Tablets 40 mg * AUROBINDO 6 (1 x 6) Unit-dose Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 40 mg (1x6) Carton