
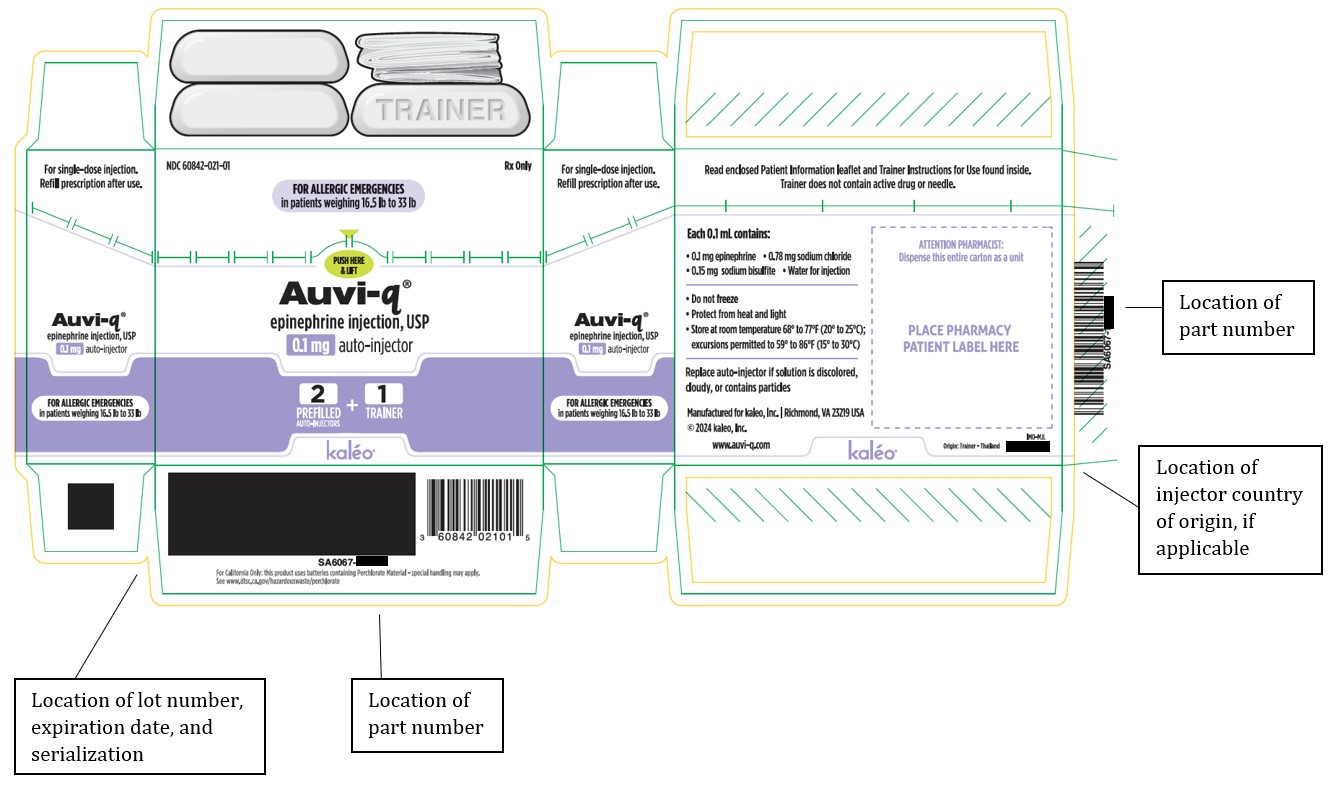
Auvi-Q epinephrine .1 mg/.1mL Injection, Solution, 2 doses
Other active recalls for Epinephrine (different manufacturers) — 2 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the alpha-Adrenergic Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Epinephrine injection is used along with emergency medical treatment to treat life-threatening allergic reactions caused by insect bites or stings, foods, medications, latex, and other causes. Epinephrine injection is also used to treat life-threatening low blood pressure associated with septic shock (a serious condition caused by a body-wide infection that can lead to dangerously low blood pressure and organ failure) in hospitalized patients. Epinephrine is in a class of medications called alpha- and beta-adrenergic agonists (sympathomimetic agents). It works by relaxing the muscles in the ai...
Read the full MedlinePlus article ↗- Epinephrine works fast but wears off quickly — sometimes in as little as 15 to 20 minutes. Anaphylaxis can come back (this is called a biphasic reaction), and you may need addition...
- Why do I need to go to the ER after using my EpiPen or Auvi-Q if I already feel better?
- Yes, it absolutely matters. Inject into the outer thigh — you can even go through your clothing if needed. Never inject into the buttocks (that spot carries a risk of serious infec...
- Where exactly do I inject it, and does it matter?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Epinephrine — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
0.15 mg / 0.1 mL
UNII TZX5469Z6I
Sodium bisulfite is a chemical salt used as a preservative and antioxidant in medicines. It prevents discoloration and degradation of active ingredients, especially in liquid formulations and injectables.
-
0.78 mg / 0.1 mL
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $309.552 | $619.10 / 2 dose packs |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J0165 | $0.234 / J0165 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Auvi-Q .1 mg/.1mLthis 60842-0021-01 | kaleo, | 2 doses | $309.552 | BX | Discontinued | — |
| Epinephrine .1 mg/.1mL 51662-1476-01 | HF | 2 doses | — | BX | FDA listed | — |
| Auvi-Q .1 mg/.1mL 51662-1661-02 | HF | 2 doses | — | BX | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 10688244 ↗ | Method of use | U-2980 | Dec 21, 2037 |
| US 10688244 ↗ | Method of use | U-2980 | Dec 21, 2037 |
| US 10842938 ↗ | Method of use | U-2980 | Dec 21, 2037 |
| US 10842938 ↗ | Method of use | U-2980 | Dec 21, 2037 |
| US 11771830 ↗ | Method of use | U-2980 | Dec 21, 2037 |
| US 11771830 ↗ | Method of use | U-2980 | Dec 21, 2037 |
| US 8226610 ↗ | Drug product | — | Apr 10, 2029 |
| US 11590286 ↗ | Drug product | — | Dec 12, 2026 |
| US 8231573 ↗ | Drug product | — | Nov 25, 2028 |
| US 8021344 ↗ | Drug product | — | Nov 2, 2029 |
| US 8206360 ↗ | Drug product | — | Feb 27, 2027 |
| US 8206360 ↗ | Drug product | — | Feb 27, 2027 |
| US 8231573 ↗ | Drug product | — | Nov 25, 2028 |
| US 7947017 ↗ | Drug product | — | Mar 12, 2028 |
| US 8021344 ↗ | Drug product | — | Nov 2, 2029 |
| US 11590286 ↗ | Drug product | — | Dec 12, 2026 |
| US 8231573 ↗ | Drug product | — | Nov 25, 2028 |
| US 7947017 ↗ | Drug product | — | Mar 12, 2028 |
| US 8226610 ↗ | Drug product | — | Apr 10, 2029 |
| US 8206360 ↗ | Drug product | — | Feb 27, 2027 |
| US 8021344 ↗ | Drug product | — | Nov 2, 2029 |
| US 8226610 ↗ | Drug product | — | Apr 10, 2029 |
| US 7947017 ↗ | Drug product | — | Mar 12, 2028 |
| US 11590286 ↗ | Drug product | — | Dec 12, 2026 |
Is there a generic version of AUVI-Q 0.1 MG AUTO-INJECTOR?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 60842-0021-01 You're viewing this | 2 DOSE PACK in 1 CARTON (60842-021-01) / .1 mL in 1 DOSE PACK | $309.55 / ea | $619.10 | 2017-11-17 | Discontinued by firm |
| 60842-0021-02 | 2 DOSE PACK in 1 CARTON (60842-021-02) / .1 mL in 1 DOSE PACK | $309.55 / ea | $619.10 | 2024-09-05 | Active |
This pack has the lowest per-ea cost of the 2 priced pack sizes ($309.55 NADAC).
This pack accounts for about 2.6% of this product's recent Medicaid fills; most go to a different pack size. See all packs ↓
Pack size FAQ
What quantity is in NDC 60842-0021-01?
What is the difference between NDC 60842-0021-01 and NDC 60842-0021-02?
What NDC number is used to bill for this package of Auvi-Q epinephrine .1 mg/.1mL Injection, Solution?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
What does the discontinued status mean for this NDC?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE AUVI-Q is indicated for the emergency treatment of type I allergic reactions, including anaphylaxis, in adult and pediatric patients who weigh 7.5 kg or greater. AUVI-Q is a non-selective alpha and beta-adrenergic receptor agonist indicated for the emergency treatment of type I allergic reactions, including anaphylaxis, in adult and pediatric patients who weigh 7.5 kg or greater. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The recommended dosage of AUVI-Q is based on weight. ( 2.1 ) Administer AUVI-Q intramuscularly or subcutaneously into the anterolateral aspect of the thigh, through clothing if necessary. ( 2.2 ) Recommended Dosage Patient’s Weight Dosage 30 kg or greater AUVI-Q 0.3 mg 15 kg to less than 30 kg AUVI-Q 0.15 mg 7.5 kg to less than 15 kg AUVI-Q 0.1 mg In the absence of clinical improvement or if symptoms worsen after the initial treatment, a second dose of AUVI-Q may be administered with a second autoinjector starting 5 minutes after the first dose.
( 2.1 ) Advise patients when to seek emergency medical assistance for close monitoring of the anaphylactic episode and in the event further treatment is required. ( 2.1 ) It is recommended that patients are prescribed and have immediate access to two AUVI-Q devices at all times. ( 2.1 ) See full prescribing information for administration instructions.
( 2.2 )
2.1Recommended Dosage The recommended dosage for patients who weigh 7.5 kg or greater is based on weight and the dosage is provided in Table 1 . Administer AUVI-Q intramuscularly or subcutaneously into the anterolateral aspect of the thigh. Table 1.
Recommended Dosage of AUVI-Q Based on Patient’s Weight Patient’s Weight Dosage 30 kg or greater AUVI-Q 0.3 mg 15 kg to less than 30 kg AUVI-Q 0.15 mg 7.5 kg to less than 15 kg AUVI-Q 0.1 mg Since the doses of epinephrine delivered from AUVI-Q are fixed, use other forms of injectable epinephrine if doses lower than 0.1 mg are deemed necessary. In the absence of clinical improvement or if symptoms worsen after the initial treatment, a second dose of AUVI-Q may be administered with a second autoinjector starting 5 minutes after the first dose.
Advise patients when to seek emergency medical assistance for close monitoring of the anaphylactic episode and in the event further treatment is required. It is recommended that patients are prescribed and have immediate access to two AUVI-Q devices at all times.
2.2Administration Instructions Each AUVI-Q contains a single dose of epinephrine for single use. Visually inspect the epinephrine solution in the viewing window of AUVI-Q for particulate matter, cloudiness, and discoloration prior to administration. Instruct caregivers of young children and infants who are prescribed AUVI-Q and who may be uncooperative and kick or move during an injection to hold the child’s leg firmly in place and limit movement prior to and during an injection [see Warnings and Precautions ( 5.1 )] .
Inject AUVI-Q intramuscularly or subcutaneously into the anterolateral aspect of the thigh, through clothing if necessary. Do not inject intravenously, and do not inject into buttocks, digits, hands or feet [see Warnings and Precautions ( 5.1 )] . If a second dose is needed, administer a new AUVI-Q starting 5 minutes after the first dose.
More than two sequential doses of epinephrine should be administered under direct medical supervision. Refer patients and caregivers to the Instructions for Use for detailed administration instructions.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: 0.3 mg (0.3 mg/0.3 mL) epinephrine injection, USP, clear and colorless solution, single-dose prefilled autoinjector 0.15 mg (0.15 mg/0.15 mL) epinephrine injection, USP, clear and colorless solution, single-dose prefilled autoinjector 0.1 mg (0.1 mg/0.1 mL) epinephrine injection, USP, clear and colorless solution, single-dose prefilled autoinjector Injection: 0.3 mg (0.3 mg/0.3 mL) epinephrine in a single-dose prefilled autoinjector ( 3 ) 0.15mg (0.15 mg/0.15 mL) epinephrine in a single-dose prefilled autoinjector ( 3 ) 0.1 mg (0.1 mg/0.1 mL) epinephrine in a single-dose prefilled autoinjector ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Do not inject intravenously, into buttock, digits, hands, or feet. ( 5.1 ) Hold the child’s leg firmly in place and limit movement prior to and during injection when administering to young children or infants to minimize the risk of injection-related injury. ( 5.1 ) Rare cases of serious skin and soft tissue infections have been reported following epinephrine injection.
Advise patients to seek medical care if they develop signs or symptoms of infection. ( 5.2 ) Administer with caution in patients with heart disease; may aggravate angina pectoris or produce ventricular arrhythmias. ( 5.3 ) May aggravate certain coexisting conditions.
( 5.3 ) The presence of a sulfite in this product should not deter use. ( 5.4 )
5.1Injection-Related Complications AUVI-Q should only be injected into the anterolateral aspect of the thigh [see Dosage and Administration ( 2.1 , 2.2 )] . Do not inject intravenously. Large doses or accidental intravenous injection of epinephrine may result in cerebral hemorrhage due to sharp rise in blood pressure.
Rapidly acting vasodilators can counteract the marked pressor effects of epinephrine for this inadvertent administration. Do not inject into buttock. Injection into the buttock may not provide effective treatment of anaphylaxis.
If AUVI-Q is injected into the buttock, advise the patient to administer a second dose of AUVI-Q into the anterolateral aspect of the thigh and if symptoms worsen or persist, then go immediately to the nearest emergency room for further treatment of anaphylaxis. Additionally, injection into the buttock has been associated with Clostridial infections (gas gangrene). Cleansing with alcohol does not kill bacterial spores, and therefore, does not lower this risk.
Do not inject into digits, hands or feet. Since epinephrine is a strong vasoconstrictor, accidental injection into the digits, hands or feet may result in loss of blood flow to the affected area and may not provide effective treatment of anaphylaxis. Advise the patient to administer a second dose of AUVI-Q into the anterolateral aspect of the thigh if experiencing anaphylaxis and then go immediately to the nearest emergency room and inform the healthcare provider in the emergency room of the location of the accidental injection.
Treatment of such inadvertent administration should consist of vasodilation, in addition to further appropriate treatment of anaphylaxis [see Adverse Reactions ( 6 )] . Hold leg firmly during injection. To minimize the risk of injection-related injury when administering AUVI-Q to young children or infants, instruct caregivers to hold the child’s leg firmly in place and limit movement prior to and during injection.
5.2Serious Infections at the Injection Site Rare cases of serious skin and soft tissue infections, including necrotizing fasciitis and myonecrosis caused by Clostridia (gas gangrene), have been reported at the injection site following epinephrine injection for anaphylaxis. Clostridium spores can be present on the skin and introduced into the deep tissue with subcutaneous or intramuscular injection. While cleansing with alcohol may reduce the presence of bacteria on the skin, alcohol cleansing does not kill Clostridium spores.
To decrease the risk of Clostridium infection, do not inject AUVI-Q into the buttock [see Warnings and Precautions ( 5.1 )] . Advise patients to seek medical care if they develop signs or symptoms of infection, such as persistent redness, warmth, swelling, or tenderness, at the epinephrine injection site.
5.3Risk Associated with Use of Epinephrine in Certain Coexisting Conditions Some patients may be at greater risk for developing adverse reactions after epinephrine administration. Despite these concerns, the presence of these conditions is not a contraindication to epinephrine administration in an acute, life-threatening situation. Therefore, instruct patients with these conditions, and/or caregivers to the circumstances under which epineph…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Injection-Related Complications [see Warnings and Precautions ( 5.1 )] Serious Infections at the Injection Site [see Warnings and Precautions ( 5.2 )] Risks Associated with Use of Epinephrine in Certain Coexisting Conditions [see Warnings and Precautions ( 5.3 )] Allergic Reactions Associated with Sulfite [see Warnings and Precautions ( 5.4 )] Adverse Reactions from Postapproval Use of Epinephrine Products The following adverse reactions have been identified during postapproval use of epinephrine.
Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Cardiovascular: angina, arrhythmias (including fatal ventricular fibrillation), cerebral hemorrhage, hypertension, pallor, palpitations, tachyarrhythmia, tachycardia, vasoconstriction, ventricular ectopy, and stress cardiomyopathy Gastrointestinal Disorders: nausea, vomiting Infections: Clostridial infections (gas gangrene) Metabolism and Nutrition Disorders: transient hyperglycemia, sweating Neurological: disorientation, impaired memory, panic, psychomotor agitations, sleepiness, tingling, weakness, hypoesthesia, dizziness, tremor, headache Psychiatric: anxiety, apprehensiveness, restlessness Respiratory: respiratory difficulties Skin and Subcutaneous Tissue Disorders: bruising, bleeding, discoloration, erythema, necrotizing fasciitis, myonecrosis Adverse reactions to epinephrine include anxiety, apprehensiveness, restlessness, tremor, weakness, dizziness, sweating, palpitations, pallor, nausea and vomiting, headache, and/or respiratory difficulties.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact kaleo, Inc. at 1-877-302-8847 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Cardiac glycosides, diuretics, or anti-arrhythmics: observe for development of cardiac arrhythmias. ( 7.1 ) Tricyclic antidepressants, monoamine oxidase inhibitors, levothyroxine sodium, certain antihistamines, and catechol-O-methyl transferase inhibitors may potentiate effects of epinephrine. ( 7.2 ) Beta-adrenergic blocking drugs antagonize cardiostimulating and bronchodilating effects of epinephrine.
( 7.3 ) Alpha-adrenergic blocking drugs antagonize vasoconstricting and hypertensive effects of epinephrine. ( 7.3 ) Ergot alkaloids may reverse the pressor effects of epinephrine. ( 7.3 )
7.1Drugs Increasing Risk of Cardiac Arrhythmias Observe patients who receive epinephrine while concomitantly taking cardiac glycosides, diuretics, or anti-arrhythmics for the development of cardiac arrhythmias [see Warnings and Precautions ( 5.3 ) and Adverse Reactions ( 6 )] .
7.2Drugs Potentiating Effects of Epinephrine The effects of epinephrine may be potentiated by tricyclic antidepressants, monoamine oxidase inhibitors, levothyroxine sodium, and certain antihistamines, notably chlorpheniramine, tripelennamine, and diphenhydramine, and catechol-O-methyl transferase (COMT) inhibitors such as entacapone.
7.3Drugs Antagonizing Effects of Epinephrine The cardiostimulating and bronchodilating effects of epinephrine are antagonized by beta- adrenergic blocking drugs, such as propranolol. The vasoconstricting and hypertensive effects of epinephrine are antagonized by alpha- adrenergic blocking drugs, such as phentolamine. Ergot alkaloids may also reverse the pressor effects of epinephrine.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Elderly patients may be at greater risk of developing adverse reactions. ( 8.5 )
8.1Pregnancy Risk Summary Prolonged experience with epinephrine use in pregnant women over several decades, based on published literature, have not identified a drug associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. There are risks to the mother and fetus associated with anaphylaxis. Epinephrine is first-line treatment of anaphylaxis and should not be delayed (see Clinical Considerations ) .
In animal reproductive studies, epinephrine administered by the subcutaneous route to rabbits, mice, and hamsters during the period of organogenesis was teratogenic at doses 7 times and higher than the maximum recommended human intramuscular and subcutaneous dose on a mg/m 2 basis (see Data ) . The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-associated maternal and embryo/fetal risk: During pregnancy, anaphylaxis can be catastrophic and can lead to hypoxic-ischemic encephalopathy and permanent central nervous system damage or death in the mother and, more commonly, in the fetus or neonate. Treatment of anaphylaxis during pregnancy should not be delayed.
Data Animal Data: In an embryofetal development study with rabbits dosed during the period of organogenesis, epinephrine was shown to be teratogenic (including gastroschisis and embryonic lethality) at doses approximately 40 times the maximum recommended intramuscular or subcutaneous dose (on a mg/m 2 basis at a maternal subcutaneous dose of 1.2 mg/kg/day for two to three days). In an embryofetal development study with mice dosed during the period of organogenesis, epinephrine was shown to be teratogenic (including embryonic lethality) at doses approximately 8 times the maximum recommended intramuscular or subcutaneous dose (on a mg/m 2 basis at a maternal subcutaneous dose of 1 mg/kg/day for 10 days).
These effects were not seen in mice at approximately 4 times the maximum recommended daily intramuscular or subcutaneous dose (on a mg/m 2 basis at a subcutaneous maternal dose of 0.5 mg/kg/day for 10 days). In an embryofetal development study with hamsters dosed during the period of organogenesis from gestation days 7 to 10, epinephrine was shown to be teratogenic at doses approximately 7 times the maximum recommended daily intramuscular or subcutaneous dose (on a mg/m 2 basis at a maternal subcutaneous dose of 0.5 mg/kg/day for 4 days).
8.2Lactation Risk Summary There is no information on the presence of epinephrine in human milk, the effects on breastfed infants, or the effects on milk production. However, due to its poor oral bioavailability and short half-life, transfer of epinephrine into breastmilk is expected to be low. Treatment of anaphylaxis in breastfeeding patients should not be delayed.
8.4Pediatric Use The safety and effectiveness of AUVI-Q for the emergency treatment of type I allergic reactions, including anaphylaxis have been established in pediatric patients who weigh 7.5 kg or greater. The use of AUVI-Q for this indication is supported by clinical experience. Clinical experience with the use of epinephrine suggests that the adverse reactions seen in pediatric patients are similar in nature and extent to those both expected and reported in adults.
Since the doses of epinephrine delivered from AUVI-Q are fixed, use other forms of injectable epinephrine if doses lower than 0.1 mg are deemed necessary. The safety and effectiveness of AUVI-Q have not been established in pediatric patients who weigh less than 7.5 kg.
8.5 Geriatric Use Clinical studies of AUVI-Q for emergency treat…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Prolonged experience with epinephrine use in pregnant women over several decades, based on published literature, have not identified a drug associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. There are risks to the mother and fetus associated with anaphylaxis. Epinephrine is first-line treatment of anaphylaxis and should not be delayed (see Clinical Considerations ) .
In animal reproductive studies, epinephrine administered by the subcutaneous route to rabbits, mice, and hamsters during the period of organogenesis was teratogenic at doses 7 times and higher than the maximum recommended human intramuscular and subcutaneous dose on a mg/m 2 basis (see Data ) . The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-associated maternal and embryo/fetal risk: During pregnancy, anaphylaxis can be catastrophic and can lead to hypoxic-ischemic encephalopathy and permanent central nervous system damage or death in the mother and, more commonly, in the fetus or neonate. Treatment of anaphylaxis during pregnancy should not be delayed.
Data Animal Data: In an embryofetal development study with rabbits dosed during the period of organogenesis, epinephrine was shown to be teratogenic (including gastroschisis and embryonic lethality) at doses approximately 40 times the maximum recommended intramuscular or subcutaneous dose (on a mg/m 2 basis at a maternal subcutaneous dose of 1.2 mg/kg/day for two to three days). In an embryofetal development study with mice dosed during the period of organogenesis, epinephrine was shown to be teratogenic (including embryonic lethality) at doses approximately 8 times the maximum recommended intramuscular or subcutaneous dose (on a mg/m 2 basis at a maternal subcutaneous dose of 1 mg/kg/day for 10 days).
These effects were not seen in mice at approximately 4 times the maximum recommended daily intramuscular or subcutaneous dose (on a mg/m 2 basis at a subcutaneous maternal dose of 0.5 mg/kg/day for 10 days). In an embryofetal development study with hamsters dosed during the period of organogenesis from gestation days 7 to 10, epinephrine was shown to be teratogenic at doses approximately 7 times the maximum recommended daily intramuscular or subcutaneous dose (on a mg/m 2 basis at a maternal subcutaneous dose of 0.5 mg/kg/day for 4 days).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of AUVI-Q for the emergency treatment of type I allergic reactions, including anaphylaxis have been established in pediatric patients who weigh 7.5 kg or greater. The use of AUVI-Q for this indication is supported by clinical experience. Clinical experience with the use of epinephrine suggests that the adverse reactions seen in pediatric patients are similar in nature and extent to those both expected and reported in adults.
Since the doses of epinephrine delivered from AUVI-Q are fixed, use other forms of injectable epinephrine if doses lower than 0.1 mg are deemed necessary. The safety and effectiveness of AUVI-Q have not been established in pediatric patients who weigh less than 7.5 kg.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of AUVI-Q for emergency treatment of type I allergic reactions, including anaphylaxis, were not conducted to determine whether they respond differently from younger patients. However, other reported clinical experience with use of epinephrine for treatment of anaphylaxis has identified that geriatric patients may be particularly sensitive to the effects of epinephrine. Therefore, these patients may be at greater risk for developing adverse reactions after epinephrine administration [see Overdosage ( 10 )] .
🆘 Overdosage ▾
10 OVERDOSAGE Overdosage of epinephrine has been reported to produce extremely elevated arterial pressure, which may result in cerebrovascular hemorrhage, particularly in elderly patients. Overdosage may also result in pulmonary edema because of peripheral vascular constriction together with cardiac stimulation. Epinephrine overdosage can also cause transient bradycardia followed by tachycardia, which may be accompanied by fatal cardiac arrhythmias; premature ventricular contractions followed by multifocal ventricular tachycardia; atrial tachycardia and occasionally by atrioventricular block; extreme pallor and coldness of the skin; metabolic acidosis; kidney failure.
Epinephrine is rapidly inactivated in the body and treatment following overdosage with epinephrine is primarily supportive. Treatment of epinephrine associated pulmonary edema consists of a rapidly acting alpha-adrenergic blocking drug (such as phentolamine mesylate) and respiratory support. Treatment of epinephrine associated arrhythmias consists of administration of a beta-adrenergic blocking drug (such as propranolol).
If necessary, pressor effects may be counteracted by rapidly acting vasodilators or α-adrenergic blocking drugs. If prolonged hypotension follows such measures, it may be necessary to administer another pressor drug. Consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdosage management recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Epinephrine acts on both alpha and beta-adrenergic receptors. Through its action on alpha-adrenergic receptors, epinephrine lessens the vasodilation and increased vascular permeability that occurs during anaphylaxis, which can lead to loss of intravascular fluid volume and hypotension. Through its action on beta-adrenergic receptors, epinephrine causes bronchial smooth muscle relaxation and helps alleviate bronchospasm, wheezing and dyspnea that may occur during anaphylaxis.
Epinephrine also alleviates pruritus, urticaria, and angioedema and may relieve gastrointestinal and genitourinary symptoms associated with anaphylaxis because of its relaxer effects on the smooth muscle of the stomach, intestine, uterus and urinary bladder.
12.2Pharmacodynamics When given subcutaneously or intramuscularly, epinephrine has a rapid onset and short duration of action.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Epinephrine acts on both alpha and beta-adrenergic receptors. Through its action on alpha-adrenergic receptors, epinephrine lessens the vasodilation and increased vascular permeability that occurs during anaphylaxis, which can lead to loss of intravascular fluid volume and hypotension. Through its action on beta-adrenergic receptors, epinephrine causes bronchial smooth muscle relaxation and helps alleviate bronchospasm, wheezing and dyspnea that may occur during anaphylaxis.
Epinephrine also alleviates pruritus, urticaria, and angioedema and may relieve gastrointestinal and genitourinary symptoms associated with anaphylaxis because of its relaxer effects on the smooth muscle of the stomach, intestine, uterus and urinary bladder.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied AUVI-Q (epinephrine injection) is a clear and colorless solution for intramuscular or subcutaneous use. AUVI-Q is available as an autoinjector as described in Table 2 . Table 2.
AUVI-Q Autoinjector Package Configurations and Strengths Package Configuration Strength National Drug Code (NDC) 2 autoinjectors 0.3 mg/0.3 mL NDC 60842-023-02 2 autoinjectors 0.15 mg/0.15 mL NDC 60842-022-02 2 autoinjectors 0.1 mg/0.1 mL NDC 60842-021-02 Storage and Handling Protect from light. Epinephrine is light sensitive and should be stored in the outer case. Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [See USP Controlled Room Temperature].
Do not freeze. Before using, check to make sure the solution in the autoinjector is clear and colorless. Replace the autoinjector if the solution is discolored, cloudy, or contains particles.
📋 Description ▾
11 DESCRIPTION AUVI-Q (epinephrine injection, USP) 0.3 mg, 0.15 mg and 0.1 mg is an autoinjector and a combination product containing drug and device components. AUVI-Q includes audible (electronic voice instructions, beeps) and visible (LED lights) cues for use. The needle automatically retracts after the injection is complete.
Each AUVI-Q 0.3 mg delivers a single dose of 0.3 mg epinephrine from epinephrine injection, USP (0.3 mL) in a sterile solution. Each AUVI-Q 0.15 mg delivers a single dose of 0.15 mg epinephrine from epinephrine injection, USP (0.15 mL) in a sterile solution. Each AUVI-Q 0.1 mg delivers a single dose of 0.1 mg epinephrine from epinephrine injection, USP (0.1 mL) in a sterile solution.
AUVI-Q 0.3 mg, AUVI-Q 0.15 mg and AUVI-Q 0.1 mg each contain 0.76 mL epinephrine solution. 0.3 mL, 0.15 mL and 0.1 mL epinephrine solution is dispensed for AUVI-Q 0.3 mg, AUVI-Q 0.15 mg and AUVI-Q 0.1 mg, respectively, when activated. The remaining solution is not available for future use and should be discarded.
Each 0.3 mL in AUVI-Q 0.3 mg contains 0.3 mg epinephrine, 2.3 mg sodium chloride, 0.45 mg sodium bisulfite, hydrochloric acid to adjust pH, and water for injection. The pH range is 2.2– 5.0. Each 0.15 mL in AUVI-Q 0.15 mg contains 0.15 mg epinephrine, 1.2 mg sodium chloride, 0.225 mg sodium bisulfite, hydrochloric acid to adjust pH, and water for injection.
The pH range is 2.2–5.0. Each 0.1 mL in AUVI-Q 0.1 mg contains 0.1 mg epinephrine, 0.78 mg sodium chloride, 0.15 mg sodium bisulfite, hydrochloric acid to adjust pH, and water for injection. The pH range is 2.2–5.0.
Epinephrine is a sympathomimetic catecholamine. Chemically, epinephrine is (-)-3,4-Dihydroxy-a-[(methylamino)methyl]benzyl alcohol with the following structure: Epinephrine solution deteriorates rapidly on exposure to air or light, turning pink from oxidation to adrenochrome and brown from the formation of melanin. AUVI-Q is not made with natural rubber latex.
AUVI-Q instructional and safety systems should be thoroughly reviewed with patients and caregivers prior to use [see Patient Counseling Information ( 17 )] . Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Administration and Training Instruct patients and/or caregivers in the appropriate use of AUVI-Q. AUVI-Q should be injected into the middle of the outer thigh (through clothing, if necessary).
Each device is a single-dose injection. Advise patients and/or caregivers when to seek emergency medical care for close monitoring of the type I allergic emergency and in the event that further treatment is required. Instruct patients and/or caregivers to inspect the epinephrine solution visually through the viewing window periodically.
AUVI-Q should be replaced if the epinephrine solution appears discolored, cloudy, or contains particles. Instruct caregivers to hold the leg of young children or infants firmly in place and limit movement prior to and during injection [see Warnings and Precautions ( 5.1 )] . Instruct patients and/or caregivers that the needle will not be visible after the injection and they may not feel the injection when it occurs.
Instruct patients and/or caregivers that AUVI-Q includes a 2- second countdown after it is activated and then the voice instructions will indicate when the injection has been completed and to seek medical care, if needed. Instruct patients that AUVI-Q’s black base will lock up onto the device housing and the lights will blink red after the injection has been completed. These post-use indicators help patients and/or caregivers know that AUVI-Q has been activated and an epinephrine injection has been administered.
Instruct patients and/or caregivers to use and practice with the Trainer to familiarize themselves with the use of AUVI-Q in an allergic emergency. The Trainer may be used multiple times. Injection-Related Complications Advise patients to seek immediate medical care in the case of accidental injection into the digits, hands, or feet because such an accidental injection to these areas may cause loss of blood flow to the affected area [see Warnings and Precautions ( 5.1 )] .
Serious Infections at the Injection Site Advise patients that rare cases of serious skin and soft tissue infections, including necrotizing fasciitis and myonecrosis caused by Clostridia (gas gangrene), have been reported at the injection site following epinephrine injection for anaphylaxis. Instruct patients to seek medical care if they develop signs or symptoms of infection, such as persistent redness, warmth, swelling, or tenderness, at the epinephrine injection site [see Warnings and Precautions ( 5.2 )] . Risks Associated with Certain Coexisting Conditions Advise patients with coexisting conditions (cardiac arrhythmia and ischemia, hypertension, pulmonary edema, hyperthyroidism, renal impairment, Parkinson’s disease, diabetes), for increased risks that may be associated with use of epinephrine [see Warnings and Precautions ( 5.3 )] .
Storage and Handling Epinephrine is light sensitive and should be stored in the outer case provided to protect it from light. Instruct patients that AUVI-Q must be used or properly disposed once the red safety guard is removed [see How Supplied/Storage and Handling ( 16 )] . Manufactured for: kaleo, Inc.
Richmond, VA 23219 USA This product may be covered by one or more U.S. patents or pending patent applications; see www.kaleo.com for details. KALÉO ® and AUVI-Q ® are registered trademarks of kaleo, Inc. © 2025 kaleo, Inc. *For California Only: This product uses batteries containing Perchlorate Material – special handling may apply. See www.dtsc.ca.gov/hazardouswaste/perchlorate