
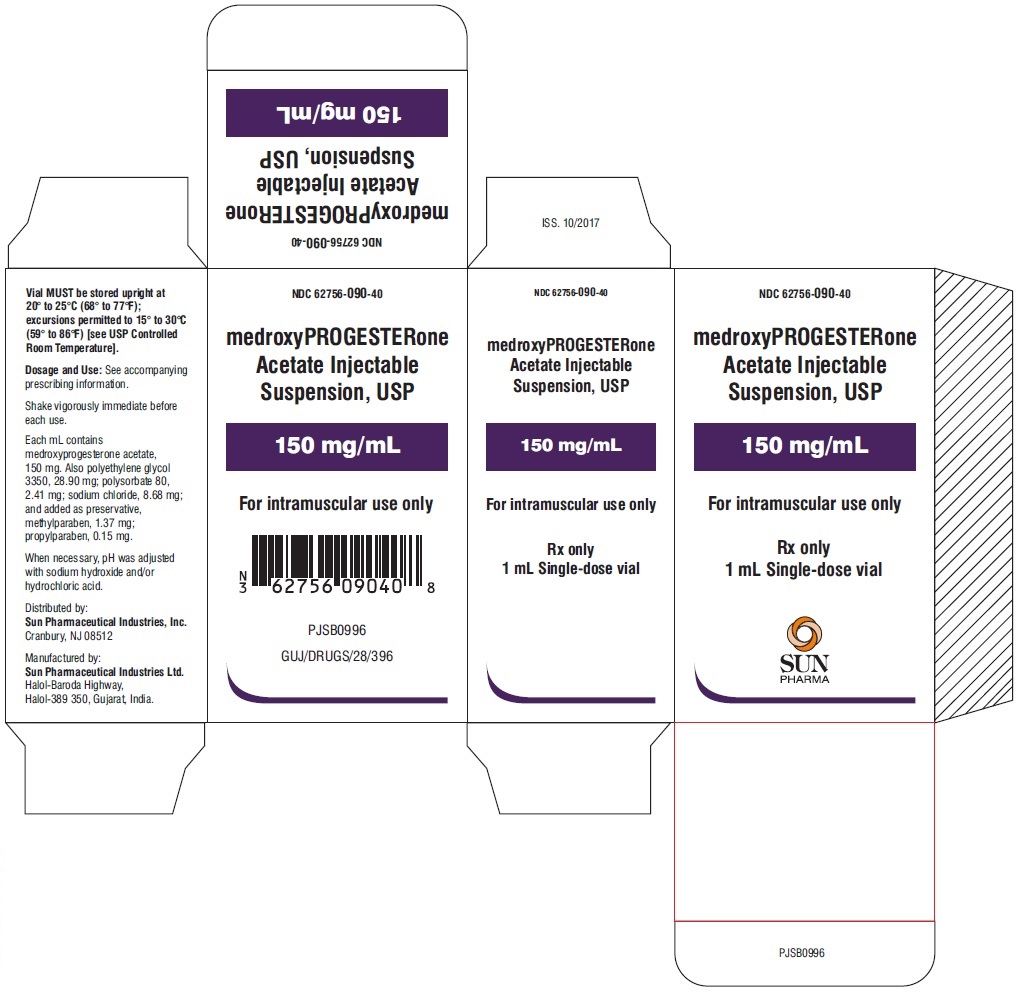
MEDROXYPROGESTERONE ACETATE 150 mg/mL Injection, Suspension, 1 vial — NDC 62756-090-40 (Billing 62756-0090-40)
This is a package of 1 vial of MEDROXYPROGESTERONE ACETATE 150 mg/mL Injection, Suspension from Sun Pharmaceutical Industries, Inc., marketed since May 2019 and currently FDA-listed; retail pharmacies pay about $26.22 per mL (NADAC).
Other active recalls for Medroxyprogesterone Acetate (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 017584
- GCN: 11251
- GPI-14 (Medi-Span): 25150035101820
- HICL (First Databank): 001442
- AHFS class code: 68:32.00.00
- RxCUI (RxNorm): 1000126
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Progestin class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Medroxyprogesterone injection is used to prevent pregnancy and to treat endometriosis (a condition in which the type of tissue that lines the uterus (womb) grows in other areas of the body and causes pain, heavy or irregular menstruation [periods], and other symptoms). Medroxyprogesterone is in a class of medications called progestins. It works to prevent pregnancy by preventing ovulation (the release of eggs from the ovaries). Medroxyprogesterone also thins the lining of the uterus which helps to prevent pregnancy in all women and slows the spread of tissue from the uterus to other parts of t...
Read the full MedlinePlus article ↗- It depends on the form. The injections prevent pregnancy, and Depo-SubQ Provera 104 also manages endometriosis-associated pain. The tablets treat missed periods and abnormal uterin...
- Depo-Provera CI and other medroxyprogesterone injectable suspensions are given into a muscle about every 3 months (13 weeks). Depo-SubQ Provera 104 is given under the skin about ev...
- Changes in your bleeding pattern are the most common, and periods often stop over time. Headache, weight gain, injection site reactions and mood changes can also occur. Call your d...
- Yes, it can lower bone mineral density, and the loss may not fully come back after stopping. That is why it is not recommended for more than 2 years unless other options are inadeq...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Medroxyprogesterone Acetate — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $26.215 | $26.22 / 1 ml |
| Medicaid paysCMS SDUD · 12 mo | $33.34 | $33.34 / 1 ml |
| Medicare drug plans payPart D · Q2 2026 | $27.44 | $27.44 / 1 ml |
| Medicare Part B allowsASP · J1050 | No ASP payment limit on file for J1050 this quarter. | |
Where does this data come from?
- CMS NADAC weekly file · file of Feb 21, 2024
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 62756-0090-40 You're viewing this | 1 VIAL, SINGLE-DOSE in 1 CARTON / 1 mL in 1 VIAL, SINGLE-DOSE | $26.22 / mL | $26.22 | 2019-05-04 | — | Active |
| 62756-0090-45 62756-090-45 Main listing | 25 VIAL, SINGLE-DOSE in 1 CARTON / 1 mL in 1 VIAL, SINGLE-DOSE | $30.77 / mL | $769.31 | 2019-05-04 | — | Active |
This pack has the lowest per-mL cost of the 2 priced pack sizes ($26.22 NADAC).
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 62756-0090-45?
What NDC number is used to bill for this package of MEDROXYPROGESTERONE ACETATE 150 mg/mL Injection, Suspension?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Medroxyprogesterone Acetate 150 mg/mL 00548-5400-00 | Amphastar | 1 vial | $18.854 | AB | Availability likely | save 28% |
| Medroxyprogesterone Acetate 150 mg/mL 55150-0329-01 | Eugia | 1 vial | $18.854 | AB | Availability likely | save 28% |
| Medroxyprogesterone Acetate 150 mg/mL 60219-1467-01 | Amneal | 1 vial | $18.854 | AB | Availability likely | save 28% |
| medroxyprogesterone acetate 150 mg/mL 70121-1467-02 | Amneal | 1 vial | $18.854 | AB | Availability likely | save 28% |
| Medroxyprogesterone Acetate 150 mg/mL 70700-0315-22 | Xiromed | 1 ml | $18.854 | AB | Availability likely | save 28% |
| medroxyprogesterone acetate 150 mg/mL 66993-0370-25 | Prasco | 25 vials | $22.850 | AB | Availability likely | save 13% |
| Medroxyprogesterone Acetate 150 mg/mL 67457-0887-01 | Mylan | 25 vials | $22.850 | AB | Availability likely | save 13% |
| Medroxyprogesterone Acetate 150 mg/mL 00548-5410-00 | Amphastar | 1 vial | $26.215 | AB | Discontinued | — |
| Medroxyprogesterone Acetate 150 mg/mLthis 62756-0090-40 | Sun | 1 vial | $26.215 | — | FDA listed | — |
| Medroxyprogesterone Acetate 150 mg/mL 00548-5701-00 | Amphastar | 1 syringe | $27.364 | AB | Availability likely | +4% |
| medroxyprogesterone acetate 150 mg/mL 66993-0371-79 | Prasco | 1 syringe | $27.364 | AB | Availability likely | +4% |
| medroxyprogesterone acetate 150 mg/mL 70121-1480-01 | Amneal | 1 syringe | $27.364 | AB | Availability likely | +4% |
| Medroxyprogesterone Acetate 150 mg/mL 55150-0330-01 | Eugia | 1 syringe | $27.364 | AB | Availability likely | +4% |
| Medroxyprogesterone Acetate 150 mg/mL 00548-5711-00 | Amphastar | 1 syringe | $38.621 | AB | Discontinued | +47% |
| Medroxyprogesterone Acetate 150 mg/mL 62756-0091-40 | Sun | 1 syringe | $38.621 | — | FDA listed | +47% |
| Depo-Provera 150 mg/mL 00009-0746-30 | Pharmacia | 1 vial | $50.994 | AB | Availability likely | +95% |
| Depo-Provera 150 mg/mL 00009-7376-11 | Pharmacia | 1 syringe | $52.335 | AB | Availability likely | +100% |
| Medroxyprogesterone Acetate Injectable Suspension 150 mg/mL 24201-0150-01 | Hikma | 1 vial | — | — | FDA listed | — |
| medroxyprogesterone acetate 150 mg/mL 50090-5619-00 | A-S | 1 vial | — | AB | FDA listed | — |
| medroxyprogesterone acetate 150 mg/mL 50090-5925-00 | A-S | 1 syringe | — | AB | FDA listed | — |
| medroxyprogesterone acetate 150 mg/mL 70518-4324-00 | REMEDYREPACK | 1 syringe | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Feb 21, 2024
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
1.37 mg / 1 mL
UNII A2I8C7HI9T
Methylparaben is a preservative derived from benzoic acid that prevents growth of bacteria, fungi, and mold in medicines. It extends the product's shelf life and maintains safety during storage.
-
28.90 mg / 1 mL
UNII G2M7P15E5P
Polyethylene glycol 3350 is a synthetic polymer used as a solvent, humectant, and thickening agent in medicines. It helps dissolve other ingredients, retain moisture in the product, and achieve the desired consistency.
-
2.41 mg / 1 mL
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
0.15 mg / 1 mL
UNII Z8IX2SC1OH
Propylparaben is a chemical preservative used to prevent bacterial and fungal growth in medicines and personal care products. It helps extend shelf life and maintain product safety during storage.
-
8.68 mg / 1 mL
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: LOSS OF BONE MINERAL DENSITY Women who use medroxyprogesterone acetate injectable suspension may lose significant bone mineral density. Bone loss is greater with increasing duration of use and may not be completely reversible [see Warnings and Precautions (5.1)] . It is unknown if use of medroxyprogesterone acetate injectable suspension during adolescence or early adulthood, a critical period of bone accretion, will reduce peak bone mass and increase the risk for osteoporotic fracture in later life [see Warnings and Precautions (5.1)] .
Medroxyprogesterone acetate injectable suspension is not recommended as a long-term (i.e., longer than 2 years) birth control method unless other options are considered inadequate [see Indications and Usage (1) and Warnings and Precautions (5.1)] . WARNING: LOSS OF BONE MINERAL DENSITY See full prescribing information for complete boxed warning . Women who use medroxyprogesterone acetate injectable suspension may lose significant bone mineral density.
Bone loss is greater with increasing duration of use and may not be completely reversible. ( 5.1 ) It is unknown if use of medroxyprogesterone acetate injectable suspension during adolescence or early adulthood, a critical period of bone accretion, will reduce peak bone mass and increase the risk for osteoporotic fracture in later life. ( 5.1 ) Medroxyprogesterone acetate injectable suspension is not recommended as a long-term (i.e., longer than 2 years) birth control method unless other options are considered inadequate.
(1, 5.1)
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Medroxyprogesterone acetate injectable suspension is indicated for use by females of reproductive potential to prevent pregnancy. Limitations of Use: The use of medroxyprogesterone acetate injectable suspension is not recommended as a long-term (i.e., longer than 2 years) birth control method unless other options are considered inadequate [see Dosage and Administration (2.1) and Warnings and Precautions (5.1)]. Medroxyprogesterone acetate is a progestin indicated for use by females of reproductive potential to prevent pregnancy.
(1) Limitations of Use: The use of medroxyprogesterone acetate injectable suspension is not recommended as a long-term (i.e., longer than 2 years) birth control method unless other options are considered inadequate. (1, 5.1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The recommended dose is 150 mg of medroxyprogesterone acetate injectable suspension every 3 months (13 weeks) administered by deep, intramuscular (IM) injection in the gluteal or deltoid muscle. ( 2.1 )
2.1Prevention of Pregnancy The 1 mL vial of medroxyprogesterone acetate injectable suspension should be vigorously shaken just before use to ensure that the dose being administered represents a uniform suspension. The recommended dose is 150 mg of medroxyprogesterone acetate injectable suspension every 3 months (13 weeks) administered by deep intramuscular (IM) injection using strict aseptic technique in the gluteal or deltoid muscle, rotating the sites with every injection. As with any IM injection, to avoid an inadvertent subcutaneous injection, body habitus should be assessed prior to each injection to determine if a longer needle is necessary particularly for gluteal IM injection.
Use for longer than 2 years is not recommended (unless other birth control methods are considered inadequate) due to the impact of long-term medroxyprogesterone acetate injectable suspension treatment on bone mineral density (BMD) [see Warnings and Precautions (5.1)] . Dosage does not need to be adjusted for body weight [ see Clinical Studies ( 14.1 )] . To ensure the patient is not pregnant at the time of the first injection, the first injection should be given ONLY during the first 5 days of a normal menstrual period; ONLY within the first 5-days postpartum if not breast-feeding; and if exclusively breast-feeding, ONLY at the sixth postpartum week.
If the time interval between injections is greater than 13 weeks, the physician should determine that the patient is not pregnant before administering the drug. The efficacy of medroxyprogesterone acetate injectable suspension depends on adherence to the dosage schedule of administration.
2.2Switching From Other Methods of Contraception When switching from other contraceptive methods, medroxyprogesterone acetate injectable suspension should be given in a manner that ensures continuous contraceptive coverage based upon the mechanism of action of both methods, (e.g., patients switching from oral contraceptives should have their first injection of medroxyprogesterone acetate injectable suspension on the day after the last active tablet or at the latest, on the day following the final inactive tablet).
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Sterile Aqueous suspension: 150 mg/mL Vials containing sterile aqueous suspension: 150 mg per mL ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS The use of medroxyprogesterone acetate injectable suspension is contraindicated in the following conditions: Known or suspected pregnancy or as a diagnostic test for pregnancy. Active thrombophlebitis, or current or past history of thromboembolic disorders, or cerebral vascular disease [ see Warnings and Precautions ( 5.2 ) ]. Known or suspected malignancy of breast [ see Warnings and Precautions ( 5.3 ) ].
Known hypersensitivity to medroxyprogesterone acetate injectable suspension or any of its other ingredients [ see Warnings and Precautions ( 5.5 ) ]. Significant liver disease [ see Warnings and Precautions (5.7) ]. Undiagnosed vaginal bleeding [ see Warnings and Precautions (5.10) ].
Known or suspected pregnancy or as a diagnostic test for pregnancy. ( 4 ) Active thrombophlebitis, or current or past history of thromboembolic disorders, or cerebral vascular disease. ( 4 ) Known or suspected malignancy of breast.
( 4 ) Known hypersensitivity to medroxyprogesterone acetate injectable suspension or any of its other ingredients. ( 4 ) Significant liver disease. ( 4 ) Undiagnosed vaginal bleeding.
( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Thromboembolic Disorders: Discontinue medroxyprogesterone acetate injectable suspension in patients who develop thrombosis. ( 5.2 ) Cancer Risks: Monitor women with a strong family history of breast cancer carefully. ( 5.3 ) Ectopic Pregnancy: Consider ectopic pregnancy if a woman using medroxyprogesterone acetate injectable suspension becomes pregnant or complains of severe abdominal pain.
( 5.4 ) Anaphylaxis and Anaphylactoid Reactions: Provide emergency medical treatment. ( 5.5 ) Liver Function: Discontinue medroxyprogesterone acetate injectable suspension if jaundice or disturbances of liver function develop. (5.7) Carbohydrate Metabolism: Monitor diabetic patients carefully.
(5.12)
5.1Loss of Bone Mineral Density Use of medroxyprogesterone acetate injectable suspension reduces serum estrogen levels and is associated with significant loss of bone mineral density (BMD). This loss of BMD is of particular concern during adolescence and early adulthood, a critical period of bone accretion. It is unknown if use of medroxyprogesterone acetate injectable suspension by younger women will reduce peak bone mass and increase the risk for osteoporotic fracture in later life.
A study to assess the reversibility of loss of BMD in adolescents was conducted with medroxyprogesterone acetate injectable suspension. After discontinuing medroxyprogesterone acetate injectable suspension in these adolescents, mean BMD loss at the total hip and femoral neck did not fully recover by 5 years (60 months) post-treatment in the sub-group of adolescents who were treated for more than 2 years [see Clinical Studies (14.3)]. Similarly, in adults, there was only partial recovery of mean BMD at the total hip, femoral neck, and lumbar spine towards baseline by 2 years post-treatment. [See Clinical Studies (14.2).] The use of medroxyprogesterone acetate injectable suspension is not recommended as a long-term (i.e., longer than 2 years) birth control method unless other options are considered inadequate.
BMD should be evaluated when a woman needs to continue to use medroxyprogesterone acetate injectable suspension long-term. In adolescents, interpretation of BMD results should take into account patient age and skeletal maturity. Other birth control methods should be considered in the risk/benefit analysis for the use of medroxyprogesterone acetate injectable suspension in women with osteoporosis risk factors.
Medroxyprogesterone acetate injectable suspension can pose an additional risk in patients with risk factors for osteoporosis (e.g., metabolic bone disease, chronic alcohol and/or tobacco use, anorexia nervosa, strong family history of osteoporosis or chronic use of drugs that can reduce bone mass such as anticonvulsants or corticosteroids).
5.2Thromboembolic Disorders There have been reports of serious thrombotic events in women using medroxyprogesterone acetate injectable suspension (150 mg). However, medroxyprogesterone acetate injectable suspension has not been causally associated with the induction of thrombotic or thromboembolic disorders. Any patient who develops thrombosis while undergoing therapy with medroxyprogesterone acetate injectable suspension should discontinue treatment unless she has no other acceptable options for birth control.
Do not re-administer medroxyprogesterone acetate injectable suspension pending examination if there is a sudden partial or complete loss of vision or if there is a sudden onset of proptosis, diplopia, or migraine. Do not re-administer if examination reveals papilledema or retinal vascular lesions.
5.3Cancer Risks Breast Cancer Women who have or have had a history of breast cancer should not use hormonal contraceptives, including medroxyprogesterone acetate injectable suspension, because breast cancer may be hormonally sensitive [see Contraindications ( 4 )]. Women with a strong family history of breast cancer should be monitored with particular care. The results of five large case-c… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following important adverse reactions observed with the use of medroxyprogesterone acetate injectable suspension are discussed in greater detail in the Warnings and Precautions section ( 5 ): Loss of Bone Mineral Density [ see Warnings and Precautions ( 5.1 ) ] Thromboembolic disease [ see Warnings and Precautions ( 5.2 ) ] Breast Cancer [ see Warnings and Precautions ( 5.3 ) ] Anaphylaxis and Anaphylactoid Reactions [ see Warnings and Precautions ( 5.5 ) ] Bleeding Irregularities [ see Warnings and Precautions (5.10) ] Weight Gain [ see Warnings and Precautions (5.11) ] Most common adverse reactions (incidence >5%) are: menstrual irregularities (bleeding or spotting) 57% at 12 months, 32% at 24 months, abdominal pain/discomfort 11%, weight gain > 10 lbs at 24 months 38%, dizziness 6%, headache 17%, nervousness 11%, decreased libido 6%.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Sun Pharmaceutical Industries, Inc. at 1-800-818-4555 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In the two clinical trials with medroxyprogesterone acetate injectable suspension, over 3,900 women, who were treated for up to 7 years, reported the following adverse reactions, which may or may not be related to the use of medroxyprogesterone acetate injectable suspension.
The population studied ranges in age from 15 to 51 years, of which 46% were White, 50% Non-White, and 4.9% Unknown race. The patients received 150 mg medroxyprogesterone acetate injectable suspension every 3-months (90 days). The median study duration was 13 months with a range of 1 to 84 months.
Fifty eight percent of patients remained in the study after 13 months and 34% after 24 months. Table 1 Adverse Reactions that Were Reported by More than 5% of Subjects Body System Body System represented from COSTART medical dictionary. Adverse Reactions [Incidence (%)] Body as a Whole Headache (16.5%) Abdominal pain/discomfort (11.2%) Metabolic/Nutritional Increased weight> 10lbs at 24 months (37.7%) Nervous Nervousness (10.8%) Dizziness (5.6%) Libido decreased (5.5%) Urogenital Menstrual irregularities: (bleeding (57.3% at 12 months, 32.1% at 24 months) amenorrhea (55% at 12 months, 68% at 24 months) Table 2 Adverse Reactions that Were Reported by between 1 and 5% of Subjects Body System Adverse Reactions [Incidence (%)] Body as a Whole Asthenia/fatigue (4.2%) Backache (2.2%) Dysmenorrhea (1.7%) Hot flashes (1.0%) Digestive Nausea (3.3%) Bloating (2.3%) Metabolic/Nutritional Edema (2.2%) Musculoskeletal Leg cramps (3.7%) Arthralgia (1.0%) Nervous Depression (1.5%) Insomnia (1.0%) Skin and Appendages Acne (1.2%) No hair growth/alopecia (1.1%) Rash (1.1%) Urogenital Leukorrhea (2.9%) Breast pain (2.8%) Vaginitis (1.2%) * Body System represented from COSTART medical dictionary.
Adverse reactions leading to study discontinuation in ≥ 2% of subjects: bleeding (8.2%), amenorrhea (2.1%), weight gain (2.0%)
6.2Postmarketing Experience The following adverse reactions have been identified during post approval use of medroxyprogesterone acetate injectable suspension. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. There have been cases of osteoporosis including osteoporotic fractures reported post-marketing in patients taking medroxyprogesterone acetate injectable suspension.
Table 3 Adverse Reactions Reported during Post-Marketing Experience Body System Body System represented from COSTART medical dictionary. Adverse Reactions Body as a Whole Chest pain, Allergic reactions including angioedema, Fever, Injection site… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Drugs or herbal products that induce certain enzymes, including CYP3A4, may decrease the effectiveness of contraceptive drug products. Counsel patients to use a back-up method or alternative method of contraception when enzyme inducers are used with medroxyprogesterone acetate injectable suspension. ( 7.1 )
7.1Changes in Contraceptive Effectiveness Associated With Co-Administration of Other Products If a woman on hormonal contraceptives takes a drug or herbal product that induces enzymes, including CYP3A4, that metabolize contraceptive hormones, counsel her to use additional contraception or a different method of contraception. Drugs or herbal products that induce such enzymes may decrease the plasma concentrations of contraceptive hormones, and may decrease the effectiveness of hormonal contraceptives. Some drugs or herbal products that may decrease the effectiveness of hormonal contraceptives include: barbiturates bosentan carbamazepine felbamate griseofulvin oxcarbazepine phenytoin rifampin St.
John’s wort topiramate HIV protease inhibitors and non-nucleoside reverse transcriptase inhibitors : Significant changes (increase or decrease) in the plasma levels of progestin have been noted in some cases of coadministration of HIV protease inhibitors. Significant changes (increase or decrease) in the plasma levels of the progestin have been noted in some cases of co-administration with non-nucleoside reverse transcriptase inhibitors. Antibiotics : There have been reports of pregnancy while taking hormonal contraceptives and antibiotics, but clinical pharmacokinetic studies have not shown consistent effects of antibiotics on plasma concentrations of synthetic steroids.
Consult the labeling of all concurrently used drugs to obtain further information about interactions with hormonal contraceptives or the potential for enzyme alterations.
7.2Laboratory Test Interactions The pathologist should be advised of progestin therapy when relevant specimens are submitted. The following laboratory tests may be affected by progestins including medroxyprogesterone acetate injectable suspension: (a) Plasma and urinary steroid levels are decreased (e.g., progesterone, estradiol, pregnanediol, testosterone, cortisol). (b) Gonadotropin levels are decreased.
(c) Sex-hormone-binding-globulin concentrations are decreased. (d) Protein-bound iodine and butanol extractable protein-bound iodine may increase. T3-uptake values may decrease.
(e) Coagulation test values for prothrombin (Factor II), and Factors VII, VIII, IX, and X may increase. (f) Sulfobromophthalein and other liver function test values may be increased. (g) The effects of medroxyprogesterone acetate on lipid metabolism are inconsistent.
Both increases and decreases in total cholesterol, triglycerides, low-density lipoprotein (LDL) cholesterol, and high-density lipoprotein (HDL) cholesterol have been observed in studies.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Nursing Mothers : Detectable amounts of drug have been identified in the milk of mothers receiving medroxyprogesterone acetate injectable suspension. ( 8.3 ) Pediatric Patients : Medroxyprogesterone acetate injectable suspension is not indicated before menarche. ( 8.4 )
8.1Pregnancy Medroxyprogesterone acetate injectable suspension should not be administered during pregnancy. [ See Contraindications and Warnings and Precautions (5.17) .]
8.3Nursing Mothers Detectable amounts of drug have been identified in the milk of mothers receiving medroxyprogesterone acetate injectable suspension. [ See Warnings and Precautions (5.13) .]
8.4Pediatric Use Medroxyprogesterone acetate injectable suspension is not indicated before menarche. Use of medroxyprogesterone acetate injectable suspension is associated with significant loss of BMD. This loss of BMD is of particular concern during adolescence and early adulthood, a critical period of bone accretion.
In adolescents, interpretation of BMD results should take into account patient age and skeletal maturity. It is unknown if use of medroxyprogesterone acetate injectable suspension by younger women will reduce peak bone mass and increase the risk of osteoporotic fractures in later life. Other than concerns about loss of BMD, the safety and effectiveness are expected to be the same for postmenarchal adolescents and adult women.
8.5Geriatric Use This product has not been studied in post-menopausal women and is not indicated in this population.
8.6Renal Impairment The effect of renal impairment on medroxyprogesterone acetate injectable suspension pharmacokinetics has not been studied.
8.7Hepatic Impairment The effect of hepatic impairment on medroxyprogesterone acetate injectable suspension pharmacokinetics has not been studied. Medroxyprogesterone acetate injectable suspension should not be used by women with significant liver disease and should be discontinued if jaundice or disturbances of liver function occur. [ See Contraindications ( 4 ) and Warnings and Precautions (5.7) .]
🤰 Pregnancy ▾
8.1Pregnancy Medroxyprogesterone acetate injectable suspension should not be administered during pregnancy. [ See Contraindications and Warnings and Precautions (5.17) .]
🧒 Pediatric Use ▾
8.4Pediatric Use Medroxyprogesterone acetate injectable suspension is not indicated before menarche. Use of medroxyprogesterone acetate injectable suspension is associated with significant loss of BMD. This loss of BMD is of particular concern during adolescence and early adulthood, a critical period of bone accretion.
In adolescents, interpretation of BMD results should take into account patient age and skeletal maturity. It is unknown if use of medroxyprogesterone acetate injectable suspension by younger women will reduce peak bone mass and increase the risk of osteoporotic fractures in later life. Other than concerns about loss of BMD, the safety and effectiveness are expected to be the same for postmenarchal adolescents and adult women.
🧓 Geriatric Use ▾
8.5Geriatric Use This product has not been studied in post-menopausal women and is not indicated in this population.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Medroxyprogesterone acetate (MPA) injectable suspension, inhibits the secretion of gonadotropins which primarily prevents follicular maturation and ovulation and causes thickening of cervical mucus. These actions contribute to its contraceptive effect.
12.2Pharmacodynamics No specific pharmacodynamic studies were conducted with medroxyprogesterone acetate injectable suspension.
12.3Pharmacokinetics Absorption Following a single 150 mg IM dose of medroxyprogesterone acetate injectable suspension in eight women between the ages of 28 and 36 years old, medroxyprogesterone acetate concentrations, measured by an extracted radioimmunoassay procedure, increase for approximately 3 weeks to reach peak plasma concentrations of 1 to 7 ng/mL. Distribution Plasma protein binding of MPA averages 86%. MPA binding occurs primarily to serum albumin.
No binding of MPA occurs with sex-hormone-binding globulin (SHBG). Metabolism MPA is extensively metabolized in the liver by P450 enzymes. Its metabolism primarily involves ring A and/or side-chain reduction, loss of the acetyl group, hydroxylation in the 2-, 6-, and 21- positions or a combination of these positions, resulting in more than 10 metabolites.
Excretion The concentrations of medroxyprogesterone acetate decrease exponentially until they become undetectable (<100 pg/mL) between 120 to 200 days following injection. Using an unextracted radioimmunoassay procedure for the assay of medroxyprogesterone acetate in serum, the apparent half-life for medroxyprogesterone acetate following IM administration of medroxyprogesterone acetate injectable suspension is approximately 50 days. Most medroxyprogesterone acetate metabolites are excreted in the urine as glucuronide conjugates with only minor amounts excreted as sulfates.
Specific Populations The effect of hepatic and/or renal impairment on the pharmacokinetics of medroxyprogesterone acetate injectable suspension is unknown.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Medroxyprogesterone acetate (MPA) injectable suspension, inhibits the secretion of gonadotropins which primarily prevents follicular maturation and ovulation and causes thickening of cervical mucus. These actions contribute to its contraceptive effect.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Medroxyprogesterone acetate injectable suspension, USP is supplied as follows: Package Configuration Strength NDC Medroxyprogesterone acetate injectable suspension, USP, 150 mg/mL, 1 mL vial 1 mL vial 150 mg/mL NDC 62756-090-40 25 x 1 mL vials 150 mg/mL NDC 62756-090-45 Vial MUST be stored upright at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Medroxyprogesterone acetate injectable suspension, USP, a contraceptive injection, contains medroxyprogesterone acetate, USP a derivative of progesterone, as its active ingredient. Medroxyprogesterone acetate is active by the parenteral and oral routes of administration. It is a white or almost white, crystalline powder that is stable in air and that melts between 205°C and 209°C.
It is freely soluble in chloroform, soluble in acetone and dioxane, sparingly soluble in alcohol and methanol, slightly soluble in ether, and insoluble in water. The chemical name for medroxyprogesterone acetate is pregn-4-ene-3, 20-dione, 17-(acetyloxy)-6-methyl-, (6α-). The structural formula is as follows: Medroxyprogesterone acetate injectable suspension, USP for IM injection is available in vials containing 1 mL of medroxyprogesterone acetate sterile aqueous suspension 150 mg/mL.
For Medroxyprogesterone acetate injectable suspension vials, each mL of sterile aqueous suspension contains: Medroxyprogesterone acetate 150 mg Polyethylene glycol 3350 28.90 mg Polysorbate 80 2.41 mg Sodium chloride 8.68 mg Methylparaben 1.37 mg Propylparaben 0.15 mg Water for injection quantity sufficient When necessary, pH is adjusted with sodium hydroxide or hydrochloric acid, or both. spl-medroxy-structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION “See FDA-approved patient labeling (Patient Information).” Advise patients at the beginning of treatment that their menstrual cycle may be disrupted and that irregular and unpredictable bleeding or spotting results, and that this usually decreases to the point of amenorrhea as treatment with medroxyprogesterone acetate injectable suspension continues, without other therapy being required. Counsel patients about the possible increased risk of breast cancer in women who use medroxyprogesterone acetate injectable suspension [ see Warnings and Precautions ( 5.3 ) ].
Counsel patients that this product does not protect against HIV infection (AIDS) and other sexually transmitted diseases. Counsel patients on Warnings and Precautions associated with use of medroxyprogesterone acetate injectable suspension. Counsel patients to use a back-up method or alternative method of contraception when enzyme inducers are used with medroxyprogesterone acetate injectable suspension.
Distributed by: Sun Pharmaceutical Industries, Inc. Cranbury, NJ 08512 Manufactured by: Sun Pharmaceutical Industries Limited Halol-Baroda Highway, Halol-389 350, Gujarat, India.
🍼 Nursing Mothers ▾
8.3Nursing Mothers Detectable amounts of drug have been identified in the milk of mothers receiving medroxyprogesterone acetate injectable suspension. [ See Warnings and Precautions (5.13) .]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption Following a single 150 mg IM dose of medroxyprogesterone acetate injectable suspension in eight women between the ages of 28 and 36 years old, medroxyprogesterone acetate concentrations, measured by an extracted radioimmunoassay procedure, increase for approximately 3 weeks to reach peak plasma concentrations of 1 to 7 ng/mL. Distribution Plasma protein binding of MPA averages 86%. MPA binding occurs primarily to serum albumin.
No binding of MPA occurs with sex-hormone-binding globulin (SHBG). Metabolism MPA is extensively metabolized in the liver by P450 enzymes. Its metabolism primarily involves ring A and/or side-chain reduction, loss of the acetyl group, hydroxylation in the 2-, 6-, and 21- positions or a combination of these positions, resulting in more than 10 metabolites.
Excretion The concentrations of medroxyprogesterone acetate decrease exponentially until they become undetectable (<100 pg/mL) between 120 to 200 days following injection. Using an unextracted radioimmunoassay procedure for the assay of medroxyprogesterone acetate in serum, the apparent half-life for medroxyprogesterone acetate following IM administration of medroxyprogesterone acetate injectable suspension is approximately 50 days. Most medroxyprogesterone acetate metabolites are excreted in the urine as glucuronide conjugates with only minor amounts excreted as sulfates.
Specific Populations The effect of hepatic and/or renal impairment on the pharmacokinetics of medroxyprogesterone acetate injectable suspension is unknown.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics No specific pharmacodynamic studies were conducted with medroxyprogesterone acetate injectable suspension.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Contraception In five clinical studies using medroxyprogesterone acetate injectable suspension, the 12-month failure rate for the group of women treated with medroxyprogesterone acetate injectable suspension was zero (no pregnancies reported) to 0.7 by Life-Table method. The effectiveness of medroxyprogesterone acetate injectable suspension is dependent on the patient returning every 3 months (13 weeks) for reinjection.
14.2Bone Mineral Density Changes in Adult Women Treated with Medroxyprogesterone Acetate Injectable Suspension In a controlled, clinical study, adult women using medroxyprogesterone acetate injectable suspension (150 mg) for up to 5 years showed spine and hip BMD mean decreases of 5 to 6%, compared to no significant change in bone mineral density (BMD) in the control group. The decline in BMD was more pronounced during the first two years of use, with smaller declines in subsequent years. Mean changes in lumbar spine BMD of -2.86%, -4.11%, -4.89%, -4.93% and -5.38% after 1, 2, 3, 4, and 5 years, respectively, were observed.
Mean decreases in BMD of the total hip and femoral neck were similar. After stopping use of medroxyprogesterone acetate injectable suspension, there was partial recovery of BMD toward baseline values during the 2-year post-therapy period. Longer duration of treatment was associated with less complete recovery during this 2-year period following the last injection.
Table 4 shows the change in BMD in women after 5 years of treatment with medroxyprogesterone acetate injectable suspension and in women in a control group, as well as the extent of recovery of BMD for the subset of the women for whom 2-year post treatment data were available. Table 4. Mean Percent Change from Baseline in BMD in Adults by Skeletal Site and Cohort (5 Years of Treatment and 2 Years of Follow-Up) Time in Study Spine Total Hip Femoral Neck Medroxyprogesterone acetate injectable suspension The treatment group consisted of women who received medroxyprogesterone acetate injectable suspension for 5 years and were then followed for 2 years post-use (total time in study of 7 years).
Control The control group consisted of women who did not use hormonal contraception and were followed for 7 years. Medroxyprogesterone acetate injectable suspension Control Medroxyprogesterone acetate injectable suspension Control 5 years -5.38% n=33 0.43% n=105 -5.16% n=21 0.19% n=65 -6.12% n=34 -0.27% n=106 7 years -3.13% n=12 0.53% n=60 -1.34% n=7 0.94% n=39 -5.38% n=13 -0.11% n=63
14.3Bone Mineral Density Changes in Adolescent Females (12 to 18 Years of Age) Treated with Medroxyprogesterone Acetate Injectable Suspension The impact of medroxyprogesterone acetate injectable suspension (150 mg) use for up to 240 weeks (4.6 years) was evaluated in an open-label non-randomized clinical study in 389 adolescent females (12 to 18 years of age). Use of medroxyprogesterone acetate injectable suspension was associated with a significant decline from baseline in BMD. Partway through the trial, drug administration was stopped (at 120 weeks).
The mean number of injections per medroxyprogesterone acetate injectable suspension user was 9.3. Table 5 summarizes the study findings. The decline in BMD at total hip and femoral neck was greater with longer duration of use.
The mean decrease in BMD at 240 weeks was more pronounced at total hip (-6.4%) and femoral neck (-5.4%) compared to lumbar spine (-2.1%). Adolescents in the untreated cohort had an increase in BMD during the period of growth following menarche. However, the two cohorts were not matched at baseline for age, gynecologic age, race, BMD and other factors that influence the rate of acquisition of BMD.
Table 5. BMD Mean Percent Change from Baseline in Adolescents Receiving ≥4 Injections per 60-week Period, by Skeletal Site and Cohort Duration of Treatment Medroxyprogesterone Acetate Injectable Suspension (150 mg IM) Unmatched, Untreated Cohort N Mean % Change N Mean % Change… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility [See Warnings and Precautions, ( 5.3 , 5.15 , and 5.17) .]
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility [See Warnings and Precautions, ( 5.3 , 5.15 , and 5.17) .]
📚 References ▾
15 REFERENCES Li CI, Beaber EF, Tang, MCT et al. Effect of Depo-Medroxyprogesterone Acetate on Breast Cancer Risk among Women 20 to 44 years of Age. Cancer Research 2012;72:2028-2035. Paul C, Skegg DCG, Spears GFS. Depot medroxyprogesterone (Depo-Provera) and risk of breast cancer. Br Med J 1989; 299:759-62.
📄 Recent Major Changes ▾
Indications and Usage (1) 12/2020
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL-Vial Label NDC 62756-090-40 medroxyPROGESTERrone Acetate Injectable Suspension, USP 150 mg/mL For intramuscular use only Store upright at 20° to 25°C (68° to 77°F) [see USP]. Rx only 1 mL Single-dose vial spl-medroxy-label
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL-Carton Label NDC 62756-090-40 medroxyPROGESTERone Acetate Injectable Suspension, USP 150 mg/mL For intramuscular use only Rx only 1 mL Single-dose vial spl-medroxy-carton