
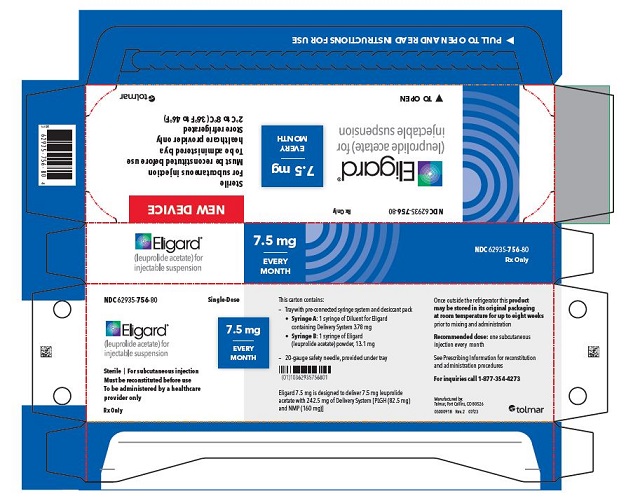
Eligard Leuprolide acetate 7.5 mg/.25mL Injection, Suspension, Extended Release, 1 syringe
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Gonadotropin Releasing Hormone Receptor Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Leuprolide injection is used to treat certain types of prostate cancer central precocious puberty (CPP; a condition causing children to enter puberty too soon, resulting in faster than normal bone growth and development of sexual characteristics) endometriosis (a condition in which the type of tissue that lines the uterus [womb] grows in other areas of the body and causes infertility, pain before and during menstrual periods, pain during and after sexual activity, and heavy, irregular bleeding) anemia (a lower-than-normal number of red blood cells) caused by uterine fibroids (growths i...
Read the full MedlinePlus article ↗- That's a really common concern, and it's smart to ask. When you first start leuprolide, your testosterone levels actually spike for a week or two before the drug kicks in and bring...
- Why does my doctor say my symptoms might get worse right after starting leuprolide?
- Hot flashes are actually one of the most common side effects in men taking leuprolide — over half of men in clinical studies experienced them. Because leuprolide drops testosterone...
- Will I get hot flashes? I thought that was just a women's issue.
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
160 mg / 0.25 mL
UNII JR9CE63FPM
Methyl pyrrolidone is a synthetic liquid solvent used in pharmaceutical formulations. It helps dissolve and deliver active ingredients in topical products and some oral medicines.
-
82.5 mg / 0.25 mL
UNII LQ35R50VR1
A synthetic polymer made from lactic and glycolic acids combined in equal parts. It acts as a binder and film-former in medications, helping create extended-release formulations that dissolve slowly in the body over time.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $281.05 | $70.26 / 0.25 ml |
| Medicare drug plans payPart D · Q2 2026 | $1,327.97 | $331.99 / 0.25 ml |
| Medicare Part B allowsASP · J9217 | $160.342 / J9217 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Eligard 62935-0753-75 | TOLMAR | 1 kit | — | — | FDA listed | — |
| Eligard 7.5 mg/.25mLthis 62935-0756-80 | TOLMAR | 1 syringe | — | — | FDA listed | — |
| Vabrinty 7.5 mg/.25mL 85043-0075-05 | URONOVA | 1 syringe | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 12397120 ↗ | Method of use | U-4001 | Dec 22, 2041 |
| US 11931559 ↗ | Drug substance | — | Dec 22, 2041 |
| US 11771841 ↗ | Drug substance | — | Dec 22, 2041 |
Is there a generic version of ELIGARD 7.5 MG SYRINGE KIT?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 62935-0756-80 You're viewing this | 1 SYRINGE in 1 CARTON (62935-756-80) / .25 mL in 1 SYRINGE | 2023-10-30 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ELIGARD is indicated for the treatment of advanced prostate cancer. ELIGARD is a gonadotropin releasing hormone (GnRH) agonist indicated for the treatment of advanced prostate cancer. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION ELIGARD is administered subcutaneously based on the following recommended dose and schedule: 7.5 mg subcutaneously every month ( 2.1 ) 22.5 mg subcutaneously every 3 months ( 2.1 ) 30 mg subcutaneously every 4 months ( 2.1 ) 45 mg subcutaneously every 6 months ( 2.1 ) See Full Prescribing Information for preparation and administration instructions. ( 2.2 , 2.3 )
2.1Recommended Dosage ELIGARD is administered subcutaneously and provides continuous release of leuprolide acetate over a one-, three-, four-, or six-month treatment period (Table 1). ELIGARD must be administered by a healthcare provider. The injection delivers the dose of leuprolide acetate incorporated in a polymer formulation.
Table 1. ELIGARD Recommended Dosing Dosage 7.5 mg 22.5 mg 30 mg 45 mg Recommended dose 1 injection every month 1 injection every 3 months 1 injection every 4 months 1 injection every 6 months As with other drugs administered by subcutaneous injection, the injection site should vary periodically. The specific injection location should be an area with sufficient soft or loose subcutaneous tissue.
In clinical trials, the injections were administered in the upper- or mid-abdominal area. Avoid areas with brawny or fibrous subcutaneous tissue or locations that could be rubbed or compressed (i.e., with a belt or clothing waistband). In patients treated with GnRH analogues for prostate cancer, treatment is usually continued upon development of metastatic castration-resistant prostate cancer.
2.2Preparation Instructions Use aseptic technique throughout the procedure. As with other similar agents, the use of gloves is recommended during mixing and administration. Allow the product to reach room temperature before mixing.
Once mixed, the product must be administered within 30 minutes or it should be discarded. ELIGARD is packaged in a carton containing: Tray containing pre-connected syringe system and desiccant pack Prescribing information Sterile safety needle and cap (located under the tray in carton) Follow the detailed instructions below to ensure correct preparation of ELIGARD prior to administration: Step 1 On a clean field open the tray by tearing off the foil from the corner and remove the contents. Discard the desiccant pack.
Remove the pre-connected syringe system from the tray. Open the sterile safety needle package by peeling back the paper tab. Note: Syringe A and Syringe B should not be lined-up yet.
The product should only be administered with the co-packaged, sterile safety needle. Step 2 Grasp the latching button on the coupling device with your finger and thumb and press until you hear a snapping sound. The two syringes will be aligned.
Do not bend the pre-connected syringe system. Step 3 Holding the syringes in a horizontal position, transfer the liquid contents of Syringe A into the leuprolide acetate powder contained in Syringe B. Thoroughly mix the product for 60 cycles by pushing the contents back and forth between both syringes to obtain a uniform suspension.
A cycle is one push of the Syringe A plunger and one push of the Syringe B plunger. When thoroughly mixed, the suspension will appear light tan to tan (ELIGARD 7.5 mg) or colorless to pale yellow (ELIGARD 22.5 mg, 30 mg, and 45 mg). Note: Product must be mixed as described; shaking will NOT provide adequate mixing.
Do not bend. Step 4 After mixing, hold the syringes vertically (upright) with Syringe B (wide syringe) on the bottom. The syringes should remain securely coupled.
Transfer all of the mixed product into Syringe B by depressing the Syringe A plunger and slightly withdrawing the Syringe B plunger. Step 5 While ensuring the Syringe A plunger is fully pushed down, hold the coupling device and unscrew Syringe B. This will disconnect Syringe B from the coupling device.
Syringe A will remain attached to the coupling device. Note: Small air bubbles will remain in the formulation – this is acceptable. Do not purge the air bubbles from Syringe B…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS ELIGARD is an injectable suspension of leuprolide acetate available in a pre-connected syringe system and packaged with a sterile safety needle and cap (Table 2), a desiccant, prescribing information and instructions for use. The pre-connected syringe system consists of syringe A and syringe B connected using a coupling device. Syringe A contains the in situ polymeric extended release technology and the syringe B contains leuprolide acetate powder.
When reconstituted, ELIGARD is administered as a single dose. Refer to Table 10 for details of the description of the dosage form before and after mixing [see How Supplied/Storage and Handling ( 16 )] . Table 2.
Specifications for ELIGARD Sterile Safety Needle and Cap ELIGARD strength Gauge Length 7.5 mg 20-gauge 5/8-inch 22.5 mg 20-gauge 5/8-inch 30 mg 20-gauge 5/8-inch 45 mg 18-gauge 5/8-inch Injectable suspension: 7.5 mg ( 3 ) Injectable suspension: 22.5 mg ( 3 ) Injectable suspension: 30 mg ( 3 ) Injectable suspension: 45 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Hypersensitivity ELIGARD is contraindicated in patients with hypersensitivity to GnRH, GnRH agonist analogs or any of the components of ELIGARD. Anaphylactic reactions to synthetic GnRH or GnRH agonist analogs have been reported in the literature. Known hypersensitivity to GnRH, GnRH agonist analogs or any of the components of ELIGARD ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Tumor Flare: Transient increase in serum levels of testosterone during treatment may result in worsening of symptoms or onset of new signs and symptoms during the first few weeks of treatment, including bone pain, neuropathy, hematuria, bladder outlet obstruction, ureteral obstruction, or spinal cord compression. Monitor patients at risk closely and manage as appropriate. ( 5.1 , 5.7 ) Hyperglycemia and diabetes: Hyperglycemia and an increased risk of developing diabetes have been reported in men receiving GnRH analogs.
Monitor blood glucose level and manage according to current clinical practice. ( 5.2 ) Cardiovascular diseases: Increased risk of myocardial infarction, sudden cardiac death and stroke has been reported in men. Monitor for cardiovascular disease and manage according to current clinical practice.
( 5.3 ) Effect on QT/QTc Interval: Androgen deprivation therapy may prolong the QT interval. Consider risks and benefits. ( 5.4 ) Convulsions have been observed in patients with or without a history of predisposing factors.
Manage convulsions according to the current clinical practice. (5.5) Severe Cutaneous Adverse Reactions (SCARs), including Stevens-Johnson syndrome/toxic epidermal necrolysis, occurred in patients treated with ELIGARD. Interrupt ELIGARD if signs or symptoms of SCARs develop.
Permanently discontinue if SCARs are confirmed. ( 5.6 ) Embryo-Fetal Toxicity: May cause fetal harm. ( 5.8 , 8.1 )
5.1Tumor Flare ELIGARD 7.5 mg, 22.5 mg, and 30 mg like other GnRH agonists, causes a transient increase in serum concentrations of testosterone during the first week of treatment. ELIGARD 45 mg causes a transient increase in serum concentrations of testosterone during the first two weeks of treatment. Patients may experience worsening of symptoms or onset of new signs and symptoms during the first few weeks of treatment, including bone pain, neuropathy, hematuria, or bladder outlet obstruction.
Cases of ureteral obstruction and/or spinal cord compression, which may contribute to paralysis with or without fatal complications, have been observed in the treatment of advanced prostate cancer using GnRH agonists. Patients with metastatic vertebral lesions and/or with urinary tract obstruction should be closely observed during the first few weeks of therapy. If spinal cord compression or ureteral obstruction develops, standard treatment of these complications should be instituted.
5.2Hyperglycemia and Diabetes Hyperglycemia and an increased risk of developing diabetes have been reported in men receiving GnRH agonists. Hyperglycemia may represent development of diabetes mellitus or worsening of glycemic control in patients with diabetes. Monitor blood glucose and/or glycosylated hemoglobin (HbA1c) periodically in patients receiving a GnRH agonist and manage with current practice for treatment of hyperglycemia or diabetes.
5.3Cardiovascular Diseases Increased risk of developing myocardial infarction, sudden cardiac death and stroke has been reported in association with use of GnRH agonists in men. The risk appears low based on the reported odds ratios, and should be evaluated carefully along with cardiovascular risk factors when determining a treatment for patients with prostate cancer. Patients receiving a GnRH agonist should be monitored for symptoms and signs suggestive of development of cardiovascular disease and be managed according to current clinical practice.
5.4Effect on QT/QTc Interval Androgen deprivation therapy may prolong the QT/QTc interval. Providers should consider whether the benefits of androgen deprivation therapy outweigh the potential risks in patients with congenital long QT syndrome, congestive heart failure, frequent electrolyte abnormalities, and in patients taking drugs known to prolong the QT interval. Electrolyte abnormalities should be corrected.
Consider periodic monitoring of electrocardiograms and electrolytes.
5.5 Convulsions Postmarketing reports of convulsion…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Tumor Flare [see Warnings and Precautions ( 5.1 )] Hyperglycemia and Diabetes [see Warnings and Precautions ( 5.2 )] Cardiovascular Disease [see Warnings and Precautions ( 5.3 )] Effect on QT/QTc Interval [see Warnings and Precautions ( 5.4 )] Convulsions [see Warnings and Precautions ( 5.5 )] Severe Cutaneous Adverse Reactions [see Warnings and Precautions ( 5. 6 )] Most common adverse reactions in clinical studies (incidence ≥ 5%): Malaise, fatigue, hot flashes/sweats, and testicular atrophy.
( 6.1 ) As with other GnRH agonists, other adverse reactions, including decreased bone density and rare cases of pituitary apoplexy have been reported. ( 6.1 , 6.2 ) To report SUSPECTED ADVERSE REACTIONS, contact Tolmar at 1-888-354-4273 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety of all ELIGARD formulations was evaluated in clinical trials involving patients with advanced prostate cancer. In addition, the safety of ELIGARD 7.5 mg was evaluated in 8 surgically castrated males (Table 4).
ELIGARD, like other GnRH analogs, caused a transient increase in serum testosterone concentrations during the first one to two weeks of treatment. Therefore, potential exacerbations of signs and symptoms of the disease during the first weeks of treatment are of concern in patients with vertebral metastases and/or urinary obstruction or hematuria. If these conditions are aggravated, it may lead to neurological problems such as weakness and/or paresthesia of the lower limbs or worsening of urinary symptoms [see Warnings and Precautions ( 5.7 )] .
During the clinical trials, injection sites were closely monitored. Refer to Table 3 for a summary of reported injection site adverse reactions. Table 3.
Reported Injection Site Adverse Reactions ELIGARD 7.5 mg 22.5 mg 30 mg 45 mg Study number AGL9904 AGL9909 AGL0001 AGL0205 Number of patients 120 117 90 111 Treatment 1 injection every month up to 6 months 1 injection every 3 months up to 6 months 1 injection every 4 months up to 8 months 1 injection every 6 months up to 12 months Number of injections 716 230 175 217 Transient burning/ stinging 248 (34.6%) injections; 84% reported as mild 50 (21.7%) injections; 86% reported as mild 35 (20%) injections; 100% reported as mild 3 35 (16%) injections; 91.4% reported as mild Pain (generally brief and mild) 4.3% of injections (18.3% of patients) 3.5% of injections (6.0% of patients) 2.3% of injections 2 (3.3% of patients) 4.6% of injections 4 Erythema (generally brief and mild) 2.6% of injections (12.5% of patients) 0.9% of injections 1 (1.7% of patients) 1.1% of injections (2.2% of patients) - Bruising (mild) 2.5% of injections (11.7% of patients) 1.7% of injections (3.4% of patients) - 2.3% of injections 5 Pruritus 1.4% of injections (9.2% of patients) 0.4% of injections (0.9% of patients) - - Induration 0.4% of injections (2.5% of patients) - - - Ulceration 0.1% of injections (> 0.8% of patients) - - - Erythema was reported following 2 injections of ELIGARD 22.5 mg.
One report characterized the erythema as mild and it resolved within 7 days. The other report characterized the erythema as moderate and it resolved within 15 days. Neither patient experienced erythema at multiple injection times.
A single reaction reported as moderate pain resolved within two minutes and all 3 mild pain reactions resolved within several days following injection of ELIGARD 30 mg. Following injection of ELIGARD 30 mg, three of the 35 burning/stinging reactions were reported as moderate. Transient pain was reported as mild in intensity in nine of ten (90%) events and moder…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Females and males of reproductive potential: ELIGARD may impair fertility. ( 8.3 ) Pediatric: Safety and effectiveness in pediatric patients have not been established. ( 8.4 ) Geriatric: This label reflects clinical trials for ELIGARD in prostate cancer where the majority of subjects were at least 65 years of age ( 8.5 ).
8.1Pregnancy Risk Summary Based on findings in animal studies and mechanism of action, ELIGARD may cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology ( 12.1 )] . There are no available data in pregnant women to inform the drug-associated risk. Expected hormonal changes that occur with ELIGARD treatment increase the risk for pregnancy loss.
In animal developmental and reproductive studies, major fetal abnormalities were observed after administration of leuprolide acetate throughout gestation in rats. Advise pregnant patients and females of reproductive potential of the potential risk to the fetus (see Data) . Data Animal Data In animal developmental and reproductive studies, major fetal abnormalities were observed after administration of leuprolide acetate throughout gestation.
There were increased fetal mortality and decreased fetal weights in rats and rabbits. The effects of fetal mortality are expected consequences of the alterations in hormonal levels brought about by this drug.
8.2Lactation The safety and efficacy of ELIGARD have not been established in females. There is no information regarding the presence of ELIGARD in human milk, the effects on the breastfed child, or the effects on milk production. Because many drugs are excreted in human milk and because of the potential for serious adverse reactions in a breastfed child from ELIGARD, a decision should be made to discontinue breastfeeding or discontinue the drug, taking into account the importance of the drug to the mother.
8.3Females and Males of Reproductive Potential Infertility Males Based on mechanism of action, ELIGARD may impair fertility in males of reproductive potential [see Clinical Pharmacology ( 12.1 )] .
8.4Pediatric Use The safety and effectiveness of ELIGARD in pediatric patients have not been established.
8.5Geriatric Use The majority of the patients (approximately 70%) studied in the clinical trials were age 70 and older. Clinical studies of ELIGARD did not include sufficient numbers of younger adult patients to determine if patients 65 years of age and older respond differently than younger adult patients.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings in animal studies and mechanism of action, ELIGARD may cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology ( 12.1 )] . There are no available data in pregnant women to inform the drug-associated risk. Expected hormonal changes that occur with ELIGARD treatment increase the risk for pregnancy loss.
In animal developmental and reproductive studies, major fetal abnormalities were observed after administration of leuprolide acetate throughout gestation in rats. Advise pregnant patients and females of reproductive potential of the potential risk to the fetus (see Data) . Data Animal Data In animal developmental and reproductive studies, major fetal abnormalities were observed after administration of leuprolide acetate throughout gestation.
There were increased fetal mortality and decreased fetal weights in rats and rabbits. The effects of fetal mortality are expected consequences of the alterations in hormonal levels brought about by this drug.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of ELIGARD in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use The majority of the patients (approximately 70%) studied in the clinical trials were age 70 and older. Clinical studies of ELIGARD did not include sufficient numbers of younger adult patients to determine if patients 65 years of age and older respond differently than younger adult patients.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Leuprolide acetate, a gonadotropin releasing hormone (GnRH) agonist, acts as an inhibitor of gonadotropin secretion when given continuously in therapeutic doses. Animal and human studies indicate that after an initial stimulation, chronic administration of leuprolide acetate results in suppression of testicular and ovarian steroidogenesis. This effect is reversible upon discontinuation of drug therapy.
12.2Pharmacodynamics Following initial administration, ELIGARD causes an initial increase in serum luteinizing hormone (LH) and follicle stimulating hormone (FSH) levels with subsequent increases in serum levels of testosterone. Administration of ELIGARD leads to sustained suppression of pituitary gonadotropins, and serum levels of testosterone consequently fall into the range normally seen in surgically castrated men approximately 21 days after initiation of therapy. Continuation of therapy with leuprolide acetate in patients with prostate cancer maintained testosterone below the castrate level for up to five years.
Following the first dose of ELIGARD, mean serum testosterone concentrations transiently increased, then fell to below castrate threshold ( < 50 ng/dL) within three weeks, and generally remained below castrate threshold levels throughout treatment for all ELIGARD concentrations. Mean serum testosterone concentrations fell to < 20 ng/dL within five weeks for all ELIGARD concentrations.
12.3Pharmacokinetics Absorption ELIGARD 7.5 mg Following a single injection of ELIGARD 7.5 mg for 1-month administration in patients, the mean peak plasma concentration was 25.3 ng/mL (C max ) at 5 hours;at the end of the 4 week dosing interval the mean concentration declined to 0.42 ng/mL. ELIGARD 22.5 mg Following a single injection of ELIGARD 22.5 mg for 3-month administration in patients, the mean peak plasma concentration was 127 ng/mL (C max ) at 5 hours; at the end of the 12 week dosing interval the mean concentration declined to 0.34 ng/mL.
ELIGARD 30 mg Following a single injection of ELIGARD 30 mg for 4-month administration in patients, the mean peak plasma concentration was 150 ng/mL (C max ) at 3.3 hours; at the end of the 16 week dosing interval the mean concentration declined to 0.1 ng/mL. ELIGARD 45 mg Following a single injection of ELIGARD 45 mg for 6-month administration in patients, the mean peak plasma concentration was 82 ng/mL at 4.5 hours (C max ); at the end of the 24 week dosing interval the mean concentration declined to 0.2 ng/mL. There was no evidence of significant accumulation during repeated dosing.
Distribution The mean steady-state volume of distribution of leuprolide following intravenous bolus administration to healthy male volunteers was 27 L. In vitro binding to human plasma proteins ranged from 43% to 49%. Elimination After the initial increase following each subcutaneous injection, serum concentration range was 0.1 – 2.00 ng/mL.
In healthy male volunteers, a 1-mg bolus of leuprolide administered intravenously revealed that the mean systemic clearance was
8.34L/h, with a terminal elimination half-life of approximately 3 hours based on a two compartment model. Metabolism No drug metabolism study was conducted with ELIGARD. Upon administration with different leuprolide acetate formulations, the major metabolite of leuprolide acetate is a pentapeptide (M-1) metabolite.
Excretion No drug excretion study was conducted with ELIGARD. Specific Populations Geriatrics [see Use in Specific Populations ( 8.5 )] Race In patients studied, mean serum leuprolide concentrations were similar regardless of race. Refer to Table 6 for distribution of study patients by race.
Table 6. Race Characterization of ELIGARD Study Patients (n) Race ELIGARD 7.5 mg ELIGARD 22.5 mg ELIGARD 30 mg ELIGARD 45 mg White 26 19 18 17 Black - 4 4 7 Hispanic 2 2 2 3 Renal and Hepatic Insufficiency The pharmacokinetics of ELIGARD in hepatically and renally impaired patients have not been de…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Leuprolide acetate, a gonadotropin releasing hormone (GnRH) agonist, acts as an inhibitor of gonadotropin secretion when given continuously in therapeutic doses. Animal and human studies indicate that after an initial stimulation, chronic administration of leuprolide acetate results in suppression of testicular and ovarian steroidogenesis. This effect is reversible upon discontinuation of drug therapy.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied ELIGARD is supplied as a single-dose, two syringe-mixing system with a sterile safety needle and cap. ELIGARD is available as follows (Table 10): Table 10. ELIGARD Product Presentations ELIGARD strength NDC number Description of Syringe A with the delivery system Description of Syringe B with leuprolide acetate Description of the suspension after mixing 7.5 mg 62935-756-80 Light tan to tan, clear, viscous solution White to off white powder Light tan to tan 22.5 mg 62935-227-10 Colorless to pale yellow, clear viscous solution White to off white powder Colorless to pale yellow 30 mg 62935-306-40 Colorless to pale yellow, clear viscous solution White to off white powder Colorless to pale yellow 45 mg 62935-461-50 Colorless to pale yellow, clear viscous solution White to off white powder Colorless to pale yellow Storage Store at 2°C to 8°C (36°F to 46°F) Once outside the refrigerator this product may be stored in its original packaging at room temperature 15°C to 30°C (59°F to 86°F) for up to eight weeks prior to mixing and administration.
📋 Description ▾
11 DESCRIPTION ELIGARD is a sterile polymeric matrix formulation of leuprolide acetate, a GnRH agonist, for subcutaneous injection. It is designed to deliver leuprolide acetate at a controlled rate over a one-, three-, four, or six-month therapeutic period. Leuprolide acetate is a synthetic nonapeptide analog of naturally occurring gonadotropin releasing hormone (GnRH) that, when given continuously, inhibits pituitary gonadotropin secretion and suppresses testicular and ovarian steroidogenesis.
The analog possesses greater potency than the natural hormone. The chemical name is 5-oxo-L-prolyl-L-histidyl-L-tryptophyl-L-seryl-L-tyrosyl-D-leucyl-L-leucyl-L-arginyl-N-ethyl-L-prolinamide acetate (salt) with the following structural formula: ELIGARD is supplied as a pre-connected syringe system comprised of two prefilled syringes (syringe A and syringe B) connected using a coupling device. Immediately prior to administration, the contents of the pre-connected syringe system are mixed until homogenous.
ELIGARD is administered subcutaneously, where it forms a solid drug delivery depot. Syringe A contains the in situ polymeric extended release technology consisting of a biodegradable poly (DL-lactide-co-glycolide) (PLGH or PLG) polymer formulation dissolved in a biocompatible solvent, N -methyl-2-pyrrolidone (NMP) and syringe B contains leuprolide acetate. Refer to Table 5 for the delivery system composition and reconstituted product formulation for each ELIGARD product.
Table 5. ELIGARD Delivery System Composition and Reconstituted Product Formulation ELIGARD 7.5 mg 22.5 mg 30 mg 45 mg In situ polymeric extended release technology Polymer PLGH PLG PLG PLG Polymer description Copolymer containing carboxyl endgroups Copolymer with hexanediol Copolymer with hexanediol Copolymer with hexanediol Polymer DL-lactide to glycolide molar ratio 50:50 75:25 75:25 85:15 Reconstituted product Polymer delivered 82.5 mg 158.6 mg 211.5 mg 165 mg NMP delivered 160.0 mg 193.9 mg 258.5 mg 165 mg Leuprolide acetate delivered 7.5 mg 22.5 mg 30 mg 45 mg Approximate Leuprolide free base equivalent 7.0 mg 21 mg 28 mg 42 mg Approximate administered formulation weight 250 mg 375 mg 500 mg 375 mg Approximate injection volume 0.25 mL 0.375 mL 0.5 mL 0.375 mL structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Hypersensitivity Inform patients that if they have experienced hypersensitivity with other GnRH agonist drugs like ELIGARD, ELIGARD is contraindicated [see Contraindications ( 4 )]. Tumor Flare Inform patients that ELIGARD can cause tumor flare during the first weeks of treatment. Inform patients that the increase in testosterone can cause an increase in urinary symptoms or pain.
Advise patients to contact their healthcare provider if ureteral obstruction, spinal cord compression, paralysis, or new or worsened symptoms occur after beginning ELIGARD treatment [see Warnings and Precautions ( 5.1 )]. Hyperglycemia and Diabetes Advise patients that there is an increased risk of hyperglycemia and diabetes with ELIGARD therapy. Inform patients that periodic monitoring for hyperglycemia and diabetes is required when being treated with ELIGARD [see Warnings and Precautions ( 5.2 )].
Cardiovascular Disease Inform patients that there is an increased risk of myocardial infarction, sudden cardiac death, and stroke with ELIGARD treatment. Advise patients to immediately report signs and symptoms associated with these events to their healthcare provider for evaluation [see Warnings and Precautions ( 5.3 )]. Severe Cutaneous Adverse Reactions Inform patients that severe cutaneous adverse reactions (SCARs), including Stevens-Johnson syndrome (SJS) and toxic epidermal necrolysis (TEN), which may be life threatening or fatal, may occur during treatment with ELIGARD.
Advise patients to contact their healthcare provider or seek medical attention right away if they experience signs or symptoms of SCARs [see Warnings and Precautions ( 5.6 )]. Injection Site Reactions Inform patients that injection site related adverse reactions may occur such as transient burning/stinging, pain, bruising, and redness. Advise patients to contact their healthcare provider if they experience rash or severe injection site reactions [see Adverse Reactions ( 6.1 )].
Urogenital Disorders Advise patients that ELIGARD may cause impotence . Infertility Inform patients that ELIGARD may cause infertility [see Use In Specific Populations ( 8.3 )]. Continuation of ELIGARD Treatment: Inform patients that ELIGARD is usually continued, often with additional medication, after the development of non-metastatic and metastatic castration-resistant prostate cancer [see Dosage and Administration ( 2.1 )].
Manufactured by: Tolmar, Fort Collins, CO 80526 ©2026 Tolmar 04006512 Rev. 6 04/2026