
Acarbose 50 mg Tablet, 100-count — NDC 63629-5698-3 (Billing 63629-5698-03)
This is a package of 100 tablets of Acarbose 50 mg Tablet from Bryant Ranch Prepack, marketed since Dec 2016 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 63629-5698-3 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 63629 labeler · 5698 product · 3 package
- Package marketed since
- Dec 10, 2016
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 6362956983 0
- FDA record last changed
- Aug 27, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 199149
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the alpha-Glucosidase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Acarbose is used (with diet only or diet and other medications) to treat type 2 diabetes (condition in which the body does not use insulin normally and therefore cannot control the amount of sugar in the blood) . Acarbose works by slowing the action of certain chemicals that break down food to release glucose (sugar) into your blood. Slowing food digestion helps keep blood glucose from rising very high after meals. Over time, people who have diabetes and high blood sugar can develop serious or life-threatening complications, including heart disease, stroke, kidney problems, nerve damage, and e...
Read the full MedlinePlus article ↗- Acarbose works in your gut — it blocks enzymes that break down carbohydrates into sugar, which slows how fast glucose gets into your blood after you eat. That's why timing matters...
- What exactly does acarbose do, and why do I need to take it with meals?
- By itself, acarbose does not cause low blood sugar — that's actually one of its advantages. However, if you're also taking a sulfonylurea or insulin alongside acarbose, the combina...
- Will I get low blood sugar (hypoglycemia) from acarbose?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Acarbose — tap one for details:
Acarbose may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.3008 | $30.08 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 5, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 63629-5698-01 63629-5698-1 Main listing | 30 TABLET in 1 BOTTLE | 2016-12-10 | — | Active |
| 63629-5698-02 63629-5698-2 | 90 TABLET in 1 BOTTLE | 2016-12-10 | — | Active |
| 63629-5698-03 You're viewing this | 100 TABLET in 1 BOTTLE | 2016-12-10 | — | Active |
You're viewing the largest of 3 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 63629-5698-01?
What NDC number is used to bill for this package of Acarbose 50 mg Tablet?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Acarbose 50 mg 23155-0148-01 | Heritage | 100 tablets | $0.169 | — | Availability likely | — |
| Acarbose 50 mg 62135-0454-90 | Chartwell | 90 tablets | $0.169 | — | Availability likely | — |
| Acarbose 50 mg 64380-0759-06 | Strides | 100 tablets | $0.169 | AB | Availability likely | — |
| Acarbose 50 mg 00054-0141-20 | Hikma | 100 tablets | — | AB | Discontinued | — |
| Acarbose 50 mgthis 63629-5698-03 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Acarbose 50 mg 71335-9725-01 | Bryant | 30 tablets | — | — | FDA listed | — |
| Acarbose 50 mg 72789-0132-60 | PD-Rx | 60 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Bryant Ranch Prepack labeler code 63629
- Amoxicillin 250 mg Capsule NDC 63629-5512-1
- Junel Fe 28 Day Norethindrone Acetate and Ethinyl Estradiol and Ferrous Fumarate Kit NDC 63629-5628-1
- Acetaminophen and Codeine Phosphate 300 mg; 30 mg Tablet NDC 63629-5666-1
- telmisartan 40 mg Tablet NDC 63629-5682-1
- Darunavir 600 and 800 mg 800 mg Tablet NDC 63629-5686-1
- Hydralazine Hydrochloride 25 mg Tablet, Film Coated NDC 63629-5696-1
- Ritonavir 100 mg Tablet NDC 63629-5702-1
- NP Thyroid 120 LEVOTHYROXINE, LIOTHYRONINE 76 ug; 18 ug Tablet NDC 63629-5716-1
- Amoxicillin 500 mg Capsule NDC 63629-5730-1
- Amoxicillin 500 mg Capsule NDC 63629-5738-1
- Amoxicillin 500 mg Capsule NDC 63629-5739-1
- Cephalexin 500 mg Capsule NDC 63629-5740-1
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Acarbose Tablets are indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION There is no fixed dosage regimen for the management of diabetes mellitus with Acarbose Tablets or any other pharmacologic agent. Dosage of Acarbose Tablets must be individualized on the basis of both effectiveness and tolerance while not exceeding the maximum recommended dose of 100 mg t.i.d. Acarbose Tablets should be taken three times daily at the start (with the first bite) of each main meal.
Acarbose Tablets should be started at a low dose, with gradual dose escalation as described below, both to reduce gastrointestinal side effects and to permit identification of the minimum dose required for adequate glycemic control of the patient. If the prescribed diet is not observed, the intestinal side effects may be intensified. If strongly distressing symptoms develop in spite of adherence to the diabetic diet prescribed, the doctor must be consulted and the dose temporarily or permanently reduced.
During treatment initiation and dose titration (see below), one-hour postprandial plasma glucose may be used to determine the therapeutic response to Acarbose Tablets and identify the minimum effective dose for the patient. Thereafter, glycosylated hemoglobin should be measured at intervals of approximately three months. The therapeutic goal should be to decrease both postprandial plasma glucose and glycosylated hemoglobin levels to normal or near normal by using the lowest effective dose of Acarbose Tablets, either as monotherapy or in combination with sulfonylureas, insulin or metformin.
Initial Dosage The recommended starting dosage of Acarbose Tablets is 25 mg given orally three times daily at the start (with the first bite) of each main meal. However, some patients may benefit from more gradual dose titration to minimize gastrointestinal side effects. This may be achieved by initiating treatment at 25 mg once per day and subsequently increasing the frequency of administration to achieve 25 mg t.i.d.
Maintenance Dosage Once a 25 mg t.i.d. dosage regimen is reached, dosage of Acarbose Tablets should be adjusted at 4-8 week intervals based on one-hour postprandial glucose or glycosylated hemoglobin levels, and on tolerance. The dosage can be increased from 25 mg t.i.d. to 50 mg t.i.d. Some patients may benefit from further increasing the dosage to 100 mg t.i.d.
The maintenance dose ranges from 50 mg t.i.d. to 100 mg t.i.d. However, since patients with low body weight may be at increased risk for elevated serum transaminases, only patients with body weight > 60 kg should be considered for dose titration above 50 mg t.i.d. (see PRECAUTIONS ).
If no further reduction in postprandial glucose or glycosylated hemoglobin levels is observed with titration to 100 mg t.i.d., consideration should be given to lowering the dose. Once an effective and tolerated dosage is established, it should be maintained. Maximum Dosage The maximum recommended dose for patients ≤ 60 kg is 50 mg t.i.d.
The maximum recommended dose for patients > 60 kg is 100 mg t.i.d. Patients Receiving Sulfonylureas or Insulin Sulfonylurea agents or insulin may cause hypoglycemia. Acarbose Tablets given in combination with a sulfonylurea or insulin will cause a further lowering of blood glucose and may increase the potential for hypoglycemia.
If hypoglycemia occurs, appropriate adjustments in the dosage of these agents should be made.
⛔ Contraindications ▾
CONTRAINDICATIONS Acarbose Tablets are contraindicated in patients with known hypersensitivity to the drug. Acarbose Tablets are contraindicated in patients with diabetic ketoacidosis or cirrhosis. Acarbose Tablets are also contraindicated in patients with inflammatory bowel disease, colonic ulceration, partial intestinal obstruction or in patients predisposed to intestinal obstruction.
In addition, Acarbose Tablets are contraindicated in patients who have chronic intestinal diseases associated with marked disorders of digestion or absorption and in patients who have conditions that may deteriorate as a result of increased gas formation in the intestine.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Digestive Tract Gastrointestinal symptoms are the most common reactions to Acarbose Tablets. In U.S. placebo-controlled trials, the incidences of abdominal pain, diarrhea, and flatulence were 19%, 31%, and 74% respectively in 1255 patients treated with Acarbose Tablets 50-300 mg t.i.d., whereas the corresponding incidences were 9%, 12%, and 29% in 999 placebo-treated patients. In a one-year safety study, during which patients kept diaries of gastrointestinal symptoms, abdominal pain and diarrhea tended to return to pretreatment levels over time, and the frequency and intensity of flatulence tended to abate with time.
The increased gastrointestinal tract symptoms in patients treated with Acarbose Tablets are a manifestation of the mechanism of action of Acarbose Tablets and are related to the presence of undigested carbohydrate in the lower GI tract. If the prescribed diet is not observed, the intestinal side effects may be intensified. If strongly distressing symptoms develop in spite of adherence to the diabetic diet prescribed, the doctor must be consulted and the dose temporarily or permanently reduced.
Elevated Serum Transaminase Levels See PRECAUTIONS . Other Abnormal Laboratory Findings Small reductions in hematocrit occurred more often in Acarbose Tablets-treated patients than in placebo-treated patients but were not associated with reductions in hemoglobin. Low serum calcium and low plasma vitamin B 6 levels were associated with Acarbose Tablets therapy but are thought to be either spurious or of no clinical significance.
Postmarketing Adverse Event Reports Additional adverse events reported from worldwide postmarketing experience include fulminant hepatitis with fatal outcome, hypersensitive skin reactions (for example, rash, erythema, exanthema and urticaria), edema, ileus/subileus, jaundice and/or hepatitis and associated liver damage, thrombocytopenia, and pneumatosis cystoides intestinalis (see PRECAUTIONS ). Pneumatosis Cystoides Intestinalis There have been rare postmarketing reports of pneumatosis cystoides intestinalis associated with the use of alpha-glucosidase inhibitors, including Acarbose Tablets.
Pneumatosis cystoides intestinalis may present with symptoms of diarrhea, mucus discharge, rectal bleeding, and constipation. Complications may include pneumoperitoneum, volvulus, intestinal obstruction, intussusception, intestinal hemorrhage, and intestinal perforation. If pneumatosis cystoides intestinalis is suspected, discontinue Acarbose Tablets and perform the appropriate diagnostic imaging.
Call your doctor for medical advice about side effects. You may report side effects to Strides Pharma Inc. at 1-877-244-9825 or go to www.strides.com
🔄 Drug Interactions ▾
Drug Interactions Certain drugs tend to produce hyperglycemia and may lead to loss of blood glucose control. These drugs include the thiazides and other diuretics, corticosteroids, phenothiazines, thyroid products, estrogens, oral contraceptives, phenytoin, nicolinic acid, sympathomimetics, calcium channel-blocking drugs, and isoniazid. When such drugs are administered to a patient receiving Acarbose Tablets, the patient should be closely observed for loss of blood glucose control.
When such drugs are withdrawn from patients receiving Acarbose Tablets in combination with sulfonylureas or insulin, patients should be observed closely for any evidence of hypoglycemia. Patients Receiving Sulfonylureas or Insulin: Sulfonylurea agents or insulin may cause hypoglycemia. Acarbose Tablets given in combination with a sulfonylurea or insulin may cause a further lowering of blood glucose and may increase the potential for hypoglycemia.
If hypoglycemia occurs, appropriate adjustments in the dosage of these agents should be made. Very rarely, individual cases of hypoglycemic shock have been reported in patients receiving Acarbose Tablets therapy in combination with sulfonylureas and/or insulin. Intestinal adsorbents (for example, charcoal) and digestive enzyme preparations containing carbohydrate-splitting enzymes (for example, amylase, pancreatin) may reduce the effect of Acarbose Tablets and should not be taken concomitantly.
Acarbose Tablets have been shown to change the bioavailability of digoxin when they are coadministered, which may require digoxin dose adjustment. (See CLINICAL PHARMACOLOGY, Drug-Drug Interactions. )
🤰 Pregnancy ▾
PREGNANCY Teratogenic Effects: Pregnancy Category B. The safety of Acarbose Tablets in pregnant women has not been established. Reproduction studies have been performed in rats at doses up to 480 mg/kg (corresponding to 9 times the exposure in humans, based on drug blood levels) and have revealed no evidence of impaired fertility or harm to the fetus due to acarbose.
In rabbits, reduced maternal body weight gain, probably the result of the pharmacodynamic activity of high doses of acarbose in the intestines, may have been responsible for a slight increase in the number of embryonic losses. However, rabbits given 160 mg/kg acarbose (corresponding to 10 times the dose in man, based on body surface area) showed no evidence of embryotoxicity and there was no evidence of teratogenicity at a dose 32 times the dose in man (based on body surface area). There are, however, no adequate and well-controlled studies of Acarbose Tablets in pregnant women.
Because animal reproduction studies are not always predictive of the human response, this drug should be used during pregnancy only if clearly needed. Because current information strongly suggests that abnormal blood glucose levels during pregnancy are associated with a higher incidence of congenital anomalies as well as increased neonatal morbidity and mortality, most experts recommend that insulin be used during pregnancy to maintain blood glucose levels as close to normal as possible. Nursing Mothers A small amount of radioactivity has been found in the milk of lactating rats after administration of radiolabeled acarbose.
It is not known whether this drug is excreted in human milk. Because many drugs are excreted in human milk, Acarbose Tablets should not be administered to a nursing woman. Pediatric Use Safety and effectiveness of Acarbose Tablets in pediatric patients have not been established.
Geriatric Use Of the total number of subjects in clinical studies of Acarbose Tablets in the United States, 27% were 65 and over, while 4% were 75 and over. No overall differences in safety and effectiveness were observed between these subjects and younger subjects. The mean steady-state area under the curve (AUC) and maximum concentrations of acarbose were approximately 1.5 times higher in elderly compared to young volunteers; however, these differences were not statistically significant.
🆘 Overdosage ▾
OVERDOSAGE Unlike sulfonylureas or insulin, an overdose of Acarbose Tablets will not result in hypoglycemia. An overdose may result in transient increases in flatulence, diarrhea, and abdominal discomfort which shortly subside. In cases of overdosage the patient should not be given drinks or meals containing carbohydrates (polysaccharides, oligosaccharides and disaccharides) for the next 4-6 hours.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Acarbose is a complex oligosaccharide that delays the digestion of ingested carbohydrates, thereby resulting in a smaller rise in blood glucose concentration following meals. As a consequence of plasma glucose reduction, Acarbose Tablets reduce levels of glycosylated hemoglobin in patients with type 2 diabetes mellitus. Systemic non-enzymatic protein glycosylation, as reflected by levels of glycosylated hemoglobin, is a function of average blood glucose concentration over time.
Mechanism of Action In contrast to sulfonylureas, Acarbose Tablets do not enhance insulin secretion. The antihyperglycemic action of acarbose results from a competitive, reversible inhibition of pancreatic alpha-amylase and membrane-bound intestinal alpha-glucoside hydrolase enzymes. Pancreatic alpha-amylase hydrolyzes complex starches to oligosaccharides in the lumen of the small intestine, while the membrane-bound intestinal alpha-glucosidases hydrolyze oligosaccharides, trisaccharides, and disaccharides to glucose and other monosaccharides in the brush border of the small intestine.
In diabetic patients, this enzyme inhibition results in a delayed glucose absorption and a lowering of postprandial hyperglycemia. Because its mechanism of action is different, the effect of Acarbose Tablets to enhance glycemic control is additive to that of sulfonylureas, insulin or metformin when used in combination. In addition, Acarbose Tablets diminish the insulinotropic and weight-increasing effects of sulfonylureas.
Acarbose has no inhibitory activity against lactase and consequently would not be expected to induce lactose intolerance. Pharmacokinetics: Absorption In a study of 6 healthy men, less than 2% of an oral dose of acarbose was absorbed as active drug, while approximately 35% of total radioactivity from a 14 C-labeled oral dose was absorbed. An average of 51% of an oral dose was excreted in the feces as unabsorbed drug-related radioactivity within 96 hours of ingestion.
Because acarbose acts locally within the gastrointestinal tract, this low systemic bioavailability of parent compound is therapeutically desired. Following oral dosing of healthy volunteers with 14 C-labeled acarbose, peak plasma concentrations of radioactivity were attained 14-24 hours after dosing, while peak plasma concentrations of active drug were attained at approximately 1 hour. The delayed absorption of acarbose-related radioactivity reflects the absorption of metabolites that may be formed by either intestinal bacteria or intestinal enzymatic hydrolysis.
Metabolism Acarbose is metabolized exclusively within the gastrointestinal tract, principally by intestinal bacteria, but also by digestive enzymes. A fraction of these metabolites (approximately 34% of the dose) was absorbed and subsequently excreted in the urine. At least 13 metabolites have been separated chromatographically from urine specimens.
The major metabolites have been identified as 4-methylpyrogallol derivatives (that is, sulfate, methyl, and glucuronide conjugates). One metabolite (formed by cleavage of a glucose molecule from acarbose) also has alpha-glucosidase inhibitory activity. This metabolite, together with the parent compound, recovered from the urine, accounts for less than 2% of the total administered dose.
Excretion The fraction of acarbose that is absorbed as intact drug is almost completely excreted by the kidneys. When acarbose was given intravenously , 89% of the dose was recovered in the urine as active drug within 48 hours. In contrast, less than 2% of an oral dose was recovered in the urine as active (that is, parent compound and active metabolite) drug.
This is consistent with the low bioavailability of the parent drug. The plasma elimination half-life of acarbose activity is approximately 2 hours in healthy volunteers. Consequently, drug accumulation does not occur with three times a day (t.i.d.) oral dosing.
Special Populations The mean steady-state area under the curve (AUC)… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
Mechanism of Action In contrast to sulfonylureas, Acarbose Tablets do not enhance insulin secretion. The antihyperglycemic action of acarbose results from a competitive, reversible inhibition of pancreatic alpha-amylase and membrane-bound intestinal alpha-glucoside hydrolase enzymes. Pancreatic alpha-amylase hydrolyzes complex starches to oligosaccharides in the lumen of the small intestine, while the membrane-bound intestinal alpha-glucosidases hydrolyze oligosaccharides, trisaccharides, and disaccharides to glucose and other monosaccharides in the brush border of the small intestine.
In diabetic patients, this enzyme inhibition results in a delayed glucose absorption and a lowering of postprandial hyperglycemia. Because its mechanism of action is different, the effect of Acarbose Tablets to enhance glycemic control is additive to that of sulfonylureas, insulin or metformin when used in combination. In addition, Acarbose Tablets diminish the insulinotropic and weight-increasing effects of sulfonylureas.
Acarbose has no inhibitory activity against lactase and consequently would not be expected to induce lactose intolerance.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Acarbose Tablets The 25 mg tablet is engraved with 'P210' on one side and '25' on the other side. Product: 63629-5697 NDC: 63629-5697-1 30 TABLET in a BOTTLE NDC: 63629-5697-2 90 TABLET in a BOTTLE The 50 mg tablet is engraved with 'P211' on one side and '50' on the other side. Product: 63629-5698 NDC: 63629-5698-1 30 TABLET in a BOTTLE NDC: 63629-5698-2 90 TABLET in a BOTTLE NDC: 63629-5698-3 100 TABLET in a BOTTLE Store at 20˚ to 25˚C (68˚ to 77˚F) [see USP Controlled Room Temperature].
Protect from moisture. Keep container tightly closed. Repackaged/Relabeled by: Bryant Ranch Prepack, Inc.
Burbank, CA 91504
📋 Description ▾
DESCRIPTION Acarbose Tablets are an oral alpha-glucosidase inhibitor for use in the management of type 2 diabetes mellitus. Acarbose is an oligosaccharide which is obtained from fermentation processes of a microorganism, Actinoplanes utahensis, and is chemically known as O-4,6-dideoxy- 4-[[(1S,4R,5S,6S)-4,5,6-trihydroxy-3-(hydroxymethyl)-2-cyclohexen-1-yl]amino]- α-D-glucopyranosyl-(1 → 4)-O-α-D-glucopyranosyl-(1 → 4)-D-glucose. It is a white to off-white powder with a molecular weight of 645.6.
Acarbose is soluble in water and has a pK a of 5.1. Its empirical formula is C 25 H 43 NO 18 and its chemical structure is as follows: Acarbose Tablets are available as 25 mg, 50 mg and 100 mg for oral use. The inactive ingredients are starch, microcrystalline cellulose, magnesium stearate, and colloidal silicon dioxide. image
⚠️ Precautions ▾
PRECAUTIONS General Macrovascular Outcomes There have been no clinical studies establishing conclusive evidence of macrovascular risk reduction with Acarbose Tablets or any other anti-diabetic drug. Hypoglycemia Because of their mechanism of action, Acarbose Tablets when administered alone should not cause hypoglycemia in the fasted or postprandial state. Sulfonylurea agents or insulin may cause hypoglycemia.
Because Acarbose Tablets given in combination with a sulfonylurea or insulin will cause a further lowering of blood glucose, it may increase the potential for hypoglycemia. Hypoglycemia does not occur in patients receiving metformin alone under usual circumstances of use, and no increased incidence of hypoglycemia was observed in patients when Acarbose Tablets were added to metformin therapy. Oral glucose (dextrose), whose absorption is not inhibited by Acarbose Tablets, should be used instead of sucrose (cane sugar) in the treatment of mild to moderate hypoglycemia.
Sucrose, whose hydrolysis to glucose and fructose is inhibited by Acarbose Tablets, is unsuitable for the rapid correction of hypoglycemia. Severe hypoglycemia may require the use of either intravenous glucose infusion or glucagon injection. Elevated Serum Transaminase Levels In long-term studies (up to 12 months, and including Acarbose Tablets doses up to 300 mg t.i.d.) conducted in the United States, treatment-emergent elevations of serum transaminases (AST and/or ALT) above the upper limit of normal (ULN), greater than 1.8 times the ULN, and greater than 3 times the ULN occurred in 14%, 6%, and 3%, respectively, of Acarbose Tablets-treated patients as compared to 7%, 2%, and 1%, respectively, of placebo-treated patients.
Although these differences between treatments were statistically significant, these elevations were asymptomatic, reversible, more common in females, and, in general, were not associated with other evidence of liver dysfunction. In addition, these serum transaminase elevations appeared to be dose related. In US studies including Acarbose Tablets doses up to the maximum approved dose of 100 mg t.i.d., treatment-emergent elevations of AST and/or ALT at any level of severity were similar between Acarbose Tablets-treated patients and placebo-treated patients (p ≥ 0.496).
In approximately 3 million patient-years of international postmarketing experience with Acarbose Tablets, 62 cases of serum transaminase elevations > 500 IU/L (29 of which were associated with jaundice) have been reported. Forty-one of these 62 patients received treatment with 100 mg t.i.d. or greater and 33 of 45 patients for whom weight was reported weighed < 60 kg. In the 59 cases where follow-up was recorded, hepatic abnormalities improved or resolved upon discontinuation of Acarbose Tablets in 55 and were unchanged in two.
Cases of fulminant hepatitis with fatal outcome have been reported; the relationship to acarbose is unclear. Loss of Control of Blood Glucose When diabetic patients are exposed to stress such as fever, trauma, infection, or surgery, a temporary loss of control of blood glucose may occur. At such times, temporary insulin therapy may be necessary.
Information for Patients Patients should be told to take Acarbose Tablets orally three times a day at the start (with the first bite) of each main meal. It is important that patients continue to adhere to dietary instructions, a regular exercise program, and regular testing of urine and/or blood glucose. Acarbose Tablets themselves do not cause hypoglycemia even when administered to patients in the fasted state.
Sulfonylurea drugs and insulin, however, can lower blood sugar levels enough to cause symptoms or sometimes life-threatening hypoglycemia. Because Acarbose Tablets given in combination with a sulfonylurea or insulin will cause a further lowering of blood sugar, it may increase the hypoglycemic potential of these agents. Hypoglycemia does not occur in patients receiving metformin alone under usual circums… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
Pharmacokinetics: Absorption In a study of 6 healthy men, less than 2% of an oral dose of acarbose was absorbed as active drug, while approximately 35% of total radioactivity from a 14 C-labeled oral dose was absorbed. An average of 51% of an oral dose was excreted in the feces as unabsorbed drug-related radioactivity within 96 hours of ingestion. Because acarbose acts locally within the gastrointestinal tract, this low systemic bioavailability of parent compound is therapeutically desired.
Following oral dosing of healthy volunteers with 14 C-labeled acarbose, peak plasma concentrations of radioactivity were attained 14-24 hours after dosing, while peak plasma concentrations of active drug were attained at approximately 1 hour. The delayed absorption of acarbose-related radioactivity reflects the absorption of metabolites that may be formed by either intestinal bacteria or intestinal enzymatic hydrolysis. Metabolism Acarbose is metabolized exclusively within the gastrointestinal tract, principally by intestinal bacteria, but also by digestive enzymes.
A fraction of these metabolites (approximately 34% of the dose) was absorbed and subsequently excreted in the urine. At least 13 metabolites have been separated chromatographically from urine specimens. The major metabolites have been identified as 4-methylpyrogallol derivatives (that is, sulfate, methyl, and glucuronide conjugates).
One metabolite (formed by cleavage of a glucose molecule from acarbose) also has alpha-glucosidase inhibitory activity. This metabolite, together with the parent compound, recovered from the urine, accounts for less than 2% of the total administered dose. Excretion The fraction of acarbose that is absorbed as intact drug is almost completely excreted by the kidneys.
When acarbose was given intravenously , 89% of the dose was recovered in the urine as active drug within 48 hours. In contrast, less than 2% of an oral dose was recovered in the urine as active (that is, parent compound and active metabolite) drug. This is consistent with the low bioavailability of the parent drug.
The plasma elimination half-life of acarbose activity is approximately 2 hours in healthy volunteers. Consequently, drug accumulation does not occur with three times a day (t.i.d.) oral dosing. Special Populations The mean steady-state area under the curve (AUC) and maximum concentrations of acarbose were approximately 1.5 times higher in elderly compared to young volunteers; however, these differences were not statistically significant.
Patients with severe renal impairment (Clcr < 25 mL/min/1.73m 2 ) attained about 5 times higher peak plasma concentrations of acarbose and 6 times larger AUCs than volunteers with normal renal function. No studies of acarbose pharmacokinetic parameters according to race have been performed. In U.S. controlled clinical studies of Acarbose Tablets in patients with type 2 diabetes mellitus, reductions in glycosylated hemoglobin levels were similar in Caucasians (n=478) and African-Americans (n=167), with a trend toward a better response in Latinos (n=132).
Drug-Drug Interactions Studies in healthy volunteers have shown that Acarbose Tablets have no effect on either the pharmacokinetics or pharmacodynamics of nifedipine, propranolol, or ranitidine. Acarbose Tablets did not interfere with the absorption or disposition of the sulfonylurea glyburide in diabetic patients. Acarbose Tablets may affect digoxin bioavailability and may require dose adjustment of digoxin by 16% (90% confidence interval: 8-23%), decrease mean C max of digoxin by 26% (90% confidence interval: 16-34%) and decreases mean trough concentrations of digoxin by 9% (90% confidence limit: 19% decrease to 2% increase).
(See PRECAUTIONS, Drug Interactions . ) The amount of metformin absorbed while taking Acarbose Tablets was bioequivalent to the amount absorbed when taking placebo, as indicated by the plasma AUC values. However, the peak plasma level of metformin was reduced by approxim… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
CLINICAL TRIALS Clinical Experience from Dose Finding Studies in Type 2 Diabetes Mellitus Patients on Dietary Treatment Only: Results from six controlled, fixed-dose, monotherapy studies of Acarbose Tablets in the treatment of type 2 diabetes mellitus, involving 769 Acarbose Tablets-treated patients, were combined and a weighted average of the difference from placebo in the mean change from baseline in glycosylated hemoglobin (HbA1c) was calculated for each dose level as presented below: Table 1 Mean Placebo-Subtracted Change in HbA1c in Fixed-Dose Monotherapy Studies * Acarbose Tablets were statistically significantly different from placebo at all doses.
Although there were no statistically significant differences among the mean results for doses ranging from 50 to 300 mg t.i.d., some patients may derive benefit by increasing the dosage from 50 to 100 mg t.i.d. ** Although studies utilized a maximum dose of 200 or 300 mg t.i.d., the maximum recommended dose for patients < 60 kg is 50 mg t.i.d.; the maximum recommended dose for patients > 60 kg is 100 mg t.i.d. Mean Placebo-Subtracted Change In HbA1c In Fixed-Dose Monotherapy Studies Dose of Acarbose Tablets* N Change in HbA1c % p-Value 25 mg t.i.d.
110 -0.44 0.0307 50 mg t.i.d. 131 -0.77 0.0001 100 mg t.i.d. 244 -0.74 0.0001 200 mg t.i.d. ** 231 -0.86 0.0001 300 mg t.i.d. ** 53 -1.00 0.0001 Results from these six fixed-dose, monotherapy studies were also combined to derive a weighted average of the difference from placebo in mean change from baseline for one-hour postprandial plasma glucose levels as shown in the following figure: Figure 1 * Acarbose Tablets were statistically significantly different from placebo at all doses with respect to effect on one-hour postprandial plasma glucose. ** The 300 mg t.i.d.
Acarbose Tablets regimen was superior to lower doses, but there were no statistically significant differences from 50 to 200 mg t.i.d. Clinical Experience in Type 2 Diabetes Mellitus Patients on Monotherapy, or in Combination with Sulfonylureas, Metformin or Insulin: Acarbose Tablets were studied as monotherapy and as combination therapy to sulfonylurea, metformin, or insulin treatment. The treatment effects on HbA1c levels and one-hour postprandial glucose levels are summarized for four placebo-controlled, double-blind, randomized studies conducted in the United States in Tables 2 and 3, respectively.
The placebo-subtracted treatment differences, which are summarized below, were statistically significant for both variables in all of these studies. Study 1 (n=109) involved patients on background treatment with diet only. The mean effect of the addition of Acarbose Tablets to diet therapy was a change in HbA1c of ‑0.78%, and an improvement of one-hour postprandial glucose of -74.4 mg/dL.
In Study 2 (n=137), the mean effect of the addition of Acarbose Tablets to maximum sulfonylurea therapy was a change in HbA1c of -0.54%, and an improvement of one-hour postprandial glucose of -33.5 mg/dL. In Study 3 (n=147), the mean effect of the addition of Acarbose Tablets to maximum metformin therapy was a change in HbA1c of -0.65%, and an improvement of one-hour postprandial glucose of -34.3 mg/dL. Study 4 (n=145) demonstrated that Acarbose Tablets added to patients on background treatment with insulin resulted in a mean change in HbA1c of -0.69%, and an improvement of one-hour postprandial glucose of -36.0 mg/dL.
A one year study of Acarbose Tablets as monotherapy or in combination with sulfonylurea, metformin or insulin treatment was conducted in Canada in which 316 patients were included in the primary efficacy analysis (Figure 2). In the diet, sulfonylurea and metformin groups, the mean decrease in HbA1c produced by the addition of Acarbose Tablets was statistically significant at six months, and this effect was persistent at one year. In the Acarbose Tablets-treated patients on insulin, there was a statistically significant reduction in HbA1c at six months, and a trend for a red… [Excerpted — this section continues on DailyMed.]
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, and Impairment of Fertility Eight carcinogenicity studies were conducted with acarbose. Six studies were performed in rats (two strains, Sprague-Dawley and Wistar) and two studies were performed in hamsters. In the first rat study, Sprague-Dawley rats received acarbose in feed at high doses (up to approximately 500 mg/kg body weight) for 104 weeks.
Acarbose treatment resulted in a significant increase in the incidence of renal tumors (adenomas and adenocarcinomas) and benign Leydig cell tumors. This study was repeated with a similar outcome. Further studies were performed to separate direct carcinogenic effects of acarbose from indirect effects resulting from the carbohydrate malnutrition induced by the large doses of acarbose employed in the studies.
In one study using Sprague-Dawley rats, acarbose was mixed with feed but carbohydrate deprivation was prevented by the addition of glucose to the diet. In a 26-month study of Sprague-Dawley rats, acarbose was administered by daily postprandial gavage so as to avoid the pharmacologic effects of the drug. In both of these studies, the increased incidence of renal tumors found in the original studies did not occur.
Acarbose was also given in food and by postprandial gavage in two separate studies in Wistar rats. No increased incidence of renal tumors was found in either of these Wistar rat studies. In two feeding studies of hamsters, with and without glucose supplementation, there was also no evidence of carcinogenicity.
Acarbose did not induce any DNA damage i n-vitro in the CHO chromosomal aberration assay, bacterial mutagenesis (Ames) assay, or a DNA binding assay. In-vivo , no DNA damage was detected in the dominant lethal test in male mice, or the mouse micronucleus test. Fertility studies conducted in rats after oral administration produced no untoward effect on fertility or on the overall capability to reproduce.
📄 Package Label / Principal Display Panel ▾
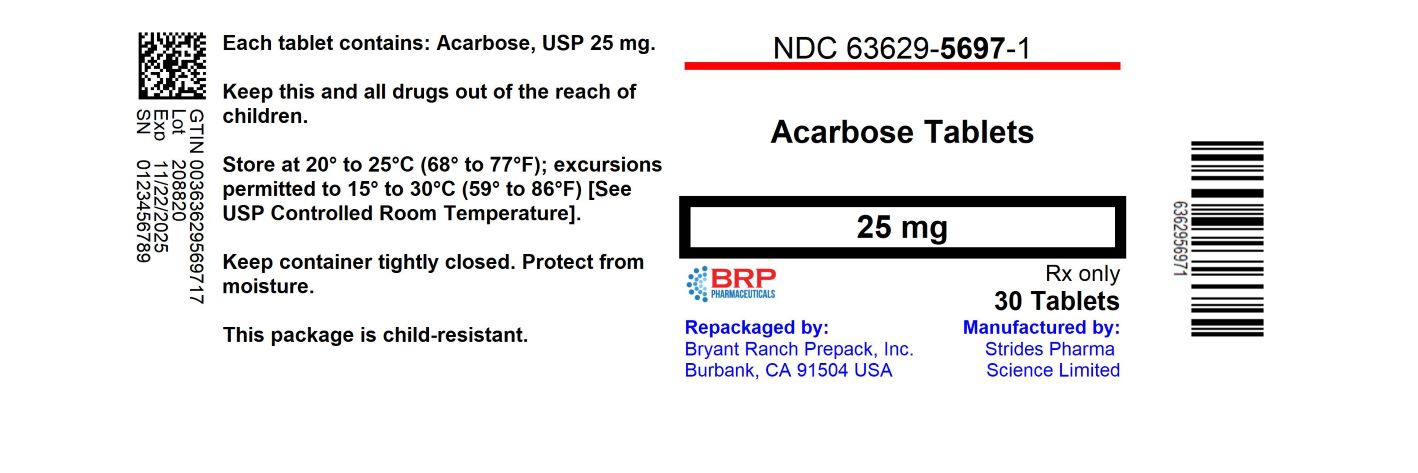
ACARBOSE TABLET Label Image
ACARBOSE TABLET Label Image
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |