
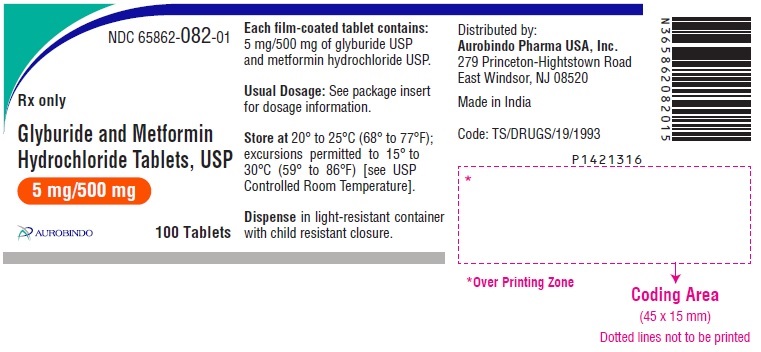
Glyburide and Metformin Hydrochloride 5 mg; 500 mg Tablet, Film Coated, 100-count — NDC 65862-082-01 (Billing 65862-0082-01)
This is a package of 100 tablets of Glyburide and Metformin Hydrochloride 5 mg; 500 mg Tablet, Film Coated from Aurobindo Pharma Limited, marketed since Nov 2007 and currently FDA-listed; retail pharmacies pay about $0.1896 per tablet (NADAC). It is the main listing for this product, which comes in 4 package sizes.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 045930
- GCN: 89879
- GPI-14 (Medi-Span): 27997002400330
- HICL (First Databank): 009690
- AHFS class code: 68:20.04.00
- RxCUI (RxNorm): 861743
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Sulfonylurea class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It helps lower blood sugar in adults with type 2 diabetes. It works best together with healthy eating and exercise. It combines two diabetes medicines in one tablet.
- Take it by mouth with meals, usually twice a day. Taking it with food helps lower the chance of low blood sugar and stomach upset. Follow your prescriber's directions and the label...
- Stomach issues like diarrhea, nausea and belly pain are most common, along with headache and dizziness. Low blood sugar can cause shakiness, sweating and hunger. Keep a quick sugar...
- Get help right away if you have unusual tiredness, muscle aches, trouble breathing, unusual sleepiness or stomach pain. These can be signs of lactic acidosis. Also seek help for se...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.190 | $18.96 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.2528 | $25.28 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.2180 | $21.80 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 65862-0082-01 You're viewing this Main listing | 100 TABLET, FILM COATED in 1 BOTTLE | $0.1896 / ea | $18.96 | 2007-11-14 | — | Active |
| 65862-0082-05 65862-082-05 | 500 TABLET, FILM COATED in 1 BOTTLE | $0.1896 / ea | $94.82 | 2007-11-14 | — | Active |
| 65862-0082-30 65862-082-30 | 30 TABLET, FILM COATED in 1 BOTTLE | — | — | 2007-11-14 | — | Active |
| 65862-0082-18 65862-082-18 | 1800 TABLET, FILM COATED in 1 BAG | — | — | — | — | Active |
You're viewing one of 4 pack sizes for this product.
This pack has the lowest per-ea cost of the 2 priced pack sizes ($0.1896 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 76% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 65862-0082-30?
What NDC number is used to bill for this package of Glyburide and Metformin Hydrochloride 5 mg; 500 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| glyburide-metformin hydrochloride 5 mg/1; 500 mg 23155-0235-01 | Heritage | 100 tablets | $0.190 | AB | Availability likely | — |
| Glyburide and Metformin Hydrochloride 5 mg/1; 500 mg 57237-0025-01 | Rising | 100 tablets | $0.190 | AB | Availability likely | — |
| Glyburide and Metformin Hydrochloride 5 mg/1; 500 mgthis 65862-0082-01 | Aurobindo | 100 tablets | $0.190 | AB | Availability likely | — |
| Glyburide and Metformin Hydrochloride 5 mg/1; 500 mg 50090-2030-00 | A-S | 60 tablets | — | AB | FDA listed | — |
| glyburide-metformin hydrochloride 5 mg/1; 500 mg 50090-7514-00 | A-S | 60 tablets | — | AB | FDA listed | — |
| Glyburide and Metformin Hydrochloride 5 mg/1; 500 mg 51655-0942-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| glyburide and metformin hydrochloride 5 mg/1; 500 mg 65841-0826-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| glyburide-metformin hydrochloride 5 mg/1; 500 mg 68071-3950-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Glyburide and Metformin Hydrochloride 5 mg/1; 500 mg 68071-4718-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| glyburide and metformin hydrochloride 5 mg/1; 500 mg 68382-0655-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Glyburide and Metformin Hydrochloride 5 mg/1; 500 mg 68788-8341-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Glyburide and Metformin Hydrochloride 5 mg/1; 500 mg 68788-8634-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| glyburide-metformin hydrochloride 5 mg/1; 500 mg 68788-8791-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Glyburide and Metformin Hydrochloride 5 mg/1; 500 mg 71335-0360-01 | Bryant | 30 tablets | — | AB | Discontinued | — |
| Glyburide and Metformin Hydrochloride 5 mg/1; 500 mg 71335-0967-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| glyburide-metformin hydrochloride 5 mg/1; 500 mg 71335-2508-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: LACTIC ACIDOSIS Postmarketing cases of metformin-associated lactic acidosis have resulted in death, hypothermia, hypotension, and resistant bradyarrhythmias. The onset of metformin-associated lactic acidosis is often subtle, accompanied only by nonspecific symptoms such as malaise, myalgias, respiratory distress, somnolence, and abdominal pain. Metformin-associated lactic acidosis was characterized by elevated blood lactate levels (>5 mmol/Liter), anion gap acidosis (without evidence of ketonuria or ketonemia), an increased lactate/pyruvate ratio; and metformin plasma levels generally >5 mcg/mL [see Warnings and Precautions (5.1) ].
Risk factors for metformin-associated lactic acidosis include renal impairment, concomitant use of certain drugs (e.g., carbonic anhydrase inhibitors such as topiramate), age 65 years old or greater, having a radiological study with contrast, surgery and other procedures, hypoxic states (e.g., a cu te congestive heart failure), excessive alcohol intake , hepatic impairment, and mitochondrial diseases [see Warnings and Precautions (5.1) ]. Steps to reduce the risk of and manage metformin-associated lactic acidosis in these high risk groups are provided [see Dosage and Administration (2.3) , Contraindications (4) and Warnings and Precautions (5.1) ] .
If metformin-associated lactic acidosis is suspected, immediately discontinue glyburide and metformin hydrochloride and institute general supportive measures in a hospital setting. Prompt hemodialysis is recommended [see Warnings and Precautions (5.1) ]. WARNING: LACTIC ACIDOSIS See full prescribing information for complete boxed warning.
Post-marketing cases of metformin-associated lactic acidosis have resulted in death, hypothermia, hypotension, and resistant bradyarrhythmias. Symptoms include malaise, myalgias, respiratory distress, somnolence, and abdominal pain. Laboratory abnormalities included elevated blood lactate levels, anion gap acidosis, increased lactate/pyruvate ratio; and metformin plasma levels generally >5 mcg/mL.
(5.1) Risk factors include renal impairment, concomitant use of certain drugs, age ≥ 65 years old, radiological study with contrast, surgery and other procedures, hypoxic states, excessive alcohol intake , hepatic impairment, and mitochondrial diseases . Steps to reduce the risk of and manage metformin-associated lactic acidosis in these high risk groups are provided in the Full Prescribing Information. (5.1) If lactic acidosis is suspected, discontinue glyburide and metformin hydrochloride and institute general supportive measures in a hospital setting.
Prompt hemodialysis is recommended. (5.1)
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Glyburide and metformin hydrochloride tablets are indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus. Glyburide and metformin hydrochloride tablets are a combination of glyburide, a sulfonylurea, and metformin hydrochloride (HCl), a biguanide, indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus. (1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Adult Dosage: Give glyburide and metformin hydrochloride tablets in divided doses, twice daily, with meals. ( 2.1 ) For patients not treated with either glyburide (or another sulfonylurea) or metformin HCl, initiate treatment with another formulation with a dose of 1.25 mg glyburide and 250mg metformin HCl orally, once or twice daily with meals. ( 2.1 ) For patients not adequately controlled on either glyburide (or another sulfonylurea) or metformin HCl alone, the recommended starting dose is 2.5 mg/500 mg or 5 mg/500 mg orally twice daily with meals.
( 2.1 ) For patients previously treated with a combination therapy of glyburide (or another sulfonylurea) and metformin HCl, the starting dose should not exceed the daily dose of glyburide (or equivalent dose of another sulfonylurea) and metformin HCl already being taken. ( 2.1 ) Increase the dose gradually on the basis of glycemic control and tolerability, up to a maximum to a maximum dose of 20 mg glyburide/2000 mg metformin HCl daily. ( 2.1 ) Renal Impairment: Prior to initiation, assess renal function with estimated glomerular filtration rate (eGFR) ( 2.4 ) Do not use in patients with eGFR below 30 mL/minute/1.73 m 2 ( 2.4 ) Initiation is not recommended in patients with eGFR between 30 to 45 mL/minute/1.73 m 2 ( 2.4 ) Assess risk/benefit if eGFR falls below 45 mL/minute/1.73 m 2 ( 2.4 ) Discontinue if eGFR falls below 30 mL/minute/1.73 m 2 ( 2.4 ) Discontinuation for Iodinated Contrast Imaging Procedures: Glyburide and metformin hydrochloride tablets may need to be discontinued at time of, or prior to, iodinated contrast imaging procedures (2.5)
2.1Dosage Give glyburide and metformin hydrochloride tablets in divided doses, twice daily, with meals. For patients not treated with either glyburide (or another sulfonylurea) or metformin hydrochloride (HCl), initiate treatment with another formulation of glyburide and metformin HCl at a starting dose of 1.25 mg glyburide and 250mg metformin HCl orally, once or twice daily with meals. For patients not adequately controlled on either glyburide (or another sulfonylurea) or metformin HCl alone, the recommended starting dose of glyburide and metformin hydrochloride tablets is 2.5 mg/500 mg or 5 mg/500 mg orally twice daily with meals.
For patients previously treated with a combination therapy of glyburide (or another sulfonylurea) and metformin HCl, the starting dose of glyburide and metformin hydrochloride tablets should not exceed the daily dose of glyburide (or equivalent dose of another sulfonylurea) and metformin HCl already being taken. Increase the dose gradually on the basis of glycemic control and tolerability, up to a maximum to a maximum dose of 20 mg glyburide/2000 mg metformin HCl daily.
2.2Patients Receiving Colesevelam Administer glyburide and metformin hydrochloride tablets at least 4 hours prior to colesevelam for patients taking both drugs concomitantly [see Drug Interactions (7) ].
2.3Recommendations for Use in Renal Impairment Assess renal function prior to initiation of glyburide and metformin hydrochloride tablets and periodically thereafter. Glyburide and metformin hydrochloride tablets are contraindicated in patients with an estimated glomerular filtration rate (eGFR) below 30 mL/minute/1.73 m 2 . Initiation of glyburide and metformin hydrochloride tablets in patients with an eGFR between 30 to 45 mL/minute/1.73 m 2 is not recommended.
In patients taking glyburide and metformin hydrochloride tablets whose eGFR later falls below 45 mL/min/1.73 m 2 , assess the benefit risk of continuing therapy. Discontinue glyburide and metformin hydrochloride tablets if the patient’s eGFR later falls below 30 mL/minute/1.73 m 2 [see Warnings and Precautions (5.1) ].
2.4Discontinuation for Iodinated Contrast Imaging Procedures Discontinue glyburide and metformin hydrochloride tablets at the time of, or prior to, an iodinated contrast imaging procedure in patients with an eGFR between 30 and 60 mL/… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Glyburide and metformin hydrochloride tablets, USP are available as: 1.25 mg/250 mg Tablets: Yellow, capsule shaped, biconvex, film-coated tablet with ‘A’ debossed on one side and ‘46’ on the other side. 2.5 mg/500 mg Tablets: Light pink, capsule shaped, biconvex, film-coated tablet with ‘A’ debossed on one side and ‘47’ on the other side. 5 mg/500 mg Tablets: Yellow, capsule shaped, biconvex, film-coated tablet with ‘A’ debossed on one side and ‘48’ on the other side Tablets: 1.25 mg glyburide and 250 mg metformin HCl (3) Tablets: 2.5 mg glyburide and 500 mg metformin HCl (3) Tablets: 5 mg glyburide and 500 mg metformin HCl (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Glyburide and metformin hydrochloride tablets are contraindicated in patients with: Severe renal impairment (eGFR below 30 mL/min/1.73 m 2 ) [see Warnings and Precautions (5.1) ]. Hypersensitivity to metformin or glyburide. Acute or chronic metabolic acidosis, including diabetic ketoacidosis, with or without coma.
Concomitant administration of bosentan [see Drug Interactions (7) ]. Severe renal impairment (eGFR below 30 mL/min/1.73 m 2 ) (4 , 5.1) Hypersensitivity to metformin or glyburide. (4) Acute or chronic metabolic acidosis, including diabetic ketoacidosis, with or without coma.
(4) Concomitant administration of bosentan. (4 , 7)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Lactic Acidosis: See boxed warning. (5.1) Hypoglycemia: May be severe. Ensure proper patient selection, dosing, and instructions, particularly in at-risk populations (e.g., elderly, renally impaired) and when used with other anti-diabetic medications.
(5.2) Potential Increased Risk of Cardiovascular Mortality with Sulfonylureas: Inform patient of risks, benefits and treatment alternatives. (5.3) Hemolytic anemia: Can occur if glucose 6-phosphate dehydrogenase (G6PD) deficient. Consider a non-sulfonylurea alternative.
(5.4) Vitamin B 12 Deficiency: Metformin may lower vitamin B 12 levels. Measure hematological parameters annually and vitamin B 12 at 2 to 3 year intervals and manage any abnormalities. (5.5)
5.1Lactic Acidosis There have been postmarketing cases of metformin-associated lactic acidosis, including fatal cases. These cases had a subtle onset and were accompanied by nonspecific symptoms such as malaise, myalgias, abdominal pain, respiratory distress, or increased somnolence; however, hypotension and resistant bradyarrhythmias have occurred with severe acidosis. Metformin-associated lactic acidosis was characterized by elevated blood lactate concentrations (>5 mmol/L), anion gap acidosis (without evidence of ketonuria or ketonemia), and an increased lactate: pyruvate ratio; metformin plasma levels were generally >5 mcg/mL.
Metformin decreases liver uptake of lactate increasing lactate blood levels which may increase the risk of lactic acidosis, especially in patients at risk. If metformin-associated lactic acidosis is suspected, general supportive measures should be instituted promptly in a hospital setting, along with immediate discontinuation of glyburide and metformin hydrochloride. In glyburide and metformin hydrochloride treated patients with a diagnosis or strong suspicion of lactic acidosis, prompt hemodialysis is recommended to correct the acidosis and remove accumulated metformin (metformin HCl is dialyzable with a clearance of up to 170 mL/min under good hemodynamic conditions).
Hemodialysis has often resulted in reversal of symptoms and recovery. Educate patients and their families about the symptoms of lactic acidosis and, if these symptoms occur, instruct them to discontinue glyburide and metformin hydrochloride and report these symptoms to their healthcare provider. For each of the known and possible risk factors for metformin-associated lactic acidosis, recommendations to reduce the risk of and manage metformin-associated lactic acidosis are provided below: Renal Impairment —The postmarketing metformin-associated lactic acidosis cases primarily occurred in patients with significant renal impairment.
The risk of metformin accumulation and metformin-associated lactic acidosis increases with the severity of renal impairment because metformin is substantially excreted by the kidney. Clinical recommendations based upon the patient’s renal function include [see Dosage and Administration (2.1) , Clinical Pharmacology (12.3) ]: Before initiating glyburide and metformin hydrochloride, obtain an estimated glomerular filtration rate (eGFR). Glyburide and metformin hydrochloride is contraindicated in patients with an eGFR less than 30 mL/min/1.73 m 2 [see CONTRAINDICATIONS (4) ] .
Initiation of glyburide and metformin hydrochloride is not recommended in patients with eGFR between 30 to 45 mL/min/1.73 m 2 . Obtain an eGFR at least annually in all patient taking glyburide and metformin hydrochloride. In patients at risk for the development of renal impairment (e.g., the elderly), renal function should be assessed more frequently.
In patients taking glyburide and metformin hydrochloride whose eGFR falls below 45 mL/min/1.73 m 2 , assess the benefit and risk of continuing therapy. Drug interactions —The concomitant use of glyburide and metformin hydrochloride with specific drugs may increase the risk of metformin-associated lactic acidosis: those that impair renal function, result in signifi… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are also discussed elsewhere in the labeling: Lactic Acidosis [see Boxed Warning and Warnings and Precautions (5.1) ] Hypoglycemia [see Warnings and Precautions (5.2) ] Cardiovascular mortality [see Warnings and Precautions (5.3) ] Hemolytic anemia [see Warnings and Precautions (5.4) ] Vitamin B 12 Deficiency [ see Warnings and Precautions (5.5) ] Most common (>5%) adverse reactions to glyburide and metformin hydrochloride diarrhea, headache, nausea/vomiting, abdominal pain, and dizziness.
(6.1) To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Studies Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. In double-blind clinical studies with glyburide and metformin hydrochloride as initial therapy or as second-line therapy of 20 and 14 weeks, respectively (see section 14 ), a total of 642 patients received glyburide and metformin hydrochloride, 312 received metformin HCl, 324 received glyburide, and 161 received placebo.
Adverse reactions are listed in Table 1. Table 1: Adverse Reactions Occurring >5% in Double-Blind Clinical Studies of Glyburide And Metformin Hydrochloride Used as Initial (20 Weeks) or Second-Line (14 Weeks) Therapy Adverse Reaction Number (%) of Patients Placebo N=161 Glyburide N=324 Metformin HCl N=312 Glyburide and Metformin Hydrochloride N=642 Diarrhea 6% 6% 21% 17% Headache 11% 11% 9% 9% Nausea/vomiting 6% 5% 12% 8% Abdominal pain 4% 3% 8% 7% Dizziness 4% 6% 4% 6% Hypoglycemia The incidence of reported symptoms of hypoglycemia (such as dizziness, shakiness, sweating, and hunger), in the initial therapy study of glyburide and metformin hydrochloride are summarized in Table 2.
For patients with a baseline HbA1c between 8% and 11% treated with glyburide and metformin hydrochloride 2.5 mg/500 mg as initial therapy, the frequency of hypoglycemic symptoms was 30% to 35%. As second-line therapy in patients inadequately controlled on sulfonylurea alone, approximately 6.8% of all patients treated with glyburide and metformin hydrochloride experienced hypoglycemic symptoms. Gastrointestinal Reactions The incidence of gastrointestinal (GI) side effects (diarrhea, nausea/vomiting, and abdominal pain) in the glyburide and metformin hydrochloride initial therapy study are summarized in Table 2.
Across all glyburide and metformin hydrochloride studies, GI symptoms were the most common adverse events with glyburide and metformin hydrochloride and were more frequent at higher dose levels. In controlled studies, <2% of patients discontinued glyburide and metformin hydrochloride therapy due to GI adverse events. Table 2: Hypoglycemia or Gastrointestinal Adverse Reactions in a Placebo- and Active-Controlled Study of Glyburide and Metformin Hydrochloride as Initial Therapy (20 Weeks) Variable Placebo N=161 Glyburide Tablets N=160 Metformin HCl Tablets N=159 Glyburide and Metformin Hydrochloride 1.25 mg/250 mg Tablets N=158 Glyburide and Metformin Hydrochloride 2.5 mg/500 mg Tablets N=162 Number (%) of patients with symptoms of hypoglycemia 3% 21% 3% 11% 38% Number (%) of patients with gastrointestinal adverse events 24% 24% 43% 32% 38% Dermatologic Reactions Allergic skin reactions, e.g., pruritus, erythema, urticaria, and morbilliform or maculopapular eruptions, occur in 1.5% of glyburide-treated patients.
These may be transient and may disappear despite continued use.
6.2Postmarketing Adverse Reactions The following adverse reactions have been identified during post-approval use of glyburide and metformin hydrochloride. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably esti… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 3 presents clinically significant drug interactions with glyburide and metformin hydrochloride. Table 3: Clinically Significant Drug Interactions with Glyburide and Metformin Hydrochloride Carbonic Anhydrase Inhibitors Clinical Impact: Carbonic anhydrase inhibitors frequently cause a decrease in serum bicarbonate and induce non-anion gap, hyperchloremic metabolic acidosis. Concomitant use of these drugs with glyburide and metformin hydrochloride may increase the risk for lactic acidosis.
Intervention: Consider more frequent monitoring of these patients. Examples: Topiramate, zonisamide, acetazolamide and dichlorphenamide. Drugs that Reduce Metformin Clearance Clinical Impact: Concomitant use of drugs that interfere with common renal tubular transport systems involved in the renal elimination of metformin (e.g., organic cationic transporter-2 [OCT2] / multidrug and toxin extrusion [MATE] inhibitors) could increase systemic exposure to metformin and may increase the risk for lactic acidosis [ see Clinical Pharmacology (12.3) ].
Intervention: Consider the benefits and risks of concomitant use with glyburide and metformin hydrochloride. Examples: Ranolazine, vandetanib, dolutegravir, and cimetidine. Alcohol Clinical Impact: Alcohol is known to potentiate the effect of metformin on lactate metabolism.
Intervention: Warn patients against excessive alcohol intake while receiving glyburide and metformin hydrochloride. Drugs that potentiate the hypoglycemic action of glyburide and metformin hydrochloride Clinical Impact: Certain drugs may potentiate the hypoglycemic action of sulfonylureas, one of the components of glyburide and metformin hydrochloride. Intervention: Closely observe patient for hypoglycemia during co-administration and for loss of glycemic control when withdrawing these agents.
Examples: Nonsteroidal anti-inflammatory agents and other highly protein-boind drugs, salicylcates, sulfonamides, chloramphenicol, probenecid, coumarins, monoamine oxidase inhibitors, beta-adrenergic blocking agents; potentially with ciprofloxacin, micronazole. Bosentan Clinical Impact: Increased risk of liver enzyme elevations was observed. Intervention: Concomitant administration is contraindicated.
Colesevalam Clinical Impact: Concomitant administration may led to reduced glyburide absorption (AUC and Cmax: -32% and -47%, respectively). Intervention: Glyburide and metformin hydrochloride should be administered at least 4 hours prior to colesevelam. Drugs Reducing Glycemic Control Clinical Impact: Certain drugs tend to produce hyperglycemia and may lead to loss of glycemic control.
Intervention: When such drugs are administered to a patient receiving glyburide and metformin hydrochloride observe the patient closely for loss of blood glucose control. When such drugs are withdrawn from a patient receiving glyburide and metformin hydrochloride, observe the patient closely for hypoglycemia. Examples: Thiazides and other diuretics, corticosteroids, phenothiazines, thyroid products, estrogens, oral contraceptives, phenytoin, nicotinic acid, sympathomimetics, calcium channel blockers, and isoniazid.
Carbonic anhydrase inhibitors may increase risk of lactic acidosis. Consider more frequent monitoring. (7) Drugs that reduce metformin clearance (such as ranolazine, vandetanib, dolutegravir, and cimetidine) may increase the accumulation of metformin.
Consider the benefits and risks of concomitant use. (7) Alcohol can potentiate the effect of metformin on lactate metabolism. Warn patients against excessive alcohol intake.
(7) The hypoglycemic action of glyburide and metformin hydrochloride may be potentiated by certain drugs. (7) Concomitant administration of colesevalam may led to reduced glyburide absorption. (7)
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Glyburide and metformin hydrochloride should be discontinued at least two weeks before expected delivery. (8.1) Females and Males of Reproductive Potential: Advise premenopausal females of the potential for an unintended pregnancy. (8.3) Geriatric Use: Assess renal function more frequently. (8.5) Hepatic Impairment: Avoid use in patients with hepatic impairment. (8.7)
8.1Pregnancy Risk Summary Available data from a small number of published studies and postmarketing experience with glyburide use in pregnancy over decades have not identified any drug associated risks for major birth defects, miscarriage, or adverse maternal outcomes. However, sulfonylureas (including glyburide) cross the placenta and have been associated with neonatal adverse reactions such as hypoglycemia. Therefore, glyburide and metformin hydrochloride should be discontinued at least two weeks before expected delivery [see Clinical Considerations ].
Limited data with metformin in pregnant women are not sufficient to determine a drug-associated risk for major birth defects or miscarriage. Published studies with metformin use during pregnancy have not reported a clear association with metformin and major birth defect or miscarriage risk [see Data ]. There are risks to the mother and fetus associated with poorly controlled diabetes mellitus in pregnancy [see Clinical Considerations ].
No evidence of harm to the fetus was observed when doses up to 500 times the maximum recommended human dose of 20 mg of glyburide, based on body surface area, were administered to rats and rabbits in reproduction studies. No adverse developmental effects were observed when metformin was administered to pregnant Sprague Dawley rats and rabbits during the period of organogenesis at doses up to 3- and 6- times, respectively, a 2000 mg clinical dose, based on body surface area [see Data ]. The estimated background risk of major birth defects is 6 to 10% in women with pre-gestational diabetes mellitus with an HbA1c >7 and has been reported to be as high as 20 to 25% in women with a HbA1c >10.
The estimated background risk of miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Poorly controlled diabetes mellitus in pregnancy increases the maternal risk for diabetic ketoacidosis, pre-eclampsia, spontaneous abortions, preterm delivery, and delivery complications.
Poorly controlled diabetes mellitus increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity. Fetal/Neonatal Adverse Reactions Neonates of women with gestational diabetes who are treated with sulfonylureas during pregnancy may be at increased risk for neonatal intensive care admission and may develop respiratory distress, hypoglycemia, birth injury, and be large for gestational age. Prolonged severe hypoglycemia, lasting 4 to 10 days, has been reported in neonates born to mothers receiving a sulfonylurea at the time of delivery and has been reported with the use of agents with a prolonged half-life.
Observe newborns for symptoms of hypoglycemia and respiratory distress and manage accordingly. Dose adjustments during pregnancy and the postpartum period Due to reports of prolonged severe hypoglycemia in neonates born to mothers receiving a sulfonylurea at the time of delivery, glyburide and metformin hydrochloride should be discontinued at least two weeks before expected delivery [see Fetal/Neonatal Adverse Reactions ]. Data Human Data Published data from post-marketing studies have not reported a clear association with metformin and major birth defects, miscarriage, or adverse maternal or fetal outcomes when metformin was used during pregnancy.
However, these studies cannot definitely establish the ab… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from a small number of published studies and postmarketing experience with glyburide use in pregnancy over decades have not identified any drug associated risks for major birth defects, miscarriage, or adverse maternal outcomes. However, sulfonylureas (including glyburide) cross the placenta and have been associated with neonatal adverse reactions such as hypoglycemia. Therefore, glyburide and metformin hydrochloride should be discontinued at least two weeks before expected delivery [see Clinical Considerations ].
Limited data with metformin in pregnant women are not sufficient to determine a drug-associated risk for major birth defects or miscarriage. Published studies with metformin use during pregnancy have not reported a clear association with metformin and major birth defect or miscarriage risk [see Data ]. There are risks to the mother and fetus associated with poorly controlled diabetes mellitus in pregnancy [see Clinical Considerations ].
No evidence of harm to the fetus was observed when doses up to 500 times the maximum recommended human dose of 20 mg of glyburide, based on body surface area, were administered to rats and rabbits in reproduction studies. No adverse developmental effects were observed when metformin was administered to pregnant Sprague Dawley rats and rabbits during the period of organogenesis at doses up to 3- and 6- times, respectively, a 2000 mg clinical dose, based on body surface area [see Data ]. The estimated background risk of major birth defects is 6 to 10% in women with pre-gestational diabetes mellitus with an HbA1c >7 and has been reported to be as high as 20 to 25% in women with a HbA1c >10.
The estimated background risk of miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Poorly controlled diabetes mellitus in pregnancy increases the maternal risk for diabetic ketoacidosis, pre-eclampsia, spontaneous abortions, preterm delivery, and delivery complications.
Poorly controlled diabetes mellitus increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity. Fetal/Neonatal Adverse Reactions Neonates of women with gestational diabetes who are treated with sulfonylureas during pregnancy may be at increased risk for neonatal intensive care admission and may develop respiratory distress, hypoglycemia, birth injury, and be large for gestational age. Prolonged severe hypoglycemia, lasting 4 to 10 days, has been reported in neonates born to mothers receiving a sulfonylurea at the time of delivery and has been reported with the use of agents with a prolonged half-life.
Observe newborns for symptoms of hypoglycemia and respiratory distress and manage accordingly. Dose adjustments during pregnancy and the postpartum period Due to reports of prolonged severe hypoglycemia in neonates born to mothers receiving a sulfonylurea at the time of delivery, glyburide and metformin hydrochloride should be discontinued at least two weeks before expected delivery [see Fetal/Neonatal Adverse Reactions ]. Data Human Data Published data from post-marketing studies have not reported a clear association with metformin and major birth defects, miscarriage, or adverse maternal or fetal outcomes when metformin was used during pregnancy.
However, these studies cannot definitely establish the absence of any metformin-associated risk because of methodological limitations, including small sample size and inconsistent comparator groups. Animal Data Reproduction studies were performed in rats and rabbits at doses up to 500 times the maximum recommended human dose of 20 mg of glyburide based on body surface area comparisons and revealed no evidence of harm to the fetus. Metformin did not adversely affect… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of glyburide and metformin hydrochloride have not been established in pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 642 patients who received glyburide and metformin hydrochloride in double-blind clinical studies, 23.8% were 65 and older while 2.8% were 75 and older. No overall differences in effectiveness or safety were observed between these patients and younger patients, but greater sensitivity of some older individuals cannot be ruled out. Elderly patients are particularly susceptible to the hypoglycemic action of anti-diabetic agents.
Hypoglycemia may be difficult to recognize in these patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy and the higher risk of hypoglycemia and lactic acidosis. Assess renal function more frequently in elderly patients [see Dosage and Administration (2) and Warnings and Precautions (5.1) ].
🆘 Overdosage ▾
10 OVERDOSAGE Glyburide Overdosage of sulfonylureas, including glyburide tablets, can produce hypoglycemia. Mild hypoglycemic symptoms, without loss of consciousness or neurological findings, should be treated with oral glucose. Severe hypoglycemic reactions with coma, seizure, or other neurological impairment are medical emergencies requiring immediate treatment.
The patient should be treated with glucagon or intravenous glucose. Patients should be closely monitored for a minimum of 24 to 48 hours since hypoglycemia may recur after apparent clinical recovery. Clearance of glyburide from plasma may be prolonged in persons with liver disease.
Because of the extensive protein binding of glyburide, dialysis is unlikely to be of benefit. Metformin Overdose of metformin has occurred, including ingestion of amounts greater than 50 g. Hypoglycemia was reported in approximately 10% of cases, but no causal association with metformin has been established.
Lactic acidosis has been reported in approximately 32% of metformin overdose cases [see Warnings and Precautions (5.1) ]. Metformin is dialyzable with a clearance of up to 170 mL/min under good hemodynamic conditions. Therefore, hemodialysis may be useful for removal of accumulated drug from patients in whom metformin overdosage is suspected.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Glyburide primarily lowers blood glucose by stimulating the release of insulin from the pancreas, an effect dependent upon functioning beta cells in the pancreatic islets. Sulfonylureas bind to the sulfonylurea receptor in the pancreatic beta-cell plasma membrane, leading to closure of the ATP-sensitive potassium channel, thereby stimulating the release of insulin. Metformin is an antihyperglycemic agent that improves glucose tolerance in patients with type 2 diabetes, lowering both basal and postprandial plasma glucose.
Metformin decreases hepatic glucose production, decreases intestinal absorption of glucose, and improves insulin sensitivity by increasing peripheral glucose uptake and utilization. With metformin therapy, insulin secretion remains unchanged while fasting insulin levels and daylong plasma insulin response may decrease.
12.3Pharmacokinetics Absorption Glyburide and Metformin Hydrochloride In bioavailability studies of glyburide and metformin hydrochloride 2.5 mg/500 mg and 5 mg/500 mg, the mean area under the plasma concentration versus time curve (AUC) for the glyburide component was 18% and 7%, respectively, greater than that of standard particle-size glyburide coadministered with metformin. The pharmacokinetics of metformin HCl component of glyburide and metformin hydrochloride was consistent with that of metformin HCl coadministered with glyburide.
Effect of food: Following administration of a single glyburide and metformin hydrochloride 5 mg/500 mg tablet with either a 20% glucose solution or a 20% glucose solution with food, there was no effect of food on the C max and a relatively small effect of food on the AUC of the glyburide component. The T max for the glyburide component was shortened from 7.5 hours to 2.75 hours with food compared to the same tablet strength administered fasting with a 20% glucose solution. The effect of food on the pharmacokinetics of the metformin component of glyburide and metformin hydrochloride was indeterminate.
However, food is known to decrease the extent of and slightly delay the absorption of metformin, as shown by approximately a 40% lower mean peak plasma concentration (C max ), a 25% lower area under the plasma concentration versus time curve (AUC), and a 35-minute prolongation of time to peak plasma concentration (T max ) following administration of a single 850 mg tablet of metformin with food, compared to the same tablet strength administered fasting. The clinical relevance of these decreases is unknown. Glyburide Single-dose studies with standard particle-size glyburide tablets in normal subjects demonstrate significant absorption of glyburide within 1 hour, peak drug levels at about 4 hours, and low but detectable levels at 24 hours.
Mean serum levels of glyburide, as reflected by areas under the serum concentration-time curve, increase in proportion to corresponding increases in dose. Bioequivalence has not been established between glyburide and metformin hydrochloride and single-ingredient standard particle-size glyburide products. Metformin The absolute bioavailability of a 500 mg metformin tablet given under fasting conditions is approximately 50% to 60%.
Studies using single oral doses of metformin tablets of 500 mg and 1500 mg, and 850 mg to 2550 mg, indicate that there is a lack of dose proportionality with increasing doses, which is due to decreased absorption rather than an alteration in elimination. At usual clinical doses and dosing schedules of metformin, steady-state plasma concentrations of metformin are reached within 24 to 48 hours and are generally <1 mcg/mL. Distribution Glyburide Sulfonylurea drugs are extensively bound to serum proteins.
Displacement from protein binding sites by other drugs may lead to enhanced hypoglycemic action. In vitro , the protein binding exhibited by glyburide is predominantly non-ionic, whereas that of other sulfonylureas (chlorpropamide, tolbutamide, tolazamide) is… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Glyburide primarily lowers blood glucose by stimulating the release of insulin from the pancreas, an effect dependent upon functioning beta cells in the pancreatic islets. Sulfonylureas bind to the sulfonylurea receptor in the pancreatic beta-cell plasma membrane, leading to closure of the ATP-sensitive potassium channel, thereby stimulating the release of insulin. Metformin is an antihyperglycemic agent that improves glucose tolerance in patients with type 2 diabetes, lowering both basal and postprandial plasma glucose.
Metformin decreases hepatic glucose production, decreases intestinal absorption of glucose, and improves insulin sensitivity by increasing peripheral glucose uptake and utilization. With metformin therapy, insulin secretion remains unchanged while fasting insulin levels and daylong plasma insulin response may decrease.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Glyburide and Metformin Hydrochloride Tablets USP, 1.25 mg/250 mg: Yellow, capsule shaped, biconvex, film-coated tablet with ‘A’ debossed on one side and ‘46’ on the other side. Bottles of 30 NDC 65862-080-30 Bottles of 100 NDC 65862-080-01 Bottles of 500 NDC 65862-080-05 Glyburide and Metformin Hydrochloride Tablets USP, 2.5 mg/500 mg: Light pink, capsule shaped, biconvex, film-coated tablet with ‘A’ debossed on one side and ‘47’ on the other side. Bottles of 30 NDC 65862-081-30 Bottles of 100 NDC 65862-081-01 Bottles of 500 NDC 65862-081-05 Glyburide and Metformin Hydrochloride Tablets USP, 5 mg/500 mg: Yellow, capsule shaped, biconvex, film-coated tablet with ‘A’ debossed on one side and ‘48’ on the other side.
Bottles of 30 NDC 65862-082-30 Bottles of 100 NDC 65862-082-01 Bottles of 500 NDC 65862-082-05 Store at 20° to 25°C (68º to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Dispense in light-resistant containers.
📋 Description ▾
11 DESCRIPTION Glyburide and metformin hydrochloride tablets, USP for oral use contain glyburide USP and metformin hydrochloride USP. Glyburide USP is a sulfonylurea and its chemical name is 1-[[p-[2-(5-chloro- o -anisamido) ethyl]phenyl]sulfonyl]-3-cyclo-hexylurea. Glyburide USP is a white to off-white crystalline compound with molecular formula of C 23 H 28 ClN 3 O 5 S and a molecular weight of 494.01.
The structural formula is represented below. Metformin hydrochloride USP is a biguanide in hydrochloride salt form and its chemical name is N,N-dimethylimidodicarbonimidic diamide monohydrochloride. It is a white to off-white crystalline compound with molecular formula of C 4 H 12 ClN 5 (monohydrochloride) and a molecular weight of 165.63.
Metformin is freely soluble in water and is practically insoluble in acetone, ether, and chloroform. The pKa of metformin is 12.4. The pH of a 1% aqueous solution of metformin is 6.68.
The structural formula is as shown: Glyburide and metformin hydrochloride tablets, USP are available in film-coated containing 1.25 mg glyburide USP with 250 mg metformin hydrochloride USP, 2.5 mg glyburide USP with 500 mg metformin hydrochloride USP, and 5 mg glyburide USP with 500 mg metformin hydrochloride USP. In addition, each film-coated tablet contains the following inactive ingredients: microcrystalline cellulose, croscarmellose sodium, povidone, magnesium stearate, hypromellose, propylene glycol, polysorbate 80, talc, titanium dioxide and FD&C Yellow#6 aluminum lake.
The 1.25 mg/250 mg and 5 mg/500 mg strengths also contain D&C Yellow#10 aluminum lake; The 2.5 mg/500 mg strength also contains FD&C Red#40 aluminum lake. Meets USP Dissolution Test 2 Glyburide Chemical Structure Metformin Hydrochloride Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Lactic Acidosis: Explain the risks of lactic acidosis, its symptoms, and conditions that predispose to its development. Advise patients to discontinue glyburide and metformin hydrochloride immediately and to promptly notify their healthcare provider practitioner if unexplained hyperventilation, myalgia, malaise, unusual somnolence, or other nonspecific symptoms occur.
Counsel patients against excessive alcohol intake and inform patients about importance of regular testing of renal function while receiving glyburide and metformin hydrochloride. Instruct patients to inform their doctor that they are taking glyburide and metformin hydrochloride prior to any surgical or radiological procedure, as temporary discontinuation may be required [see Warnings and Precautions (5.1) ]. Hypoglycemia: Inform patients that hypoglycemia may occur when taking glyburide and metformin hydrochloride.
Explain to patients the risks of hypoglycemia, its symptoms and treatment, and conditions that predispose to its development [see Warnings and Precautions (5.2) ]. Cardiovascular Mortality: Inform patients that the administration of oral hypoglycemic drugs has been reported to be associated with increased cardiovascular mortality as compared to treatment with diet alone or diet plus insulin. Inform patients of the potential risks and benefits of glyburide and of alternative modes of therapy [see Warnings and Precautions (5.3) ].
Vitamin B 12 Deficiency: Inform patients about importance of regular hematological testing while receiving glyburide and metformin hydrochloride [see Warnings and Precautions (5.5) ]. Females of Reproductive Age: Inform females that treatment with glyburide and metformin hydrochloride may result in ovulation in some premenopausal anovulatory women which may lead to unintended pregnancy [see Use in Specific Populations (8.3) ]. Distributed by: Aurobindo Pharma USA, Inc.
279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 032, India Trademarks are the property of their respective owners. Revised: 06/2026
🍼 Nursing Mothers ▾
8.3Females and Males of Reproductive Potential Discuss the potential for unintended pregnancy with premenopausal women as therapy with glyburide and metformin hydrochloride may result in ovulation in some anovulatory women.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption Glyburide and Metformin Hydrochloride In bioavailability studies of glyburide and metformin hydrochloride 2.5 mg/500 mg and 5 mg/500 mg, the mean area under the plasma concentration versus time curve (AUC) for the glyburide component was 18% and 7%, respectively, greater than that of standard particle-size glyburide coadministered with metformin. The pharmacokinetics of metformin HCl component of glyburide and metformin hydrochloride was consistent with that of metformin HCl coadministered with glyburide.
Effect of food: Following administration of a single glyburide and metformin hydrochloride 5 mg/500 mg tablet with either a 20% glucose solution or a 20% glucose solution with food, there was no effect of food on the C max and a relatively small effect of food on the AUC of the glyburide component. The T max for the glyburide component was shortened from 7.5 hours to 2.75 hours with food compared to the same tablet strength administered fasting with a 20% glucose solution. The effect of food on the pharmacokinetics of the metformin component of glyburide and metformin hydrochloride was indeterminate.
However, food is known to decrease the extent of and slightly delay the absorption of metformin, as shown by approximately a 40% lower mean peak plasma concentration (C max ), a 25% lower area under the plasma concentration versus time curve (AUC), and a 35-minute prolongation of time to peak plasma concentration (T max ) following administration of a single 850 mg tablet of metformin with food, compared to the same tablet strength administered fasting. The clinical relevance of these decreases is unknown. Glyburide Single-dose studies with standard particle-size glyburide tablets in normal subjects demonstrate significant absorption of glyburide within 1 hour, peak drug levels at about 4 hours, and low but detectable levels at 24 hours.
Mean serum levels of glyburide, as reflected by areas under the serum concentration-time curve, increase in proportion to corresponding increases in dose. Bioequivalence has not been established between glyburide and metformin hydrochloride and single-ingredient standard particle-size glyburide products. Metformin The absolute bioavailability of a 500 mg metformin tablet given under fasting conditions is approximately 50% to 60%.
Studies using single oral doses of metformin tablets of 500 mg and 1500 mg, and 850 mg to 2550 mg, indicate that there is a lack of dose proportionality with increasing doses, which is due to decreased absorption rather than an alteration in elimination. At usual clinical doses and dosing schedules of metformin, steady-state plasma concentrations of metformin are reached within 24 to 48 hours and are generally <1 mcg/mL. Distribution Glyburide Sulfonylurea drugs are extensively bound to serum proteins.
Displacement from protein binding sites by other drugs may lead to enhanced hypoglycemic action. In vitro , the protein binding exhibited by glyburide is predominantly non-ionic, whereas that of other sulfonylureas (chlorpropamide, tolbutamide, tolazamide) is predominantly ionic. Acidic drugs, such as phenylbutazone, warfarin, and salicylates, displace the ionic-binding sulfonylureas from serum proteins to a far greater extent than the non-ionic binding glyburide.
It has not been shown that this difference in protein binding results in fewer drug-drug interactions with glyburide tablets in clinical use. Metformin The apparent volume of distribution (V/F) of metformin following single oral doses of 850 mg averaged 654±358 L. Metformin is negligibly bound to plasma proteins.
Metformin partitions into erythrocytes, most likely as a function of time. Metabolism and Elimination Glyburide The decrease of glyburide in the serum of normal healthy individuals is biphasic; the terminal half-life is about 10 hours. The major metabolite of glyburide is the 4-trans-hydroxy derivative.
A second metabolite, the 3-cis-hydroxy derivative, also occurs. These… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Patients with Inadequate Glycemic Control on Diet and Exercise Alone In a 20-week, double-blind, placebo-controlled, multicenter U.S. clinical study, involving 806 drug-naive patients with type 2 diabetes, whose hyperglycemia was not adequately controlled with dietary management alone (baseline fasting plasma glucose [FPG] below 240 mg/dL, baseline hemoglobin A 1c [HbA1c] between 7% and 11%), were randomized to receive initial therapy with placebo, 2.5 mg glyburide, 500 mg metformin HCl, glyburide and metformin hydrochloride 1.25 mg/250 mg, or glyburide and metformin hydrochloride 2.5 mg/500 mg.
After 4 weeks, the dose was progressively increased to a maximum of 4 tablets daily as needed to reach a target FPG of 126 mg/dL. Study data at 20 weeks are summarized in Table 5. Table 5: Mean Change in Hemoglobin A1c and Fasting Plasma Glucose in Patients Receiving Placebo, Glyburide, Metformin HCl or Glyburide and Metformin Hydrochloride at 20 Weeks a p<0.001 b p<0.05 c p=NS Placebo Glyburide 2.5 mg tablets Metformin HCl 500 mg tablets Glyburide and Metformin Hydrochloride 1.25 mg/250 mg tablets Glyburide and Metformin Hydrochloride 2.5 mg/500 mg tablets Mean Final Dose 0 mg 5.3 mg 1317 mg 2.78 mg/557 mg 4.1 mg/824 mg Hemoglobin A 1c N=147 N=142 N=141 N=149 N=152 Baseline Mean (%) 8.14 8.14 8.23 8.22
8.20Mean Change from Baseline −0.21 −1.24 −1.03 −1.48 −1.53 Difference from Placebo −1.02 −0.82 −1.26 a −1.31 a Difference from Glyburide −0.24 b −0.29 b Difference from Metformin −0.44 b −0.49 b Fasting Plasma Glucose N=159 N=158 N=156 N=153 N=154 Baseline Mean FPG (mg/dL) 177.2 178.9 175.1 178 176.6 Mean Change from Baseline 4.6 −35.7 −21.2 −41.5 −40.1 Difference from Placebo −40.3 −25.8 −46.1 a −44.7 a Difference from Glyburide −5.8 c −4.5 c Difference from Metformin −20.3 c −18.9 c Final HbA1c Distribution (%) N=147 N=142 N=141 N=149 N=152 <7% 19.7% 59.9% 50.4% 66.4% 71.7% ≥7% and <8% 37.4% 26.1% 29.8% 25.5% 19.1% ≥8% 42.9% 14.1% 19.9% 8.1% 9.2% Mean baseline body weight was 87 kg, 87 kg, 89 kg, 89 kg and 87 kg in the placebo, glyburide 2.5mg, metformin 500mg, glyburide and metformin hydrochloride 1.25mg/250mg and 2.5mg/500mg arms, respectively.
Mean change in body weight from baseline to week 20 was -0.7 kg, +1.7 kg, -0.6 kg, +1.4 kg and +1.9 in the placebo, glyburide, metformin, glyburide and metformin hydrochloride 1.25mg/250mg and 2.5mg/500mg arms, respectively. Patients with Inadequate Glycemic Control on Sulfonylurea Alone In a 16-week, double-blind, active-controlled U.S. clinical study, a total of 639 patients with type 2 diabetes not adequately controlled (mean baseline HbA1c 9.5%, mean baseline FPG 213 mg/dL) while being treated with at least one-half the maximum dose of a sulfonylurea (e.g., glyburide 10 mg, glipizide 20 mg) were randomized to receive glyburide (fixed dose, 20 mg), metformin HCl (500 mg), glyburide and metformin hydrochloride 2.5 mg/500 mg, or glyburide and metformin hydrochloride 5 mg/500 mg.
The doses of metformin HCl and glyburide and metformin hydrochloride were titrated to a maximum of 4 tablets daily as needed to achieve FPG <140 mg/dL. Study data at 16 weeks are summarized in Table 6. Table 6: Mean Change in Hemoglobin A1c and Fasting Plasma Glucose in Patients Receiving Glyburide, Metformin HCl or Glyburide and Metformin Hydrochloride at 16 Weeks a p<0.001 Glyburide 5 mg tablets Metformin HCl 500 mg tablets Glyburide and Metformin Hydrochloride 2.5 mg/500 mg tablets Glyburide and Metformin Hydrochloride 5 mg/500 mg tablets Mean Final Dose 20 mg 1840 mg 8.8 mg/1760 mg 17 mg/1740 mg Hemoglobin A 1c N=158 N=142 N=154 N=159 Baseline Mean (%) 9.63 9.51 9.43
9.44Final Mean 9.61 9.82 7.92
7.91Difference from Glyburide −1.69 a −1.70 a Difference from Metformin −1.90 a −1.91 a Fasting Plasma Glucose N=163 N=152 N=160 N=160 Baseline Mean (mg/dL) 218.4 213.4 212.2 210.2 Final Mean 221.0 233.8 169.6 161.1 Difference from Glyburide −51.3 a −59.9 a Difference from Metformin −64.2 a −72.7… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No animal studies have been conducted with the combined products in glyburide and metformin hydrochloride. The following data are based on findings in studies performed with the individual products. Glyburide Studies in rats with glyburide alone at doses up to 300 mg/kg/day (approximately 145 times the maximum recommended human daily dose of 20 mg for the glyburide component of glyburide and metformin hydrochloride based on body surface area comparisons) for 18 months revealed no carcinogenic effects.
In a 2-year oncogenicity study of glyburide in mice, there was no evidence of treatment-related tumors. There was no evidence of mutagenic potential of glyburide alone in the following in vitro tests: Salmonella microsome test (Ames test) and in the DNA damage/alkaline elution assay. No evidence of impaired fertility was observed when doses up to 500 times the maximum recommended human dose of 20 mg of glyburide, based on body surface area comparisons, were administered to rats in reproduction studies.
Metformin Long-term carcinogenicity studies have been performed in rats (dosing duration of 104 weeks) and mice (dosing duration of 91 weeks) at doses up to and including 900 mg/kg/day and 1500 mg/kg/day, respectively. These doses are both approximately 4 times the maximum recommendation human daily dose of 2000 mg on body surface area comparisons. No evidence of carcinogenicity with metformin was found in either male or female mice.
Similarly, there was no tumorigenic potential observed with metformin in male rats. There was, however, an increased incidence of benign stromal uterine polyps in female rats treated with 900 mg/kg/day. There was no evidence of a mutagenic potential of metformin in the following in vitro tests: Ames test ( S. typhimurium ), gene mutation test (mouse lymphoma cells), or chromosomal aberrations test (human lymphocytes).
Results in the in vivo mouse micronucleus test were also negative. Fertility of male or female rats was unaffected by metformin when administered at doses as high as 600 mg/kg/day, which is approximately 3 times the maximum recommended human daily dose of 2000 mg based on body surface area comparisons.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No animal studies have been conducted with the combined products in glyburide and metformin hydrochloride. The following data are based on findings in studies performed with the individual products. Glyburide Studies in rats with glyburide alone at doses up to 300 mg/kg/day (approximately 145 times the maximum recommended human daily dose of 20 mg for the glyburide component of glyburide and metformin hydrochloride based on body surface area comparisons) for 18 months revealed no carcinogenic effects.
In a 2-year oncogenicity study of glyburide in mice, there was no evidence of treatment-related tumors. There was no evidence of mutagenic potential of glyburide alone in the following in vitro tests: Salmonella microsome test (Ames test) and in the DNA damage/alkaline elution assay. No evidence of impaired fertility was observed when doses up to 500 times the maximum recommended human dose of 20 mg of glyburide, based on body surface area comparisons, were administered to rats in reproduction studies.
Metformin Long-term carcinogenicity studies have been performed in rats (dosing duration of 104 weeks) and mice (dosing duration of 91 weeks) at doses up to and including 900 mg/kg/day and 1500 mg/kg/day, respectively. These doses are both approximately 4 times the maximum recommendation human daily dose of 2000 mg on body surface area comparisons. No evidence of carcinogenicity with metformin was found in either male or female mice.
Similarly, there was no tumorigenic potential observed with metformin in male rats. There was, however, an increased incidence of benign stromal uterine polyps in female rats treated with 900 mg/kg/day. There was no evidence of a mutagenic potential of metformin in the following in vitro tests: Ames test ( S. typhimurium ), gene mutation test (mouse lymphoma cells), or chromosomal aberrations test (human lymphocytes).
Results in the in vivo mouse micronucleus test were also negative. Fertility of male or female rats was unaffected by metformin when administered at doses as high as 600 mg/kg/day, which is approximately 3 times the maximum recommended human daily dose of 2000 mg based on body surface area comparisons.
📄 Patient Package Insert ▾
PATIENT INFORMATION Glyburide and Metformin Hydrochloride (glye’ bure ide and met for’ min hye” droe klor’ ide) Tablets USP, for oral use What is the most important information I should know about glyburide and metformin hydrochloride tablets? Glyburide and metformin hydrochloride tablets can cause serious side effects, including: Lactic Acidosis. Metformin hydrochloride, a medicine in glyburide and metformin hydrochloride tablets, can cause a rare, but serious, side effect called lactic acidosis (a build-up of lactic acid in the blood) that can cause death.
Lactic acidosis is a medical emergency and must be treated in a hospital. Stop taking glyburide and metformin hydrochloride tablets and call your healthcare provider right away if you get any of the following symptoms of lactic acidosis: feel very weak and tired have unusual sleepiness or sleep longer than usual have unusual (not normal) muscle pain feel cold, especially in your arms and legs have trouble breathing feel dizzy or lightheaded have unexplained stomach or intestinal problems with nausea and vomiting, or diarrhea have a slow or irregular heartbeat You have a higher chance of getting lactic acidosis if you: have severe kidney problems. “See “Do not take glyburide and metformin hydrochloride tablets if you:” have liver problems. drink a lot of alcohol (very often or short-term “binge” drinking). get dehydrated (lose a large amount of body fluids).
This can happen if you are sick with a fever, vomiting, or diarrhea. Dehydration can also happen when you sweat a lot with activity or exercise and do not drink enough fluids. have certain x-ray tests with injectable dyes or contrast agents. have surgery or other procedures for which you need to restrict the amount of food and liquid you eat and drink. have congestive heart failure. have a heart attack, severe infection, or stroke. are 65 years of age or older. have a genetically inherited disease affecting mitochondria (the energy-producing parts within cells) such as mitochondrial encephalomyopathy with lactic acidosis, and stroke-like episodes (MELAS) syndrome and maternally inherited diabetes and deafness (MIDD).
Tell your healthcare provider if you have any of the problems in the list above. Tell your healthcare provider that you are taking glyburide and metformin hydrochloride tablets before you have surgery or x-ray tests. Your healthcare provider may need to stop glyburide and metformin hydrochloride tablets for a while if you have surgery or certain x-ray tests.
Glyburide and metformin hydrochloride tablets can have other serious side effects. See “What are the possible side effects of glyburide and metformin hydrochloride tablets?” What is glyburide and metformin hydrochloride tablets? Glyburide and metformin hydrochloride tablets are a prescription medicine that contains glyburide (sulfonylurea) and metformin hydrochloride.
Glyburide and metformin hydrochloride tablets is used with diet and exercise to help control high blood sugar (hyperglycemia) in adults with type 2 diabetes. It is not known if glyburide and metformin hydrochloride tablets are safe and effective in children under 18 years of age. Do not take glyburide and metformin hydrochloride tablets if you: have severe kidney problems. are allergic to metformin hydrochloride, glyburide or any of the ingredients in glyburide and metformin hydrochloride tablets.
See the end of this Patient Information leaflet for a complete list of ingredients in glyburide and metformin hydrochloride tablets. have a condition called metabolic acidosis, including diabetic ketoacidosis (high levels of certain acids called “ketones” in your blood or urine). take bosentan. Before taking glyburide and metformin hydrochloride tablets tell your healthcare provider about all medical conditions, including if you: have a history or risk for diabetic ketoacidosis. See “Do not take glyburide and metformin hydrochloride tablets if you: ” have kidney problems. have liver problems. hav… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Boxed Warning 03/2026
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 1.25 mg/250 mg (100 Tablets Bottle) NDC 65862-080-01 Rx only Glyburide and Metformin Hydrochloride Tablets, USP 1.25 mg/250 mg AUROBINDO 100 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 1.25 mg/250 mg (100 Tablets Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 2.5 mg/500 mg (100 Tablets Bottle) NDC 65862-081-01 Rx only Glyburide and Metformin Hydrochloride Tablets, USP 2.5 mg/500 mg AUROBINDO 100 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 2.5 mg/500 mg (100 Tablets Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 5 mg/500 mg (100 Tablets Bottle) NDC 65862-082-01 Rx only Glyburide and Metformin Hydrochloride Tablets, USP 5 mg/500 mg AUROBINDO 100 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 5 mg/500 mg (100 Tablets Bottle)