
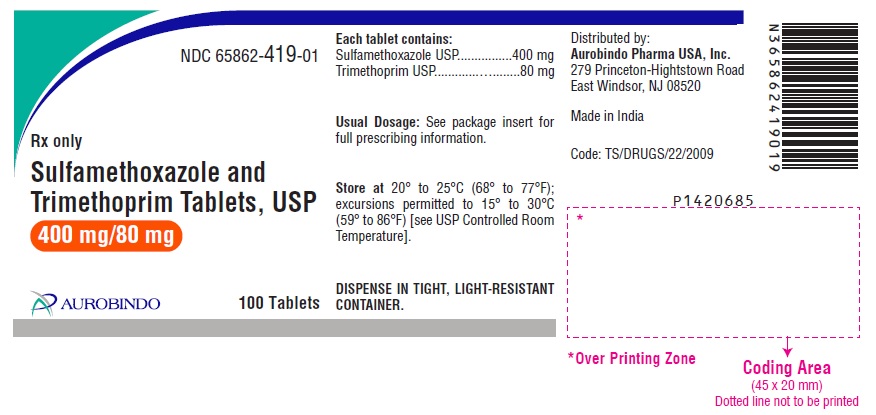
Sulfamethoxazole and Trimethoprim 400 mg; 80 mg Tablet, 20-count
Other active recalls for Sulfamethoxazole And Trimethoprim (different manufacturers) — 5 · tap to view
Past resolved recalls for this product (1)
🆔 Identity & classification
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- The IV form is used when your infection is serious enough that you need the medication working quickly and reliably, or when you're not able to take pills by mouth right now. Once...
- Why am I getting this antibiotic through an IV instead of just taking a pill?
- The most common things people notice are nausea, vomiting, and skin rashes — those are uncomfortable but not usually dangerous on their own. What you want to report right away is a...
- What side effects should I actually expect, and which ones should make me call someone?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII F05Q2T2JA0
Docusate sodium is a stool softener compound that helps medicines dissolve and move through the digestive tract. It acts as a surfactant, reducing surface tension in the intestines, and also serves as a wetting agent in tablet formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OJ245FE5EU
Sodium benzoate is a salt derived from benzoic acid, a preservative. It's added to medicines to prevent growth of bacteria, fungi, and other microorganisms that could spoil the product.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1395 | $2.79 / 20 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Sulfamethoxazole and Trimethoprim 400 mg/1; 80 mg 50268-0728-15 | AvPAK | 50 tablets | $0.040 | AB | Availability likely | — |
| Sulfamethoxazole and Trimethoprim 400 mg/1; 80 mg 57237-0232-01 | Rising | 100 tablets | $0.040 | AB | Availability likely | — |
| Sulfamethoxazole and Trimethoprim 400 mg/1; 80 mg 62135-0897-18 | Chartwell | 180 tablets | $0.040 | AB | Availability likely | — |
| Sulfamethoxazole and Trimethoprim 400 mg/1; 80 mg 53489-0145-01 | Sun | 100 tablets | $0.046 | AB | FDA listed | — |
| Sulfamethoxazole and Trimethoprim 400 mg/1; 80 mg 42291-0758-01 | AvKARE | 100 tablets | — | AB | FDA listed | — |
| Bactrim 400 mg/1; 80 mg 49708-0145-01 | Sun | 100 tablets | — | AB | FDA listed | — |
| Sulfamethoxazole and Trimethoprim 400 mg/1; 80 mg 53746-0271-01 | Amneal | 100 tablets | — | AB | FDA listed | — |
| Sulfamethoxazole and Trimethoprim 400 mg/1; 80 mg 61971-0115-01 | Vista | 100 tablets | — | AB | FDA listed | — |
| Sulfamethoxazole and Trimethoprim 400 mg/1; 80 mg 65162-0271-05 | Amneal | 50 tablets | — | AB | FDA listed | — |
| Sulfamethoxazole and Trimethoprim 400 mg/1; 80 mgthis 65862-0419-20 | Aurobindo | 20 tablets | — | — | FDA listed | — |
| Sulfamethoxazole and Trimethoprim 400 mg/1; 80 mg 69043-0010-01 | Cronus | 100 tablets | — | AB | FDA listed | — |
| Sulfamethoxazole and Trimethoprim 400 mg/1; 80 mg 70518-3454-00 | REMEDYREPACK | 6 tablets | — | AB | Discontinued | — |
| Sulfamethoxazole and Trimethoprim 400 mg/1; 80 mg 68071-3579-01 | NuCare | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
💊 Medicaid utilization by pack size
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 65862-0419-01 | 100 TABLET in 1 BOTTLE (65862-419-01) | $0.0397 / ea | $3.97 | 2010-02-16 | Active |
| 65862-0419-05 | 500 TABLET in 1 BOTTLE (65862-419-05) | $0.0397 / ea | $19.87 | 2010-02-16 | Active |
| 65862-0419-20 You're viewing this | 20 TABLET in 1 BOTTLE (65862-419-20) | — | — | 2010-02-16 | Active |
| 65862-0419-99 | 1000 TABLET in 1 BOTTLE (65862-419-99) | — | — | 2010-02-16 | Active |
| 65862-0419-25 | 25000 TABLET in 1 BAG (65862-419-25) | — | — | — | Active |
| 65862-0419-39 | 3000 TABLET in 1 BAG (65862-419-39) | — | — | — | Active |
You're viewing the smallest of 6 pack sizes for this product.
This pack shows little to no recent Medicaid volume — the 100 tablets pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 65862-0419-20?
What is the difference between NDC 65862-0419-20 and NDC 65862-0419-01?
What NDC number is used to bill for this package of Sulfamethoxazole and Trimethoprim 400 mg; 80 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What "drug for further processing" means
FDA lists this package under the "drug for further processing" marketing category: Aurobindo Pharma Limited supplies it to other companies for further processing or repackaging (blister cards that are later repackaged or co-packaged are a common example). The units themselves are a finished dosage form — which is why pricing or Medicaid data can still appear — but this exact package code may not be the presentation a retail pharmacy dispenses.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Is this NDC FDA-approved?
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Where does this data come from?
📄 Full FDA label FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE To reduce the development of drug-resistant bacteria and maintain the effectiveness of sulfamethoxazole and trimethoprim tablets and other antibacterial drugs, sulfamethoxazole and trimethoprim tablets should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to empiric selection of therapy.
Urinary Tract Infections For the treatment of urinary tract infections due to susceptible strains of the following organisms: Escherichia coli, Klebsiella species, Enterobacter species, Morganella morganii, Proteus mirabilis and Proteus vulgaris. It is recommended that initial episodes of uncomplicated urinary tract infections be treated with a single effective antibacterial agent rather than the combination. Acute Otitis Media For the treatment of acute otitis media in pediatric patients due to susceptible strains of Streptococcus pneumoniae or Haemophilus influenzae when in the judgment of the physician sulfamethoxazole and trimethoprim offers some advantage over the use of other antimicrobial agents.
To date, there are limited data on the safety of repeated use of sulfamethoxazole and trimethoprim tablets in pediatric patients under two years of age. Sulfamethoxazole and trimethoprim tablets are not indicated for prophylactic or prolonged administration in otitis media at any age. Acute Exacerbations of Chronic Bronchitis in Adults For the treatment of acute exacerbations of chronic bronchitis due to susceptible strains of Streptococcus pneumoniae or Haemophilus influenzae when a physician deems that sulfamethoxazole and trimethoprim tablets could offer some advantage over the use of a single antimicrobial agent.
Shigellosis For the treatment of enteritis caused by susceptible strains of Shigella flexneri and Shigella sonnei when antibacterial therapy is indicated. Pneumocystis jirovecii Pneumonia For the treatment of documented Pneumocystis jirovecii pneumonia and for prophylaxis against P. jirovecii pneumonia in individuals who are immunosuppressed and considered to be at an increased risk of developing P. jirovecii pneumonia. Traveler's Diarrhea in Adults For the treatment of traveler's diarrhea due to susceptible strains of enterotoxigenic E. coli.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Sulfamethoxazole and trimethoprim tablets are contraindicated in pediatric patients less than 2 months of age. Urinary Tract Infections and Shigellosis in Adults and Pediatric Patients, and Acute Otitis Media in Children Adults: The usual adult dosage in the treatment of urinary tract infections is 1 sulfamethoxazole and trimethoprim DS (double strength) tablet or 2 sulfamethoxazole and trimethoprim tablets every 12 hours for 10 to 14 days. An identical daily dosage is used for 5 days in the treatment of shigellosis.
Children: The recommended dose for children with urinary tract infections or acute otitis media is 40 mg/kg sulfamethoxazole and 8 mg/kg trimethoprim per 24 hours, given in two divided doses every 12 hours for 10 days. An identical daily dosage is used for 5 days in the treatment of shigellosis. The following table is a guideline for the attainment of this dosage: Children 2 months of age or older: Weight Dose–every 12 hours lb kg Tablets 22 10 – 44 20 1 66 30 1½ 88 40 2 or 1 DS tablet For Patients with Impaired Renal Function When renal function is impaired, a reduced dosage should be employed using the following table: Creatinine Clearance (mL/min) Recommended Dosage Regimen Above 30 Usual standard regimen 15–30 ½ the usual regimen Below 15 Use not recommended Acute Exacerbations of Chronic Bronchitis in Adults The usual adult dosage in the treatment of acute exacerbations of chronic bronchitis is 1 sulfamethoxazole and trimethoprim DS (double strength) tablet or 2 sulfamethoxazole and trimethoprim tablets every 12 hours for 14 days.
Pneumocystis jirovecii Pneumonia Treatment Adults and Children: The recommended dosage for treatment of patients with documented Pneumocystis jirovecii pneumonia is 75 to 100 mg/kg sulfamethoxazole and 15 to 20 mg/kg trimethoprim per 24 hours given in equally divided doses every 6 hours for 14 to 21 days. 12 The following table is a guideline for the upper limit of this dosage: Weight Dose-every 6 hours lb kg Tablets 18 8 – 35 16 1 53 24 1½ 70 32 2 or 1 DS tablet 88 40 2½ 106 48 3 or 1½ DS tablets 141 64 4 or 2 DS tablets 176 80 5 or 2½ DS tablets For the lower limit dose (75 mg/kg sulfamethoxazole and 15 mg/kg trimethoprim per 24 hours) administer 75% of the dose in the above table.
Prophylaxis Adults: The recommended dosage for prophylaxis in adults is 1 sulfamethoxazole and trimethoprim DS (double strength) tablet daily. 13 Children: For children, the recommended dose is 750 mg/m 2 /day sulfamethoxazole with 150 mg/m 2 /day trimethoprim given orally in equally divided doses twice a day, on 3 consecutive days per week. The total daily dose should not exceed 1600 mg sulfamethoxazole and 320 mg trimethoprim.
14 The following table is a guideline for the attainment of this dosage in children: Body Surface Area Dose-every 12 hours (m 2 ) Tablets 0.26 – 0.53 ½ 1.06 1 Traveler's Diarrhea in Adults For the treatment of traveler’s diarrhea, the usual adult dosage is 1 sulfamethoxazole and trimethoprim DS (double strength) tablet or 2 sulfamethoxazole and trimethoprim tablets every 12 hours for 5 days.
⛔ Contraindications ▾
CONTRAINDICATIONS Sulfamethoxazole and trimethoprim tablets are contraindicated in the following situations: known hypersensitivity to trimethoprim or sulfonamides history of drug-induced immune thrombocytopenia with use of trimethoprim and/or sulfonamides documented megaloblastic anemia due to folate deficiency pediatric patients less than 2 months of age marked hepatic damage severe renal insufficiency when renal function status cannot be monitored concomitant administration with dofetilide (see PRECAUTIONS ).
⚠️ Warnings ▾
WARNINGS Embryofetal Toxicity Some epidemiologic studies suggest that exposure to sulfamethoxazole and trimethoprim during pregnancy may be associated with an increased risk of congenital malformations, particularly neural tube defects, cardiovascular malformations, urinary tract defects, oral clefts, and club foot. If sulfamethoxazole and trimethoprim is used during pregnancy, or if the patient becomes pregnant while taking this drug, the patient should be advised of the potential hazards to the fetus (see PRECAUTIONS ).
Hypersensitivity and Other Serious or Fatal Reactions Fatalities and serious adverse reactions including severe cutaneous adverse reactions (SCARs) including Stevens-Johnson syndrome, toxic epidermal necrolysis, drug reaction with eosinophilia and systemic symptoms (DRESS), acute febrile neutrophilic dermatosis (AFND), acute generalized erythematous pustulosis (AGEP); fulminant hepatic necrosis; agranulocytosis, aplastic anemia and other blood dyscrasias; acute and delayed lung injury; anaphylaxis and circulatory shock have occurred with the administration of sulfamethoxazole and trimethoprim products, including sulfamethoxazole and trimethoprim (see ADVERSE REACTIONS ).
Hypersensitivity Reactions of the Respiratory Tract Cough, shortness of breath and pulmonary infiltrates potentially representing hypersensitivity reactions of the respiratory tract have been reported in association with sulfamethoxazole and trimethoprim treatment. Respiratory Failure Other severe pulmonary adverse reactions occurring within days to week of sulfamethoxazole and trimethoprim initiation and resulting in prolonged respiratory failure requiring mechanical ventilation or extracorporeal membrane oxygenation (ECMO), lung transplantation or death have also been reported in patients and otherwise healthy individuals treated with sulfamethoxazole and trimethoprim products.
Circulatory Shock Circulatory shock with fever, severe hypotension, and confusion requiring intravenous fluid resuscitation and vasopressors has occurred within minutes to hours of re-challenge with sulfamethoxazole and trimethoprim products, including sulfamethoxazole and trimethoprim, in patients with history of recent (days to weeks) exposure to sulfamethoxazole and trimethoprim. Management of Hypersensitivity and Other Serious Reactions Sulfamethoxazole and trimethoprim should be discontinued at the first appearance of skin rash or any sign of a serious adverse reaction.
A skin rash may be followed by a more severe reaction, such as Stevens-Johnson syndrome, toxic epidermal necrolysis, DRESS, AFND, AGEP, hepatic necrosis, or serious blood disorders (see PRECAUTIONS and ADVERSE REACTIONS ). Clinical signs, such as rash, pharyngitis, fever, arthralgia, cough, chest pain, dyspnea, pallor, purpura or jaundice may be early indications of serious reactions. Hemophagocytic Lymphohistiocytosis Cases of hemophagocytic lymphohistiocytosis (HLH) have been reported in patients treated with sulfamethoxazole-trimethoprim.
HLH is a life-threatening syndrome of pathologic immune activation characterized by clinical signs and symptoms of extreme systemic inflammation. Signs and symptoms of HLH may include fever, hepatosplenomegaly, rash, lymphadenopathy, neurologic symptoms, cytopenias, high serum ferritin, hypertriglyceridemia, and liver enzyme and coagulation abnormalities. If HLH is suspected, discontinue sulfamethoxazole and trimethoprim immediately and institute appropriate management.
Thrombocytopenia Sulfamethoxazole and trimethoprim-induced thrombocytopenia may be an immune-mediated disorder. Severe cases of thrombocytopenia that are fatal or life threatening have been reported. Thrombocytopenia usually resolves within a week upon discontinuation of sulfamethoxazole and trimethoprim.
Streptococcal Infections and Rheumatic Fever The sulfonamides should not be used for treatment of group A β-hemolytic streptococcal infections. In an established infection, they will not erad…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The following adverse reactions associated with the use of sulfamethoxazole and trimethoprim were identified in clinical trials, postmarketing or published reports. Because some of these reactions were reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. The most common adverse reactions are gastrointestinal disturbances (nausea, vomiting, anorexia) and allergic skin reactions (such as rash and urticaria).
Fatalities and serious adverse reactions, including severe cutaneous adverse reactions (SCARs), including Stevens-Johnson syndrome, toxic epidermal necrolysis, drug reaction with eosinophilia and systemic symptoms (DRESS), acute febrile neutrophilic dermatosis (AFND), acute generalized erythematous pustulosis (AGEP); fulminant hepatic necrosis; agranulocytosis, aplastic anemia and other blood dyscrasias; acute and delayed lung injury; anaphylaxis and circulatory shock have occurred with the administration of sulfamethoxazole and trimethoprim products, including sulfamethoxazole and trimethoprim (see WARNINGS ).
Hematologic: Agranulocytosis, aplastic anemia, thrombocytopenia, leukopenia, neutropenia, hemolytic anemia, megaloblastic anemia, hypoprothrombinemia, methemoglobinemia, eosinophilia, thrombotic thrombocytopenic purpura, idiopathic thrombocytopenic purpura. Allergic/Immune Reactions: Stevens-Johnson syndrome, toxic epidermal necrolysis, anaphylaxis, allergic myocarditis, erythema multiforme, exfoliative dermatitis, angioedema, drug fever, chills, Henoch-Schoenlein purpura, serum sickness-like syndrome, generalized allergic reactions, generalized skin eruptions, photosensitivity, conjunctival and scleral injection, pruritus, urticaria, rash, periarteritis nodosa, hemophagocytic lymphohistiocytosis (HLH), systemic lupus erythematosus, drug reaction with eosinophilia and systemic symptoms (DRESS), acute generalized erythematous pustulosis (AGEP), and acute febrile neutrophilic dermatosis (AFND) (see WARNINGS ).
Gastrointestinal: Hepatitis (including cholestatic jaundice and hepatic necrosis), elevation of serum transaminase and bilirubin, pseudomembranous enterocolitis, pancreatitis, stomatitis, glossitis, nausea, emesis, abdominal pain, diarrhea, anorexia. Genitourinary: Renal failure, interstitial nephritis, BUN and serum creatinine elevation, renal insufficiency, oliguria and anuria, crystalluria and nephrotoxicity in association with cyclosporine. Metabolic and Nutritional: Hyperkalemia, hyponatremia (see PRECAUTIONS: Electrolyte Abnormalities ), metabolic acidosis.
Neurologic: Aseptic meningitis, convulsions, peripheral neuritis, ataxia, vertigo, tinnitus, headache. Psychiatric: Hallucinations, depression, apathy, nervousness. Endocrine: The sulfonamides bear certain chemical similarities to some goitrogens, diuretics (acetazolamide and the thiazides) and oral hypoglycemic agents.
Cross-sensitivity may exist with these agents. Diuresis and hypoglycemia have occurred. Musculoskeletal: Arthralgia, myalgia, rhabdomyolysis.
Respiratory: Cough, shortness of breath and pulmonary infiltrates, acute eosinophilic pneumonia, acute and delayed lung injury, interstitial lung disease, acute respiratory failure (see WARNINGS ). Cardiovascular System: QT prolongation resulting in ventricular tachycardia and torsades de pointes , circulatory shock (see WARNINGS ) . Miscellaneous: Weakness, fatigue, insomnia.
🔄 Drug Interactions ▾
Drug Interactions Potential for Sulfamethoxazole and Trimethoprim to Affect Other Drugs Trimethoprim is an inhibitor of CYP2C8 as well as OCT2 transporter. Sulfamethoxazole is an inhibitor of CYP2C9. Avoid coadministration of sulfamethoxazole and trimethoprim with drugs that are substrates of CYP2C8 and 2C9 or OCT2.
Table 1: Drug Interactions with Sulfamethoxazole and Trimethoprim Drug(s) Recommendation Comments Diuretics Avoid concurrent use In elderly patients concurrently receiving certain diuretics, primarily thiazides, an increased incidence of thrombocytopenia with purpura has been reported. Warfarin Monitor prothrombin time and INR It has been reported that sulfamethoxazole and trimethoprim may prolong the prothrombin time in patients who are receiving the anticoagulant warfarin (a CYP2C9 substrate). This interaction should be kept in mind when sulfamethoxazole and trimethoprim is given to patients already on anticoagulant therapy, and the coagulation time should be reassessed.
Phenytoin Monitor serum phenytoin levels Sulfamethoxazole and trimethoprim may inhibit the hepatic metabolism of phenytoin (a CYP2C9 substrate). Sulfamethoxazole and trimethoprim, given at a common clinical dosage, increased the phenytoin half-life by 39% and decreased the phenytoin metabolic clearance rate by 27%. When administering these drugs concurrently, one should be alert for possible excessive phenytoin effect.
Methotrexate Avoid concurrent use Sulfonamides can also displace methotrexate from plasma protein binding sites and can compete with the renal transport of methotrexate, thus increasing free methotrexate concentrations. Cyclosporine Avoid concurrent use There have been reports of marked but reversible nephrotoxicity with coadministration of sulfamethoxazole and trimethoprim and cyclosporine in renal transplant recipients. Digoxin Monitor serum digoxin levels Increased digoxin blood levels can occur with concomitant sulfamethoxazole and trimethoprim therapy, especially in elderly patients.
Indomethacin Avoid concurrent use Increased sulfamethoxazole blood levels may occur in patients who are also receiving indomethacin. Pyrimethamine Avoid concurrent use Occasional reports suggest that patients receiving pyrimethamine as malaria prophylaxis in doses exceeding 25 mg weekly may develop megaloblastic anemia if sulfamethoxazole and trimethoprim is prescribed. Tricyclic Antidepressants (TCAs) Monitor therapeutic response and adjust dose of TCA accordingly The efficacy of tricyclic antidepressants can decrease when coadministered with sulfamethoxazole and trimethoprim.
Oral Hypoglycemics Monitor blood glucose more frequently Like other sulfonamide-containing drugs, sulfamethoxazole and trimethoprim potentiates the effect of oral hypoglycemic that are metabolized by CYP2C8 (e.g., pioglitazone, repaglinide, and rosiglitazone) or CYP2C9 (e.g., glipizide and glyburide) or eliminated renally via OCT2 (e.g., metformin). Additional monitoring of blood glucose may be warranted. Amantadine Avoid concurrent use In the literature, a single case of toxic delirium has been reported after concomitant intake of sulfamethoxazole and trimethoprim and amantadine (an OCT2 substrate).
Cases of interactions with other OCT2 substrates, memantine and metformin, have also been reported. Angiotensin Converting Enzyme Inhibitors Avoid concurrent use In the literature, three cases of hyperkalemia in elderly patients have been reported after concomitant intake of sulfamethoxazole and trimethoprim and an angiotensin converting enzyme inhibitor. 5,6 Zidovudine Monitor for hematologic toxicity Zidovudine and sulfamethoxazole and trimethoprim are known to induce hematological abnormalities.
Hence, there is potential for an additive myelotoxicity when coadministered. 7 Dofetilide Concurrent administration is contraindicated Elevated plasma concentrations of dofetilide have been reported following concurrent administration of trimethoprim and dofetilide. Increased plasma…
🔄 Drug / Laboratory Test Interactions ▾
Drug/Laboratory Test Interactions Sulfamethoxazole and trimethoprim, specifically the trimethoprim component, can interfere with a serum methotrexate assay as determined by the competitive binding protein technique (CBPA) when a bacterial dihydrofolate reductase is used as the binding protein. No interference occurs, however, if methotrexate is measured by a radioimmunoassay (RIA). The presence of sulfamethoxazole and trimethoprim may also interfere with the Jaffé alkaline picrate reaction assay for creatinine, resulting in overestimations of about 10% in the range of normal values.
🤰 Pregnancy ▾
Pregnancy While there are no large, well-controlled studies on the use of sulfamethoxazole and trimethoprim in pregnant women, Brumfitt and Pursell, 11 in a retrospective study, reported the outcome of 186 pregnancies during which the mother received either placebo or sulfamethoxazole and trimethoprim. The incidence of congenital abnormalities was 4.5% (3 of 66) in those who received placebo and 3.3% (4 of 120) in those receiving sulfamethoxazole and trimethoprim. There were no abnormalities in the 10 children whose mothers received the drug during the first trimester.
In a separate survey, Brumfitt and Pursell also found no congenital abnormalities in 35 children whose mothers had received oral sulfamethoxazole and trimethoprim at the time of conception or shortly thereafter. Because sulfamethoxazole and trimethoprim may interfere with folic acid metabolism, sulfamethoxazole and trimethoprim should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Teratogenic Effects Human Data While there are no large prospective, well controlled studies in pregnant women and their babies, some retrospective epidemiologic studies suggest an association between first trimester exposure to sulfamethoxazole and trimethoprim with an increased risk of congenital malformations, particularly neural tube defects, cardiovascular abnormalities, urinary tract defects, oral clefts, and club foot.
These studies, however, were limited by the small number of exposed cases and the lack of adjustment for multiple statistical comparisons and confounders. These studies are further limited by recall, selection, and information biases, and by limited generalizability of their findings. Lastly, outcome measures varied between studies, limiting cross-study comparisons.
Alternatively, other epidemiologic studies did not detect statistically significant associations between sulfamethoxazole and trimethoprim exposure and specific malformations. Animal Data In rats, oral doses of either 533 mg/kg sulfamethoxazole or 200 mg/kg trimethoprim produced teratologic effects manifested mainly as cleft palates. These doses are approximately 5 and 6 times the recommended human total daily dose on a body surface area basis.
In two studies in rats, no teratology was observed when 512 mg/kg of sulfamethoxazole was used in combination with 128 mg/kg of trimethoprim. In some rabbit studies, an overall increase in fetal loss (dead and resorbed conceptuses) was associated with doses of trimethoprim 6 times the human therapeutic dose based on body surface area. Nonteratogenic Effects See CONTRAINDICATIONS section.
🧒 Pediatric Use ▾
Pediatric Use Sulfamethoxazole and trimethoprim is contraindicated for infants younger than 2 months of age (see INDICATIONS AND USAGE and CONTRAINDICATIONS sections).
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of sulfamethoxazole and trimethoprim did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. There may be an increased risk of severe adverse reactions in elderly patients, particularly when complicating conditions exist, e.g., impaired kidney and/or liver function, possible folate deficiency, or concomitant use of other drugs. Severe skin reactions, generalized bone marrow suppression (see WARNINGS and ADVERSE REACTIONS sections), a specific decrease in platelets (with or without purpura), and hyperkalemia are the most frequently reported severe adverse reactions in elderly patients.
In those concurrently receiving certain diuretics, primarily thiazides, an increased incidence of thrombocytopenia with purpura has been reported. Increased digoxin blood levels can occur with concomitant sulfamethoxazole and trimethoprim therapy, especially in elderly patients. Serum digoxin levels should be monitored.
Hematological changes indicative of folic acid deficiency may occur in elderly patients. These effects are reversible by folinic acid therapy. Appropriate dosage adjustments should be made for patients with impaired kidney function and duration of use should be as short as possible to minimize risks of undesired reactions (see DOSAGE AND ADMINISTRATION section).
The trimethoprim component of sulfamethoxazole and trimethoprim may cause hyperkalemia when administered to patients with underlying disorders of potassium metabolism, with renal insufficiency or when given concomitantly with drugs known to induce hyperkalemia, such as angiotensin converting enzyme inhibitors. Close monitoring of serum potassium is warranted in these patients. Discontinuation of sulfamethoxazole and trimethoprim treatment is recommended to help lower potassium serum levels.
Sulfamethoxazole and trimethoprim tablets contain 0.45 mg sodium (0.02 mEq) of sodium per tablet. Sulfamethoxazole and trimethoprim DS tablets contain 0.9 mg (0.04 mEq) of sodium per tablet. Pharmacokinetics parameters for sulfamethoxazole were similar for geriatric subjects and younger adult subjects.
The mean maximum serum trimethoprim concentration was higher and mean renal clearance of trimethoprim was lower in geriatric subjects compared with younger subjects (see CLINICAL PHARMACOLOGY: Geriatric Pharmacokinetics ).
🆘 Overdosage ▾
OVERDOSAGE Acute The amount of a single dose of sulfamethoxazole and trimethoprim that is either associated with symptoms of overdosage or is likely to be life-threatening has not been reported. Signs and symptoms of overdosage reported with sulfonamides include anorexia, colic, nausea, vomiting, dizziness, headache, drowsiness and unconsciousness. Pyrexia, hematuria and crystalluria may be noted.
Blood dyscrasias and jaundice are potential late manifestations of overdosage. Signs of acute overdosage with trimethoprim include nausea, vomiting, dizziness, headache, mental depression, confusion and bone marrow depression. General principles of treatment include the institution of gastric lavage or emesis, forcing oral fluids, and the administration of intravenous fluids if urine output is low and renal function is normal.
Acidification of the urine will increase renal elimination of trimethoprim. The patient should be monitored with blood counts and appropriate blood chemistries, including electrolytes. If a significant blood dyscrasia or jaundice occurs, specific therapy should be instituted for these complications.
Peritoneal dialysis is not effective and hemodialysis is only moderately effective in eliminating sulfamethoxazole and trimethoprim. Chronic Use of sulfamethoxazole and trimethoprim at high doses and/or for extended periods of time may cause bone marrow depression manifested as thrombocytopenia, leukopenia and/or megaloblastic anemia. If signs of bone marrow depression occur, the patient should be given leucovorin 5 to 15 mg daily until normal hematopoiesis is restored.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Sulfamethoxazole and trimethoprim is rapidly absorbed following oral administration. Both sulfamethoxazole and trimethoprim exist in the blood as unbound, protein-bound and metabolized forms; sulfamethoxazole also exists as the conjugated form. Sulfamethoxazole is metabolized in humans to at least 5 metabolites: the N 4 -acetyl-, N 4 -hydroxy-, 5-methylhydroxy-, N 4 -acetyl-5-methylhydroxy- sulfamethoxazole metabolites, and an N-glucuronide conjugate.
The formulation of N 4 -hydroxy metabolite is mediated via CYP2C9. Trimethoprim is metabolized in vitro to 11 different metabolites, of which, five are glutathione adducts and six are oxidative metabolites, including the major metabolites, 1- and 3-oxides and the 3- and 4-hydroxy derivatives. The free forms of sulfamethoxazole and trimethoprim are considered to be the therapeutically active forms.
In vitro studies suggest that trimethoprim is a substrate of P-glycoprotein, OCT1 and OCT2, and that sulfamethoxazole is not a substrate of P-glycoprotein. Approximately 70% of sulfamethoxazole and 44% of trimethoprim are bound to plasma proteins. The presence of 10 mg percent sulfamethoxazole in plasma decreases the protein binding of trimethoprim by an insignificant degree; trimethoprim does not influence the protein binding of sulfamethoxazole.
Peak blood levels for the individual components occur 1 to 4 hours after oral administration. The mean serum half-lives of sulfamethoxazole and trimethoprim are 10 and 8 to 10 hours, respectively. However, patients with severely impaired renal function exhibit an increase in the half-lives of both components, requiring dosage regimen adjustment (see DOSAGE AND ADMINISTRATION section).
Detectable amounts of sulfamethoxazole and trimethoprim are present in the blood 24 hours after drug administration. During administration of 800 mg sulfamethoxazole and 160 mg trimethoprim b.i.d., the mean steady-state plasma concentration of trimethoprim was 1.72 mcg/mL. The steady-state mean plasma levels of free and total sulfamethoxazole were 57.4 mcg/mL and 68 mcg/mL, respectively.
These steady-state levels were achieved after three days of drug administration. 1 Excretion of sulfamethoxazole and trimethoprim is primarily by the kidneys through both glomerular filtration and tubular secretion. Urine concentrations of both sulfamethoxazole and trimethoprim are considerably higher than are the concentrations in the blood.
The average percentage of the dose recovered in urine from 0 to 72 hours after a single oral dose of sulfamethoxazole and trimethoprim is 84.5% for total sulfonamide and 66.8% for free trimethoprim. Thirty percent of the total sulfonamide is excreted as free sulfamethoxazole, with the remaining as N 4 -acetylated metabolite. 2 When administered together as sulfamethoxazole and trimethoprim, neither sulfamethoxazole nor trimethoprim affects the urinary excretion pattern of the other.
Both sulfamethoxazole and trimethoprim distribute to sputum, vaginal fluid and middle ear fluid; trimethoprim also distributes to bronchial secretion, and both pass the placental barrier and are excreted in human milk. Pharmacokinetics in Pediatric Patients A simulation conducted with data from a pharmacokinetic study in 153 infants and children demonstrated that mean steady state AUC and maximum plasma concentration of trimethoprim and sulfamethoxazole would be comparable between pediatric patients 2 months to 18 years receiving 8/40 (trimethoprim/ sulfamethoxazole) mg/kg/day divided every 12 hours and adult patients receiving 320/1600 (trimethoprim/ sulfamethoxazole) mg/day.
Pharmacokinetics in Geriatric Patients The pharmacokinetics of sulfamethoxazole 800 mg and trimethoprim 160 mg were studied in 6 geriatric subjects (mean age: 78.6 years) and 6 young healthy subjects (mean age: 29.3 years) using a non-U.S. approved formulation. Pharmacokinetic values for sulfamethoxazole in geriatric subjects were similar to those observed in young adu…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Sulfamethoxazole and Trimethoprim Tablets USP, 400 mg/80 mg are white to off-white circular, beveled edge uncoated tablets, debossed with “H 48” on one side and deep break line on the other side. Bottles of 20 NDC 65862-419-20 Bottles of 100 NDC 65862-419-01 Bottles of 500 NDC 65862-419-05 Bottles of 1,000 NDC 65862-419-99 Sulfamethoxazole and Trimethoprim Tablets USP, 800 mg/160 mg are white to off-white oval, beveled edge uncoated tablets, debossed with “H 49” on one side and deep break line on other side.
Bottles of 20 NDC 65862-420-20 Bottles of 100 NDC 65862-420-01 Bottles of 500 NDC 65862-420-05 Bottles of 1,000 NDC 65862-420-99 Store at 20º to 25ºC (68º to 77ºF); excursions permitted to 15º to 30ºC (59° to 86°F) [see USP Controlled Room Temperature]. DISPENSE IN TIGHT, LIGHT-RESISTANT CONTAINER.
📋 Description ▾
DESCRIPTION Sulfamethoxazole and trimethoprim is a synthetic antibacterial combination product available in DS (double strength) tablets, each containing 800 mg sulfamethoxazole and 160 mg trimethoprim; in tablets, each containing 400 mg sulfamethoxazole and 80 mg trimethoprim for oral administration. Sulfamethoxazole is N 1 -(5-methyl-3-isoxazolyl) sulfanilamide; the molecular formula is C 10 H 11 N 3 O 3 S. It is a white to off-white, practically odorless, crystalline powder, tasteless compound with a molecular weight of 253.28 and the following structural formula: Trimethoprim is 2,4-diamino-5-(3,4,5-trimethoxybenzyl) pyrimidine; the molecular formula is C 14 H 18 N 4 O 3 .
It is a white or cream-colored crystals or crystalline powder with a molecular weight of 290.3 and the following structural formula: Inactive ingredients: Docusate sodium, magnesium stearate, pregelatinized starch (maize), sodium benzoate, and sodium starch glycolate. Sulfamethoxazole Chemical Structure Trimethoprim Chemical Structure
💬 Information for Patients ▾
Information for Patients Hypersensitivity and Other Serious Reactions: Advise patients to stop taking sulfamethoxazole and trimethoprim immediately if they experience any clinical signs such as rash, pharyngitis, fever, arthralgia, cough, chest pain, dyspnea, pallor, purpura or jaundice and to contact their healthcare provider as soon as possible (see WARNINGS and ADVERSE REACTIONS ). Antibacterial Resistance: Patients should be counseled that antibacterial drugs including sulfamethoxazole and trimethoprim tablets should only be used to treat bacterial infections.
They do not treat viral infections (e.g., the common cold). When sulfamethoxazole and trimethoprim tablets are prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed. Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by sulfamethoxazole and trimethoprim tablets or other antibacterial drugs in the future.
Crystalluria and Stone Formation: Advise patients to maintain an adequate fluid intake in order to prevent crystalluria and stone formation. Diarrhea: Advise patients that diarrhea is a common problem caused by antibiotics which usually ends when the antibiotic is discontinued. Sometimes after starting treatment with antibiotics, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibiotic.
If this occurs, patients should contact their physician as soon as possible.