
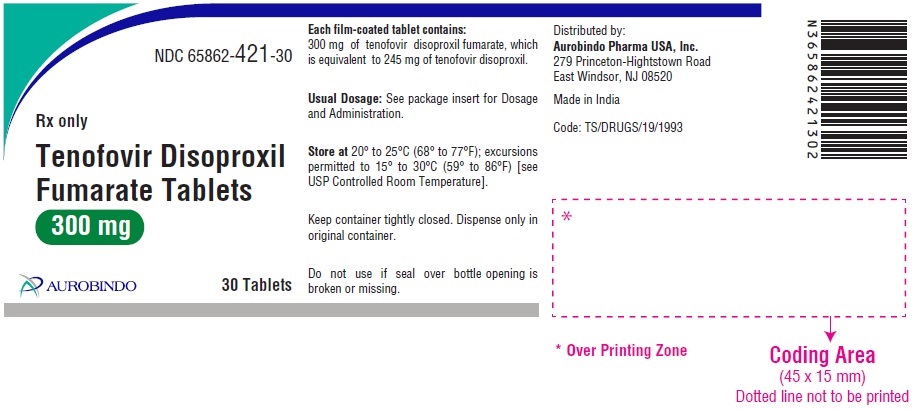
Tenofovir Disoproxil Fumarate 300 mg Tablet, Film Coated, 30-count — NDC 65862-421-30 (Billing 65862-0421-30)
This is a package of 30 tablets of Tenofovir Disoproxil Fumarate 300 mg Tablet, Film Coated from Aurobindo Pharma Limited, marketed since Jan 2018 and currently FDA-listed; retail pharmacies pay about $0.2938 per tablet (NADAC). It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 65862-421-30 alone.
- Record
- FDA NDC Directory package listing · Drug for further processing
- Code segments
- 65862 labeler · 421 product · 30 package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 30 EA per package
- Barcode (UPC-A, from the NDC)
- 3 6586242130 2
- Medicaid fills, this package
- 1,749 prescriptions in the last four reported quarters
- FDA record last changed
- Oct 1, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 048843
- GCN: 14822
- GPI-14 (Medi-Span): 12108570100320
- HICL (First Databank): 022937
- AHFS class code: 08:18.08.20
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
Clinical
This is an oral prescription tablet containing tenofovir disoproxil fumarate, a nucleotide reverse transcriptase inhibitor. Tenofovir disoproxil fumarate is typically used as part of combination therapy to treat HIV-1 infection and chronic hepatitis B in adults. The medication functions by slowing the reproduction of these viruses in the body. This is a film-coated tablet intended to be taken by mouth.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Tenofovir Disoproxil Fumarate — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.294 | $8.81 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $1.38 | $41.31 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $1.04 | $31.29 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 65862-0421-30 You're viewing this Main listing | 30 TABLET, FILM COATED in 1 BOTTLE | $0.2938 / ea | $8.81 | 2018-01-26 | — | Active |
| 65862-0421-22 65862-421-22 | 2000 TABLET, FILM COATED in 1 BAG | — | — | — | — | Active |
You're viewing the smallest of 2 pack sizes for this product.
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 65862-0421-22?
What NDC number is used to bill for this package of Tenofovir Disoproxil Fumarate 300 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| tenofovir disoproxil fumarate 300 mg 00904-6821-04 | Major | 30 tablets | $0.294 | AB | Availability likely | — |
| Tenofovir Disoproxil Fumarate 300 mg 16714-0820-01 | NorthStar | 30 tablets | $0.294 | AB | Availability likely | — |
| tenofovir disoproxil fumarate 300 mg 33342-0096-07 | Macleods | 30 tablets | $0.294 | AB | Availability likely | — |
| Tenofovir Disoproxil Fumarate 300 mg 50268-0758-12 | AvPAK | 20 tablets | $0.294 | AB | Availability likely | — |
| Tenofovir Disoproxil Fumarate 300 mg 62135-0466-30 | Chartwell | 30 tablets | $0.294 | AB | Availability likely | — |
| Tenofovir Disoproxil Fumarate 300 mg 64380-0714-04 | Strides | 30 tablets | $0.294 | AB | Availability likely | — |
| Tenofovir Disoproxil Fumarate 300 mgthis 65862-0421-30 | Aurobindo | 30 tablets | $0.294 | — | Availability likely | — |
| Tenofovir Disoproxil Fumarate 300 mg 69076-0105-03 | Quinn | 30 tablets | $0.294 | AB | Availability likely | — |
| Tenofovir disoproxil fumarate 300 mg 69097-0533-02 | Cipla | 30 tablets | $0.294 | AB | Availability likely | — |
| Tenofovir Disoproxil Fumarate 300 mg 71921-0105-33 | Florida | 30 tablets | $0.294 | AB | Availability likely | — |
| Viread 300 mg 61958-0401-01 | Gilead | 30 tablets | $40.687 | AB | Availability likely | +13748% |
| Tenofovir Disoproxil Fumarate 300 mg 31722-0535-01 | Camber | 100 tablets | — | AB | FDA listed | — |
| Tenofovir Disoproxil Fumarate 300 mg 42291-0800-30 | AvKARE | 30 tablets | — | AB | FDA listed | — |
| Tenofovir Disoproxil Fumarate 300 mg 50090-7202-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Tenofovir Disoproxil Fumarate 300 mg 63629-9729-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Tenofovir Disoproxil Fumarate 300 mg 71335-2364-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Tenofovir Disoproxil Fumarate 300 mg 72789-0361-07 | PD-Rx | 7 tablets | — | AB | FDA listed | — |
| tenofovir disoproxil fumarate 300 mg 63285-0872-00 | Patheon | 30 tablets | — | — | FDA listed | — |
| Tenofovir Disoproxil Fumarate 300 mg 66406-0103-00 | Patheon | 14861 tablets | — | — | FDA listed | — |
| Tenofovir Disoproxil Fumarate 300 mg 47234-0401-03 | Takeda | 30000 tablets | — | — | FDA listed | — |
| Tenofovir Disoproxil Fumarate 300 mg 71335-3155-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 36SFW2JZ0W
Hypromellose 2910 is a plant-based thickening agent derived from cellulose. In medicines, it forms a protective coating on tablets or capsules and controls how quickly the drug dissolves and releases into your body.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII XHX3C3X673
Triacetin is a clear, oily liquid made from glycerin and acetic acid. It works as a plasticizer and solvent in medicines, helping soften coatings and improve how liquids mix together in formulations.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Aurobindo Pharma Limited labeler code 65862
- Bupropion Hydrochloride 50 kg/50kg Powder NDC 65862-413-37
- Rabeprazole Sodium 50 kg/50kg Powder NDC 65862-414-37
- Metoprolol Succinate 50 kg/50kg Powder NDC 65862-415-37
- Metoprolol Tartrate 50 kg/50kg Powder NDC 65862-416-37
- Sulfamethoxazole and Trimethoprim 400 mg; 80 mg Tablet NDC 65862-419-01
- Sulfamethoxazole and Trimethoprim 800 mg; 160 mg Tablet NDC 65862-420-01
- Gemfibrozil 50 kg/50kg Powder NDC 65862-424-37
- Perindopril tert-Butylamine 50 kg/50kg Powder NDC 65862-425-37
- Pantoprazole Sodium Sesquihydrate 50 kg/50kg Powder NDC 65862-426-37
- Losartan Potassium 50 kg/50kg Powder NDC 65862-428-37
- Donepezil Hydrochloride 50 kg/50kg Powder NDC 65862-429-37
- Cetirizine Hydrochloride 5 mg Tablet NDC 65862-444-59
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full FDA label FDA SPL
🚨 Boxed Warning ▾
WARNING: POSTTREATMENT ACUTE EXACERBATION OF HEPATITIS B Severe acute exacerbations of hepatitis B virus (HBV) have been reported in HBV-infected patients who have discontinued anti-hepatitis B therapy, including t enofovir disoproxil fumarate. Hepatic function should be monitored closely with both clinical and laboratory follow-up for at least several months in HBV-infected patients who discontinue anti-hepatitis B therapy, including tenofovir disoproxil fumarate. If appropriate, resumption of anti-hepatitis B therapy may be warranted [see Warnings and Precautions (5.1) ] .
WARNING: POSTTREATMENT ACUTE EXACERBATION OF HEPATITIS B See full prescribing information for complete boxed warning. Severe acute exacerbations of hepatitis B virus (HBV) have been reported in HBV-infected patients who have discontinued anti-hepatitis B therapy, including tenofovir disoproxil fumarate. Hepatic function should be monitored closely in HBV-infected patients who discontinue tenofov ir disoproxil fumarate.
If appropriate, resumption of anti-hepatitis B therapy may be warranted. (5.1)
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Tenofovir disoproxil fumarate is a nucleotide analog HIV-1 reverse transcriptase inhibitor and an HBV reverse transcriptase inhibitor and is indicated: in combination with other antiretroviral agents for the treatment of HIV-1 infection in adults and pediatric patients 2 years of age and older weighing at least 10 kg. (1.1) for the treatment of chronic hepatitis B in adults and pediatric patients 2 years and older weighing at least 10 kg. (1.2)
1.1HIV-1 Infection Tenofovir disoproxil fumarate tablets are indicated in combination with other antiretroviral agents for the treatment of human immunodeficiency virus type 1 (HIV-1) infection in adults and pediatric patients 2 years of age and older weighing at least 10 kg.
1.2Chronic Hepatitis B Tenofovir disoproxil fumarate tablets are indicated for the treatment of chronic hepatitis B virus (HBV) in adults and pediatric patients 2 years of age and older weighing at least 10 kg.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Testing: Prior to or when initiating tenofovir disoproxil fumarate test for hepatitis B virus infection and HIV-1 infection. Prior to initiation and during use of tenofovir disoproxil fumarate, on a clinically appropriate schedule, assess serum creatinine, estimated creatinine clearance, urine glucose, and urine protein in all patients. In patients with chronic kidney disease, also assess serum phosphorous.
(2.1) Recommended tablet dosage in adults and pediatric patients weighing at least 35 kg: One tenofovir disoproxil fumarate 300 mg tablet once daily taken orally without regard to food. (2.2) Recommended dosage in pediatric patients at least 2 years of age and adults: Tablets: For patients weighing at least 17 kg who can swallow an intact tablet, one tenofovir disoproxil fumarate tablet (150 mg, 200 mg, 250 mg, or 300 mg based on body weight) once daily taken orally without regard to food. (2.2) Recommended dosage in renally impaired adult patients: Creatinine clearance (CrCl) 30 to 49 mL/min: 300 mg every 48 hours.
(2.4) CrCl 10 to 29 mL/min: 300 mg every 72 to 96 hours. (2.4) Hemodialysis: 300 mg every 7 days or after approximately 12 hours of dialysis. (2.4)
2.1Testing Prior to Initiation of Tenofovir Disoproxil Fumarate Tablets for Treatment of HIV-1 Infection or Chronic Hepatitis B Prior to or when initiating tenofovir disoproxil fumarate tablets, test patients for HBV infection and HIV-1 infection. Tenofovir disoproxil fumarate tablets alone should not be used in patients with HIV-1 infection [see Warnings and Precautions (5.3) ]. Prior to initiation and during use of tenofovir disoproxil fumarate tablets, on a clinically appropriate schedule, assess serum creatinine, estimated creatinine clearance, urine glucose and urine protein in all patients.
In patients with chronic kidney disease, also assess serum phosphorus [see Warnings and Precautions (5.2) ].
2.2Recommended Tablet Dosage in Adults and Pediatric Patients 2 Years and Older Weighing at Least 17 kg The recommended dosage of tenofovir disoproxil fumarate tablets in adults and pediatric patients weighing at least 35 kg is one 300 mg tablet taken orally once daily without regard to food. The dosage for tenofovir disoproxil fumarate tablet is the same for both HIV and HBV indications. The recommended dosage of tenofovir disoproxil fumarate tablet in adults and pediatric patients 2 years and older weighing at least 17 kg is 8 mg of tenofovir disoproxil fumarate (TDF) per kg of body weight (up to a maximum of 300 mg) once daily.
Dosage for pediatric patients 2 years and older weighing between 17 kg and 35 kg and able to swallow an intact tablet is provided in Table 1. Weight should be monitored periodically and the tenofovir disoproxil fumarate tablets dose adjusted accordingly. Table 1 Recommended Dosing for Patients 2 Years and Older and Weighing at Least 17 kg Using Tenofovir Disoproxil Fumarate Tablets Body Weight (kg) Dosing of Tenofovir Disoproxil Fumarate Tablets 17 to less than 22 one 150 mg tablet once daily 22 to less than 28 one 200 mg tablet once daily 28 to less than 35 one 250 mg tablet once daily at least 35 one 300 mg tablet once daily
2.4Dosage Adjustment in Patients with Renal Impairment Significant increase in drug exposures occurred when tenofovir disoproxil fumarate tablets were administered to subjects with moderate to severe renal impairment (creatinine clearance below 50 mL/min). Table 3 provides dosage interval adjustment for patients with renal impairment. No dosage adjustment of tenofovir disoproxil fumarate tablets 300 mg is necessary for patients with mild renal impairment (creatinine clearance 50 to 80 mL/min) [see Warnings and Precautions (5.3), Use in Specific Populations (8.6), and Clinical Pharmacology (12.3)] .
Table 3 Dosage Interval Adjustment for Adult Patients with Altered Creatinine Clearance a. Calculated using ideal (lean) body weight. b. Generally once weekly assuming 3 hemodialysis sessions a… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tenofovir disoproxil fumarate is available as tablets in four dose strengths. 150 mg Tablets: 150 mg of tenofovir disoproxil fumarate (TDF) (equivalent to 123 mg of tenofovir disoproxil): white to off-white, capsule shaped, biconvex, film-coated tablets debossed with ‘35’ on one side and ‘J’ on the other side. 200 mg Tablets: 200 mg of TDF (equivalent to 163 mg of tenofovir disoproxil): white to off-white, round shaped, biconvex, film-coated tablets debossed with ‘K’ on one side and ‘25’ on the other side.
250 mg Tablets: 250 mg of TDF (equivalent to 204 mg of tenofovir disoproxil): white to off-white, capsule shaped, biconvex, film-coated tablets debossed with ‘69 Y’ on one side and plain on the other side. 300 mg Tablets: 300 mg of TDF (equivalent to 245 mg of tenofovir disoproxil): white to off-white, oval shaped, biconvex, film-coated tablets debossed with ‘I’ on one side and ‘36’ on the other side. Tablets: 150 mg, 200 mg, 250 mg, and 300 mg of tenofovir disoproxil fumarate.
(3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS New onset or worsening renal impairment: Can include acute renal failure and Fanconi syndrome. Avoid administering tenofovir disoproxil fumarate with concurrent or recent use of nephrotoxic drugs. (5.2) HIV testing: HIV antibody testing should be offered to all HBV-infected patients before initiating therapy with tenofovir disoproxil fumarate.
Tenofovir disoproxil fumarate should only be used as part of an appropriate antiretroviral combination regimen in HIV-infected patients with or without HBV coinfection. (5.3) Immune reconstitution syndrome: May necessitate further evaluation and treatment. (5.4) Decreases in bone mineral density (BMD): Consider assessment of BMD in patients with a history of pathologic fracture or other risk factors for osteoporosis or bone loss.
(5.5) Lactic acidosis/severe hepatomegaly with steatosis: Discontinue treatment in patients who develop symptoms or laboratory findings suggestive of lactic acidosis or pronounced hepatotoxicity. (5.6)
5.1Severe Acute Exacerbation of Hepatitis B in Patients with HBV Infection All patients should be tested for the presence of chronic hepatitis B virus (HBV) before or when initiating tenofovir disoproxil fumarate [see Dosage and Administration (2.1) ]. Discontinuation of anti-HBV therapy, including tenofovir disoproxil fumarate, may be associated with severe acute exacerbations of hepatitis B. Patients infected with HBV who discontinue tenofovir disoproxil fumarate should be closely monitored with both clinical and laboratory follow-up for at least several months after stopping treatment.
If appropriate, resumption of anti-hepatitis B therapy may be warranted, especially in patients with advanced liver disease or cirrhosis, since posttreatment exacerbation of hepatitis may lead to hepatic decompensation and liver failure.
5.2New Onset or Worsening Renal Impairment Tenofovir is principally eliminated by the kidney. Renal impairment, including cases of acute renal failure and Fanconi syndrome (renal tubular injury with severe hypophosphatemia), has been reported with the use of tenofovir disoproxil fumarate [see Adverse Reactions (6.2) ] . Prior to initiation and during use of tenofovir disoproxil fumarate, on a clinically appropriate schedule, assess serum creatinine, estimated creatinine clearance, urine glucose, and urine protein in all patients.
In patients with chronic kidney disease, also assess serum phosphorus. Dosing interval adjustment of tenofovir disoproxil fumarate and close monitoring of renal function are recommended in all patients with creatinine clearance below 50 mL/min [see Dosage and Administration (2.4) ] . No safety or efficacy data are available in patients with renal impairment who received tenofovir disoproxil fumarate using these dosing guidelines, so the potential benefit of tenofovir disoproxil fumarate therapy should be assessed against the potential risk of renal toxicity.
Tenofovir disoproxil fumarate should be avoided with concurrent or recent use of a nephrotoxic agen t (e.g., high-dose or multiple non-steroidal anti-inflammatory drugs [NSAIDs]) [see Drug Interactions (7.1) ] . Cases of acute renal failure after initiation of high-dose or multiple NSAIDs have been reported in HIV-infected patients with risk factors for renal dysfunction who appeared stable on TDF. Some patients required hospitalization and renal replacement therapy.
Alternatives to NSAIDs should be considered, if needed, in patients at risk for renal dysfunction. Persistent or worsening bone pain, pain in extremities, fractures and/or muscular pain or weakness may be manifestations of proximal renal tubulopathy and should prompt an evaluation of renal function in patients at risk of renal dysfunction.
5.3Patients Coinfected with HIV-1 and HBV Due to the risk of development of HIV-1 resistance, tenofovir disoproxil fumarate should only be used in HIV-1 and HBV coinfected patients as part of an appropriate antiretroviral combination regim… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in other sections of the labeling: Severe Acute Exacerbation of Hepatitis B in Patients with HBV Infection [see Warnings and Precautions (5.1) ] . New Onset or Worsening Renal Impairment [see Warnings and Precautions (5.2) ] . Immune Reconstitution Syndrome [see Warnings and Precautions (5.4) ] .
Bone Loss and Mineralization Defects [see Warnings and Precautions (5.5) ]. Lactic Acidosis/Severe Hepatomegaly with Steatosis [see Warnings and Precautions (5.6) ]. In HIV-infected adult subjects: Most common adverse reactions (incidence greater than or equal to 10%, Grades 2 to 4) were rash, diarrhea, nausea, headache, pain, depression, and asthenia.
(6.1) In HBV-infected subjects with compensated liver disease: Most common adverse reaction (all grades) was nausea (9%). (6.1) In HBV-infected subjects with decompensated liver disease: Most common adverse reactions (incidence greater than or equal to 10%, all grades) were abdominal pain, nausea, insomnia, pruritus, vomiting, dizziness, and pyrexia. (6.1) In pediatric subjects: Adverse reactions in pediatric subjects were consistent with those observed in adults.
(6.1) To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse Reactions from Clinical Trials Experience in HIV-1 Infected Adults More than 12,000 subjects have been treated with tenofovir disoproxil fumarate alone or in combination with other antiretroviral medicinal products for periods of 28 days to 215 weeks in clinical trials and expanded access programs.
A total of 1,544 subjects have received tenofovir disoproxil fumarate 300 mg once daily in clinical trials; over 11,000 subjects have received tenofovir disoproxil fumarate in expanded access programs. The most common adverse reactions (incidence greater than or equal to 10%, Grades 2 to 4) identified from any of the 3 large controlled clinical trials include rash, diarrhea, headache, pain, depression, asthenia, and nausea. Clinical Trials in Treatment-Naïve HIV-1 Infected Adult Subjects In Trial 903, 600 antiretroviral-naïve subjects received tenofovir disoproxil fumarate (N=299) or stavudine (d4T) (N=301) administered in combination with lamivudine (3TC) and efavirenz (EFV) for 144 weeks.
The most common adverse reactions were mild to moderate gastrointestinal events and dizziness. Mild adverse reactions (Grade 1) were common with a similar incidence in both arms and included dizziness, diarrhea, and nausea. Table 4 provides the treatment-emergent adverse reactions (Grades 2 to 4) occurring in greater than or equal to 5% of subjects treated in any treatment group.
Table 4 Selected Adverse Reactions a (Grades 2 to 4) Reported in ≥5% in Any Treatment Group in Trial 903 (0 to 144 Weeks) a. Frequencies of adverse reactions are based on all treatment-emergent adverse events, regardless of relationship to study drug. b. Rash event includes rash, pruritus, maculopapular rash, urticaria, vesiculobullous rash, and pustular rash. c.
Lipodystrophy represents a variety of investigator-described adverse events not a protocol-defined syndrome. d. Peripheral neuropathy includes peripheral neuritis and neuropathy. Tenofovir Disoproxil Fumarate+3TC+EFV d4T+3TC+EFV N=299 N=301 Rash event b 18% 12% Headache 14% 17% Pain 13% 12% Diarrhea 11% 13% Depression 11% 10% Back pain 9% 8% Nausea 8% 9% Fever 8% 7% Abdominal pain 7% 12% Asthenia 6% 7% Anxiety 6% 6% Vomiting 5% 9% Insomnia 5% 8% Arthralgia 5% 7% Pneumonia 5% 5% Dyspepsia 4% 5% Dizziness 3% 6% Myalgia 3% 5% Lipodystrophy c 1% 8% Peripheral neuropathy d 1% 5% Laboratory Abnormalities: Table… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Tenofovir disoproxil fumarate increases didanosine concentrations. Dose reduction and close monitoring for didanosine toxicity are warranted. ( 7.2 ) Coadministration decreases atazanavir concentrations.
When coadministered with tenofovir disoproxil fumarate, use atazanavir given with ritonavir. ( 7.2 ) Coadministration of tenofovir disoproxil fumarate with certain HIV-1 protease inhibitors or certain drugs to treat HCV increases tenofovir concentrations. Monitor for evidence of tenofovir toxicity.
( 7.2 ) Consult Full Prescribing Information prior to and during treatment for important drug interactions. ( 7.2 )
7.1Drugs Affecting Renal Function Tenofovir is primarily eliminated by the kidneys [see Clinical Pharmacology (12.3) ]. Coadministration of tenofovir disoproxil fumarate with drugs that are eliminated by active tubular secretion may increase concentrations of tenofovir and/or the coadministered drug. Some examples include, but are not limited to, acyclovir, cidofovir, ganciclovir, valacyclovir, valganciclovir, aminoglycosides (e.g., gentamicin), and high-dose or multiple NSAIDs [see Warnings and Precautions (5.2) ].
Drugs that decrease renal function may increase concentrations of tenofovir. In the treatment of chronic hepatitis B, tenofovir disoproxil fumarate should not be administered in combination with HEPSERA (adefovir dipivoxil).
7.2Established and Significant Interactions Table 12 provides a listing of established or clinically significant drug interactions. The drug interactions described are based on studies conducted with TDF [see Clinical Pharmacology (12.3) ]. Table 12 Established and Significant a Drug Interactions: Alteration in Dose or Regimen May Be Recommended Based on Drug Interaction Trials a.
This table is not all inclusive. b. ↑=Increase, ↓=Decrease Concomitant Drug Class: Drug Name Effect on Concentration b Clinical Comment NRTI: didanosine ↑ didanosine Patients receiving tenofovir disoproxil fumarate and didanosine should be monitored closely for didanosine-associated adverse reactions. Discontinue didanosine in patients who develop didanosine-associated adverse reactions. Higher didanosine concentrations could potentiate didanosine-associated adverse reactions, including pancreatitis, and neuropathy.
Suppression of CD4+ cell counts has been observed in patients receiving tenofovir disoproxil fumarate with didanosine 400 mg daily. In patients weighing greater than 60 kg, reduce the didanosine dose to 250 mg when it is coadministered with tenofovir disoproxil fumarate. In patients weighing less than 60 kg, reduce the didanosine dose to 200 mg when it is coadministered with tenofovir disoproxil fumarate.
When coadministered, tenofovir disoproxil fumarate and Videx EC may be taken under fasted conditions or with a light meal (less than 400 kcal, 20% fat). HIV-1 Protease Inhibitors : atazanavir lopinavir/ritonavir atazanavir/ritonavir darunavir/ritonavir ↓ atazanavir ↑ tenofovir When coadministered with tenofovir disoproxil fumarate, atazanavir 300 mg should be given with ritonavir 100 mg. Monitor patients receiving tenofovir disoproxil fumarate concomitantly with lopinavir/ritonavir, ritonavir-boosted atazanavir, or ritonavir-boosted darunavir for TDF-associated adverse reactions.
Discontinue tenofovir disoproxil fumarate in patients who develop TDF-associated adverse reactions. Hepatitis C Antiviral Agents: sofosbuvir/velpatasvir sofosbuvir/velpatasvir/ voxilaprevir ledipasvir/sofosbuvir ↑ tenofovir Monitor patients receiving tenofovir disoproxil fumarate concomitantly with EPCLUSA ® (sofosbuvir/velpatasvir) for adverse reactions associated with TDF. Monitor patients receiving tenofovir disoproxil fumarate concomitantly with HARVONI ® (ledipasvir/sofosbuvir) without an HIV-1 protease inhibitor/ritonavir or an HIV-1 protease inhibitor/cobicistat combination, for adverse reactions associated with TDF.
In patients receiving tenofovir disoproxil fumarate concomitantly with HARVON… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Breastfeeding in HIV-1 infected mothers is not recommended due to the potential for HIV-1 transmission. (8.2)
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to tenofovir disoproxil fumarate during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Available data from the APR show no increase in the overall risk of major birth defects with first trimester exposure for tenofovir disoproxil fumarate (TDF) (2.1%) compared with the background rate for major birth defects of 2.7% in a U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP) (see Data) .
The rate of miscarriage for individual drugs is not reported in the APR. In the U.S. general population, the estimated background risk of miscarriage in clinically recognized pregnancies is 15 to 20%. Published studies in HBV-infected subjects do not report an increased risk of adverse pregnancy-related outcomes with the use of tenofovir disoproxil fumarate during the third trimester of pregnancy (see Data) .
In animal reproduction studies, no adverse developmental effects were observed when TDF was administered at doses/exposures ≥14 (TDF) and 2.7 (tenofovir) times those of the recommended daily dose of tenofovir disoproxil fumarate (see Data) . Data Human Data Based on prospective reports from the APR exposures to TDF-containing regimens during pregnancy resulting in live births (including 3,342 exposed in the first trimester and 1,475 exposed in the second/third trimester), there was no increase in overall major birth defects with TDF compared with the background birth defect rate of 2.7% in a U.S. reference population of the MACDP.
The prevalence of major birth defects in live births was 2.3% (95% CI: 1.8% to 2.8%) with first trimester exposure to TDF-containing regimens, and 2.1% (95% CI: 1.4% to 3.0%) with the second/third trimester exposure to TDF-containing regimens. Prospective reports from the APR of overall major birth defects in pregnancies exposed to TDF are compared with a U.S. background major birth defect rate. Methodological limitations of the APR include the use of MACDP as the external comparator group.
Limitations of using an external comparator include differences in methodology and populations, as well as confounding due to the underlying disease. In published data from three controlled clinical trials, a total of 327 pregnant women with chronic HBV infection were administered tenofovir disoproxil fumarate from 28 to 32 weeks gestation through 1 to 2 months postpartum and followed for up to 12 months after delivery. There were no new safety findings in pregnant women compared with the known safety profile of tenofovir disoproxil fumarate in HBV-infected adults.
An increased risk of adverse pregnancy-related outcomes was not observed; 2 stillbirths were identified, and there was 1 major birth defect (talipes) and 1 occurrence of multiple congenital abnormalities (not further specified) in tenofovir disoproxil fumarate-exposed infants. Infants were followed for up to 12 months after delivery; there were no clinically relevant drug-related safety findings in infants exposed to tenofovir disoproxil fumarate during late gestation. Animal Data TDF was administered orally to pregnant rats (at 0, 50, 150, or 450 mg/kg/day) and rabbits (at 0, 30, 100, or 300 mg/kg/day) through organogenesis (on gestation days 7 through 17, and 6 through 18, respectively).
No significant toxicological effects were observed in embryo-fetal toxicity studies performed with TDF in rats at doses up to 14 times the human dose based on body surface area comparisons and in rabbits at doses up to 19 times the human dose based on body surface area comparisons. In a pre/postnatal development study in rats, TDF was administered orally through l… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to tenofovir disoproxil fumarate during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Available data from the APR show no increase in the overall risk of major birth defects with first trimester exposure for tenofovir disoproxil fumarate (TDF) (2.1%) compared with the background rate for major birth defects of 2.7% in a U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP) (see Data) .
The rate of miscarriage for individual drugs is not reported in the APR. In the U.S. general population, the estimated background risk of miscarriage in clinically recognized pregnancies is 15 to 20%. Published studies in HBV-infected subjects do not report an increased risk of adverse pregnancy-related outcomes with the use of tenofovir disoproxil fumarate during the third trimester of pregnancy (see Data) .
In animal reproduction studies, no adverse developmental effects were observed when TDF was administered at doses/exposures ≥14 (TDF) and 2.7 (tenofovir) times those of the recommended daily dose of tenofovir disoproxil fumarate (see Data) . Data Human Data Based on prospective reports from the APR exposures to TDF-containing regimens during pregnancy resulting in live births (including 3,342 exposed in the first trimester and 1,475 exposed in the second/third trimester), there was no increase in overall major birth defects with TDF compared with the background birth defect rate of 2.7% in a U.S. reference population of the MACDP.
The prevalence of major birth defects in live births was 2.3% (95% CI: 1.8% to 2.8%) with first trimester exposure to TDF-containing regimens, and 2.1% (95% CI: 1.4% to 3.0%) with the second/third trimester exposure to TDF-containing regimens. Prospective reports from the APR of overall major birth defects in pregnancies exposed to TDF are compared with a U.S. background major birth defect rate. Methodological limitations of the APR include the use of MACDP as the external comparator group.
Limitations of using an external comparator include differences in methodology and populations, as well as confounding due to the underlying disease. In published data from three controlled clinical trials, a total of 327 pregnant women with chronic HBV infection were administered tenofovir disoproxil fumarate from 28 to 32 weeks gestation through 1 to 2 months postpartum and followed for up to 12 months after delivery. There were no new safety findings in pregnant women compared with the known safety profile of tenofovir disoproxil fumarate in HBV-infected adults.
An increased risk of adverse pregnancy-related outcomes was not observed; 2 stillbirths were identified, and there was 1 major birth defect (talipes) and 1 occurrence of multiple congenital abnormalities (not further specified) in tenofovir disoproxil fumarate-exposed infants. Infants were followed for up to 12 months after delivery; there were no clinically relevant drug-related safety findings in infants exposed to tenofovir disoproxil fumarate during late gestation. Animal Data TDF was administered orally to pregnant rats (at 0, 50, 150, or 450 mg/kg/day) and rabbits (at 0, 30, 100, or 300 mg/kg/day) through organogenesis (on gestation days 7 through 17, and 6 through 18, respectively).
No significant toxicological effects were observed in embryo-fetal toxicity studies performed with TDF in rats at doses up to 14 times the human dose based on body surface area comparisons and in rabbits at doses up to 19 times the human dose based on body surface area comparisons. In a pre/postnatal development study in rats, TDF was administered orally through lactation at doses up to 600 mg/kg/day; no adverse effects were observed in the offspring at tenofovir exposures of approximately 2.7 times higher than… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use Pediatric Patients 2 Years and Older with HIV-1 Infection The safety and effectiveness of tenofovir disoproxil fumarate in pediatric patients 2 years to less than 18 years of age is supported by data from two randomized trials. Trial 352 was a randomized controlled trial in 92 HIV-1 treatment experienced subjects 2 years to less than 12 years of age who were virologically suppressed on a stavudine- or zidovudine-containing regimen and were randomized to either switch to a tenofovir disoproxil fumarate-containing regimen (N=44) or stay on their original regimen (N=48) for 48 weeks.
At Week 48, 89% of subjects in the tenofovir disoproxil fumarate treatment group and 90% of subjects in the d4T or AZT treatment group had HIV-1 RNA concentrations <400 copies/mL. Trial 321 was a placebo-controlled trial in 87 HIV-1 treatment experienced subjects 12 years to less than 18 years of age who were treated with tenofovir disoproxil fumarate (N=45) or placebo (N=42) in combination with an optimized background regimen for 48 weeks. Overall, the trial failed to show a difference in virologic response between the tenofovir disoproxil fumarate and placebo groups.
Subgroup analyses suggest the lack of difference in virologic response may be attributable to imbalances between treatment arms in baseline viral susceptibility to tenofovir disoproxil fumarate and OBR [see Adverse Reactions (6.1) and Clinical Studies (14.3) ]. Although changes in HIV-1 RNA in these highly treatment-experienced subjects in Trial 321 were less than anticipated, the pharmacokinetic profile of tenofovir in patients 2 years to less than 18 years of age at the recommended doses was similar to that found to be safe and effective in adult clinical trials [see Clinical Pharmacology (12.3) ].
The effects of tenofovir disoproxil fumarate-associated changes in BMD and biochemical markers on long-term bone health and future fracture risk in HIV-1 pediatric patients 2 years and older are unknown. The long-term effect of lower spine and total body BMD on skeletal growth in pediatric patients 2 years and older, and in particular, the effects of long-duration exposure in younger children is unknown [see Warnings and Precautions (5.5) , Adverse Reactions (6.1) ]. Safety and effectiveness of tenofovir disoproxil fumarate in pediatric patients younger than 2 years of age and weighing less than 10 kg with HIV-1 infection have not been established.
Pediatric Patients 2 Years of Age and Older with Chronic Hepatitis B The safety and effectiveness of tenofovir disoproxil fumarate in pediatric patients 2 years to less than 18 years of age is supported by data from two randomized trials (Trial 115 and Trial 144) in which tenofovir disoproxil fumarate was administered to HBV-infected treatment-experienced subjects. In Trial 115, 106 HBeAg negative (9%) and positive (91%) subjects 12 years to less than 18 years of age with chronic HBV infection were randomized to receive blinded treatment with tenofovir disoproxil fumarate or placebo for 72 weeks.
At Week 72, 88% of subjects in the tenofovir disoproxil fumarate group and 0% of subjects in the placebo group had HBV DNA <400 copies/mL (69 IU/mL). In Trial 144, 89 HBeAg positive (96%) and negative (4%) subjects 2 years to less than 12 years of age were treated with tenofovir disoproxil fumarate 8 mg/kg up to maximum dose of 300 mg or placebo once daily for 48 weeks. At Week 48, 77% of subjects in the tenofovir disoproxil fumarate group and 7% of subjects in the placebo group had HBV DNA <400 copies/mL (69 IU/mL).
The effects of tenofovir disoproxil fumarate-associated changes in BMD and biochemical markers on long-term bone health and future fracture risk in chronic HBV-infected pediatric patients 2 years and older are unknown. The long-term effect of lower spine and total body BMD on skeletal growth in pediatric patients 2 years and older, and in particular, the effects of long-duration exposure in younger children is unknown [see… [Excerpted — this section continues on DailyMed.]
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of tenofovir disoproxil fumarate did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In general, dose selection for the elderly patient should be cautious, keeping in mind the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE If overdose occurs, the patient must be monitored for evidence of toxicity, and standard supportive treatment applied as necessary. Tenofovir is efficiently removed by hemodialysis with an extraction coefficient of approximately 54%. Following a single 300 mg dose of tenofovir disoproxil fumarate, a four-hour hemodialysis session removed approximately 10% of the administered tenofovir dose.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Tenofovir disoproxil fumarate is an antiviral drug [see Microbiology (12.4) ] .
12.3Pharmacokinetics The pharmacokinetics of TDF have been evaluated in healthy volunteers and HIV-1 infected individuals. Tenofovir pharmacokinetics are similar between these populations. Absorption Tenofovir disoproxil fumarate is a water soluble diester prodrug of the active ingredient tenofovir.
The oral bioavailability of tenofovir from tenofovir disoproxil fumarate in fasted subjects is approximately 25%. Following oral administration of a single dose of tenofovir disoproxil fumarate 300 mg to HIV-1 infected subjects in the fasted state, maximum serum concentrations (C max ) are achieved in 1.0 ± 0.4 hrs. C max and AUC values are 0.30 ± 0.09 mcg/mL and 2.29 ± 0.69 mcg•hr/mL, respectively.
The pharmacokinetics of tenofovir are dose proportional over a tenofovir disoproxil fumarate dose range of 75 to 600 mg and are not affected by repeated dosing. In a single-dose bioequivalence study conducted under non-fasted conditions (dose administered with 4 oz. applesauce) in healthy adult volunteers, the mean C max of tenofovir was 26% lower for the oral powder relative to the tablet formulation. Mean AUC of tenofovir was similar between the oral powder and tablet formulations.
Distribution In vitro binding of tenofovir to human plasma or serum proteins is less than 0.7 and 7.2%, respectively, over the tenofovir concentration range 0.01 to 25 mcg/mL. The volume of distribution at steady-state is 1.3 ±
0.6L/kg and 1.2 ±
0.4L/kg, following intravenous administration of tenofovir 1.0 mg/kg and 3.0 mg/kg. Metabolism and Elimination In vitro studies indicate that neither tenofovir disoproxil nor tenofovir are substrates of CYP enzymes. Following IV administration of tenofovir, approximately 70 to 80% of the dose is recovered in the urine as unchanged tenofovir within 72 hours of dosing.
Following single dose, oral administration of tenofovir disoproxil fumarate, the terminal elimination half-life of tenofovir is approximately 17 hours. After multiple oral doses of tenofovir disoproxil fumarate 300 mg once daily (under fed conditions), 32 ± 10% of the administered dose is recovered in urine over 24 hours. Tenofovir is eliminated by a combination of glomerular filtration and active tubular secretion.
There may be competition for elimination with other compounds that are also renally eliminated. Effects of Food on Oral Absorption Administration of tenofovir disoproxil fumarate 300 mg tablets following a high-fat meal (~700 to 1,000 kcal containing 40 to 50% fat) increases the oral bioavailability, with an increase in tenofovir AUC 0–∞ of approximately 40% and an increase in C max of approximately 14%. However, administration of tenofovir disoproxil fumarate with a light meal did not have a significant effect on the pharmacokinetics of tenofovir when compared to fasted administration of the drug.
Food delays the time to tenofovir C max by approximately 1 hour. C max and AUC of tenofovir are 0.33 ± 0.12 mcg/mL and 3.32 ± 1.37 mcg•hr/mL following multiple doses of tenofovir disoproxil fumarate 300 mg once daily in the fed state, when meal content was not controlled. Specific Populations Race There were insufficient numbers from racial and ethnic groups other than Caucasian to adequately determine potential pharmacokinetic differences among these populations.
Gender Tenofovir pharmacokinetics are similar in male and female subjects. Pediatric Patients 2 Years and Older: Steady-state pharmacokinetics of tenofovir were evaluated in 31 HIV-1 infected pediatric subjects 2 years to less than 18 years of age (Table 13). Tenofovir exposure achieved in these pediatric subjects receiving oral once daily doses of tenofovir disoproxil fumarate 300 mg (tablet) or 8 mg/kg of body weight (powder) up to a maximum dose of 300 mg was similar to exposures achieved in adults receiving once-daily doses of tenofovir disoproxil fumar… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Tenofovir disoproxil fumarate is an antiviral drug [see Microbiology (12.4) ] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Tenofovir Disoproxil Fumarate Tablets, 150 mg are white to off-white, capsule shaped, biconvex, film-coated tablets debossed with ‘35’ on one side and ‘J’ on the other side. Bottles of 30 NDC 65862-818-30 3 x 10 Unit-dose Tablets NDC 65862-818-03 Tenofovir Disoproxil Fumarate Tablets, 200 mg are white to off-white, round shaped, biconvex, film-coated tablets debossed with ‘K’ on one side and ‘25’ on the other side. Bottles of 30 NDC 65862-819-30 3 x 10 Unit-dose Tablets NDC 65862-819-03 Tenofovir Disoproxil Fumarate Tablets, 250 mg are white to off-white, capsule shaped, biconvex, film-coated tablets debossed with ‘69 Y’ on one side and plain on the other side.
Bottles of 30 NDC 65862-820-30 3 x 10 Unit-dose Tablets NDC 65862-820-03 Tenofovir Disoproxil Fumarate Tablets, 300 mg are white to off-white, oval shaped, biconvex, film-coated tablets debossed with ‘I’ on one side and ‘36’ on the other side. Bottles of 30 NDC 65862-421-30 Store at 20º to 25ºC (68º to 77ºF); excursions permitted to 15º to 30ºC (59° to 86°F) [see USP Controlled Room Temperature]. • Keep container tightly closed. • Dispense only in original container. • Do not use if seal over bottle opening is broken or missing.
📋 Description ▾
11 DESCRIPTION Tenofovir disoproxil fumarate (TDF) (a prodrug of tenofovir) which is a fumaric acid salt of bis-isopropoxycarbonyloxymethyl ester derivative of tenofovir. TDF is converted in vivo to tenofovir, an acyclic nucleoside phosphonate (nucleotide) analog of adenosine 5'-monophosphate. Tenofovir exhibits activity against HIV-1 reverse transcriptase.
The chemical name of TDF is 9-[( R )-2-[[bis[[(isopropoxycarbonyl)oxy]methoxy]phosphinyl]methoxy]propyl]adenine fumarate (1:1). It has a molecular formula of C 19 H 30 N 5 O 10 P • C 4 H 4 O 4 and a molecular weight of 635.52. It has the following structural formula: Tenofovir disoproxil fumarate is a white to off-white, crystalline powder with a solubility of 13.4 mg/mL in distilled water at 25°C.
It has an octanol/phosphate buffer (pH 6.5) partition coefficient (log p) of 1.25 at 25°C. Tenofovir disoproxil fumarate is available as tablets. Tenofovir disoproxil fumarate tablets are for oral administration and are available in the following strengths: 150 mg, 200 mg, 250 mg, and 300 mg of TDF (equivalent to 123 mg, 163 mg, 204 mg, and 245 mg of tenofovir disoproxil, respectively).
All strengths of tenofovir disoproxil fumarate tablets contain the following inactive ingredients: croscarmellose sodium, lactose monohydrate, magnesium stearate, microcrystalline cellulose, and pregelatinized starch (maize) (gluten free). The 300 mg strength tablets are coated with Opadry II White 32K18425, which contains hypromellose 15cP, lactose monohydrate, titanium dioxide, and triacetin. The 150 mg, 200 mg, and 250 mg strength tablets are coated with Aquarius BT18242 Cool Vanilla, which contains hypromellose 2910, lactose monohydrate, titanium dioxide and triacetin.
In this insert, all dosages are expressed in terms of TDF except where otherwise noted. Tenofovir Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Severe Acute Exacerbation of Hepatitis B in Patients Infected with HBV Inform patients that severe acute exacerbations of hepatitis B have been reported in patients infected with hepatitis B virus (HBV) and have discontinued tenofovir disoproxil fumarate tablets. Advise patients not to discontinue tenofovir disoproxil fumarate tablets without first informing their healthcare provider.
All patients should be tested for HBV infection before or when starting tenofovir disoproxil fumarate and those who are infected with HBV need close medical follow-up for several months after stopping tenofovir disoproxil fumarate tablets to monitor for exacerbations of hepatitis [see Warnings and Precautions (5.1) ]. New Onset or Worsening Renal Impairment Inform patients that renal impairment, including cases of acute renal failure and Fanconi syndrome, has been reported in association with the use of tenofovir disoproxil fumarate tablets.
Advise patients to avoid tenofovir disoproxil fumarate tablets with concurrent or recent use of a nephrotoxic agent (e.g., high-dose or multiple NSAIDs) [see Warnings and Precautions (5.2) ] . The dosing interval of tenofovir disoproxil fumarate tablets may need adjustment in HIV-1 infected patients with renal impairment. Immune Reconstitution Syndrome Inform patients that in some patients with advanced HIV infection (AIDS) signs and symptoms of inflammation from previous infections may occur soon after anti-HIV treatment is started.
It is believed that these symptoms are due to an improvement in the body’s immune response, enabling the body to fight infections that may have been present with no obvious symptoms. Advise patients to inform their healthcare provider immediately of any symptoms of infection [see Warnings and Precautions (5.4) ]. Bone Loss and Mineralization Defects Inform patients that decreases in bone mineral density have been observed with the use of tenofovir disoproxil fumarate tablets.
Consider bone monitoring in patients who have a history of pathologic bone fracture or at risk for osteopenia [see Warnings and Precautions (5.5) ]. Lactic Acidosis and Severe Hepatomegaly Inform patients that lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported. Treatment with tenofovir disoproxil fumarate tablets should be suspended in any patient who develops clinical symptoms suggestive of lactic acidosis or pronounced hepatotoxicity [see Warnings and Precautions (5.6) ] .
Drug Interactions Advise patients that tenofovir disoproxil fumarate may interact with many drugs; therefore, advise patients to report to their healthcare provider the use of any other medication, including other HIV drugs and drugs for treatment of hepatitis C virus [see Warnings and Precautions (5.7) and Drug Interactions (7) ]. Dosing Recommendations Inform patients that it is important to take tenofovir disoproxil fumarate tablets on a regular dosing schedule with or without food and to avoid missing doses as it can result in development of resistance [see Dosage and Administration (2) ].
Pregnancy Registry Inform patients that there is an antiretroviral pregnancy registry to monitor fetal outcomes of pregnant women exposed to tenofovir disoproxil fumarate [see Use in Specific Populations (8.1) ] . Lactation Instruct mothers not to breastfeed if they are taking tenofovir disoproxil fumarate tablets for the treatment of HIV-1 infection because of the risk of passing the HIV-1 virus to the baby [see Use in Specific Populations (8.2) ] . Treatment Duration Advise patients that in the treatment of chronic hepatitis B, the optimal duration of treatment is unknown.
The relationship between response and long-term prevention of outcomes such as hepatocellular carcinoma is not known.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetics of TDF have been evaluated in healthy volunteers and HIV-1 infected individuals. Tenofovir pharmacokinetics are similar between these populations. Absorption Tenofovir disoproxil fumarate is a water soluble diester prodrug of the active ingredient tenofovir.
The oral bioavailability of tenofovir from tenofovir disoproxil fumarate in fasted subjects is approximately 25%. Following oral administration of a single dose of tenofovir disoproxil fumarate 300 mg to HIV-1 infected subjects in the fasted state, maximum serum concentrations (C max ) are achieved in 1.0 ± 0.4 hrs. C max and AUC values are 0.30 ± 0.09 mcg/mL and 2.29 ± 0.69 mcg•hr/mL, respectively.
The pharmacokinetics of tenofovir are dose proportional over a tenofovir disoproxil fumarate dose range of 75 to 600 mg and are not affected by repeated dosing. In a single-dose bioequivalence study conducted under non-fasted conditions (dose administered with 4 oz. applesauce) in healthy adult volunteers, the mean C max of tenofovir was 26% lower for the oral powder relative to the tablet formulation. Mean AUC of tenofovir was similar between the oral powder and tablet formulations.
Distribution In vitro binding of tenofovir to human plasma or serum proteins is less than 0.7 and 7.2%, respectively, over the tenofovir concentration range 0.01 to 25 mcg/mL. The volume of distribution at steady-state is 1.3 ±
0.6L/kg and 1.2 ±
0.4L/kg, following intravenous administration of tenofovir 1.0 mg/kg and 3.0 mg/kg. Metabolism and Elimination In vitro studies indicate that neither tenofovir disoproxil nor tenofovir are substrates of CYP enzymes. Following IV administration of tenofovir, approximately 70 to 80% of the dose is recovered in the urine as unchanged tenofovir within 72 hours of dosing.
Following single dose, oral administration of tenofovir disoproxil fumarate, the terminal elimination half-life of tenofovir is approximately 17 hours. After multiple oral doses of tenofovir disoproxil fumarate 300 mg once daily (under fed conditions), 32 ± 10% of the administered dose is recovered in urine over 24 hours. Tenofovir is eliminated by a combination of glomerular filtration and active tubular secretion.
There may be competition for elimination with other compounds that are also renally eliminated. Effects of Food on Oral Absorption Administration of tenofovir disoproxil fumarate 300 mg tablets following a high-fat meal (~700 to 1,000 kcal containing 40 to 50% fat) increases the oral bioavailability, with an increase in tenofovir AUC 0–∞ of approximately 40% and an increase in C max of approximately 14%. However, administration of tenofovir disoproxil fumarate with a light meal did not have a significant effect on the pharmacokinetics of tenofovir when compared to fasted administration of the drug.
Food delays the time to tenofovir C max by approximately 1 hour. C max and AUC of tenofovir are 0.33 ± 0.12 mcg/mL and 3.32 ± 1.37 mcg•hr/mL following multiple doses of tenofovir disoproxil fumarate 300 mg once daily in the fed state, when meal content was not controlled. Specific Populations Race There were insufficient numbers from racial and ethnic groups other than Caucasian to adequately determine potential pharmacokinetic differences among these populations.
Gender Tenofovir pharmacokinetics are similar in male and female subjects. Pediatric Patients 2 Years and Older: Steady-state pharmacokinetics of tenofovir were evaluated in 31 HIV-1 infected pediatric subjects 2 years to less than 18 years of age (Table 13). Tenofovir exposure achieved in these pediatric subjects receiving oral once daily doses of tenofovir disoproxil fumarate 300 mg (tablet) or 8 mg/kg of body weight (powder) up to a maximum dose of 300 mg was similar to exposures achieved in adults receiving once-daily doses of tenofovir disoproxil fumarate 300 mg.
Table 13 Mean (± SD) Tenofovir Pharmacokinetic Parameters by Age Groups for HIV-1 infected Pediatric Patients 2 years… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Overview of Clinical Trials The efficacy and safety of tenofovir disoproxil fumarate in adults and pediatric subjects were evaluated in the trials summarized in Table 19. Table 19 Trials Conducted with Tenofovir Disoproxil Fumarate in Adults and Pediatric Subjects for HIV-1 Treatment and Chronic HBV Treatment Trial Population Study Arms (N) a Timepoint (Week) a. Randomized and dosed. b.
Randomized, double-blind, active-controlled trial. c. Randomized, open-label active-controlled trial. d. Randomized, double-blind, placebo-controlled trial.
Trial 903 b (NCT00158821) HIV-1 treatment-naïve adults Tenofovir disoproxil fumarate +lamivudine+efavirenz (299) stavudine+lamivudine+efavirenz (301) 144 Trial 934 c (NCT00112047) emtricitabine+ tenofovir disoproxil fumarate +efavirenz (257) zidovudine/lamivudine+efavirenz (254) 144 Trial 907 d (NCT00002450) HIV-1 treatment-experienced adults Tenofovir disoproxil fumarate (368) Placebo (182) 24 Trial 0102 b (NCT00117676) HBeAg-negative adults with chronic HBV Tenofovir disoproxil fumarate (250) HEPSERA (125) 48 Trial 0103 b (NCT00116805) HBeAg-positive adults with chronic HBV Tenofovir disoproxil fumarate (176) HEPSERA (90) 48 Trial 121 b (NCT00737568) Adults with lamivudine-resistant chronic HBV Tenofovir disoproxil fumarate (141) 96 Trial 0108 b (NCT00298363) Adults with chronic HBV and decompensated liver disease Tenofovir disoproxil fumarate (45) 48 Trial 352 c (NCT00528957) HIV-1 treatment experienced pediatric subjects 2 years to <12 years Tenofovir disoproxil fumarate (44) stavudine or zidovudine (48) 48 Trial 321 d (NCT00352053) HIV-1 treatment-experienced pediatric subjects 12 years to <18 years Tenofovir disoproxil fumarate (45) Placebo (42) 48 Trial 115 d (NCT00734162) Pediatric subjects 12 years to <18 years with chronic HBV Tenofovir disoproxil fumarate (52) Placebo (54) 72 Trial 144 d (NCT01651403) Pediatric subjects 2 years to <12 years with chronic HBV Tenofovir disoproxil fumarate (60) Placebo (29) 48
14.2Clinical Trial Results in Adults with HIV-1 Infection Treatment-Naïve Subjects: Trial 903 Data through 144 weeks are reported for Trial 903, a double-blind, active-controlled multicenter trial comparing tenofovir disoproxil fumarate (300 mg once daily) administered in combination with lamivudine (3TC) and efavirenz (EFV) versus stavudine (d4T), 3TC, and EFV in 600 antiretroviral-naïve subjects. Subjects had a mean age of 36 years (range 18 to 64); 74% were male, 64% were Caucasian, and 20% were Black. The mean baseline CD4+ cell count was 279 cells/mm 3 (range 3 to 956) and median baseline plasma HIV-1 RNA was 77,600 copies/mL (range 417 to 5,130,000).
Subjects were stratified by baseline HIV-1 RNA and CD4+ cell count. Forty-three percent of subjects had baseline viral loads >100,000 copies/mL and 39% had CD4+ cell counts <200 cells/mm 3 . Table 20 provides treatment outcomes through 48 and 144 weeks.
Table 20 Outcomes of Randomized Treatment at Week 48 and 144 (Trial 903) Outcomes At Week 48 At Week 144 Tenofovir Disoproxil Fumarate+3TC+EFV (N=299) d4T+3TC+EFV (N=301) Tenofovir Disoproxil Fumarate+3TC+EFV (N=299) d4T+3TC+EFV (N=301) a. Subjects achieved and maintained confirmed HIV-1 RNA <400 copies/mL through Week 48 and 144. b. Includes confirmed viral rebound and failure to achieve confirmed <400 copies/mL through Week 48 and 144. c.
Includes lost to follow-up, subject’s withdrawal, noncompliance, protocol violation and other reasons. Responder a 79% 82% 68% 62% Virologic failure b 6% 4% 10% 8% Rebound 5% 3% 8% 7% Never suppressed 0% 1% 0% 0% Added an antiretroviral agent 1% 1% 2% 1% Death <1% 1% <1% 2% Discontinued due to adverse event 6% 6% 8% 13% Discontinued for other reasons c 8% 7% 14% 15% Achievement of plasma HIV-1 RNA concentrations of <400 copies/mL at Week 144 was similar between the two treatment groups for the population stratified at baseline on the basis of HIV-1 RNA concentration (> or ≤100,000 copies/mL) and CD4+ cell count (<… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Long-term oral carcinogenicity studies of TDF in mice and rats were carried out at exposures up to approximately 16 times (mice) and 5 times (rats) those observed in humans at the therapeutic dose for HIV-1 infection. At the high dose in female mice, liver adenomas were increased at exposures 16 times that in humans. In rats, the study was negative for carcinogenic findings at exposures up to 5 times that observed in humans at the therapeutic dose.
Mutagenesis Tenofovir disoproxil fumarate was mutagenic in the in vitro mouse lymphoma assay and negative in an in vitro bacterial mutagenicity test (Ames test). In an in vivo mouse micronucleus assay, TDF was negative when administered to male mice. Impairment of Fertility There were no effects on fertility, mating performance or early embryonic development when TDF was administered to male rats at a dose equivalent to 10 times the human dose based on body surface area comparisons for 28 days prior to mating and to female rats for 15 days prior to mating through day seven of gestation.
There was, however, an alteration of the estrous cycle in female rats.
13.2Animal Toxicology and/or Pharmacology Tenofovir and TDF administered in toxicology studies to rats, dogs, and monkeys at exposures (based on AUCs) greater than or equal to 6 fold those observed in humans caused bone toxicity. In monkeys the bone toxicity was diagnosed as osteomalacia. Osteomalacia observed in monkeys appeared to be reversible upon dose reduction or discontinuation of tenofovir.
In rats and dogs, the bone toxicity manifested as reduced bone mineral density. The mechanism(s) underlying bone toxicity is unknown. Evidence of renal toxicity was noted in 4 animal species.
Increases in serum creatinine, BUN, glycosuria, proteinuria, phosphaturia, and/or calciuria and decreases in serum phosphate were observed to varying degrees in these animals. These toxicities were noted at exposures (based on AUCs) 2 to 20 times higher than those observed in humans. The relationship of the renal abnormalities, particularly the phosphaturia, to the bone toxicity is not known.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Long-term oral carcinogenicity studies of TDF in mice and rats were carried out at exposures up to approximately 16 times (mice) and 5 times (rats) those observed in humans at the therapeutic dose for HIV-1 infection. At the high dose in female mice, liver adenomas were increased at exposures 16 times that in humans. In rats, the study was negative for carcinogenic findings at exposures up to 5 times that observed in humans at the therapeutic dose.
Mutagenesis Tenofovir disoproxil fumarate was mutagenic in the in vitro mouse lymphoma assay and negative in an in vitro bacterial mutagenicity test (Ames test). In an in vivo mouse micronucleus assay, TDF was negative when administered to male mice. Impairment of Fertility There were no effects on fertility, mating performance or early embryonic development when TDF was administered to male rats at a dose equivalent to 10 times the human dose based on body surface area comparisons for 28 days prior to mating and to female rats for 15 days prior to mating through day seven of gestation.
There was, however, an alteration of the estrous cycle in female rats.
📄 Patient Package Insert ▾
Patient Information Tenofovir Disoproxil Fumarate Tablets (ten OF oh vir DYE soe PROX il FUE ma rate) Read this Patient Information before you start taking tenofovir disoproxil fumarate tablets and each time you get a refill. There may be new information. This information does not take the place of talking with your healthcare provider about your medical condition or treatment.
What is the most important information I should know about tenofovir disoproxil fumarate tablets? Tenofovir disoproxil fumarate tablets can cause serious side effects, including: Worsening of Hepatitis B virus infection (HBV). Your healthcare provider will test you for HBV and HIV before starting treatment with tenofovir disoproxil fumarate tablets.
If you have HBV infection and take tenofovir disoproxil fumarate tablets your HBV may get worse (flare-up) if you stop taking tenofovir disoproxil fumarate tablets . A “flare-up” is when your HBV infection suddenly returns in a worse way than before. Do not run out of tenofovir disoproxil fumarate tablets.
Refill your prescription or talk to your healthcare provider before your tenofovir disoproxil fumarate tablets are all gone. Do not stop taking tenofovir disoproxil fumarate tablets without first talking to your healthcare provider. If you stop taking tenofovir disoproxil fumarate tablets, your healthcare provider will need to check your health often and do blood tests regularly to check your HBV infection.
Tell your healthcare provider about any new or unusual symptoms you may have after you stop taking tenofovir disoproxil fumarate tablets. For more information about side effects, see “What are the possible side effects of tenofovir disoproxil fumarate tablets?” What are tenofovir disoproxil fumarate tablets? Tenofovir disoproxil fumarate tablets are a prescription medicine that is used to: treat HIV-1 infection when used with other anti-HIV-1 medicines in adults and children 2 years of age and older who weigh at least 22 pounds (10 kg).
HIV is the virus that causes AIDS (Acquired Immune Deficiency Syndrome). treat HBV infection in adults and children 2 years of age and older who weigh at least 22 pounds (10 kg). It is not known if tenofovir disoproxil fumarate tablets are safe and effective in children under 2 years of age. What should I tell my healthcare provider before taking tenofovir disoproxil fumarate tablets?
Before you take tenofovir disoproxil fumarate tablets, tell your healthcare provider about all of your medical conditions, including if you: have liver problems, including HBV infection have kidney problems or receive kidney dialysis treatment have bone problems have HIV infection are pregnant or plan to become pregnant. Tell your healthcare provider if you become pregnant during treatment with tenofovir disoproxil fumarate tablets. Pregnancy Registry .
There is a pregnancy registry for women who take tenofovir disoproxil fumarate tablets during pregnancy. The purpose of this registry is to collect information about the health of you and your baby. Talk to your healthcare provider about how you can take part in this registry. are breastfeeding or plan to breastfeed.
Tenofovir disoproxil fumarate can pass to your baby in your breast milk. Do not breastfeed if you have HIV-1 because of the risk of passing HIV-1 to your baby. If you take tenofovir disoproxil fumarate tablets for treatment of HBV infection, talk with your healthcare provider about the best way to feed your baby.
Tell your healthcare provider about all the medicines you take, including prescription and non-prescription medicines, vitamins, and herbal supplements. Some medicines may interact with tenofovir disoproxil fumarate tablets. Keep a list of your medicines and show it to your healthcare provider and pharmacist when you get a new medicine.
You can ask your healthcare provider or pharmacist for a list of medicines that interact with tenofovir disoproxil fumarate. Do not start a new medicine without telling your healthcare p… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 150 mg (30 Tablets Bottle) NDC 65862-818-30 Rx only Tenofovir Disoproxil Fumarate Tablets 150 mg AUROBINDO 30 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 150 mg (30 Tablets Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 150 mg (3 x 10) Unit Dose Tablets NDC 65862-818-03 Rx only Tenofovir Disoproxil Fumarate Tablets 150 mg AUROBINDO 30 (3 x1 0) Unit-dose Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 150 mg (3 x 10) Unit Dose Tablets
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 200 mg (30 Tablets Bottle) NDC 65862-819-30 Rx only Tenofovir Disoproxil Fumarate Tablets 200 mg AUROBINDO 30 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 200 mg (30 Tablets Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 200 mg (3 x 10) Unit Dose Tablets NDC 65862-819-03 Rx only Tenofovir Disoproxil Fumarate Tablets 200 mg AUROBINDO 30 (3 x1 0) Unit-dose Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 200 mg (3 x 10) Unit Dose Tablets
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 250 mg (30 Tablets Bottle) NDC 65862-820-30 Rx only Tenofovir Disoproxil Fumarate Tablets 250 mg AUROBINDO 30 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 250 mg (30 Tablets Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 250 mg (3 x 10) Unit Dose Tablets NDC 65862-820-03 Rx only Tenofovir Disoproxil Fumarate Tablets 250 mg AUROBINDO 30 (3 x1 0) Unit-dose Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 300 mg (3 x 10) Unit Dose Tablets
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 300 mg (30 Tablets Bottle) NDC 65862-421-30 Rx only Tenofovir Disoproxil Fumarate Tablets 300 mg AUROBINDO 30 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 300 mg (30 Tablets Bottle)
Medicaid utilization & spend
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What "drug for further processing" means
FDA lists this package under the "drug for further processing" marketing category: Aurobindo Pharma Limited supplies it to other companies for further processing or repackaging (blister cards that are later repackaged or co-packaged are a common example). The units themselves are a finished dosage form — which is why pricing or Medicaid data can still appear — but this exact package code may not be the presentation a retail pharmacy dispenses.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |