
Fosinopril Sodium 10 mg Tablet, 4,000-count — NDC 65862-471-49 (Billing 65862-0471-49)
This is a package of 4,000 tablets of Fosinopril Sodium 10 mg Tablet from Aurobindo Pharma Limited, marketed since Mar 2011 and currently FDA-listed.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 016017
- GCN: 48581
- GPI-14 (Medi-Span): 36100027100310
- HICL (First Databank): 006106
- AHFS class code: 24:32.04.00
- RxCUI (RxNorm): 857169
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Angiotensin Converting Enzyme Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It treats high blood pressure and helps manage heart failure. For heart failure it is added to your usual treatment, such as diuretics. It can be used alone or with a thiazide diur...
- It is a tablet taken by mouth, usually once a day. You can take it with or without food. If you also take an antacid, space the two about 2 hours apart. Follow your prescriber's di...
- The most common are cough, dizziness, nausea, headache, and tiredness. Many are mild and pass. A dry cough that won't go away is worth mentioning to your doctor.
- Get emergency help if your face, lips, tongue, or throat swell, or if you have trouble breathing. Call your doctor for fainting, severe belly pain, or yellow skin or eyes.
Patient education
Supplement & herbal interactions
Fosinopril may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 65862-0471-30 65862-471-30 Main listing | 30 TABLET in 1 BOTTLE | 2011-03-30 | — | Active |
| 65862-0471-90 65862-471-90 | 90 TABLET in 1 BOTTLE | 2011-03-30 | — | Active |
| 65862-0471-99 65862-471-99 | 1000 TABLET in 1 BOTTLE | 2011-03-30 | — | Active |
| 65862-0471-49 You're viewing this | 4000 TABLET in 1 BAG | — | — | Active |
You're viewing the largest of 4 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 65862-0471-30?
What NDC number is used to bill for this package of Fosinopril Sodium 10 mg Tablet?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Fosinopril sodium 10 mg 43547-0386-09 | Solco | 90 tablets | $0.154 | AB | Availability likely | — |
| Fosinopril Sodium 10 mg 62135-0041-90 | Chartwell | 90 tablets | $0.154 | AB | Availability likely | — |
| Fosinopril Sodium 10 mg 69097-0856-05 | Cipla | 90 tablets | $0.154 | AB | Availability likely | — |
| Fosinopril sodium 10 mg 76282-0200-10 | Exelan | 1000 tablets | $0.154 | AB | Availability likely | — |
| Fosinopril Sodium 10 mg 50090-2977-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Fosinopril Sodium 10 mgthis 65862-0471-49 | Aurobindo | 4000 tablets | — | AB | FDA listed | — |
| Fosinopril Sodium 10 mg 71335-0381-01 | Bryant | 30 tablets | — | AB | Discontinued | — |
| Fosinopril sodium 10 mg 71335-0726-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII 68401960MK
Crospovidone is a synthetic polymer made from polyvinylpyrrolidone. It acts as a disintegrant, helping tablets break apart quickly in the stomach so the medicine dissolves and absorbs into the body.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII 7CV7WJK4UI
Sodium stearyl fumarate is a synthetic compound made from stearyl alcohol and fumaric acid. It acts as a lubricant and glidant in tablets and capsules, helping ingredients flow smoothly during manufacturing and preventing sticking.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY When pregnancy is detected, discontinue fosinopril sodium tablets as soon as possible. Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus. See WARNINGS: Fetal Toxicity
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Fosinopril sodium tablets are indicated for the treatment of hypertension. It may be used alone or in combination with thiazide diuretics. Fosinopril sodium tablets are indicated in the management of heart failure as adjunctive therapy when added to conventional therapy including diuretics with or without digitalis (see DOSAGE AND ADMINISTRATION ).
In using fosinopril sodium tablets, consideration should be given to the fact that another angiotensin-converting enzyme inhibitor, captopril, has caused agranulocytosis, particularly in patients with renal impairment or collagen-vascular disease. Available data are insufficient to show that fosinopril sodium tablets do not have a similar risk (see WARNINGS ). In considering use of fosinopril sodium tablets, it should be noted that in controlled trials ACE inhibitors have an effect on blood pressure that is less in black patients than in non-blacks.
In addition, ACE inhibitors (for which adequate data are available) cause a higher rate of angioedema in black than in non-black patients (see WARNINGS: Head and Neck Angioedema and Intestinal Angioedema ).
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Hypertension Adults The recommended initial dose of fosinopril sodium tablets is 10 mg once a day, both as monotherapy and when the drug is added to a diuretic. Dosage should then be adjusted according to blood pressure response at peak (2 to 6 hours) and trough (about 24 hours after dosing) blood levels. The usual dosage range needed to maintain a response at trough is 20 to 40 mg but some patients appear to have a further response to 80 mg.
In some patients treated with once daily dosing, the antihypertensive effect may diminish toward the end of the dosing interval. If trough response is inadequate, dividing the daily dose should be considered. If blood pressure is not adequately controlled with fosinopril sodium tablets alone, a diuretic may be added.
Concomitant administration of fosinopril sodium tablets with potassium supplements, potassium salt substitutes, or potassium-sparing diuretics can lead to increases of serum potassium (see PRECAUTIONS ). In patients who are currently being treated with a diuretic, symptomatic hypotension occasionally can occur following the initial dose of fosinopril sodium tablets. To reduce the likelihood of hypotension, the diuretic should, if possible, be discontinued 2 to 3 days prior to beginning therapy with fosinopril sodium tablets (see WARNINGS ).
Then, if blood pressure is not controlled with fosinopril sodium tablets alone, diuretic therapy should be resumed. If diuretic therapy cannot be discontinued, an initial dose of 10 mg of fosinopril sodium tablets should be used with careful medical supervision for several hours and until blood pressure has stabilized. (See WARNINGS and PRECAUTIONS: Information for Patients and Drug Interactions .) Since concomitant administration of fosinopril sodium tablets with potassium supplements, or potassium-containing salt substitutes or potassium-sparing diuretics may lead to increases in serum potassium, they should be used with caution (see PRECAUTIONS ).
Pediatrics In children, doses of fosinopril sodium tablets between 0.1 and 0.6 mg/kg have been studied and shown to reduce blood pressure to a similar extent (see CLINICAL PHARMACOLOGY: Pharmacodynamics and Clinical Effects ). Based on this, the recommended dose of fosinopril sodium tablets in children weighing more than 50 kg is 5 to 10 mg once per day as monotherapy. An appropriate dosage strength is not available for children weighing less than 50 kg.
Heart Failure Digitalis is not required for fosinopril sodium tablets to manifest improvements in exercise tolerance and symptoms. Most placebo-controlled clinical trial experience has been with both digitalis and diuretics present as background therapy. The usual starting dose of fosinopril sodium tablets should be 10 mg once daily.
Following the initial dose of fosinopril sodium tablets, the patient should be observed under medical supervision for at least 2 hours for the presence of hypotension or orthostasis, and if present, until blood pressure stabilizes. An initial dose of 5 mg is preferred in heart failure patients with moderate to severe renal failure or those who have been vigorously diuresed. Dosage should be increased, over a several week period, to a dose that is maximal and tolerated but not exceeding 40 mg once daily.
The usual effective dosage range is 20 to 40 mg once daily. The appearance of hypotension, orthostasis, or azotemia early in dose titration should not preclude further careful dose titration. Consideration should be given to reducing the dose of concomitant diuretic.
For Hypertensive or Heart Failure Patients With Renal Impairment In patients with impaired renal function, the total body clearance of fosinoprilat is approximately 50% slower than in patients with normal renal function. Since hepatobiliary elimination partially compensates for diminished renal elimination, the total body clearance of fosinoprilat does not differ appreciably with any degree of renal insufficiency (creatinine c… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Fosinopril sodium tablets are contraindicated in patients who are hypersensitive to this product or to any other angiotensin-converting enzyme inhibitor (e.g., a patient who has experienced angioedema with any other ACE inhibitor therapy).
⚠️ Warnings ▾
WARNINGS Anaphylactoid and Possibly Related Reactions Presumably because angiotensin-converting enzyme inhibitors affect the metabolism of eicosanoids and polypeptides, including endogenous bradykinin, patients receiving ACE inhibitors (including fosinopril sodium) may be subject to a variety of adverse reactions, some of them serious. Head and Neck Angioedema Angioedema involving the extremities, face, lips, mucous membranes, tongue, glottis, or larynx has been reported in patients treated with ACE inhibitors. If angioedema involves the tongue, glottis, or larynx, airway obstruction may occur and be fatal.
If laryngeal stridor or angioedema of the face, lips, mucous membranes, tongue, glottis, or extremities occurs, treatment with fosinopril sodium should be discontinued and appropriate therapy instituted immediately. Where there is involvement of the tongue, glottis, or larynx, likely to cause airway obstruction, appropriate therapy, e.g., subcutaneous epinephrine solution 1:1000 (0.3 mL to 0.5 mL) should be promptly administered (see PRECAUTIONS: Information for Patients and ADVERSE REACTIONS ). Intestinal Angioedema Intestinal angioedema has been reported in patients treated with ACE inhibitors.
These patients presented with abdominal pain (with or without nausea or vomiting); in some cases there was no prior history of facial angioedema and C-1 esterase levels were normal. The angioedema was diagnosed by procedures including abdominal CT scan or ultrasound, or at surgery, and symptoms resolved after stopping the ACE inhibitor. Intestinal angioedema should be included in the differential diagnosis of patients on ACE inhibitors presenting with abdominal pain.
Anaphylactoid reactions during desensitization Two patients undergoing desensitizing treatment with hymenoptera venom while receiving ACE inhibitors sustained life-threatening anaphylactoid reactions. In the same patients, these reactions were avoided when ACE inhibitors were temporarily withheld, but they reappeared upon inadvertent rechallenge. Anaphylactoid reactions during membrane exposure Anaphylactoid reactions have been reported in patients dialyzed with high-flux membranes and treated concomitantly with an ACE inhibitor.
Anaphylactoid reactions have also been reported in patients undergoing low-density lipoprotein apheresis with dextran sulfate absorption. Hypotension Fosinopril sodium can cause symptomatic hypotension. Like other ACE inhibitors, fosinopril has been only rarely associated with hypotension in uncomplicated hypertensive patients.
Symptomatic hypotension is most likely to occur in patients who have been volume- and/or salt-depleted as a result of prolonged diuretic therapy, dietary salt restriction, dialysis, diarrhea, or vomiting. Volume and/or salt depletion should be corrected before initiating therapy with fosinopril sodium. In patients with heart failure, with or without associated renal insufficiency, ACE inhibitor therapy may cause excessive hypotension, which may be associated with oliguria or azotemia, and (rarely) with acute renal failure and death.
In such patients, fosinopril sodium therapy should be started under close medical supervision; they should be followed closely for the first 2 weeks of treatment and whenever the dose of fosinopril or diuretic is increased. Consideration should be given to reducing the diuretic dose in patients with normal or low blood pressure who have been treated vigorously with diuretics or who are hyponatremic. If hypotension occurs, the patient should be placed in a supine position, and, if necessary, treated with intravenous infusion of physiological saline.
Fosinopril sodium treatment usually can be continued following restoration of blood pressure and volume. Neutropenia/Agranulocytosis Another angiotensin-converting enzyme inhibitor, captopril, has been shown to cause agranulocytosis and bone marrow depression, rarely in uncomplicated patients, but more frequently in patients with renal impairment,… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Fosinopril sodium has been evaluated for safety in more than 2100 individuals in hypertension and heart failure trials, including approximately 530 patients treated for a year or more. Generally adverse events were mild and transient, and their frequency was not prominently related to dose within the recommended daily dosage range. Hypertension In placebo-controlled clinical trials (688 fosinopril sodium-treated patients), the usual duration of therapy was 2 to 3 months.
Discontinuations due to any clinical or laboratory adverse event were 4.1% and 1.1% in fosinopril sodium-treated and placebo-treated patients, respectively. The most frequent reasons (0.4 to 0.9%) were headache, elevated transaminases, fatigue, cough (see PRECAUTIONS: General , Cough ), diarrhea, and nausea and vomiting. During clinical trials with any fosinopril sodium regimen, the incidence of adverse events in the elderly (≥65 years old) was similar to that seen in younger patients.
Clinical adverse events probably or possibly related or of uncertain relationship to therapy, occurring in at least 1% of patients treated with fosinopril sodium alone and at least as frequent on fosinopril sodium as on placebo in placebo-controlled clinical trials are shown in the table below. Clinical Adverse Events in Placebo-Controlled Trials (Hypertension) Fosinopril Sodium (N=688) Incidence (Discontinuation) Placebo (N=184) Incidence (Discontinuation) Cough 2.2 (0.4) 0 (0) Dizziness 1.6 (0) 0 (0) Nausea/Vomiting 1.2 (0.4) 0.5 (0) The following events were also seen at >1% on fosinopril sodium but occurred in the placebo group at a greater rate: headache, diarrhea, fatigue, and sexual dysfunction.
Other clinical events probably or possibly related, or of uncertain relationship to therapy occurring in 0.2 to 1% of patients (except as noted) treated with fosinopril sodium in controlled or uncontrolled clinical trials (N=1479) and less frequent, clinically significant events include (listed by body system): General: Chest pain, edema, weakness, excessive sweating. Cardiovascular: Angina/myocardial infarction, cerebrovascular accident, hypertensive crisis, rhythm disturbances, palpitations, hypotension, syncope, flushing, claudication.
Orthostatic: hypotension occurred in 1.4% of patients treated with fosinopril monotherapy. Hypotension or orthostatic hypotension was a cause for discontinuation of therapy in 0.1% of patients. Dermatologic: Urticaria, rash, photosensitivity, pruritus.
Endocrine/Metabolic: Gout, decreased libido. Gastrointestinal: Pancreatitis, hepatitis, dysphagia, abdominal distention, abdominal pain, flatulence, constipation, heartburn, appetite/weight change, dry mouth. Hematologic: Lymphadenopathy.
Immunologic: Angioedema. (See WARNINGS: Head and Neck Angioedema and Intestinal Angioedema .) Musculoskeletal: Arthralgia, musculoskeletal pain, myalgia/muscle cramp. Nervous/Psychiatric: Memory disturbance, tremor, confusion, mood change, paresthesia, sleep disturbance, drowsiness, vertigo.
Respiratory: Bronchospasm, pharyngitis, sinusitis/rhinitis, laryngitis/hoarseness, epistaxis. A symptom-complex of cough, bronchospasm, and eosinophilia has been observed in two patients treated with fosinopril. Special Senses: Tinnitus, vision disturbance, taste disturbance, eye irritation.
Urogenital: Renal insufficiency, urinary frequency. Heart Failure In placebo-controlled clinical trials (361 fosinopril sodium-treated patients), the usual duration of therapy was 3 to 6 months. Discontinuations due to any clinical or laboratory adverse event, except for heart failure, were 8% and 7.5% in fosinopril sodium-treated and placebo-treated patients, respectively.
The most frequent reason for discontinuation of fosinopril sodium was angina pectoris (1.1%). Significant hypotension after the first dose of fosinopril sodium occurred in 14/590 (2.4%) of patients; 5/590 (0.8%) patients discontinued due to first dose hypotension. Clinical adverse events probably or po… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
Drug Interactions Diuretics Patients on diuretics, especially those with intravascular volume depletion, may occasionally experience an excessive reduction of blood pressure after initiation of therapy with fosinopril sodium tablets. The possibility of hypotensive effects with fosinopril sodium can be minimized by either discontinuing the diuretic or increasing salt intake prior to initiation of treatment with fosinopril sodium. If this is not possible, the starting dose should be reduced and the patient should be observed closely for several hours following an initial dose and until blood pressure has stabilized (see DOSAGE AND ADMINISTRATION ).
Potassium supplements and potassium-sparing diuretics Fosinopril sodium can attenuate potassium loss caused by thiazide diuretics. Potassium-sparing diuretics (spironolactone, amiloride, triamterene, and others) or potassium supplements can increase the risk of hyperkalemia. Therefore, if concomitant use of such agents is indicated, they should be given with caution, and the patient’s serum potassium should be monitored frequently.
Lithium Increased serum lithium levels and symptoms of lithium toxicity have been reported in patients receiving ACE inhibitors during therapy with lithium. These drugs should be coadministered with caution, and frequent monitoring of serum lithium levels is recommended. If a diuretic is also used, the risk of lithium toxicity may be increased.
Antacids In a clinical pharmacology study, coadministration of an antacid (aluminum hydroxide, magnesium hydroxide, and simethicone) with fosinopril reduced serum levels and urinary excretion of fosinoprilat as compared with fosinopril administrated alone, suggesting that antacids may impair absorption of fosinopril. Therefore, if concomitant administration of these agents is indicated, dosing should be separated by 2 hours. Gold Nitritoid reactions (symptoms include facial flushing, nausea, vomiting, and hypotension) have been reported rarely in patients on therapy with injectable gold (sodium aurothiomalate) and concomitant ACE inhibitor therapy including fosinopril sodium.
Other Neither fosinopril sodium nor its metabolites have been found to interact with food. In separate single or multiple dose pharmacokinetic interaction studies with chlorthalidone, nifedipine, propranolol, hydrochlorothiazide, cimetidine, metoclopramide, propantheline, digoxin, and warfarin, the bioavailability of fosinoprilat was not altered by coadministration of fosinopril with any one of these drugs. In a study with concomitant administration of aspirin and fosinopril sodium, the bioavailability of unbound fosinoprilat was not altered.
In a pharmacokinetic interaction study with warfarin, bioavailability parameters, the degree of protein binding, and the anticoagulant effect (measured by prothrombin time) of warfarin were not significantly changed. Dual Blockade of the Renin-Angiotensin System (RAS) Dual blockade of the RAS with angiotensin receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypotension, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy. Closely monitor blood pressure, renal function and electrolytes in patients on fosinopril and other agents that affect the RAS.
Do not co-administer aliskiren with fosinopril in patients with diabetes. Avoid use of aliskiren with fosinopril in patients with renal impairment (GFR <60 mL/min).
🔄 Drug / Laboratory Test Interactions ▾
Drug/Laboratory Test Interaction Fosinopril may cause a false low measurement of serum digoxin levels with the Digi-Tab ® RIA Kit for Digoxin. Other kits, such as the Coat-A-Count ® RIA Kit, may be used.
🧒 Pediatric Use ▾
Pediatric Use Neonates with a history of in utero exposure to fosinopril sodium tablets: If oliguria or hypotension occurs, direct attention toward support of blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and/or substituting for disordered renal function. Removal of fosinopril, which crosses the placenta, from the neonatal circulation is not significantly accelerated by these means.
The antihypertensive effects of fosinopril have been evaluated in a double-blind study in pediatric patients 6 to 16 years of age (see CLINICAL PHARMACOLOGY: Pharmacodynamics and Clinical Effects: Hypertension ). The pharmacokinetics of fosinopril have been evaluated in pediatric patients 6 to 16 years of age (see CLINICAL PHARMACOLOGY: Pharmacokinetics and Metabolism ). Fosinopril was generally well tolerated and adverse effects were similar to those described in adults (see ADVERSE REACTIONS: Pediatric Patients ).
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of fosinopril sodium did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
OVERDOSAGE Oral doses of fosinopril at 2600 mg/kg in rats were associated with significant lethality. Human overdoses of fosinopril have not been reported, but the most common manifestation of human fosinopril overdosage is likely to be hypotension. Laboratory determinations of serum levels of fosinoprilat and its metabolites are not widely available, and such determinations have, in any event, no established role in the management of fosinopril overdose.
No data are available to suggest physiological maneuvers (e.g., maneuvers to change the pH of the urine) that might accelerate elimination of fosinopril and its metabolites. Fosinoprilat is poorly removed from the body by both hemodialysis and peritoneal dialysis. Angiotensin II could presumably serve as a specific antagonist-antidote in the setting of fosinopril overdose, but angiotensin II is essentially unavailable outside of scattered research facilities.
Because the hypotensive effect of fosinopril is achieved through vasodilation and effective hypovolemia, it is reasonable to treat fosinopril overdose by infusion of normal saline solution. No adverse clinical events were reported in 23 pediatric patients, age 6 months to 6 years, given a single 0.3 mg/kg oral dose of fosinopril. There is a published report of a 20-month-old female, weighing 12 kg, who ingested approximately 200 mg fosinopril sodium.
After receiving gastric lavage and activated charcoal within 1 hour of the ingestion, she made an uneventful recovery.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action In animals and humans, fosinopril sodium is hydrolyzed by esterases to the pharmacologically active form, fosinoprilat, a specific competitive inhibitor angiotensin-converting enzyme (ACE). ACE is a peptidyl dipeptidase that catalyzes the conversion of angiotensin I to the vasoconstrictor substance, angiotensin II. Angiotensin II also stimulates aldosterone secretion by the adrenal cortex.
Inhibition of ACE results in decreased plasma angiotensin II, which leads to decreased vasopressor activity and to decreased aldosterone secretion. The latter decrease may result in a small increase of serum potassium. In 647 hypertensive patients treated with fosinopril alone for an average of 29 weeks, mean increases in serum potassium of 0.1 mEq/L were observed.
Similar increases were observed among all patients treated with fosinopril, including those receiving concomitant diuretic therapy. Removal of angiotensin II negative feedback on renin secretion leads to increased plasma renin activity. ACE is identical to kininase, an enzyme that degrades bradykinin.
Whether increased levels of bradykinin, a potent vasodepressor peptide, play a role in the therapeutic effects of fosinopril sodium remains to be elucidated. While the mechanism through which fosinopril sodium lowers blood pressure is believed to be primarily suppression of the renin-angiotensin-aldosterone system, fosinopril sodium has an antihypertensive effect even in patients with low-renin hypertension. Although fosinopril sodium was antihypertensive in all races studied, black hypertensive patients (usually a low-renin hypertensive population) had a smaller average response to ACE inhibitor monotherapy than non-black patients.
In patients with heart failure, the beneficial effects of fosinopril sodium are thought to result primarily from suppression of the renin-angiotensin-aldosterone system; inhibition of the angiotensin-converting enzyme produces decreases in both preload and afterload. Pharmacokinetics and Metabolism Following oral administration, fosinopril (the prodrug) is absorbed slowly. The absolute absorption of fosinopril averaged 36% of an oral dose.
The primary site of absorption is the proximal small intestine (duodenum/jejunum). While the rate of absorption may be slowed by the presence of food in the gastrointestinal tract, the extent of absorption of fosinopril is essentially unaffected. Fosinoprilat is highly protein-bound (approximately 99.4%), has a relatively small volume of distribution, and has negligible binding to cellular components in blood.
After single and multiple oral doses, plasma levels, areas under plasma concentration-time curves (AUCs), and peak concentrations (C maxs ) are directly proportional to the dose of fosinopril. Times to peak concentrations are independent of dose and are achieved in approximately 3 hours. After an oral dose of radiolabeled fosinopril, 75% of radioactivity in plasma was present as active fosinoprilat, 20 to 30% as a glucuronide conjugate of fosinoprilat, and 1 to 5% as a p -hydroxy metabolite of fosinoprilat.
Since fosinoprilat is not biotransformed after intravenous administration, fosinopril, not fosinoprilat, appears to be the precursor for the glucuronide and p -hydroxy metabolites. In rats, the p -hydroxy metabolite of fosinoprilat is as potent an inhibitor of ACE as fosinoprilat; the glucuronide conjugate is devoid of ACE inhibitory activity. After intravenous administration, fosinoprilat was eliminated approximately equally by the liver and kidney.
After oral administration of radiolabeled fosinopril, approximately half of the absorbed dose is excreted in the urine and the remainder is excreted in the feces. In two studies involving healthy subjects, the mean body clearance of intravenous fosinoprilat was between 26 and 39 mL/min. In healthy subjects, the terminal elimination half-life (t ½ ) of an intravenous dose of radiolabeled fosinoprilat is approximately 12 hour… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Fosinopril Sodium Tablets USP, 10 mg are white to off-white, flat, capsule shaped, uncoated tablets with notched sides at double bisect and debossed with ‘X’ and ‘77’ on either side of the score line on one side and plain on the other side. Bottles of 30 NDC 65862-471-30 Bottles of 90 NDC 65862-471-90 Bottles of 1,000 NDC 65862-471-99 Fosinopril Sodium Tablets USP, 20 mg are white to off-white, round, biconvex, uncoated tablets debossed with ‘X’ on one side and ‘84’ on the other side. Bottles of 30 NDC 65862-472-30 Bottles of 90 NDC 65862-472-90 Bottles of 1,000 NDC 65862-472-99 Fosinopril Sodium Tablets USP, 40 mg are white to off-white, round, biconvex, uncoated tablets debossed with ‘X’ on one side and ‘69’ on the other side.
Bottles of 30 NDC 65862-473-30 Bottles of 90 NDC 65862-473-90 Bottles of 1,000 NDC 65862-473-99 Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Protect from moisture by keeping bottle tightly closed. Distributed by: Aurobindo Pharma USA, Inc.
279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 038, India Revised: 07/2019
📋 Description ▾
DESCRIPTION Fosinopril sodium tablets, USP are the sodium salt of fosinopril, the ester prodrug of an angiotensin-converting enzyme (ACE) inhibitor, fosinoprilat. It contains a phosphinate group capable of specific binding to the active site of angiotensin-converting enzyme. Fosinopril sodium is designated chemically as: L-proline, 4-cyclohexyl-1-[[[2-methyl-1-(1-oxopropoxy)propoxy] (4-phenylbutyl) phosphinyl] acetyl]-, sodium salt, trans- .
Fosinopril sodium, USP is a white to almost white powder. It is soluble in water (100 mg/mL), methanol, and ethanol and slightly soluble in hexane. Its structural formula is: Its molecular formula is C 30 H 45 NNaO 7 P, and its molecular weight is 585.65.
Fosinopril sodium, USP is available for oral administration as 10 mg, 20 mg, and 40 mg tablets. Inactive ingredients include: anhydrous lactose, crospovidone, microcrystalline cellulose, povidone, and sodium stearyl fumarate. Chemical Structure
💬 Information for Patients ▾
Information for Patients Angioedema Angioedema, including laryngeal edema, can occur with treatment with ACE inhibitors, especially following the first dose. Patients should be advised to immediately report to their physician any signs or symptoms suggesting angioedema (e.g., swelling of face, eyes, lips, tongue, larynx, mucous membranes, and extremities; difficulty in swallowing or breathing; hoarseness) and to discontinue therapy. (See WARNINGS: Head and Neck Angioedema and Intestinal Angioedema and ADVERSE REACTIONS .) Symptomatic Hypotension Patients should be cautioned that lightheadedness can occur, especially during the first days of therapy, and it should be reported to a physician.
Patients should be told that if syncope occurs, fosinopril sodium should be discontinued until the physician has been consulted. All patients should be cautioned that inadequate fluid intake or excessive perspiration, diarrhea, or vomiting can lead to an excessive fall in blood pressure, with the same consequences of lightheadedness and possible syncope. Hyperkalemia Patients should be told not to use potassium supplements or salt substitutes containing potassium without consulting the physician.
Neutropenia Patients should be told to promptly report any indication of infection (e.g., sore throat, fever), which could be a sign of neutropenia. Pregnancy Female patients of childbearing age should be told about the consequences of exposure to fosinopril during pregnancy. Discuss treatment options with women planning to become pregnant.
Patients should be asked to report pregnancies to their physicians as soon as possible.
⚠️ Precautions ▾
PRECAUTIONS General Impaired Renal Function As a consequence of inhibiting the renin-angiotensin-aldosterone system, changes in renal function may be anticipated in susceptible individuals. In patients with severe congestive heart failure whose renal function may depend on the activity of the renin-angiotensin-aldosterone system, treatment with angiotensin-converting enzyme inhibitors, including fosinopril sodium tablets, may be associated with oliguria and/or progressive azotemia and (rarely) with acute renal failure and/or death.
In hypertensive patients with renal artery stenosis in a solitary kidney or bilateral renal artery stenosis, increases in blood urea nitrogen and serum creatinine may occur. Experience with another angiotensin-converting enzyme inhibitor suggests that these increases are usually reversible upon discontinuation of ACE inhibitor and/or diuretic therapy. In such patients, renal function should be monitored during the first few weeks of therapy.
Some hypertensive patients with no apparent preexisting renal vascular disease have developed increases in blood urea nitrogen and serum creatinine, usually minor and transient, especially when fosinopril sodium has been given concomitantly with a diuretic. This is more likely to occur in patients with preexisting renal impairment. Dosage reduction of fosinopril sodium and/or discontinuation of the diuretic may be required.
Evaluation of patients with hypertension or heart failure should always include assessment of renal function (see DOSAGE AND ADMINISTRATION ). Impaired renal function decreases total clearance of fosinoprilat and approximately doubles AUC. In general, no adjustment of dosing is needed.
However, patients with heart failure and severely reduced renal function may be more sensitive to the hemodynamic effects (e.g., hypotension) of ACE inhibition (see CLINICAL PHARMACOLOGY ). Hyperkalemia In clinical trials, hyperkalemia (serum potassium greater than 10% above the upper limit of normal) has occurred in approximately 2.6% of hypertensive patients receiving fosinopril sodium. In most cases, these were isolated values which resolved despite continued therapy.
In clinical trials, 0.1% of patients (2 patients) were discontinued from therapy due to an elevated serum potassium. Risk factors for the development of hyperkalemia include renal insufficiency, diabetes mellitus, and the concomitant use of potassium-sparing diuretics, potassium supplements, and/or potassium-containing salt substitutes, which should be used cautiously, if at all, with fosinopril sodium tablets (see PRECAUTIONS: Drug Interactions ). Cough Presumably due to the inhibition of the degradation of endogenous bradykinin, persistent nonproductive cough has been reported with all ACE inhibitors, always resolving after discontinuation of therapy.
ACE inhibitor-induced cough should be considered in the differential diagnosis of cough. Impaired Liver Function Since fosinopril is primarily metabolized by hepatic and gut wall esterases to its active moiety, fosinoprilat, patients with impaired liver function could develop elevated plasma levels of unchanged fosinopril. In a study in patients with alcoholic or biliary cirrhosis, the extent of hydrolysis was unaffected, although the rate was slowed.
In these patients, the apparent total body clearance of fosinoprilat was decreased and the plasma AUC approximately doubled. Surgery/Anesthesia In patients undergoing surgery or during anesthesia with agents that produce hypotension, fosinopril will block the angiotensin II formation that could otherwise occur secondary to compensatory renin release. Hypotension that occurs as a result of this mechanism can be corrected by volume expansion.
Hemodialysis Recent clinical observations have shown an association of hypersensitivity-like (anaphylactoid) reactions during hemodialysis with high-flux dialysis membranes (e.g., AN69) in patients receiving ACE inhibitors as medication. In these patients, consi… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Ingestion of 20 mg daily for 3 days resulted in detectable levels of fosinoprilat in breast milk. Fosinopril sodium should not be administered to nursing mothers.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility No evidence of a carcinogenic effect was found when fosinopril was given in the diet to mice and rats for up to 24 months at doses up to 400 mg/kg/day. On a body weight basis, the highest dose in mice and rats is about 250 times the maximum human dose of 80 mg, assuming a 50 kg subject. On a body surface area basis, in mice, this dose is 20 times the maximum human dose; in rats, this dose is 40 times the maximum human dose.
Male rats given the highest dose level had a slightly higher incidence of mesentery/omentum lipomas. Neither fosinopril nor the active fosinoprilat was mutagenic in the Ames microbial mutagen test, the mouse lymphoma forward mutation assay, or a mitotic gene conversion assay. Fosinopril was also not genotoxic in a mouse micronucleus test in vivo and a mouse bone marrow cytogenetic assay in vivo .
In the Chinese hamster ovary cell cytogenetic assay, fosinopril increased the frequency of chromosomal aberrations when tested without metabolic activation at a concentration that was toxic to the cells. However, there was no increase in chromosomal aberrations at lower drug concentrations without metabolic activation or at any concentration with metabolic activation. There were no adverse reproductive effects in male and female rats treated with 15 or 60 mg/kg daily.
On a body weight basis, the high dose of 60 mg/kg is about 38 times the maximum recommended human dose. On a body surface area basis, this dose is 6 times the maximum recommended human dose. There was no effect on pairing time prior to mating in rats until a daily dose of 240 mg/kg, a toxic dose, was given; at this dose, a slight increase in pairing time was observed.
On a body weight basis, this dose is 150 times the maximum recommended human dose. On a body surface area basis, this dose is 24 times the maximum recommended human dose.
📄 Package Label / Principal Display Panel ▾
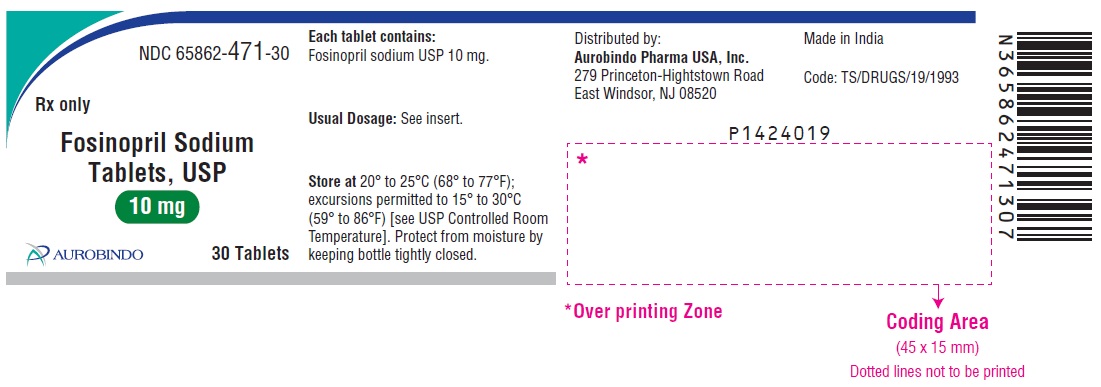
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 10 mg (30 Tablet Bottle) NDC 65862-471-30 Rx only Fosinopril Sodium Tablets, USP 10 mg 30 Tablets AUROBINDO PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 10 mg (30 Tablet Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 20 mg (30 Tablet Bottle) NDC 65862-472-30 Rx only Fosinopril Sodium Tablets, USP 20 mg AUROBINDO 30 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 20 mg (30 Tablet Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 40 mg (30 Tablet Bottle) NDC 65862-473-30 Rx only Fosinopril Sodium Tablets, USP 40 mg AUROBINDO 30 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 40 mg (30 Tablet Bottle)
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |