
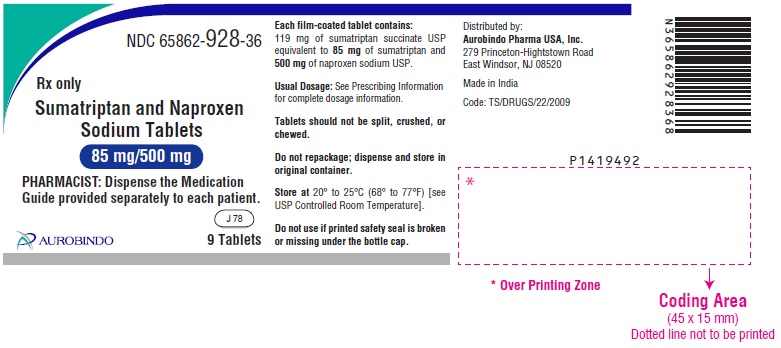
Sumatriptan and Naproxen Sodium 85 mg; 500 mg Tablet, Film Coated, 9-count — NDC 65862-928-36 (Billing 65862-0928-36)
This is a package of 9 tablets of Sumatriptan and Naproxen Sodium 85 mg; 500 mg Tablet, Film Coated from Aurobindo Pharma Limited, marketed since Feb 2018 and currently FDA-listed; retail pharmacies pay about $10.46 per tablet (NADAC). It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 063885
- GCN: 99597
- GPI-14 (Medi-Span): 67992002600320
- HICL (First Databank): 035534
- AHFS class code: 28:08.04.04
- RxCUI (RxNorm): 849450
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Serotonin-1b and Serotonin-1d Receptor Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $10.463 | $94.17 / 9 tablets |
| Medicaid paysCMS SDUD · 12 mo | $18.42 | $165.75 / 9 tablets |
| Medicare drug plans payPart D · Q2 2026 | $22.93 | $206.38 / 9 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 65862-0928-36 You're viewing this Main listing | 9 TABLET, FILM COATED in 1 BOTTLE | 2018-02-15 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Sumatriptan and Naproxen Sodium 85 mg/1; 500 mg 16714-0891-01 | NorthStar | 9 tablets | $10.463 | AB | Availability likely | — |
| Sumatriptan and Naproxen Sodium 85 mg/1; 500 mg 47335-0410-22 | Sun | 9 tablets | $10.463 | AB | Availability likely | — |
| Sumatriptan and Naproxen Sodium 85 mg/1; 500 mgthis 65862-0928-36 | Aurobindo | 9 tablets | $10.463 | AB | Availability likely | — |
| Sumatriptan Succinate and Naproxen Sodium 85 mg/1; 500 mg 44183-0850-09 | Currax | 9 tablets | $31.832 | AB | FDA listed | +204% |
| Treximet 85 mg/1; 500 mg 42847-0850-09 | Currax | 9 tablets | $133.918 | AB | FDA listed | +1180% |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII K679OBS311
Carboxymethylcellulose sodium is a plant-derived thickening agent made from cellulose. In medicines, it acts as a binder to hold ingredients together, a disintegrant to help the tablet break apart, or a thickener in liquids.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII LX22YL083G
A simple sugar derived from corn or other sources. It acts as a filler to give the medicine bulk and volume, and as a sweetener to improve taste in oral medications.
-
UNII 1DI56QDM62
A natural fatty substance from soybeans that helps mix oil and water-based ingredients together. It acts as an emulsifier and lubricant in medicines to improve texture and help the product break down properly in your body.
-
UNII 7CVR7L4A2D
A starch-derived carbohydrate produced by breaking down corn, potato, or tapioca starch. It functions as a filler and binder to give the medicine bulk and texture, and sometimes as a mild sweetener or texture enhancer in powders and tablets.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII RDH86HJV5Z
Povidone K90 is a synthetic polymer made from a chemical called vinyl pyrrolidone. It acts as a binder to hold pill ingredients together and as a dispersant to help the medicine break down and dissolve properly in your body.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 8MDF5V39QO
A white powder form of baking soda that acts as a buffer and pH regulator in medicines. It helps maintain the right acid-base balance and may aid tablet disintegration.
-
UNII 7CV7WJK4UI
Sodium stearyl fumarate is a synthetic compound made from stearyl alcohol and fumaric acid. It acts as a lubricant and glidant in tablets and capsules, helping ingredients flow smoothly during manufacturing and preventing sticking.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
13 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: RISK OF SERIOUS CARDIOVASCULAR AND GASTROINTESTINAL EVENTS Cardiovascular Thrombotic Events Nonsteroidal anti-inflammatory drugs (NSAIDs) cause an increased risk of serious cardiovascular thrombotic events, including myocardial infarction and stroke, which can be fatal. This risk may occur early in treatment and may increase with duration of use [see Warnings and Precautions (5.1) ] . Sumatriptan and naproxen sodium is contraindicated in the setting of coronary artery bypass graft (CABG) surgery [see Contraindications (4) Warnings and Precautions (5.1) ] .
Gastrointestinal Bleeding, Ulceration, and Perforation NSAIDs cause an increased risk of serious gastrointestinal (GI) adverse events including bleeding, ulceration, and perforation of the stomach or intestines, which can be fatal. These events can occur at any time during use and without warning symptoms. Elderly patients and patients with a prior history of peptic ulcer disease and/or GI bleeding are at greater risk for serious GI events [see Warnings and Precautions (5.2) ] .
WARNING: RISK OF SERIOUS CARDIOVASCULAR AND GASTROINTESTINAL EVENTS See full prescribing information for complete boxed warning. Nonsteroidal anti-inflammatory drugs (NSAIDs) cause an increased risk of serious cardiovascular thrombotic events, including myocardial infarction and stroke, which can be fatal. This risk may occur early in treatment and may increase with duration of use.
( 5.1 ) Sumatriptan and naproxen sodium is contraindicated in the setting of coronary artery bypass graft (CABG) surgery ( 4 , 5.1 ) NSAIDs cause an increased risk of serious gastrointestinal (GI) adverse events including bleeding, ulceration, and perforation of the stomach or intestines, which can be fatal. These events can occur at any time during use and without warning symptoms. Elderly patients and patients with a prior history of peptic ulcer disease and/or GI bleeding are at greater risk for serious GI events.
( 5.2 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Sumatriptan and naproxen sodium tablets are indicated for the acute treatment of migraine with or without aura in adults and pediatric patients 12 years of age and older. Limitations of Use: Use only if a clear diagnosis of migraine headache has been established. If a patient has no response to the first migraine attack treated with sumatriptan and naproxen sodium tablets, reconsider the diagnosis of migraine before sumatriptan and naproxen sodium tablets are administered to treat any subsequent attacks.
Sumatriptan and naproxen sodium tablets are not indicated for the prevention of migraine attacks. Safety and effectiveness of sumatriptan and naproxen sodium tablets have not been established for cluster headache. Sumatriptan and naproxen sodium tablets are a combination of sumatriptan, a serotonin (5-HT) 1b/1d receptor agonist (triptan), and naproxen sodium, a non-steroidal anti-inflammatory drug, indicated for the acute treatment of migraine with or without aura in adults and pediatric patients 12 years of age and older.
(1) Limitations of Use: Use only if a clear diagnosis of migraine headache has been established. (1) Not indicated for the prophylactic therapy of migraine attacks. (1) Not indicated for the treatment of cluster headache.
(1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Adults Recommended dosage: 1 tablet of 85 mg/500 mg. (2.1) Maximum dosage in a 24-hour period: 2 tablets of 85 mg/500 mg; separate doses by at least 2 hours. (2.1) Pediatric Patients 12 to 17 years of Age Maximum dosage in a 24-hour period: 1 tablet of 85 mg/500 mg.
2.1Dosage in Adults The recommended dosage for adults is 1 tablet of sumatriptan and naproxen sodium 85 mg/500 mg. Sumatriptan and naproxen sodium tablets 85 mg/500 mg contain a dose of sumatriptan higher than the lowest effective dose. The choice of the dose of sumatriptan, and of the use of a fixed combination such as in sumatriptan and naproxen sodium tablets 85 mg/500 mg should be made on an individual basis, weighing the possible benefit of a higher dose of sumatriptan with the potential for a greater risk of adverse reactions.
The maximum recommended dosage in a 24-hour period is 2 tablets, taken at least 2 hours apart. The safety of treating an average of more than 5 migraine headaches in adults in a 30-day period has not been established. Use the lowest effective dosage for the shortest duration consistent with individual patient treatment goals [see Warnings and Precautions (5) ] .
2.2Dosage in Pediatric Patients 12 to 17 Years of Age The maximum recommended dosage in a 24-hour period is 1 tablet of sumatriptan and naproxen sodium 85 mg/500 mg. The safety of treating an average of more than 2 migraine headaches in pediatric patients in a 30-day period has not been established. Use the lowest effective dosage for the shortest duration consistent with individual patient treatment goals [see Warnings and Precautions (5) ] .
2.3Dosing in Patients with Hepatic Impairment Sumatriptan and naproxen sodium tablets are contraindicated in patients with severe hepatic impairment [see Contraindications (4) , Use in Specific Populations (8.7) , Clinical Pharmacology (12.3) ] . Use the lowest effective dosage for the shortest duration consistent with individual patient treatment goals [see Warnings and Precautions (5) ] .
2.4Administration Information Sumatriptan and naproxen sodium tablets may be administered with or without food. Tablets should not be split, crushed, or chewed.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Sumatriptan and Naproxen Sodium Tablets, 85 mg/500 mg are white to off-white, modified capsule shaped, film-coated, matted finish tablets debossed with “J78” on one side and plain on the other side. Tablets: 85 mg sumatriptan/500 mg naproxen sodium (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Sumatriptan and naproxen sodium tablets are contraindicated in the following patients: Ischemic coronary artery disease (CAD) (angina pectoris, history of myocardial infarction, or documented silent ischemia) or coronary artery vasospasm, including Prinzmetal’s angina [see Warnings and Precautions (5.1) ]. In the setting of coronary artery bypass graft (CABG) surgery [see Warnings and Precautions (5.1) ]. Wolff-Parkinson-White syndrome or arrhythmias associated with other cardiac accessory conduction pathway disorders [see Warnings and Precautions (5.3) ] .
History of stroke or transient ischemic attack (TIA) or history of hemiplegic or basilar migraine because these patients are at a higher risk of stroke [s ee Warnings and Precautions (5.5) ]. Peripheral vascular disease [see Warnings and Precautions (5.6) ]. Ischemic bowel disease [see Warnings and Precautions (5.6) ].
Uncontrolled hypertension [see Warnings and Precautions (5.8) ]. Recent use (i.e., within 24 hours) of ergotamine-containing medication, ergot-type medication (such as dihydroergotamine or methysergide), or another 5-hydroxytryptamine 1 (5-HT 1 ) agonist [see Drug Interactions (7) ]. Concurrent administration of a monoamine oxidase (MAO)-A inhibitor or recent (within 2 weeks) use of an MAO-A inhibitor [see Drug Interactions (7) , Clinical Pharmacology (12.3) ].
History of asthma, urticaria, or allergic-type reactions after taking aspirin or other NSAIDs. Severe, sometimes fatal, anaphylactic reactions to NSAIDs have been reported in such patients [see Warnings and Precautions (5.13 , 5.14 , 5.18) ]. Known hypersensitivity (e.g., anaphylactic reactions, angioedema, and serious skin reactions) to sumatriptan, naproxen, or any components of sumatriptan and naproxen sodium tablets [see Warnings and Precautions (5.14) ].
Severe hepatic impairment [see Warnings and Precautions (5.7) , Use in Specific Populations (8.7) , Clinical Pharmacology (12.3) ]. History of coronary artery disease or coronary vasospasm. ( 4 ) In the setting of CABG surgery.
( 4 ) Wolff-Parkinson-White syndrome or other cardiac accessory conduction pathway disorders. ( 4 ) History of stroke, transient ischemic attack, or hemiplegic or basilar migraine. ( 4 ) Peripheral vascular disease.
( 4 ) Ischemic bowel disease. ( 4 ) Uncontrolled hypertension. ( 4 ) Recent (within 24 hours) use of another 5-HT 1 agonist (e.g., another triptan) or of ergotamine-containing medication.
( 4 ) Concurrent or recent (past 2 weeks) use of monoamine oxidase-A inhibitor. ( 4 ) History of asthma, urticaria, other allergic type reactions, rhinitis, or nasal polyps syndrome after taking aspirin or other NSAID/analgesic drugs. ( 4 ) Known hypersensitivity to sumatriptan, naproxen, or any components of sumatriptan and naproxen sodium (angioedema and anaphylaxis seen).
( 4 ) Severe hepatic impairment. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Cardiovascular Thrombotic Events: Perform cardiac evaluation in patients with cardiovascular risk factors. ( 5.1 ) Arrhythmias: Discontinue sumatriptan and naproxen sodium if occurs. ( 5.3 ) Chest, Throat, Neck, and/or Jaw Pain/Tightness/Pressure: Generally not associated with myocardial ischemia; evaluate for coronary artery disease in patients at high risk.
( 5.4 ) Cerebrovascular Events: Discontinue sumatriptan and naproxen sodium if occurs. ( 5.5 ) Other Vasospasm Reactions: Discontinue sumatriptan and naproxen sodium if non-coronary vasospastic reaction occurs. ( 5.6 ) Hepatotoxicity: Inform patients of warning signs and symptoms of hepatotoxicity.
Discontinue if abnormal liver tests persist or worsen or if clinical signs and symptoms of liver disease develop. ( 5.7 ) Hypertension: Patients taking some antihypertensive medications may have impaired response to these therapies when taking NSAIDs. Monitor blood pressure.
( 5.8 ) Heart Failure and Edema: Avoid use of sumatriptan and naproxen sodium in patients with severe heart failure unless benefits are expected to outweigh risk of worsening heart failure. ( 5.9 ) Medication Overuse Headache: Detoxification may be necessary. ( 5.10 ) Serotonin Syndrome: Discontinue sumatriptan and naproxen sodium if occurs.
( 5.11 ) Renal Toxicity and Hyperkalemia: Monitor renal function in patients with renal or hepatic impairment, heart failure, dehydration, or hypovolemia. Avoid use of sumatriptan and naproxen sodium in patients with advanced renal disease. ( 5.12 ) Anaphylactic Reactions: Sumatriptan and naproxen sodium should not be given to patients with the aspirin triad.
Seek emergency help if an anaphylactic reaction occurs. ( 5.13 ) Serious Skin Reactions: Discontinue sumatriptan and naproxen sodium at first sign of rash or other signs of hypersensitivity. ( 5.14 ) Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS): Discontinue and evaluate clinically.
( 5.15 ) Fetal Toxicity: Limit use of NSAIDs, including sumatriptan and naproxen sodium, between about 20 to 30 weeks in pregnancy due to the risk of oligohydramnios/fetal renal dysfunction. Avoid use of NSAIDs in women at about 30 weeks gestation and later in pregnancy due to the risks of oligohydramnios/fetal renal dysfunction and premature closure of the fetal ductus arteriosus. ( 5.16 , 8.1 ) Hematologic Toxicity: Monitor hemoglobin or hematocrit in patients with any signs or symptoms of anemia.
( 5.17 ) Exacerbation of Asthma Related to Aspirin Sensitivity: Sumatriptan and naproxen sodium is contraindicated in patients with aspirin-sensitive asthma. Monitor patients with preexisting asthma (without aspirin sensitivity). ( 5.18 )
5.1Cardiovascular Thrombotic Events The use of sumatriptan and naproxen sodium is contraindicated in patients with ischemic or vasospastic coronary artery disease (CAD) and in the setting of coronary artery bypass graft (CABG) surgery due to increased risk of serious cardiovascular events with sumatriptan and NSAIDS [see Contraindications (4) ] . Cardiovascular Events with Sumatriptan There have been rare reports of serious cardiac adverse reactions, including acute myocardial infarction, occurring within a few hours following administration of sumatriptan.
Some of these reactions occurred in patients without known CAD. Sumatriptan and naproxen sodium may cause coronary artery vasospasm (Prinzmetal’s angina), even in patients without a history of CAD. Cardiovascular Thrombotic Events with Nonsteroidal Anti-inflammatory Drugs Clinical trials of several COX-2 selective and nonselective NSAIDs of up to three years duration have shown an increased risk of serious cardiovascular (CV) thrombotic events, including myocardial infarction (MI) and stroke, which can be fatal.
Based on available data, it is unclear that the risk for CV thrombotic events is similar for all NSAIDs. The relative increase in serious CV thrombotic events over baseline conferred by NSAID use appear… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described below and elsewhere in labeling: Cardiovascular Thrombotic Events [see Warnings and Precautions (5.1) ] GI Bleeding, Ulceration and Perforation [see Warnings and Precautions (5.2) ] Arrhythmias [see Warnings and Precautions (5.3) ] Chest, Throat, Neck, and/or Jaw Pain/Tightness/Pressure [see Warnings and Precautions (5.4) ] Cerebrovascular Events [see Warnings and Precautions (5.5) ] Other Vasospasm Reactions [see Warnings and Precautions (5.6) ] Hepatotoxicity [see Warnings and Precautions (5.7) ] Hypertension [see Warnings and Precautions (5.8) ] Heart Failure and Edema [see Warnings and Precautions (5.9) ] Medication Overuse Headache [see Warnings and Precautions (5.10) ] Serotonin Syndrome [see Warnings and Precautions (5.11) ] Renal Toxicity and Hyperkalemia [see Warnings and Precautions (5.12) ] Anaphylactic Reactions [see Warnings and Precautions (5.13) ] Serious Skin Reactions [see Warnings and Precautions (5.14) ] Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS) [see Warnings and Precautions (5.15) ] Hematological Toxicity [see Warnings and Precautions (5.17) ] Exacerbation Asthma Related to Aspirin Sensitivity [see Warnings and Precautions (5.18) ] Seizures [see Warnings and Precautions (5.19) ] The most common adverse reactions (incidence ≥2%) were: Adults: Dizziness, somnolence, nausea, chest discomfort/chest pain, neck/throat/jaw pain/tightness/pressure, paresthesia, dyspepsia, dry mouth.
(6.1) Pediatrics: Hot flush (i.e., hot flash[es]) and muscle tightness. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adults The adverse reactions reported below are specific to the clinical trials with sumatriptan and naproxen sodium 85/500 mg. See also the full prescribing information for naproxen and sumatriptan products.
Table 1 lists adverse reactions that occurred in 2 placebo-controlled clinical trials (Study 1 and 2) in adult patients who received 1 dose of study drug. Only adverse reactions that occurred at a frequency of 2% or more in any group treated with sumatriptan and naproxen sodium 85/500 mg and that occurred at a frequency greater than the placebo group are included in Table 1. Table 1.
Adverse Reactions in Pooled Placebo-Controlled Trials in Adult Patients with Migraine Adverse Reactions Sumatriptan and Naproxen Sodium Tablets 85/500 mg % (n = 737) Placebo % (n = 752) Sumatriptan 85 mg % (n = 735) Naproxen Sodium 500 mg % (n = 732) Nervous system disorders Dizziness 4 2 2 2 Somnolence 3 2 2 2 Paresthesia 2 <1 2 <1 Gastrointestinal disorders Nausea 3 1 3 <1 Dyspepsia 2 1 2 1 Dry mouth 2 1 2 <1 Pain and other pressure sensations Chest discomfort/chest pain 3 <1 2 1 Neck/throat/jaw pain/tightness/pressure 3 1 3 1 The incidence of adverse reactions in controlled clinical trials was not affected by gender or age of the patients.
There were insufficient data to assess the impact of race on the incidence of adverse reactions. Pediatric Patients 12 to 17 Years of Age In a placebo controlled clinical trial that evaluated pediatric patients 12 to 17 years of age who received 1 dose of sumatriptan and naproxen sodium 10/60 mg, 30/180 mg, or 85/500 mg, adverse reactions occurred in 13% of patients who received 10/60 mg, 9% of patients who received 30/180 mg, 13% who received 85/500 mg, and 8% who received placebo. No patients who received sumatriptan and naproxen sodium experienced adverse reactions leading to withdrawal from the trial.
The incidence of adverse reactions in pediatric patients 12 to 17 years of age was comparable across all 3 do… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Drugs that Interfere with Hemostasis (e.g. warfarin, aspirin, SSRIs/SNRIs): Monitor patients for bleeding who are concomitantly taking sumatriptan and naproxen sodium with drugs that interfere with hemostasis. Concomitant use of sumatriptan and naproxen sodium and analgesic doses of aspirin is not generally recommended. ( 7.1 ) ACE Inhibitors and ARBs: Concomitant use with sumatriptan and naproxen sodium in elderly, volume depleted, or those with renal impairment may result in deterioration of renal function.
In such high risk patients, monitor for signs of worsening renal function. ( 7.1 ) Diuretics: NSAIDs can reduce natriuretic effect of loop and thiazide diuretics. Monitor patients to assure diuretic efficacy including antihypertensive effects.
( 7.1 ) Digoxin: Concomitant use with sumatriptan and naproxen sodium can increase serum concentration and prolong half-life of digoxin. Monitor serum digoxin levels. ( 7.1 ) Lithium: Increases lithium plasma levels.
( 7.1 ) Methotrexate: Increases methotrexate plasma levels. ( 7.1 )
7.1Clinically Significant Drug Interactions with Sumatriptan and Naproxen Sodium See Table 3 for clinically significant drug interactions with NSAIDs or Sumatriptan. Table 3. Clinically Significant Drug Interactions with Naproxen or Sumatriptan Ergot-Containing Drugs Clinical Impact: Ergot-containing drugs have been reported to cause prolonged vasospastic reactions.
Intervention: Because these effects may be additive, coadministration of sumatriptan and naproxen sodium and ergotamine-containing or ergot-type medications (like dihydroergotamine or methysergide) within 24 hours of each other is contraindicated. Monoamine Oxidase-A Inhibitors Clinical Impact: MAO-A inhibitors increase systemic exposure of orally administered sumatriptan by 7-fold. Intervention: The use of sumatriptan and naproxen sodium in patients receiving MAO-A inhibitors is contraindicated.
Other 5-HT 1 Agonists Clinical Impact: 5-HT 1 agonist drugs can cause vasospastic effects. Intervention: Because these effects may be additive, coadministration of sumatriptan and naproxen sodium and other 5 HT 1 agonists (e.g., triptans) within 24 hours of each other is contraindicated. Drugs That Interfere with Hemostasis Clinical Impact: Naproxen and anticoagulants such as warfarin have a synergistic effect on bleeding.
The concomitant use of naproxen and anticoagulants have an increased risk of serious bleeding compared to the use of either drug alone. Serotonin release by platelets plays an important role in hemostasis. Case-control and cohort epidemiological studies showed that concomitant use of drugs that interfere with serotonin reuptake and an NSAID may potentiate the risk of bleeding more than an NSAID alone.
Intervention: Monitor patients with concomitant use of sumatriptan and naproxen sodium with anticoagulants (e.g., warfarin), antiplatelet agents (e.g., aspirin), selective serotonin reuptake inhibitors (SSRIs), and serotonin norepinephrine reuptake inhibitors (SNRIs) for signs of bleeding [see Warnings and Precautions (5.17) ]. Aspirin Clinical Impact: A pharmacodynamic (PD) study has demonstrated an interaction in which lower dose naproxen (220 mg/day or 220 mg twice daily) interfered with the antiplatelet effect of low-dose immediate-release aspirin, with the interaction most marked during the washout period of naproxen [see Clinical Pharmacology (12.2) ] .
There is reason to expect that the interaction would be present with prescription doses of naproxen or with enteric-coated low-dose aspirin; however, the peak interference with aspirin function may be later than observed in the PD study due to the longer washout period. Controlled clinical studies showed that the concomitant use of NSAIDs and analgesic doses of aspirin does not produce any greater therapeutic effect than the use of NSAIDs alone. In a clinical study, the concomitant use of an NSAID and aspirin was associated with a significantly increased inc… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Infertility: NSAIDs are associated with reversible infertility. Consider withdrawal of sumatriptan and naproxen sodium in women who have difficulties conceiving ( 8.3 )
8.1Pregnancy Risk Summary Use of NSAIDs, including sumatriptan and naproxen sodium, can cause premature closure of the fetal ductus arteriosus and fetal renal dysfunction leading to oligohydramnios and, in some cases, neonatal renal impairment. Because of these risks, limit dose and duration of sumatriptan and naproxen sodium use between about 20 and 30 weeks of gestation, and avoid sumatriptan and naproxen sodium use at about 30 weeks of gestation and later in pregnancy (see Clinical Considerations, Data) . Premature Closure of Fetal Ductus Arteriosus Use of NSAIDs, including sumatriptan and naproxen sodium, at about 30 weeks gestation or later in pregnancy increases the risk of premature closure of the fetal ductus arteriosus.
Oligohydramnios/Neonatal Renal Impairment Use of NSAIDs at about 20 weeks gestation or later in pregnancy has been associated with cases of fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment. Data from observational studies regarding other potential embryofetal risks of NSAID use in women in the first or second trimesters of pregnancy are inconclusive. Data from a prospective pregnancy exposure registry and epidemiological studies of pregnant women have not detected an increased frequency of birth defects or a consistent pattern of birth defects among women exposed to sumatriptan compared with the general population ( see Human Data ).
In animal studies, administration of sumatriptan and naproxen, alone or in combination, during pregnancy resulted in developmental toxicity (increased incidences of fetal malformations, embryofetal and pup mortality, decreased embryofetal growth) at clinically relevant doses ( see Animal Data ). Based on animal data, prostaglandins have been shown to have an important role in endometrial vascular permeability, blastocyst implantation, and decidualization. In animal studies, administration of prostaglandin synthesis inhibitors such as naproxen sodium resulted in increased pre- and post-implantation loss.
Prostaglandins also have been shown to have an important role in fetal kidney development. In published animal studies, prostaglandin synthesis inhibitors have been reported to impair kidney development when administered at clinically relevant doses. All pregnancies have a background risk of birth defects, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. The reported rate of major birth defects among deliveries to women with migraine ranged from 2.2% to 2.9% and the reported rate of miscarriage was 17%, which were similar to rates reported in women without migraine. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Several studies have suggested that women with migraine may be at increased risk of preeclampsia and gestational hypertension during pregnancy.
Fetal/Neonatal Adverse Reactions Premature Closure of Fetal Ductus Arteriosus: Avoid use of NSAIDs in women at about 30 weeks gestation and later in pregnancy, because NSAIDs, including sumatriptan and naproxen sodium, can cause premature closure of the fetal ductus arteriosus ( see Data ). Oligohydramnios/Neonatal Renal Impairment: If an NSAID is necessary at about 20 weeks gestation or later in pregnancy, limit the use to the lowest effective dose and shortest duration possible. If sumatriptan and naproxen sodium treatment extends beyond 48 hours, consider monitoring with ultrasound for oligohydramnios.
If oligohydramnios occurs, discontinue sumatriptan and naproxen sodium and follow up according to clinical practice ( see Data ). Labor or Delivery There are no studies on the effects of napr… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Use of NSAIDs, including sumatriptan and naproxen sodium, can cause premature closure of the fetal ductus arteriosus and fetal renal dysfunction leading to oligohydramnios and, in some cases, neonatal renal impairment. Because of these risks, limit dose and duration of sumatriptan and naproxen sodium use between about 20 and 30 weeks of gestation, and avoid sumatriptan and naproxen sodium use at about 30 weeks of gestation and later in pregnancy (see Clinical Considerations, Data) . Premature Closure of Fetal Ductus Arteriosus Use of NSAIDs, including sumatriptan and naproxen sodium, at about 30 weeks gestation or later in pregnancy increases the risk of premature closure of the fetal ductus arteriosus.
Oligohydramnios/Neonatal Renal Impairment Use of NSAIDs at about 20 weeks gestation or later in pregnancy has been associated with cases of fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment. Data from observational studies regarding other potential embryofetal risks of NSAID use in women in the first or second trimesters of pregnancy are inconclusive. Data from a prospective pregnancy exposure registry and epidemiological studies of pregnant women have not detected an increased frequency of birth defects or a consistent pattern of birth defects among women exposed to sumatriptan compared with the general population ( see Human Data ).
In animal studies, administration of sumatriptan and naproxen, alone or in combination, during pregnancy resulted in developmental toxicity (increased incidences of fetal malformations, embryofetal and pup mortality, decreased embryofetal growth) at clinically relevant doses ( see Animal Data ). Based on animal data, prostaglandins have been shown to have an important role in endometrial vascular permeability, blastocyst implantation, and decidualization. In animal studies, administration of prostaglandin synthesis inhibitors such as naproxen sodium resulted in increased pre- and post-implantation loss.
Prostaglandins also have been shown to have an important role in fetal kidney development. In published animal studies, prostaglandin synthesis inhibitors have been reported to impair kidney development when administered at clinically relevant doses. All pregnancies have a background risk of birth defects, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. The reported rate of major birth defects among deliveries to women with migraine ranged from 2.2% to 2.9% and the reported rate of miscarriage was 17%, which were similar to rates reported in women without migraine. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Several studies have suggested that women with migraine may be at increased risk of preeclampsia and gestational hypertension during pregnancy.
Fetal/Neonatal Adverse Reactions Premature Closure of Fetal Ductus Arteriosus: Avoid use of NSAIDs in women at about 30 weeks gestation and later in pregnancy, because NSAIDs, including sumatriptan and naproxen sodium, can cause premature closure of the fetal ductus arteriosus ( see Data ). Oligohydramnios/Neonatal Renal Impairment: If an NSAID is necessary at about 20 weeks gestation or later in pregnancy, limit the use to the lowest effective dose and shortest duration possible. If sumatriptan and naproxen sodium treatment extends beyond 48 hours, consider monitoring with ultrasound for oligohydramnios.
If oligohydramnios occurs, discontinue sumatriptan and naproxen sodium and follow up according to clinical practice ( see Data ). Labor or Delivery There are no studies on the effects of naproxen tablets during labor or delivery. In animal studies, NSAIDS, including naproxen, inhibit prostaglandin synthesis, cause delayed parturition, and increase the incidence of stillbirth.
Data Human… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of sumatriptan and naproxen sodium in pediatric patients under 12 years of age have not been established. The safety and efficacy of sumatriptan and naproxen sodium for the acute treatment of migraine in pediatric patients 12 to 17 years of age was established in a double-blind, placebo-controlled trial [see Adverse Reactions (6.1) and Clinical Studies (14.2) ].
🧓 Geriatric Use ▾
8.5Geriatric Use Elderly patients, compared to younger patients, are at greater risk for NSAID-associated serious cardiovascular, gastrointestinal, and/or renal adverse reactions. Sumatriptan and naproxen sodium is not recommended for use in elderly patients who have decreased renal function, higher risk for unrecognized CAD, and increases in blood pressure that may be more pronounced in the elderly [see Warnings and Precautions (5.1 , 5.2 , 5.3 , 5.8, 5.12) and Clinical Pharmacology (12.3) ]. A cardiovascular evaluation is recommended for geriatric patients who have other cardiovascular risk factors (e.g., diabetes, hypertension, smoking, obesity, strong family history of CAD) prior to receiving sumatriptan and naproxen sodium [see Warnings and Precautions (5.1) ].
🆘 Overdosage ▾
10 OVERDOSAGE Patients (N = 670) have received single oral doses of 140 to 300 mg of sumatriptan without significant adverse effects. Volunteers (N = 174) have received single oral doses of 140 to 400 mg without serious adverse events. Overdose of sumatriptan in animals has been fatal and has been heralded by convulsions, tremor, paralysis, inactivity, ptosis, erythema of the extremities, abnormal respiration, cyanosis, ataxia, mydriasis, salivation, and lacrimation.
Symptoms following acute NSAID overdosages have been typically limited to lethargy, drowsiness, nausea, vomiting and epigastric pain. Gastrointestinal bleeding has occurred. Hypertension, acute renal failure, respiratory depression, and coma have occurred, but were rare [see Warnings and Precautions (5.1 , 5.2) ] .
Manage patients with symptomatic and supportive care following an NSAID overdosage. There are no specific antidotes. Consider emesis and/or activated charcoal (60 to 100 grams in adults, 1 to 2 grams per kg of body weight in pediatric patients) and/or osmotic cathartic in symptomatic patients seen within four hours of ingestion or in patients with a large overdosage (5 to 10 times the recommended dosage).
Hemodialysis does not decrease the plasma concentration of naproxen because of the high degree of its protein binding. It is unknown what effect hemodialysis or peritoneal dialysis has on the serum concentrations of sumatriptan. Forced diuresis, alkalinization of urine, hemodialysis, or hemoperfusion may not be useful due to high protein binding.
For additional information about overdosage treatment contact a poison control center (1-800-222-1222).
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Sumatriptan and naproxen sodium tablets contain sumatriptan and naproxen. Sumatriptan binds with high affinity to cloned 5-HT 1B/1D receptors. Sumatriptan presumably exerts its therapeutic effects in the treatment of migraine headache through agonist effects at the 5-HT 1B/1D receptors on intracranial blood vessels and sensory nerves of the trigeminal system, which result in cranial vessel constriction and inhibition of neuropeptide release.
Sumatriptan and naproxen sodium has analgesic, anti-inflammatory, and antipyretic properties. The mechanism of action of sumatriptan and naproxen sodium, like that of other NSAIDs, is not completely understood but involves inhibition of cyclooxygenase (COX-1 and COX-2). Naproxen is a potent inhibitor of prostaglandin synthesis in vitro .
Naproxen concentrations reached during therapy have produced in vivo effects. Prostaglandins sensitize afferent nerves and potentiate the action of bradykinin in inducing pain in animal models. Prostaglandins are mediators of inflammation.
Because naproxen is an inhibitor of prostaglandin synthesis, its mode of action may be due to a decrease of prostaglandins in peripheral tissues.
12.2Pharmacodynamics In a healthy volunteer study, 10 days of concomitant administration of naproxen 220 mg once-daily with low-dose immediate-release aspirin (81 mg) showed an interaction with the antiplatelet activity of aspirin as measured by % serum thromboxane B 2 inhibition at 24 hours following the day 10 dose [98.7% (aspirin alone) vs 93.1% (naproxen and aspirin)]. The interaction was observed even following discontinuation of naproxen on day 11 (while aspirin dose was continued) but normalized by day 13. In the same study, the interaction was greater when naproxen was administered 30 minutes prior to aspirin [98.7% vs 87.7%] and minimal when aspirin was administered 30 minutes prior to naproxen [98.7% vs 95.4%].
Following administration of naproxen 220 mg twice-daily with low-dose immediate–release aspirin (first naproxen dose given 30 minutes prior to aspirin), the interaction was minimal at 24 h following day 10 dose [98.7% vs 95.7%]. However, the interaction was more prominent after discontinuation of naproxen (washout) on day 11 [98.7% vs 84.3%] and did not normalize completely by day 13 [98.5% vs 90.7%] [see Drug Interactions (7.1) ] . Blood Pressure In a randomized, double-blind, parallel group, active control trial, sumatriptan and naproxen sodium 85/500 mg administered intermittently over 6 months did not increase blood pressure in a normotensive adult population (n = 122).
However, significant elevation in blood pressure has been reported with 5-HT 1 agonists and NSAIDs in patients with and without a history of hypertension.
12.3Pharmacokinetics Absorption and Bioavailability Sumatriptan, when given as sumatriptan and naproxen sodium 85/500 mg, has a mean C max similar to that of sumatriptan succinate 100 mg tablets alone. The median T max of sumatriptan, when given as sumatriptan and naproxen sodium 85/500 mg, was 1 hour (range: 0.3 to 4.0 hours), which is slightly different compared with sumatriptan succinate 100 mg tablets (median T max of 1.5 hours). Naproxen, when given as sumatriptan and naproxen sodium 85/500 mg, has a C max which is approximately 36% lower than naproxen sodium 550 mg tablets and a median T max of 5 hours (range: 0.3 to 12 hours), which is approximately 4 hours later than from naproxen sodium tablets 550 mg.
AUC values for sumatriptan and for naproxen are similar for sumatriptan and naproxen sodium 85/500 mg compared with sumatriptan succinate 100 mg tablets or naproxen sodium 550 mg tablets, respectively. In a crossover trial in 16 subjects, the pharmacokinetics of both components administered as sumatriptan and naproxen sodium 85/500 mg were similar during a migraine attack and during a migraine-free period. Bioavailability of sumatriptan is approximately 15%, primarily due to presys… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Sumatriptan and naproxen sodium tablets contain sumatriptan and naproxen. Sumatriptan binds with high affinity to cloned 5-HT 1B/1D receptors. Sumatriptan presumably exerts its therapeutic effects in the treatment of migraine headache through agonist effects at the 5-HT 1B/1D receptors on intracranial blood vessels and sensory nerves of the trigeminal system, which result in cranial vessel constriction and inhibition of neuropeptide release.
Sumatriptan and naproxen sodium has analgesic, anti-inflammatory, and antipyretic properties. The mechanism of action of sumatriptan and naproxen sodium, like that of other NSAIDs, is not completely understood but involves inhibition of cyclooxygenase (COX-1 and COX-2). Naproxen is a potent inhibitor of prostaglandin synthesis in vitro .
Naproxen concentrations reached during therapy have produced in vivo effects. Prostaglandins sensitize afferent nerves and potentiate the action of bradykinin in inducing pain in animal models. Prostaglandins are mediators of inflammation.
Because naproxen is an inhibitor of prostaglandin synthesis, its mode of action may be due to a decrease of prostaglandins in peripheral tissues.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Sumatriptan and Naproxen Sodium Tablets, 85 mg/500 mg contain 119 mg of sumatriptan succinate USP equivalent to 85 mg of sumatriptan and 500 mg of naproxen sodium USP and is supplied as white to off-white, modified capsule shaped, film-coated, matted finish tablets debossed with “J78” on one side and plain on the other side. Bottles of 9 NDC 65862-928-36 Store at 20º to 25°C (68º to 77°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Sumatriptan and naproxen sodium tablets contain sumatriptan (as the succinate), a selective 5-hydroxytryptamine 1 (5-HT 1 ) receptor subtype agonist, and naproxen sodium, a member of the arylacetic acid group of NSAIDs. Sumatriptan succinate is chemically designated as 3-[2-(dimethylamino)ethyl]-N-methyl-indole-5-methanesulfonamide succinate (1:1), and it has the following structure: The molecular formula is C 14 H 21 N 3 O 2 S.C 4 H 6 O 4 , representing a molecular weight of 413.5. Sumatriptan succinate USP is a white or almost white powder that is freely soluble in water, sparingly soluble in methanol, practically insoluble in methylene chloride.
Naproxen sodium is chemically designated as (S)-6-methoxy-α-methyl-2-naphthaleneacetic acid, sodium salt, and it has the following structure: The molecular formula is C 14 H 13 NaO 3 , representing a molecular weight of 252.23. Naproxen sodium USP is a white to creamy crystalline powder, sparingly soluble in water, in methanol and in alcohol, practically insoluble in chloroform, in acetone and in toluene. Each sumatriptan and naproxen sodium 85 mg/500 mg tablet for oral administration contains 119 mg of sumatriptan succinate USP equivalent to 85 mg of sumatriptan and 500 mg of naproxen sodium USP.
Each tablet also contains the inactive ingredients colloidal silicon dioxide, croscarmellose sodium, crospovidone, dextrose monohydrate, lecithin (soya), maltodextrin, microcrystalline cellulose, silicified microcrystalline cellulose, povidone, sodium bicarbonate, sodium carboxymethyl cellulose, sodium stearyl fumarate, talc, and titanium dioxide. Chemical Structure Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Medication Guide ) that accompanies each prescription dispensed. Inform patients, families, or their caregivers of the following information before initiating therapy with sumatriptan and naproxen sodium and periodically during the course of ongoing therapy. Cardiovascular Thrombotic Events, Prinzmetal's Angina, Other Vasospasm-Related Events, Arrhythmias and Cerebrovascular Events Advise patients to be alert for the symptoms of cardiovascular thrombotic effects such as myocardial infarction or stroke, which may result in hospitalization and even death.
Although serious cardiovascular events can occur without warning symptoms, patients should be alert for signs and symptoms of chest pain, shortness of breath, weakness, irregular heartbeat, significant rise in blood pressure, weakness and slurring of speech, and should be advised to report any of these symptoms to their health care provider immediately. Apprise patients of the importance of this follow-up [see Warnings and Precautions (5.1 , 5.3 , 5.5 , 5.6 , 5.8) ] . Gastrointestinal Bleeding, Ulceration, and Perforation Advise patients to report symptoms of ulcerations and bleeding, including epigastric pain, dyspepsia, melena, and hematemesis to their health care provider.
In the setting of concomitant use of low-dose aspirin for cardiac prophylaxis, inform patients of the increased risk for and the signs and symptoms of GI bleeding [see Warnings and Precautions (5.2) ] . Hepatotoxicity Inform patients of the warning signs and symptoms of hepatotoxicity (e.g., nausea, fatigue, lethargy, pruritus, diarrhea, jaundice, right upper quadrant tenderness, and “flu-like” symptoms). If these occur, instruct patients to stop sumatriptan and naproxen sodium and seek immediate medical therapy [see Warnings and Precautions (5.7) ] .
Anaphylactic Reactions Inform patients that anaphylactic reactions have occurred in patients receiving the components of sumatriptan and naproxen sodium. Such reactions can be life-threatening or fatal. In general, anaphylactic reactions to drugs are more likely to occur in individuals with a history of sensitivity to multiple allergens.
Inform patients of the signs of an anaphylactic reaction (e.g., difficulty breathing, swelling of the face or throat). If these occur, patients should be instructed to seek immediate emergency help [see Contraindications (4) , Warnings and Precautions (5.13) ]. Serious Skin Reactions , including DRESS Inform patients that sumatriptan and naproxen sodium, like other NSAID-containing products, may increase the risk of serious skin side effects such as exfoliative dermatitis, Stevens-Johnson syndrome, toxic epidermal necrolysis, and DRESS, which may result in hospitalizations and even death.
Although serious skin reactions may occur without warning, patients should be alert for the signs and symptoms of skin rash and blisters, fever, or other signs of hypersensitivity such as itching and should ask for medical advice when observing any indicative signs or symptoms. Advise patients to stop taking sumatriptan and naproxen sodium immediately if they develop any type of rash or fever and contact their healthcare providers as soon as possible [see Warnings and Precautions (5.14 , 5.15) ] . Fetal Toxicity Inform pregnant women to avoid use of sumatriptan and naproxen sodium and other NSAIDs starting at 30 weeks gestation because of the risk of the premature closing of the fetal ductus arteriosus.
If treatment with sumatriptan and naproxen sodium is needed for a pregnant woman between about 20 to 30 weeks gestation, advise her that she may need to be monitored for oligohydramnios, if treatment continues for longer than 48 hours [see Warnings and Precautions (5.16) , Use in Specific Populations (8.1) ] . Lactation Advise patients to notify their healthcare provider if they are breastfeeding or plan to breastfeed [see Use in Specific Populati… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
MEDICATION GUIDE Sumatriptan and Naproxen Sodium (soo'' ma trip' tan and na prox' en soe' dee um) Tablets Read this Medication Guide before you start taking sumatriptan and naproxen sodium tablets and each time you get a refill. There may be new information. This Medication Guide does not take the place of talking with your healthcare provider about your medical condition or treatment.
What is the most important information I should know about sumatriptan and naproxen sodium tablets? Sumatriptan and naproxen sodium tablets may increase your chance of a heart attack or stroke that can lead to death. Sumatriptan and naproxen sodium tablets contain 2 medicines: sumatriptan and naproxen sodium (a nonsteroidal anti-inflammatory drug [NSAID]).
This risk may happen early in treatment and may increase: with increasing doses of NSAIDs with longer use of NSAIDs Do not take sumatriptan and naproxen sodium tablets right before or after a heart surgery called a “coronary artery bypass graft (CABG)." Avoid taking sumatriptan and naproxen sodium tablets after a recent heart attack, unless your healthcare provider tells you to. You may have an increased risk of another heart attack if you take NSAIDs after a recent heart attack. Stop taking sumatriptan and naproxen sodium tablets and get emergency help right away if you have any of the following symptoms of a heart attack or stroke: discomfort in the center of your chest that lasts for more than a few minutes, or that goes away and comes back severe tightness, pain, pressure, or heaviness in your chest, throat, neck, or jaw pain or discomfort in your arms, back, neck, jaw, or stomach shortness of breath with or without chest discomfort breaking out in a cold sweat nausea or vomiting feeling lightheaded weakness in one part or on one side of your body slurred speech Sumatriptan and naproxen sodium tablets are not for people with risk factors for heart disease unless a heart exam is done and shows no problem.
You have a higher risk for heart disease if you: have high blood pressure have high cholesterol levels smoke are overweight have diabetes have a family history of heart disease Sumatriptan and naproxen sodium tablets can cause ulcers and bleeding in the stomach and intestines at any time during your treatment. Ulcers and bleeding can happen without warning symptoms and may cause death. Your chance of getting an ulcer or bleeding increases with: past history of stomach ulcers, or stomach or intestinal bleeding with use of NSAIDs the use of medicines called “corticosteroids,” “anticoagulants,” and antidepressant medicines called “SSRIs” or “SNRIs” longer use more frequent use smoking drinking alcohol older age having poor health advanced liver disease bleeding problems Sumatriptan and naproxen sodium tablets may cause serious allergic reactions or serious skin reactions that can be life-threatening.
Stop taking sumatriptan and naproxen sodium tablets and get emergency help right away if you develop: sudden wheezing swelling of your lips, tongue, throat or body rash fainting problems breathing or swallowing reddening of your skin with blisters or peeling blisters or bleeding of your lips, eye lids, mouth, nose, or genitals Sumatriptan and naproxen sodium tablets should only be used exactly as prescribed, at the lowest dose possible for your treatment, and for the shortest time needed. Sumatriptan and naproxen sodium tablets already contain an NSAID (naproxen).
Do not use sumatriptan and naproxen sodium tablets with other medicines to lessen pain or fever or with other medicines for colds or sleeping problems without talking to your healthcare provider first, because they may contain an NSAID also. What are sumatriptan and naproxen sodium tablets? Sumatriptan and naproxen sodium tablets are a prescription medicine that contains sumatriptan and naproxen sodium (an NSAID).
Sumatriptan and naproxen sodium tablets are used to treat acute migraine headaches with or without aura in patients 12 years… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
8.3Females and Males of Reproductive Potential Infertility Females Based on the mechanism of action, the use of prostaglandin-mediated NSAIDs, including naproxen tablets, may delay or prevent rupture of ovarian follicles, which has been associated with reversible infertility in some women. Published animal studies have shown that administration of prostaglandin synthesis inhibitors has the potential to disrupt prostaglandin-mediated follicular rupture required for ovulation. Small studies in women treated with NSAIDs have also shown a reversible delay in ovulation.
Consider withdrawal of NSAIDs, including naproxen tablets, in women who have difficulties conceiving or who are undergoing investigation of infertility.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption and Bioavailability Sumatriptan, when given as sumatriptan and naproxen sodium 85/500 mg, has a mean C max similar to that of sumatriptan succinate 100 mg tablets alone. The median T max of sumatriptan, when given as sumatriptan and naproxen sodium 85/500 mg, was 1 hour (range: 0.3 to 4.0 hours), which is slightly different compared with sumatriptan succinate 100 mg tablets (median T max of 1.5 hours). Naproxen, when given as sumatriptan and naproxen sodium 85/500 mg, has a C max which is approximately 36% lower than naproxen sodium 550 mg tablets and a median T max of 5 hours (range: 0.3 to 12 hours), which is approximately 4 hours later than from naproxen sodium tablets 550 mg.
AUC values for sumatriptan and for naproxen are similar for sumatriptan and naproxen sodium 85/500 mg compared with sumatriptan succinate 100 mg tablets or naproxen sodium 550 mg tablets, respectively. In a crossover trial in 16 subjects, the pharmacokinetics of both components administered as sumatriptan and naproxen sodium 85/500 mg were similar during a migraine attack and during a migraine-free period. Bioavailability of sumatriptan is approximately 15%, primarily due to presystemic (first-pass) metabolism and partly due to incomplete absorption.
Naproxen is absorbed from the gastrointestinal tract with an in vivo bioavailability of 95%. Food had no significant effect on the bioavailability of sumatriptan or naproxen administered as sumatriptan and naproxen sodium, but slightly delayed the T max of sumatriptan by about 0.6 hour [see Dosage and Administration (2.3) ] . Distribution Plasma protein binding is 14% to 21%.
The effect of sumatriptan on the protein binding of other drugs has not been evaluated. The volume of distribution of sumatriptan is
2.7L/kg. The volume of distribution of naproxen is
0.16L/kg. At therapeutic levels naproxen is greater than 99% albumin bound. At doses of naproxen greater than 500 mg/day, there is a less-than-proportional increase in plasma levels due to an increase in clearance caused by saturation of plasma protein binding at higher doses (average trough C ss = 36.5, 49.2, and 56.4 mg/L with 500-; 1,000-; and 1,500 mg daily doses of naproxen, respectively).
However, the concentration of unbound naproxen continues to increase proportionally to dose. Metabolism In vitro studies with human microsomes suggest that sumatriptan is metabolized by monoamine oxidase (MAO), predominantly the A isoenzyme. No significant effect was seen with an MAO-B inhibitor.
Naproxen is extensively metabolized to 6-0-desmethyl naproxen, and both parent and metabolites do not induce metabolizing enzymes. Elimination The elimination half-life of sumatriptan is approximately 2 hours. Radiolabeled 14 C-sumatriptan administered orally is largely renally excreted (about 60%), with about 40% found in the feces.
Most of a radiolabeled dose of sumatriptan excreted in the urine is the major metabolite indole acetic acid (IAA) or the IAA glucuronide, both of which are inactive. Three percent of the dose can be recovered as unchanged sumatriptan. The clearance of naproxen is 0.13 mL/min/kg.
Approximately 95% of the naproxen from any dose is excreted in the urine, primarily as naproxen (less than 1%), 6-0-desmethyl naproxen (less than 1%), or their conjugates (66% to 92%). The plasma half-life of the naproxen anion in humans is approximately 19 hours. The corresponding half-lives of both metabolites and conjugates of naproxen are shorter than 12 hours, and their rates of excretion have been found to coincide closely with the rate of naproxen disappearance from the plasma.
In patients with renal failure, metabolites may accumulate. Specific Populations Geriatrics The pharmacokinetics of sumatriptan and naproxen sodium in geriatric patients have not been studied. Elderly patients are more likely to have decreased hepatic function and decreased renal function [see Specific Populations (8.5) ].
The pharmacokinetics of oral… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics In a healthy volunteer study, 10 days of concomitant administration of naproxen 220 mg once-daily with low-dose immediate-release aspirin (81 mg) showed an interaction with the antiplatelet activity of aspirin as measured by % serum thromboxane B 2 inhibition at 24 hours following the day 10 dose [98.7% (aspirin alone) vs 93.1% (naproxen and aspirin)]. The interaction was observed even following discontinuation of naproxen on day 11 (while aspirin dose was continued) but normalized by day 13. In the same study, the interaction was greater when naproxen was administered 30 minutes prior to aspirin [98.7% vs 87.7%] and minimal when aspirin was administered 30 minutes prior to naproxen [98.7% vs 95.4%].
Following administration of naproxen 220 mg twice-daily with low-dose immediate–release aspirin (first naproxen dose given 30 minutes prior to aspirin), the interaction was minimal at 24 h following day 10 dose [98.7% vs 95.7%]. However, the interaction was more prominent after discontinuation of naproxen (washout) on day 11 [98.7% vs 84.3%] and did not normalize completely by day 13 [98.5% vs 90.7%] [see Drug Interactions (7.1) ] . Blood Pressure In a randomized, double-blind, parallel group, active control trial, sumatriptan and naproxen sodium 85/500 mg administered intermittently over 6 months did not increase blood pressure in a normotensive adult population (n = 122).
However, significant elevation in blood pressure has been reported with 5-HT 1 agonists and NSAIDs in patients with and without a history of hypertension.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Adults The efficacy of sumatriptan and naproxen sodium in the acute treatment of migraine with or without aura in adults was demonstrated in 2 randomized, double-blind, multicenter, parallel-group trials utilizing placebo and each individual active component of sumatriptan and naproxen sodium 85/500 mg as comparison treatments (Study 1 and Study 2). Patients enrolled in these 2 trials were predominately female (87%) and white (88%), with a mean age of 40 years (range: 18 to 65 years). Patients were instructed to treat a migraine of moderate to severe pain with 1 tablet.
No rescue medication was allowed within 2 hours postdose. Patients evaluated their headache pain 2 hours after taking 1 dose of study medication; headache relief was defined as a reduction in headache severity from moderate or severe pain to mild or no pain. Associated symptoms of nausea, photophobia, and phonophobia were also evaluated.
Sustained pain free was defined as a reduction in headache severity from moderate or severe pain to no pain at 2 hours postdose without a return of mild, moderate, or severe pain and no use of rescue medication for 24 hours postdose. The results from Study 1 and 2 are summarized in Table 4. In both trials, the percentage of patients achieving headache pain relief 2 hours after treatment was significantly greater among patients receiving sumatriptan and naproxen sodium 85/500 mg (65% and 57%) compared with those who received placebo (28% and 29%).
Further, the percentage of patients who remained pain free without use of other medications through 24 hours postdose was significantly greater among patients receiving a single dose of sumatriptan and naproxen sodium 85/500 mg (25% and 23%) compared with those who received placebo (8% and 7%) or either sumatriptan (16% and 14%) or naproxen sodium (10%) alone. Table 4. Percentage of Adult Patients with 2-Hour Pain Relief and Sustained Pain Free Following Treatment a a P values provided only for prespecified comparisons. b P <0.05 versus placebo and sumatriptan. c P <0.01 versus placebo, sumatriptan, and naproxen sodium.
Sumatriptan and Naproxen Sodium Tablets 85/500 mg Sumatriptan 85 mg Naproxen Sodium 500 mg Placebo 2-Hour Pain Relief Study 1 65% b n = 364 55% n = 361 44% n = 356 28% n = 360 Study 2 57% b n = 362 50% n = 362 43% n = 364 29% n = 382 Sustained Pain Free (2 to 24 Hours) Study 1 25% c n = 364 16% n = 361 10% n = 356 8% n = 360 Study 2 23% c n = 362 14% n = 362 10% n = 364 7% n = 382 The percentage of patients achieving initial headache pain relief within 2 hours following treatment with sumatriptan and naproxen sodium 85/500 mg is shown in Figure 1.
Compared with placebo, there was a decreased incidence of photophobia, phonophobia, and nausea 2 hours after the administration of sumatriptan and naproxen sodium 85/500 mg. The estimated probability of taking a rescue medication over the first 24 hours is shown in Figure 2. Sumatriptan and naproxen sodium 85/500 mg was more effective than placebo regardless of the presence of aura; duration of headache prior to treatment; gender, age, or weight of the subject; or concomitant use of oral contraceptives or common migraine prophylactic drugs (e.g., beta-blockers, anti-epileptic drugs, tricyclic antidepressants).
Figure 1 Figure 2
14.2Pediatric Patients 12 to 17 Years of Age The efficacy of sumatriptan and naproxen sodium in the acute treatment of migraine with or without aura in pediatric patients 12 to 17 years of age was demonstrated in a randomized, double-blind, multicenter, parallel-group, placebo-controlled, multicenter trial comparing 3 doses of sumatriptan and naproxen sodium and placebo (Study 3). Patients enrolled in this trial were mostly female (59%) and white (81%), with a mean age of 15 years. Patients were required to have at least a 6-month history of migraine attacks with or without aura usually lasting 3 hours or more when untreated.
Following a single-blind, placebo run-in phase, plac… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis The carcinogenic potential of sumatriptan and naproxen sodium has not been studied. In carcinogenicity studies in mouse and rat, sumatriptan was administered orally for 78 and 104 weeks, respectively, at doses up to 160 mg/kg/day. The highest doses tested are approximately 5 (mouse) and 9 (rat) times the maximum human daily dose (MHDD) of 170 mg sumatriptan on a mg/m 2 basis (two tablets of sumatriptan and naproxen sodium 85/500 mg in a 24-hour period).
The carcinogenic potential of naproxen was evaluated in a 2-year oral carcinogenicity study in rats at doses of 8, 16, and 24 mg/kg/day and in another 2-year oral carcinogenicity study in rats at a dose of 8 mg/kg/day. No evidence of tumorigenicity was found in either study. The highest dose tested is less than the MHDD (1000 mg) of naproxen, on a mg/m 2 basis.
Mutagenesis Sumatriptan and naproxen sodium tested alone and in combination were negative in an in vitro bacterial reverse mutation assay, and in an in vivo micronucleus assay in mice. The combination of sumatriptan and naproxen sodium was negative in an in vitro mouse lymphoma tk assay in the presence and absence of metabolic activation. However, in separate in vitro mouse lymphoma tk assays, naproxen sodium alone was reproducibly positive in the presence of metabolic activation.
Naproxen sodium alone and in combination with sumatriptan was positive in an in vitro clastogenicity assay in mammalian cells in the presence and absence of metabolic activation. The clastogenic effect for the combination was reproducible within this assay and was greater than observed with naproxen sodium alone. Sumatriptan alone was negative in these assays.
Chromosomal aberrations were not induced in peripheral blood lymphocytes following 7 days of twice-daily dosing with sumatriptan and naproxen sodium in human volunteers. In previous studies, sumatriptan alone was negative in in vitro (bacterial reverse mutation [Ames], gene cell mutation in Chinese hamster V79/HGPRT, chromosomal aberration in human lymphocytes) and in vivo (rat micronucleus) assays. Impairment of Fertility The effect of sumatriptan and naproxen sodium on fertility in animals has not been studied.
When sumatriptan (5, 50, 500 mg/kg/day) was administered orally to male and female rats prior to and throughout the mating period, there was a drug-related decrease in fertility secondary to a decrease in mating in animals treated with doses greater than 5 mg/kg/day (less than the MHDD of 170 mg on a mg/m 2 basis). It is not clear whether this finding was due to an effect on males or females or both.
13.2Animal Toxicology and/or Pharmacology Corneal Opacities Dogs receiving oral sumatriptan developed corneal opacities and defects in the corneal epithelium. Corneal opacities were seen at the lowest dosage tested, 2 mg/kg/day, and were present after 1 month of treatment. Defects in the corneal epithelium were noted in a 60-week study.
Earlier examinations for these toxicities were not conducted and no-effect doses were not established. The lowest dose tested is less than the MHDD (170 mg) of sumatriptan on a mg/m 2 basis.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis The carcinogenic potential of sumatriptan and naproxen sodium has not been studied. In carcinogenicity studies in mouse and rat, sumatriptan was administered orally for 78 and 104 weeks, respectively, at doses up to 160 mg/kg/day. The highest doses tested are approximately 5 (mouse) and 9 (rat) times the maximum human daily dose (MHDD) of 170 mg sumatriptan on a mg/m 2 basis (two tablets of sumatriptan and naproxen sodium 85/500 mg in a 24-hour period).
The carcinogenic potential of naproxen was evaluated in a 2-year oral carcinogenicity study in rats at doses of 8, 16, and 24 mg/kg/day and in another 2-year oral carcinogenicity study in rats at a dose of 8 mg/kg/day. No evidence of tumorigenicity was found in either study. The highest dose tested is less than the MHDD (1000 mg) of naproxen, on a mg/m 2 basis.
Mutagenesis Sumatriptan and naproxen sodium tested alone and in combination were negative in an in vitro bacterial reverse mutation assay, and in an in vivo micronucleus assay in mice. The combination of sumatriptan and naproxen sodium was negative in an in vitro mouse lymphoma tk assay in the presence and absence of metabolic activation. However, in separate in vitro mouse lymphoma tk assays, naproxen sodium alone was reproducibly positive in the presence of metabolic activation.
Naproxen sodium alone and in combination with sumatriptan was positive in an in vitro clastogenicity assay in mammalian cells in the presence and absence of metabolic activation. The clastogenic effect for the combination was reproducible within this assay and was greater than observed with naproxen sodium alone. Sumatriptan alone was negative in these assays.
Chromosomal aberrations were not induced in peripheral blood lymphocytes following 7 days of twice-daily dosing with sumatriptan and naproxen sodium in human volunteers. In previous studies, sumatriptan alone was negative in in vitro (bacterial reverse mutation [Ames], gene cell mutation in Chinese hamster V79/HGPRT, chromosomal aberration in human lymphocytes) and in vivo (rat micronucleus) assays. Impairment of Fertility The effect of sumatriptan and naproxen sodium on fertility in animals has not been studied.
When sumatriptan (5, 50, 500 mg/kg/day) was administered orally to male and female rats prior to and throughout the mating period, there was a drug-related decrease in fertility secondary to a decrease in mating in animals treated with doses greater than 5 mg/kg/day (less than the MHDD of 170 mg on a mg/m 2 basis). It is not clear whether this finding was due to an effect on males or females or both.
📄 Recent Major Changes ▾
Warnings and Precautions ( 5.14 ) 11/2024
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL NDC 65862-928-36 Rx only Sumatriptan and Naproxen Sodium Tablets 85 mg/500 mg PHARMACIST: Dispense the Medication Guide provided separately to each patient. J78 AUROBINDO 9 Tablets PACKAGE LABEL.PRINCIPAL DISPLAY PANEL