
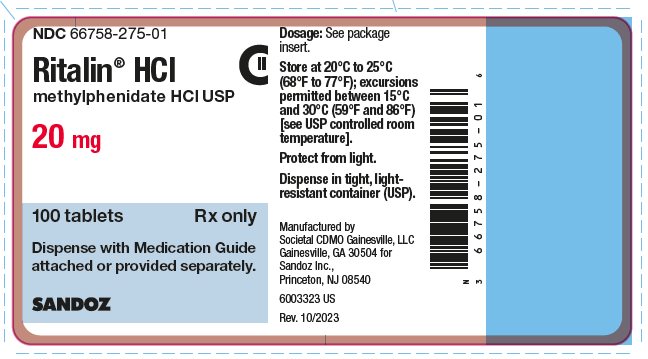
Ritalin methylphenidate hydrochloride 20 mg Tablet, 100-count
Other active recalls for Methylphenidate Hydrochloride (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Central Nervous System Stimulant class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Methylphenidate is used to control symptoms of attention deficit hyperactivity disorder (ADHD; condition that makes it hard to pay attention, control your behavior, and remain still or quiet) and to treat narcolepsy (condition that causes people to be very sleepy during the day and to fall asleep suddenly). Methylphenidate is in a class of medications called central nervous system (CNS) stimulants. It works by changing the amounts of certain natural substances in the brain.
Read the full MedlinePlus article ↗- Methylphenidate helps boost two brain chemicals — dopamine and norepinephrine — that play a big role in attention, focus, and impulse control. When those chemicals are more availab...
- What exactly is methylphenidate supposed to do for my ADHD?
- Methylphenidate is a controlled substance, and it does have a real potential for abuse and dependence — that's something the FDA takes seriously enough to put a boxed warning on th...
- The most common ones — decreased appetite, some trouble sleeping, headache, and a slightly faster heartbeat — are annoying but usually manageable and tend to improve over time. For...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Methylphenidate Hydrochloride — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII J2B2A4N98G
Lactose is a natural sugar derived from milk. In medications, it serves as a filler and binder to add bulk and help hold tablet or capsule ingredients together during manufacturing.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 2944357O2O
A natural gum derived from the tragacanth shrub, used as a thickener, stabilizer, and binder in medicines. It helps create the right consistency and keeps ingredients evenly mixed throughout the product.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $1.633 | $163.30 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $1.67 | $166.68 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $1.79 | $178.63 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Methylphenidate Hydrochloride 20 mg 00115-1802-01 | Amneal | 100 tablets | $0.210 | — | Availability likely | save 87% |
| Methylphenidate Hydrochloride 20 mg 00406-1146-01 | SpecGx | 100 tablets | $0.210 | AB | Availability likely | save 87% |
| Methylphenidate Hydrochloride 20 mg 10702-0102-01 | KVK-TECH, | 100 tablets | $0.210 | AB | Availability likely | save 87% |
| Methylphenidate Hydrochloride 20 mg 16729-0480-01 | Accord | 100 tablets | $0.210 | AB | Availability likely | save 87% |
| Methylphenidate Hydrochloride 20 mg 31722-0175-01 | Camber | 100 tablets | $0.210 | AB | Availability likely | save 87% |
| Methylphenidate hydrochloride 20 mg 43547-0488-10 | Solco | 100 tablets | $0.210 | AB | Availability likely | save 87% |
| Methylphenidate Hydrochloride 20 mg 50268-0529-15 | AvPAK | 50 tablets | $0.210 | AB | Discontinued | save 87% |
| Methylphenidate Hydrochloride 20 mg 67877-0618-01 | Ascend | 100 tablets | $0.210 | AB | Availability likely | save 87% |
| Methylphenidate Hydrochloride 20 mg 75834-0326-01 | Nivagen | 100 tablets | $0.210 | AB | Availability likely | save 87% |
| Methylphenidate Hydrochloride 20 mg 43386-0575-01 | Lupin | 100 tablets | $0.227 | AB | FDA listed | save 86% |
| Ritalin 20 mg 00078-0441-05 | Novartis | 100 tablets | $1.633 | AB | Discontinued | — |
| Ritalin 20 mgthis 66758-0275-01 | Sandoz | 100 tablets | $1.633 | AB | Availability likely | — |
| Methylphenidate Hydrochloride 20 mg 13107-0382-01 | Aurolife | 100 tablets | — | — | FDA listed | — |
| Methylphenidate Hydrochloride 20 mg 55466-0103-12 | Neolpharma, | 100 tablets | — | AB | Discontinued | — |
| Methylphenidate Hydrochloride 20 mg 57664-0230-08 | Sun | 100 tablets | — | AB | FDA listed | — |
| Methylphenidate Hydrochloride 20 mg 71335-1219-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Methylphenidate Hydrochloride 20 mg 72162-2087-01 | Bryant | 100 tablets | — | — | FDA listed | — |
| Methylphenidate Hydrochloride 20 mg 72162-2430-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Methylphenidate Hydrochloride 20 mg 72865-0124-01 | XLCare | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 66758-0275-01 You're viewing this | 100 TABLET in 1 BOTTLE (66758-275-01) | 2024-12-18 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: ABUSE, MISUSE, AND ADDICTION Ritalin has a high potential for abuse and misuse, which can lead to the development of a substance use disorder, including addiction. Misuse and abuse of CNS stimulants, including Ritalin, can result in overdose and death [see Overdosage ( 10 )] , and this risk is increased with higher doses or unapproved methods of administration, such as snorting or injection. Before prescribing Ritalin, assess each patient’s risk for abuse, misuse, and addiction.
Educate patients and their families about these risks, proper storage of the drug, and proper disposal of any unused drug. Throughout Ritalin treatment, reassess each patient’s risk of abuse, misuse, and addiction and frequently monitor for signs and symptoms of abuse, misuse, and addiction [see Warnings and Precautions ( 5.1 ) and Drug Abuse and Dependence ( 9.2 )]. WARNING: ABUSE, MISUSE, AND ADDICTION See full prescribing information for complete boxed warning.
Ritalin has a high potential for abuse and misuse, which can lead to the development of a substance use disorder, including addiction. Misuse and abuse of CNS stimulants, including Ritalin, can result in overdose and death ( 5.1 , 9.2 , 10 ): • Before prescribing Ritalin, assess each patient’s risk for abuse, misuse, and addiction. • Educate patients and their families about these risks, proper storage of the drug, and proper disposal of any unused drug. • Throughout treatment, reassess each patient’s risk and frequently monitor for signs and symptoms of abuse, misuse, and addiction.
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Ritalin is indicated for the treatment of: • Attention Deficit Hyperactivity Disorders (ADHD) in pediatric patients 6 years and older and adults • Narcolepsy Ritalin is a central nervous system (CNS) stimulant indicated for the treatment of Attention Deficit Hyperactivity Disorders (ADHD) and Narcolepsy ( 1 ).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Pediatric Patients 6 Years and Older: Start with 5 mg twice daily (before breakfast and lunch), titrating the dose weekly in 5- to 10-mg increments. Dosages above 60 mg/day are not recommended ( 2.2 ). • Adults: Average daily dosage is 20 mg to 30 mg, administered 2 or 3 times daily, preferably 30 to 45 minutes before meals. Maximum total daily dosage is 60 mg ( 2.2 ).
2.1Pretreatment Screening Prior to treating patients with Ritalin, assess: • for the presence of cardiac disease (i.e., perform a careful history, family history of sudden death or ventricular arrhythmia, and physical exam) [see Warnings and Precautions ( 5.2 )]. • the family history and clinically evaluate patients for motor or verbal tics or Tourette’s syndrome before initiating Ritalin [see Warnings and Precautions ( 5.10 )].
2.2General Dosing Information Pediatric Patients 6 years and Older : Start with 5 mg orally twice daily (before breakfast and lunch). Increase dosage gradually, in increments of 5-to 10-mg weekly. Daily dosage above 60 mg is not recommended.
Adults : Average dosage is 20 to 30 mg daily. Administer orally in divided doses 2 or 3 times daily, preferably 30 to 45 minutes before meals. Maximum total daily dosage is 60 mg.
Patients who are unable to sleep if medication is taken late in the day should take the last dose before 6 p.m.
2.3Dosage Reduction and Discontinuation If paradoxical worsening of symptoms or other adverse reactions occur, reduce the dosage, or, if necessary, discontinue Ritalin. If improvement is not observed after appropriate dosage adjustment over a one-month period, the drug should be discontinued.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS • 5 mg, round, yellow, flat with CIBA monogram on one side and NDC# 7 on the reverse side • 10 mg, round, pale green, biconvex with CIBA monogram on one side and NDC# 3 and a partial bisection on the reverse side • 20 mg, round, pale yellow, biconvex with CIBA monogram on one side and NDC# 34 and a partial bisection on the reverse side • Tablets: 5 mg, 10 mg, and 20 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS • Hypersensitivity to methylphenidate or other components of Ritalin. Hypersensitivity reactions, such as angioedema and anaphylactic reactions, have been reported in patients treated with methylphenidate [see Adverse Reactions ( 6 )] . • Concomitant treatment with monoamine oxidase inhibitors (MAOIs), or within 14 days following discontinuation of treatment with an MAOI, because of the risk of hypertensive crises [see Drug Interactions ( 7.1 )] . • Known hypersensitivity to methylphenidate or other product components of Ritalin ( 4 ). • Concurrent treatment with a monoamine oxidase inhibitor (MAOI), or use of an MAOI within the preceding 14 days ( 4 ).
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Risks to Patients with Serious Cardiac Disease : Avoid use in patients with known structural cardiac abnormalities, cardiomyopathy, serious cardiac arrhythmias, coronary artery disease, or other serious cardiac disease ( 5.2 ). • Increased Blood Pressure and Heart Rate : Monitor blood pressure and pulse ( 5.3 ). • Psychiatric Adverse Reactions : Prior to initiating Ritalin, screen patients for risk factors for developing a manic episode. If new psychotic or manic symptoms occur, consider discontinuing Ritalin ( 5.4 ). • Priapism : If abnormally sustained or frequent and painful erections occur, patients should seek immediate medical attention ( 5.5 ). • Peripheral Vasculopathy, Including Raynaud’s Phenomenon : Careful observation for digital changes is necessary during Ritalin treatment.
Further clinical evaluation (e.g., rheumatology referral) may be appropriate for patients who develop signs or symptoms of peripheral vasculopathy ( 5.6 ). • Long-Term Suppression of Growth in Pediatric Patients : Closely monitor growth (height and weight) in pediatric patients. Pediatric patients not growing or gaining height or weight as expected may need to have their treatment interrupted ( 5.7 ). • Acute Angle Closure Glaucoma: Ritalin -treated patients considered at risk for acute angle closure glaucoma (e.g., patients with significant hyperopia) should be evaluated by an ophthalmologist ( 5.8 ). • Increased Intraocular Pressure (IOP) and Glaucoma: Prescribe Ritalin to patients with open-angle glaucoma or abnormally increased IOP only if the benefit of treatment is considered to outweigh the risk.
Closely monitor patients with a history of increased IOP or open angle glaucoma ( 5.9 ). • Motor and Verbal Tics, and Worsening of Tourette’s Syndrome: Before initiating Ritalin, assess the family history and clinically evaluate patients for tics or Tourette’s syndrome. Regularly monitor patients for the emergence or worsening of tics or Tourette’s syndrome. Discontinue treatment if clinically appropriate ( 5.10 ).
5.1Abuse, Misuse, and Addiction Ritalin have a high potential for abuse and misuse. The use of Ritalin exposes individuals to the risks of abuse and misuse, which can lead to the development of a substance use disorder, including addiction. Ritalin can be diverted for non-medical use into illicit channels or distribution [see Drug Abuse and Dependence ( 9.2 )].
Misuse and abuse of CNS stimulants, including Ritalin, can result in overdose and death [see Overdosage ( 10 )], and this risk is increased with higher doses or unapproved methods of administration, such as snorting or injection. Before prescribing Ritalin, assess each patient’s risk for abuse, misuse, and addiction. Educate patients and their families about these risks and proper disposal of any unused drug.
Advise patients to store Ritalin in a safe place, preferably locked, and instruct patients to not give Ritalin to anyone else. Throughout Ritalin treatment, reassess each patient’s risk of abuse, misuse, and addiction and frequently monitor for signs and symptoms of abuse, misuse, and addiction.
5.2Risks to Patients with Serious Cardiac Disease Sudden death has been reported in patients with structural cardiac abnormalities or other serious cardiac disease who are treated with CNS stimulants at the recommended ADHD dosage. Avoid Ritalin use in patients with known serious structural cardiac abnormalities, cardiomyopathy, serious cardiac arrhythmia, coronary artery disease, or other serious cardiac disease.
5.3Increased Blood Pressure and Heart Rate CNS stimulants cause an increase in blood pressure (mean increase approximately 2 to 4 mmHg) and heart rate (mean increase approximately 3 to 6 beats per minute). Some patients may have larger increases. Monitor all Ritalin-treated patients for hypertension and tachycardia.
5.4Psychiatric Adverse Reactions Exacerbation of Pre-existing Psychosis CNS stimulants may exacerbate symptoms of behavior d…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following are discussed in more detail in other sections of the labeling: • Abuse, Misuse, and Addiction [see Boxed Warning, Warnings and Precautions ( 5.1 ), Drug Abuse and Dependence ( 9.2 , 9.3 )] • Known hypersensitivity to methylphenidate or other ingredients of Ritalin [see Contraindications ( 4 )] • Hypertensive crisis with Concomitant Use of Monoamine Oxidase Inhibitors [see Contraindications ( 4 ), Drug Interactions ( 7.1 )] • Risks to Patients with Serious Cardiac Disease [see Warnings and Precautions ( 5.2 )] • Increased Blood Pressure and Heart Rate [see Warnings and Precautions ( 5.3 )] • Psychiatric Adverse Reactions [see Warnings and Precautions ( 5.4 )] • Priapism [see Warnings and Precautions ( 5.5 )] • Peripheral Vasculopathy, Including Raynaud’s Phenomenon [see Warnings and Precautions ( 5.6 )] • Long-Term Suppression of Growth in Pediatric Patients [see Warnings and Precautions ( 5.7 )] • Acute Angle Closure Glaucoma [see Warnings and Precautions ( 5.8 )] • Increased Intraocular Pressure and Glaucoma [see Warnings and Precautions ( 5.9 )] • Motor and Verbal Tics, and Worsening of Tourette’s Syndrome [see Warnings and Precautions ( 5.10 )] The following adverse reactions associated with the use of Ritalin and other methylphenidate products were identified in clinical trials, spontaneous reports, and literature.
Because these reactions were reported voluntarily from a population of uncertain size, it is not always possible to estimate their frequency reliably or to establish a causal relationship to drug exposure. Adverse Reactions Reported with Ritalin Infections and Infestations: nasopharyngitis Blood and the Lymphatic System Disorders: leukopenia, thrombocytopenia, anemia Immune System Disorders: hypersensitivity reactions, including angioedema, and anaphylaxis Metabolism and Nutrition Disorders: decreased appetite, reduced weight gain, and suppression of growth during prolonged use in pediatric patients Psychiatric Disorders: insomnia, anxiety, restlessness, agitation, psychosis (sometimes with visual and tactile hallucinations), depressed mood, depression Nervous System Disorders: headache, dizziness, tremor, dyskinesia, including choreoatheetoid movements, drowsiness, convulsions, cerebrovascular disorders (including vasculitis, cerebral hemorrhages and cerebrovascular accidents), serotonin syndrome in combination with serotonergic drugs Eye Disorders: blurred vision, difficulties in visual accommodation Cardiac Disorders: tachycardia, palpitations, increased blood pressure, arrhythmias, angina pectoris Respiratory, Thoracic, and Mediastinal Disorders: cough Gastrointestinal Disorders: dry mouth, nausea, vomiting, abdominal pain, dyspepsia Hepatobiliary Disorders: abnormal liver function, ranging from transaminase elevation to severe hepatic injury Skin and Subcutaneous Tissue Disorders: hyperhidrosis, pruritus, urticaria, exfoliative dermatitis, scalp hair loss, erythema multiforme rash, thrombocytopenic purpura Musculoskeletal and Connective Tissue Disorders: arthralgia, muscle cramps, rhabdomyolysis, trismus Investigations: weight loss (adult ADHD patients) Vascular Disorders: peripheral coldness, Raynaud's phenomenon Additional Adverse Reactions Reported with Other Methylphenidate-Containing Products The list below shows adverse reactions not listed for Ritalin that have been reported with other methylphenidate-containing products.
Blood and Lymphatic Disorders: pancytopenia Immune System Disorders: hypersensitivity reactions, such as auricular swelling, bullous conditions, eruptions, exanthemas Psychiatric Disorders: affect lability, mania, disorientation, and libido changes Nervous System Disorders: migraine, motor and verbal tics Eye Disorders: diplopia, increased intraocular pressure, mydriasis Cardiac Disorders: sudden cardiac death, myocardial infarction, bradycardia, extrasystole Respiratory, Thoracic, and Mediastinal Disorders: pharyngolaryngeal pain, dyspnea Gastroin…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Antihypertensive Drugs: Monitor blood pressure. Adjust dosage of antihypertensive drug as needed ( 7.1 ).
7.1Clinically Important Drug Interactions with Ritalin Table 1 presents clinically important drug interactions with Ritalin. Table 1: Clinically Important Drug Interactions with Ritalin Monoamine Oxidase Inhibitors (MAOI) Clinical Impact Concomitant use of MAOIs and CNS stimulants, including Ritalin can cause hypertensive crisis. Potential outcomes include death, stroke, myocardial infarction, aortic dissection, ophthalmological complications, eclampsia, pulmonary edema, and renal failure [see Contraindications ( 4 )] .
Intervention Concomitant use of Ritalin with MAOIs or within 14 days after discontinuing MAOI treatment is contraindicated. Antihypertensive Drugs Clinical Impact Ritalin may decrease the effectiveness of drugs used to treat hypertension [see Warnings and Precautions ( 5.3 )] . Intervention Monitor blood pressure and adjust the dosage of the antihypertensive drug as needed.
Halogenated Anesthetics Clinical Impact Concomitant use of halogenated anesthetics and Ritalin may increase the risk of sudden blood pressure and heart rate increase during surgery. Intervention Avoid use of Ritalin in patients being treated with anesthetics on the day of surgery. Risperidone Clinical Impact Combined use of methylphenidate with risperidone when there is a change, whether an increase or decrease, in dosage of either or both medications, may increase the risk of extrapyramidal symptoms (EPS) Intervention Monitor for signs of EPS
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to ADHD medications, including Ritalin, during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for ADHD Medications at 1-866-961-2388 or visiting https://womensmentalhealth.org/adhd-medications/ . Risk Summary Published studies and postmarketing reports on methylphenidate use during pregnancy have not identified a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes.
There may be risks to the fetus associated with the use of CNS stimulants use during pregnancy (see Clinical Considerations) . No effects on morphological development were observed in embryo-fetal development studies with oral administration of methylphenidate to pregnant rats and rabbits during organogenesis at doses up to 10 and 15 times, respectively, the maximum recommended human dose (MRHD) of 60 mg/day given to adolescents on a mg/m 2 basis. However, spina bifida was observed in rabbits at a dose 52 times the MRHD given to adolescents.
A decrease in pup body weight was observed in a pre- and post-natal development study with oral administration of methylphenidate to rats throughout pregnancy and lactation at doses 6 times the MRHD given to adolescents (see Data) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions CNS stimulants, such as Ritalin, can cause vasoconstriction and thereby decrease placental perfusion. No fetal and/or neonatal adverse reactions have been reported with the use of therapeutic doses of methylphenidate during pregnancy; however, premature delivery and low birth weight infants have been reported in amphetamine-dependent mothers.
Data Animal Data In embryo-fetal development studies conducted in rats and rabbits, methylphenidate was administered orally at doses of up to 75 and 200 mg/kg/day, respectively, during the period of organogenesis. Malformations (increased incidence of fetal spina bifida) were observed in rabbits at the highest dose, which is approximately 52 times the MRHD of 60 mg/day given to adolescents on a mg/m 2 basis. The no effect level for embryo-fetal development in rabbits was 60 mg/kg/day (15times the MRHD given to adolescents on a mg/m 2 basis).
There was no evidence of morphological development effects in rats, although increased incidences of fetal skeletal variations were seen at the highest dose level (10 times the MRHD of 60 mg/day given to adolescents on a mg/m 2 basis), which was also maternally toxic. The no effect level for embryo-fetal development in rats was 25 mg/kg/day (3 times the MRHD on a mg/m 2 basis). When methylphenidate was administered to rats throughout pregnancy and lactation at doses of up to 45 mg/kg/day, offspring body weight gain was decreased at the highest dose (6 times the MRHD of 60 mg/day given to adolescents on a mg/m 2 basis), but no other effects on postnatal development were observed.
The no effect level for pre- and postnatal development in rats was 15 mg/kg/day (approximately 2 times the MRHD given to adolescents on a mg/m 2 basis).
8.2Lactation Risk Summary Limited published literature, based on milk sampling from seven mothers, reports that methylphenidate is present in human milk, which resulted in infant doses of 0.16% to 0.7% of the maternal weight-adjusted dosage and a milk/plasma ratio ranging between 1.1 and 2.7. There are no reports of adverse effects on the breastfed infant and no effects on milk production. Long-term neurodeve…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to ADHD medications, including Ritalin, during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for ADHD Medications at 1-866-961-2388 or visiting https://womensmentalhealth.org/adhd-medications/ . Risk Summary Published studies and postmarketing reports on methylphenidate use during pregnancy have not identified a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes.
There may be risks to the fetus associated with the use of CNS stimulants use during pregnancy (see Clinical Considerations) . No effects on morphological development were observed in embryo-fetal development studies with oral administration of methylphenidate to pregnant rats and rabbits during organogenesis at doses up to 10 and 15 times, respectively, the maximum recommended human dose (MRHD) of 60 mg/day given to adolescents on a mg/m 2 basis. However, spina bifida was observed in rabbits at a dose 52 times the MRHD given to adolescents.
A decrease in pup body weight was observed in a pre- and post-natal development study with oral administration of methylphenidate to rats throughout pregnancy and lactation at doses 6 times the MRHD given to adolescents (see Data) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions CNS stimulants, such as Ritalin, can cause vasoconstriction and thereby decrease placental perfusion. No fetal and/or neonatal adverse reactions have been reported with the use of therapeutic doses of methylphenidate during pregnancy; however, premature delivery and low birth weight infants have been reported in amphetamine-dependent mothers.
Data Animal Data In embryo-fetal development studies conducted in rats and rabbits, methylphenidate was administered orally at doses of up to 75 and 200 mg/kg/day, respectively, during the period of organogenesis. Malformations (increased incidence of fetal spina bifida) were observed in rabbits at the highest dose, which is approximately 52 times the MRHD of 60 mg/day given to adolescents on a mg/m 2 basis. The no effect level for embryo-fetal development in rabbits was 60 mg/kg/day (15times the MRHD given to adolescents on a mg/m 2 basis).
There was no evidence of morphological development effects in rats, although increased incidences of fetal skeletal variations were seen at the highest dose level (10 times the MRHD of 60 mg/day given to adolescents on a mg/m 2 basis), which was also maternally toxic. The no effect level for embryo-fetal development in rats was 25 mg/kg/day (3 times the MRHD on a mg/m 2 basis). When methylphenidate was administered to rats throughout pregnancy and lactation at doses of up to 45 mg/kg/day, offspring body weight gain was decreased at the highest dose (6 times the MRHD of 60 mg/day given to adolescents on a mg/m 2 basis), but no other effects on postnatal development were observed.
The no effect level for pre- and postnatal development in rats was 15 mg/kg/day (approximately 2 times the MRHD given to adolescents on a mg/m 2 basis).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of Ritalin for the treatment of ADHD have been established in pediatric patients aged 6 to 17 years. The safety and effectiveness of Ritalin in pediatric patients less than aged 6 years have not been established. The long-term efficacy of methylphenidate in pediatric patients has not been established.
Long-Term Suppression of Growth Growth should be monitored during treatment with stimulants, including Ritalin. Pediatric patients who are not growing or gaining weight as expected may need to have their treatment interrupted [see Warnings and Precautions ( 5.7 )] . Juvenile Animal Toxicity Data Rats treated with methylphenidate early in the postnatal period through sexual maturation demonstrated a decrease in spontaneous locomotor activity in adulthood.
A deficit in acquisition of a specific learning task was observed in females only. The doses at which these findings were observed are at least 4 times the MRHD of 60 mg/day given to children on a mg/m 2 basis. In a study conducted in young rats, methylphenidate was administered orally at doses of up to 100 mg/kg/day for 9 weeks, starting early in the postnatal period (postnatal Day 7) and continuing through sexual maturity (postnatal Week 10).
When these animals were tested as adults (postnatal Weeks 13 to 14), decreased spontaneous locomotor activity was observed in males and females previously treated with 50 mg/kg/day (approximately 4 times the MRHD of 60 mg/day given to children on a mg/m 2 basis) or greater, and a deficit in the acquisition of a specific learning task was seen in females exposed to the highest dose (8 times the MRHD given to children on a mg/m 2 basis). The no effect level for juvenile neurobehavioral development in rats was 5 mg/kg/day ( approximately 0.5 times the MRHD given to children on a mg/m 2 basis).
The clinical significance of the long-term behavioral effects observed in rats is unknown.
🧓 Geriatric Use ▾
8.5Geriatric Use Ritalin has not been studied in the geriatric population.
🆘 Overdosage ▾
10 OVERDOSAGE Clinical Effects of Overdose Overdose of CNS stimulants is characterized by the following sympathomimetic effects: • Cardiovascular effects including tachyarrhythmias, and hypertension or hypotension. Vasospasm, myocardial infarction, or aortic dissection may precipitate sudden cardiac death. Takotsubo cardiomyopathy may develop. • CNS effects including psychomotor agitation, confusion, and hallucinations.
Serotonin syndrome, seizures, cerebral vascular accidents, and coma may occur. • Life-threatening hyperthermia (temperatures greater than 104°F) and rhabdomyolysis may develop. Overdose Management Consider the possibility of multiple drug ingestion. Because methylphenidate has a large volume of distribution and is rapidly metabolized, dialysis is not useful.
Consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdose management recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Methylphenidate hydrochloride is a CNS stimulant. The mode of therapeutic action in ADHD and narcolepsy is not known.
12.2Pharmacodynamics Methylphenidate is a racemic mixture comprised of the d- and l-threo enantiomers. The d-threo enantiomer is more pharmacologically active than the l-threo enantiomer. Methylphenidate blocks the reuptake of norepinephrine and dopamine into the presynaptic neuron and increases the release of these monoamines into the extraneuronal space.
Cardiac Electrophysiology A formal QT study has not been conducted in patients taking Ritalin. The effect of dexmethylphenidate, the pharmacologically active d- enantiomer of Ritalin, on the QT interval was evaluated in a double-blind, placebo- and open-label active (moxifloxacin)-controlled study following single doses of dexmethlyphenidate XR 40 mg (maximum recommended adult total daily dosage) in 75 healthy volunteers. Electrocardiograms were collected up to 12 hours postdose.
Frederica’s method for heart rate correction was employed to derive the corrected QT interval (QTcF). The maximum mean prolongation of QTcF intervals was less than 5 ms, and the upper limit of the 90% confidence interval was below 10 ms for all time-matched comparisons versus placebo. This was below the threshold of clinical concern and there was no evident exposure response relationship.
12.3Pharmacokinetics Absorption The absolute bioavailability of methylphenidate is 22 ± 8 % for the d-enantiomer and 5 ± 3 % for the l-enantiomer. Peak plasma concentrations of approximately 4.3 ± 2.3 ng/mL were reached on an average of 2 hours after administration of 10 mg tablet. The time to peak rate in children was 1.9 hours (0.3 to 4.4 hours) for Ritalin.
Effect of Food Ingestion with food has no relevant effect on absorption of Ritalin. Distribution Binding to plasma proteins is low (10% to 33%). The volume of distribution was 2.65 ±
1.11L/kg for d-methylphenidate and 1.80 ±
0.91L/kg for l -methylphenidate. Elimination The systemic clearance is 0.40 ±
0.12L/h/kg for d-methylphenidate and 0.73 ±
0.28L/h/kg for l -methylphenidate. Metabolism Methylphenidate is metabolized primarily by de-esterification to alpha-phenyl-piperidine acetic acid (ritalinic acid), which has little or no pharmacologic activity. Excretion After oral administration, 78% to 97% of the dose is excreted in the urine and 1% to 3% in feces in the form of metabolites within 48 to 96 hours.
Most of the dose is excreted in the urine as alpha-phenyl-2-piperidine acetic acid (60% to 86%). Studies in Specific Populations Male and Female Patients No gender differences in the pharmacokinetics of methylphenidate between healthy male and female adults are expected. Racial or Ethnic Groups There is insufficient experience with the use of Ritalin to detect ethnic variations in pharmacokinetics.
Patients with Renal Impairment Ritalin has not been studied in renally-impaired patients. Renal impairment is expected to have minimal effect on the pharmacokinetics of methylphenidate since less than 1% of a radiolabeled dose is excreted in the urine as unchanged compound, and the major metabolite (ritalinic acid), has little or no pharmacologic activity. Patients with Hepatic Impairment Ritalin has not been studied in patients with hepatic impairment.
Hepatic impairment is expected to have minimal effect on the pharmacokinetics of methylphenidate since it is metabolized primarily to ritalinic acid by nonmicrosomal hydrolytic esterases that are widely distributed throughout the body.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Methylphenidate hydrochloride is a CNS stimulant. The mode of therapeutic action in ADHD and narcolepsy is not known.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING • 5 mg tablets (NDC 66758-273-01) round, yellow, (imprinted "CIBA 7") supplied in bottles of 100 • 10 mg tablets (NDC 66758-274-01) round, pale green, scored, (imprinted "CIBA 3") supplied in bottles of 100 • 20 mg tablets (NDC 66758-275-01) round, pale yellow, scored, (imprinted "CIBA 34") supplied in bottles of 100 Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C and 30°C (59°F and 86°F) [see USP controlled room temperature]. Protect from light. Dispense in tight, light-resistant container (USP).
📋 Description ▾
11 DESCRIPTION Ritalin contains methylphenidate hydrochloride, a CNS stimulant. It is available as tablets of 5 mg, 10 mg, and 20 mg strengths for oral administration. Methylphenidate hydrochloride is methyl α-phenyl-2-piperidineacetate hydrochloride, and its structural formula is: Methylphenidate hydrochloride USP is a white, odorless, fine crystalline powder.
Its solutions are acid to litmus. It is freely soluble in water and in methanol, soluble in alcohol, and slightly soluble in chloroform and in acetone. Its molecular weight is 269.77 g/mol.
Ritalin tablets contains the following inactive ingredients: D&C Yellow No. 10 (5-mg and 20-mg tablets), FD&C Green No. 3 (10-mg tablets), lactose, magnesium stearate, polyethylene glycol, starch (5-mg and 10-mg tablets), sucrose, talc, and tragacanth (20-mg tablets).
Methylphenidate hydrochloride structural formula.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Abuse, Misuse, and Addiction Educate patients and their families about the risks of abuse, misuse, and addiction of Ritalin, which can lead to overdose and death, and proper disposal of any unused drug [see Warnings and Precautions ( 5.1 ), Drug Abuse and Dependence ( 9.2 ), Overdosage ( 10 )] . Advise patients to store Ritalin in a safe place, preferably locked, and instruct patients to not give Ritalin to anyone else.
Risks to Patients with Serious Cardiac Disease Advise patients that there are potential risks to patient with serious cardiac disease, including sudden death, with Ritalin use. Instruct patients to contact a healthcare provider immediately if they develop symptoms, such as exertional chest pain, unexplained syncope, or other symptoms suggestive of cardiac disease [see Warnings and Precautions ( 5.2 )]. Increased Blood Pressure and Heart Rate Instruct patients that Ritalin can cause elevations of their blood pressure and pulse rate [see Warnings and Precautions ( 5.3 )] .
Psychiatric Adverse Reactions Advise patients that Ritalin, at recommended doses, can cause psychotic or manic symptoms, even in patients without prior history of psychotic symptoms or mania [see Warnings and Precautions ( 5.4 )] . Priapism Advise patients of the possibility of painful or prolonged penile erections (priapism). Instruct them to seek immediate medical attention in the event of priapism [see Warnings and Precautions ( 5.5 )] .
Circulation Problems in Fingers and Toes [Peripheral Vasculopathy, Including Raynaud’s Phenomenon] Instruct patients about the risk of peripheral vasculopathy, including Raynaud’s phenomenon, and associated signs and symptoms: fingers or toes may feel numb, cool, painful, and/or may change color from pale, to blue, to red. Instruct patients to report to their physician any new numbness, pain, skin color change, or sensitivity to temperature in fingers or toes. Instruct patients to call their physician immediately with any signs of unexplained wounds appearing on fingers or toes while taking Ritalin.
Further clinical evaluation (e.g., rheumatology referral) may be appropriate for certain patients [see Warnings and Precautions ( 5.6 )] . Long-Term Suppression of Growth in Pediatric Patients Advise patients that Ritalin may cause slowing of growth and weight loss [see Warnings and Precautions ( 5.7 )] . Increased Intraocular Pressure (IOP) and Glaucoma Advise patients that IOP and glaucoma may occur during treatment with Ritalin [see Warnings and Precautions ( 5.9 )] .
Motor and Verbal Tics, and Worsening of Tourette’s Syndrome Advise patients that motor and verbal tics and worsening of Tourette’s Syndrome may occur during treatment with Ritalin. Instruct patients to notify their healthcare provider if emergence of new tics or worsening of tics or Tourette’s syndrome occurs [see Warnings and Precautions ( 5.10 )]. Pregnancy Registry Advise patients that there is a pregnancy exposure registry that monitors pregnancy outcomes in patients exposed to ADHD medications, including RITALIN, during pregnancy [see Use in Specific Populations ( 8.1 )] .
Manufactured by Societal CDMO Gainesville, LLC Gainesville, GA 30504 for Sandoz Inc., Princeton, NJ 08540
💬 Medication Guide ▾
MEDICATION GUIDE RITALIN ® (rit-ah-lin) (methylphenidate hydrochloride) tablets, for oral use, CII What is the most important information I should know about RITALIN? RITALIN may cause serious side effects, including: • Abuse, misuse, and addiction. RITALIN has a high chance for abuse and misuse and may lead to substance use problems, including addiction.
Misuse and abuse of RITALIN, other methylphenidate containing medicines, and amphetamine containing medicines, can lead to overdose and death. The risk of overdose and death is increased with higher doses of RITALIN or when it is used in ways that are not approved, such as snorting or injection. o Your healthcare provider should check you or your child’s risk for abuse, misuse, and addiction before starting treatment with RITALIN and will monitor you or your child during treatment. o RITALIN may lead to physical dependence after prolonged use, even if taken as directed by your healthcare provider. o Do not give RITALIN to anyone else.
See “ What is RITALIN? ” for more information. o Keep RITALIN in a safe place and properly dispose of any unused medicine. See “ How should I store RITALIN? ” for more information. o Tell your healthcare provider if you or your child have ever abused or been dependent on alcohol, prescription medicines, or street drugs. • Risks for people with serious heart disease. Sudden death has happened in people who have heart defects or other serious heart disease.
Your healthcare provider should check you or your child carefully for heart problems before starting RITALIN. Tell your healthcare provider if you or your child have any heart problems, heart disease, or heart defects. Call your healthcare provider or go to the nearest hospital emergency room right away if you or your child has any signs of heart problems, such as chest pain, shortness of breath, or fainting while taking RITALIN. • Increased blood pressure and heart rate.
Your healthcare provider should check you or your child’s blood pressure and heart rate regularly during treatment with RITALIN. • Mental (psychiatric) problems: All Patients o new or worse behavior and thought problems o new or worse bipolar illness o new psychotic symptoms (such as hearing voices, believing things that are not true, are suspicious) or new manic symptoms Tell your healthcare provider about any mental problems you or your child have, or about a family history of suicide, bipolar illness, or depression.
Call your healthcare provider right away if you or your child have any new or worsening mental symptoms or problems while taking RITALIN, especially seeing or hearing things that are not real, believing things that are not real, or are suspicious. What is RITALIN? • RITALIN is a central nervous system (CNS) stimulant prescription medicine. It is used for the treatment of Attention Deficit Hyperactivity Disorder (ADHD).
RITALIN may help increase attention and decrease impulsiveness and hyperactivity in patients with ADHD. • RITALIN should be used as a part of a total treatment program for ADHD that may include counseling or other therapies. • RITALIN is also used in the treatment of a sleep disorder called narcolepsy. It is not known if RITALIN is safe and effective in children under 6 years of age. RITALIN is a federally controlled substance (CII) because it contains methylphenidate that can be a target for people who abuse prescription medicines or street drugs.
Keep RITALIN in a safe place to protect it from theft. Never give your RITALIN to anyone else, because it may cause death or harm them. Selling or giving away RITALIN may harm others and is against the law.
Who should not take RITALIN? RITALIN should not be taken if you or your child: • are allergic to methylphenidate hydrochloride, or any of the ingredients in RITALIN. See the end of this Medication Guide for a complete list of ingredients in RITALIN. • are taking or have taken within the past 14 days an anti-depression medicine called a monoamine oxid…