
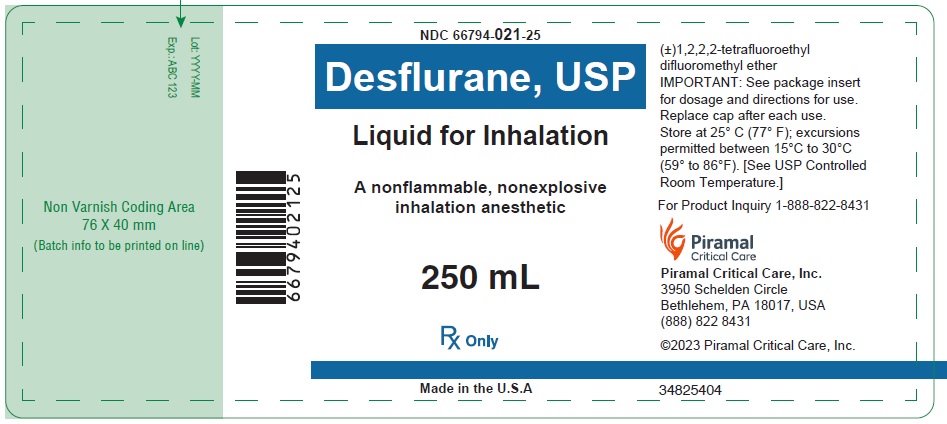
Desflurane 250 mL/250mL Liquid
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the General Anesthetic class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Desflurane is a general anesthetic — a gas you breathe in through a mask or breathing tube that puts you into a controlled state of unconsciousness so you don't feel anything durin...
- What exactly is desflurane and why is my doctor using it for my surgery?
- The most common things people notice after surgery with desflurane are nausea and vomiting — about 1 in 4 patients experience this. You may also have a mild sore throat or a headac...
- What side effects should I expect when I wake up?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Desflurane — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Suprane 240 mL/240mL 00404-9961-25 | Henry | 1 bottle | — | — | FDA listed | — |
| Desflurane 240 mL/240mL 00781-6172-86 | Sandoz | 6 bottles | — | — | FDA listed | — |
| Suprane 240 mL/240mL 10019-0641-24 | Baxter | 6 bottles | — | — | Discontinued | — |
| Suprane 240 mL/240mL 10019-0644-24 | Baxter | 6 bottles | — | — | Discontinued | — |
| Suprane 240 mL/240mL 10019-0646-24 | Baxter | 6 bottles | — | — | Discontinued | — |
| Desflurane 250 mL/250mLthis 66794-0021-35 | Piramal | 6 bottles | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 66794-0021-25 | 250 mL in 1 BOTTLE, GLASS (66794-021-25) | 2023-02-14 | Active |
| 66794-0021-35 You're viewing this | 6 BOTTLE in 1 CARTON (66794-021-35) / 250 mL in 1 BOTTLE (66794-021-20) | 2026-07-01 | Active |
Pack size FAQ
What quantity is in NDC 66794-0021-35?
What NDC number is used to bill for this package of Desflurane 250 mL/250mL Liquid?
🧭 About this NDC listing & data coverage
Listed without an FDA application
This product's marketing category indicates it is marketed without an approved FDA application (no NDA, ANDA, or BLA on file). Having an NDC does not by itself establish FDA approval — the NDC Directory is a listing system, not an approval decision. Approval-linked data such as Orange Book therapeutic-equivalence ratings therefore does not apply.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Is this NDC FDA-approved?
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Desflurane, USP, liquid for inhalation a general anesthetic, is an inhalation agent indicated: • for induction and/or maintenance of anesthesia in adults ( 1.1 ) • for maintenance of anesthesia in pediatric patients following induction with agents other than Desflurane, USP, liquid for inhalation and intubation.
1.1Induction of Anesthesia Desflurane USP, liquid for inhalation is indicated as an inhalation agent for induction of anesthesia for inpatient and outpatient surgery in adults. Desflurane, USP, liquid for inhalation is contraindicated as an inhalation agent for the induction of anesthesia in pediatric patients because of a high incidence of moderate to severe upper airway adverse events.
1.2Maintenance of Anesthesia Desflurane USP, liquid for inhalation is indicated as an inhalation agent for maintenance of anesthesia for inpatient and outpatient surgery in adults and in pediatric patients. After induction of anesthesia with agents other than Desflurane USP, liquid for inhalation and tracheal intubation, Desflurane USP, liquid for inhalation is indicated for maintenance of anesthesia in infants and children. Desflurane USP, liquid for inhalation is not approved for maintenance of anesthesia in non-intubated children due to an increased incidence of respiratory adverse reactions, including coughing, laryngospasm, and secretions [ see Warnings and Precautions ( 5.3 ) and Clinical Studies ( 14.5 ) ] .
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Only persons trained in the administration of general anesthesia should administer Desflurane. Only a vaporizer specifically designed and designated for use with desflurane should be utilized for its administration. Facilities for maintenance of a patent airway, artificial ventilation, oxygen enrichment, and circulatory resuscitation must be immediately available.
Desflurane administered by inhalation. The administration of general anesthesia must be individualized based on the patient's response. Hypotension and respiratory depression increase as anesthesia with desflurane is deepened.
The minimum alveolar concentration (MAC) of desflurane decreases with increasing patient age. The MAC for Desflurane is also reduced by concomitant N 2 O administration ( see Table 1 ). The dose should be adjusted accordingly.
The following table provides mean relative potency based upon age and effect of N 2 O in predominately ASA physical status I or II patients. Benzodiazepines and opioids decrease the MAC of Desflurane . [see Drug Interactions ( 7.1 , Table 3)]. Desflurane also decreases the doses of neuromuscular blocking agents required [ see Drug Interactions ( 7.2 , Table 4) ] .
The dose should be adjusted accordingly. Table 1 Effect of Age on Minimum Alveolar Concentration of Desflurane Mean ± SD (percent atmospheres) Age N O 2 100% N N 2 O 60% / 40% O 2 2 weeks 6 9.2 ± 0.0 - - 10 weeks 5 9.4 ± 0.4 - - 9 months 4 10.0 ± 0.7 5 7.5 ± 0.8 2 years 3 9.1 ± 0.6 - - 3 years - - 5 6.4 ± 0.4 4 years 4 8.6 ± 0.6 - - 7 years 5 8.1 ± 0.6 - - 25 years 4 7.3 ± 0.0 4 4.0 ± 0.3 45 years 4 6.0 ± 0.3 6 2.8 ± 0.6 70 years 6 5.2 ± 0.6 6 1.7 ±
0.4N = number of crossover pairs (using up-and-down method of quantal response) • Desflurane should be administered only by persons trained in the administration of general anesthesia. It should only be administered using a vaporizer specifically designed and designated for use with Desflurane. ( 2 ) • The administration of general anesthesia must be individualized based on the patient’s response, including cardiovascular and pulmonary changes.
( 2 ) • Desflurane should not be used as the sole agent for anesthetic induction in patients with coronary artery disease or where increases in heart rate or blood pressure are undesirable. ( 2.6 ) • For dosing considerations in patients with intracranial space occupying lesions, see Full Prescribing Information. ( 2.7 )
2.1Preanesthetic Medication Issues such as whether or not to premedicate and the choice of premedication(s) must be individualized. In clinical studies, patients scheduled to be anesthetized with Desflurane frequently received IV preanesthetic medication, such as opioid and/or benzodiazepine.
2.2Induction In adults, some premedicated with opioid, a frequent starting concentration was 3% Desflurane increased in 0.5-1.0% increments every 2 to 3 breaths. End-tidal concentrations of 4-11%, Desflurane with and without N 2 O, produced anesthesia within 2 to 4 minutes. When Desflurane was tested as the primary anesthetic induction agent, the incidence of upper airway irritation (apnea, breathholding, laryngospasm, coughing and secretions) was high.
During induction in adults, the overall incidence of oxyhemoglobin desaturation (SpO 2 < 90%) was 6% [ see Adverse Reactions ( 6.1 ) ]. After induction in adults with an intravenous drug such as thiopental or propofol, Desflurane can be started at approximately 0.5-1 MAC, whether the carrier gas is O 2 or N 2 O/O 2 . Inspired concentrations of Desflurane greater than 12% have been safely administered to patients, particularly during induction of anesthesia.
Such concentrations will proportionately dilute the concentration of oxygen; therefore, maintenance of an adequate concentration of oxygen may require a reduction of nitrous oxide or air if these gases are used concurrently.
2.3Maintenance Surgical levels of anesthesia in adults may be maintained with concentrations of 2.5-8.5% Desflur…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Desflurane USP, liquid for inhalation is a colorless, non-flammable, volatile liquid (below 22.8 o C) for inhalation, 100% desflurane. Liquid (volatile): 100% ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS The use of Desflurane is contraindicated in the following conditions: • Known or suspected genetic susceptibility to malignant hyperthermia [see Warnings and Precautions ( 5.1 ), Clinical Pharmacology ( 12.5 )]. • Patients in whom general anesthesia is contraindicated. • Induction of anesthesia in pediatric patients. • Patients with known sensitivity to Desflurane or to other halogenated agents [ see Warnings and Precautions ( 5.5 )]. • Patients with a history of moderate to severe hepatic dysfunction following anesthesia with Desflurane or other halogenated agents and not otherwise explained [ see Warnings and Precautions ( 5.5 ) ]. • Patients with known or suspected genetic susceptibility to malignant hyperthermia ( 4 ) • Patients in whom general anesthesia is contraindicated ( 4 ) • Induction of anesthesia in pediatric patients ( 4 ) • Patients with known sensitivity to halogenated agents ( 4 ) • Patients with a history of moderate to severe hepatic dysfunction following anesthesia with halogenated agents and not otherwise explained.
( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Malignant Hyperthermia : Malignant hyperthermia may occur, especially in individuals with known or suspected susceptibility based on genetic factors or family history. Discontinue triggering agents, administer intravenous dantrolene sodium, and apply supportive therapies. ( 5.1 ) • Perioperative Hyperkalemia : Perioperative hyperkalemia may occur.
Patients with latent or overt neuromuscular disease, particularly with Duchenne muscular dystrophy, appear to be most vulnerable. Early, aggressive intervention is recommended. ( 5.2 ) • Respiratory Adverse Reactions in Pediatric Patients : - Not approved for maintenance of anesthesia in non-intubated children due to an increased incidence of respiratory adverse reactions.
Monitor and treat accordingly.( 5.3 ) - May cause airway narrowing and increased airway resistance in children with asthma or a history of recent upper airway infection. Monitor and treat accordingly.( 5.3 ) • QTc Prolongation : Carefully monitor cardiac rhythm when administering Desflurane to susceptible patients. ( 5.4 ) • Interactions with Desiccated Carbon Dioxide (CO 2 ) Absorbents : May react with desiccated CO 2 absorbents to produce carbon monoxide.
Replace desiccated CO 2 absorbent before administration of Desflurane. ( 5.5 ) • Hepatobiliary Disorders : May cause sensitivity hepatitis in patients sensitized by previous exposure to halogenated anesthetics. Approach repeated anesthesia with caution.
( 5.6 ) • Pediatric Neurotoxicity : In developing animals, exposures greater than 3 hours cause neurotoxicity. Weigh benefits against potential risks when considering elective procedures in children under 3 years old. ( 5.7 ) • Postoperative Agitation in Children : May cause postoperative agitation during emergence from anesthesia in children.
( 5.9 )
5.1Malignant Hyperthermia In susceptible individuals, volatile anesthetic agents, including desflurane, may trigger malignant hyperthermia, a skeletal muscle hypermetabolic state leading to high oxygen demand. Fatal outcomes of malignant hyperthermia have been reported. The risk of developing malignant hyperthermia increases with the concomitant administration of succinylcholine and volatile anesthetic agents.
Desflurane can induce malignant hyperthermia in patients with known or suspected susceptibility based on genetic factors or family history, including those with certain inherited ryanodine receptor ( RYR1 ) or dihydropyridine receptor ( CACNA1S ) variants. [see Contraindications ( 4 ), Clinical Pharmacology ( 12.5 )] Signs consistent with malignant hyperthermia may include hyperthermia, hypoxia, hypercapnia, muscle rigidity (e.g., jaw muscle spasm), tachycardia (e.g., particularly that unresponsive to deepening anesthesia or analgesic medication administration), tachypnea, cyanosis, arrhythmias, hypovolemia, and hemodynamic instability.
Skin mottling, coagulopathies, and renal failure may occur later in the course of the hypermetabolic process. Successful treatment of malignant hyperthermia depends on early recognition of the clinical signs. If malignant hyperthermia is suspected, discontinue all triggering agents (i.e., volatile anesthetic agents and succinylcholine), administer intravenous dantrolene sodium, and initiate supportive therapies.
Consult prescribing information for intravenous dantrolene sodium for additional information on patient management. Supportive therapies include administration of supplemental oxygen and respiratory support based on clinical need, maintenance of hemodynamic stability and adequate urinary output, management of fluid and electrolyte balance, correction of acid base derangements, and institution of measures to control rising temperature.
5.2Perioperative Hyperkalemia Use of inhaled anesthetic agents has been associated with rare increases in serum potassium levels that have resulted in cardiac arrhythmias and death in pediatric patients during the postoperative period. Patients with latent…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (incidence> 10%) are coughing, breath holding, apnea, nausea, vomiting. ( 6 ) To report SUSPECTED ADVERSE REACTIONS, Piramal Critical Care, Inc. at 1-888-822-8431 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse event information is derived from controlled clinical trials, the majority of which were conducted in the United States. The studies were conducted using a variety of premedications, other anesthetics, and surgical procedures of varying length.
Most adverse events reported were mild and transient, and may reflect the surgical procedures, patient characteristics (including disease) and/or medications administered. Of the 2,143 patients exposed to Desflurane in clinical trials, 370 adults and 152 children were induced with desflurane alone and 987 patients were maintained principally with desflurane. The frequencies given reflect the percent of patients with the event.
Each patient was counted once for each type of adverse event. They are presented in alphabetical order according to body system. Table 2 Frequency of Events Occurring in Greater Than 1% of Clinical Trial Patients (in Reports Deemed “Probably Causally Related”) Induction (use as a mask inhalation agent) Adult Patients (N=370) : Coughing 34%, breathholding 30%, apnea 15%, increased secretions*, laryngospasm*, oxyhemoglobin desaturation (SpO 2< 90%)*, pharyngitis*.
Maintenance or Recovery Adult and Intubated Pediatric Patients (N=687): Body as a Whole Headache Cardiovascular Bradycardia, hypertension, nodal arrhythmia, tachycardia Digestive Nausea 27%, vomiting 16% Nervous System Increased salivation Respiratory Apnea*, breathholding, cough increased*, laryngospasm*, pharyngitis Special Senses Conjunctivitis (conjunctival hyperemia) *Incidence of events 3% - 10% Frequency of Events Occurring in Less Than 1% of Patients (in Reports Deemed “Probably Causally Related”) Reported in 3 or more patients, regardless of severity Adverse reactions reported only from postmarketing experience or in the literature, not seen in clinical trials, are considered rare and are italicized.
Cardiovascular Arrhythmia, bigeminy, abnormal electrocardiogram, myocardial ischemia, vasodilation Digestive Hepatitis Nervous System Agitation, dizziness Respiratory Asthma, dyspnea, hypoxia Frequency of Events Occurring in Less Than 1% of Clinical Trial Patients (in Reports Deemed “Causal Relationship Unknown”) Reported in 3 or more patients , regardless of severity Body as a Whole Fever Cardiovascular Hemorrhage, myocardial infarction Metabolic and Nutrition Increased creatinine phosphokinase Musculoskeletal System Myalgia Skin and Appendages Pruritus
6.2Postmarketing Experience The following adverse reactions have been identified during post-approval use of Desflurane. Because these reactions are reported voluntarily from a population of uncertain size, it is not possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Blood and Lymphatic System Disorders: Coagulopathy Metabolism and Nutrition Disorders: Hyperkalemia, Hypokalemia, metabolic acidosis Nervous System Disorders: Convulsion, Post-operative agitation in children Eye Disorders: Ocular icterus Cardiac Disorders: Cardiac arrest, QTc prolongation, Torsade de pointes, ventricular failure, ventricular hypokinesia, atrial fibrillation Vascular Disorders: Malignant hypertension, hemorrhage, hypotension, shock Respiratory, Thoracic and Mediastinal Disorders: Respiratory arrest, respiratory failure, respiratory distress, bronchospasm, hemoptysis Gastrointestinal Disorders: Pancreatitis acute, abdominal pain Hepatobiliary Disorders: Hepatic failure,…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS No clinically significant adverse interactions with commonly used preanesthetic drugs, or drugs used during anesthesia (muscle relaxants, intravenous agents, and local anesthetic agents) were reported in clinical trials. The effect of Desflurane on the disposition of other drugs has not been determined. Similar to isoflurane, desflurane does not predispose to premature ventricular arrhythmias in the presence of exogenously infused epinephrine in swine. • Concomitant use of N 2 O, benzodiazepines and/or opioids reduces the MAC of Desflurane.
Adjust dose accordingly. ( 7.1 , 7.3 ) • Desflurane decreases the doses of neuromuscular blocking agents required. Adjust dose accordingly.
( 7.2 )
7.1Benzodiazepines and Opioids (MAC Reduction) Benzodiazepines and opioids decrease the amount of desflurane (MAC) needed to produce anesthesia. This effect is shown in Table 3 for intravenous midazolam (25-50 mcg/kg) and intravenous fentanyl (3-6 mcg/kg) in patients of two different age groups. Table 3 Desflurane MAC with Fentanyl or Midazolam Mean ± SD (percent reduction) Dose 18-30 years 31-65 years No fentanyl 6.4 ± 0.0 6.3 ± 0.4 3 mcg/kg fentanyl 3.5 ± 1.9 (46%) 3.1 ± 0.6 (51%) 6 mcg/kg fentanyl 3.5 ± 1.9 (46%) 2.3 ± 1.0 (64%) No midazolam 6.9 ± 0.1 5.9 ± 0.6 25 mcg/kg midazolam - 4.9 ± 0.9 (16%) 50 mcg/kg midazolam - 4.9 ± 0.5 (17%)
7.2Neuromuscular Blocking Agents Anesthetic concentrations of desflurane at equilibrium (administered for 15 or more minutes before testing) reduced the ED 95 of succinylcholine by approximately 30% and that of atracurium and pancuronium by approximately 50% compared to N 2 O/opioid anesthesia (see Table 4) . The effect of desflurane on duration of nondepolarizing neuromuscular blockade has not been studied. Table 4 Dosage of Muscle Relaxant Causing 95% Depression in Neuromuscular Blockade Desflurane Concentration Mean ED 95 (mcg/kg) Pancuronium Atracurium Succinylcholine Vecuronium
0.65 MAC 60% N 2 O/O 2 26 133 - -
1.25 MAC 60% N 2 O/O 2 18 119 - -
1.25MAC O 2 22 120 360 19 Dosage reduction of neuromuscular blocking agents during induction of anesthesia may result in delayed onset of conditions suitable for endotracheal intubation or inadequate muscle relaxation, because potentiation of neuromuscular blocking agents requires equilibration of muscle with the delivered partial pressure of Desflurane. Among nondepolarizing drugs, pancuronium, atracurium and vecuronium interactions have been studied. In the absence of specific guidelines: 1.
For endotracheal intubation, do not reduce the dose of nondepolarizing muscle relaxants or succinylcholine. 2. During maintenance of anesthesia, the dose of nondepolarizing muscle relaxants is likely to be reduced compared to that during N 2 O/opioid anesthesia.
Administration of supplemental doses of muscle relaxants should be guided by the response to nerve stimulation.
7.3Concomitant use with N 2 O Concomitant administration of N 2 O reduces the MAC of Desflurane [see Dosage and Administration ( 2 ), Table 1].
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS .. • Geriatric Use : The minimum alveolar concentration (MAC) of Desflurane decreases with increasing patient age. ( 8.5 ) See 17 for PATIENT COUNSELING INFORMATION. Revised: 06/2025
8.1Pregnancy Risk Summary There are no adequate and well-controlled studies in pregnant women. In animal reproduction studies, embryo-fetal toxicity (reduced viable fetuses and/or increased post-implantation loss) was noted in pregnant rats and rabbits administered 1 MAC desflurane for 4 hours a day (4 MAC-hours/day) during organogenesis. Published studies in pregnant primates demonstrate that the administration of anesthetic and sedation drugs that block NMDA receptors and/or potentiate GABA activity during the period of peak brain development increases neuronal apoptosis in the developing brain of the offspring when used for longer than 3 hours.
There are no data on pregnancy exposures in primates corresponding to periods prior to the third trimester in humans [See Data]. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15- 20%, respectively. Clinical Considerations Labor or Delivery The safety of Desflurane during labor or delivery has not been demonstrated. Desflurane is a uterine-relaxant.
Data Animal Data Pregnant rats were exposed to 8.2% desflurane (1 MAC; 60% oxygen) for 0.5, 1.0, or 4.0 hours (0.5, 1.0, or
4.0MAC-hours) per day during organogenesis (Gestation Day 6-15). Embryo-fetal toxicity (increased post-implantation loss and reduced viable fetuses) was noted in the 4 hour treatment group in the presence of maternal toxicity (reduced body weight gain). There was no evidence of malformations in any group.
Pregnant rabbits were exposed to 8.9% desflurane (1 MAC; 60% oxygen) for 0.5, 1.0, or 3.0 hours per day during organogenesis (Gestation Days 6-18). Fetal toxicity (reduced viable fetuses) was noted in the 3 hour treatment group in the presence of maternal toxicity (reduced body weight). There was no evidence of malformations in any group.
Pregnant rats were exposed to 8.2% desflurane (1 MAC; 60% oxygen) for 0.5, 1.0, or 4.0 hours per day from late gestation and through lactation (Gestation Day 15 to Lactation Day 21). Pup body weights were reduced in the 4 hours per day group in the presence of maternal toxicity (increased mortality and reduced body weight gain). This study did not evaluate neurobehavioral function including learning and memory or reproductive behavior in the first generation (F1) pups.
In a published study in primates, administration of an anesthetic dose of ketamine for 24 hours on Gestation Day 122 increased neuronal apoptosis in the developing brain of the fetus. In other published studies, administration of either isoflurane or propofol for 5 hours on Gestation Day 120 resulted in increased neuronal and oligodendrocyte apoptosis in the developing brain of the offspring. With respect to brain development, this time period corresponds to the third trimester of gestation in the human.
The clinical significance of these findings is not clear; however, studies in juvenile animals suggest neuroapoptosis correlates with long-term cognitive deficits [See Warnings and Precautions ( 5.6 ), Use in Specific Populations ( 8.4 ), and Nonclinical Toxicology ( 13.2 )].
8.2Lactation It is not known whether this drug is excreted in human milk. Because many drugs are excreted in human milk, caution should be exercised when Desflurane is administered to a nursing woman.
8.4Pediatric Use Respiratory Adverse Reactions in Pediatric Patients Desflurane is indicated for maintenance of anesthesia in infants and children after induction of anesthesia with agents other than Desflurane, and tracheal intubation. Is…
🆘 Overdosage ▾
10 OVERDOSAGE The symptoms of overdosage of Desflurane can present as a deepening of anesthesia, cardiac and/or respiratory depression in spontaneously breathing patients, and cardiac depression in ventilated patients in whom hypercapnia and hypoxia may occur only at a late stage. In the event of overdosage, or suspected overdosage, take the following actions: discontinue administration of Desflurane, maintain a patent airway, initiate assisted or controlled ventilation with oxygen, and maintain adequate cardiovascular function.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.2Pharmacodynamics Changes in the clinical effects of desflurane rapidly follow changes in the inspired concentration. The duration of anesthesia and selected recovery measures for Desflurane are given in the following tables: In 178 female outpatients undergoing laparoscopy, premedicated with fentanyl (1.5-2.0 mcg/kg), anesthesia was initiated with propofol 2.5 mg/kg, desflurane/N 2 O 60% in O 2 or desflurane/O 2 alone. Anesthesia was maintained with either propofol 1.5-9.0 mg/kg/hr, desflurane 2.6-8.4% in N 2 O 60% in O 2 , or desflurane 3.1-8.9% in O 2 .
Emergence and Recovery After Outpatient Laparoscopy 178 Females, Ages 20-47 Times in Minutes: Mean ± SD (Range) Induction: Propofol Propofol Desflurane/ N 2 O Desflurane/ O 2 Maintenance: Propofol/ N 2 O Desflurane/ N 2 O Desflurane/ N 2 O Desflurane/ O 2 Number of Pts: N = 48 N = 44 N = 43 N = 43 Median age 30 (20 – 43) 26 (21 – 47) 29 (21 – 42) 30 (20 – 40) Anesthetic Time 49 ± 53 (8 – 336) 45 ± 35 (11 – 178) 44 ± 29 (14 – 149) 41 ± 26 (19 – 126) Time to open eyes 7 ± 3 (2 – 19) 5 ± 2* (2 – 10) 5 ± 2* (2 – 12) 4 ± 2* (1 – 11) Time to state name 9 ± 4 (4 – 22) 8 ± 3 (3 – 18) 7 ± 3* (3 – 16) 7 ± 3* (2 – 15) Time to stand 80 ± 34 (40 – 200) 86 ± 55 (30 – 320) 81 ± 38 (35 – 190) 77 ± 38 (35 – 200) Time to walk 110 ± 6 (47 – 285) 122 ± 85 (37 – 375) 108 ± 59 (48 – 220) 108 ± 66 (49 – 250) Time to fit for discharge 152 ± 75 (66 – 375) 157 ± 80 (73 – 385) 150 ± 66 (68 – 310) 155 ± 73 (69 – 325) *Differences were statistically significant (p < 0.05) by Dunnett's procedure comparing all treatments to the propofol- propofol/N 2 O (induction and maintenance) group.
Results for comparisons greater than one hour after anesthesia show no differences between groups and considerable variability within groups. In 88 unpremedicated outpatients, anesthesia was initiated with thiopental 3-9 mg/kg or desflurane in O 2 . Anesthesia was maintained with isoflurane 0.7-1.4% in N 2 O 60%, desflurane 1.8-7.7% in N 2 O 60%, or desflurane 4.4-11.9% in O 2.
Emergence and Recovery Times in Outpatient Surgery 46 Males, 42 Females, Ages 19-70 Times In Minutes: Mean ± SD (Range) Induction: Thiopental Thiopental Thiopental Desflurane/ O 2 Maintenance: Isoflurane/ N 2 O Desflurane/ N 2 O Desflurane/ O 2 Desflurane/ O 2 Number of Pts: N = 23 N = 21 N = 23 N = 21 Median age 43 (20 – 70) 40 (22 – 67) 43 (19 – 70) 41 (21 – 64) Anesthetic Time 49 ± 23 (11 – 94) 50 ± 19 (16 – 80) 50 ± 27 (16 – 113) 51 ± 23 (19 – 117) Time to open eyes 13 ± 7 (5 – 33) 9 ± 3* (4 – 16) 12 ± 8 (4 – 39) 8 ± 2* (4 – 13) Time to state name 17 ± 10 (6 – 44) 11 ± 4* (6 – 19) 15 ± 10 (6 – 46) 9 ± 3* (5 – 14) Time to walk 195 ± 67 (124 – 365) 176 ± 60 (101 – 315) 168 ± 34 (119 – 258) 181 ± 42 (92 – 252) Time to fit for discharge 205 ± 53 (153 – 365) 202 ± 41 (144 – 315) 197 ± 35 (155 – 280) 194 ± 37 (134 – 288) *Differences were statistically significant (p < 0.05) by Dunnett's procedure comparing all treatments to the thiopental-isoflurane/N 2 O (induction and maintenance) group.
Results for comparisons greater than one hour after anesthesia show no differences between groups and considerable variability within groups. Recovery from anesthesia was assessed at 30, 60, and 90 minutes following
0.5MAC desflurane (3%) or isoflurane (0.6%) in N 2 O 60% using subjective and objective tests. At 30 minutes after anesthesia, only 43% of the patients in the isoflurane group were able to perform the psychometric tests compared to 76% in the desflurane group (p < 0.05). Recovery Tests: Percent of Preoperative Baseline Values 16 Males, 22 Females, Ages 20-65 Percent: Mean ± SD Maintenance: 60 Minutes After Anesthesia 90 Minutes After Anesthesia Desflurane/ N 2 O Isoflurane/ N 2 O Desflurane/ N 2 O Isoflurane/ N 2 O Confusion Δ 66 ± 6 47 ± 8 75 ± 7* 56 ± 8 Fatigue Δ 70 ± 9* 33 ± 6 89 ± 12* 47 ± 8 Drowsiness Δ 66 ± 5* 36 ± 8 76 ± 7* 49 ± 9 Clumsiness Δ 65 ± 5 49 ± 8 80 ± 7* 57 ± 9 Comfort Δ 59 ± 7* 30 ± 6 60 ± 8* 31 ± 7 DSST+…
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED / STORAGE AND HANDLING Desflurane USP, liquid for inhalation is available in an amber-colored glass bottle containing 250 mL of desflurane, USP, NDC 66794-021-25.
16.1Safety and Handling Occupational Caution There is no specific work exposure limit established for Desflurane USP, liquid for inhalation. However, the National Institute for Occupational Safety and Health Administration (NIOSH) recommends that no worker should be exposed at ceiling concentrations greater than 2 ppm of any halogenated anesthetic agent over a sampling period not to exceed one hour. Principle routes of exposure include: Skin contact – May cause skin irritation.
In case of contact, immediately flush skin with plenty of water. Remove contaminated clothing and shoes. Seek medical attention if irritation develops.
Eye contact – May cause eye irritation. In case of contact, immediately flush eyes with plenty of water for at least 15 minutes. Seek medical attention if irritation develops.
Ingestion – No specific hazards other than therapeutic effects. Do NOT induce vomiting unless directed to do so by medical personnel. Never give anything by mouth to an unconscious person.
If large quantities of this material are swallowed, seek medical attention immediately. Inhalation – If individuals smell vapors, or experience dizziness or headaches, they should be moved to an area with fresh air. Individuals could also experience the following: Cardiovascular effects: may include fluctuations in heart rate, changes in blood pressure, chest pain.
Respiratory effects: may include shortness of breath, bronchospasms, laryngospasms, respiratory depression. Gastrointestinal effects: may include nausea, upset stomach, loss of appetite. Nervous System effects: may include ataxia, tremor, disturbance of speech, lethargy, headache, dizziness, blurred vision.
The predicted effects of acute overexposure by inhalation of Desflurane USP, liquid for inhalation include headache, dizziness or (in extreme cases) unconsciousness. [see Overdosage ( 10 )]. There are no documented adverse effects of chronic exposure to halogenated anesthetic vapors ( W aste A nesthetic G ases or WAGs) in the workplace. Although results of some epidemiological studies suggest a link between exposure to halogenated anesthetics and increased health problems (particularly spontaneous abortion), the relationship is not conclusive.
Since exposure to WAGs is one possible factor in the findings for these studies, operating room personnel, and pregnant women in particular, should minimize exposure. Precautions include adequate general ventilation in the operating room, the use of a well-designed and well-maintained scavenging system; work practices to minimize leaks and spills while the anesthetic agent is in use, and routine equipment maintenance to minimize leaks. Consistent with clinical data, concentrations would need to reach 2-3% in inspired air before individuals would likely experience dizziness or other physiologic effects.
16.2Storage Store at 25 ◦ C (77 ◦ F); excursions permitted between 15 ◦ to 30 ◦ C (59 ◦ to 86 ◦ F). [See USP Controlled Room Temperature.] Desflurane USP, liquid for inhalation has been demonstrated to be stable for the period defined by the expiration dating on the label. The bottle should be recapped after each use of Desflurane USP, liquid for inhalation.
📋 Description ▾
11 DESCRIPTION Desflurane USP, liquid for inhalation a nonflammable liquid administered via vaporizer, is a general inhalation anesthetic. It is (±)1,2,2,2-tetrafluoroethyl difluoromethyl ether: Some physical constants are: Molecular weight 168.04 Specific gravity (at 20°C/4°C) 1.465 Vapor pressure in mm Hg 669 mm Hg @ 20°C 731 mm Hg @ 22°C 757 mm Hg @ 22.8°C (boiling point;1atm) 764 mm Hg @ 23°C 798 mm Hg @ 24°C 869 mm Hg @ 26°C Partition coefficients at 37°C: Blood/Gas 0.424 Olive Oil/Gas
18.7 Brain/Gas
0.54 Mean Component/Gas Partition Coefficients Polypropylene (Y piece)
6.7 Polyethylene (circuit tube)
16.2 Latex rubber (bag)
19.3 Latex rubber (bellows)
10.4 Polyvinylchloride (endotracheal tube)
34.7Desflurane USP, liquid for inhalation is nonflammable as defined by the requirements of International Electrotechnical Commission 601-2-13. Desflurane USP, liquid for inhalation is a colorless, volatile liquid below 22.8°C. Data indicate that Desflurane USP, liquid for inhalation is stable when stored under normal room lighting conditions according to instructions.
Desflurane USP, liquid for inhalation is chemically stable. The only known degradation reaction is through prolonged direct contact with soda lime producing low levels of fluoroform (CHF 3 ). The amount of CHF 3 obtained is similar to that produced with MAC-equivalent doses of isoflurane.
No discernible degradation occurs in the presence of strong acids. Desflurane USP, liquid for inhalation does not corrode stainless steel, brass, aluminum, anodized aluminum, nickel plated brass, copper, or beryllium. desflurane-structure