
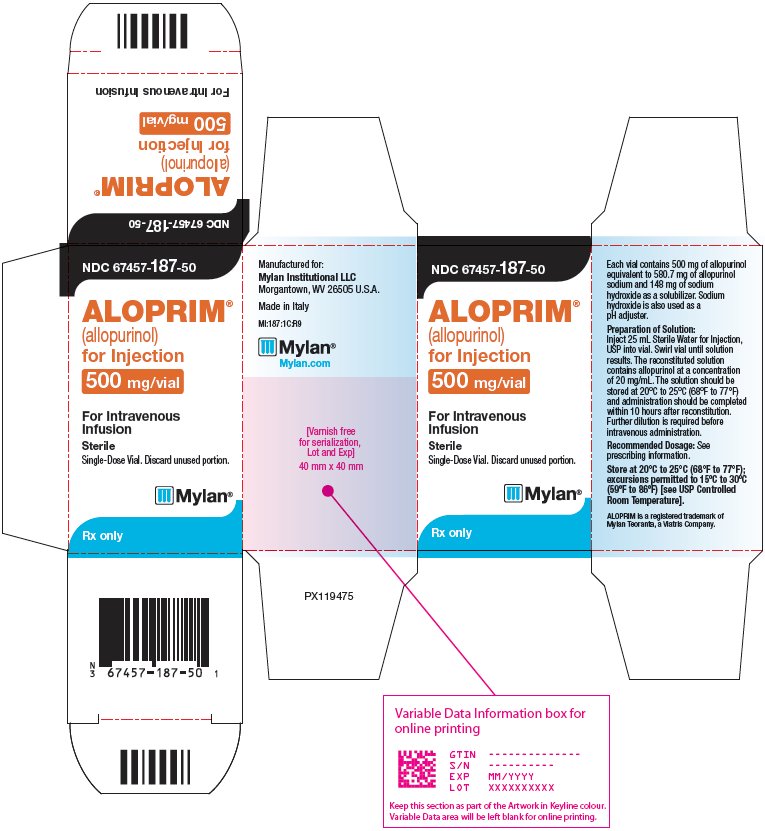
Aloprim Allopurinol 500 mg/25mL Injection, Powder, Lyophilized, For Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Xanthine Oxidase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Allopurinol injection is used to treat high levels of uric acid (a natural substance that builds up in the blood as tumors break down) in people with certain types of cancer who are being treated with chemotherapy medications who cannot take oral allopurinol. Allopurinol is in a class of medications called xanthine oxidase inhibitors. It works by reducing the production of uric acid in the body.
Read the full MedlinePlus article ↗- Aloprim, the IV form of allopurinol, is specifically for people going through chemotherapy who can't take pills — maybe because of nausea, difficulty swallowing, or another medical...
- Why am I getting allopurinol through an IV instead of a pill?
- The biggest thing to watch for is any kind of skin reaction — a rash, blistering, or peeling skin. While rare, allopurinol can cause very serious skin reactions like Stevens-Johnso...
- What's the most important side effect I should watch for?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Allopurinol — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
148 mg / 25 mL
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
1 inactive ingredient listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J0206 | $4.074 / J0206 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Allopurinol sodium 500 mg/25mL 00143-9533-01 | Hikma | 1 vial | — | AP | FDA listed | — |
| Allopurinol 500 mg/25mL 65219-0380-30 | Fresenius | 1 vial | — | AP | FDA listed | — |
| Aloprim 500 mg/25mLthis 67457-0187-50 | Mylan | 1 vial | — | AP | FDA listed | — |
| Allopurinol 500 mg/25mL 68083-0380-01 | Gland | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 67457-0187-50 You're viewing this | 1 VIAL, GLASS in 1 CARTON (67457-187-50) / 25 mL in 1 VIAL, GLASS | 2007-05-15 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ALOPRIM is indicated for the management of adult and pediatric patients with leukemia, lymphoma, and solid tumor malignancies who are receiving cancer therapy which causes elevations of serum and urinary uric acid levels and who cannot tolerate oral therapy. ALOPRIM is a xanthine oxidase inhibitor indicated for the management of adult and pediatric patients with leukemia, lymphoma, and solid tumor malignancies who are receiving cancer therapy which causes elevations of serum and urinary uric acid levels and who cannot tolerate oral therapy.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Recommended Dosage ( 2.2 ) Adult Patients 200 mg/m 2 /day to 400 mg/m 2 /day Maximum 600 mg/day Pediatric Patients Starting Dose 200 mg/m 2 /day Maximum 400 mg/day • Recommended Dosage in Adult Patients with Renal Impairment ( 2.2 , 5.2 , 8.6 ) Creatinine Clearance Recommended Daily Dose 10 to 20 mL/min 200 mg/day Less than 10 mL/min 100 mg/day On dialysis 50 mg every 12 hours, or 100 mg every 24 hours
2.1Recommended Dosage Initiate therapy with ALOPRIM 24 to 48 hours before the start of chemotherapy known to cause tumor cell lysis. Additionally, administer fluids sufficient to yield a daily urinary output of at least two liters in adults with a neutral or, preferably, slightly alkaline urine. The recommended daily dose of ALOPRIM is shown in Table 1.
Administer the daily dose as single infusion or in equally divided infusions at 6-, 8-, or 12-hour intervals at a rate appropriate for the volume of infusate. Table 1: Recommended Daily Dose of ALOPRIM Adult Patients 200 mg/m 2 /day to 400 mg/m 2 /day intravenously Maximum 600 mg/day Pediatric Patients Starting Dose 200 mg/m 2 /day intravenously Maximum 400 mg/day The dosage of ALOPRIM to lower serum uric acid to normal or near-normal varies with the severity of the disease. Monitor serum uric acid levels at least daily and administer ALOPRIM at a dose and frequency to maintain the serum uric acid within the normal range.
Discontinue ALOPRIM when the patient is able to take oral therapy or when the risk of tumor lysis has abated.
2.2Dosage Modifications in Patients with Renal Impairment Reduce the dose of ALOPRIM in patients with impaired renal function [see Use in Specific Populations (8.6) and Clinical Pharmacology (12.3) ] . The recommended dosage reductions of ALOPRIM in adult patients with renal impairment are shown in Table 2. Table 2: Recommended Daily Dose of ALOPRIM in Adult Patients with Renal Impairment Creatinine Clearance Recommended Daily Dose 10 to 20 mL/min 200 mg/day Less than 10 mL/min 100 mg/day On dialysis 50 mg every 12 hours, or 100 mg every 24 hours Treatment with ALOPRIM has not been studied in pediatric patients with severe renal impairment or on dialysis.
For pediatric patients with severe renal impairment or on dialysis, consider the risks and potential benefits before initiating treatment with ALOPRIM [see Warnings and Precautions (5.2) and Use In Specific Populations (8.6) ] .
2.3Preparation Instructions Reconstitue and further dilute ALOPRIM prior to intravenous infusion. Reconstitution • Reconstitute each vial of ALOPRIM with 25 mL of Sterile Water for Injection, USP to obtain a concentration of 20 mg/mL of allopurinol. • Inspect the reconstituted solution for discoloration and particulate matter. The reconstituted solution should appear as a clear, almost colorless solution with no more than a slight opalescence.
Do not use if the reconstituted solution contains particulate matter or discoloration is present. Dilution • Dilute with 0.9% Sodium Chloride Injection, USP or 5% Dextrose for Injection, USP to obtain a final concentration of less than 6 mg/mL. • Inspect the diluted solution for particulate matter or discoloration and discard if present. • If not used immediately, the diluted ALOPRIM solution can be stored at 20° to 25°C (68° to 77°F) for up to 10 hours after initial reconstitution. The storage includes time for infusion.
Do not refrigerate the reconstituted and/or diluted product. • If stored, the administration should be completed within 10 hours after reconstitution. • Discard unused portion.
2.4Administration Instructions Do not mix ALOPRIM with or administer it through the same intravenous port as agents which are incompatible in solution with ALOPRIM. The following table lists drugs that are known to be physically incompatible in solution with ALOPRIM. Table 3: Drugs That Are Physically Incompatible in Solution with ALOPRIM Amikacin sulfate Hydroxyzine HCl Amphotericin B Idarubicin HCl Carmustine Imi…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS For Injection: 500 mg of allopurinol as a sterile, white lyophilized powder or cake in a single-dose vial for reconstitution. For injection: 500 mg as a white lyophilized powder or cake in a single-dose vial for reconstitution ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS ALOPRIM is contraindicated in patients with a history of severe reaction to any formulation of allopurinol. Known hypersensitivity to allopurinol. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Skin Rash and Hypersensitivity: Discontinue ALOPRIM at the first appearance of skin rash or other signs which may indicate a hypersensitivity reaction. Allopurinol has been associated with serious and sometimes fatal dermatologic reactions. ( 5.1 ) • Renal Function Impairment: Patients with decreased renal function require lower doses of allopurinol.
( 5.2 ) • Hepatotoxicity: If signs and symptoms of hepatotoxicity develop, liver function evaluation should be performed. ( 5.3 ) • Myelosuppression: Bone marrow suppression has been reported with allopurinol. ( 5.4 ) • Drowsiness: Drowsiness has been reported in patients taking ALOPRIM.
( 5.5 )
5.1Skin Rash and Hypersensitivity Serious and sometimes fatal dermatologic reactions, including toxic epidermal necrolysis (TEN), Stevens-Johnson syndrome (SJS), and drug reaction with eosinophilia and systemic symptoms (DRESS) have been reported in patients taking allopurinol [see Adverse Reactions (6.1) ] . These reactions occur in approximately 5 in 10,000 (0.05%) patients taking allopurinol. Other serious hypersensitivity reactions that have been reported include exfoliative, urticarial and purpuric lesions; generalized vasculitis; and irreversible hepatotoxicity.
Discontinue ALOPRIM at the first appearance of skin rash or other signs which may indicate a hypersensitivity reaction. The HLA-B*58:01 allele is a genetic marker for severe skin reactions indicative of hypersensitivity to allopurinol. Patients who carry the HLA-B*58:01 allele are at a higher risk of allopurinol hypersensitivity syndrome (AHS), but hypersensitivity reactions have been reported in patients who do not carry this allele.
The frequency of this allele is higher in individuals of African, Asian (e.g., Han Chinese, Korean, Thai), and Native Hawaiian/Pacific Islander ancestry [see Clinical Pharmacology (12.5) ] . The use of ALOPRIM is not recommended in HLA-B*58:01 positive patients unless the benefits clearly outweigh the risks. Prior to starting ALOPRIM, consider testing for the HLA-B*58:01 allele in genetically at-risk populations.
Screening is generally not recommended in patients from populations in which the prevalence of HLA-B*58:01 is low, or in current allopurinol users, as the risk of SJS/TEN/DRESS is largely confined to the first few months of therapy, regardless of HLA-B*58:01 status. Hypersensitivity reactions to ALOPRIM may be increased in patients with decreased renal function receiving thiazide diuretics and ALOPRIM concurrently. In addition, concomitant use of the following drugs may increase the risk of skin rash, which may be severe: bendamustine, thiazide diuretics, ampicillin and amoxicillin [see Drug Interactions (7.1) ] .
Patients should stop ALOPRIM and seek medical attention if they develop a rash.
5.2Renal Function Impairment Treatment with ALOPRIM may result in renal impairment due to formation of xanthine calculi or due to precipitation of urates in patients receiving concomitant uricosuric agents. Patients with pre-existing renal disease, including renal impairment or history of kidney stones, may be at increased risk for worsening renal impairment due to xanthine calculi or precipitation of urates while receiving treatment with ALOPRIM. Monitor serum creatinine at least daily during the early stages of allopurinol administration.
Maintain fluid intake sufficient to yield a urinary output of at least 2 liters per day in adults. In patients with severely impaired renal function or increase in uric acid concentration associated with decreased urate clearance, reduce the dosage of ALOPRIM [see Use In Specific Populations (8.6) and Dosage and Administration (2.1 , 2.2) ] .
5.3Hepatotoxicity Cases of reversible clinical hepatotoxicity have been noted in patients taking oral allopurinol. In some patients, asymptomatic rises in serum alkaline phosphatase or serum transaminase have been observed. If anorexia, weight loss, or pruritus develop in patients on allopuri…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: • Skin Rash and Hypersensitivity [see Warnings and Precautions (5.1) ] • Renal Function Impairment [see Warnings and Precautions (5.2) ] • Hepatoxicity [see Warnings and Precautions (5.3) ] • Myelosuppression [see Warnings and Precautions (5.4) ] • Drowsiness [see Warnings and Precautions (5.5) ] Most common adverse reactions (incidence > 1%) are skin rash, nausea, vomiting, and renal failure/insufficiency.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Mylan at 1-877-446-3679 (1-877-4-INFO-RX) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety of ALOPRIM was evaluated in an uncontrolled compassionate use study of 1,378 patients with advanced malignancies requiring treatment with cytotoxic chemotherapy and in patients with other serious conditions. Adverse reactions were reported in 9% (125/1378) of the patients treated with ALOPRIM.
The most common adverse reaction was skin rash. Two patients experience serious adverse reactions (decreased renal function and generalized seizure) and one patient experienced severe diarrhea. Approximately 1.1% of patients experienced allergic adverse reactions (including rash, eosinophilia, local injection site reaction).
A listing of the adverse reactions reported from clinical trials follows: Incidence Greater Than 1%: Cutaneous/Dermatologic: rash (1.5%) Genitourinary: renal failure/insufficiency (1.2%) Gastrointestinal: nausea (1.3%), vomiting (1.2%) Incidence Less Than 1%: Body as a Whole: fever, pain, chills, alopecia, infection, sepsis, enlarged abdomen, mucositis/pharyngitis, blast crisis, cellulitis, hypervolemia Cardiovascular: heart failure, cardiorespiratory arrest, hypertension, pulmonary embolus, hypotension, decreased venous pressure, flushing, headache, stroke, septic shock, cardiovascular disorder, ECG abnormality, hemorrhage, bradycardia, thrombophlebitis, ventricular fibrillation Cutaneous/Dermatologic: urticaria, pruritus, local injection site reaction Gastrointestinal: diarrhea, gastrointestinal bleeding, hyperbilirubinemia, splenomegaly, hepatomegaly, intestinal obstruction, jaundice, flatulence, constipation, liver failure, proctitis Genitourinary: hematuria, increased creatinine, oliguria, kidney function abnormality, urinary tract infection Hematologic: leukopenia, marrow aplasia, thrombocytopenia, eosinophilia, neutropenia, anemia, pancytopenia, ecchymosis, bone marrow suppression, disseminated intravascular coagulation Metabolic: hypocalcemia, hyperphosphatemia, hypokalemia, hyperuricemia, electrolyte abnormality, hypercalcemia, hyperglycemia, hypernatremia, hyponatremia, metabolic acidosis, edema, glycosuria, hyperkalemia, lactic acidosis, water intoxication, hypomagnesemia Neurologic: seizure, status epilepticus, myoclonus, twitching, agitation, mental status changes, cerebral infarction, coma, dystonia, paralysis, tremor Pulmonary: respiratory failure/insufficiency, ARDS, increased respiration rate, apnea Musculoskeletal: arthralgia Other: hypotonia, diaphoresis, tumor lysis syndrome
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Clinically important interactions with the drugs listed below were observed in patients undergoing treatment with an oral allopurinol formulation. • Capecitabine: Avoid the concomitant use of allopurinol ( 7.2 ). • Pegloticase: Discontinue and do not institute allopurinol therapy during treatment with pegloticase ( 7.2 ). • Mercaptopurine or Azathioprine: Reduce mercaptopurine or azathioprine dose as recommended in the respective prescribing information ( 7.2 ). • See full prescribing information for complete list of significant drug interactions ( 7 ).
7.1Drugs Known to Affect the Occurrence of Skin Rash and Hypersensitivity Concomitant use of the following drugs may increase the risk of skin rash, which may be severe: bendamustine, thiazide diuretics, ampicillin and amoxicillin. Renal impairment may further increase risk with concomitant use of thiazide diuretics [see Warnings and Precautions (5.1) (5.2) and Clinical Pharmacology (12.2) ] . Monitor renal function and reduce the dose of ALOPRIM in patients with concomitant thiazide diuretic use and impaired renal function [see Dosage and Administration (2.2) ].
Discontinue ALOPRIM at the first appearance of skin rash or other signs which may indicate a hypersensitivity reaction when use concomitantly with these drugs.
7.2Other Drugs Known to Have Clinically Important Drug Interactions with ALOPRIM Table 4: Interventions for Clinically Important Drug Interactions with ALOPRIM Capecitabine Clinical Impact Concomitant use with allopurinol may decrease concentration of capecitabine’s active metabolites, which may decrease capecitabine efficacy. Intervention Avoid the use of ALOPRIM during treatment with capecitabine. Cyclosporine Clinical Impact Concomitant use of allopurinol increases cyclosporine concentrations which may increase the risk of adverse reactions.
Intervention Increase frequency of monitoring cyclosporine concentrations as reflected in the prescribing information when used concomitantly with ALOPRIM. Cytotoxic Agents Clinical Impact Concomitant use of allopurinol with cytotoxic agents increases bone marrow suppression among patients with neoplastic disease, except leukemia [see Warnings and Precautions (5.4) and Clinical Pharmacology (12.2) ] . Intervention Blood count monitoring and regular physician follow-up recommended.
Fluorouracil Clinical Impact Based on non-clinical data, allopurinol may decrease anti-tumor activity due to suppression of phosphorylation of 5-fluorouracil. Intervention Concomitant administration with fluorouracil should be avoided. Mercaptopurine or Azathioprine Clinical Impact Allopurinol inhibits xanthine oxidase mediated metabolism of mercaptopurine and azathioprine.
Concomitant use of allopurinol increases the exposure of either mercaptopurine or azathioprine which may increase the risk of their adverse reactions including myelosuppression [see Warnings and Precautions (5.4) ] . Intervention Reduce the dosage of mercaptopurine or azathioprine as recommended in the respective prescribing information. Pegloticase Clinical Impact Concomitant use of ALOPRIM and pegloticase may potentially blunt the rise of serum uric acid levels and increase the risk of pegloticase related anaphylaxis in patients whose uric acid level increase to above 6 mg/dL.
Intervention Discontinue and do not institute ALOPRIM therapy during treatment with pegloticase. Theophylline Clinical Impact Concomitant use of allopurinol doses greater than or equal to 600 mg/day may decrease the clearance of theophylline. Intervention Monitor and adjust theophylline doses as reflected in the prescribing information.
Uricosuric Agents Clinical Impact Uricosuric agents increase the excretion of the active allopurinol metabolite oxypurinol. Concomitant use with uricosuric agents decreases oxypurinol exposure which may reduce the inhibition of xanthine oxidase by oxypurinol and increases the urinary excretion of uric acid. Intervention Monitor uric acid levels du…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Pregnancy: May cause fetal harm ( 8.1 ). • Lactation: Advise not to breastfeed ( 8.2 ).
8.1Pregnancy Risk Summary Based on findings in animals, ALOPRIM may cause fetal harm when administered to a pregnant woman. Adverse developmental outcomes have been described in exposed animals (see Data ) . Allopurinol and its metabolite oxypurinol have been shown to cross the placenta following administration of maternal allopurinol.
Available limited published data on allopurinol use in pregnant women do not demonstrate a clear pattern or increase in frequency of adverse developmental outcomes. Among approximately 50 pregnancies described in published literature, 2 infants with major congenital malformations have been reported with following maternal allopurinol exposure. Advise pregnant women of the potential risk to a fetus.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data There was no evidence of fetotoxicity or teratogenicity in rats or rabbits treated during the period of organogenesis with oral allopurinol at doses up to 200 mg/kg/day and up to 100 mg/kg/day, respectively (about three times the human dose on a mg/m 2 basis). However, there is a published report in pregnant mice that single intraperitoneal doses of 50 or 100 mg/kg (about 1/3 or 3/4 the human dose on a mg/m 2 basis) of allopurinol on gestation days 10 or 13 produced significant increases in fetal deaths and teratogenic effects (cleft palate, harelip, and digital defects).
It is uncertain whether these findings represented a fetal effect or an effect secondary to maternal toxicity. In another published study with no reported maternal toxicity, allopurinol administered orally at 15 or 45 mg/kg to pregnant rats during organogenesis caused embryonic resorptions, growth retardation, decreased fetal weight, and skeletal, liver, kidney, and brain abnormalities. In rats, maternal treatment with allopurinol in normoxic pregnancy has been shown to increase the cardiac protein levels of sarcoplasmic/endoplasmic reticulum calcium ATPase 2 (SERCA2a) in the adult male offspring.
The mechanism underlying this effect is not understood. However, this effect was not matched by an increase in left ventricular end diastolic pressure or sympathetic dominance in hearts of adult male offspring of normoxic pregnancy treated with allopurinol.
8.2Lactation Risk Summary Allopurinol and oxypurinol are present in human milk. Based on information from a single case report, allopurinol and its active metabolite, oxypurinol, were detected in the milk of a mother at five weeks postpartum at an estimated relative infant dose of 0.14 and 0.2 mg/kg of allopurinol and between 7.2 to 8 mg/kg of oxypurinol daily. There was no report of effects of allopurinol on the breastfed infant or on milk production.
Because of the potential for serious adverse reactions in a breastfed child, advise women not to breastfeed during treatments with ALOPRIM and for one week after the last dose.
8.4Pediatric Use The safety and effectiveness of ALOPRIM have been established in approximately 200 pediatric patients. The efficacy and safety profile observed in this patient population were similar to that observed in adults.
8.5Geriatric Use Clinical studies of ALOPRIM did not include sufficient numbers of patients 65 years and older to determine whether they respond differently than younger patients.
8.6Renal Impairment Allopurinol and its primary active metabolite, oxypurinol, are eliminated by the kidneys [see Clinical Pharmacology (12.3) ] . Therefore, changes in renal function will likely increase allopurinal and oxypurinol exposure. In patients…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings in animals, ALOPRIM may cause fetal harm when administered to a pregnant woman. Adverse developmental outcomes have been described in exposed animals (see Data ) . Allopurinol and its metabolite oxypurinol have been shown to cross the placenta following administration of maternal allopurinol.
Available limited published data on allopurinol use in pregnant women do not demonstrate a clear pattern or increase in frequency of adverse developmental outcomes. Among approximately 50 pregnancies described in published literature, 2 infants with major congenital malformations have been reported with following maternal allopurinol exposure. Advise pregnant women of the potential risk to a fetus.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data There was no evidence of fetotoxicity or teratogenicity in rats or rabbits treated during the period of organogenesis with oral allopurinol at doses up to 200 mg/kg/day and up to 100 mg/kg/day, respectively (about three times the human dose on a mg/m 2 basis). However, there is a published report in pregnant mice that single intraperitoneal doses of 50 or 100 mg/kg (about 1/3 or 3/4 the human dose on a mg/m 2 basis) of allopurinol on gestation days 10 or 13 produced significant increases in fetal deaths and teratogenic effects (cleft palate, harelip, and digital defects).
It is uncertain whether these findings represented a fetal effect or an effect secondary to maternal toxicity. In another published study with no reported maternal toxicity, allopurinol administered orally at 15 or 45 mg/kg to pregnant rats during organogenesis caused embryonic resorptions, growth retardation, decreased fetal weight, and skeletal, liver, kidney, and brain abnormalities. In rats, maternal treatment with allopurinol in normoxic pregnancy has been shown to increase the cardiac protein levels of sarcoplasmic/endoplasmic reticulum calcium ATPase 2 (SERCA2a) in the adult male offspring.
The mechanism underlying this effect is not understood. However, this effect was not matched by an increase in left ventricular end diastolic pressure or sympathetic dominance in hearts of adult male offspring of normoxic pregnancy treated with allopurinol.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of ALOPRIM have been established in approximately 200 pediatric patients. The efficacy and safety profile observed in this patient population were similar to that observed in adults.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of ALOPRIM did not include sufficient numbers of patients 65 years and older to determine whether they respond differently than younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE In the management of overdosage, there is no specific antidote for ALOPRIM. Both allopurinol and oxypurinol are dialyzable; however, the usefulness of hemodialysis or peritoneal dialysis in the management of an overdose of ALOPRIM is unknown.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Allopurinol is a structural analogue of the natural purine base, hypoxanthine. Allopurinol and its oxypurinol metabolite inhibitor xanthine oxidase, the enzyme responsible for the conversion of hypoxanthine to xanthine and of xanthine to uric acid, the end product of purine metabolism in humans. Allopurinol does not disrupt the biosynthesis of purines.
The action of oral allopurinol differs from that of uricosuric agents, which lower the serum uric acid level by increasing urinary excretion of uric acid. Allopurinol reduces both the serum and urinary uric acid levels by inhibiting the formation of uric acid. The use of allopurinol to block the formation of urates avoids the hazard of increased renal excretion of uric acid posed by uricosuric drugs.
12.2Pharmacodynamics Allopurinol reduces the production of uric acid by inhibiting the biochemical reactions immediately preceding its formation in a dose dependent manner. The pharmacological action of allopurinol is generally believed to be mediated by its oxypurinol metabolite. Effect on Hypoxanthine and Xanthine Reutilization of both hypoxanthine and xanthine for nucleotide and nucleic acid synthesis is markedly enhanced when their oxidations are inhibited by allopurinol and oxypurinol.
This reutilization does not disrupt normal nucleic acid anabolism because feedback inhibition is an integral part of purine biosynthesis. As a result of xanthine oxidase inhibition, the serum concentration of hypoxanthine plus xanthine in patients receiving allopurinol for treatment of hyperuricemia is usually in the range of 0.3 to 0.4 mg/dL compared to a normal level of approximately 0.15 mg/dL. A maximum of 0.9 mg/dL of these oxypurines has been reported when the serum urate was lowered to less than 2 mg/dL by high doses of allopurinol.
These values are far below the saturation levels, at which point their precipitation would be expected to occur (above 7 mg/dL). The increased xanthine and hypoxanthine in the urine in patients who were treated with oral allopurinol have not been accompanied by problems of nephrolithiasis; however, there are isolated case reports of xanthine crystalluria. Drug Interaction Studies Fluorouracil Based on non-clinical data, allopurinol may decrease anti-tumor activity due to suppression of phosphorylation of 5-fluorouracil.
Pegloticase Concomitant use of ALOPRIM and pegloticase may potentially blunt the rise of serum uric acid levels required for monitoring the safe use of pegloticase. Cytotoxic Agents Enhanced bone marrow suppression by cyclophosphamide and other cytotoxic agents has been reported among patients with neoplastic disease, except leukemia, in the presence of allopurinol. Thiazide Diuretics Reports that the concomitant administration of allopurinol and thiazide diuretics contributed to increased allopurinol toxicity were reviewed; however, a causal mechanism or cause-and-effect relationship was not found.
12.3Pharmacokinetics Following single 100 mg and 300 mg intravenous and oral administration of ALOPRIM, the relative intravenous Cmax was approximately 3-fold and 3.8-fold and AUC 0-inf was approximately 1.9-fold higher for allopurinol at both dosages, respectively. The relative intravenous oxypurinol C max and AUC 0-inf was approximately 1 compaired to oral administration at both dosages. The C max and AUC 0- inf for both allopurinol and oxypurinol following intravenous administration of ALOPRIM were dose proportional in the dose range of 100 to 300 mg.
Distribution The steady-state allopurinol volume of distribution (mean ± S.D.) is approximately 0.87 ±
0.13L/Kg following intravenous adminstration. Elimination The half-life (mean ± S.D.) of allopurinol and oxypurinol are approximately 1.21 ± 0.33 and 23.5 ± 4.5 hours following intravenous administration, respectively. The net renal clearance of oxypurinol about 30 mL/min. Metabolism Allopurinol is a weak CYP1A2 inhibitor. Allopurinol is rapidly e…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Allopurinol is a structural analogue of the natural purine base, hypoxanthine. Allopurinol and its oxypurinol metabolite inhibitor xanthine oxidase, the enzyme responsible for the conversion of hypoxanthine to xanthine and of xanthine to uric acid, the end product of purine metabolism in humans. Allopurinol does not disrupt the biosynthesis of purines.
The action of oral allopurinol differs from that of uricosuric agents, which lower the serum uric acid level by increasing urinary excretion of uric acid. Allopurinol reduces both the serum and urinary uric acid levels by inhibiting the formation of uric acid. The use of allopurinol to block the formation of urates avoids the hazard of increased renal excretion of uric acid posed by uricosuric drugs.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING ALOPRIM (allopurinol) for Injection is supplied in 30 mL flint glass single-dose vials. Each vial contains 500 mg of allopurinol as a sterile, white, lyophilized powder or cake for reconstitution. NDC 67457-187-50 One vial per carton Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION ALOPRIM (allopurinol) for Injection, a xanthine oxidase inhibitor, is a sterile, white, lyophilized powder or cake, in a single-dose vial for reconstitution. Each vial contains 500 mg of allopurinol equivalent to 580.7 mg of allopurinol sodium and 148 mg of sodium hydroxide as a solubilizer. Sodium hydroxide is also used as a pH adjuster.
ALOPRIM (allopurinol) for Injection contains no preservatives. Allopurinol is a xanthine oxidase inhibitor. The chemical name for allopurinol sodium is 1,5-dihydro-4 H -pyrazolo[3,4- d ]pyrimidin-4-one monosodium salt.
It is a white amorphous mass with a molecular weight of 158.09 and molecular formula C 5 H 3 N 4 NaO. The structural formula is: The pKa of allopurinol sodium is 9.31. Allopurinol Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Skin Rash and Hypersensitivity Inform patients that ALOPRIM may increase the risk of serious and sometimes fatal dermatologic reactions, including toxic epidermal necrolysis (TEN), Stevens-Johnson syndrome (SJS), and drug reaction with eosinophilia and systemic symptoms (DRESS). Instruct the patient to be alert for skin rash, blisters, fever or other signs and symptoms of these hypersensitivity reactions. Advise patients to stop the ALOPRIM immediately if they develop any type of rash and seek medical attention [see Warnings and Precautions (5.1) ] .
Renal Function Impairment Advise patients to stay well hydrated (e.g., 2 liters of liquid per day) while taking ALOPRIM [see Warnings and Precautions (5.2) ] . Hepatotoxicity Advise patients of the risk of hepatoxicity and to report any signs and symptoms of liver failure, including jaundice, pruritus, bleeding, bruising, or anorexia to their healthcare provider [see Warnings and Precautions (5.3) ] . Myelosuppression Advise patients of the risk of myelosuppression and to report any signs and symptoms of infection, fever, bleeding, shortness of breath, or significant fatigue to their healthcare provider [see Warnings and Precautions (5.4) ] .
Drowsiness Inform patients that drowsiness has been reported in patients taking ALOPRIM and to be cautious when engaging in activities where alertness is mandatory [see Warnings and Precautions (5.5) ] . Pregnancy Advise pregnant women of the potential risk to a fetus. Advise women to notify their healthcare provider if they become pregnant or intend to become pregnant during treatment with Aloprim [see Use in Specific Populations (8.1) ].
Lactation Advise women not to breastfeed during treatment with ALOPRIM for one week after the last dose . [see Use in Specific Populations (8.2) ]. Manufactured for: Mylan Institutional LLC Morgantown, WV 26505 U.S.A. Manufactured by: NerPharMa Srl V.le Pasteur 10 20014 Nerviano (MI), Italy MI:ALOPIJ:R9 P2119476 ALOPRIM is a registered trademark of Mylan Teoranta, a Viatris Company.