
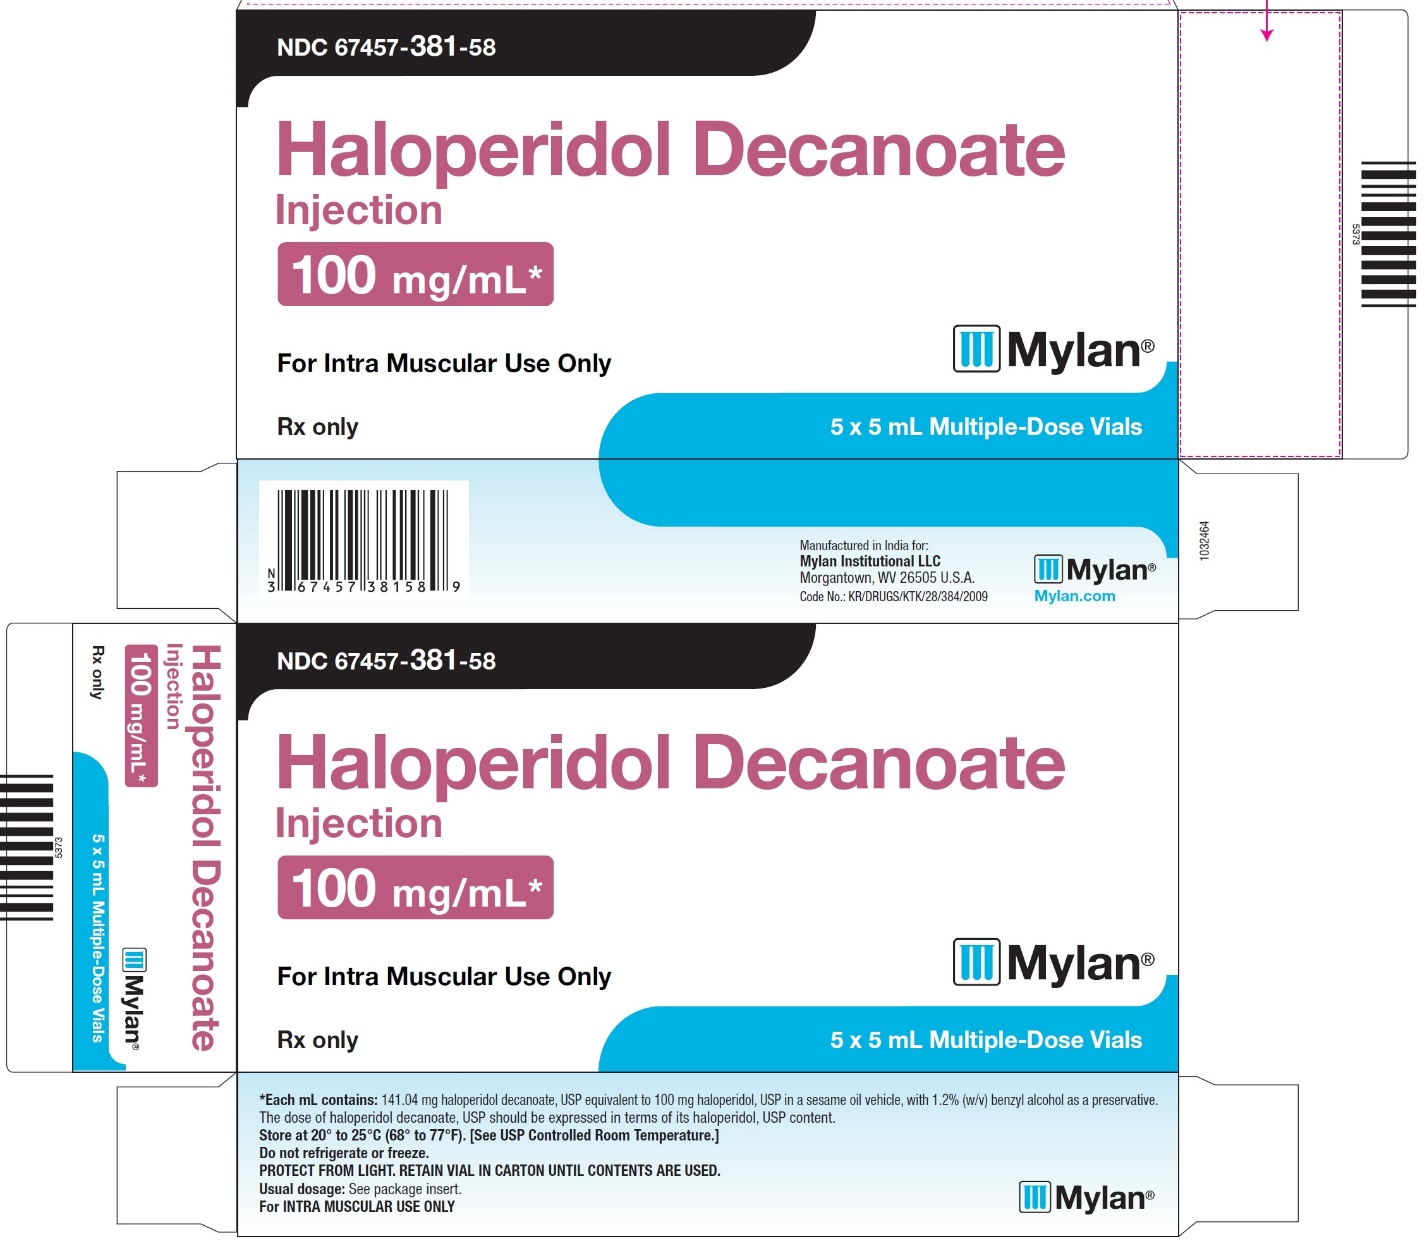
Haloperidol Decanoate 100 mg/mL Injection, 5 vials
Other active recalls for Haloperidol Decanoate (different manufacturers) — 6 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Typical Antipsychotic class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Haloperidol injection and haloperidol extended-release injection are used to treat schizophrenia (a mental illness that causes disturbed or unusual thinking, loss of interest in life, and strong or inappropriate emotions). . Haloperidol is in a class of medications called conventional antipsychotics. It works by changing the activity of certain natural substances in the brain.
Read the full MedlinePlus article ↗- Haloperidol is mainly used to manage symptoms of psychotic disorders — things like hallucinations and severely disorganized thinking. It's also used to control the tics and vocal s...
- The most common things people notice early on are muscle stiffness, tremors, or a restless, can't-sit-still feeling. Some people also feel drowsy or notice their blood pressure dip...
- What side effects should I watch out for when I first start taking it?
- Yes — a few things need prompt attention. If you develop sudden muscle spasms in your neck or jaw, throat tightening, or trouble swallowing or breathing, get help right away. Also...
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII LKG8494WBH
Benzyl alcohol is a clear liquid used as a preservative and solvent in medicines. It helps prevent bacterial and fungal growth and dissolves other ingredients to create uniform liquid formulations.
-
UNII QX10HYY4QV
Sesame oil is a plant-derived oil from sesame seeds. It's used in medicines as a solvent or carrier to dissolve or suspend active ingredients, helping them mix evenly throughout the formulation.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $14.324 | $71.62 / 5 ml |
| Medicaid paysCMS SDUD · 12 mo | $18.83 | $94.13 / 5 ml |
| Medicare drug plans payPart D · Q2 2026 | $23.10 | $115.48 / 5 ml |
| Medicare Part B allowsASP · J1631 | $5.291 / J1631 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| haloperidol decanoate 100 mg/mL 25021-0833-01 | Sagent | 10 vials | $7.439 | AO | Availability likely | save 48% |
| Haloperidol Decanoate 100 mg/mL 65145-0167-10 | Caplin | 10 vials | $7.439 | AO | Availability likely | save 48% |
| Haloperidol Decanoate 100 mg/mL 71288-0503-02 | Meitheal | 10 vials | $7.439 | AO | Availability likely | save 48% |
| Haloperidol Decanoate 100 mg/mL 72485-0521-10 | Armas | 10 vials | $7.439 | AO | Availability likely | save 48% |
| Haloperidol Decanoate 100 mg/mLthis 67457-0409-13 | Mylan | 5 vials | $14.324 | AO | Availability likely | — |
| Haloperidol Decanoate 100 mg/mL 70069-0867-05 | Somerset | 10 vials | $14.324 | AO | Availability likely | — |
| Haloperidol Decanoate 100 mg/mL 70069-0384-01 | Somerset | 1 vial | $14.324 | AO | Availability likely | — |
| Haloperidol Decanoate 100 mg/mL 00143-9296-01 | Hikma | 1 vial | $14.324 | AO | Availability likely | — |
| Haloperidol Decanoate 100 mg/mL 65145-0169-01 | Caplin | 1 vial | $14.324 | AO | Availability likely | — |
| Haloperidol decanoate 100 mg/mL 70710-1464-01 | Zydus | 1 vial | $14.324 | AO | Availability likely | — |
| Haloperidol Decanoate 100 mg/mL 71288-0504-05 | Meitheal | 1 vial | $14.324 | AO | Availability likely | — |
| Haloperidol Decanoate 100 mg/mL 70069-0868-01 | Somerset | 1 vial | $14.324 | AO | Availability likely | — |
| Haloperidol Decanoate 100 mg/mL 00143-9295-01 | Hikma | 1 vial | $16.016 | AO | Availability likely | +12% |
| Haloperidol Decanoate 100 mg/mL 63323-0471-01 | Fresenius | 1 vial | $16.016 | AO | Availability likely | +12% |
| Haloperidol Decanoate 100 mg/mL 68001-0581-41 | BluePoint | 1 vial | $16.016 | AO | Availability likely | +12% |
| Haloperidol decanoate 100 mg/mL 68001-0658-41 | BluePoint | 1 vial | $16.016 | AO | Availability likely | +12% |
| Haloperidol Decanoate 100 mg/mL 70069-0383-01 | Somerset | 1 vial | $16.016 | AO | Availability likely | +12% |
| Haloperidol decanoate 100 mg/mL 70710-1463-01 | Zydus | 1 vial | $16.016 | AO | Availability likely | +12% |
| Haloperidol Decanoate 100 mg/mL 72603-0230-01 | NorthStar | 1 vial | $16.016 | AO | Availability likely | +12% |
| Haloperidol Decanoate 100 mg/mL 10147-0922-05 | Patriot | 5 ampules | $29.346 | — | FDA listed | +105% |
| Haloperidol Decanoate 100 mg/mL 68001-0579-48 | BluePoint | 5 ampules | $29.346 | AO | FDA listed | +105% |
| Haloperidol Decanoate 100 mg/mL 70069-0031-05 | Somerset | 5 ampules | $32.927 | AO | Availability likely | +130% |
| Haldol Decanoate 100 mg/mL 50458-0254-14 | Janssen | 5 ampules | — | — | FDA listed | — |
| Haloperidol Decanoate 100 mg/mL 68083-0138-02 | Gland | 1 vial | — | AO | FDA listed | — |
| Haloperidol Decanoate 100 mg/mL 70518-4240-00 | REMEDYREPACK | 10 vials | — | AO | FDA listed | — |
| Haloperidol Decanoate 100 mg/mL 70518-4584-00 | REMEDYREPACK | 10 vials | — | AO | FDA listed | — |
| Haloperidol Decanoate 100 mg/mL 70756-0616-05 | Lifestar | 5 vials | — | AO | FDA listed | — |
| Haloperidol decanoate 100 mg/mL 70771-1853-01 | Zydus | 1 vial | — | AO | FDA listed | — |
| Haloperidol decanoate 100 mg/mL 70771-1854-01 | Zydus | 1 vial | — | AO | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 67457-0409-13 You're viewing this | 5 VIAL in 1 CARTON (67457-409-13) / 1 mL in 1 VIAL (67457-409-00) | 2014-03-01 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: INCREASED MORTALITY IN ELDERLY PATIENTS WITH DEMENTIA-RELATED PSYCHOSIS Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. Haloperidol decanoate injection is not approved for the treatment of patients with dementia-related psychosis [see Warnings and Precautions (5.1) ] . WARNING: INCREASED MORTALITY IN ELDERLY PATIENTS WITH DEMENTIA-RELATED PSYCHOSIS See full prescribing information for complete boxed warning.
Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. Haloperidol decanoate injection is not approved for the treatment of patients with dementia-related psychosis ( 5.1 ).
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Haloperidol decanoate injection is indicated for the treatment of schizophrenia in adults who were previously taking a stable dosage of an immediate-release oral haloperidol product. Haloperidol decanoate injection is a typical antipsychotic indicated for the treatment of schizophrenia in adults who were previously taking a stable dosage of an immediate-release oral haloperidol product ( 1 ).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Administer haloperidol decanoate injection by deep intramuscular injection every 4 weeks by a healthcare provider. Do not administer intravenously ( 2.1 ). • For the recommended dosage, including the first recommended dose and the maintenance dosage, see the Dosage and Administration section ( 2.1 ). • If schizophrenia symptoms worsen during dosage modification of haloperidol decanoate injection, consider administering an immediate-release oral haloperidol product in addition to haloperidol decanoate injection therapy ( 2.2 ).
2.1Recommended Dosage and Administration Administer haloperidol decanoate injection by deep intramuscular injection every 4 weeks by a health care professional. Do not administer haloperidol decanoate injection intravenously. When injecting haloperidol decanoate injection, use a 21-gauge needle.
The maximum volume per injection site is 3 mL. Table 1 below describes the recommended dosage for haloperidol decanoate injection. The maximum recommended initial dose is 100 mg.
If the calculated first recommended dose of haloperidol decanoate injection is greater than 100 mg, then administer two deep intramuscular injections as follows: • 100 mg on the first day • Remainder of the amount 3 to 7 days later. Table 1: Haloperidol Decanoate Injection Recommended Dosage Population First Recommended Dose Maintenance Dosage Clinical experience with haloperidol decanoate injection at a dosage greater than 450 mg every 4 weeks has been limited. Adult patients less than 65 years old stabilized on ≤ 10 mg of daily immediate-release oral haloperidol with normal hepatic function.
10-15 times previous daily dose of immediate-release oral haloperidol. 10-15 times previous daily dose of immediate-release oral haloperidol administered every 4 weeks. Adult patients less than 65 years old stabilized on ≤ 10 mg of daily immediate-release oral haloperidol with hepatic impairment OR Adult patients 65 years and older 10-15 times previous daily dose of immediate-release oral haloperidol.
Consider starting at the low end of the dosing range [see Use in Specific Populations (8.5 , 8.6) and Clinical Pharmacology (12.3) ] . The dosage may be increased by increments of 50 mg or less every 4 weeks until an optimal therapeutic effect is obtained. The typical effective dosage range is between 50 and 200 mg every 4 weeks.
Adult patients less than 65 years old stabilized on > 10 mg of daily immediate-release oral haloperidol 10-20 times previous daily dose of immediate-release oral haloperidol 10-15 times previous daily dose of immediate-release oral haloperidol administered every 4 weeks. The dosage may be increased by increments of 50 mg or less every 4 weeks until an optimal therapeutic effect is obtained.
2.2Recommended Supplemental Immediate-Release Oral Haloperidol Therapy If schizophrenia symptoms worsen during dosage modification of haloperidol decanoate injection, consider administering an immediate-release oral haloperidol product in addition to haloperidol decanoate injection therapy.
2.3Preparation Instructions Visually inspect haloperidol decanoate injection for particulate matter and discoloration prior to administration. Do not use if the solution has debris or is not clear or not colorless to pink or amber in color. Discard unused portion.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: • Haloperidol 50 mg/mL (present as haloperidol decanoate, USP) is a clear, slightly viscous, colorless to pink or amber solution, free from visible foreign material, in a single-dose vial • Haloperidol 100 mg/mL (present as haloperidol decanoate, USP) is a clear, slightly viscous, colorless to pink or amber solution, free from visible foreign material, in a single-dose vial Injection: • Haloperidol 50 mg/mL (present as haloperidol decanoate) in single-dose vials ( 3 ). • Haloperidol 100 mg/mL (present as haloperidol decanoate) in single-dose vials ( 3 ).
⛔ Contraindications ▾
4 CONTRAINDICATIONS Haloperidol decanoate injection is contraindicated in patients with: • Severe toxic central nervous system depression or comatose states from any cause. • Known hypersensitivity to haloperidol or any components of haloperidol decanoate injection. Hypersensitivity reactions, including anaphylactic reactions and angioedema, have been reported in patients treated with haloperidol [see Warnings and Precautions (5.9) and Adverse Reactions (6.2) ] . • Parkinson’s disease [see Warnings and Precautions (5.7) ] . • Dementia with Lewy bodies [see Warnings and Precautions (5.7) ] . • Severe toxic central nervous system depression or comatose states from any cause ( 4 ). • Known hypersensitivity to haloperidol or any components of haloperidol decanoate injection ( 4 ). • Parkinson’s disease ( 4 , 5.7 , 6.1 ). • Dementia with Lewy bodies ( 4 , 5.7 ).
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Sudden Death, Torsades de Pointes (TdP), and QTc Interval Prolongation: Avoid use of haloperidol decanoate injection in patients who are at risk of developing TdP. Avoid concomitant use of haloperidol decanoate injection with drugs that may increase risk of QTc interval prolongation or increase haloperidol exposure. Obtain ECG and serum electrolytes at baseline and during treatment as clinically indicated ( 5.2 ). • Tachycardia and Hypotension: Monitor orthostatic vital signs ( 5.3 ). • Cerebrovascular Adverse Reactions Including Stroke in Elderly Patients with Dementia-Related Psychosis: Use with caution in patients with schizophrenia who have risk factors for cerebrovascular adverse reactions ( 5.4 ). • Tardive Dyskinesia: Discontinue treatment if clinically appropriate ( 5.5 ). • Neuroleptic Malignant Syndrome (NMS): Immediately discontinue and monitor closely ( 5.6 ). • Seizures: Haloperidol decanoate injection is generally not recommended in patients receiving antiseizure drugs or who have a history of seizures or EEG abnormalities.
If clinically, indicated, maintain patients taking haloperidol decanoate injection on adequate antiseizure therapy ( 5.8 ). • Potential for Cognitive and Motor Impairment: Advise patients to not drive a motor vehicle or operate hazardous machinery until they are reasonably certain haloperidol decanoate injection does not impair their cognitive and motor functions ( 5.11 ). • Risk of Encephalopathic Syndrome with Concomitant Use of Lithium: Monitor closely for early signs of neurological toxicity and discontinue haloperidol decanoate injection if such signs appear ( 5.12 ). • Leukopenia, Neutropenia, and Agranulocytosis: Perform complete blood counts (CBC) in patients with pre-existing low white blood cell count (WBC) or history of leukopenia or neutropenia.
Consider discontinuing haloperidol decanoate injection if clinically significant decline in WBC occurs in absence of other causative factors. Discontinue haloperidol decanoate injection in patients with clinically significant neutropenia or an absolute neutrophile count of < 1,000/mm 3 ( 5.13 ). • Hyperprolactinemia: Elevated prolactin levels may occur during acute and chronic use ( 5.14 ).
5.1Increased Mortality in Elderly Patients with Dementia-Related Psychosis Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. In an analysis of 17 placebo-controlled trials (modal duration of 10 weeks), largely in patients taking atypical antipsychotic drugs, the risk of death in antipsychotic drug-treated patients was 1.6 to 1.7 times the risk of death in placebo- treated patients. Over the course of a typical 10-week controlled trial, the incidence of death in antipsychotic drug-treated patients was about 4.5%, compared to an incidence of about 2.6% in placebo-treated patients.
Although the causes of death were varied, most of the deaths appeared to be either cardiovascular (e.g., heart failure, sudden death) or infectious (e.g., pneumonia) in nature. Haloperidol decanoate injection is not approved for the treatment of patients with dementia- related psychosis [see Indications and Usage (1) ] .
5.2Sudden Death, Torsades de Pointes, and QTc Interval Prolongation Cases of sudden death, torsades de pointes (TdP) and QTc interval prolongation have been reported in haloperidol-treated patients [see Adverse Reactions (6.1 , 6.2) ] . Cases have been reported even in the absence of predisposing factors. Higher than recommended haloperidol dosages were associated with a higher risk of TdP and QTc interval prolongation.
Avoid use of haloperidol decanoate injection in patients who are at significant risk of developing TdP including those with congenital long QT syndrome, uncontrolled or significant cardiac disease, recent myocardial infarction, ischemic cardiomyopathy, unstable angina, bradyarrhythmias, uncontrolled hypertension, high degree atrioventricular block, se…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in more detail in other sections of the labeling: • Sudden Death, Torsades de Pointes, and QTc Interval Prolongation [see Warnings and Precautions (5.2) ] • Tachycardia and Hypotension [see Warnings and Precautions (5.3) ] • Tardive Dyskinesia [see Warnings and Precautions (5.5) ] • Neuroleptic Malignant Syndrome [see Warnings and Precautions (5.6) ] • Seizures [see Warnings and Precautions (5.8) ] • Hypersensitivity Reactions [see Warnings and Precautions (5.9) ] • Leukopenia, Neutropenia, and Agranulocytosis [see Warnings and Precautions (5.13) ] • Hyperprolactinemia [see Warnings and Precautions (5.14) ] • Risk of Severe Neurotoxicity in Patients with Thyrotoxicosis [see Warnings and Precautions (5.15) ] The most common adverse reactions (incidence ≥ 5%) were oculogyric crisis and parkinsonism ( 6.1 ).
To report SUSPECTED ADVERSE REACTIONS, contact Viatris at 1-877-446-3679 (1-877-4-INFO-RX) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse Reactions Identified in Clinical Trials with Haloperidol Decanoate Injection The data described below reflect exposure to 15 mg to 500 mg (1.7 times the maximum recommended dosage) of haloperidol decanoate injection monthly in 13 clinical trials of 410 adult patients with schizophrenia or an unapproved condition.
These clinical trials comprised of: • 1 double-blind, active comparator-controlled trial with fluphenazine decanoate (Trial 1). • 2 trials comparing haloperidol decanoate injection to oral haloperidol (Trials 2 and 3). • 9 open-label trials. • 1 dose-response trial. The most common adverse reactions that occurred in ≥ 5% of haloperidol decanoate injection-treated patients in Trial 1 were Parkinsonism and oculogyric crisis. Adverse reactions that occurred in ≥ 1% of haloperidol decanoate injection-treated patients in Trial 1 are shown in Table 2.
Trial 1 was not designed to evaluate meaningful comparisons of the incidence of adverse reactions in the haloperidol decanoate injection and fluphenazine decanoate treatment groups. Table 2: Adverse Reactions that Occurred in ≥ 1% of Haloperidol Decanoate Injection-treated Patients and Fluphenazine Decanoate-treated Patients in Trial 1 The study was not designed to evaluate meaningful comparisons of the incidence of adverse reactions in the haloperidol decanoate injection and the fluphenazine decanoate treatment groups.
Haloperidol Decanoate Injection (n = 36) Fluphenazine Decanoate (n = 36) Extrapyramidal disorder: Parkinsonism 31% 44% Oculogyric crisis 6% 0% Akinesia 3% 22% Akathisia 3% 14% Tremor 3% 0% Abdominal pain 3% 0% Headache 3% 0% Less common adverse reactions (< 1%) that occurred in Trial 1 and other adverse reactions that occurred in Trials 2 and 3, and open-label and dose-response clinical trials of haloperidol decanoate injection are listed below. • Cardiac Disorders: Tachycardia • Endocrine Disorders: Hyperprolactinemia • Eye Disorders: Vision blurred • Gastrointestinal Disorders: Constipation, Dry mouth, Salivary hypersecretion • General Disorders and Administration Site Conditions: Weight increased, Injection site reaction • Musculoskeletal and Connective Tissue Disorders: Muscle rigidity • Nervous System Disorders: Dyskinesia, Dystonia, Cogwheel rigidity, Hypertonia, Masked facies, Sedation, Somnolence • Reproductive System Disorders: Erectile dysfunction Adverse Reactions Identified in Clinical Trials with Immediate-Release Haloperidol Products Based on clinical trials with immediate-release haloperidol products that included 1,579 patients, the following adverse reactions were reported: • Musculoskeletal and Connective Tissue Disorders: Torticollis, Trismu…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Drugs that Prolong QTc Interval: Avoid concomitant use with haloperidol decanoate injection ( 7.1 ). • See full prescribing information for additional clinically significant drug interactions with haloperidol decanoate injection ( 7.2 ).
7.1Drugs that Prolong the QTc Interval Avoid concomitant use of haloperidol decanoate injection with other drugs with a known potential to prolong the QTc interval. If concomitant use cannot be avoided [see Warnings and Precautions (5.2) ] : • Obtain ECGs when initiating and during concomitant use as clinically indicated. • Obtain serum electrolytes (including potassium, calcium, phosphorus, and magnesium) when initiating and during concomitant use as clinically indicated. QTc interval prolongation has been observed with haloperidol decanoate injection treatment.
Concomitant use of haloperidol decanoate injection with other products that prolong the QTc interval may result in a greater increase in the QTc interval, and adverse reactions associated with QTc interval prolongation, including torsade de pointes, other serious arrythmias, and sudden death [see Warnings and Precautions (5.2) ] .
7.2Other Clinically Significant Drug Interactions Table 3 describes other clinically significant drug interactions of haloperidol decanoate injection. Table 3: Other Clinically Significant Drugs Interactions See www.fda.gov/CYPandTransporterInteractingDrugs for examples of CYP3A4 and/or CYP2D6 inhibitors, CYP3A4 inducers, and CYP2D6 substrates. CNS Depressants Clinical Impact Haloperidol may potentiate CNS depressants.
Prevention or Management Avoid concomitant use of haloperidol decanoate injection with CNS depressants such as anesthetics, opioids, and alcohol. CYP3A4 and/or CYP2D6 Inhibitors Clinical Impact CYP3A4 and/or CYP2D6 inhibitors increase haloperidol exposure (haloperidol is a CYP3A4 and CYP2D6 substrate) [see Clinical Pharmacology (12.3) ] . Concomitant use of haloperidol decanoate injection and CYP3A4 and/or CYP2D6 inhibitors may increase the risk of haloperidol-associated adverse reactions.
Prevention or Management Monitor for signs or symptoms of increased or prolonged pharmacologic effects of haloperidol. Decrease the dosage of haloperidol decanoate injection as clinically necessary. CYP3A4 Inducers Clinical Impact CYP3A4 inducers decrease haloperidol exposure (haloperidol is a CYP3A4 substrate) [see Clinical Pharmacology (12.3) ] .
Concomitant use of haloperidol decanoate injection with CYP3A4 inducers may reduce the effectiveness of haloperidol decanoate injection. Prevention or Management Monitor patients and if necessary, increase the dosage of haloperidol decanoate injection. CYP2D6 Substrates Clinical Impact Haloperidol is a CYP2D6 inhibitor.
Plasma concentrations of CYP2D6 substrates may increase when they are concomitantly administered with haloperidol decanoate injection. Prevention or Management Monitor plasma concentrations of the CYP2D6 substrate, if possible. Consider reducing the dosage of the CYP2D6 substrate, if necessary.
Refer to the Prescribing Information of the CYP2D6 substrate. Dopaminergic Drugs Clinical Impact Haloperidol may antagonize the effects of levodopa, dopamine agonists, and other drugs intended to increase dopamine levels. Prevention or Management Haloperidol decanoate injection is contraindicated in patients with Parkinson’s disease and dementia with Lewy bodies.
For conditions other than Parkinson’s disease and dementia with Lewy bodies, when possible, avoid concomitant use of haloperidol decanoate injection with dopaminergic drugs [see Warnings and Precautions (5.7) ] . Anticholinergic Drugs Clinical Impact The healthcare provider should keep in mind the possible increase in intraocular pressure when anticholinergic drugs are administered concomitantly with haloperidol decanoate injection. Prevention or Management Monitor and manage patients as clinically appropriate.
Lithium Clinical Impact Concomitant use of haloperidol decanoate…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Pregnancy: Neonates exposed to haloperidol decanoate injection during the third trimester of pregnancy may develop extrapyramidal and/or withdrawal symptoms (agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress, and decreased feeding) ( 8.1 ). • Lactation: Monitor breastfed infants for excessive sedation, irritability, poor feeding, abnormal muscle movements, and tremors ( 8.2 ).
8.1Pregnancy Risk Summary Available data from published epidemiologic studies of pregnant patients exposed to haloperidol have not established a drug-associated risk of major birth defects or miscarriage. Case reports of limb malformations in neonates have been reported in haloperidol-treated mothers; however, causal relationships were not established in these cases. There are risks to the pregnant patient from untreated schizophrenia, including increased risk of relapse, hospitalization, and suicide (see Clinical Considerations ) .
Haloperidol decanoate injection should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Neonates exposed to antipsychotic drugs during the third trimester of pregnancy are at risk for extrapyramidal and/or withdrawal symptoms (agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress, and decreased feeding) following delivery (see Clinical Considerations ) . The estimated background risk of major birth defects and miscarriage in patients with schizophrenia is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Clinical Considerations Disease-associated Maternal and/or Embryo/Fetal Risk There is risk to the pregnant patient from untreated schizophrenia, including increased risk of schizophrenia relapse, hospitalization, and suicide.
Schizophrenia is associated with increased adverse perinatal outcomes, including preterm birth. It is not known if this is a direct result of the illness or other comorbid factors. Fetal/Neonatal Adverse Reactions Extrapyramidal and/or withdrawal symptoms, including agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress and decreased feeding have been reported in neonates who were exposed to antipsychotic drugs during the third trimester of pregnancy.
Transient neonatal dyskinesia has also been reported. Some neonates recovered within hours or days without specific treatment; others required prolonged hospitalization. Monitor neonates for extrapyramidal, withdrawal, and dyskinesia symptoms and manage symptoms appropriately.
Data Animal Data Rats or rabbits administered oral haloperidol at doses of 0.5 to 7.5 mg/kg (approximately 0.2 to 7 times the maximum recommended human oral dose (MRHD) of 20 mg/day based on mg/m 2 body surface area) showed an increase in incidence of resorption, reduced fertility, delayed delivery, and pup mortality. No fetal abnormalities were observed at these doses in rats or rabbits. Cleft palate has been observed in mice administered oral haloperidol at a dose of 0.5 mg/kg, which is approximately 0.1 times the oral MRHD based on mg/m 2 body surface area.
8.2Lactation Risk Summary Literature reports suggest that haloperidol is detected in human milk of haloperidol-treated mothers with a relative infant dose ranging from 2% to 12%. Haloperidol has also been detected in the plasma and urine of breastfed infants. There has been a report of lethargy, poor feeding, and slowing of motor movements in an infant exposed to haloperidol through human milk.
Haloperidol may increase prolactin levels in some patients which can lead to galactorrhea. Monitor infants exposed to haloperidol decanoate via human milk for excessive sedation, irritability, poor feeding, and extrapyramidal symptoms (tremors and abnormal muscle movements). T…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from published epidemiologic studies of pregnant patients exposed to haloperidol have not established a drug-associated risk of major birth defects or miscarriage. Case reports of limb malformations in neonates have been reported in haloperidol-treated mothers; however, causal relationships were not established in these cases. There are risks to the pregnant patient from untreated schizophrenia, including increased risk of relapse, hospitalization, and suicide (see Clinical Considerations ) .
Haloperidol decanoate injection should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Neonates exposed to antipsychotic drugs during the third trimester of pregnancy are at risk for extrapyramidal and/or withdrawal symptoms (agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress, and decreased feeding) following delivery (see Clinical Considerations ) . The estimated background risk of major birth defects and miscarriage in patients with schizophrenia is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Clinical Considerations Disease-associated Maternal and/or Embryo/Fetal Risk There is risk to the pregnant patient from untreated schizophrenia, including increased risk of schizophrenia relapse, hospitalization, and suicide.
Schizophrenia is associated with increased adverse perinatal outcomes, including preterm birth. It is not known if this is a direct result of the illness or other comorbid factors. Fetal/Neonatal Adverse Reactions Extrapyramidal and/or withdrawal symptoms, including agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress and decreased feeding have been reported in neonates who were exposed to antipsychotic drugs during the third trimester of pregnancy.
Transient neonatal dyskinesia has also been reported. Some neonates recovered within hours or days without specific treatment; others required prolonged hospitalization. Monitor neonates for extrapyramidal, withdrawal, and dyskinesia symptoms and manage symptoms appropriately.
Data Animal Data Rats or rabbits administered oral haloperidol at doses of 0.5 to 7.5 mg/kg (approximately 0.2 to 7 times the maximum recommended human oral dose (MRHD) of 20 mg/day based on mg/m 2 body surface area) showed an increase in incidence of resorption, reduced fertility, delayed delivery, and pup mortality. No fetal abnormalities were observed at these doses in rats or rabbits. Cleft palate has been observed in mice administered oral haloperidol at a dose of 0.5 mg/kg, which is approximately 0.1 times the oral MRHD based on mg/m 2 body surface area.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of haloperidol decanoate injection have not been established in pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of haloperidol decanoate injection did not include sufficient numbers of patients 65 years of age and older to determine whether they respond differently from younger adult patients. The exposure of haloperidol may be higher in geriatric patients compared to young adult patients. Results from small clinical studies suggest a lower clearance and a longer elimination half-life of haloperidol in geriatric patients [see Clinical Pharmacology (12.3) ] .
Consider starting at the low end of the recommended dosing range for the first haloperidol decanoate injection dose in geriatric patients [see Dosage and Administration (2.1) ] . Antipsychotic drugs increase the risk of death in elderly patients with dementia-related psychosis. Haloperidol decanoate injection is not approved for the treatment of patients with dementia-related psychosis [see Warnings and Precautions (5.1) ] .
Elderly patients with dementia-related psychosis treated with antipsychotics had an increased risk of cerebrovascular adverse reactions (e.g., stroke, transient ischemic attack) including fatalities, compared to those treated with placebo [see Warnings and Precautions (5.4) ] . Antipsychotic drugs increase the risk of tardive dyskinesia and this risk appears to be highest among the elderly, particularly elderly women [see Warnings and Precautions (5.5) ] .
🆘 Overdosage ▾
10 OVERDOSAGE Reported overdose signs and symptoms are those resulting from an exaggeration of the drug’s known pharmacologic effects (e.g., drowsiness and sedation, tachycardia and hypotension) and adverse reactions, the most prominent of which would be: 1) severe extrapyramidal symptoms, 2) hypotension, or 3) sedation. Patients may appear comatose with respiratory depression and hypotension which could be severe enough to produce a shock-like state. Extrapyramidal reactions may be manifested by muscular weakness or rigidity and a generalized or localized tremor, as demonstrated by the akinetic or agitans types, respectively.
The risk of QTc interval prolongation and torsade de pointes should be considered [see Adverse Reactions (6.2) ] . Management of Overdose There is no specific antidote for a haloperidol overdose. • Should hypotension occur and a vasopressor be required, epinephrine must not be used since haloperidol decanoate injection may block its vasopressor activity, and paradoxical further lowering of the blood pressure may occur. Instead, metaraminol, phenylephrine or norepinephrine should be used. • In case of severe extrapyramidal reactions, antiparkinson drugs should be administered, and should be continued for several weeks, and then withdrawn gradually as extrapyramidal symptoms may emerge if discontinued abruptly. • Monitor ECG and vital signs for signs of QTc interval prolongation or dysrhythmias and continue monitoring until the dysrhythmias resolve and the haloperidol-induced QTc interval prolongation resolves. • Dialysis is not recommended in the treatment of overdose because it removes only very small amounts of haloperidol.
Consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdose management recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism of action of haloperidol decanoate injection for the treatment of schizophrenia in adults is unclear. However, its effect in schizophrenia could be mediated through its activity as an antagonist at central dopamine type 2 receptors. Haloperidol also binds to alpha-1 adrenergic receptors, but with lower affinity, and displays minimal binding to muscarinic cholinergic and histaminergic (H1) receptors.
12.2Pharmacodynamics The exposure-response relationship and time course of pharmacodynamic response for the safety and effectiveness of haloperidol have not been fully characterized.
12.3Pharmacokinetics Absorption The plasma concentrations of haloperidol gradually rise, reaching a peak at about 6 days after the haloperidol decanoate injection, and fall thereafter, with an apparent half-life of about 3 weeks. Steady state plasma concentrations of haloperidol are achieved within 2 to 4 months in patients receiving monthly haloperidol decanoate injections. The relationship between the haloperidol decanoate injection dosage and plasma haloperidol concentration is roughly linear for dosages below 450 mg (1.5 times the maximum recommended dosage [see Dosage and Administration (2.1) ] ; however, the pharmacokinetics of haloperidol following intramuscular injections can be quite variable between patients.
Elimination Metabolism Haloperidol is metabolized by several routes. The major pathways are glucuronidation and ketone reduction. The cytochrome P450 enzyme system is also involved, particularly CYP3A4 and, to a lesser extent, CYP2D6.
Excretion Less than 3% of administered haloperidol is eliminated unchanged in the urine. The apparent half-life of haloperidol following intramuscular injection of haloperidol decanoate injection is about 3 weeks. Specific Populations Patients with Hepatic Impairment Studies in patients with hepatic impairment have not been conducted.
Haloperidol is extensively metabolized in the liver, therefore, haloperidol concentrations may be higher in patients with hepatic impairment compared to patients with normal hepatic function [see Use in Specific Populations (8.6) ] . Geriatric Patients Haloperidol plasma concentrations in geriatric patients were higher than in younger adult patients when administered the same dosage. Results from small clinical studies suggest a lower clearance and a longer elimination half-life of haloperidol in geriatric patients.
The results are within the observed variability in haloperidol pharmacokinetics [see Use in Specific Populations (8.5) ] . Patients with Renal Impairment Studies in patients with renal impairment have not been conducted. Drug Interaction Studies Ketoconazole and Paroxetine The haloperidol plasma concentrations increased when ketoconazole (400 mg/day, strong CYP3A4 inhibitor) and paroxetine (20 mg/day, strong CYP2D6 inhibitor) were concomitantly administered with haloperidol [see Drug Interactions (7.2) ] .
Valproate Sodium valproate, a drug known to inhibit glucuronidation, does not affect haloperidol plasma concentrations. Rifampin In a study with 12 patients with schizophrenia, concomitant administration of oral haloperidol and rifampin, a strong CYP3A4 inducer, resulted in decreased plasma haloperidol concentrations by a mean of 70% and increased mean scores on the Brief Psychiatric Rating Scale from baseline. In five other patients with schizophrenia treated with oral haloperidol and rifampin, discontinuation of rifampin resulted in a mean 3.3-fold increase in haloperidol concentrations [see Drug Interactions (7.2) ] .
Carbamazepine In a study with 11 patients with schizophrenia, concomitant administration of haloperidol and increasing doses of carbamazepine, a CYP3A4 strong inducer, resulted in decreased haloperidol plasma concentrations in a linear manner with increasing carbamazepine concentrations [see Drug Interactions (7.2) ] . Effect of Haloperidol on Other Drugs Haloperidol is an inhibito…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of action of haloperidol decanoate injection for the treatment of schizophrenia in adults is unclear. However, its effect in schizophrenia could be mediated through its activity as an antagonist at central dopamine type 2 receptors. Haloperidol also binds to alpha-1 adrenergic receptors, but with lower affinity, and displays minimal binding to muscarinic cholinergic and histaminergic (H1) receptors.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied Haloperidol Decanoate Injection, is a clear, slightly viscous, colorless to pink or amber solution, free from visible foreign material and available as: 50 mg/mL containing 50 mg haloperidol as 70.52 mg per mL haloperidol decanoate, USP: NDC 67457-410-13 1 mL single-dose vials packaged in cartons of ten 100 mg/mL containing 100 mg haloperidol as 141.04 mg per mL haloperidol decanoate, USP: NDC 67457-409-13 1 mL single-dose vials packaged in cartons of five Storage and Handling Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Do not refrigerate or freeze.
Protect from light. Retain vial in carton until contents are used. Discard unused portion.
📋 Description ▾
11 DESCRIPTION Haloperidol decanoate injection is the decanoate ester of haloperidol, for intramuscular use. Haloperidol is a typical antipsychotic. The structural formula of haloperidol decanoate is 4-(4-Chlorophenyl)-1-[4-(4-fluorophenyl)-4-oxobutyl]piperidin-4-yl decanoate: Haloperidol decanoate, USP is a white or almost white powder.
The molecular formula is C 31 H 41 CIFNO 3 and has a molecular weight of 530.11. Haloperidol decanoate is very soluble in alcohol, in methanol and in methylene chloride, practically insoluble in water. Each mL of haloperidol decanoate injection contains: • 50 mg of haloperidol (present as 70.52 mg of haloperidol decanoate, USP) in a sesame oil vehicle, with 1.2% (w/v) benzyl alcohol as a preservative. • 100 mg of haloperidol (present as 141.04 mg of haloperidol decanoate, USP) in a sesame oil vehicle, with 1.2% (w/v) benzyl alcohol as a preservative.
Haloperidol Decanoate Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Sudden Death, Torsades de Pointes, and QTc Interval Prolongation Inform patients that there have been reports of sudden death, Torsades de Pointes, and QTc interval prolongation in haloperidol-treated patients. Advise patients or caregivers to seek immediate medical attention if they suspect or develop signs or symptoms associated with the clinical consequences of QTc interval prolongation [see Warnings and Precautions (5.2) ] . Tardive Dyskinesia Inform patients that tardive dyskinesia (TD) may develop with haloperidol decanoate injection.
Counsel patients on the signs and symptoms of tardive dyskinesia and to contact their healthcare provider if these abnormal movements occur [see Warnings and Precautions (5.5) ] . Neuroleptic Malignant Syndrome Counsel patients about a potentially fatal adverse reaction, Neuroleptic Malignant Syndrome (NMS), that has been reported with administration of antipsychotic drugs. Advise patients, family members, or caregivers to contact the health care provider or to report to the emergency room if they experience signs and symptoms of NMS [see Warnings and Precautions (5.6) ] .
Hypersensitivity Reactions Inform patients of the potential risk of hypersensitivity reactions. Advise patients to stop taking haloperidol decanoate injection and seek immediate attention if signs or symptoms of a hypersensitivity reaction occur [see Warnings and Precautions (5.9) ] . Falls Inform patients that haloperidol decanoate injection can cause somnolence, orthostatic hypotension, motor instability and sensory abnormality that may lead to falls.
Advise patients to notify their healthcare provider if any of these symptoms occur [see Warnings and Precautions (5.10) ] . Potential for Cognitive and Motor Impairment Inform patients of the risk and advise them to not drive a motor vehicle or operate hazardous machinery until they are reasonably certain that treatment with haloperidol decanoate injection does not impair their cognitive and motor functions [see Warnings and Precautions (5.11) ] . Leukopenia/Neutropenia Advise patients with a pre-existing low WBC or a history of drug induced leukopenia or neutropenia that they should have their CBC monitored while taking haloperidol decanoate injection [see Warnings and Precautions (5.13) ] .
Hyperprolactinemia Counsel patients on signs and symptoms of hyperprolactinemia that may be associated with chronic use of haloperidol decanoate injection. Advise the patients to seek medical attention if they experience any of the following: amenorrhea, galactorrhea, erectile dysfunction or gynecomastia [see Warnings and Precautions (5.14) ] . Pregnancy Advise pregnant patients to notify their health care provider if they become pregnant or intend to become pregnant during treatment with haloperidol decanoate injection.
Advise patients that haloperidol decanoate injection exposure during the third trimester of pregnancy may cause adverse effects in the neonate, including agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress, and decreased feeding [see Use in Specific Populations (8.1) ] . Lactation Advise breastfeeding patients using haloperidol decanoate injection to monitor infants for excess sedation, irritability, poor feeding, and extrapyramidal symptoms (tremors and abnormal muscle movements) and to seek medical care if they notice these signs [see Use in Specific Populations (8.2) ] .
Infertility Advise females and males of reproductive potential that haloperidol decanoate injection may impair fertility due to an increase in serum prolactin levels [see Use in Specific Populations (8.3) ] . Drug Interactions Advise patients to inform their health care provider before starting or discontinuing a prescription drug, nonprescription drug, or supplement [see Warnings and Precautions (5.2) and Drug Interactions (7) ] . Distributed by: Mylan Institutional LLC, a Viatris Company Morgantown, WV 26505 U.S.A.
Manufactured by: Mylan La…